

How Shoulder Impingement Is Diagnosed: The Exam Tests and When an Ultrasound or MRI Is Ordered

Key Takeaways
- Shoulder impingement is diagnosed primarily by history and physical examination; imaging is not required to confirm it.
- Neer and Hawkins-Kennedy tests are sensitive but not specific, so clinicians read them as a cluster alongside the painful arc, strength testing and a neck screen.
- A painful arc between roughly 60 and 120 degrees of arm elevation, with pain easing above and below, is one of the more characteristic exam findings.
- Plain X-rays cannot show tendons but do reveal bone spurs, calcium deposits and arthritis, which is why they are often the first image ordered.
- Ultrasound shows the tendon and bursa moving in real time, while MRI maps the whole joint including the labrum, so the choice depends on the question being asked.
- Persistent weakness after an injury, or no improvement after several weeks to months of structured rehabilitation, are the two most common triggers for ordering a scan.
Shoulder impingement is diagnosed mainly by a clinician's history and hands-on examination: where the pain sits, which movements provoke it, and how the shoulder behaves during provocation tests such as Neer, Hawkins-Kennedy and the painful arc. Imaging is not needed to make the diagnosis. An X-ray, ultrasound or MRI is usually ordered only when symptoms fail to improve with rehabilitation, weakness or trauma suggests a tear, or another cause needs excluding.
The bathroom shelf is only shoulder high, but reaching for the shampoo has started to feel like a small negotiation. The arm goes up, catches somewhere around the ear, and a sharp pinch fires through the top of the shoulder. Lower the arm and the pain fades. Sleep on that side and it comes back at two in the morning. A friend says it sounds like impingement and asks whether you have had a scan yet.
That question, in one form or another, brings a great many people to a clinic. They want a picture of what is wrong. What tends to surprise them is that a shoulder impingement diagnosis usually rests on a careful conversation and a set of movements performed in the exam room, not on a machine.
This explainer walks through what the clinician is actually doing with your arm, what the tests can and cannot prove, and the specific circumstances in which an ultrasound or MRI earns its place.
What shoulder impingement actually means, in plain language
Picture the top of the shoulder as a low bridge. The bridge is the acromion, the bony shelf at the outer end of the shoulder blade. Passing underneath it is a set of tendons called the rotator cuff, four muscles that hold the ball of the upper arm centered in its shallow socket and help lift and rotate the arm. Between the tendons and the bridge sits the subacromial bursa, a thin fluid-filled cushion that lets the tendons glide.
The space under that bridge is small, around a centimeter in many adults, and it narrows further as the arm rises. Impingement describes what happens when the cuff tendons or the bursa are pinched or rubbed in that gap during overhead movement. The pinched tissue becomes irritated, the bursa may thicken, and a tendon can develop the fraying or degeneration known as tendinopathy. According to the NHS, this irritation is one of the most common reasons for shoulder pain, especially in people who lift, reach or throw repeatedly.
Why the space narrows varies from person to person. In some, a bone spur or a downward-sloping acromion takes up room. In others, the shoulder blade sits or moves poorly because of muscle weakness or posture, so the bridge dips toward the tendons with every lift. Tendons that have swollen from overuse can also crowd themselves out. That variety is exactly why the diagnosis leans on examination: the clinician is trying to work out not just whether the tendons are pinched, but why.
You may also hear the newer term subacromial pain syndrome. Many specialists prefer it because it describes the pain and its location without assuming a single mechanical cause. For a patient, the practical meaning is the same.
Why shoulder impingement diagnosis starts with your story, not a scan
Before a hand touches your shoulder, the clinician wants roughly ten minutes of history. That conversation carries more diagnostic weight than most people expect, because impingement has a fairly recognizable pattern and its main look-alikes have different ones.

Expect questions about onset. Did the pain creep in over weeks after a new job, a garden project or a return to swimming, or did it arrive in a single moment when you fell or lifted something heavy? Gradual onset points toward irritation; a sudden event raises the possibility of a torn tendon or a joint injury and changes how quickly imaging enters the picture.
Location matters. Impingement pain typically sits at the front and outer side of the shoulder and can radiate partway down the upper arm, but it rarely travels past the elbow. Pain that runs into the forearm or fingers, or that comes with tingling or numbness, makes the clinician think about the neck, where a pinched nerve can masquerade as a shoulder problem.
Timing is the third clue. The classic complaint, described on both the Mayo Clinic and Cleveland Clinic patient pages, is pain when reaching overhead or behind the back, when lying on the affected side, and at night. Stiffness that stops the arm moving in every direction, even when someone else moves it for you, sounds more like frozen shoulder.
Finally, the clinician asks about the whole person: age, work, sport, diabetes, previous shoulder surgery, and general health. Unexplained weight loss, fevers or a history of cancer are not features of impingement and prompt a different, faster pathway. None of this is small talk. Each answer either strengthens the working diagnosis or opens a door to something else.
What happens during the physical exam
The examination usually follows the same rough order: look, feel, move, then test. Knowing the sequence makes it less mysterious.
Looking comes first, ideally with both shoulders visible. The clinician watches how you hold yourself and compares the two sides. Wasting of the muscles above or behind the shoulder blade can hint at a long-standing tendon problem or a nerve issue. They will watch the shoulder blade as you raise and lower your arms; a blade that wings out or hitches upward suggests the muscles controlling it are not doing their share, which is one common driver of impingement.
Feeling follows. Gentle pressure along the collarbone, the joint at its outer end, the bony point of the acromion, the front of the shoulder where the biceps tendon runs, and the tender spot just below the acromion helps map where the pain lives. Tenderness confined to the small joint at the tip of the shoulder points toward that joint rather than the tendons beneath.
Moving is next, in two forms. Active range is how far you can lift, rotate and reach behind on your own. Passive range is how far the clinician can move the relaxed arm. Impingement usually leaves passive range near normal while active lifting hurts through an arc in the middle of the movement. A shoulder that is equally restricted both ways behaves more like frozen shoulder or arthritis.
Strength testing rounds out this stage. The clinician resists your arm in specific positions to load each rotator cuff tendon in turn. Pain with preserved strength suggests irritation. Genuine weakness, especially if it is painless or came on after an injury, raises the possibility of a tear and is one of the main reasons imaging gets ordered sooner rather than later.
Which shoulder impingement test does the doctor use? Neer, Hawkins-Kennedy and the painful arc
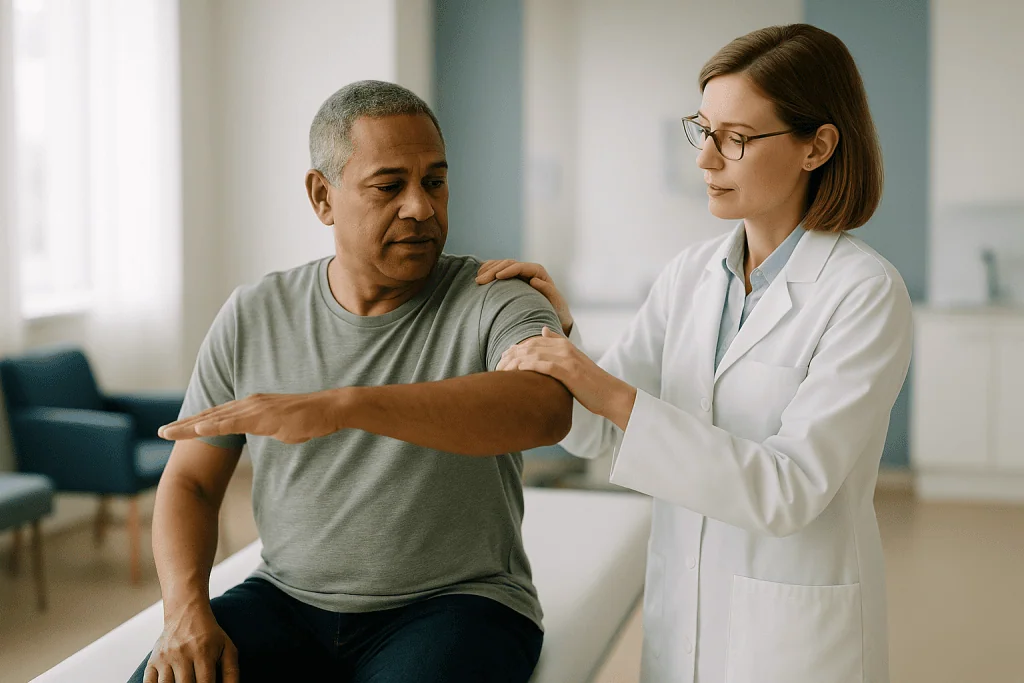
The provocation tests are the part of the visit most people remember, because they deliberately reproduce the pinch. Each one positions the arm so that the cuff tendons and bursa are pressed toward the acromion. Pain in the right place counts as a positive result.
| Test | What the clinician does | What a positive result suggests |
|---|---|---|
| Neer | Stabilizes the shoulder blade and lifts your straight, inward-turned arm forward and up | Pain at the top or front of the shoulder as the tendons meet the acromion |
| Hawkins-Kennedy | Bends your elbow to 90 degrees, brings the arm forward and rotates it inward | Pain as the cuff is driven under the ligament and acromion |
| Painful arc | Asks you to lift the arm out to the side and lower it slowly | Pain mainly between roughly 60 and 120 degrees that eases above and below |
| Empty can (Jobe) | Arm out to the side, thumb down, resisted upward push | Pain or weakness in the supraspinatus, the top cuff tendon |
| External rotation strength | Elbows at your sides, you push outward against resistance | Weakness in the back cuff tendons, raising concern for a tear |
| Drop arm | Arm lifted to the side, you lower it slowly | Inability to control the descent suggests a larger tear |
The clinician may also perform tests aimed at neighbors of the cuff: pressing the arm across the body to load the joint at the collarbone’s tip, or resisting a forward lift with the palm up to stress the biceps tendon. A quick neck screen, turning and tilting the head while noting any arm symptoms, checks for referred pain.
A systematic review of shoulder examination tests published in the British Journal of Sports Medicine and indexed on PubMed found that no single impingement test is accurate enough to confirm or exclude the problem on its own. Clusters of positive tests, taken together with the history, perform considerably better.
What the special tests can and cannot prove
Here is the honest part that rarely appears in a quick online explainer. The named tests are good at reproducing pain. They are far less good at telling you exactly which structure is responsible.
Consider what a positive Neer test involves: the arm is forced upward so that everything under the acromion, the bursa, the top cuff tendon, the biceps tendon and even the joint capsule, is compressed together. Pain confirms that something in that space objects to being squeezed. It cannot say whether the culprit is a swollen bursa, a frayed tendon or a small partial tear. The PubMed-indexed systematic review of examination tests reported that Neer and Hawkins-Kennedy are sensitive, meaning they pick up most people with subacromial pain, but not very specific, meaning they are also positive in other conditions.
This is why an experienced examiner reads the pattern rather than any single result. Pain on Neer and Hawkins-Kennedy, a painful arc in the middle of abduction, tenderness beneath the acromion, preserved strength, and a normal neck screen together build a coherent picture. A clean neck screen and a normal biceps test quietly remove alternatives from the list. Strength tests earn particular attention, because weakness is the finding most likely to change management.
Some clinicians add an injection of local anesthetic into the subacromial space as a diagnostic step. If pain and the positive tests disappear for the hour or two the anesthetic works, the space under the acromion is very likely the source. Whether that injection is offered, and whether a corticosteroid is added for longer relief, is a judgment for the treating clinician based on your circumstances.
The message for patients is reassuring in its own way. A skilled exam is not a guess. It is a structured process of weighing probabilities, and for most people it is enough to start treatment without waiting for a scan.
Can you test yourself for shoulder impingement at home?
Many people try. A search for the Neer or Hawkins test turns up videos, and it is tempting to raise the arm, feel the pinch and declare the matter settled. The honest answer is that you can notice a pattern at home, but you cannot make a diagnosis there.
The reason is not that the movements are secret. It is that the value of each test lies in the comparison with everything else the clinician checks in the same session. A pinch at the top of the shoulder when you lift your arm is consistent with impingement. It is also consistent with irritation of the joint at the end of the collarbone, with early frozen shoulder, with a calcium deposit in the tendon, and with a partial tear. Distinguishing among these requires someone to feel exactly where you are tender, to move the relaxed arm passively, to test the strength of each tendon separately, and to screen the neck. None of that can be done on yourself with any reliability.
Self-testing also carries two quieter risks. One is false reassurance: a person who cannot reproduce the pinch may assume nothing is wrong and keep loading a tendon that is quietly fraying. The other is anxiety in the opposite direction, treating an ordinary post-workout ache as a structural problem and stopping activity that would actually have helped.
What you can usefully do at home is observe and record. Note which movements hurt, whether pain wakes you, whether the arm feels weak or merely sore, and whether anything travels below the elbow. Note what you were doing in the weeks before it began. That log is genuinely helpful to the clinician and makes the appointment more productive than any home version of a provocation test.
Ruling out the look-alikes: neck, frozen shoulder, tears and the collarbone joint
A good shoulder exam spends as much effort excluding other conditions as confirming impingement. Four impostors come up again and again.
The neck is the first. Nerve roots leaving the cervical spine can be irritated by a bulging disc or arthritic narrowing, and the pain frequently lands in the shoulder and upper arm. Clues that point toward the neck include pain or tingling that travels past the elbow into the hand, symptoms that change when you turn or tilt your head, and a shoulder that moves normally when examined directly. MedlinePlus lists neck problems among the conditions that commonly mimic rotator cuff pain.
Frozen shoulder, medically called adhesive capsulitis, is the second. The joint capsule thickens and tightens so that movement is lost in every direction, and crucially it is lost even when the clinician moves the arm for you. Impingement rarely restricts passive movement in this global way. Frozen shoulder is also more common in people with diabetes and often follows a period of immobility.
A rotator cuff tear is the third and the most important to separate, because a full-thickness tear in a younger or active person may be managed differently. Impingement and tears sit on a spectrum, and long-standing irritation can progress to a tear, but weakness that persists after pain is controlled, a positive drop arm test, or a sudden loss of function after a fall are the findings that push a clinician toward imaging.
The acromioclavicular joint, where the collarbone meets the shoulder blade, is the fourth. Pain here is felt right on top of the shoulder, is reproduced by pressing the arm across the chest, and is tender to a fingertip on the joint itself. It responds to different treatment, so it is worth getting right.
When is an X-ray ordered first?
If any imaging happens at the first visit, it is usually a plain X-ray, and that surprises people who expected something more sophisticated. X-rays cannot show tendons or the bursa. What they show well is bone, and bone answers several questions that matter.
The Mayo Clinic notes that X-rays in shoulder pain are used mainly to look for bone spurs, arthritis and calcium deposits. A spur on the underside of the acromion, or an acromion that slopes downward, narrows the space the tendons pass through and helps explain why irritation has developed. Calcium deposits within a tendon, a condition called calcific tendinopathy, can cause intense pain that mimics impingement but follows a different course. Arthritis of the main shoulder joint or the collarbone joint shows up as narrowing and roughening of the bony surfaces.
X-rays are also the right first step after a fall or direct blow, when a fracture of the upper arm or collarbone must be excluded before anyone presses on the shoulder too enthusiastically. In older adults, an upward migration of the ball of the joint on a standing X-ray can hint at a large, long-standing cuff tear, because the tendons are no longer holding the ball down in its socket.
Not everyone needs an X-ray. A younger person with a short history of overhead pain, no injury and normal strength is often treated on the basis of the exam alone, with imaging reserved for the situation where things do not improve. Whether an X-ray is taken at the outset therefore depends on age, mechanism and what the exam has shown, and it is a decision the clinician makes with you rather than a fixed rule.
Ultrasound vs MRI for shoulder impingement: which one, and when
When soft tissue needs to be seen, two tools compete. Both can show the cuff tendons, the bursa and fluid in the joint. They differ in how they work, what else they reveal and how they fit into a patient’s pathway.
Ultrasound uses sound waves and a handheld probe. Its great advantage is that it is dynamic: the sonographer can watch the tendon slide under the acromion while you raise your arm and can see the bursa bunch up in real time, which is a direct observation of the impingement itself. It reliably shows bursal thickening, tendon swelling and full-thickness tears, and it lets the examiner press on the exact spot that hurts to confirm the finding matches the symptom. Its limits are that it depends heavily on the operator’s skill and cannot see deep structures such as the cartilage rim of the socket, called the labrum, or the inside of the joint.
MRI uses a magnetic field to build detailed cross-sectional pictures. It shows the whole shoulder at once: every cuff tendon, the labrum, the joint capsule, bone marrow and the biceps tendon. It is the preferred test when a clinician suspects several problems, when surgery is being considered and the surgeon needs a full map, or when ultrasound has been inconclusive. Its drawbacks are time in the scanner, difficulty for people with claustrophobia or certain implants, and a tendency to reveal age-related changes that are not causing the pain.
Both the Mayo Clinic and NHS patient guidance describe ultrasound and MRI as the tests used when a tear or another structural cause is suspected, rather than as routine steps. For a straightforward impingement picture, many pathways favor ultrasound first because it answers the main question, is the tendon torn, while showing the bursa in motion. MRI follows when the answer is unclear or the plan is changing.
Who is usually imaged early, and who is usually asked to wait
Deciding when to image is where clinical judgment shows most clearly, and it helps to understand the reasoning rather than simply receiving a verdict.
Early imaging, meaning at or soon after the first visit, is generally reserved for people whose history or exam raises a specific concern. A fall or forceful pull followed by sudden weakness suggests an acute tear, and tears in that setting are often assessed promptly because the treatment discussion may differ. Marked weakness on strength testing, a positive drop arm sign, or a visible loss of muscle bulk points the same way. Pain that is severe and unrelenting, especially at rest, with fever, unexplained weight loss or a history of cancer, is not an impingement pattern and warrants urgent evaluation. Suspected shoulder instability in a young athlete, or a locking or catching sensation that suggests a labral problem, may also lead a clinician toward MRI sooner.
Most people fall into a different group. They have gradual-onset overhead pain, night discomfort, positive impingement tests and preserved strength. For them, guidance from the NHS and Mayo Clinic supports starting treatment with activity modification and a structured exercise program before any scan, because the scan is unlikely to change that initial plan. The NHS notes that impingement commonly settles over a few weeks to a few months with the right exercises.
Waiting is not the same as being dismissed. It is a recognition that scans of shoulders in adults over about fifty frequently show bursal thickening, tendon degeneration and even small tears in people who have no pain at all. Imaging too early risks attaching a label to a finding that is simply part of the shoulder’s history. The right time to look is when the picture would change what happens next.
How long does shoulder impingement take to heal, and what the following weeks usually look like
Once a working diagnosis is in place, the weeks that follow tend to have a recognizable shape, though the pace varies widely between individuals.
The first fortnight usually centers on calming the tendon. That means temporarily avoiding the overhead reaching, throwing or heavy lifting that provokes the pinch, adjusting sleeping position, and sometimes using cold packs or an anti-inflammatory medicine of the class known as NSAIDs to take the edge off pain. Any decision about medicine, including whether it suits your stomach, kidneys or heart, belongs to the prescribing clinician.
From around the second or third week, the emphasis shifts to movement. A physical therapist typically prescribes exercises that restore control of the shoulder blade, strengthen the rotator cuff in positions that do not pinch, and gradually reintroduce lifting. Progress is measured by function: sleeping through the night, reaching a high shelf, returning to a sport. The NHS advises that shoulder impingement often improves over a few weeks or months with these exercises, and that pain which has not eased after a couple of weeks of self-care is a reason to see a clinician.
By six to twelve weeks, most people with straightforward impingement have noticeably less pain and better movement, although full return to overhead sport may take longer. If there has been little change by this stage despite a genuine effort at rehabilitation, this is the point at which clinicians commonly revisit the diagnosis, order imaging if it has not been done, and discuss options such as a guided corticosteroid injection. Surgery to create more room under the acromion is considered far less often than it once was and is generally reserved for people who have not improved after prolonged conservative care.
My shoulder impingement is not getting better: what usually happens next
Plateaus are common and disheartening. Several months of dutiful exercises, and the shelf still feels out of reach. It helps to know that a stalled recovery is itself a diagnostic clue, and that clinicians follow a fairly predictable line of thought when it happens.
The first question is whether the diagnosis was right. Persistent pain despite appropriate rehabilitation is the single most common reason a shoulder that was initially treated on examination alone is sent for ultrasound or MRI. The scan is looking for a tear that has been masquerading as simple irritation, a calcium deposit, a problem with the biceps tendon or labrum, or early frozen shoulder that has crept in behind the original complaint.
The second question is whether the treatment has been the right kind and the right amount. Impingement exercises need to target the muscles that position the shoulder blade, not just the cuff, and they need enough load and consistency to change tissue. A therapist may adjust the program, check technique, or address contributing factors such as a stiff thoracic spine or a desk setup that keeps the shoulders rounded for eight hours a day.
The third question is whether a different intervention is warranted. A corticosteroid injected into the subacromial space can reduce inflammation in the bursa and, in combination with continued exercise, may open a window in which rehabilitation becomes possible. Whether it is offered, and how many times, depends on the clinician’s assessment of benefit and risk for you.
Only after these steps, and typically after many months, does a surgical opinion usually enter the conversation. Even then, the discussion is about weighing options, not about a guaranteed fix, and the choice stays with you and your treating team.
What people often get wrong about shoulder impingement diagnosis
Some misunderstandings come up so reliably that they deserve direct correction.
The first is that a scan is the gold standard and the exam is a formality. The reverse is closer to the truth. Imaging finds structure; it does not find pain. Studies of people with no shoulder symptoms routinely show bursal thickening and tendon degeneration, especially past middle age, which is why the Mayo Clinic frames scans as tools for suspected tears and other specific problems rather than as a routine step.
The second is that impingement is always caused by a bone spur pressing down on the tendon. Spurs contribute in some people, but many cases are driven by weakness and poor control of the shoulder blade or by a tendon that has swollen from overuse. This matters because the treatment for a movement problem is retraining, not removal of bone.
The third is that rest alone will settle it. Rest calms the tendon in the short term, but the NHS is explicit that improvement depends on the right exercises. A shoulder that is kept still for weeks risks stiffening, and stiffness invites frozen shoulder.
The fourth is that a positive Neer or Hawkins test proves impingement. As the PubMed-indexed systematic review found, these tests are sensitive but not specific, and they are read as part of a cluster.
The fifth is that a tear on a scan means surgery. Many partial tears and some full-thickness tears are managed without an operation, particularly in older adults, and the decision depends on function, symptoms and goals rather than on the image alone.
The last is that a pain-free day means the problem is fixed. Tendons recover slowly and quietly. Returning to heavy overhead loading at the first good week is one of the commonest reasons symptoms flare again.
Questions to ask your care team
A ten-minute appointment goes further when you arrive with questions that fit the way clinicians think. These are the ones worth writing down.
- Based on your examination, how confident are you that this is impingement rather than a tear, the neck or the joint at the end of my collarbone?
- Which of my test results pointed you toward this diagnosis, and did any of them point away from it?
- Was my strength normal? If not, which tendon seemed weak, and what does that change?
- Do I need an X-ray, ultrasound or MRI now, and if not, what would make you order one later?
- If an ultrasound is chosen over an MRI, what can it show and what would it miss?
- What should I stop doing for now, and for roughly how long?
- Which exercises matter most, how often should I do them, and how will we know they are working?
- At what point, if I have not improved, would you want to see me again or change the plan?
- If an injection is suggested, what is it meant to achieve, and what are the risks for someone with my health history?
- Are there features of my situation that make surgery more or less likely to come up later?
Bring your own log as well: which movements hurt, how sleep has been affected, and what you were doing in the weeks before it started. If you take regular medicines or have conditions such as diabetes, heart disease or kidney problems, say so early, because they affect which treatments are appropriate. Every answer you receive should leave the decision in your hands and those of the team treating you, with a clear sense of what happens next and when.
When to call your doctor
Most shoulder impingement is a nuisance rather than an emergency, and it is reasonable to try a couple of weeks of activity modification before booking an appointment. The NHS advises seeing a clinician if shoulder pain has not eased after around two weeks of self-care, or sooner if it is stopping you from working or sleeping.
Some features should not wait. Contact your doctor promptly, or seek urgent care, if you notice any of the following:
- Sudden inability to lift the arm, or obvious weakness, especially after a fall, a heavy lift or a forceful pull
- A visible deformity, a lump, or a shoulder that looks out of place
- Severe pain at rest that does not settle with position change, particularly with fever, chills or feeling generally unwell
- Redness, heat and swelling over the joint, which can signal infection
- Numbness, tingling or weakness spreading into the forearm and hand, or symptoms in both arms
- Unexplained weight loss, night sweats or a personal history of cancer alongside new shoulder pain
- Shoulder or arm pain that comes on with exertion, breathlessness, chest tightness or sweating, which needs emergency assessment because it can indicate a heart problem
Call as well if a diagnosed impingement is clearly worsening despite following the plan, if pain begins to restrict movement in every direction rather than just overhead, or if you develop new symptoms after an injection such as increasing pain, fever or redness at the site.
None of these signs confirms a serious problem. They simply mark the point at which the pattern no longer fits ordinary impingement, and a clinician should look again and decide, with you, whether imaging or a different pathway is needed.
Frequently asked questions
How long does shoulder impingement take to heal?
Most people improve over a few weeks to a few months with activity modification and a structured exercise program, according to NHS guidance. Pain often eases within the first several weeks, while full strength and confident overhead movement can take longer, and return to throwing or overhead sport is usually the last milestone. Recovery that has stalled after roughly three months is a reason to revisit the diagnosis with your clinician.
My shoulder impingement isn't getting better. What should I do?
Go back to your clinician rather than pushing through. A plateau after a genuine attempt at rehabilitation is the most common reason ultrasound or MRI is ordered, because it may reveal a tear, a calcium deposit or early frozen shoulder that changes the plan. The therapist may also adjust exercise technique and load, and a guided injection may be discussed. Decisions about next steps rest with your treating team.
How can I test myself for shoulder impingement?
You cannot reliably diagnose impingement on yourself. Reproducing a pinch when lifting the arm is consistent with impingement but also with collarbone joint irritation, a partial tear, calcific tendinopathy or early frozen shoulder. Telling them apart requires someone to feel exactly where you are tender, move the relaxed arm passively, test each tendon’s strength and screen the neck. Keep a log of what hurts and bring it to your appointment.
What is the most accurate shoulder impingement test?
No single test is accurate enough on its own. A systematic review of shoulder examination tests found that Neer and Hawkins-Kennedy pick up most people with subacromial pain but are also positive in other conditions. Accuracy improves when several findings agree: positive provocation tests, a painful arc in mid-range, tenderness under the acromion, preserved strength and a normal neck screen together make impingement much more likely.
Is ultrasound or MRI better for shoulder impingement?
Neither is better for every situation. Ultrasound shows the tendon and bursa moving under the acromion in real time and reliably detects full-thickness tears, but it depends on operator skill and cannot see the labrum or inside the joint. MRI maps the whole shoulder and is preferred when several problems are suspected or surgery is being considered. Many pathways use ultrasound first and MRI when questions remain.
Do I need an MRI to diagnose shoulder impingement?
Usually not. The diagnosis rests on your history and examination, and Mayo Clinic and NHS guidance describe MRI as a test for suspected tears or other structural problems rather than a routine step. Scans of pain-free adults often show bursal thickening and tendon wear, so imaging too early can attach a label to something harmless. MRI becomes useful when weakness, trauma or a stalled recovery changes the picture.
What are the best exercises for shoulder impingement syndrome?
The most useful programs focus on controlling the shoulder blade and strengthening the rotator cuff in positions that do not pinch, then gradually reintroducing overhead loading. Which specific exercises suit you depends on what the exam showed, such as blade weakness, cuff weakness or stiffness elsewhere, so a physical therapist should tailor and progress them. The NHS notes that the right exercises are central to recovery.
Can shoulder impingement be mistaken for a neck problem?
Yes, and the reverse is equally common. A pinched nerve in the cervical spine often refers pain to the shoulder and upper arm. Clues pointing to the neck include tingling or pain traveling past the elbow into the hand, symptoms that change when you turn or tilt your head, and a shoulder that moves normally on direct examination. A brief neck screen is part of every thorough shoulder exam.
Why did the doctor order an X-ray if it cannot show tendons?
Because bone explains a lot. An X-ray shows a spur or downward-sloping acromion that narrows the tendon space, calcium deposits within a tendon, arthritis at the main joint or the collarbone joint, and fractures after a fall. In older adults it can also reveal the ball of the joint sitting high in its socket, a sign of a large long-standing cuff tear. It is a quick way to rule several things in or out.
Does a tear on my scan mean I need surgery?
Not necessarily. Many partial tears and some full-thickness tears are managed without an operation, particularly in older adults or when the tear is small and function is good. Surgeons weigh symptoms, strength, age, activity goals and how the shoulder has responded to rehabilitation rather than the image alone. A scan finding starts a conversation with your treating team; it does not settle it.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Who Is a Candidate for Cartilage Restoration? Defect Size, Alignment and Age Considerations
A cartilage restoration candidate is usually someone with a single, well-defined area of damaged joint cartilage, healthy surrounding cartilage, a stable and reasonably well-aligned…
What X-Rays and MRI Show After a Shoulder Dislocation: Fractures, Labrum and Ligament Damage
An x-ray after shoulder dislocation confirms the joint is out, shows which direction it went, and checks for associated fractures of the humeral head,…

Life After Cruciate Ligament Surgery: Stairs, Driving, Desk Work and Sport in Order
Life after cruciate surgery follows a fairly predictable order. Walking with crutches comes first, usually within days; stairs and desk work return over the…

ACL Surgery Cost: What Reconstruction Really Costs, Market by Market
ACL reconstruction typically costs USD 20,000–50,000 in the United States, GBP 7,000–14,000 for private surgery in the UK, and EUR 3,900–7,150 within our guide…

Tendon Surgery Recovery: Why the Splint Stays On and How Gliding Exercises Begin
Tendon surgery recovery time is usually measured in months rather than weeks. A splint typically protects a repaired hand tendon for roughly four to…

Preparing for Arthroscopy: Medication Review, Fasting and Arranging a Ride Home
Preparing for arthroscopy usually rests on three tasks: giving your surgical team a complete list of every prescription medicine, over-the-counter product and supplement you…