

Ozempic Injection Site Reactions and Rashes: What Is Normal and What Signals an Allergy

Key Takeaways
- In Ozempic's pivotal trials, injection site reactions such as redness or discomfort occurred in about 0.2 percent of participants, a rate similar to placebo pens.
- A normal reaction stays under roughly 5 centimeters, does not spread, and fades within one to three days; hives elsewhere on the body or swelling of the lips or tongue are not site reactions and need urgent care.
- Controlled pharmacokinetic studies found comparable semaglutide exposure from abdomen, thigh and upper arm, so site choice is about comfort and rotation, not effectiveness.
- Lipohypertrophy, the rubbery fat thickening seen with repeated insulin injections in one spot, is the main reason to move each injection at least a finger's width from the last.
- About 1 percent of trial participants developed antibodies to semaglutide, but these were not clearly linked to allergic reactions or loss of effect.
- The FDA declared the semaglutide shortage resolved in February 2025, meaning compounded versions, which are not FDA-approved or tested for sterility and potency, are no longer permitted for routine mass production.
Most Ozempic injection site reactions are mild: a small red, itchy or tender spot where the needle went in that fades within a few days, reported in well under 1 percent of people in clinical trials. A rash that spreads, hives far from the injection site, swelling of the lips, tongue or face, or any trouble breathing can signal a true allergy and needs urgent medical care.
Scroll through any weight-loss forum this month and you will find the same photo posted a dozen different ways: a thumb-sized pink circle on a stomach or thigh, a ruler held beside it, and a caption asking whether this is “the Ozempic rash.” As of June 2025 those posts are multiplying for a reason. In February 2025 the US Food and Drug Administration declared the long-running semaglutide shortage over, and in January 2025 the Ozempic label gained a new indication for protecting the kidneys in people with type 2 diabetes. More people are now holding a pen for the first time, and more are comparing their skin online.
Here is the honest frame for every Ozempic injection site question that follows. The medicine is injected into the fat just under the skin, a layer with nerves, small blood vessels and immune cells that notice a needle and a cold liquid. Some reaction is biology, not alarm. The task is to know which pink circle is ordinary and which one is a signal.
What changed recently with Ozempic, and why skin reactions are back in the news
Ozempic, the brand name for injectable semaglutide, was approved in the United States in December 2017 to help manage blood sugar in adults with type 2 diabetes. In January 2020 its label added a second job: lowering the risk of major cardiovascular events such as heart attack and stroke in adults with type 2 diabetes and known heart disease. In January 2025 a third indication arrived, reducing the risk of worsening kidney disease in adults with type 2 diabetes and chronic kidney disease, based on the FLOW trial published in 2024.
Two other dated shifts explain the current wave of skin questions. First, in February 2025 the FDA announced that the semaglutide shortage had resolved. During the shortage, compounded versions had been widely dispensed; compounded semaglutide is not an FDA-approved product, its ingredients and sterility are not reviewed the way an approved medicine is, and it is not something to seek out or self-use. Reports of unusual injection site reactions in people switching from compounded vials to the approved pen have circulated online, though they remain anecdotal.
Second, the prescribing information has for several years carried a warning about serious hypersensitivity reactions, including anaphylaxis (a sudden, body-wide allergic reaction) and angioedema (deep swelling of the lips, face, tongue or throat), identified from reports after the drug reached the market. Consumer references such as MedlinePlus and Mayo Clinic list these among the reasons to seek emergency help. None of that is new in 2025, but a larger, newer population of users is encountering the warning for the first time, and that is what has pushed “Ozempic rash” into the trending column.
What does a normal Ozempic injection site reaction look like?
Picture a mosquito bite that behaved itself. The typical reaction is a patch of erythema (medical shorthand for skin redness) roughly the size of a coin, centered on the puncture point. It may itch, feel slightly warm or firm, and show a pinprick dot or a tiny bruise in the middle. It appears within minutes to a few hours and is usually fading by the next day and gone within two to three days.
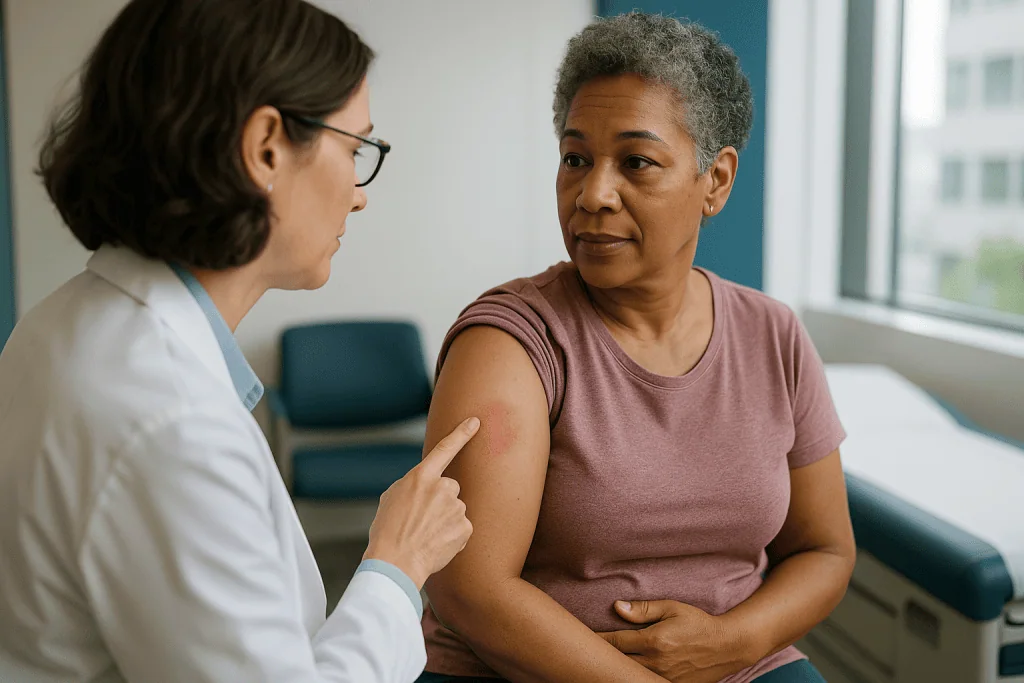
Several ordinary features reassure clinicians:
- It stays local, generally under about 5 centimeters (two inches) across, and does not creep outward over time.
- It is not accompanied by fever, chills, or feeling unwell.
- There is no pus, no streaking redness tracking toward the groin or armpit, and the skin is not hot and shiny.
- It tends to be worse when the medicine was injected straight from the refrigerator, or when the same spot was used recently.
A cool compress and leaving the area alone are what the patient leaflet and most clinic nurses suggest; scratching turns a quiet bump into a scabbed one. Over-the-counter remedies are a conversation for the pharmacist or prescriber, not a do-it-yourself experiment, because some topical products can mask changes a clinician would want to see.
Think of this reaction as the skin filing a routine report rather than raising an alarm. The sections that follow explain how common it is, why it happens at all, and how it differs from the rarer reactions that genuinely matter.
How common are Ozempic injection site reactions, by the numbers?
Less common than the comment sections suggest. In the clinical trial program that supported Ozempic’s approval, which enrolled several thousand adults with type 2 diabetes, injection site reactions such as discomfort or redness were reported in about 0.2 percent of people receiving the drug. That is roughly two in every thousand. The placebo pens, which contained the same liquid without semaglutide, produced reactions at a similar low rate, suggesting that the needle and the solution contribute as much as the active ingredient.
For comparison, older daily injectable medicines of the same family, known as GLP-1 receptor agonists (drugs that mimic a gut hormone called glucagon-like peptide-1 to lower blood sugar and appetite), have historically carried higher injection site reaction rates in their own trials, partly because they are injected every day rather than once a week. Insulin, injected several times daily, is better known still for skin changes.
Rates in real-world use are harder to pin down. Pharmacovigilance systems, which collect voluntary side-effect reports after approval, cannot calculate a true frequency because nobody knows how many uneventful injections went unreported. They can, however, flag patterns. Skin reactions at the site, hives, and rare cases of angioedema and anaphylaxis all appear in those systems, which is why they sit in the label.
One number worth holding onto: about 1 percent of trial participants developed antibodies against semaglutide. Antibodies are immune proteins that recognize a foreign molecule. Their presence was not clearly tied to a loss of effect or to allergic events in the trial data, but it is a reminder that the immune system does take notice of an injected peptide, even one engineered to resemble a human hormone.
Why does skin react to a semaglutide injection at all?
Three things arrive under your skin with every injection: a needle, a cold liquid, and a molecule. Each has its own way of provoking a response.

The needle is the simplest. Pushing a fine point through the dermis breaks capillaries and nerve endings. Small bruises and a brief sting are mechanical, not immunological. A blunt or reused needle, or one pushed in at an angle, bruises more.
The liquid is a sterile solution that includes semaglutide plus inactive ingredients called excipients, substances added to keep a medicine stable and free of microbes. The Ozempic pen contains phenol as a preservative, along with buffers that set the acidity and propylene glycol that helps keep the peptide dissolved. Phenol can produce mild, short-lived irritation in some skin, and a solution injected straight from the refrigerator stings more than one that has rested at room temperature as the leaflet allows.
The molecule is where the immune system enters. Semaglutide is a peptide (a short chain of amino acids) modified with a fatty acid tail so it binds to albumin in the blood and lasts about a week. Resident immune cells in the fat layer, including mast cells, can release histamine in response to any injected foreign material, producing the classic itchy pink wheal within minutes. A slower response, driven by T cells rather than histamine, can produce an eczema-like patch that appears 24 to 72 hours later and lasts longer.
Finally, repeated injection into the same patch of fat stimulates fat cells to enlarge, a change called lipohypertrophy. It is well documented with insulin and plausible with any injected hormone, which is why rotation matters, a point we return to below.
Ozempic rash: the five kinds of skin reaction and how to tell them apart
“Ozempic rash” is a search term, not a diagnosis. It covers at least five distinct patterns that differ in timing, spread and seriousness. The table summarizes what clinicians look for; the sections that follow fill in the detail.
| Pattern | When it appears | What it looks like | Usual course | Signal level |
|---|---|---|---|---|
| Local irritant reaction | Minutes to a few hours | Coin-sized redness, mild itch or tenderness at the site | Fades within 1–3 days | Expected; mention at next visit |
| Delayed local hypersensitivity | 24–72 hours | Itchy, dry or eczema-like patch at or around the site, may recur each week | Lasts days to a week or more | Call the prescriber |
| Urticaria (hives) | Minutes to hours | Raised, pale-centered itchy welts that move around the body, often far from the site | Individual welts last under 24 hours | Same-day medical contact |
| Angioedema | Minutes to hours | Deep swelling of lips, eyelids, tongue, throat or hands | Can progress quickly | Emergency |
| Anaphylaxis | Usually within minutes | Hives plus breathing difficulty, throat tightness, dizziness, vomiting or faintness | Rapid, life-threatening | Emergency |
Two further patterns deserve a line each. Cellulitis, a bacterial skin infection, produces spreading, hot, painful redness that may come with fever and does not fit the rhythm of injection timing; it needs prompt assessment. And bruising, lumps or firm nodules are mechanical or fat-tissue changes rather than rashes at all, covered in their own section.
The organizing principle is simple. Reactions that stay put and fade are the body’s local commentary. Reactions that travel, swell or interfere with breathing involve the whole immune system, and those are the ones the label’s hypersensitivity warning is about.
What signals a true allergy to semaglutide rather than irritation?
Allergy is an immune reaction aimed at a specific trigger; irritation is a nonspecific response to a physical or chemical insult. On the skin they can look alike for the first hour. Four questions help clinicians separate them.
Does it leave the injection site? Hives on the back, chest or scalp when the injection went into the thigh mean histamine is circulating, not just released locally. That pattern points toward a systemic allergic response and warrants same-day contact with the prescriber.
Is there swelling in soft tissue? Angioedema favors the lips, eyelids, tongue and throat because those tissues are loose and swell easily. A thick-feeling tongue, a voice that sounds different, or difficulty swallowing are emergency signs, even without breathing trouble yet.
Are other systems involved? Anaphylaxis, as the Mayo Clinic describes it, typically combines skin changes with at least one of: wheezing or shortness of breath, a drop in blood pressure causing dizziness or fainting, or sudden vomiting and cramping. It can unfold within minutes of an injection. It is rare with semaglutide, but it has been reported, which is why the label advises people with a known serious hypersensitivity to the drug or its ingredients not to use it and why anyone who experiences such a reaction should seek emergency care and inform the prescriber.
Does it recur in a pattern? A delayed, eczema-like patch appearing a day or two after every injection, growing larger with each week, suggests a sensitization process rather than a one-off irritant. That is not an emergency, but it is a conversation to have soon, because clinicians sometimes consider whether the active drug or an excipient such as phenol is the more likely trigger, and because other medicines in the same class use different excipients.
Never test the question yourself by injecting again to “see if it happens twice.” That decision belongs to the prescribing clinician, who can weigh the pattern and, if needed, involve an allergist.
Is Ozempic in the thigh better than the stomach for avoiding reactions?
The pen’s approved instructions list three areas: the abdomen (keeping clear of the area around the navel), the front of the thigh, and the back of the upper arm. Pharmacokinetic studies, which measure how much drug reaches the bloodstream and how fast, found semaglutide exposure to be broadly comparable across these sites. In practical terms the medicine works the same way whether you choose the stomach or the thigh.
Comfort and skin reactions are a different question, and here the evidence is mostly experiential rather than from trials. Patterns that nurses report and that are consistent with what is known about subcutaneous tissue (the fat layer just under the skin):
- The abdomen usually has the thickest, most even fat layer and the fewest nerve endings per square centimeter, so many people find it the least uncomfortable.
- The thigh has a thinner fat layer in lean people and more nerve supply; some report more stinging there, others prefer it because they can see what they are doing.
- The upper arm is hard to reach without help and is easier to inject into muscle by accident if the fat layer is thin.
No controlled study shows one site producing fewer rashes than another. What does seem to matter is variety. A spot used last week is still recovering, and reinjecting it stacks irritation on irritation. Rotating within a region, and between regions, spreads the load.
One honest caveat for people losing weight quickly: as the abdominal fat layer thins, a site that was comfortable in month one can feel different in month six. If an area starts to sting or bruise more than it used to, that is a reasonable thing to mention to the clinician or pharmacist, who can review technique rather than leaving you to guess.
Do you pinch the skin for an Ozempic injection, and does technique cause rashes?
The Ozempic pen is designed with a very short, fine needle intended to reach the fat layer without pinching in most adults, and the manufacturer’s instructions for use do not require a skin fold. That differs from older insulin syringes with longer needles, where pinching helped avoid muscle. Because this is a hands-on skill, the right teacher is the nurse or pharmacist who demonstrates the pen; the leaflet in the box is the written version of the same instructions, and neither should be replaced by a video from a stranger.
Technique does influence skin reactions, and the mechanisms are mechanical rather than mysterious:
- Injecting cold medicine stings more. The leaflet describes conditions under which a pen can be kept at room temperature; follow that rather than improvising.
- Alcohol left wet on the skin is carried in by the needle and burns. Letting the swab dry fully takes seconds and removes a common cause of a sharp sting.
- Pulling the needle out before the pen has finished delivering can leave medicine in the dermis, the upper skin layer, where it is more irritating than in fat.
- Needles are single use. A reused needle is blunter and no longer sterile, and both raise the odds of bruising and of infection.
- Injecting into muscle, more likely in very lean areas, hurts more and may change how quickly the drug is absorbed.
Pressing gently on the site for a few seconds afterward reduces bruising; rubbing does the opposite. And a red mark that keeps appearing on exactly the same spot is often a technique or rotation habit rather than an allergy, which is a welcome finding because habits are fixable.
If any step feels uncertain, ask the prescriber’s office for a repeat demonstration. Clinics do this routinely, and a five-minute refresher resolves more “rash” complaints than any cream.
Why rotating your Ozempic injection site matters more than choosing the perfect one
Rotation is the single most evidence-backed habit for skin health with any injected hormone, and the evidence comes largely from insulin. People who inject insulin into the same small area day after day develop lipohypertrophy, a rubbery thickening of fat under the skin. The National Institute of Diabetes and Digestive and Kidney Diseases notes that such lumps can change how insulin is absorbed, making glucose control less predictable. The same biology applies to any hormone injected into fat, including semaglutide, even though weekly dosing gives the tissue far more time to recover.
A simple rotation plan that nurses commonly teach:
- Divide each region into zones, for example the left and right halves of the abdomen, and alternate between them week to week.
- Within a zone, move at least a finger’s width (about 2 centimeters) from the last puncture point.
- Avoid skin that is bruised, scarred, thickened, tattooed over recently, or affected by a current rash.
- Keep a note on a calendar or phone of where the last injection went; memory is unreliable across seven days.
Rotation also reduces the delayed, eczema-like reactions discussed earlier, because the immune cells in a recently injected patch are already primed. Giving them a week off and moving a hand’s breadth away lowers the chance of stacking one response on another.
What rotation cannot do is prevent a true systemic allergy. Hives on the back or swelling of the lips are not a site problem and should never be managed by simply switching to the other thigh. That distinction is worth repeating because it is the most common misunderstanding in online threads: a local problem has local solutions, a body-wide problem needs a clinician.
Bruising, lumps and nodules at the injection site: are they dangerous?
Not usually, but each has a story, and the story determines whether it needs a second look.
A bruise is blood that leaked from a small vessel nicked by the needle. It can appear immediately or bloom the next day, turn purple then yellow-green, and clear within one to two weeks. People taking blood thinners or aspirin bruise more easily, as do those with thin fat layers or low vitamin C intake. A bruise that is unusually large, keeps growing, or appears without any injection should be reported, because it may point to a bleeding tendency unrelated to the pen.
A small firm lump felt a day or two later is often a tiny pocket of medicine still being absorbed or minor inflammation around the track of the needle. These soften over several days. A lump that persists for weeks, enlarges, feels hot, or oozes needs medical evaluation; a sterile abscess (a walled-off collection without infection) or an infected one are both possible, and the two are managed differently.
A rubbery, painless thickening across an area that has been used repeatedly fits lipohypertrophy, described in the previous section. It is not dangerous in itself, but it signals that rotation has lapsed and that absorption from that area may be uneven. Clinicians usually advise resting the area for weeks to months and will say how long.
Rarely, a persistent nodule turns out to be something unrelated to the injection, such as a cyst or lipoma (a benign fatty growth) that was there already and only noticed because attention was drawn to the area. That is one more reason to describe lumps to a clinician rather than diagnosing them from a photo.
For all of these, the useful record is a dated photo with a coin for scale. It turns a vague “it looked worse last week” into information a clinician can act on.
What the evidence actually says about Ozempic skin reactions, graded by strength
Readers deserve to know not just what is claimed but how firm the ground is. Here is the evidence sorted by quality.
Strong (randomized controlled trials). The frequency of local injection site reactions, around 0.2 percent of participants, comes from the pivotal SUSTAIN trials, randomized studies comparing semaglutide with placebo or other diabetes medicines in several thousand adults. Placebo-controlled design is what allows the conclusion that the needle and solution contribute as much as the drug. The roughly 1 percent rate of anti-semaglutide antibodies is also trial-derived. Comparable drug exposure across abdomen, thigh and upper arm comes from controlled pharmacokinetic studies in volunteers, which are small but well designed for that question.
Moderate (observational data and pharmacovigilance). Serious hypersensitivity reactions, including anaphylaxis and angioedema, were identified from post-marketing reports rather than trials. These reports establish that the events occur and are rare, but they cannot give a reliable rate or always prove causation. Real-world discontinuation patterns, discussed later, also come from observational claims data.
Weak (expert opinion and extrapolation). The advice to rotate sites and avoid lipohypertrophy is extrapolated from decades of insulin experience and endorsed by diabetes educators; it is sensible biology rather than something tested in a semaglutide trial. Preferences for abdomen over thigh for comfort are experiential. The idea that excipients such as phenol explain some delayed reactions is plausible and supported by case reports, but has not been tested systematically.
Unsupported. Claims that an injection site rash signals the drug is “detoxing” fat, that it predicts weight-loss success, or that it can be prevented with a specific supplement have no evidence behind them.
The practical upshot: the common reaction is well characterized and reassuring; the rare serious one is real but uncommon; and most technique advice is reasonable rather than proven. That is an honest map, and it is enough to act on.
Common myths about Ozempic rashes and injection sites, corrected
“You can smell when someone is on Ozempic.” There is no study, case series or pharmacology that supports a detectable “Ozempic smell.” What is documented is slower stomach emptying, which can cause belching, reflux and the sulfur-tasting burps many users describe, and the fruity or acetone-like breath that comes from ketones when anyone eats very little or follows a very low-carbohydrate diet. Both are about what is happening in the gut and metabolism, not a drug odor seeping through the skin.
“A rash at the site means you’re allergic and must stop.” A coin-sized red patch that fades in days is irritation, not allergy, and the prescribing clinician, not the rash, decides whether anything about treatment should change. Stopping a prescribed medicine because of a social-media verdict can destabilize blood sugar in people with diabetes.
“The stomach absorbs it faster than the thigh.” Controlled studies found comparable exposure across approved sites. Choose for comfort and rotation, not speed.
“Compounded semaglutide is the same thing, just cheaper.” Compounded products are not FDA-approved, are not tested for purity, potency or sterility the way the branded pen is, and with the shortage resolved in February 2025 are no longer permitted for routine mass production. They are not for sale or self-use outside narrow, clinician-directed circumstances.
“Ozempic face is a type of rash.” The term describes the loss of facial fat volume that accompanies rapid weight loss by any method, which Harvard Health explains is a consequence of the weight loss itself rather than a skin reaction to the drug.
“Pressing an ice cube on the site before injecting prevents all reactions.” Cold numbs briefly and may reduce the sting, but it does nothing to prevent an immune response, and very cold skin can bruise more easily.
“If one GLP-1 medicine gives you a rash, they all will.” Different products use different excipients and different peptides. Whether a reaction to one predicts a reaction to another is a question for an allergist or the prescriber, not an assumption.
Why are people stopping Ozempic, and does a rash have anything to do with it?
Skin reactions are, by the data, a minor reason. The leading causes of discontinuation in both trials and real-world analyses are gastrointestinal. In clinical trials roughly one in five people on Ozempic reported nausea at some point, with vomiting, diarrhea and constipation also common, especially in the first weeks and after dose adjustments made by the prescriber. For a minority these effects were persistent enough to lead them to stop.
Observational analyses of US insurance claims, which track prescriptions filled rather than reasons given, have found that a substantial share of people who start a GLP-1 medicine for weight management no longer fill it a year later; estimates range widely, from roughly a third to more than half, depending on the population and whether the drug was prescribed for diabetes or weight. Those studies cannot say why each person stopped, but surveys and clinician reports point to a familiar list: side effects, difficulty with access during the shortage years, changes in insurance coverage, reaching a personal goal, or feeling that benefits had plateaued.
Two facts from the evidence belong in this conversation. First, weight regain after stopping is well documented; in an extension of a major semaglutide weight-management trial, participants regained about two thirds of lost weight within a year of discontinuation. Second, for people prescribed Ozempic for type 2 diabetes, stopping removes its blood sugar, heart and kidney benefits along with its side effects.
None of this is an argument for or against continuing. It is context. Anyone weighing whether to stop, including because of a troubling skin reaction, should bring that question to the prescribing clinician, who can distinguish a reaction that needs the medicine reconsidered from one that needs a technique refresher, and who can plan what happens next if a change is made.
When to see a doctor about an Ozempic injection site reaction or rash
Most of this article has been about distinguishing ordinary from concerning. This section is the distilled version to keep on your phone.
Call emergency services immediately if, after an injection, you notice:
- Swelling of the lips, tongue, face, eyelids or throat, or a feeling that the throat is closing.
- Wheezing, shortness of breath, or difficulty swallowing or speaking.
- Hives together with dizziness, faintness, a racing heart, or sudden vomiting or cramps.
- A rash that is blistering, peeling, or involves the mouth or eyes.
Contact the prescriber the same day if:
- Hives or an itchy rash appear anywhere away from the injection site.
- Redness at the site spreads beyond about 5 centimeters, feels hot, or comes with fever or red streaks.
- A lump is painful, enlarging, or draining fluid.
- A reaction at the site appears a day or two after each injection and is getting larger week by week.
Mention at the next scheduled visit if:
- You get a small red, itchy or bruised spot that fades within a few days.
- You have noticed firm, rubbery areas where you often inject.
- A site that used to be comfortable has started to sting as you lose weight.
Bring dated photos with something for scale, a note of which site you used and when, and the pen’s lot information if a reaction was unusual, because clinicians may report it to the manufacturer and the FDA. Do not stop, skip or alter a prescribed dose on your own, and do not inject again to test whether a serious reaction repeats. Every decision about continuing, pausing or switching medicines rests with the clinician who prescribed it, who knows your diabetes, heart and kidney picture and can weigh a skin reaction against the reasons the medicine was started.
Frequently asked questions
Is a small red bump at my Ozempic injection site normal?
Yes, a coin-sized red, itchy or slightly tender spot that fades within one to three days is a recognized mild reaction and occurred in about 0.2 percent of trial participants. It should stay local and not come with fever. Mention it at your next visit, and contact the prescriber sooner if it spreads, feels hot, or appears a day or two after every injection and keeps growing.
What does an Ozempic rash from a true allergy look like?
A true allergic reaction typically produces hives, raised itchy welts that appear away from the injection site and move around the body, sometimes with swelling of the lips, eyelids, tongue or throat. If swelling, wheezing, dizziness or trouble swallowing accompany the rash, that pattern fits anaphylaxis and is an emergency. A spot confined to the needle site that fades in days is irritation rather than allergy.
Is Ozempic in the thigh better than the stomach?
Neither is better for how the medicine works; controlled studies found comparable drug exposure from the abdomen, thigh and upper arm. Many people find the abdomen more comfortable because its fat layer is thicker and has fewer nerve endings, while the thigh may sting more in lean people. The useful habit is rotating between and within approved areas rather than favoring one spot.
Do you pinch the skin for an Ozempic injection?
The Ozempic pen uses a short, fine needle designed to reach the fat layer without a skin fold in most adults, and the manufacturer’s instructions do not require pinching. Because technique is hands-on, learn it from the nurse or pharmacist who demonstrates the pen and follow the leaflet in the box. Ask for a repeat demonstration if a step feels uncertain or a site keeps bruising.
Can you smell when someone is on Ozempic?
No evidence supports a detectable drug odor. What people may notice is sulfur-tasting burps or reflux from slower stomach emptying, which the medicine causes, and acetone-like breath from ketones when someone eats very little or follows a very low-carbohydrate diet. Both relate to digestion and metabolism rather than to semaglutide leaving the body through the skin or breath.
Why does my injection site itch for days after Ozempic?
Itching that lasts several days, especially if it appears a day or two after each injection as a dry or eczema-like patch, suggests a delayed local hypersensitivity driven by immune cells rather than simple needle irritation. It is not an emergency, but it should be reported to the prescriber soon, because the pattern can grow with repeated exposure and clinicians may want to assess whether the drug or an inactive ingredient is responsible.
Why are people stopping Ozempic?
The most common reasons in trials and real-world analyses are gastrointestinal side effects such as nausea, vomiting and constipation, followed by access problems during the shortage years, insurance changes, and reaching personal goals. Skin reactions are a minor contributor. Weight regain after stopping is well documented, and for people with type 2 diabetes stopping also removes blood sugar, heart and kidney benefits, so the decision belongs with the prescribing clinician.
Can I inject Ozempic into a spot that still has a mark from last week?
It is better not to. A site that is still red, bruised, lumpy or thickened is still recovering, and reinjecting it stacks irritation on irritation and encourages lipohypertrophy, a rubbery fat thickening that can make absorption uneven. Move at least a finger’s width away, alternate between approved regions, and keep a simple note of where each injection went so memory does not have to carry it.
Does a rash at the Ozempic injection site mean the medicine is working?
No. A local skin reaction reflects the needle, the solution and the skin’s immune cells, not the medicine’s effect on appetite or blood sugar, and in trials placebo pens caused reactions at a similar rate. Claims that a rash signals detoxing or predicts weight loss have no evidence behind them. The medicine’s effects are judged by blood sugar readings, weight trends and how you feel, reviewed with your clinician.
Are compounded semaglutide injections more likely to cause skin reactions?
There is no controlled comparison, so the honest answer is unknown. What is known is that compounded semaglutide is not FDA-approved, is not tested for purity, potency or sterility the way the branded pen is, and with the shortage resolved in February 2025 is no longer permitted for routine mass production. It is not for sale or self-use outside narrow, clinician-directed circumstances, and any unusual reaction to it should be reported to a clinician.
References
- Semaglutide Injection: MedlinePlus Drug Information
- GLP-1 Agonists: Cleveland Clinic
- Insulin, Medicines, and Other Diabetes Treatments: NIDDK, National Institutes of Health
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Ozempic, Blood Pressure and Cholesterol: What the Cardiometabolic Trials Found
In randomized trials, Ozempic (semaglutide) modestly lowered systolic blood pressure, typically by about 2–5 mmHg compared with placebo, reduced triglycerides by roughly a fifth…

Traveling With Ozempic or Mounjaro: Storage, Time Zones and Airport Rules
Traveling with Ozempic, Wegovy or Mounjaro is routine if you plan for temperature and timing. Keep pens in carry-on luggage, never checked, inside an…

Ozempic Not Working? The Common Reasons Weight Loss Stalls and What Doctors Check
If Ozempic is not working, the most common reasons are that the dose is still being stepped up, daily calories remain higher than reduced…

GLP-1 Medicines in Menopause: What Studies Show for Midlife Weight and Metabolic Change
GLP-1 medicines produce substantial average weight loss in randomized trials of adults with obesity, and subgroup data suggest women in and after menopause lose…

Ozempic vs Metformin: How the Two Diabetes Medicines Differ, and Why They Are Often Combined
Ozempic (semaglutide) and metformin both lower blood sugar in type 2 diabetes but work differently. Metformin, a daily tablet, mainly reduces glucose released by…

GLP-1 Long-Term Effects: What Multi-Year Studies Show About Staying on These Medicines
Multi-year studies of GLP-1 medicines such as semaglutide and tirzepatide, with follow-up of up to about four years, have not identified new serious long-term…