

What X-Rays and MRI Show After a Shoulder Dislocation: Fractures, Labrum and Ligament Damage

Key Takeaways
- X-rays are taken both before and after reduction because the second film often reveals a Hill-Sachs dent or glenoid rim fragment that was hidden while the joint was out of place.
- The axillary or scapular Y view, not the front-on view, is what reliably separates an anterior from a posterior dislocation, and posterior dislocations are the ones most often missed on a single film.
- Plain x-rays cannot show the labrum, ligaments, capsule or rotator cuff, so a normal post-reduction film does not rule out the soft-tissue injuries that most affect long-term stability.
- MRI is usually reserved for young athletes after a first dislocation, anyone with recurrent instability, and older adults who stay weak after the pain settles, rather than being ordered for everyone.
- Rotator cuff tears, not labral tears, are the more common accompanying injury in adults over about forty, which is why persistent weakness in this group prompts further imaging.
- The NHS gives a typical full recovery window of around 12–16 weeks, with younger, active people carrying the highest risk of the shoulder dislocating again according to Mayo Clinic.
An x-ray after shoulder dislocation confirms the joint is out, shows which direction it went, and checks for associated fractures of the humeral head, glenoid rim or greater tuberosity, both before and after the shoulder is put back. X-rays cannot show the labrum, ligaments or capsule; when those soft-tissue injuries need assessment, usually in younger or recurrent cases, the treating team may add an MRI or MR arthrogram.
The rugby player is still in his boots when he arrives, right arm cradled against his stomach, shoulder squared off in a way that looks wrong even from across the room. He wants one thing: for someone to put it back. What he does not expect is the detour to the imaging suite first, and then a second visit to the same machine an hour later, after the joint has slipped home and the pain has dropped away.
That double trip is not bureaucracy. An x ray after shoulder dislocation answers two separate questions, one before the joint is relocated and one afterward, and the answers change what happens next. A hidden chip of bone on the socket rim, a dent in the ball of the arm bone, a fracture line near the tendons: any of these can turn a straightforward sling-and-physiotherapy plan into something more careful.
Then there is the question the x-ray cannot answer at all. The cartilage rim and ligaments that hold the shoulder together are invisible on film, which is why MRI enters the conversation for some people and not for others. This article walks through what each scan shows, what it misses, and how those pictures shape recovery.
Will a dislocated shoulder show on an X-ray?
Yes, almost always. A shoulder dislocation means the ball of the upper arm bone, the humeral head, has been forced completely out of its shallow socket, the glenoid. On a standard front-on x-ray the ball normally sits neatly against the socket like an egg resting in a very shallow cup. When it is dislocated, the ball is visibly displaced, usually forward and downward toward the ribs, and the smooth overlap between the two surfaces is lost.
X-rays work by passing a small dose of radiation through the body onto a detector. Dense bone absorbs more radiation and shows up white; muscle, tendon and cartilage let most of it through and appear as shades of grey that blend together. That is exactly why the test is so good at one job and so limited at another: bone position and bone breaks are obvious, while the soft structures that actually stabilise the shoulder are essentially invisible.
According to Mayo Clinic, the shoulder is the most mobile joint in the body, which is precisely what makes it the joint most often dislocated. The glenoid covers only a fraction of the humeral head, so the joint relies on a rim of cartilage called the labrum, a bag-like capsule and a set of ligaments to stay in place. When those give way, the bone moves, and the x-ray records the result.
One caveat is worth knowing. A partial slip, where the ball moves and then drops back on its own (a subluxation), may look completely normal on x-ray by the time the image is taken. The film shows the current position, not the history. In that situation the story you tell the clinician matters as much as the picture.
Why doctors take an X-ray before and after putting the shoulder back
The first x-ray, taken while the shoulder is still out, does three things. It confirms the diagnosis, since a very swollen shoulder or a fracture just below the ball can mimic a dislocation on examination. It shows the direction of displacement, which decides which manoeuvre the clinician will use to relocate it. And it screens for fractures that could be made worse by pulling on the arm. A break through the surgical neck of the humerus, for instance, is a reason to slow down and reconsider how, and where, the joint is reduced.
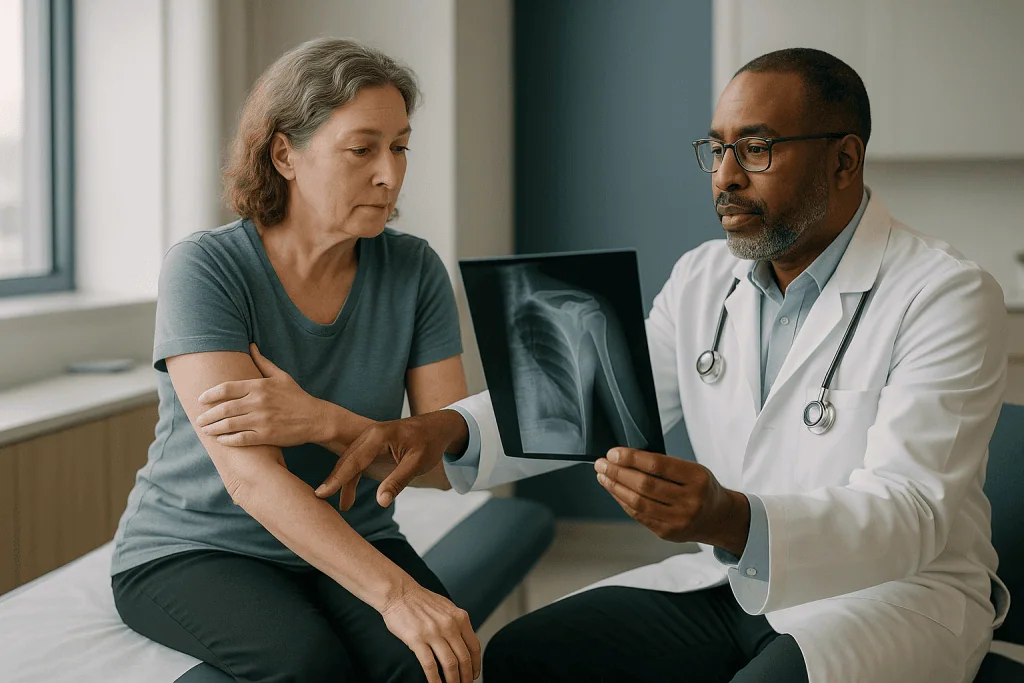
Relocating the joint is called a reduction: a controlled, unhurried set of movements, usually with pain relief or sedation chosen by the emergency team, that guides the ball back into the socket. Mayo Clinic notes that once the shoulder is back in place, the severe pain usually eases almost immediately.
Then comes the second x-ray. Its purpose is different. It confirms the ball is truly seated, not perched on the rim in a near-miss position, and it re-checks for fractures that were hidden by overlapping bone in the dislocated position. A dent in the back of the humeral head, or a small fragment off the front of the socket, often becomes visible only once the anatomy is restored.
Some emergency departments skip the pre-reduction film in clear-cut recurrent cases when the patient recognises the injury and there is no suggestion of high-energy trauma. That is a clinical judgment, made by the treating team, and the post-reduction x-ray is still the standard check. Neither image is optional in a first-time dislocation with a real mechanism of injury.
What the x ray after shoulder dislocation looks for: the three common fractures
Three bony injuries come up again and again on the x ray after shoulder dislocation, and each tells the treating team something different.
The first is the Hill-Sachs lesion: a compression dent on the back of the humeral head, created when the ball is levered against the hard front edge of the socket on its way out. Picture pressing a thumb into a ripe peach. Small dents are common and usually of little consequence. Larger ones matter because they can catch on the rim when the arm is raised and rotated outward, which is one mechanical reason a shoulder keeps slipping.
The second is the bony Bankart lesion: a fracture of the front lower rim of the glenoid, where the labrum attaches. Losing a piece of that rim is like breaking a chip off the edge of a saucer; the cup that was already shallow becomes shallower still. The size of the missing segment is one of the factors surgeons weigh when discussing whether a shoulder is likely to stay stable with rehabilitation alone.
The third is a greater tuberosity fracture, a break at the bony knob on the outer side of the humeral head where the rotator cuff tendons insert. This one is more common in older adults and can be mistaken for a rotator cuff tear on examination, which is why the post-reduction film is read so carefully in this age group.
Less common findings include fractures of the coracoid, the small hook of bone at the front of the shoulder blade, and of the surgical neck of the humerus. Any fracture changes the plan, sometimes toward a longer period of protection, sometimes toward a specialist review, and always toward a conversation about what was seen.
Shoulder dislocation x ray views: why the axillary or Y view matters
A single front-on picture is not enough. Standard shoulder dislocation x ray views include at least two, and often three, angles, because a joint can look normal from the front while sitting entirely out of place from the side.

The anteroposterior (AP) view is the straight-on shot. In an anterior dislocation the humeral head sits low and toward the midline, often overlapping the socket, and the diagnosis is usually obvious. The scapular Y view is taken from the side along the plane of the shoulder blade, where the blade’s outline forms a Y shape; the socket sits at the junction and the ball should be centred on it. If the ball lies in front of or behind that junction, the joint is dislocated in that direction.
The axillary view is taken with the arm held slightly away from the body and the beam angled up through the armpit. It shows the ball and socket in cross-section and is the single most reliable view for distinguishing front from back and for spotting small rim fractures. It is also the view most often skipped, because lifting a freshly injured arm hurts. Modified axillary techniques exist for exactly this reason and require very little movement.
Why does this matter to a patient? Because the view that hurts most to obtain is often the one that prevents a missed diagnosis. If a clinician asks you to hold your arm a few centimetres from your side for a moment, that discomfort is buying the clearest possible picture of the socket rim and the direction of the injury.
Anterior versus posterior shoulder dislocation x ray: the one that gets missed
Mayo Clinic describes anterior dislocation, where the ball moves forward, as by far the most common pattern, typically produced by a fall onto an outstretched arm or a forceful twist with the arm raised. On x-ray the displacement is dramatic and hard to miss.
Posterior dislocation, with the ball pushed backward, is much rarer and behaves differently. It follows a fall onto a forward-flexed arm, a direct blow to the front of the shoulder, or a violent muscle contraction such as during a seizure or an electric shock. The clue that worries emergency clinicians is that a posterior shoulder dislocation x ray can look almost normal on the front-on view. The ball sits roughly level with the socket, just slightly behind it, and the outline stays deceptively tidy.
Radiologists look for subtle signs. The humeral head may appear unusually rounded, sometimes described as resembling a light bulb, because the arm is locked in internal rotation. The normal crescent of overlap between ball and socket may be lost, or the gap between them may widen. None of these is conclusive on its own, which is why the axillary or Y view is essential when the story or the examination raises suspicion.
Missed posterior dislocations do happen, and a shoulder that stays out for weeks becomes progressively harder to treat. This is one of the strongest arguments for taking multiple views in every acute shoulder injury and for asking your clinician directly, if your shoulder feels locked and the film has been called normal, whether a second angle has been checked.
Inferior dislocation, where the arm is stuck pointing upward, is rarer still and unmistakable both in the room and on film.
What an X-ray cannot see: labrum, ligaments and capsule
Here is the honest limit of the technology. The structures most likely to be torn in a dislocation are the ones the x-ray cannot show.
The labrum is a ring of fibrous cartilage around the edge of the glenoid, a little like the rubber gasket on a jar lid. It deepens the socket and anchors the main stabilising ligaments. When the ball is forced forward, the front lower labrum is frequently peeled off the bone. That is the soft-tissue Bankart lesion, distinct from the bony version described earlier, and it is completely invisible on plain film.
The glenohumeral ligaments are thickened bands within the joint capsule, the fibrous bag that encloses the joint. They act as check-reins at the extremes of movement. In a dislocation they can stretch, tear in the middle, or pull away from the humeral side, an injury called a HAGL lesion (humeral avulsion of the glenohumeral ligament). Again, none of this appears on x-ray.
The rotator cuff, the group of four tendons wrapping the humeral head, is also invisible. In people over roughly forty, a dislocation is more likely to tear the cuff than to tear the labrum, and Mayo Clinic lists cuff and other soft-tissue damage among the recognised complications of the injury. A normal post-reduction x-ray in an older adult who still cannot lift the arm after the initial pain settles is a classic reason to move on to further imaging.
Nerve and blood vessel injury, particularly to the axillary nerve that supplies the deltoid muscle, is assessed by examination rather than imaging. Numbness over the outer shoulder or weakness raising the arm is documented before and after reduction for this reason.
When is an MRI after shoulder dislocation needed, and who is usually asked to wait?
Not everyone needs one. An MRI after shoulder dislocation is a targeted test, and the treating team weighs several factors before ordering it.
MRI is commonly considered when a first-time dislocation occurs in a young, active person, particularly someone in contact or overhead sport, because this group has the highest risk of the shoulder dislocating again, a pattern Mayo Clinic describes when discussing recurrent instability. Knowing whether the labrum has detached helps frame the conversation about rehabilitation versus early surgical repair. It is also used when a shoulder keeps slipping despite good physiotherapy, when the x-ray shows a bone fragment whose size needs clarifying (though CT is often preferred for bone), and when an older adult remains weak after the pain has faded, raising concern about a rotator cuff tear.
Who is usually asked to wait? Many people with a first, uncomplicated anterior dislocation, a clean post-reduction x-ray and no ongoing weakness begin rehabilitation without any MRI. The plan is to see how the shoulder behaves over the following weeks. Scanning everyone would find labral tears in many shoulders that go on to do perfectly well with strengthening, and a scan result does not by itself decide treatment.
Timing matters too. In the first days after injury, blood and fluid inside the joint can actually help outline a torn labrum on a standard MRI. Later, once that fluid has settled, radiologists often prefer an MR arthrogram, in which a contrast fluid is injected into the joint before scanning to spread the structures apart. Which test, and whether at all, sits with the clinician who examined you.
What MRI shows that X-rays miss: Bankart tears, HAGL lesions and rotator cuff damage
MRI builds its images from the behaviour of water molecules in a strong magnetic field rather than from radiation, so tissues with different water content appear distinct. Cartilage, ligament, tendon, muscle and fluid each have their own signal, which is what makes the test suited to soft tissue.
On MRI, a soft-tissue Bankart lesion appears as the front lower labrum lifted away from the glenoid rim, often with joint fluid tracking into the gap. Variants exist in which the labrum is torn but still tethered by periosteum, the thin membrane covering bone, and radiologists describe these carefully because they can heal differently. The scan also shows the size and position of a Hill-Sachs dent, though CT measures bone loss more precisely.
A HAGL lesion, where the inferior ligament tears from the humerus rather than the socket, is a finding that specifically changes surgical planning if repair is considered, and it is essentially an MRI diagnosis. Capsular stretching is harder to quantify but can be inferred from an unusually roomy joint on the images.
For older adults, MRI answers the rotator cuff question. A full-thickness tear shows as a gap in the tendon filled with fluid; a partial tear shows as signal change without a complete gap. Mayo Clinic lists rotator cuff damage among the injuries that can accompany a dislocation, and in this age group it is often the finding that most influences the recovery path.
The scan also reveals bone bruising, cartilage surface damage and, occasionally, an unexpected fracture the x-ray under-called. What it cannot do is predict with certainty who will dislocate again. A torn labrum is a risk marker, not a verdict, and that distinction belongs in the conversation with your team.
X-ray, CT, MRI or MR arthrogram: which scan answers which question
Each test has a job. The table below summarises what the treating team is typically hoping to learn from each, and where the limits lie. It is a guide to the conversation, not a menu; the choice depends on your age, your activity, what the examination shows and what the first films revealed.
| Test | Best at showing | Poor at showing | Typical situation |
|---|---|---|---|
| Plain x-ray | Joint position, direction of dislocation, obvious fractures, Hill-Sachs dent, larger rim fragments | Labrum, ligaments, capsule, rotator cuff | Every acute dislocation, before and after reduction |
| CT scan | Precise size and shape of bone loss on glenoid and humeral head, complex fractures | Soft tissue | Planning when x-ray shows a significant bony fragment, or recurrent instability with suspected bone loss |
| MRI (no contrast) | Labrum, ligaments, rotator cuff, bone bruising, joint fluid | Fine bone detail; subtle labral tears once early joint fluid has resolved | Young athletes after a first dislocation, older adults with persistent weakness |
| MR arthrogram | Detailed labral and capsular anatomy, small or partially healed tears | Requires an injection into the joint; less useful for bone measurement | Recurrent instability, or a delayed scan when surgery is being discussed |
A few practical notes. CT and x-ray use ionising radiation; MRI does not, but it takes longer, requires lying still inside a tunnel, and is unsuitable for some implanted devices, so you will be asked a safety questionnaire beforehand. MedlinePlus explains that dislocation diagnosis rests on examination first, with imaging chosen to confirm and to look for associated injury. Ultrasound, performed at the bedside, can also assess the rotator cuff and is sometimes used to confirm a reduction, though it is not a substitute for the post-reduction x-ray in most settings.
What the days and weeks after a dislocated shoulder usually look like
Once the joint is back and the post-reduction film is clear, the shoulder is rested in a sling. The NHS advises that many people can come out of the sling after a few days for gentle movement, while the treating team may recommend longer protection if there is a fracture or a concern about early re-dislocation. Ice wrapped in a cloth for short periods helps swelling in the first days; pain relief is usually a simple analgesic or anti-inflammatory chosen and explained by the prescribing clinician, and any decision about medicines belongs with that clinician.
Physiotherapy typically begins with pendulum swings and passive range-of-motion work, then progresses to strengthening the rotator cuff and the muscles that steady the shoulder blade. The aim is to teach the muscular stabilisers to compensate for whatever the ligaments have lost. Movements that reproduce the injury position, the arm raised and rotated outward, are reintroduced last and cautiously.
The NHS gives a typical full recovery window of around 12–16 weeks, though return to contact sport or heavy overhead work is a separate conversation and often comes later. Mayo Clinic notes that recovery is slower and more guarded when nerve, blood vessel or significant soft-tissue damage accompanies the dislocation.
A follow-up visit, often within a couple of weeks, is where the team re-examines strength and sensation, reviews the films, and decides whether MRI is warranted. This is also the moment to raise persistent numbness over the outer shoulder, ongoing weakness lifting the arm, or a feeling that the joint is about to slip. Those symptoms redirect the plan; silence about them delays it.
How painful is a dislocated shoulder, and do you fully recover?
People searching for a number out of ten will not find an honest one. Pain is personal, and the same injury produces very different scores in different people. What the evidence does support is the pattern: pain while the joint is out is typically intense, driven by stretched capsule, muscle spasm and the abnormal position, and it drops sharply once the ball is back in the socket. Mayo Clinic describes this near-immediate relief after reduction. Afterward, a deep ache and stiffness persist for days to weeks, generally easing as swelling settles.
Do you fully recover? Many people do, in the practical sense of regaining pain-free movement and strength within the NHS’s typical 12–16 week window and returning to the things they did before. Two qualifications matter. First, a first dislocation raises the chance of another, and Mayo Clinic is clear that younger, active people, especially men, carry the highest recurrence risk. Second, older adults may find that a coexisting rotator cuff tear, rather than the dislocation itself, becomes the limiting factor.
Neither outcome is fixed. Recurrence risk is influenced by what the imaging shows (bone loss, a detached labrum), by how thoroughly the stabilising muscles are rebuilt, and by the demands you place on the shoulder afterward. Surgery to repair the labrum or address bone loss is one option the team may discuss when instability persists or the imaging findings are substantial; it carries its own risks and a rehabilitation of its own, and it is not the default for every first dislocation.
The realistic framing is this: recovery is common, recurrence is possible, and the imaging findings plus your age and activity are what the team uses to estimate where you sit between the two.
What should you not do after a shoulder dislocation?
The most important prohibition is the first one: do not let anyone try to force the shoulder back in at the roadside, the sideline or the kitchen table. Mayo Clinic advises against attempting to move or push the joint back into place, because the manoeuvre can damage the joint surfaces, the surrounding vessels and nerves, or convert a simple dislocation into one with a fracture. Support the arm in the position it is in and get to emergency care.
After reduction, the rules shift toward protecting healing tissue. Avoid raising the arm out to the side and rotating it outward, the classic throwing or reaching-back position, until your physiotherapist clears it; this is the movement that dislocated the joint and the one most likely to do so again while the capsule is healing. Skip heavy lifting, pushing and pulling with the affected arm for the period your team specifies. Do not remove the sling early because the pain has eased; pain relief is not the same as tissue healing.
Resist the temptation to test the joint. People sometimes probe how far the arm will go to reassure themselves. That reassurance is not worth the risk while the labrum and ligaments are re-attaching.
Do not ignore new symptoms. Tingling, numbness, coldness or colour change in the hand, or an inability to lift the arm that persists once the acute pain has settled, need review rather than patience.
Finally, do not skip the rehabilitation once the shoulder feels normal. The muscular stability that protects against a second dislocation is built in the weeks after you stop hurting, which is exactly when motivation tends to fade.
What people often get wrong about shoulder dislocation imaging
“A normal x-ray means nothing is torn.” This is the most common misunderstanding. A clean post-reduction film rules out major fractures and confirms position. It says nothing about the labrum, ligaments or rotator cuff, which are the structures most often injured. Normal x-ray plus persistent weakness or instability is a reason for further assessment, not reassurance.
“If the MRI shows a tear, I need surgery.” Not necessarily. Labral tears are common after dislocation, and many shoulders with a torn labrum become stable with rehabilitation. Surgeons weigh the scan alongside age, activity, recurrence and bone loss. The image informs the decision; it does not make it.
“I popped it back myself, so I don’t need an x-ray.” Self-reduction, or spontaneous reduction, is not uncommon in people with recurrent instability. It still leaves open the questions a film answers: is the joint fully seated, and did this episode chip bone? Mayo Clinic’s guidance on seeking prompt care after dislocation applies whether or not the joint went back on its own.
“Only athletes dislocate shoulders.” Falls in older adults are a major cause, and in that group the associated rotator cuff tear is often the bigger problem than the dislocation.
“The pain rating tells the doctor how bad the damage is.” Pain intensity at the time of injury correlates poorly with what the imaging shows. A modest ache can accompany a significant labral tear; agonising pain can settle into a shoulder with no structural damage at all.
“Once it’s back in, the injury is over.” Reduction ends the emergency. The weeks that follow decide the long-term outcome.
Questions to ask your care team about your X-ray and MRI results
Imaging reports are written for clinicians, and the words in them can sound alarming without context. These questions help turn a report into a plan you understand.
- Which direction did my shoulder dislocate, and did the x-ray show any fracture of the humeral head, socket rim or greater tuberosity?
- If there is a Hill-Sachs dent or a rim fragment, how large is it, and does its size change what you recommend?
- Was an axillary or Y view obtained, and was the joint confirmed to be fully seated afterward?
- Do I need an MRI or MR arthrogram, and if not now, what would prompt one later?
- If an MRI has been done, is the labrum detached, are the ligaments intact, and is the rotator cuff torn?
- Given my age, activity and these findings, how do you estimate my risk of the shoulder dislocating again?
- What movements should I avoid, for how long, and who will tell me when they are safe again?
- Is surgery something you would consider for me, what would it involve, and what are the alternatives?
- How long should I use the sling, and when does physiotherapy start?
- What signs would mean I should come back before my scheduled follow-up?
Ask for a copy of the imaging report and, if possible, a look at the images themselves. Seeing the dent on the humeral head, or the ball sitting square in the socket after reduction, makes the plan far more concrete. Bring a second person to the follow-up if you can; shoulder anatomy is hard to absorb while you are also worrying about work, sport or how you will sleep tonight. The decisions about further scans, rehabilitation intensity and surgery belong to you and your treating team together.
When to call your doctor after a shoulder dislocation
A shoulder that has been put back and imaged should steadily improve. Certain signs mean the plan needs to change, and they warrant prompt contact with your team or, in some cases, emergency care.
Seek emergency care immediately if the shoulder appears to have dislocated again, if the hand or forearm becomes numb, cold, pale or blue, if you cannot feel a pulse at the wrist, or if there is sudden, severe swelling. The NHS and Mayo Clinic both flag numbness, tingling and circulation changes as signs of possible nerve or blood vessel injury that need urgent assessment.
Contact your doctor promptly, without waiting for the routine follow-up, if you notice any of the following.
- Persistent numbness or a patch of altered sensation over the outer shoulder, which can indicate injury to the axillary nerve.
- Ongoing inability to lift the arm away from the body once the initial pain has eased, especially if you are over forty; this raises the question of a rotator cuff tear.
- A sense that the joint is loose, catching or about to slip during ordinary movements.
- Pain that worsens rather than improves after the first few days, or pain that wakes you regularly at night beyond the early period.
- Fever, spreading redness or warmth around the shoulder, particularly if any injection or procedure was performed.
- New clicking or locking that was not present before the injury.
Pediatric considerations deserve a separate mention. In children and adolescents the growth plate near the shoulder can be injured in a fall that looks like a dislocation, and imaging is read with that in mind. Any child with a shoulder injury who cannot move the arm normally should be assessed rather than watched at home.
None of these signs means something has gone wrong with your care. They are the signals that tell the treating team where to look next.
Frequently asked questions
Will a dislocated shoulder show on an X-ray?
Yes. A complete dislocation is clearly visible on a standard x-ray as the humeral head sitting outside the glenoid socket. The film also shows the direction of displacement and any associated fracture. A partial slip that has already returned to place may look normal, so describing exactly what happened to the clinician matters as much as the image.
Why do I need a second x-ray after the shoulder is put back in?
The post-reduction x-ray confirms the ball is fully seated in the socket and re-checks for fractures that overlapping bone may have hidden in the dislocated position. Dents in the humeral head and chips off the socket rim frequently become visible only once the anatomy is restored, and these findings can change how long the shoulder is protected.
What is a Hill-Sachs lesion on an x ray?
A Hill-Sachs lesion is a compression dent on the back of the humeral head, created when the ball is forced against the hard front edge of the socket during dislocation. On x-ray it appears as a flattened or notched area. Small dents are common; larger ones can catch on the socket rim and contribute to repeat dislocations.
When is an MRI after shoulder dislocation recommended?
MRI is commonly considered for young, active people after a first dislocation, for anyone whose shoulder keeps slipping despite rehabilitation, and for older adults who remain weak once the initial pain has settled. It assesses the labrum, ligaments and rotator cuff, which x-rays cannot show. The decision rests with the treating team based on examination and the first films.
What does a posterior shoulder dislocation x ray look like?
A posterior dislocation can look deceptively normal on a front-on x-ray, with the humeral head appearing unusually round and sitting slightly behind the socket. The axillary or scapular Y view shows the displacement clearly. Because this pattern is rare and subtle, radiologists look specifically for it when the history involves a seizure, electric shock or a fall onto a forward-flexed arm.
Do you ever fully recover from a dislocated shoulder?
Many people regain full, pain-free movement, with the NHS describing a typical recovery of around 12–16 weeks. The main long-term concern is recurrence, which Mayo Clinic notes is highest in younger, active people. Imaging findings such as bone loss or a detached labrum, along with how well the stabilising muscles are rebuilt, influence that risk.
How painful is a dislocated shoulder on a scale of 1 to 10?
There is no reliable single number, because pain is personal and varies widely. The evidence supports a pattern rather than a score: pain while the joint is out is usually intense, then eases sharply once the shoulder is reduced, as Mayo Clinic describes. A deep ache and stiffness typically follow for days to weeks and settle as swelling resolves.
What should you not do after a shoulder dislocation?
Do not let anyone force the joint back outside a medical setting, since this can damage nerves, vessels and joint surfaces. After reduction, avoid raising the arm out to the side and rotating it outward until cleared, do not stop using the sling early just because pain has eased, and do not skip rehabilitation once the shoulder feels normal.
Can an X-ray show a torn labrum or ligament?
No. The labrum, ligaments and joint capsule are soft tissues that appear as indistinguishable grey on x-ray. A normal post-reduction film only confirms position and rules out obvious fractures. If a soft-tissue tear is suspected because of ongoing instability or weakness, MRI or an MR arthrogram is the test that shows these structures.
Does a torn labrum on MRI mean I will need surgery?
Not automatically. Labral tears are common after dislocation, and many shoulders stabilise with structured rehabilitation. Surgeons weigh the scan alongside age, activity level, whether the shoulder has dislocated more than once, and how much bone has been lost from the socket or humeral head. Surgery is one option among others, and the choice sits with you and your treating team.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Who Is a Candidate for Cartilage Restoration? Defect Size, Alignment and Age Considerations
A cartilage restoration candidate is usually someone with a single, well-defined area of damaged joint cartilage, healthy surrounding cartilage, a stable and reasonably well-aligned…

Life After Cruciate Ligament Surgery: Stairs, Driving, Desk Work and Sport in Order
Life after cruciate surgery follows a fairly predictable order. Walking with crutches comes first, usually within days; stairs and desk work return over the…

ACL Surgery Cost: What Reconstruction Really Costs, Market by Market
ACL reconstruction typically costs USD 20,000–50,000 in the United States, GBP 7,000–14,000 for private surgery in the UK, and EUR 3,900–7,150 within our guide…
How Shoulder Impingement Is Diagnosed: The Exam Tests and When an Ultrasound or MRI Is Ordered
Shoulder impingement is diagnosed mainly by a clinician's history and hands-on examination: where the pain sits, which movements provoke it, and how the shoulder…

Tendon Surgery Recovery: Why the Splint Stays On and How Gliding Exercises Begin
Tendon surgery recovery time is usually measured in months rather than weeks. A splint typically protects a repaired hand tendon for roughly four to…

Preparing for Arthroscopy: Medication Review, Fasting and Arranging a Ride Home
Preparing for arthroscopy usually rests on three tasks: giving your surgical team a complete list of every prescription medicine, over-the-counter product and supplement you…