

Who Is Hyperbaric Oxygen Therapy For? Wounds, Radiation Injury and Other Recognized Indications

Key Takeaways
- Hyperbaric oxygen works by dissolving oxygen directly into blood plasma at two to three times normal atmospheric pressure, reaching tissue that red blood cells cannot.
- Decompression sickness and arterial gas embolism are the only indications where hyperbaric oxygen is the primary treatment; everywhere else it is added to surgery, antibiotics or wound care.
- Delayed radiation injury to the jaw, bladder or rectum can appear months or years after radiotherapy and is one of the best-established non-emergency indications.
- An untreated collapsed lung is the one absolute barrier to treatment, while colds, ear infections and uncontrolled blood sugar usually mean waiting rather than refusal.
- A typical session lasts about two hours, and elective courses may run to 40 or more weekday sessions, so a clear stopping rule should be agreed before starting.
- Properly controlled trials have not shown benefit for autism, most brain injury or anti-aging uses, and soft home chambers do not reach medical pressures.
Hyperbaric oxygen therapy is used for a short, specific list of recognized conditions: decompression sickness, air or gas embolism, carbon monoxide poisoning, slow-healing diabetic foot ulcers, delayed radiation injury to bone and soft tissue, certain severe infections, compromised skin grafts and flaps, crush injuries, and some cases of sudden hearing loss. Evidence for conditions outside this list is weak or absent, and the decision rests with the treating team.
The wound on his heel was the size of a quarter when he first noticed it, and six months later it was still there. Dressings changed twice a week, antibiotics twice, and the ulcer simply would not close. Then a nurse at the wound clinic mentioned a chamber, pressurized oxygen, and a course that might run for weeks. His first question was the one most people ask: is this real medicine, or something sold on late-night television?
It is both, depending on who is offering it and for what. The list of hyperbaric oxygen therapy conditions treated on solid evidence is short and well defined. It began with divers, moved to poisonings and stubborn wounds, and now includes the delayed damage that radiotherapy can leave behind years after a cancer is treated. Alongside that recognized list sits a much longer one of hopeful claims, and telling the two apart matters.
This explainer walks through what the therapy does inside the body, who the guidelines say it is for, what a course actually feels like, and where the evidence stops.
How hyperbaric oxygen therapy works, in plain language
Oxygen normally travels through the blood attached to hemoglobin, the protein inside red blood cells. At sea level, hemoglobin is already close to fully loaded, so simply breathing more oxygen does little extra for most tissues. Hyperbaric oxygen therapy changes the physics. Inside a sealed chamber, the air pressure is raised to roughly two to three times normal atmospheric pressure while the patient breathes pure oxygen, a setting described by both the Mayo Clinic and MedlinePlus.
Under that pressure, oxygen dissolves directly into the liquid part of the blood, the plasma, in amounts that are impossible at normal pressure. Plasma reaches places that red blood cells struggle to enter: tissue with damaged or narrowed small vessels, swollen limbs, bone deprived of blood supply by radiation. Think of it as the difference between a river that only carries boats and a river that has itself become the cargo.
Several things follow from that flood of dissolved oxygen. Starved tissue gets the fuel it needs to repair. Cells that build new blood vessels and collagen are stimulated. White blood cells, which rely on oxygen to kill bacteria, work more effectively. Certain bacteria that thrive without oxygen, such as the organisms behind gas gangrene, are inhibited. And in gas-related emergencies, pressure physically shrinks bubbles of nitrogen or air trapped in blood vessels, a mechanism the NHS describes in its decompression sickness guidance.
None of these effects is mysterious, and none is unlimited. Oxygen at high pressure is also a mild toxin to the lungs and nervous system if the exposure is too long, which is why sessions are timed, pressures are set by protocol, and the therapy is delivered under medical supervision rather than bought as a wellness product.
Hyperbaric oxygen therapy conditions treated: the recognized indications
Mainstream medical sources, including the Mayo Clinic, Cleveland Clinic and Johns Hopkins Medicine, describe a consistent core list of conditions for which hyperbaric oxygen is an accepted treatment. The exact wording differs slightly between countries and payers, but the substance does not.
| Condition group | Examples | Why pressurized oxygen helps |
|---|---|---|
| Gas-related emergencies | Decompression sickness, arterial gas embolism | Pressure shrinks bubbles; oxygen flushes out nitrogen |
| Poisoning | Carbon monoxide poisoning | Displaces carbon monoxide from hemoglobin faster |
| Chronic wounds | Diabetic foot ulcers that fail standard care | Raises tissue oxygen, supports new vessel growth |
| Radiation injury | Osteoradionecrosis of the jaw, radiation cystitis and proctitis | Stimulates blood vessel regrowth in scarred tissue |
| Severe infections | Gas gangrene, necrotizing soft tissue infection, refractory osteomyelitis | Inhibits anaerobic bacteria, boosts white cell killing |
| Threatened tissue | Compromised skin grafts and flaps, crush injury, compartment syndrome | Keeps borderline tissue alive while swelling settles |
| Other | Severe anemia when transfusion is not possible, sudden sensorineural hearing loss, severe burns | Dissolved oxygen substitutes for lost red cells; supports inner ear and skin |
Two features of this list deserve a second look. First, nearly every entry involves tissue that is short of oxygen for a mechanical reason: a bubble, a poison, a damaged vessel, a swollen compartment. The therapy fixes an oxygen delivery problem; it is not a general tonic. Second, in most of these conditions hyperbaric oxygen is an adjunct, added to surgery, antibiotics, wound care or blood-sugar control rather than replacing them.
That framing explains both the successes and the limits. Where the problem is oxygen delivery, the rationale is strong. Where it is not, as in most neurological and developmental conditions, the rationale is weak, and the evidence follows.
Diving injuries and carbon monoxide poisoning: the emergency uses
Hyperbaric medicine was born underwater. When a diver ascends too quickly, nitrogen dissolved in the blood and tissues forms bubbles, a condition the NHS describes as decompression sickness. Bubbles can lodge in joints, skin, the spinal cord or the brain, producing joint pain, rash, numbness, weakness or confusion. Recompression in a chamber shrinks the bubbles, and breathing pure oxygen widens the gap between nitrogen in the body and nitrogen in the lungs, so the gas leaves faster. The NHS lists recompression as the standard treatment and notes it should begin as soon as possible.
Arterial gas embolism is the close cousin: air entering an artery, whether from a lung injury during ascent or, rarely, during a medical procedure. The same logic applies, and these are the only indications in which hyperbaric oxygen is the primary treatment rather than an add-on.
Carbon monoxide poisoning is the other emergency indication. The gas binds to hemoglobin far more tightly than oxygen does, so red cells carry poison instead of fuel. The CDC reports that more than 400 people in the United States die each year from unintentional carbon monoxide poisoning not linked to fires, and more than 100,000 visit emergency departments. Oxygen at normal pressure clears the gas over hours; oxygen under pressure clears it faster and may reduce the risk of delayed memory, mood and movement problems that can surface days to weeks later.
Not every poisoned patient is sent to a chamber. Mainstream guidance reserves hyperbaric treatment for more severe exposures, for example those with loss of consciousness, heart involvement, pregnancy or very high blood carbon monoxide levels. The emergency team weighs the benefit against the delay and risk of transport. If you suspect carbon monoxide in your home, the CDC advice is simple: get everyone outside into fresh air and call emergency services.
Hyperbaric chamber for wound healing: diabetic foot ulcers and other chronic wounds
The man with the heel ulcer belongs to the largest group of people who receive hyperbaric oxygen today. Diabetes damages small blood vessels and nerves, so a minor injury to the foot may go unnoticed, heal poorly and become infected. Low oxygen in the surrounding tissue is a central reason these wounds stall. Raising tissue oxygen, even for a couple of hours a day, encourages new capillaries, collagen production and infection control.

Guidelines and major centers describe a specific candidate rather than anyone with a wound. The Cleveland Clinic and Johns Hopkins Medicine list diabetic foot ulcers that have not responded to standard care as a recognized indication. In practice that means the wound has already been offloaded, debrided, dressed appropriately and treated for infection, and blood supply has been assessed. A foot with a blocked major artery needs that artery addressed first; oxygen cannot reach tissue if the pipe is closed.
How strong is the evidence? Honest answer: moderate and contested. Several randomized trials and systematic reviews suggest more ulcers heal and fewer major amputations occur when hyperbaric oxygen is added for deeper, non-healing diabetic ulcers, but the trials are small, vary in quality and do not all agree. The Mayo Clinic frames the therapy as a treatment that may help some wounds heal, which is the right level of confidence. No percentage from any single trial should be read as a prediction for an individual foot.
Other chronic wounds appear in treatment lists less consistently. Venous leg ulcers, pressure injuries and arterial ulcers are not core indications in most guidance, and a wound team will usually say so. The daily discipline that matters most for a diabetic ulcer remains unchanged throughout a hyperbaric course: pressure off the wound, glucose under control, and regular inspection.
Radiation injury: when damage shows up months or years after cancer treatment
Radiotherapy saves lives, and it leaves a signature. The beam damages small blood vessels in the tissue it passes through, and over time that tissue can become scarred, poorly supplied and fragile. The Cleveland Clinic describes this delayed radiation injury as something that can appear months or even years after treatment has finished. A tooth extraction in a jaw that was irradiated for head and neck cancer may fail to heal and expose bone, a condition called osteoradionecrosis. The bladder lining irradiated for prostate or cervical cancer may bleed; the rectum may become inflamed and ulcerated.
These are among the clearest examples of an oxygen delivery problem. The tissue is not infected or malignant; it is starved. Hyperbaric oxygen is used to stimulate the regrowth of small vessels, a process called angiogenesis, in the scarred field. Mainstream centers list radiation cystitis, radiation proctitis and osteoradionecrosis as recognized indications, and some use it before planned surgery or dental work in irradiated tissue to improve the odds that the site will heal.
What does the evidence show? For radiation cystitis and proctitis, controlled trials and systematic reviews report improvement in bleeding and symptoms for a meaningful proportion of patients, though results vary and not everyone responds. For osteoradionecrosis of the jaw, the picture is more mixed; trials have reached different conclusions, and practice differs between centers. A hyperbaric physician should be able to describe this uncertainty plainly rather than promising repair.
Courses for radiation injury tend to be among the longer ones, because new vessel growth is slow. Mayo Clinic notes that treatment plans range from a single session to 40 or more depending on the condition. People finishing cancer care often find a daily commitment of this size emotionally heavy, and that burden is a legitimate part of the conversation with the oncology and hyperbaric teams.
Infections, grafts, crush injuries and sudden hearing loss
The remaining recognized indications share the same thread: tissue in danger because oxygen cannot reach it or because bacteria exploit its absence.
Gas gangrene is caused by Clostridium bacteria that flourish where oxygen is scarce and produce toxins that destroy muscle. Surgery to remove dead tissue and antibiotics are the foundation of treatment; hyperbaric oxygen is added because high tissue oxygen halts toxin production and inhibits the bacteria. Necrotizing soft tissue infections, the rapidly spreading infections sometimes called flesh-eating, are handled on the same principle, with the chamber supporting rather than replacing the surgeon. Chronic osteomyelitis, a bone infection that keeps returning despite antibiotics and surgery, is also on most lists.
Skin grafts and flaps are living tissue moved from one part of the body to another, and in the first days their blood supply is precarious. When a graft looks dusky or a flap edge begins to fail, hyperbaric oxygen can keep borderline tissue alive while new vessels connect. Crush injuries and compartment syndrome, in which swelling inside a muscle compartment squeezes off its own blood flow, are treated for similar reasons, usually alongside urgent surgery.
Sudden sensorineural hearing loss is an outlier on the list because the mechanism is less certain. The inner ear is metabolically demanding and poorly supplied, and the leading theory is that a brief loss of oxygen damages the hair cells. Hyperbaric oxygen is generally considered alongside steroid medicines, and mainstream guidance suggests it is most relevant when started soon after the hearing loss begins. Evidence shows some benefit in hearing thresholds in pooled trials, but quality is limited.
Severe anemia when transfusion is refused or impossible, and severe thermal burns, complete the list in most guidance. The treating team decides case by case.
Who should not do hyperbaric oxygen therapy, and who is usually asked to wait
The typical candidate is someone with one of the recognized conditions who has already received the standard treatment for it and whose body can tolerate pressure changes. The exclusions follow from the physics of a sealed, pressurized, oxygen-rich space.
An untreated collapsed lung, called a pneumothorax, is the one absolute barrier described across sources including the Mayo Clinic and Johns Hopkins. Air trapped in the chest expands as pressure falls at the end of a session and can become life-threatening. A chest X-ray is often part of the assessment for this reason.
Several other situations lead teams to pause or adjust. A cold, sinus infection or ear infection makes it hard to equalize pressure and raises the risk of eardrum injury, so sessions are often deferred until it clears. Some lung diseases that trap air, uncontrolled seizures, a high fever, and certain chemotherapy drugs that interact with high oxygen are reviewed carefully. Pregnancy is handled individually; carbon monoxide poisoning in pregnancy is actually a reason to treat, while elective use is generally avoided. Claustrophobia is manageable for many people but genuinely disabling for some, and a frank conversation before the first session matters more than bravado.
Implanted devices such as pacemakers and insulin pumps need checking against the manufacturer’s pressure rating. Anything that could spark, including some hearing aids, battery-powered items, hand warmers, and petroleum-based skin products, is removed because oxygen under pressure turns a small spark into a fire. Patients wear cotton garments supplied by the unit for the same reason.
Who is asked to wait rather than refused? Often the person whose wound has not yet had a fair trial of standard care, whose blood supply has not been assessed, or whose blood sugar is uncontrolled. Addressing those first is not a delay tactic; it is what makes the oxygen worth delivering.
What actually happens during a session, and how long can a person stay in a hyperbaric chamber?
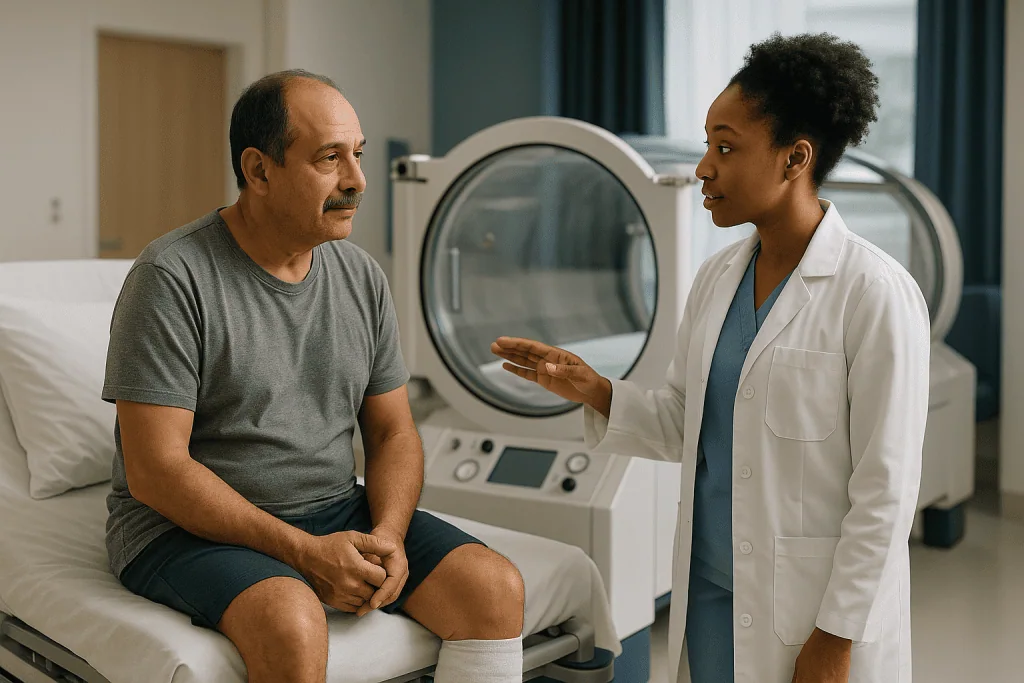
Two kinds of chamber exist. A monoplace chamber is a clear acrylic tube for one person lying down, filled with pure oxygen; the patient breathes it directly. A multiplace chamber is a room for several people, pressurized with air, in which each person breathes oxygen through a hood or mask while a trained attendant sits with them. Both achieve the same pressures. The choice depends on what the center has and how unwell the patient is.
A session begins with compression. Over several minutes the pressure rises, and ears feel exactly as they do in a descending airplane. Swallowing, yawning or gently blowing against a pinched nose equalizes them, and staff coach this at the first visit because it is the single most common source of trouble. The chamber may feel warm during compression and cool during decompression.
Once at pressure, the patient rests. People read, watch a screen through the acrylic, nap or listen to music. The Mayo Clinic and Johns Hopkins Medicine both describe a typical session as lasting about two hours including compression and decompression. Longer protocols exist for emergencies such as decompression sickness, and in a multiplace chamber the attendant may schedule short breaks breathing ordinary air to lower the risk of oxygen toxicity.
The question of how long a person can stay is really a question of safety limits, not endurance. Oxygen at high pressure irritates the lungs and, more rarely, the brain if exposure runs too long, so sessions are capped by protocol and spaced out, usually one per day on weekdays for elective indications. Nobody lives in a chamber, and longer is not better.
Decompression brings the ears back into play, this time with fullness that usually clears on its own. Blood sugar is often checked before and after in people with diabetes, because the therapy can lower glucose.
Hyperbaric oxygen therapy side effects and risks: what the evidence shows
Most people finish a course of hyperbaric oxygen with nothing worse than tired ears. Still, this is a medical procedure with real risks, and mainstream sources describe them consistently.
Middle ear barotrauma is the most common complication. Pressure changes stretch the eardrum, causing pain, fullness, fluid behind the drum or, less often, a small perforation. The Mayo Clinic lists middle ear injuries, including leaking fluid and eardrum rupture, as the leading side effect. Sinus pain follows the same mechanism. Both are far less likely when the patient equalizes early and often, and when sessions are postponed during a head cold.
Temporary nearsightedness is surprisingly frequent during longer courses. High oxygen changes the shape of the lens inside the eye, and distance vision blurs. The Mayo Clinic describes this as temporary and related to lens changes rather than permanent damage. People are generally advised not to order new glasses until some time after the course ends. Those with early cataracts may notice them progress.
Oxygen toxicity affecting the brain can cause a seizure during a session. This is rare, is managed by removing the oxygen source, and does not mean the person has epilepsy. Lung irritation from oxygen, with chest tightness or cough, is uncommon at standard protocols. Low blood sugar in people with diabetes is practical rather than dramatic, which is why glucose is checked.
The gravest risk is fire. Oxygen-enriched environments make ordinary materials burn fiercely, which is why chambers have strict rules about what enters them. The Mayo Clinic names fire as a risk precisely because it is preventable with discipline. Collapsed lung from trapped air is rare and is the reason for pre-treatment screening.
Side effects should be reported at once to the hyperbaric team, who can adjust pressure, pace or timing. Nobody should push through ear pain to finish a session.
What the following days and weeks usually look like
For emergencies, the timeline is compressed. A diver with decompression sickness or a person with carbon monoxide poisoning may have one long session or a handful over a few days, then follow-up with the emergency or neurology team to check for lingering symptoms. Delayed neurological effects after carbon monoxide can appear days to weeks after the exposure, so a return visit is usually arranged even when the person feels well.
For wounds and radiation injury, the course is a daily rhythm. The Mayo Clinic notes that plans range from a single session to 40 or more depending on the condition, which for elective indications usually means weekday visits over several weeks. Each day follows the same shape: arrive, change into cotton garments, have ears and blood sugar checked, spend about two hours in the chamber, change back, go home. People often describe fatigue in the first week that eases as the routine settles.
Wound progress is not visible day to day. The wound team measures the ulcer at intervals, looks for fresh pink granulation tissue at the base and new skin creeping in from the edges, and watches for infection. If nothing has changed after a reasonable number of sessions, most protocols call for a reassessment rather than more of the same, and that honesty is a sign of a good program.
With radiation cystitis or proctitis, bleeding and urgency may begin to ease during the course or in the weeks that follow, because new vessel growth continues after the oxygen stops. With osteoradionecrosis, the jaw surgeon and hyperbaric team coordinate the timing of any extraction or reconstruction around the sessions.
Blurred distance vision, if it developed, typically improves after the course ends. Ear fullness clears. Driving is usually unaffected unless vision has changed noticeably, and the team will advise.
What people often get wrong about hyperbaric oxygen therapy conditions treated
The myths cluster around a single misunderstanding: that more oxygen is simply good for everything.
The first error is treating the therapy as a general healing or anti-aging tonic. Healthy tissue is already well oxygenated at normal pressure; adding more does not make cells younger or sharper. Claims about reversing aging, boosting athletic performance or detoxifying the body are not supported by controlled evidence and are not among the recognized indications described by the Mayo Clinic, Cleveland Clinic or Johns Hopkins Medicine.
The second is assuming that neurological and developmental conditions respond. Autism, cerebral palsy, stroke recovery, traumatic brain injury, multiple sclerosis and post-viral fatigue syndromes are all marketed as targets. Small, uncontrolled studies and personal testimonies circulate widely. When properly controlled trials have been done, as with autism and some brain injury studies, they have generally not shown benefit over placebo-pressure sessions. Honest sources describe these uses as unproven, and families should hear that word rather than a sales pitch.
The third is believing that a soft, inflatable home or spa chamber does the same job. Those devices typically reach only a fraction of the pressure used in medical units and are usually filled with air, not oxygen, so the plasma-oxygen effect that drives the therapy barely occurs. They also carry fire and pressure risks without medical supervision.
The fourth is thinking hyperbaric oxygen replaces surgery, antibiotics or wound care. In almost every recognized indication it is added to those treatments, not swapped for them.
The fifth is the opposite error: dismissing the whole field because of the hype. For a diver with the bends, a person poisoned by carbon monoxide, or a patient with bleeding radiation cystitis, this is established, evidence-based medicine. The task is to keep the two lists separate.
Will insurance pay for a hyperbaric chamber, and what are the alternatives?
Coverage questions come up early, and the honest answer has a structure even if it has no single number. Health insurers and public programs in most countries pay for hyperbaric oxygen when two things are true: the condition is on their recognized list, and the clinical criteria for that condition have been met. For a diabetic foot ulcer, the criteria usually include depth of the wound, evidence of adequate blood supply and documentation that standard care has been tried for a defined period. For radiation injury, documentation of prior radiotherapy and the diagnosis is usually required. Emergency indications are generally covered as emergencies.
Uses outside the recognized list are, as a rule, not covered, which is one practical reason the recognized list matters. A hyperbaric unit attached to a hospital will typically check coverage before an elective course begins, and the treating physician’s documentation is what makes or breaks approval. Ask the team directly what criteria apply to your situation and how they will document them; that is a fair question, not a difficult one.
Alternatives depend entirely on the condition. For a diabetic foot ulcer, the alternatives are also the foundations: offloading footwear or casting, debridement, infection control, revascularization if an artery is blocked, and advanced dressings or negative-pressure therapy. For radiation cystitis, options include bladder irrigation, medicines instilled into the bladder, and procedures to seal bleeding vessels. For osteoradionecrosis, surgical debridement and certain medicines that improve blood flow in scarred tissue are used in some centers. For sudden hearing loss, steroid medicines given by mouth or injected through the eardrum are the main comparator.
None of these is obviously superior for every patient. The right comparison is made by the team that knows the wound, the bladder or the ear in front of them.
Questions to ask your care team before starting
A good hyperbaric unit welcomes questions, and the quality of its answers tells you a great deal. Bring these to the consultation.
- Which recognized indication am I being treated for, and what evidence supports hyperbaric oxygen in that specific situation?
- Has my standard treatment been fully optimized first? For a wound, has blood supply been assessed and infection addressed?
- How many sessions are planned, how will progress be measured, and at what point would you stop if nothing is changing?
- Which of my medicines or implanted devices need review before I enter the chamber?
- How will my blood sugar be monitored around sessions if I have diabetes?
- What should I do if I develop a cold, ear pain or sinus congestion during the course?
- Who is physically present and medically responsible during each session?
- What is the plan if I feel panicky inside the chamber?
- Which side effects should I report immediately, and who do I call?
- How does this course coordinate with my surgeon, oncologist or wound team?
Two of those deserve emphasis. The stopping rule matters because the therapy is time-consuming and a program that keeps adding sessions without reassessment is not serving the patient. And the question about who is responsible during a session separates supervised medical hyperbaric units from facilities offering soft chambers or wellness packages; in a medical unit a physician trained in hyperbaric medicine oversees the treatment and a trained attendant is present or watching throughout.
It is also reasonable to ask how the unit handles the ears. Centers that teach equalization carefully, screen for infection and slow compression for people who struggle have fewer barotrauma injuries. Write the answers down; a daily course is easier when you understand the plan you are living inside.
When to call your doctor
Most hyperbaric courses pass without incident, but certain signs need prompt attention rather than patience.
Call the hyperbaric unit or your doctor the same day if you develop sharp or persistent ear pain, fluid or blood draining from an ear, a sudden change in hearing, or sinus pain that does not settle after a session. These point to barotrauma and the team may need to examine the eardrum and adjust or pause treatment. Do the same for a head cold or fever before a session; attending while congested is how eardrums get hurt.
Report new or worsening blurred vision promptly. Some lens change is expected, but a sudden drop in vision, eye pain or seeing halos is not.
Seek emergency care immediately for chest pain, sudden breathlessness, coughing up blood, a seizure or collapse, or new weakness, numbness or confusion. Chest symptoms after a session can signal trapped air escaping into the chest and must be assessed urgently. If you are being treated for a wound and the wound becomes hot, red, swollen, foul-smelling or starts spreading, or you develop a fever and chills, contact the wound team the same day; an infection can advance quickly in a diabetic foot.
For people recovering from carbon monoxide poisoning, new headache, memory problems, mood changes or difficulty walking in the days or weeks after exposure should be reported even if the initial treatment went well, because delayed neurological effects are recognized.
If you suspect carbon monoxide in a home, move everyone into fresh air first and call emergency services, as the CDC advises. For a diver with joint pain, rash, numbness or confusion after a dive, the NHS guidance is to seek emergency help immediately and mention the diving history.
Every decision about continuing, pausing or stopping treatment belongs with your treating team. Tell them early, and they can act early.
Frequently asked questions
What conditions is hyperbaric oxygen therapy used to treat?
It is used for decompression sickness, air or gas embolism, carbon monoxide poisoning, diabetic foot ulcers that fail standard care, delayed radiation injury such as osteoradionecrosis and radiation cystitis, gas gangrene and other severe infections, refractory osteomyelitis, compromised skin grafts and flaps, crush injuries, severe anemia when transfusion is not possible, sudden sensorineural hearing loss and severe burns. Major centers such as the Mayo Clinic and Johns Hopkins describe this same core list.
What is hyperbaric oxygen therapy used for most often today?
Chronic wounds, especially diabetic foot ulcers, and delayed radiation injury account for most elective treatment in hospital hyperbaric units, because these are long courses given daily over weeks. Emergency uses such as carbon monoxide poisoning and diving injuries are fewer in number but are the indications where the therapy has the clearest and oldest evidence base.
Who should not do hyperbaric oxygen therapy?
Anyone with an untreated collapsed lung, because trapped air expands dangerously during decompression. People with a current cold, ear or sinus infection are usually asked to wait, as are those with uncontrolled fever or seizures. Certain lung diseases, some chemotherapy drugs, pregnancy for elective use, and implanted devices not rated for pressure all need individual review by the hyperbaric physician before a decision is made.
Will insurance pay for a hyperbaric chamber?
Usually yes when the condition is on the payer’s recognized list and the clinical criteria are documented, for example a diabetic ulcer of sufficient depth with adequate blood supply after standard care has been tried. Emergency indications are generally covered as emergencies. Uses outside the recognized list are typically not covered. The treating team’s documentation determines approval, so ask them what criteria apply to you.
How long can a person stay in a hyperbaric chamber?
A standard session lasts about two hours including compression and decompression, according to the Mayo Clinic and Johns Hopkins Medicine. Longer protocols exist for diving emergencies. The limit is set by oxygen toxicity to the lungs and nervous system, not by comfort, so sessions are timed by protocol and spaced out, usually one per weekday for elective conditions. Staying longer is not safer or more effective.
What are the most common hyperbaric oxygen therapy side effects?
Middle ear barotrauma is the most common, with ear pain, fullness or fluid behind the eardrum from pressure changes. Temporary nearsightedness from changes in the eye’s lens is frequent during longer courses and generally resolves after treatment ends. Rarer effects include sinus pain, low blood sugar in people with diabetes, oxygen-related seizures and lung irritation. Fire and collapsed lung are serious but preventable with screening and chamber safety rules.
Does a hyperbaric chamber for wound healing really work?
For deep diabetic foot ulcers that have not healed with standard care, randomized trials and systematic reviews suggest more wounds heal and fewer major amputations occur when hyperbaric oxygen is added, but the studies are small and not all agree. It does not help wounds with a blocked main artery until blood flow is restored, and it does not replace offloading, debridement and glucose control.
Can hyperbaric oxygen therapy help autism, stroke or long-term fatigue?
Controlled trials have generally not shown benefit for autism, and evidence for stroke recovery, traumatic brain injury, multiple sclerosis and post-viral fatigue remains unproven. These are not recognized indications in mainstream guidance. Personal testimonies and small uncontrolled studies circulate widely, but when sessions have been compared against placebo-pressure sessions, differences have been small or absent. Families should expect honest uncertainty, not promises.
Is a soft home hyperbaric chamber the same as a hospital chamber?
No. Inflatable chambers sold for home or spa use typically reach only a fraction of the pressure used in medical units and are usually filled with air rather than oxygen, so the plasma-oxygen effect that drives the therapy barely occurs. They also carry fire and pressure risks without medical supervision and are not used for any recognized indication in hospital practice.
How many hyperbaric oxygen sessions are needed?
It depends on the condition. The Mayo Clinic notes that plans range from a single session, as in some emergencies, to 40 or more for chronic wounds and radiation injury. Elective courses usually run on weekdays over several weeks. Your team should set a number, measure progress at intervals, and agree in advance when they would stop if the condition is not improving.
References
- Hyperbaric oxygen therapy, MedlinePlus Medical Encyclopedia
- Hyperbaric Oxygen Therapy, Cleveland Clinic
- About Carbon Monoxide Poisoning, CDC
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Driving After Knee or Hip Replacement: The Honest Timelines
Most people are cleared to drive about four weeks after a right knee replacement and four to six weeks after a right hip replacement,…

Dissolvable Stitches: How Long They Take, Why Some Spit, and When to Check In
Dissolvable stitches usually hold a wound together for one to eight weeks, and the body fully absorbs the material within weeks to several months,…

What to Avoid After a Stent, and When You Can Fly or Drink Again
After a coronary stent, the most important things to avoid are stopping your antiplatelet medicines without your cardiologist's say-so, smoking, heavy lifting or soaking…

Arthrofibrosis: When a Knee Gets Stiff After Surgery, and What Helps
Arthrofibrosis is an excessive buildup of internal scar tissue after joint surgery or injury, most often in the knee, that causes persistent stiffness, pain,…

Chronic Wound Care for Diabetic Foot Ulcers: Blood Sugar, Offloading and Daily Foot Checks
Diabetic foot ulcer care rests on three pillars working at once: keeping pressure off the wound (offloading), keeping blood glucose in the range your…

How to Sleep (and Live) with a Kidney Stent
Most people sleep better with a kidney (ureteral) stent by lying on the side opposite the stent or slightly propped up, emptying the bladder…