

Blood Tests, Imaging or Biopsy: How Doctors Confirm the Type of Vasculitis Before Treatment

Key Takeaways
- No single test confirms vasculitis; the type is assembled from blood and urine results, imaging of the affected vessels and, where tissue is reachable, a biopsy read alongside the clinical picture.
- ESR and CRP are usually raised in active vasculitis but are nonspecific, and they can be normal in skin-limited or early disease, so normal markers do not exclude it.
- ANCA antibodies against PR3 or MPO point toward granulomatosis with polyangiitis, microscopic polyangiitis and eosinophilic granulomatosis with polyangiitis, yet the test can be positive without vasculitis and negative with it.
- A simple urine test for blood and protein is often the first sign of silent kidney inflammation and is the finding most likely to turn a clinic-pace workup into an urgent one.
- Large-vessel vasculitis is frequently confirmed by ultrasound, CT or MR angiography or PET because the aorta cannot be biopsied, while small-vessel disease relies on antibodies, urine and tissue.
- Because inflamed vessels alternate with normal segments, a negative temporal artery or skin biopsy lowers the probability of vasculitis without ruling it out when symptoms and imaging are convincing.
Doctors confirm the type of vasculitis by combining three layers of evidence rather than relying on one test. Blood and urine tests show inflammation, antibodies such as ANCA, and whether kidneys are affected. Imaging maps which vessels are inflamed, and can be enough for large-artery disease. A biopsy of affected tissue gives the most definitive answer where it is safely reachable, and the treating team weighs all three together.
She left the clinic with three slips of paper: one for the blood draw, one for an ultrasound of the arteries at her temples, and one for a small surgical procedure she had never heard of before that morning. Nobody had said the word for certain yet. They had said possibly, and we need to be sure which kind.
That pause between suspicion and certainty is where most people first meet vasculitis biopsy and blood tests, and it is an unsettling place to be. The condition has more than a dozen named forms, they behave differently, and the treatments differ enough that guessing is not an option.
What follows is an honest walk through how clinicians actually narrow it down: what each test can show, what it cannot, why a biopsy sometimes decides the matter and sometimes is skipped, and what the weeks of waiting usually look like.
How doctors actually confirm vasculitis: a process in layers
Vasculitis is inflammation of the walls of blood vessels, which can narrow, weaken or block them and starve the tissue they supply. That single sentence hides a lot of variety. The inflammation can target the aorta, which is as wide as a garden hose, or capillaries in a kidney that are thinner than a hair. The type is named largely by the size of vessel involved and by the immune pattern behind it, and that is exactly what the diagnostic workup is trying to pin down.
No single result does the job. Clinicians build the picture in layers. The first layer is the story and the examination: which organs are complaining, how fast things changed, whether there was a recent infection or a new medicine. The second is laboratory work, blood and urine, which shows how inflamed the body is, whether particular antibodies are present, and whether the kidneys are quietly involved. The third is imaging, which maps which vessels are affected and how badly. The fourth, where it is safe and reachable, is tissue: a biopsy that lets a pathologist look at the vessel wall itself.
Running alongside all of this is a second task that patients rarely see: ruling out the mimics. Infections of the heart valves, certain cancers, drug reactions and clotting disorders can all produce fevers, rashes and organ damage that look like vasculitis. Several of the tests ordered early are there to exclude these look-alikes, which is why the list can seem longer than the question deserves.
The Mayo Clinic describes this combined approach of blood tests, urine tests, imaging and biopsy as standard. The order and emphasis change with the suspected type, and the sections below explain why.
Can vasculitis be diagnosed with blood tests? What labs are abnormal, and when they stay normal
Blood tests can strongly suggest vasculitis, point toward a type, and track its activity. On their own, they almost never confirm it. Knowing that upfront saves a lot of confusion when results arrive.
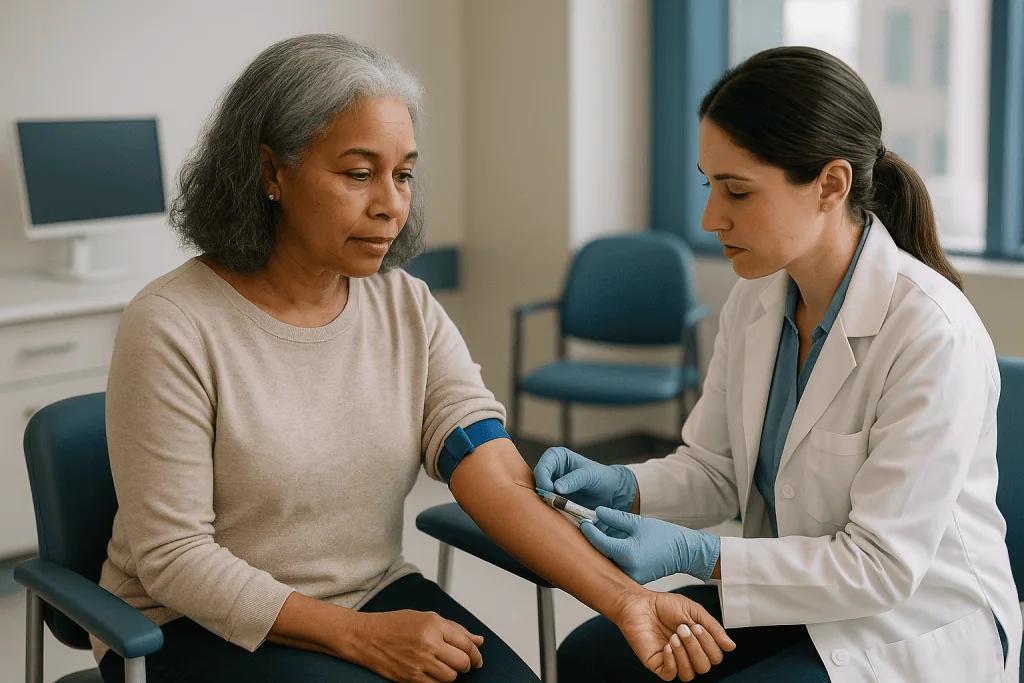
The most commonly abnormal labs are the inflammation markers. Erythrocyte sedimentation rate, or ESR, measures how quickly red cells settle in a tube over an hour; inflammation makes them clump and fall faster. C-reactive protein, or CRP, is a protein the liver releases within hours of inflammation starting. Both are usually raised in active vasculitis, but both rise with infection, injury and many other illnesses too, so they describe the fire without naming the arsonist.
A full blood count often shows anemia of chronic inflammation, a high platelet count, and sometimes a high white cell count. A marked excess of eosinophils, a type of white cell involved in allergy, is a clue toward eosinophilic granulomatosis with polyangiitis. Kidney function tests, chiefly creatinine, show whether filtering is impaired. Liver tests and muscle enzymes may be checked depending on symptoms.
Can the labs be normal? Yes, and this is the honest answer people searching for it deserve. Vasculitis limited to the skin may leave ESR and CRP unremarkable. Early disease, or disease that has partly settled by the time blood is drawn, can look reassuring on paper while an artery is still inflamed. Some people with giant cell arteritis have only modestly raised markers. A normal panel lowers suspicion; it does not close the case when the clinical picture is strong, and that is precisely when imaging and biopsy earn their place.
ANCA blood test for vasculitis, and the other antibody tests that narrow the type
ANCA stands for antineutrophil cytoplasmic antibodies: antibodies the immune system makes against proteins inside its own neutrophils, a kind of white blood cell. When these antibodies activate neutrophils, the cells damage the lining of small vessels. Two targets matter clinically. Antibodies against proteinase 3 (often reported as c-ANCA) are typical of granulomatosis with polyangiitis. Antibodies against myeloperoxidase (p-ANCA) are more typical of microscopic polyangiitis and some cases of eosinophilic granulomatosis with polyangiitis.
A positive ANCA in the right clinical setting is powerful evidence, and MedlinePlus lists the test as a core tool for these three conditions. Two cautions apply. First, ANCA can be positive in people without vasculitis, including some with inflammatory bowel disease, chronic infections or reactions to certain medicines. Second, a negative result does not rule vasculitis out; a meaningful share of people with eosinophilic granulomatosis with polyangiitis, and some with the other two types, test negative. The antibody is read alongside the organs involved, never in isolation.
Other antibody and immune tests round out the picture. Antinuclear antibodies and specific lupus antibodies are checked because lupus and rheumatoid arthritis can both cause secondary vasculitis; Mayo Clinic lists these immune system diseases among recognized triggers. Rheumatoid factor and complement proteins (C3 and C4, which are consumed when immune complexes form) help identify immune-complex disease. Cryoglobulins are antibodies that clump in the cold and clog small vessels; testing for them requires the sample to be kept warm, which is why that tube is handled differently. Hepatitis B and C serology is routine because both viruses can drive vasculitis, and treating the virus changes the plan. Anti-GBM antibodies are checked when kidneys and lungs are both affected.
Why the urine test matters more than most people expect
Of all the samples requested, the small plastic pot is the one people take least seriously, and it is often the one that changes the urgency of everything.

Small-vessel vasculitis frequently inflames the glomeruli, the microscopic filtering units of the kidney. This is called glomerulonephritis. It is usually painless. There is no flank ache, no fever, often no change in how much a person urinates, until a great deal of function has been lost. The kidney does not complain early; it simply leaks.
A urine dipstick picks up two leaks. Blood that cannot be seen with the naked eye, and protein that a healthy filter would hold back. Mayo Clinic notes that urine testing for red blood cells and protein is a standard part of the vasculitis workup for exactly this reason. When the dipstick is positive, the sample goes under a microscope. Red cells that have been squeezed through an inflamed filter look distorted, and clumps of them called red cell casts, molded in the shape of the kidney tubule, are a strong sign that the bleeding comes from the glomerulus rather than the bladder.
Blood tests add the second half of the story. Creatinine, a waste product filtered by the kidneys, rises as filtering falls, and the estimated filtration rate derived from it gives a running measure of how much function remains. A rising creatinine with active urine sediment moves a case from clinic pace to hospital pace, because kidney inflammation that is treated early can recover and kidney inflammation left for weeks may scar.
This is also the finding that most often prompts a kidney biopsy, which both confirms the type and shows how much of the damage is still reversible. Expect to be asked for urine at nearly every visit afterward; it is the cheapest early-warning system in medicine.
Imaging for vasculitis: when pictures can stand in for a biopsy
Imaging answers the question blood tests cannot: which vessels, and how far along the inflammation has gone. Its value depends enormously on vessel size.
For large arteries it is often the main confirmation. Nobody can biopsy the aorta, so for suspected Takayasu arteritis or aortic involvement in giant cell arteritis, clinicians rely on CT angiography or MR angiography, which inject contrast and map the artery’s shape and wall thickness, and sometimes PET scanning, which highlights tissue that is burning glucose at the rate inflamed tissue does. Ultrasound of the temporal and axillary arteries has become a first-line test in many centers for giant cell arteritis: an inflamed wall shows a dark ring around the flowing blood, known as the halo sign. Where that ring is clear and the clinical picture fits, some teams proceed without a biopsy.
Medium-sized vessels, the arteries supplying the gut, kidneys and nerves, are the territory of polyarteritis nodosa. Here conventional or CT angiography can show the small beaded aneurysms and narrowings that are typical, often sparing the patient a deep organ biopsy.
Small vessels are below the resolution of every scanner. Imaging cannot see capillaries inflame, but it can see the consequences: nodules or bleeding in the lungs on chest CT, destruction in the sinuses, swelling along a nerve on MRI. Mayo Clinic lists X-ray, ultrasound, CT, MRI, PET and angiography among the tools used, and the choice follows the symptoms.
Two limits are worth knowing. Imaging shows damage and wall thickening but cannot always separate active inflammation from old scarring, and it cannot tell a pathologist what kind of cells are in the wall. Those are the gaps a biopsy fills.
Vasculitis biopsy and blood tests: why tissue still carries the final word
Blood tests describe the weather in the body. A biopsy walks outside and looks at the sky. That is the simplest way to explain why, after a dozen tubes and two scans, a clinician may still ask to remove a sliver of skin, artery or kidney.
Under the microscope a pathologist can see things no blood test infers. Inflammatory cells sitting inside the vessel wall rather than merely around it. Fibrinoid necrosis, which is the wall dying and being replaced by a smeared protein deposit. Granulomas, organized clusters of immune cells that point toward granulomatosis with polyangiitis or giant cell arteritis. Giant multinucleated cells, the signature of the latter. With a technique called direct immunofluorescence, the lab can also light up immune deposits: a predominance of IgA antibody in a skin vessel, for instance, confirms IgA vasculitis in a way nothing in the blood can.
Tissue also does the exclusion work. Lymphoma, certain infections and cholesterol emboli can all imitate vasculitis on scans and labs, and each looks entirely different on a slide. For that reason guideline-level advice from Mayo Clinic and others still treats biopsy as the most definitive way to confirm the diagnosis where affected tissue can be safely sampled.
Honesty requires the caveat. Vasculitis is patchy; inflamed segments alternate with normal ones, which pathologists call skip lesions. A sample can miss the inflamed stretch, so a negative biopsy lowers probability without abolishing it. The yield is highest when the biopsy is taken from an organ that is actively symptomatic and from a lesion that is fresh rather than healing. Choosing that site, and deciding whether blood and imaging have already answered the question well enough, is a judgment the treating team makes case by case.
Temporal artery biopsy procedure: what actually happens on the day
Giant cell arteritis, sometimes called temporal arteritis, is inflammation of the large and medium arteries of the head and neck. The NHS notes it most often affects people over 50 and that it can threaten eyesight, which is why it is the one form of vasculitis in which treatment usually begins the same day it is suspected, before any biopsy result.
The biopsy itself is a minor procedure done under local anesthetic, usually as a day case. After the skin at the temple is numbed, the surgeon makes a short incision just in front of or above the ear, within or near the hairline so the scar is largely hidden. A segment of the superficial temporal artery is freed and removed; because skip lesions are common, surgeons aim for a reasonably long piece rather than a snippet. The vessel ends are tied off. The scalp has a generous blood supply from other arteries, so removing this one does not cause problems. The wound is closed with stitches and a dressing applied, and most people go home within hours.
Discomfort is usually mild: tenderness and bruising at the site, sometimes a tight sensation when chewing for a few days. Risks are uncommon but worth naming in plain terms. The wound can bleed or become infected. A small patch of scalp may feel numb. The nerve branch that lifts the eyebrow runs nearby, and rarely it is bruised, producing a temporary or occasionally lasting droop on that side.
The NHS is clear that treatment should start straight away when giant cell arteritis is suspected, and clinicians arrange the biopsy promptly rather than delaying medicine for it. Ask your team how they time the two in your case. A negative result does not by itself overturn a convincing story backed by ultrasound.
Skin, kidney, nerve and lung biopsies, and how vasculitis skin biopsy results are read
The skin is the easiest window into small-vessel disease, and the purple, non-blanching spots called palpable purpura are an invitation to look. A punch biopsy uses a small circular blade, a few millimeters across, under local anesthetic; it takes minutes and usually needs a single stitch or none. Timing matters more than people expect. A spot that appeared within the past day or two shows active inflammation; an older, fading spot may show only debris. Dermatologists often take two samples, one for routine staining and one for direct immunofluorescence.
Reading vasculitis skin biopsy results involves two questions. First, the pattern: the most common report is leukocytoclastic vasculitis, a descriptive term meaning neutrophils have swarmed the small vessel walls and fragmented, leaving nuclear dust. That pattern confirms vasculitis in the skin but does not name the cause; it can accompany drugs, infections, IgA vasculitis, ANCA disease or cryoglobulins. Second, the deposits: IgA dominance points to IgA vasculitis, mixed immunoglobulins and complement suggest an immune-complex process, and a sparse or absent deposit pattern is more typical of ANCA-associated disease. The report is then matched to the blood tests and the organs involved.
Kidney biopsy is done with a needle through the back under ultrasound guidance and local anesthetic. The main risk is bleeding, so people lie flat for a period afterward and are monitored; the sample shows both the type of inflammation and how much scarring has already set in, which guides how aggressive treatment needs to be.
Nerve and muscle biopsies are considered when a person develops sudden weakness or numbness in one limb after another, a pattern called mononeuritis multiplex. Lung tissue can be reached by bronchoscopy or, when nodules sit deep, by a surgical approach. Each site carries its own risks, and each is chosen only when less invasive evidence has run out.
Vasculitis biopsy and blood tests by vessel size: a comparison table
Grouping the main forms by vessel size shows why two people with the same word on their referral letter can have entirely different test lists. The table summarizes the typical pattern; individual cases vary and the team adapts to symptoms.
| Vessel size and examples | Blood and urine tests that matter most | Imaging usually used | Biopsy, if needed |
|---|---|---|---|
| Large: giant cell arteritis, Takayasu arteritis | ESR, CRP, full blood count | Temporal and axillary ultrasound, CT or MR angiography, PET | Temporal artery |
| Medium: polyarteritis nodosa, Kawasaki disease | Inflammation markers, hepatitis B serology, kidney function | Angiography of gut and kidney arteries; echocardiography in Kawasaki | Skin, nerve or muscle; rarely needed in Kawasaki |
| Small, ANCA-associated: GPA, MPA, EGPA | ANCA (PR3 and MPO), urine dipstick and microscopy, creatinine, eosinophil count | Chest CT, sinus imaging | Kidney, skin, nasal or lung tissue |
| Small, immune complex: IgA vasculitis, cryoglobulinemic vasculitis, anti-GBM disease | Complement, cryoglobulins, hepatitis C serology, anti-GBM, urine | Chest imaging when lungs involved | Skin with immunofluorescence, kidney |
Two patterns stand out. The larger the vessel, the more the diagnosis leans on imaging, because the tissue is out of reach. The smaller the vessel, the more it leans on antibodies, urine and biopsy, because scanners cannot see the problem directly.
Kawasaki disease, which the NHS notes mainly affects children under 5, is a reminder that some diagnoses rest on clinical criteria: a pattern of fever, rash and other signs, supported by heart ultrasound rather than any single confirmatory test. Children with typical IgA vasculitis are often diagnosed the same way. The table is a map of the usual routes, not a checklist every patient must complete.
Who is usually offered a biopsy, and who is asked to wait or skip it
The decision to take tissue comes down to one question: will the answer change what happens next, and is the risk of getting it proportionate?
A biopsy is usually favored when the type of vasculitis remains genuinely uncertain after blood tests and imaging, when the proposed treatment is strong enough that the team wants to be sure, when a mimic such as infection or lymphoma is realistically on the list, and when affected tissue sits somewhere accessible. Skin lesions, a tender temporal artery, an inflamed kidney and a nasal crust in someone with suspected granulomatosis with polyangiitis all meet that last test. Kidney biopsy earns an extra argument: it shows how much scarring exists, which informs how hard to treat and how much function is likely to be recoverable.
People are commonly asked to wait, or the biopsy is skipped altogether, in several situations. Large-vessel disease with clear angiography or ultrasound findings may not need tissue at all. Children with classic IgA vasculitis or Kawasaki disease are usually diagnosed on clinical grounds. Someone who is very unwell, with lungs bleeding or kidneys failing fast, is treated first on the strength of ANCA, urine and imaging; the biopsy, if still useful, follows once they are stable. Significant bleeding risk, whether from anticoagulant medicines or low platelets, can shift the balance against a kidney or lung biopsy.
Starting treatment before a biopsy is not the compromise it sounds like. In giant cell arteritis the NHS advises beginning medicine as soon as the condition is suspected to protect eyesight, with the biopsy arranged promptly afterward. For sampled skin and kidney, teams aim to take tissue early because treatment gradually erases the features a pathologist needs. These are judgment calls, and the treating team makes them with the whole picture in front of them.
What the days and weeks after testing usually look like
The workup rarely ends on a single afternoon, and the pace depends on how threatened any organ is.
After a skin or temporal artery biopsy, the practical side is ordinary wound care: keep the dressing dry as instructed, expect bruising, avoid heavy exertion for a few days, and return for stitch removal if the stitches are not dissolvable. After a kidney biopsy there is a period of lying flat and observation for bleeding, then a short stretch of avoiding heavy lifting; your team will give you the specific interval they use. Blood in the urine for a day or so afterward is common and should be reported if it persists or worsens.
Pathology takes time, and immunofluorescence and special stains take longer than routine slides. Ask at the outset how results will reach you and whether a results appointment is already booked. Clinicians often use that visit to assemble everything: labs, scans, tissue and the clinical course since the first appointment, which sometimes clarifies things more than any test did.
Where treatment has already begun, the first weeks are also about monitoring. Glucocorticoids, the corticosteroid medicines usually used first, work by broadly suppressing the immune response and can calm inflammation within days; they also raise blood sugar and blood pressure and affect sleep and mood, so expect repeat blood tests and checks. Other immune-modulating medicines are often added so the steroid can be reduced over time, and the choice depends heavily on the confirmed type, which is the whole point of the diagnostic effort. All of these decisions, including how fast anything changes, belong to the prescribing team.
Expect the urine pot at every visit, and expect ESR and CRP to be rechecked as a running gauge of how settled the inflammation is.
What people often get wrong about vasculitis testing
Some misunderstandings cause real distress, and a few lead people to argue with a workup that is actually sound.
A positive ANCA means I have vasculitis. It raises the probability substantially in the right context, but ANCA can appear with inflammatory bowel disease, long-standing infections and certain medicines. Clinicians read it alongside organs, urine and sometimes tissue.
My inflammation markers are normal, so it cannot be vasculitis. Skin-limited disease and early or partly settled disease can leave ESR and CRP unremarkable. A normal result lowers suspicion; it does not end the conversation when the story is convincing.
Everyone needs a biopsy. Large-vessel disease is frequently confirmed by imaging, and several childhood forms are diagnosed on clinical criteria. Tissue is taken when it will change the plan and can be obtained safely.
A negative biopsy means I am fine. Vasculitis skips segments. A sample can miss the inflamed stretch, which is why a negative temporal artery biopsy in someone with typical symptoms and a positive ultrasound does not settle the question on its own.
Blood tests alone can tell the type. They can suggest it. The type is a synthesis of vessel size, antibody pattern, organs involved and, often, what the pathologist sees.
Starting steroids before the biopsy ruins everything. It gradually blurs the picture, which is why teams move quickly, but in giant cell arteritis protecting eyesight comes first and useful findings often persist for a time.
Vasculitis is one disease, and it is contagious or self-inflicted. It is a family of conditions, none of which can be passed to another person. Some are triggered by infections or medicines, most arise from an immune system misfire nobody chose.
The diagnosis is automatically a catastrophe. Seriousness varies enormously by type and organ involvement, and the testing exists precisely so treatment can be matched to the actual risk.
Questions to ask your care team
A long test list is easier to tolerate when you understand what each piece is for. These questions are the ones clinicians are generally glad to be asked, because they make the next steps clearer for everyone.
- Which type of vasculitis do you suspect, and which vessel size does that involve?
- Which of my blood test results pointed you in that direction, and which were reassuring?
- Is my urine showing blood or protein, and if so, what does that mean for my kidneys right now?
- Was my ANCA test positive or negative, and how much weight are you placing on it?
- Will imaging alone be enough to confirm this, or do you expect to need a biopsy?
- If a biopsy is planned, which tissue will you sample, why that site, and what are the specific risks for me?
- What would a negative biopsy result change, and what would it not change?
- Are we treating now and confirming afterward, or waiting for results first, and why?
- What conditions are you ruling out alongside vasculitis, such as infection or other autoimmune disease?
- Which symptoms should make me call you the same day while we are waiting?
- How and when will I get my results, and who do I contact if I have not heard?
- Which specialists will be involved, and who is coordinating the overall plan?
Writing the answers down, or bringing someone who can, is worth doing. Vasculitis workups move across several departments, and the person who holds the whole picture in their head is, ideally, you as much as any one clinician. If something is unclear, say so; the type names are genuinely confusing, and asking for the plain-language version is a reasonable request at any stage.
When to call your doctor: red-flag signs during and after the workup
Diagnosis can take weeks, and vasculitis does not always wait politely. Some symptoms mean the process needs to speed up, and a few mean emergency care now. Treat this as guidance on urgency, not as a tool for diagnosing yourself.
Call emergency services or go to the nearest emergency department for any of the following: sudden loss or blurring of vision in one or both eyes, double vision, or a curtain across the sight; signs of stroke such as facial droop, weakness on one side, or slurred speech; coughing up blood, severe or rapidly worsening breathlessness, or chest pain; severe abdominal pain, especially with vomiting or blood in the stool; and new, severe headache unlike any before, particularly with scalp tenderness or pain in the jaw when chewing in someone over 50, which the NHS lists among the warning features of giant cell arteritis.
Contact your care team the same day for: visible blood in the urine, a sharp fall in how much urine you pass, or sudden swelling of the legs or face; new numbness, tingling or weakness in a hand or foot, especially one limb after another; a rapidly spreading rash of purple spots that do not fade when pressed; fever with no clear cause; and any new symptom that your team told you to watch for.
After a biopsy, call if the wound bleeds through the dressing or keeps bleeding after firm pressure, becomes increasingly red, hot or discharging, or if you develop fever. After a kidney biopsy, report persistent or increasing blood in the urine, dizziness, or pain in the back or abdomen that is getting worse rather than better.
None of this means waiting it out. Vasculitis treated early tends to leave less permanent damage than vasculitis treated late, and the people who know your case want to hear from you.
Frequently asked questions
What labs are abnormal with vasculitis?
The most consistently abnormal labs are the inflammation markers ESR and CRP, which are usually raised when vasculitis is active. A full blood count often shows anemia and high platelets, and raised eosinophils suggest one specific type. Creatinine rises if kidneys are involved, urine may contain blood and protein, and antibody tests such as ANCA, ANA, complement and cryoglobulins help point to the type.
Can you have vasculitis with normal blood tests?
Yes. Vasculitis confined to the skin can leave ESR and CRP normal, and early or partly settled disease may look unremarkable on paper while an artery remains inflamed. Some people with giant cell arteritis have only modest rises in markers. Normal results lower suspicion, but when symptoms are convincing clinicians move on to imaging and biopsy rather than stopping at the blood work.
What autoimmune disease is linked to vasculitis?
Several. Lupus, rheumatoid arthritis and scleroderma can all cause secondary vasculitis, which is why antinuclear antibodies and rheumatoid factor are checked in the workup. Inflammatory bowel disease is associated with positive ANCA and occasionally vasculitis. Separately, the ANCA-associated vasculitides are themselves autoimmune diseases, and hepatitis B and C infections can trigger immune-complex forms, so viral serology is routine.
How serious is a vasculitis diagnosis?
It varies widely by type and by which organs are involved. Skin-limited disease may settle with little intervention, while vasculitis affecting kidneys, lungs, nerves or the arteries supplying the eyes can cause permanent damage if treatment is delayed. The purpose of the detailed workup is to match treatment intensity to the actual risk, and most forms can be controlled with current approaches when found early.
Is the ANCA blood test for vasculitis definitive on its own?
No. A positive ANCA with matching symptoms, active urine sediment and organ involvement is strong evidence for granulomatosis with polyangiitis or microscopic polyangiitis, but ANCA can also appear with inflammatory bowel disease, chronic infections and certain medicines. A negative result does not exclude vasculitis, particularly the eosinophilic type. Clinicians interpret it alongside imaging and, often, a biopsy.
What does the temporal artery biopsy procedure feel like?
It is done under local anesthetic as a day case, so the main sensation is pressure rather than pain during the procedure. Afterward people typically describe tenderness and bruising at the temple and sometimes a tight feeling when chewing for a few days. Risks are uncommon and include wound bleeding or infection, a numb patch of scalp, and rarely a weakened eyebrow lift on that side.
How are vasculitis skin biopsy results reported?
The report usually describes the pattern first, most often leukocytoclastic vasculitis, meaning neutrophils have infiltrated and fragmented within small vessel walls. That confirms vasculitis in the skin but not the cause. A second part, direct immunofluorescence, describes immune deposits: IgA dominance indicates IgA vasculitis, while sparse deposits fit ANCA-associated disease. Your team combines the report with blood tests and symptoms to name the type.
Will starting steroids before a biopsy ruin the result?
Treatment gradually blurs the features a pathologist needs, which is why teams arrange biopsies promptly, but it does not instantly erase them. In suspected giant cell arteritis the NHS advises starting medicine straight away to protect eyesight, with the biopsy following soon after. Your team balances the urgency of treatment against the value of tissue; never delay prescribed medicine to protect a test.
Can imaging replace a biopsy for vasculitis?
Often for large vessels, rarely for small ones. CT or MR angiography, PET and temporal artery ultrasound can confirm giant cell arteritis or Takayasu arteritis because the aorta and its branches cannot be sampled. Capillaries and small arterioles are below scanner resolution, so small-vessel disease usually still relies on antibodies, urine findings and a biopsy of skin, kidney or another affected organ.
Why does my doctor keep asking for urine samples?
Because kidney inflammation in vasculitis is usually painless and the urine shows it before you feel anything. Blood and protein on a dipstick, and red cell casts under the microscope, signal that the kidney’s filtering units are inflamed. Repeating the test at each visit lets the team catch new or returning kidney involvement early, when treatment is most likely to preserve function.
References
- NHS: Vasculitis
- NHS: Temporal arteritis (giant cell arteritis)
- MedlinePlus: Erythrocyte Sedimentation Rate (ESR)
- Cleveland Clinic: Vasculitis
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
What Scleroderma Treatment Can and Cannot Change: Setting Realistic Expectations
Scleroderma treatment can control many of the condition's effects, including Raynaud's attacks, reflux, joint stiffness and, in many people, the pace of skin thickening…

Gentle Exercise and Physical Therapy in Reactive Arthritis: Restoring Mobility Safely
Physical therapy for reactive arthritis usually begins with gentle range-of-motion movements to keep inflamed joints from stiffening, then adds low-load strengthening and walking or…

When Hardening Skin or Reflux Warrants a Scleroderma Evaluation by a Rheumatologist
See a rheumatologist for scleroderma when symptoms cluster rather than appear alone: fingers that turn white or blue in the cold together with puffy…

When Does Big Toe Pain Call for a Gout Assessment by a Specialist?
Big toe pain usually warrants a gout assessment when the joint becomes hot, swollen and intensely painful within hours, when it is your first…

Is Ankylosing Spondylitis Only a Young Man’s Disease? Myths That Delay Treatment
Ankylosing spondylitis is not only a young man's disease. It most often begins between the late teens and early thirties and is diagnosed more…

Physical Therapy for Psoriatic Arthritis: Keeping Strength and Flexibility Between Flares
Physical therapy for psoriatic arthritis uses individually prescribed strengthening, range-of-motion, aerobic and posture work to protect joints, tendons and muscles between flares, while teaching…