

Diagnosing HUS: Blood Counts, Kidney Function and Stool Testing for the Infection Behind It

Key Takeaways
- HUS is diagnosed from three findings read together: fragmented red cells with signs of hemolysis, a low platelet count, and acute kidney injury shown by rising creatinine and abnormal urine.
- The CDC estimates that 5 to 10 percent of people diagnosed with STEC O157 infection develop HUS, typically about seven days after diarrhea starts, often as it improves.
- A stool sample collected as early as possible, tested by both culture and Shiga toxin or PCR, has the best chance of identifying the E. coli behind typical HUS; a negative test does not exclude it.
- ADAMTS13 activity distinguishes HUS from thrombotic thrombocytopenic purpura, which looks identical on a blood smear but has a different cause and treatment.
- Atypical HUS accounts for roughly 10 percent of cases, and MedlinePlus Genetics notes that many people with it have normal blood complement levels, so the diagnosis often rests on excluding other causes.
- Kidney recovery lags behind platelet recovery, and long-term follow-up of blood pressure, urine protein and creatinine is standard because late kidney effects can appear months or years later.
HUS diagnosis tests center on three findings that appear together: a complete blood count and blood smear showing red cells being destroyed and a low platelet count, kidney function tests such as creatinine and urinalysis showing acute kidney injury, and a stool test for Shiga toxin-producing E. coli. When no infection is found, clinicians add ADAMTS13 activity and complement studies to rule out TTP and evaluate atypical HUS.
The pediatric ward is quiet at 2 a.m. except for a father pacing the corridor with a phone in his hand. Four days ago his daughter had stomach cramps and diarrhea that turned bloody. Tonight she is pale, puffy around the eyes, and has barely wet a diaper since lunch. A nurse has just drawn what feels like an alarming number of blood tubes from a very small arm, and someone has asked him, gently, to save the next dirty diaper.
He does not yet know the phrase hemolytic uremic syndrome. He does know that everyone moved faster after the word “platelets” was spoken at the bedside. What he is watching is the start of the hus diagnosis tests that turn a frightening cluster of symptoms into a name, a mechanism and a plan.
This article walks through that workup the way a clinician thinks about it: what each tube and sample is for, what the numbers mean, and where the honest uncertainties lie.
What HUS is, and why the diagnosis rests on three findings
Hemolytic uremic syndrome, usually shortened to HUS, is a condition in which tiny blood clots form inside small blood vessels, especially those of the kidney. The name is a compressed description of what the laboratory finds. “Hemolytic” means red blood cells are being broken apart; “uremic” refers to waste products building up because the kidneys have stopped filtering properly; “syndrome” signals a recognizable pattern rather than a single test.
The mechanism explains the pattern. Something injures the lining of small vessels, most often a toxin released by certain strains of the bacterium Escherichia coli. Damaged vessel walls trigger clotting. Platelets, the cell fragments that plug leaks, are consumed in those clots, so the platelet count falls. Red blood cells squeezing past strands of clot are physically sheared, so they burst, and the fragments show up on a blood smear. The kidney, with its dense network of filtering capillaries, is the organ most starved of flow, so kidney function drops.
That is why the diagnosis rests on a triad rather than one number: evidence of red cell destruction, a low platelet count, and acute kidney injury. According to the NIH’s National Institute of Diabetes and Digestive and Kidney Diseases, HUS is one of the most common causes of sudden kidney failure in children, and it most often follows an intestinal infection. Adults can develop it too, though less commonly.
Two broad forms exist. The typical or infection-associated form follows Shiga toxin-producing E. coli, often called STEC, and accounts for the large majority of childhood cases. The atypical form, aHUS, arises without that infection, usually because of an overactive part of the immune system called complement. MedlinePlus Genetics notes that atypical HUS makes up roughly 10 percent of all HUS. Telling the two apart is the second half of the diagnostic story, and it matters because their treatment paths diverge.
What HUS diagnosis tests actually involve on the first day
For the person in the bed, the first hours are a blur of blood draws, a urine collection and a request for a stool sample. It helps to know that almost everything can be started from a single venous blood draw, with the tubes split among different laboratory machines, plus one urine sample and one stool specimen.
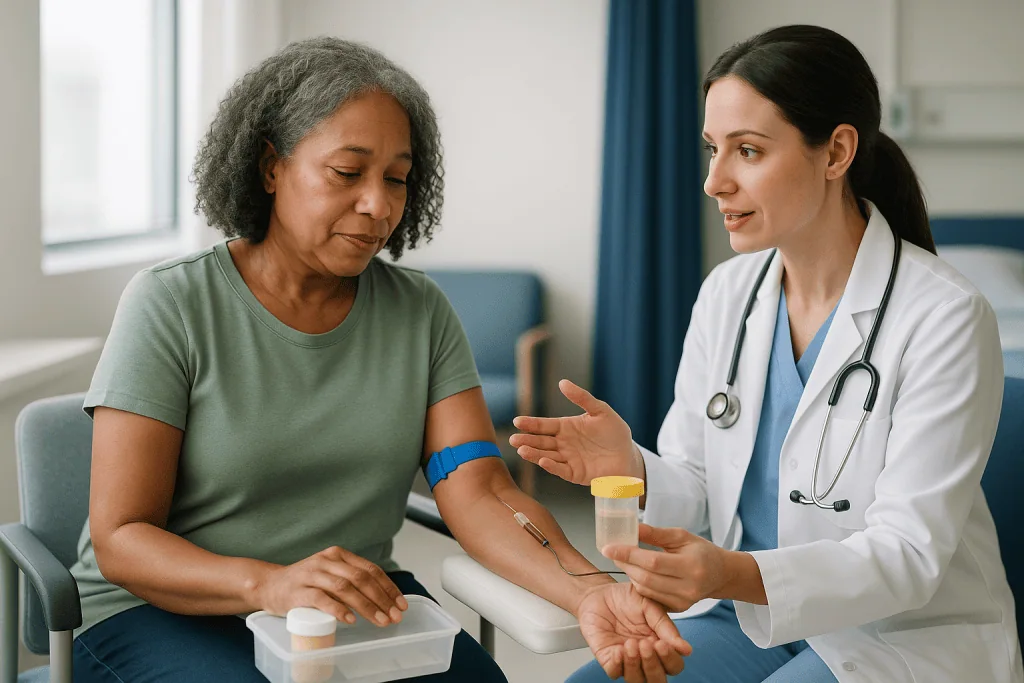
Clinicians start with a complete blood count, or CBC, an automated tally of red cells, white cells and platelets. They add a peripheral blood smear, in which a drop of blood is spread on a glass slide and examined under a microscope for fragmented red cells called schistocytes. A metabolic panel measures creatinine and urea, both waste products that rise when the kidneys are not clearing them, along with sodium, potassium and bicarbonate.
Several markers of red cell destruction are sent at the same time. Lactate dehydrogenase, or LDH, is an enzyme released when cells break; haptoglobin is a protein that mops up freed hemoglobin and is used up when hemolysis is brisk; bilirubin rises as broken-down hemoglobin is processed; a reticulocyte count shows whether the bone marrow is racing to replace lost cells. A Coombs test, also called a direct antiglobulin test, checks whether antibodies are attacking the red cells, which would point away from HUS toward an immune cause.
Urinalysis looks for blood and protein leaking through injured kidney filters. Stool goes to microbiology for culture and toxin testing. In many units, ADAMTS13 activity and complement studies are drawn on that same first day, even before results are back, so that no one has to wait days for a second sample if the picture turns out to be more complex.
Nothing about this panel is exotic. What makes hus diagnosis tests distinctive is the speed and the way results are read together rather than one at a time.
What tests diagnose hemolytic anemia in HUS, and how to read them
Anemia simply means too few red blood cells or too little hemoglobin to carry oxygen comfortably. Hemolytic anemia is the subtype in which the shortage arises because cells are being destroyed faster than the marrow can replace them. In HUS, the destruction is mechanical, and the laboratory pattern reflects that.
Hemoglobin falls, sometimes over just a day or two. LDH climbs because ruptured cells spill the enzyme into plasma. Haptoglobin drops, often to undetectable levels, as it binds free hemoglobin and is cleared. Indirect bilirubin rises as the liver processes the pigment from broken cells. The reticulocyte count rises as the marrow responds. Each of these alone has other explanations; together, they say hemolysis with reasonable confidence.
The smear supplies the crucial detail. Schistocytes, red cells sliced into helmet or triangle shapes, indicate that cells are being torn as they pass through clots in small vessels. Their presence defines a group of conditions called thrombotic microangiopathies, or TMAs, of which HUS and thrombotic thrombocytopenic purpura are the two best known. A negative Coombs test confirms that antibodies are not the culprit.
Platelets complete the picture. Thrombocytopenia, a platelet count below the normal range, results from platelets being consumed in microclots. The Mayo Clinic describes low platelets, anemia and kidney injury as the defining features clinicians look for when they suspect HUS.
One caution belongs here. The severity of anemia and the platelet count do not track neatly with how sick a person is or how the kidney will fare. A modestly low platelet count can accompany severe kidney injury, and vice versa. Hematology results answer the question “is a thrombotic microangiopathy present?” They do not, by themselves, predict what happens next.
How kidney function is measured when HUS is suspected
The “uremic” part of the syndrome is assessed with a handful of tests that most people have had at a routine checkup, interpreted here with a very different level of urgency.

Serum creatinine is the workhorse. Creatinine is a waste product of normal muscle turnover, and healthy kidneys clear it steadily; when filtration drops, it accumulates. Because children have less muscle, a creatinine that would look unremarkable in an adult can represent serious injury in a toddler, so laboratories and clinicians interpret it against age-specific norms. Blood urea, sometimes reported as BUN, rises in parallel. From creatinine, age and body size, an estimated glomerular filtration rate, or eGFR, can be calculated to express how much filtering capacity remains.
Electrolytes matter just as much. Potassium can climb dangerously when the kidneys cannot excrete it, which is why repeated blood draws are common in the first days. Bicarbonate falls as acid accumulates. Sodium and fluid balance are tracked closely because both dehydration from diarrhea and fluid overload from failing kidneys are real risks, often in the same patient within the same week.
Urine tells its own story. Urinalysis often shows blood and protein, evidence that the delicate filtering membranes have been damaged. Urine output is measured, sometimes to the milliliter, because a falling output is one of the earliest bedside signs that filtration is stalling. Cleveland Clinic lists reduced urination, swelling and high blood pressure among the signs that accompany the kidney injury of HUS.
Blood pressure is checked frequently. Injured kidneys retain salt and water and release hormones that raise pressure, and hypertension in a child who has never had it is a meaningful clue.
The care team uses these numbers together to decide whether the kidneys need temporary support with dialysis. That decision, like every treatment decision in HUS, rests with the clinicians at the bedside who can see the trend, not any single value.
Stool test for E. coli: finding the infection behind it
In the infection-associated form, the trigger is Shiga toxin, a poison produced by certain E. coli strains, most famously O157:H7 but also many non-O157 types. The CDC estimates that roughly 5 to 10 percent of people diagnosed with STEC O157 infection go on to develop HUS, typically about seven days after the diarrhea begins, often just as the intestinal symptoms are improving.
That timing is why a stool sample is requested so early and so insistently. The bacteria and their toxin are most detectable during and shortly after the diarrheal phase. By the time kidney injury is obvious, the organism may already be fading from the gut, so a sample collected on day one of admission has a better chance of catching it than one collected three days later.
Laboratories use a combination of approaches. Stool culture on selective media can grow E. coli O157, which behaves differently from harmless gut E. coli on certain agar plates. Because many non-O157 strains look identical to normal flora on culture, most laboratories also run an assay for Shiga toxin itself or a molecular test, a PCR, that detects the genes encoding the toxin. The CDC advises that stool from anyone with suspected STEC be tested both by culture and by a toxin or gene-based method so that non-O157 infections are not missed.
A positive result confirms the infection-associated form and has public health consequences: STEC is reportable, and local health departments may look for a shared food source or contacts at risk. A negative result does not exclude it, particularly if the sample was collected late. Clinicians weigh the history of bloody diarrhea heavily even when the laboratory cannot recover the organism.
Families sometimes feel that the stool request is an afterthought compared with the blood tests. In truth, it is the single test most likely to explain why this happened at all.
The HUS diagnostic panel at a glance
Seeing the tests side by side clarifies why so many tubes are drawn. Each row answers a different question, and the diagnosis emerges from the whole column rather than any one line. Normal ranges vary by age and laboratory, so the direction of change matters more than the exact figure.
| Test | What it measures | Usual finding in HUS | Question it answers |
|---|---|---|---|
| Complete blood count | Hemoglobin, platelets, white cells | Low hemoglobin, low platelets | Is there anemia with platelet consumption? |
| Peripheral blood smear | Shape of red cells under microscope | Fragmented cells (schistocytes) | Is destruction mechanical, inside small vessels? |
| LDH, haptoglobin, bilirubin, reticulocytes | Markers of red cell breakdown and marrow response | LDH and bilirubin high, haptoglobin low, reticulocytes high | Is hemolysis active? |
| Direct antiglobulin (Coombs) test | Antibodies on red cells | Negative | Is an immune attack the cause instead? |
| Creatinine, urea, eGFR | Kidney filtering capacity | Creatinine and urea rising | How much kidney injury is present? |
| Electrolytes | Potassium, sodium, bicarbonate | Potassium may rise, bicarbonate may fall | Is there immediate danger needing correction? |
| Urinalysis and urine output | Blood, protein, volume | Blood and protein present, output falling | Are the kidney filters damaged and functioning? |
| Stool culture, Shiga toxin or PCR | STEC bacteria or toxin genes | Positive in infection-associated HUS | What triggered this? |
| ADAMTS13 activity | Enzyme that trims clotting protein | Not severely reduced in HUS | Is this TTP rather than HUS? |
| Complement studies (C3, C4, factor H and others) | Immune proteins and regulators | May be abnormal in atypical HUS | Is complement dysregulation driving it? |
Two features of this table deserve emphasis. First, the top half establishes that a thrombotic microangiopathy exists, while the bottom half sorts out which one. Second, several tests are sent before anyone knows whether they will be needed, because waiting for results to arrive in sequence could cost days in a condition where days matter.
HUS vs TTP: why ADAMTS13 testing is part of the workup
Thrombotic thrombocytopenic purpura, or TTP, is the condition most easily confused with HUS. Both produce fragmented red cells, low platelets and organ injury from microclots. The distinction is not academic: the treatments differ substantially, and TTP can deteriorate quickly without its specific therapy.
The biology explains the test. ADAMTS13 is an enzyme that trims a large clotting protein called von Willebrand factor into manageable pieces. In TTP, the enzyme is missing or blocked, usually by an antibody the immune system has mistakenly produced. Uncut von Willebrand factor forms long, sticky strands that snag platelets throughout the body. In HUS, the enzyme works normally; the clots come from vessel wall injury instead.
Measuring ADAMTS13 activity therefore separates the two. Severely reduced activity points to TTP; preserved or only modestly reduced activity supports HUS or another TMA. Because the assay is specialized and may be run at a reference laboratory, results can take several days. Clinicians often draw the sample early and begin treatment decisions on clinical grounds while it is pending, then adjust once the result arrives.
Clinical clues help in the meantime. TTP is more common in adults and tends to produce more neurological symptoms with less severe kidney injury, whereas HUS is dominated by kidney failure, especially in children after diarrhea. The overlap is large enough, however, that guidelines from hematology and nephrology societies consistently recommend testing rather than guessing.
For a patient or parent hearing both acronyms, the practical translation is this: the team is checking whether the small-vessel clotting is caused by a missing enzyme or by damaged vessel walls, because the answer changes the plan. A period of uncertainty while the result returns is normal and does not mean the team is unsure what to do in the meantime.
Atypical HUS diagnosis: complement, genetics and ruling out lookalikes
When someone has the full HUS picture but no bloody diarrhea, a negative stool test, and preserved ADAMTS13 activity, attention turns to the atypical form. Atypical HUS, or aHUS, is driven by complement, a cascade of blood proteins that normally helps destroy microbes. In aHUS the cascade runs unchecked and injures the body’s own vessel linings, particularly in the kidney.
Complement testing measures components such as C3 and C4 and regulators such as factor H and factor I. Low C3 with normal C4 suggests overactivation of a particular arm of the pathway, but MedlinePlus Genetics notes that many people with aHUS have normal complement levels in the blood, so a normal result does not exclude the diagnosis. Antibodies against factor H, which block a key brake on the system, are checked as well.
Genetic testing looks for variants in genes that encode complement proteins and their regulators. MedlinePlus Genetics describes changes in several such genes, with the CFH gene the most frequently affected, and explains that many people who carry a variant never develop disease unless a trigger such as infection, pregnancy or certain medicines tips the balance. A meaningful proportion of people with clinical aHUS have no identifiable variant at all. Genetic results usually take weeks and inform prognosis, relapse risk and family counseling more than the first days of care.
Equally important is excluding other causes of the same laboratory pattern. Severe hypertension, certain infections including pneumococcal disease, some cancers and chemotherapy agents, autoimmune conditions such as lupus, organ transplantation and complications of pregnancy can all produce a thrombotic microangiopathy. Clinicians work through these with history, targeted blood tests and sometimes imaging.
Atypical hus diagnosis is therefore partly a process of elimination and partly a positive search for complement abnormalities. It is a diagnosis the team builds over days to weeks, and early treatment decisions are made on the clinical picture while confirmatory results are pending.
Who is tested urgently, and who is usually watched instead
Not everyone with diarrhea needs the full panel, and not everyone with a low platelet count has HUS. The workup is aimed at people in whom the combination of findings, or the risk of developing them, is high.
Urgent testing is standard for anyone with bloody diarrhea who develops pallor, unusual tiredness, reduced urination, swelling, bruising or petechiae (tiny red spots from bleeding under the skin), or confusion. Children under five with a confirmed or suspected STEC infection fall into a closely monitored group even before those signs appear, because the Mayo Clinic identifies this age group as the one in which HUS most often develops. Older adults and people with weakened immunity are also watched carefully.
People with a confirmed STEC infection but no laboratory signs of HUS are commonly managed with repeated blood counts and kidney tests over the roughly one to two weeks during which HUS can emerge, rather than with the complete TMA panel. This is the group most often told that the plan is to “wait and recheck.” The waiting is not neglect; it reflects the fact that HUS can only be diagnosed once its laboratory features appear, and hydration and observation are the mainstays in the meantime.
Anyone with a thrombotic microangiopathy but no diarrheal history moves quickly to the extended workup for TTP, atypical HUS and secondary causes, because these conditions can worsen fast and their treatments are time-sensitive.
Special situations prompt specific attention. Pregnancy and the weeks after delivery are recognized triggers for aHUS and for other conditions that mimic it, so a new mother with anemia, low platelets and rising creatinine is evaluated with particular urgency. People who have had a kidney transplant, are receiving certain cancer therapies or have autoimmune disease are similarly flagged. The decision about how far and how fast to test always sits with the treating team, who can see the trajectory that a single snapshot cannot show.
How the testing pathway looks for a child, and how families can help
Because most infection-associated HUS occurs in young children, much of this workup happens in pediatric settings, and the practical experience deserves its own description.
Blood sampling is the part children fear most. Pediatric teams commonly use a small indwelling cannula so that repeated samples can be drawn without repeated needle sticks, and topical numbing preparations and distraction techniques are routine. Parents are usually welcome to hold or comfort the child during draws, and asking what comfort measures are available is entirely reasonable. Frequent sampling in the first days is expected; each draw is checking whether potassium, creatinine and platelet counts are stable or shifting.
Urine collection can be surprisingly important and surprisingly tricky. In diapered children, staff may weigh diapers to estimate output or use a collection bag. Keeping a log of wet diapers or bathroom trips before arriving at hospital gives the team a baseline that no test can reconstruct.
Stool is the sample families can most directly help with. Saving a sample from the earliest possible bowel movement, even a small amount in a clean container provided by the clinic, improves the chance of identifying the organism. Staff will explain safe handling, since STEC spreads easily and hand hygiene protects siblings and caregivers.
Preparing a child honestly helps. Explaining that the tests look for “tiny broken blood cells” and check how the kidneys are working gives a concrete reason for each poke, and children often cope better when they know how many samples are planned for the day.
The NIH’s kidney institute notes that most children with infection-associated HUS recover kidney function, though some need dialysis for a period and a minority have lasting effects requiring long-term follow-up. Families should expect the team to describe the plan in stages rather than as a single answer, because the tests are tracking a moving picture.
What the following days and weeks usually look like
HUS is diagnosed over hours but monitored over weeks, and understanding the rhythm helps people interpret what the team is doing.
In the first two to three days, blood counts and kidney tests are typically repeated at least daily, sometimes more often. Platelets frequently keep falling for a short time after diagnosis before they stabilize, and creatinine may continue to rise even as treatment begins, because the kidney injury that has already occurred takes time to declare itself fully. A rising creatinine on day two is therefore not automatically a sign that things are going wrong. Potassium and fluid balance drive many of the immediate decisions, including whether temporary dialysis is needed.
Toward the end of the first week, recovery of the platelet count is often the first encouraging laboratory sign, followed by a fall in LDH as hemolysis slows. Kidney recovery lags behind; creatinine may plateau for days before it begins to drift down, and urine output returning is often noticed before the numbers improve. Blood pressure may remain elevated for a while and is monitored closely.
Results that were pending at admission return during this window. ADAMTS13 activity usually comes back within days; complement studies and antibody testing within days to a couple of weeks; genetic testing often takes several weeks. Each result may refine the diagnosis and, in atypical cases, the treatment plan.
After discharge, follow-up focuses on the kidney. Cleveland Clinic and the NIH both note that some people who recover from the acute illness develop high blood pressure, protein in the urine or reduced kidney function months or years later, so periodic checks of blood pressure, urinalysis and creatinine are standard for a prolonged period. For atypical HUS, monitoring also watches for relapse, and the schedule is individualized by the nephrology team.
None of these timelines is a promise. They describe typical patterns reported by major medical sources, and any individual course is interpreted by the clinicians following it.
Kidney biopsy and imaging: when they add something
Most HUS is diagnosed without a biopsy, and people are sometimes surprised by that. The reason is straightforward: the combination of blood smear, platelet count, kidney tests and stool findings is usually convincing enough, and biopsy carries bleeding risk that is heightened when platelets are low.
A kidney biopsy involves passing a fine needle through the back into the kidney under ultrasound guidance to remove a sliver of tissue for microscopic examination. In thrombotic microangiopathy it reveals characteristic changes: swollen vessel linings, clots in tiny arteries and glomeruli, and thickened capillary walls. Biopsy becomes useful in specific situations, such as when the laboratory picture is incomplete, when another kidney disease might be present alongside or instead of HUS, when the kidneys fail to recover on the expected timeline, or when the diagnosis in an adult remains unclear after the extended workup. The decision balances diagnostic value against bleeding risk and is made by the nephrology team, often after platelets have partially recovered.
Imaging plays a supporting role. Kidney ultrasound is commonly performed early to check kidney size, exclude obstruction, and rule out structural causes of kidney failure. It is painless and safe in children. In infection-associated HUS the kidneys may appear enlarged and bright on ultrasound, though these findings are not specific.
Because HUS can affect organs beyond the kidney, other imaging is guided by symptoms. Brain imaging is considered if there is confusion, seizures or unusual drowsiness, since Shiga toxin and microclots can injure the brain. Abdominal imaging may be used when severe abdominal pain raises concern about bowel complications, which can accompany the colitis that precedes typical HUS. Heart involvement, though less common, may prompt an echocardiogram or cardiac blood tests.
The pattern here is consistent with the rest of the workup: routine blood and urine tests establish the diagnosis, and more invasive or elaborate investigations are reserved for the questions those tests cannot answer.
What people often get wrong about HUS testing
Several misunderstandings surface repeatedly in clinic conversations and online forums. Correcting them saves worry and, occasionally, prevents a dangerous delay.
The first is the belief that a negative stool test means it is not HUS. Stool culture and toxin testing are most sensitive during the diarrheal phase; by the time kidney injury appears, the organism may be gone. A convincing history of bloody diarrhea followed by the laboratory triad is treated as infection-associated HUS whether or not the laboratory recovers the bacterium.
The second is that the diarrhea improving means the danger has passed. The CDC describes HUS developing about a week after the onset of STEC symptoms, frequently as the diarrhea is resolving. Feeling better in the gut is precisely the window in which pallor, fatigue and reduced urination should be watched for, not the signal to stop watching.
The third is that HUS and TTP are the same disease with two names. They share a laboratory appearance but differ in cause and treatment, which is why ADAMTS13 testing is part of any careful workup rather than an optional extra.
The fourth is that normal complement levels rule out atypical HUS. MedlinePlus Genetics is explicit that many people with aHUS have normal blood complement levels, and a normal genetic panel does not exclude the diagnosis either. Atypical HUS is often diagnosed clinically after other causes are excluded.
The fifth is that one abnormal platelet count is diagnostic. Low platelets have dozens of causes, from viral illness to medication effects. Without fragmented red cells and kidney injury, a low count is a prompt for further testing, not a diagnosis of HUS.
A final misconception concerns antibiotics and antidiarrheal medicines during STEC infection. Whether these help or harm is a question with real evidence behind it and real nuance, and it belongs entirely to the treating clinician. This article deliberately does not offer guidance on it.
Questions to ask your care team about hus blood test results
People coping with HUS often leave rounds with a head full of numbers and no framework for what to ask. These questions are designed to draw out the information that actually shapes decisions.
- Which of the three features, hemolysis, low platelets and kidney injury, is present so far, and which are you still watching for?
- Has the blood smear shown fragmented red cells, and was the Coombs test negative?
- Was a stool sample sent for both culture and Shiga toxin or PCR testing, and when should the result be back?
- Have ADAMTS13 activity and complement studies been sent, and how will the plan change depending on what they show?
- What is the creatinine trend over the last 24 hours, and what would prompt a decision about dialysis?
- How often will blood be drawn today, and what comfort measures are available for a child?
- Which specialists are involved, and who is the single point of contact for updates?
- Is there any sign of involvement beyond the kidney, such as the brain, heart or bowel, and how is that being monitored?
- If this turns out to be atypical HUS, what does the diagnostic process look like from here and how long will genetic results take?
- What follow-up of blood pressure, urine and kidney function will be needed after discharge, and for how long?
- Should other household members be tested or take precautions, given that STEC can spread between people?
- Is this infection reportable to the health department, and will someone contact us about a possible source?
Writing the answers down in one notebook, with the date and the name of the person who answered, makes it far easier to follow the trend across a stay that may involve several teams. It also helps to ask which numbers the team is watching most closely that day; the answer changes as the illness evolves, and knowing it turns a wall of results into a small number of meaningful ones.
When to call your doctor
HUS is an emergency, and the interval between the first warning sign and serious kidney injury can be short. The following situations warrant urgent medical contact or a trip to the emergency department rather than a wait for a routine appointment.
During or after any diarrheal illness, especially one with blood in the stool, seek care promptly for unusual paleness, marked tiredness or listlessness, noticeably less urination than usual (in a young child, fewer wet diapers or none for many hours), swelling of the face, hands or legs, small purple or red spots on the skin, easy bruising, or blood in the urine. Confusion, unusual irritability, extreme sleepiness, a seizure, severe headache, or difficulty breathing require emergency care immediately, as these can indicate involvement of the brain, heart or lungs. The CDC advises that anyone with diarrhea lasting more than three days, or diarrhea with fever above 102°F, bloody stools, vomiting that prevents keeping liquids down, or signs of dehydration should be seen by a clinician.
For people already diagnosed with HUS and recovering at home, the same signs apply, with the addition of high blood pressure readings if home monitoring has been arranged, persistent vomiting, or a return of dark or reduced urine.
For anyone with a history of atypical HUS, new fatigue, pallor, swelling, reduced urine or bruising should be reported to the nephrology team the same day, because relapse is a recognized possibility and early testing changes the response. Pregnant or recently delivered women with these symptoms should contact their maternity or medical team urgently.
None of these signs confirms HUS on its own, and this list is not a tool for self-diagnosis. It is a guide to when the blood counts and kidney tests described in this article need to happen now rather than later. The interpretation of those tests, and every decision that follows, belongs to the treating team.
Frequently asked questions
What is HUS in hematology?
In hematology, HUS is classified as a thrombotic microangiopathy: a disorder in which microclots form in small vessels, consuming platelets and shearing red blood cells. Its laboratory signature is Coombs-negative hemolytic anemia with fragmented red cells on the smear, low platelets, and elevated LDH. What distinguishes it from other microangiopathies is the prominence of acute kidney injury and, in the typical form, a preceding Shiga toxin-producing E. coli infection.
What tests diagnose hemolytic anemia?
Hemolytic anemia is confirmed with a complete blood count showing low hemoglobin, a raised reticulocyte count showing the marrow is compensating, elevated LDH and indirect bilirubin, low haptoglobin, and a blood smear examined for abnormal red cell shapes. A direct antiglobulin (Coombs) test determines whether antibodies are causing the destruction. In HUS the Coombs test is negative and the smear shows fragmented cells, pointing to mechanical damage in small vessels.
What is atypical HUS disease?
Atypical HUS is a form of hemolytic uremic syndrome not caused by Shiga toxin-producing E. coli. It results from uncontrolled activation of complement, a set of immune proteins that normally fight infection but in aHUS injure the body’s own small blood vessels, especially in the kidney. Many people carry genetic variants affecting complement regulation, and an infection, pregnancy or certain medicines can trigger an episode. It accounts for roughly 10 percent of HUS cases.
What is the life expectancy of someone with aHUS disease?
There is no single answer, and this article does not quote survival figures. Outlook in atypical HUS depends on how quickly the diagnosis is made, how much kidney function recovers, whether relapses occur, and the underlying genetic variant if one is found. Complement-blocking therapies have changed the landscape of the condition, and long-term monitoring is standard. The treating nephrology team is the right source for an individualized discussion of prognosis.
How do doctors tell HUS vs TTP apart?
The decisive test is ADAMTS13 activity, the enzyme that trims von Willebrand factor. Severely reduced activity indicates TTP; preserved activity supports HUS or another microangiopathy. Clinical clues help while the result is pending: TTP is more common in adults and tends toward neurological symptoms, whereas HUS is dominated by kidney injury and often follows bloody diarrhea in children. Because the treatments differ, clinicians test rather than rely on the clinical picture alone.
What do hemolytic uremic syndrome lab values typically show?
Typical results include low hemoglobin, low platelets, elevated LDH, low or undetectable haptoglobin, raised indirect bilirubin and reticulocytes, fragmented red cells on the smear, a negative Coombs test, rising creatinine and urea, and urine containing blood and protein. Potassium may be high and bicarbonate low. Exact values depend on age and laboratory reference ranges, so clinicians focus on the direction and speed of change rather than a single number.
How is the stool test for E. coli done in suspected HUS?
A small stool sample is sent to a microbiology laboratory, where it is cultured on selective media to grow E. coli O157 and tested for Shiga toxin or the genes that produce it using an immunoassay or PCR. The CDC recommends both approaches because many non-O157 strains are missed by culture alone. Samples collected early in the diarrheal illness are most likely to be positive, so clinicians request them promptly.
Can HUS be diagnosed without a kidney biopsy?
Yes, and most cases are. The combination of hemolysis markers, fragmented red cells, low platelets, kidney injury and a stool test result is usually sufficient. Biopsy carries bleeding risk when platelets are low, so it is reserved for situations where the picture is unclear, another kidney disease is suspected, recovery stalls, or an adult’s diagnosis remains uncertain after the extended workup. The nephrology team makes that judgment.
How long after E. coli infection do HUS tests become abnormal?
The CDC describes HUS developing about seven days after STEC symptoms begin, often as diarrhea is improving, though the window ranges over roughly one to two weeks. Blood counts and kidney tests are typically normal early in the diarrheal phase and become abnormal as microclots form. This is why clinicians following a confirmed STEC infection repeat blood tests during that period rather than relying on a single early result.
Why are complement and genetic tests sent if results take weeks?
These tests inform the longer-term picture in atypical HUS rather than the first days of care. Complement levels and antibodies against factor H can return within days to a couple of weeks and may support the diagnosis. Genetic results typically take several weeks and help clarify relapse risk, prognosis and implications for family members. Early treatment decisions are made on the clinical picture while these results are pending.
References
- Hemolytic-uremic syndrome (MedlinePlus Medical Encyclopedia)
- Atypical hemolytic-uremic syndrome (MedlinePlus Genetics)
- About Escherichia coli Infection (CDC)
- Hemolytic Uremic Syndrome (Cleveland Clinic)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Preparing a Child for Vesicoureteral Reflux Surgery: Fasting, Comfort and What to Explain
Preparing a child for vesicoureteral reflux (VUR) surgery means following the surgical team's written fasting times exactly, keeping the child as well as possible…

Will the Stone Pass on Its Own? How Size and Location Decide Kidney Stone Treatment
Most kidney stones pass without surgery, particularly stones smaller than about 6 mm that have already reached the lower part of the ureter. A…

How Clean Intermittent Catheterization Is Taught and What a Daily Routine Looks Like
Clean intermittent catheterization training is usually taught one-on-one by a continence or urology nurse, starting with hand hygiene, anatomy and a demonstration, then supervised…

How Potassium Disorders Are Treated: Correcting Levels and Finding the Cause
High potassium (hyperkalemia) is treated in stages matched to how high the level is and whether the heart is affected. Urgent cases receive intravenous…

Neurogenic Bladder Consultation Checklist: Neurology Reports, Scans and Medication Lists
A neurogenic bladder consultation checklist covers three things: the neurology reports that name your condition and where the nerve damage sits, any brain, spine…

Complicated UTI Work-Up: Urine Culture, Kidney Function Tests and When Imaging Is Ordered
A complicated UTI work-up usually starts with a urinalysis and a urine culture to identify the bacteria and show which antibiotics act against them,…