

Helping a Loved One With a Nephrostomy Tube: Dressings, Drainage Bags and the First Night Home

Key Takeaways
- A nephrostomy tube drains urine by gravity alone, so the bag must always sit below kidney level and the tubing must run downhill without loops or kinks.
- A pink tinge in the urine for the first day or two after placement is expected; bright red urine, clots or blood returning after it had cleared is not.
- Serious complications such as bleeding needing transfusion or sepsis occur in a low single-digit percentage of placements, and most appear within the first two days.
- Long-term tubes are typically exchanged every 2–3 months because mineral deposits gradually narrow the catheter, and earlier if they block or shift.
- Fever of 38°C (100.4°F) or above with shivering or flank pain in someone with a nephrostomy tube is a same-hour call, not a wait-until-morning problem.
- A partially pulled-out tube should be taped where it is and reported; pushing it back in can injure the kidney and often fails to restore drainage.
Most people can go home with a nephrostomy tube once the site is stable, and family members can safely help with dressings, bag emptying and checking drainage after teaching from the care team. The essentials are clean hands, a dry secured dressing, a bag kept below kidney level, and urine that keeps flowing. Fever, no drainage, heavy bleeding or a dislodged tube need same-day medical contact.
The hospital bag is unpacked, the discharge folder sits on the kitchen table, and a thin tube runs from your mother’s back to a bag now taped to her thigh. She looks tired. You look at the folder, then at the tube, and think: nobody actually showed me what to do at two in the morning.
That gap between the ward and the first night home is where most of the worry lives. Nephrostomy tube care for family carers is not complicated, but it is unfamiliar, and unfamiliar things feel bigger in the dark. The good news is that the tasks involved are small, repeatable and learnable by anyone who can wash their hands and read a measuring line.
This guide walks through what the tube does, how to change a dressing and empty a bag without panic, what the urine should look like, and the handful of signs that mean you pick up the phone rather than wait until morning.
What a nephrostomy tube actually is and how it works
A nephrostomy tube is a soft, narrow catheter placed through the skin of the back directly into the kidney so urine can drain into a bag outside the body. It is put in by an interventional radiologist, a doctor who uses imaging such as ultrasound and X-ray to guide needles and tubes, usually under local anesthetic with sedation rather than a general anesthetic.
The kidney makes urine constantly and sends it down a tube called the ureter to the bladder. When that path is blocked, urine backs up, the kidney swells (hydronephrosis) and pressure begins to damage the filtering tissue. Infection behind a blockage is particularly dangerous because trapped, infected urine has nowhere to go. A nephrostomy gives the urine a side door: it bypasses the blockage entirely, so the kidney can empty and the pressure drops.
Inside the kidney, the tip of the catheter usually curls into a small loop, sometimes held by a fine internal thread, so it does not slide out easily. Outside, it is fixed to the skin with a stitch, an adhesive anchoring device or both, then covered with a dressing. The external end connects to a drainage bag with a tap.
Nothing about the tube is doing active work. It is a passive channel, which is why gravity, kinks and clots matter so much. Urine only flows downhill and only through a clear lumen. Almost every troubleshooting step you will learn comes back to those two facts. MedlinePlus describes the placement and purpose of the procedure in plain terms, and the reasons for it range from kidney stones to tumors pressing on the ureter to scarring after surgery or radiotherapy.
Who usually goes home with a nephrostomy tube, and who is asked to wait
Can patients go home with a nephrostomy tube? Yes, and most do. The tube itself is not a reason to stay in hospital once the immediate risks after placement have settled. Teams generally look for a short list before discharge: urine draining steadily, no heavy bleeding, temperature and blood pressure stable, pain controlled, and someone at home, or the patient themselves, able to manage the basics.
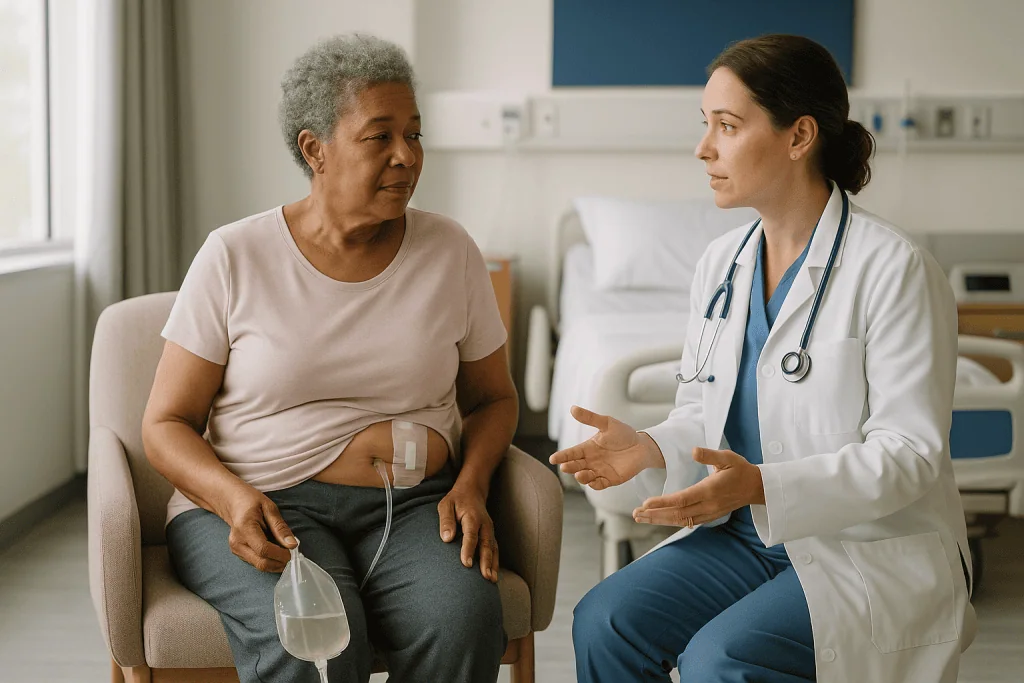
People commonly sent home within a day or two include those whose tube was placed for a stone or a stricture that will be treated definitively later, and those with a cancer-related blockage who are otherwise well enough to be at home. Some will keep the tube for a few weeks; others for many months, with planned exchanges.
People more often asked to wait include those who had sepsis, meaning infection in the bloodstream causing a body-wide reaction, at the time of placement. They usually need intravenous antibiotics and monitoring until the infection is clearly settling. So do those whose urine is still heavily blood-stained, those whose kidney function is being watched closely with daily blood tests, and those whose pain is not yet controlled by tablets. Frailty, confusion or living alone without support can also tip the decision toward a longer stay or a step-down setting.
None of this is a judgment on the patient or the family. The interventional radiology literature, including the technical review by Dagli and Ramchandani, notes that serious complications such as bleeding needing transfusion or sepsis occur in a low single-digit percentage of placements, and most show up in the first day or two. Waiting out that window in hospital is simply the cautious choice for higher-risk patients. The treating team makes the call, and it is fair to ask them what specifically they are waiting to see.
Before you leave the ward: what a family carer should ask for
The most useful hour of nephrostomy tube care for family carers happens before discharge, at the bedside, with a nurse. Ask to watch one dressing change and one bag change, then ask to do the next one yourself while they watch. Reading instructions is not the same as having done it once with a professional standing by.
Leave with written, dated instructions that name the specific supplies your relative uses. Manufacturers vary in how connectors lock and how taps open, and a diagram for a different system is worse than none. Check the folder for these items:
- A phone number that is answered at night and at weekends, and a clear statement of which service to call for which problem.
- The date and place of the next tube check or exchange, and who arranges it.
- Enough dressings, bags, securing devices and anchoring tape for at least the first week, plus a note on how ongoing supplies are ordered.
- A list of current medicines with an explanation of any that were started, paused or changed in hospital, and whether a course of antibiotics has a fixed end date.
Ask two practical questions that are often skipped. First, does this tube have a stitch, and if so, is it expected to stay in or be removed at the first review? Second, is the tube capped, connected to a bag, or attached to an internal stent as well? The answer changes what a dry bag means.
Finally, ask what the team considers normal for this patient. Someone with one working kidney draining into the bag produces a very different volume from someone whose other kidney is fine and whose bladder is still filling normally. Knowing the expected daily output in advance turns a vague worry into a measurable question.
Nephrostomy tube care for family: getting through the first night home
The first night is mostly about position and reassurance. Before bed, connect the larger night bag if the team supplied one. It holds more, so nobody has to get up to empty it, and its longer tubing allows it to hang from the bed frame in a holder or sit in a clean bowl on the floor. The bag must stay below the level of the kidney, so it should never rest on the mattress or be tucked under a pillow. Urine flows down; if the bag sits higher than the tube exit, it can flow back.

Lay the tubing in a gentle curve with no loops that could trap urine and no tension pulling at the dressing. Sleeping on the tube side is usually uncomfortable and can kink the catheter, so most people find their back or the opposite side works best. A pillow behind the back stops a sleeper rolling over onto the site.
Loose nightwear and a top sheet rather than a heavy duvet make it easier to glance at the bag without disturbing anyone. One check before you go to sleep and one when you naturally wake is plenty. You are looking for three things: urine has increased in the bag since the last look, the dressing is still dry and attached, and your relative is not in new or worsening pain.
Some mild ache around the site and a little pink tinge to the urine in the first days after placement are common and described in patient information from MedlinePlus. What is not expected is a bag that has not changed in several hours, a soaked dressing, shivering or a temperature. Keep the out-of-hours number on the bedside table, not in the folder downstairs. Most first nights are uneventful. Knowing exactly what would make you call makes it far easier to sleep.
How to do a nephrostomy tube dressing change without pulling the tube
A dressing change has one non-negotiable goal: the tube stays exactly where it is. Everything else, including neatness, comes second. Your team’s written protocol overrides anything here, but the sequence is broadly the same everywhere.
Set up first. Wash your hands with soap and water for at least 20 seconds, the standard the CDC uses in its hand hygiene guidance, and dry them on a clean towel. Lay out the new dressing, any anchoring device, saline or the cleaning solution you were given, gauze and a bin bag within arm’s reach. Have your relative sit leaning forward on a chair or lie on their side so you can see the site clearly in good light.
Remove the old dressing slowly, peeling toward the tube rather than away from it, and supporting the catheter with your other hand at all times. If an adhesive anchoring device is being replaced, release it according to its own instructions before lifting it. Look at the skin: a small ring of redness where the tube enters is common; spreading redness, swelling, pus or a foul smell is not, and should be reported.
Clean from the tube outward in a single sweep with each piece of gauze, then discard it, so you are always moving away from the entry point rather than dragging skin bacteria toward it. Let the skin dry completely. Damp skin under a dressing softens and breaks down.
Place the new anchoring device or fresh tape, then the dressing, leaving a gentle curve in the tube rather than a tight bend. Note the position of any marking on the catheter relative to the skin; a change in that mark is an early sign the tube has moved. How often dressings are changed varies by team, but the universal rule is sooner if it is wet, lifting or soiled, because a wet dressing is a highway for bacteria.
Nephrostomy bag emptying, day bags and night bags
Emptying the bag is the task you will do most, so it is worth making it boring. Wash your hands, take the bag to the toilet, open the tap at the bottom and let the urine run out without the outlet touching the bowl. Wipe the outlet with clean tissue, close the tap fully and wash your hands again. Most people empty when the bag is between a third and a half full; a heavy bag pulls on the tubing and on the dressing.
Day bags are small, strap to the thigh or calf under clothing and let people move about. Night bags are larger and connect either directly to the tube or to the outlet of the day bag, depending on the system your team uses. Switching is done in the morning and evening with clean hands, taking care never to let the open ends touch anything, including your fingers.
Measuring matters more than families expect. Many bags have volume markings; where they do not, pour into a measuring jug the team has given you. Write the amount and time on a simple chart on the fridge. A daily total that suddenly halves, or a run of empties that produce almost nothing, is far easier to spot on paper than from memory. If the other kidney is still passing urine into the bladder, keep that output separate; the team only wants to know what the tube produces.
Bag changes, as opposed to emptying, follow the schedule the team sets. Reused bags should be rinsed as instructed and never shared between people. Some teams advise leaving the bag connected permanently between planned changes because every disconnection is a chance for bacteria to enter. If your written instructions say not to disconnect for showering, follow them even if it is awkward; the reasoning is infection control, not convenience.
What the urine in the bag should look like, and when to worry
The bag is a window into the kidney, and learning to read it is one of the most reassuring skills a carer can pick up. Fresh urine from a healthy, draining kidney is pale yellow to amber and clear. After placement, a pink or light red tinge for the first day or two is common as the puncture track heals. Small flecks of debris or a little sediment settling at the bottom of the bag are also common, particularly where stones or infection were the reason for the tube.
| What you see | What it often means | What to do |
|---|---|---|
| Pale yellow, clear, steady flow | Kidney draining as expected | Nothing; record volume as usual |
| Dark yellow, small volumes | Often low fluid intake | Encourage drinks within any limit the team set; call if no improvement |
| Light pink in first days | Expected after placement | Watch; report if it deepens |
| Bright red, clots, or red that returns days later | Bleeding that needs assessment | Call the team the same day; urgently if heavy |
| Cloudy, strong smell, with fever or shivering | Possible infection | Call the same day |
| No new urine for several hours | Kink, blockage or displacement | Check tubing and position; call if not resolved |
Two cautions on interpretation. Some foods and medicines change urine color, so a single odd-looking bag in a well person is rarely an emergency. And cloudiness alone, without fever, pain or a change in how your relative feels, may simply be sediment. The combination is what counts. The NHS lists fever, shivering, flank pain and feeling generally unwell as the pattern that suggests kidney infection, and that pattern in someone with a nephrostomy tube should always prompt a call.
Nephrostomy tube not draining: what to check before you call
A bag that has stopped filling is the most common late-night alarm, and in a fair share of cases the cause is mechanical and visible. Run through this sequence calmly before ringing, unless your relative also has fever, severe pain or looks unwell, in which case ring first.
Start at the bag and work back. Is the tap fully closed so urine is not leaking out unseen? Is the bag below kidney level, or has it ended up on the bed? Is there a loop of tubing hanging lower than the bag, holding a column of urine that cannot climb back up? Straighten the tubing so it runs steadily downhill.
Now the tubing itself. Look for a kink where it passes under a strap, a waistband or the body. Check that your relative is not lying on it. Confirm the connection between tube and bag is pushed fully home. Then look at the dressing: has it become wet? Leaking around the tube while the bag stays empty often means the catheter is blocked, so urine is finding the path of least resistance along the outside of it.
Look at the position marking on the tube. If more catheter is visible than before, it may have partially pulled out. Do not push it back in. Tape it securely in its current position and call.
Finally, think about intake. Someone who has drunk very little all day, or who has been vomiting, may simply have less urine to produce. Dark, concentrated urine in the last measured bag supports that explanation.
Do not flush the tube unless you have been specifically taught to and told to do so for this patient. Flushing pushes fluid toward the kidney; done without training, it can force bacteria inward or damage the kidney lining. If the checks above do not restore flow within an hour or two, or sooner if the tube is the only working drainage for the only functioning kidney, call the team.
Keeping infection away: hands, skin and showers
The tube creates a direct route from the outside world into a kidney, so infection control is the heart of daily care. The dominant risk is not exotic; it is hands. The CDC’s guidance is straightforward: soap and water for at least 20 seconds before and after touching the tube, dressing or bag, or an alcohol-based hand rub when soap is not available and hands are not visibly dirty. Anyone helping, including visiting relatives who just want to hold the bag while your loved one moves, follows the same rule.
The skin around the entry site needs to be clean, dry and undisturbed. Avoid creams, powders or antiseptic ointments unless the team prescribes them; occlusive products trap moisture and some irritate. If the skin becomes red, itchy or broken from adhesive, tell the team rather than improvising with different tapes, as they may switch to a different securing device.
Showering is usually allowed once the site has sealed, but the specifics come from your team. Common approaches include covering the dressing with a waterproof cover, showering with the bag connected and hanging low, or timing the shower just before a planned dressing change so a damp dressing can be replaced immediately. Baths and swimming are generally discouraged while the tube is in, because sitting in water soaks the dressing and immerses the site.
Fluids help, within limits. Unless the team has restricted intake because of heart or kidney failure, drinking enough to keep urine pale keeps the catheter flushed from the inside and dilutes any bacteria present. There is no evidence that any particular drink prevents catheter infection, so ordinary water is the sensible default.
Watch for the pattern the NHS describes for kidney infection: temperature of 38°C (100.4°F) or above, shivering, pain in the side or back, cloudy or smelly urine, and feeling generally unwell. In someone with a nephrostomy tube that combination can develop quickly, and it is one of the few situations where waiting until morning is the wrong choice.
Living with a nephrostomy tube: what you can and cannot do
What can I not do with a nephrostomy tube? Fewer things than most families fear. Walking, climbing stairs, light housework, sitting in the garden, working at a desk and driving once pain is controlled and any sedation has worn off are usually fine. The tube is a restriction on the site, not on the person.
The genuine limits cluster around three risks: pulling, soaking and pressure. Anything that yanks the tubing is out, so no heavy lifting, no vigorous twisting sports, no letting the bag dangle where it can catch on a door handle. Water immersion, meaning baths, swimming pools and hot tubs, is generally avoided while the tube is in. Lying flat on the tube side for long periods can kink the catheter and is uncomfortable, so people learn to sleep and rest on the other side or their back.
Clothing adapts easily. Loose waistbands, tops that do not rub the site and a leg bag worn under trousers or a long skirt keep the tube invisible in public. Some people prefer the bag on the calf so it can be emptied without undressing.
Intimacy is not off limits. Securing the tube, choosing positions that keep weight off the site and emptying the bag beforehand are the practical points, and the team will not be embarrassed if you ask.
Travel is possible with planning: enough supplies for the trip plus spares, the discharge letter, a contact number, and knowledge of where the nearest emergency department is at the destination. Long journeys should include regular movement to reduce clot risk, the same advice given to anyone recently discharged from hospital.
Emotionally, the tube can feel like a public sign of illness even when it is hidden. Many people describe self-consciousness in the first weeks that eases as the routine becomes ordinary. Family carers help most by treating the care as a shared task rather than a fuss, and by noticing when the person, not just the tube, needs attention.
The following weeks: exchanges, follow-up and what recovery really means
How long does it take to recover from a nephrostomy tube? The honest answer is that there are two recoveries running at once. The first is recovery from the placement itself: soreness at the site, tiredness from the hospital stay and any light-headedness from sedation. For most people this settles over several days, according to patient information from MedlinePlus, though anyone who was septic before placement will take longer to feel like themselves.
The second recovery belongs to the condition that caused the blockage, and the tube is only one stage in that story. A stone may be treated a few weeks later, after which the tube comes out. A stricture may be widened or stented. A tumor pressing on the ureter may be treated with chemotherapy, radiotherapy or surgery, with the tube staying in for months while that happens. For some people with advanced disease the tube is long-term, and care shifts to keeping it comfortable and trouble-free.
Long-term tubes are exchanged on a schedule because the material gradually collects mineral deposits and debris that can block it. Dagli and Ramchandani’s review describes routine exchange at roughly 2–3 month intervals as standard practice in interventional radiology, with earlier exchange if the tube blocks or is displaced. Exchange is a quick outpatient procedure over a guidewire and is usually far less uncomfortable than the original placement.
Follow-up typically includes a check of kidney function through blood tests, review of the site, and imaging to see whether the blockage has changed. Patients whose other kidney works well may be given the option of a trial without the tube once the obstruction is treated; that decision rests with the urology and radiology teams and depends on how the kidney drains on imaging.
Kidney function recovery after relief of obstruction varies enormously with how long the blockage was present and how severe it was. Cleveland Clinic’s material on hydronephrosis notes that prolonged obstruction can cause permanent damage, which is why placement is often treated as urgent even when the person feels reasonably well.
Life expectancy with a nephrostomy tube: the question people are afraid to ask
Search engines see this question constantly, usually typed late at night by someone who has just brought a parent home. It deserves a straight answer. A nephrostomy tube does not shorten life on its own. It is a drainage device, not a disease, and plenty of people live with one for years while the underlying problem is managed.
What determines the outlook is the reason the tube was needed. Someone with a kidney stone that will be cleared in a few weeks has the same life expectancy as they had before the stone. Someone whose ureter is compressed by an advanced cancer has an outlook set by that cancer, and the tube is there to protect kidney function and reduce infection risk while it is treated or controlled. In that setting a tube can add comfort and time by preventing kidney failure and sepsis, but it does not change the trajectory of the cancer itself.
Where the tube does carry its own risk is through complications: blocked tubes, displaced tubes and infections that can, if unrecognized, progress to sepsis. Complication rates in the interventional radiology literature, including the review by Dagli and Ramchandani, are low, and the majority of tube-related problems are treatable when reported promptly. This is exactly why family involvement in care matters: a carer who notices cloudy urine and a shiver on a Tuesday evening prevents the hospital admission that would otherwise happen on Thursday.
If the question behind the question is about prognosis for a specific illness, the person to ask is the consultant responsible for that illness, and you are entitled to ask directly. Online forums contain heartfelt stories but no way to know whether another patient’s circumstances resemble your relative’s. A frank conversation with the treating team, with the patient’s permission and ideally with the patient present, gives a more useful answer than any statistic.
What people often get wrong about nephrostomy tubes
Some misunderstandings show up repeatedly in clinic and cause real harm, so they are worth naming.
Myth: the tube must be flushed to keep it clear. Some patients are taught to flush, most are not. Unrequested flushing can push bacteria into the kidney or raise pressure inside it. If you have not been taught for this specific patient, do not flush.
Myth: a little blood always means something is wrong. A pink tinge in the first day or two after placement or exchange is expected. What needs reporting is bright red urine, clots, blood that returns after clearing, or bleeding accompanied by dizziness or a fast heartbeat.
Myth: if the tube slips out a bit, push it back. Never. The internal loop may no longer be in the kidney, and reinserting blindly can injure tissue. Secure it where it is and call. Because the track can start to close within hours, a fully dislodged tube is a same-day problem.
Myth: keeping the bag high keeps it out of the way. Urine flows downhill only. A bag above kidney level stops draining and can let urine flow back toward the kidney, carrying bacteria with it.
Myth: antibiotics prevent infection while the tube is in. Long-term preventive antibiotics are not routine for nephrostomy tubes; they encourage resistant bacteria. Antibiotics are prescribed for a diagnosed infection, for a fixed course, by the treating clinician. Never start leftover antibiotics at home because the urine looks cloudy.
Myth: the tube means the kidney has failed. Often it means the opposite: the kidney is working, which is why urine backed up when its exit was blocked. The tube is protecting a functioning organ.
Myth: carers need medical training. Dressings, emptying and observation are routinely taught to families and are performed safely at home every day. What carers need is one supervised practice, written instructions for their equipment, and a number to call.
Questions to ask your care team before and after discharge
A good discharge conversation is a two-way exchange, and teams generally welcome specific questions because they reduce avoidable calls later. Bring a notebook, or ask permission to record the answers on a phone.
- Why does my relative need this tube, and what is the plan for treating the blockage?
- How long do you expect the tube to stay in, and what would change that estimate?
- Is the tube stitched, anchored with a device, or both? Will the stitch be removed, and when?
- How much urine should we expect in the bag over 24 hours, and does the other kidney still drain to the bladder?
- How often should the dressing be changed, with which products, and who supplies them?
- Should the bag ever be disconnected for showering, or stay attached between scheduled changes?
- Are we expected to flush the tube? If yes, please show us and write down exactly when.
- What counts as too much blood in the urine for this patient?
- Which number do we ring at night and at weekends, and when should we go straight to an emergency department instead?
- When is the next exchange or review, and how do we get there?
- Which medicines have changed in hospital, and is anything being stopped or finished on a set date?
- Are there activity restrictions specific to my relative’s other conditions?
Two further questions are useful for family carers themselves. First, is there a community or district nursing service that can share dressing changes, particularly early on? Second, if the patient becomes unable to manage or to tell us how they feel, who makes decisions about the tube and about escalation? That question is easier to ask on a calm day than in a crisis.
Write the answers down, keep them with the discharge letter, and take the same notebook to every follow-up appointment. Over time it becomes a record of what normal looks like for this person, which is the single most useful reference you can have.
When to call your doctor: red flags with a nephrostomy tube
Most days with a nephrostomy tube pass without incident. The value of a family carer lies in recognizing the few situations that should not wait, and having the confidence to act on them. Call the number your team gave you, or seek urgent care, for any of the following.
Call urgently, the same hour:
- Temperature of 38°C (100.4°F) or above, shivering or shaking, especially with cloudy urine or new pain in the side; the NHS describes this pattern as suggestive of kidney infection, and behind a tube it can progress rapidly to sepsis.
- Confusion, drowsiness, fast breathing, a racing pulse or feeling faint, which can be signs of sepsis or significant bleeding.
- Bright red urine, clots in the tube or bag, or bleeding that soaks the dressing.
- The tube has come out completely, or a much longer length is visible than before.
- Severe pain at the site or in the flank that is new or rapidly worsening.
Call the same day:
- No urine in the bag for several hours after you have checked the tap, tubing position, kinks and bag height, particularly if the tube drains the only working kidney.
- Urine leaking around the tube onto the dressing while the bag stays empty.
- Spreading redness, swelling, pus or a foul smell at the entry site.
- Persistent cloudiness or strong smell even without fever, or a marked drop in daily volume.
- Nausea and vomiting that stops your relative keeping fluids down.
Do not attempt to reinsert a dislodged tube, do not flush unless taught, and do not give antibiotics left over from a previous course. If you cannot reach the specialist team and your relative has a fever or looks unwell, go to the emergency department and take the discharge letter with you.
Every decision about treatment, including whether the tube stays, is exchanged or is removed, rests with the treating team. Your job is to notice and to report. Done well, that is a large part of what keeps someone with a nephrostomy tube safely at home.
Frequently asked questions
Can patients go home with a nephrostomy tube?
Yes, most people go home once urine is draining steadily, bleeding has settled and temperature and blood pressure are stable. Teams usually want to see that the patient or a family member can empty the bag, keep the dressing dry and knows which signs need a call. People who were septic at placement or have heavy bleeding are commonly kept in longer.
What is the average life expectancy for someone with a nephrostomy tube?
The tube itself does not determine life expectancy; the condition that caused the blockage does. Someone with a stone that will be cleared has the same outlook as before. Someone with advanced cancer has an outlook set by that cancer, and the tube protects kidney function while it is treated. For a specific prognosis, ask the consultant responsible for the underlying illness.
What can I not do with a nephrostomy tube?
Avoid anything that pulls on the tube, soaks the dressing or presses on the site: heavy lifting, twisting sports, baths, swimming, hot tubs and lying on the tube side for long periods. Walking, stairs, desk work, light housework and driving once pain is controlled are usually fine. Your team may add restrictions based on other conditions.
How long does it take to recover from a nephrostomy tube?
Soreness and tiredness from placement usually ease over several days. The longer recovery belongs to the underlying cause: a stone treated weeks later, a stricture that is stented, or a cancer treated over months. Kidney function recovery after relieving a blockage depends on how long and how severely the kidney was obstructed, which your team can discuss.
How often should a nephrostomy tube dressing change be done?
Follow the interval your team wrote down for your relative’s specific products, and change it sooner whenever it becomes wet, lifting or soiled. A damp dressing lets bacteria reach the entry site. During each change, support the tube with one hand, clean from the tube outward, let the skin dry fully, and check the position mark on the catheter.
What is the right technique for nephrostomy bag emptying?
Wash hands, open the tap over the toilet without letting the outlet touch anything, close it fully, wipe the outlet with clean tissue and wash hands again. Empty when the bag is a third to half full so its weight does not pull on the dressing. Record the volume and time on a chart so trends are easy to spot.
What should I do if the nephrostomy tube is not draining?
Check that the tap is closed, the bag is below kidney level, the tubing has no kinks or low loops, the connection is firm and nobody is lying on the tube. Look for leaking around the dressing or extra length of catheter showing. Do not flush unless taught. If flow does not return within an hour or two, or your relative has fever or pain, call the team.
Can someone with a nephrostomy tube shower?
Usually yes, once the site has sealed, but the method depends on your team’s instructions. Options include a waterproof dressing cover, showering with the bag connected and hanging low, or showering immediately before a planned dressing change. Baths, swimming and hot tubs are generally avoided because immersion soaks the site.
Is it normal to see blood in a nephrostomy bag?
A light pink tinge for a day or two after placement or exchange is common as the puncture track heals. Bright red urine, visible clots, blood that returns after clearing, or bleeding with dizziness or a fast pulse needs a same-day call, and urgently if heavy. Blood-thinning medicines can increase bleeding, so mention them when you ring.
What is living with a nephrostomy tube like day to day?
Once the routine settles, most people describe it as an inconvenience rather than a disability. A leg bag hides under ordinary clothing, sleeping on the opposite side becomes habit, and emptying takes a minute. Self-consciousness in the first weeks is common and usually eases. Carers help most by treating the tasks as ordinary and noticing when the person, not just the tube, needs support.
References
- MedlinePlus: Percutaneous urinary procedures
- NIH PubMed Central: Percutaneous Nephrostomy: Technical Aspects and Indications (Dagli & Ramchandani, Seminars in Interventional Radiology)
- NHS: Kidney infection
- CDC: About Handwashing
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Bladder Problems After Childbirth: What Is Common, What Is Treated and When to Get Help
Bladder problems after childbirth are common and usually improve. Leaking with coughing or exercise, sudden urgency, and difficulty emptying can follow the stretching of…

TURP Recovery Week by Week: Catheter Days, Bladder Flushing and Getting Back to Normal Routines
After a TURP, most men spend one to three days in hospital with a catheter and bladder flushing, then go home once they can…

After a Renal Angiogram: Puncture Site Rest, Fluids and When Normal Activity Resumes
Recovery after a renal angiogram is usually short. Most people lie flat for several hours so the artery puncture can seal, drink fluids to…

Living With Renal Tubular Acidosis: Bone Health, Kidney Stones and Ongoing Follow-Up
Renal tubular acidosis (RTA) is a kidney tubule disorder that leaves the blood mildly but persistently acidic. Over time that acid load draws calcium…

Ureteroscopy vs Shock Wave Lithotripsy for Ureteral Stones: How the Choice Is Made
Ureteroscopy and shock wave lithotripsy both treat ureteral stones, and neither is better for everyone. Urologists weigh stone size, location, hardness, how far the…

Urinary Infections in Women and Men: Why the Causes Differ and How Care Is Adjusted
Urinary infections differ between women and men mainly because of anatomy. A woman's short urethra opens close to the bowel, so gut bacteria reach…