

How Masseter Botox Is Injected: Locating the Chewing Muscle and What the Session Involves
Key Takeaways
- The masseter is located by the clench test: biting down makes the muscle bulge so the clinician can feel its front, lower and rear borders before marking injection points.
- Injectors stay below an imaginary line from the tragus of the ear to the corner of the mouth to keep botulinum toxin away from the muscles that lift the smile.
- Botulinum toxin blocks acetylcholine release at the nerve-muscle junction, so the masseter weakens within days and shrinks from disuse over the following weeks.
- NHS guidance puts the typical duration of botulinum toxin effects at around three to four months, after which muscle activity gradually returns.
- Masseter injection is off-label in the United States, and MedlinePlus carries a boxed warning about toxin spread causing swallowing, speech or breathing difficulty.
- Mayo Clinic lists botulinum toxin among options for severe bruxism only after other treatments have failed, and the NIH's dental institute describes the evidence for jaw disorders as limited.
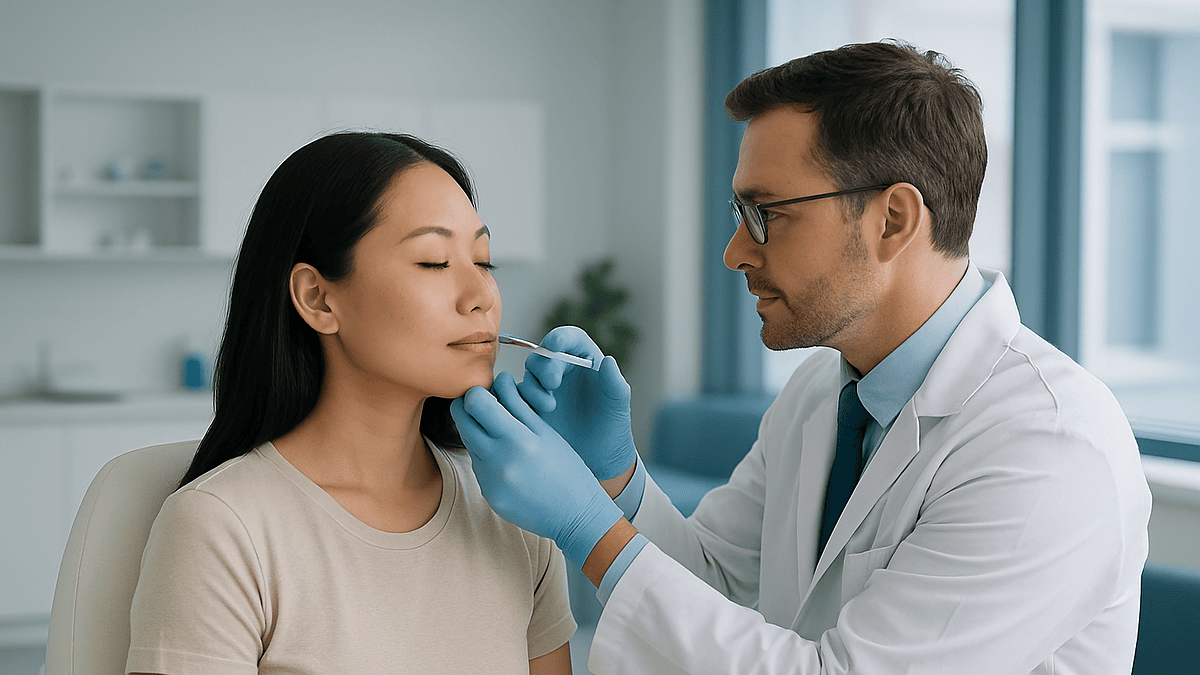
In a masseter botox procedure, a clinician first asks you to clench your teeth so the masseter, the thick chewing muscle at the back of the jaw, stands out under the skin. After marking a safe zone in the lower part of the muscle, they inject small amounts of botulinum toxin type A at a few points on each side. The session is short, uses a fine needle, and the muscle gradually weakens and slims over the following weeks.
It usually starts with a photograph. Someone looks at a picture taken from slightly below and notices that the corners of their jaw seem to have squared off, or they wake for the third morning in a row with a dull ache in their cheeks and a dentist’s warning about worn enamel still in their ears. Then a friend mentions having her “jaw done,” and a search begins.
Most of what comes up about the masseter botox procedure is written to sell it. Far less explains what actually happens in the chair: how a clinician finds a muscle they cannot see, why they press on your cheek while you bite down, and what the small pen marks are for.
This explainer walks through that session from the consultation to the weeks afterward, with the evidence laid out plainly, the risks stated in neutral terms, and every decision left where it belongs, with you and the clinician who examines you.
What the masseter botox procedure actually is
“Masseter Botox” is shorthand. The medicine involved is botulinum toxin type A, a purified protein that temporarily blocks the signal between a nerve and the muscle it controls. Botox is one brand name for that class of medicine; others exist, and clinicians choose among them for their own reasons. Throughout this article, the word is used because it is what people type, not as a recommendation of any product.
The masseter is the broad chewing muscle that runs from the cheekbone down to the angle of the jaw. When a clinician injects botulinum toxin into it, the muscle receives fewer nerve signals, contracts less forcefully, and, over weeks, loses some bulk from underuse. Cleveland Clinic describes this general mechanism for all botulinum toxin injections: the medicine prevents the release of acetylcholine, the chemical messenger that tells a muscle to tighten.
Two facts shape everything that follows. First, in the United States the masseter is not among the approved uses of botulinum toxin products. Injecting it for jaw slimming or clenching is off-label, meaning a licensed prescriber may do it based on clinical judgment, but the manufacturer has not sought approval for that use. A reputable clinician will say so. Second, the effect is temporary by design. The nerve endings recover, and the muscle regains its strength.
So the procedure is best understood as a reversible, repeated medical treatment rather than a one-time change, and the person doing it needs a working knowledge of facial anatomy, because the masseter shares its neighborhood with the salivary gland and the muscles that lift your smile.
Where is the masseter muscle, and why does it widen the jaw?
Put your fingertips on your cheek just in front of your earlobe and bite down. The firm block that rises under your fingers is the masseter. It anchors above to the zygomatic arch, the bony ridge of the cheekbone, and below to the outer surface of the mandible, the lower jaw, near its angle.
Anatomists divide it into a superficial part, which runs slightly backward and downward, and a deeper part that sits more vertically behind it. The superficial part is what most people can feel, and it is the part most responsible for a squared jawline when it enlarges.
Why would a chewing muscle grow? For the same reason a biceps does: repeated, forceful work. Mayo Clinic notes that bruxism, the medical term for clenching or grinding the teeth, often happens during sleep and can occur while awake as well. Years of nighttime clenching act like resistance training for the masseter. Hard, chewy diets and habits such as frequent gum chewing add load. Some people are also simply born with a wider mandible or a thicker muscle, and no injection changes bone.
That last point matters when setting expectations. A clinician assessing the lower face will try to work out how much of the width is muscle and how much is bone or fat. Muscle softens when you relax and hardens when you clench; bone does not move. If most of the fullness is skeletal, botulinum toxin will not deliver what the person is picturing, and an honest consultation will say so before any needle appears.
How does botulinum toxin work in a chewing muscle?
Every time you bite, a motor nerve releases acetylcholine at the junction where it meets the muscle fiber. The muscle reads that chemical as “contract.” Botulinum toxin type A enters the nerve ending and disables the machinery that releases acetylcholine. The nerve is still alive and still trying; the message simply does not get through.
MedlinePlus describes the result plainly: the injected muscle is weakened or relaxed for a period of time. Two consequences follow in the masseter. The first is quick. Within days the muscle contracts less forcefully, which is why some people describe a softer bite or less morning jaw tightness early on. The second is slower. A muscle that works less begins to shrink, the way an arm in a cast loses some of its bulk. This is the visible slimming, and it lags the weakening by weeks.
The effect is dose-related and point-related, which is why placement is the whole art. Botulinum toxin diffuses a short distance from where it is placed. Put it in the thick lower belly of the masseter and the chewing muscle relaxes. Put it too far forward or too high and it can drift into the risorius or zygomaticus, small muscles that pull the corner of the mouth outward and upward, producing a lopsided smile. Place it too far back and it can affect the parotid gland, the large salivary gland that lies over the rear of the masseter, sometimes causing dryness.
Over months, the nerve sprouts new endings and the original junction recovers. Strength returns, and with continued use, so does bulk. Nothing about the mechanism is permanent, which is both its safety margin and its limitation.
Who is masseter Botox usually for, and who is asked to wait?
People arrive at this conversation from two directions. Some are troubled by a jawline they feel is heavier or squarer than they would like, particularly when the width is clearly muscular. Others come with a functional complaint: clenching, grinding, jaw fatigue, or headaches that their dentist has linked to overactive chewing muscles. Many sit in both camps at once.
Clinicians tend to consider the procedure when the masseter is visibly or palpably enlarged, when the person understands that results are temporary and gradual, and when the goals are realistic. For clenching, Mayo Clinic lists botulinum toxin injections among options that may be considered for people with severe bruxism who have not responded to other treatments, which places it after mouth guards and behavioral approaches rather than before them.
Who is usually asked to wait or advised against it? MedlinePlus and NHS guidance on botulinum toxin injections converge on several groups:
- People who are pregnant or breastfeeding, because safety data are lacking.
- People with neuromuscular conditions such as myasthenia gravis or motor neuron disease, in which weakening a muscle further can be hazardous.
- Anyone with an infection or skin problem at the injection site, until it clears.
- Those with a known allergy to any component of the product.
- People taking certain medicines, including some antibiotics and muscle relaxants, that can amplify the toxin’s effect; the prescriber reviews this list.
Clinicians also pause when someone hopes to fix a jaw that is broad because of bone, when a person already has thin cheeks or loose skin along the jaw that might look more hollow or lax after muscle shrinkage, or when expectations cannot be reconciled with what the mechanism can deliver. Those judgments belong to the treating clinician after an in-person examination.
Before the injection: the consultation and mapping the muscle
A good session begins long before the vial is opened. The clinician will ask what bothers you and listen for whether the answer is appearance, symptoms, or both, because the answer changes where and how they inject. Someone seeking a slimmer angle and someone seeking relief from clenching may be treated similarly, but the conversation about what success looks like differs.
Expect questions about your medical history: nerve or muscle disorders, previous botulinum toxin treatments and how you responded, medicines and supplements, allergies, pregnancy plans, and dental work. NHS guidance on botulinum toxin injections emphasizes that it is a prescription medicine and that a prescriber must assess you face to face before it is given. Photographs from the front and both sides are standard, both for planning and for comparison later.
Then comes the physical examination. The clinician watches your face at rest, then asks you to clench hard, relax, and repeat. They palpate the masseter with fingertips, feeling for its front edge, its lower attachment along the jawbone, and any particularly thick region, often the lower third. They note whether one side is bulkier, which is common, and whether your smile is symmetric at baseline, so that any later change can be judged fairly.
This is also the moment for the honest disclosures: that the use is off-label, that results are temporary, that the visible change is gradual, and what the known side effects are. If any of these are skipped, it is reasonable to ask.
Finally, the clinician draws. With a skin-safe marker they outline the muscle borders and the injection points. Those marks are not decoration; they are the map that keeps the medicine in the right muscle and out of the wrong ones.
Locating the chewing muscle: the clench test and the safe zone
The masseter cannot be seen directly, so clinicians find it by feel and by function. The clench test is the core of this. You bite down firmly on your back teeth while the clinician’s fingers rest on your cheek. The muscle bunches upward and outward, and its edges become obvious: a soft front border a finger’s width or two in front of the ear-to-mouth line, a firm lower edge where it attaches to the mandible, and a rear border tucked in front of the ear.
Most injectors then define a treatment zone with three landmarks:
- The lower boundary is the bony edge of the jaw, which they can feel with a thumb.
- The upper boundary is an imaginary line from the tragus, the small cartilage flap in front of the ear canal, to the corner of the mouth. Staying below this line keeps the medicine away from the smile muscles and reduces the chance of an asymmetric grin.
- The front boundary is the palpable anterior edge of the masseter itself, located while you clench.
Within that zone, the clinician identifies the thickest part of the muscle, usually in the lower third near the angle of the jaw, because that is where the bulk that widens the face lives and where the needle has the most muscle to sit in. The number of points and the spacing between them vary with the size and shape of the muscle and with the injector’s training, so there is no universal pattern.
Why so much care about a few centimeters? The parotid gland drapes over the back of the masseter, and the risorius and zygomaticus lie just beyond its front edge. Medicine placed a little too far in any direction can produce dryness or a smile that pulls unevenly. Good placement is the main safety tool available in this procedure, which is why the clinician’s anatomical training matters more than any brand of toxin.
The masseter botox procedure step by step
Once the plan is agreed and the marks are drawn, the session itself is brief. Mayo Clinic describes botulinum toxin injections generally as taking only a few minutes and usually being performed in a clinician’s office. The masseter is no exception.
The skin over the marked area is cleaned with an antiseptic, and any makeup is removed. Some clinicians offer a numbing cream or a cold pack beforehand; others do not, because the needle is very fine and the muscle is not especially sensitive. If you have a strong preference, say so during the consultation.
You will be asked to sit upright and, often, to clench once more so the clinician can confirm the muscle position under their fingers. Holding the skin steady with one hand, they pass a thin needle through the skin and the thin layer of fat into the belly of the muscle. The depth is deeper than for forehead lines, since the masseter is a thick muscle sitting on bone. A small amount of solution is delivered, the needle is withdrawn, and the clinician moves to the next mark. Gentle pressure with gauze controls any pinpoint bleeding.
Both sides are usually treated in the same visit, with the clinician sometimes adjusting placement if one masseter is noticeably larger than the other. The whole injecting phase commonly takes less time than the conversation before it.
Afterward you may notice small raised bumps at the injection points that settle quickly, and occasionally a dot of bruising. You can usually leave immediately and return to ordinary activities; NHS guidance notes that most people can go about their day after botulinum toxin injections, with a few precautions covered in the next sections. A follow-up visit is often scheduled for some weeks later to review the response.
How painful is masseter Botox?
People consistently ask this before anything else, and the honest answer is: usually not very, but not nothing. Mayo Clinic describes botulinum toxin injections as causing little discomfort, and the masseter tends to be among the more comfortable areas because the skin over it is thicker and less richly supplied with sensory nerves than the forehead or the area around the eyes.
Most people describe each pass as a brief pinch or pressure, followed by a mild ache as the fluid enters the muscle. The needle is very fine. Because the masseter is deep and sits against bone, some notice a dull, heavy sensation rather than a sharp sting. The discomfort ends when the needle comes out; there is no lingering burn like there can be with some injectable medicines.
Several factors nudge the experience one way or the other:
- Clenched versus relaxed: injecting into a tense muscle can feel more uncomfortable, so clinicians typically ask you to relax after they have located the muscle.
- Anxiety: worry heightens pain perception. Knowing what to expect, and asking the clinician to talk you through each step, genuinely helps.
- Cold or numbing cream: both blunt the pinch, though many people skip them.
- Individual sensitivity, which varies as much as for any injection.
In the hours afterward, a tender, slightly bruised feeling at the injection sites is common and fades within a day or two. Some people report mild jaw fatigue when chewing tough food in the first week or so as the muscle weakens, which is the intended effect making itself known rather than a complication.
Severe or escalating pain is not expected and should prompt a call to the clinician, as should swelling that increases rather than settles.
Masseter botox aftercare and how long masseter botox lasts: the following weeks
The first evening is quiet. NHS guidance on botulinum toxin injections advises avoiding rubbing or massaging the treated area for a period after the session, along with strenuous exercise, alcohol, and heat exposure such as saunas or sunbeds on the day, because these may increase bruising or encourage the medicine to spread. Staying upright for a few hours is a common instruction, and your clinician will give their own version.
Nothing visible happens for a while, and that is normal. Mayo Clinic notes that botulinum toxin injections generally begin working within one to three days, though it may take a week or more to see the full effect. In the masseter, the first sign is usually functional: chewing gum or steak feels a little more tiring, and people who clench often notice their jaw is looser on waking.
The slimming lags behind. The muscle has to shrink from disuse, and that is a matter of weeks. NHS guidance describes the full effect of botulinum toxin taking two to three weeks to develop, and many people find that the change in the jaw’s outline continues to settle for some time after that, which is why follow-up reviews are typically scheduled several weeks out rather than days.
Duration is the question behind “how long does masseter botox last.” NHS guidance states that the effects of botulinum toxin injections usually last around three to four months, after which muscle activity gradually returns. Mayo Clinic frames it as three months or longer depending on what is treated. Individual variation is wide, and a strong, heavily used chewing muscle may recover its bulk more quickly than a small facial muscle.
Whether and when to repeat is a decision made with the clinician at review, weighing your response, your goals, and any side effects.
Is there a downside to masseter Botox? Side effects and risks
Yes, and they deserve a clear-eyed look. The common effects are minor and short-lived. NHS and Mayo Clinic both list pain, swelling, and bruising at the injection site, headache, and flu-like symptoms in the days afterward among the frequent reactions to botulinum toxin injections. In the masseter specifically, mild chewing fatigue is expected and usually settles as you adapt.
The area-specific risks are the ones people are rarely told about:
- Smile asymmetry: if medicine reaches the risorius or zygomaticus, one side of the mouth may not lift fully. This is temporary but can last as long as the treatment does.
- Paradoxical bulging: when the superficial part of the muscle weakens but the deep part does not, a lump may appear when clenching. It typically resolves and can be addressed at review.
- Cheek hollowing or a sunken look, particularly in people with little facial fat or after repeated treatments.
- Sagging or jowling along the jaw in those whose skin was already lax, because the muscle was providing some support.
- Dry mouth or altered saliva if the parotid gland is affected.
- Bite changes or difficulty with very hard foods early on.
MedlinePlus carries the boxed warning that applies to every botulinum toxin product: the toxin may spread beyond the injection area and cause symptoms such as muscle weakness, double or blurred vision, drooping eyelids, hoarseness, trouble speaking, difficulty swallowing, or trouble breathing, which can appear hours to weeks after injection. These are rare with cosmetic use, but they are the reason the medicine is prescription-only and the reason the red-flag list later in this article exists.
The other downside is quieter: cost of time and repetition, the off-label status, and the fact that the evidence for long-term repeated use in a chewing muscle is thinner than for approved indications. A clinician should be willing to discuss all of it.
Does masseter botox for jaw clenching or TMJ actually work? What the evidence shows
Here the honest answer is “sometimes, for some people, and the research is not settled.” Bruxism and temporomandibular disorders, the group of conditions affecting the jaw joint and the muscles around it, are common and frequently overlap. Mayo Clinic notes that clenching can lead to jaw pain, headaches, worn or damaged teeth, and disrupted sleep, and that it often improves with conservative measures.
Where does botulinum toxin fit? Mayo Clinic lists it among treatments that may be considered for severe bruxism that has not responded to other approaches. The National Institute of Dental and Craniofacial Research, part of the NIH, takes a cautious tone on temporomandibular disorders more broadly, advising that treatments be reversible and conservative where possible and noting that many treatments have not been rigorously tested. Botulinum toxin is reversible, which fits that principle, but the same body of guidance stresses that evidence for injections in TMD remains limited.
Mechanistically the logic is sound: a muscle that cannot contract as hard cannot grind as hard. Small trials have reported reduced pain and clenching frequency in some participants, while others have found effects similar to placebo or short-lived. Systematic reviews generally conclude that the studies are small, vary in method, and do not yet allow firm recommendations. That is the evidence-graded position, and it is worth holding onto when a headline promises a solution.
Practically, this means clinicians usually expect a person with grinding to have tried, or to continue, a properly fitted night guard, attention to stress and sleep, and treatment of any contributing factors before or alongside injections. It also means a dental assessment matters, because grinding can damage teeth regardless of how relaxed the muscle feels. The decision to try botulinum toxin for symptoms is a clinical one, made after examination, and revisited at each review.
Masseter Botox compared with the alternatives
Muscle relaxation with botulinum toxin is one tool among several, and which one suits a person depends on whether the concern is appearance, symptoms, or both. Laying them side by side clarifies the trade-offs.
| Approach | What it targets | Reversible? | Typical timeline | Main limitations |
|---|---|---|---|---|
| Botulinum toxin into the masseter | Muscle bulk and clenching force | Yes, wears off | Weakening in days; visible change over weeks; effects around 3–4 months (NHS) | Off-label; repeat treatments; smile or saliva side effects if misplaced |
| Custom night guard (occlusal splint) | Tooth wear and some muscle strain from grinding | Yes | Protects teeth from first night; symptom change varies | Does not slim the jaw; needs dental fitting and adherence |
| Behavioral and stress approaches | Daytime clenching habits, sleep quality | Yes | Gradual, over weeks to months | Requires sustained effort; less useful for purely aesthetic goals |
| Surgical jaw contouring | Bone width at the mandibular angle | No | Permanent after recovery from surgery | Major surgery with anesthesia, swelling and surgical risks |
| Doing nothing for now | Preserves options | Not applicable | Ongoing | Grinding may continue to wear teeth if untreated |
A few observations flow from the table. A night guard and botulinum toxin are not rivals; Mayo Clinic frames guards as a first-line protective measure and injections as a later option for severe cases, and many people use both. Surgery is the only route that changes bone, and it is the only irreversible one, which is why clinicians rarely suggest it unless the width is clearly skeletal and the person has considered it carefully. For someone whose main wish is a softer jawline from an enlarged muscle, the injection remains the least invasive option that addresses muscle directly. None of these choices should be made from a comparison chart; they are the raw material for a conversation with a clinician who has examined you.
What people often get wrong about masseter Botox
Myths cluster around this procedure, partly because so much writing about it comes from people selling it. A few corrections, each grounded in how the medicine actually behaves.
“It’s permanent after a few sessions.” It is not. Botulinum toxin blocks nerve signals temporarily, and MedlinePlus and NHS guidance describe effects that wear off over months. A muscle that has been relaxed repeatedly may take longer to rebuild, but the mechanism has no permanent phase. Anyone who stops treatment can expect strength and, with use, bulk to return.
“It will fix my square jaw.” Only if the squareness is muscle. Bone does not respond to a medicine that acts on nerve endings. The clench test during consultation exists precisely to sort muscle from bone, and a clinician who skips it is skipping the most important part of the assessment.
“The change is instant.” Mayo Clinic describes onset over one to three days with full effect taking a week or more, and the visible slimming in a chewing muscle comes later still, as the muscle shrinks from disuse. Judging the result in the first week is judging it too early.
“More is better.” Over-treatment is where the hollowed, sunken look and the drooping along the jaw come from. Conservative placement with review is safer than an aggressive first session, and adjustments can be made at follow-up. Dosing is entirely the prescriber’s call and varies with anatomy.
“It’s just cosmetic, so it’s trivial.” It is a prescription medicine with a boxed warning about distant spread, which is why NHS guidance insists on a face-to-face assessment by a prescriber. The risk is low, and it is real.
“It will stop me grinding.” The evidence, as the NIH’s dental institute notes for jaw disorders generally, is limited. Some people find relief; others do not; teeth still need protection.
Questions to ask your care team before a masseter botox procedure
Bringing a short list to the consultation does two things: it gets you the information you need, and it shows you how the clinician handles being asked. Both are useful. The questions below are drawn from what people commonly wish they had asked.
- Is my jaw width mostly muscle, bone, or fat, and how did you decide? Ask them to show you with the clench test.
- What are you trying to achieve on each side, and how will you handle the fact that one masseter is often larger than the other?
- Which botulinum toxin product do you use, and what is your training in injecting the masseter specifically? Anatomy knowledge is the main safety tool here.
- Is this use off-label, and what does that mean for me?
- How will you protect the smile muscles and the parotid gland? A clear description of the safe zone is a reassuring answer.
- What side effects have you seen in this area, and how did you manage them?
- Do any of my medicines, supplements or medical conditions change the plan? Bring a full list, including antibiotics you have recently taken.
- What should I do and avoid in the first day, and for how long?
- When will you review me, and what will you be looking for?
- If I have clenching or grinding, do you want me to continue a night guard, and do you want to speak with my dentist?
- What happens if I get an uneven smile or a lump when clenching? Can it be corrected, and when?
- How do I reach you outside clinic hours if something worries me?
Write the answers down or ask permission to record them. A clinician who welcomes these questions and answers in plain language is telling you something about how the rest of your care will go. One who brushes them off is telling you something too.
When to call your doctor
Most people notice nothing more than tenderness and a small bruise after masseter injections. A short list of signs, drawn from MedlinePlus and NHS guidance on botulinum toxin, should prompt a prompt call to the clinician who treated you or to your regular doctor.
Seek urgent medical help, using emergency services if needed, for any of the following, which can indicate that the toxin has spread beyond the injection area or that an allergic reaction is developing:
- Difficulty swallowing, choking on food or liquids, or a sense that food is sticking.
- Trouble breathing, shortness of breath, or a change in your voice or speech.
- Widespread muscle weakness, or weakness in muscles far from the jaw.
- Double vision, blurred vision, or a drooping eyelid.
- Hives, swelling of the lips, tongue or throat, wheezing, dizziness or fainting.
MedlinePlus notes that symptoms of toxin spread can appear hours to weeks after an injection, so these signs matter even if the session was some time ago.
Call your clinician within a day or so, without emergency urgency, if you notice:
- An uneven smile or a mouth corner that does not lift fully.
- A lump that appears when you clench, or one side looking noticeably different from the other after the settling period.
- Persistent dry mouth or a change in saliva.
- Increasing pain, redness, warmth or swelling at the injection sites rather than gradual improvement, which could suggest infection.
- Difficulty chewing that is interfering with eating rather than just making tough foods tiring.
- Any new symptom you did not expect and cannot explain.
Keep the contact details you were given at the appointment somewhere you can find them. Reporting a problem early gives the treating team the best chance to assess it, and it also helps them refine how they treat you and others in future. Every decision about what to do next, including whether to repeat, adjust, or stop treatment, rests with them after they have examined you.
Frequently asked questions
How painful is masseter Botox?
Most people describe it as a brief pinch followed by a dull pressure, and Mayo Clinic notes that botulinum toxin injections generally cause little discomfort. The skin over the masseter is relatively thick and less sensitive than the forehead. Mild tenderness at the injection sites for a day or two is common, and numbing cream or a cold pack can be offered if you are anxious about needles.
How long does masseter Botox last?
NHS guidance states that the effects of botulinum toxin injections usually last around three to four months before muscle activity gradually returns, and Mayo Clinic describes three months or longer depending on the area treated. In a strong chewing muscle the return of bulk depends on how heavily it is used, so individual timelines vary, and your clinician will assess this at review.
Is there a downside to masseter Botox?
Yes. Beyond bruising and tenderness, area-specific risks include an uneven smile if medicine reaches nearby muscles, a lump when clenching, cheek hollowing or jaw sagging in some people, and dry mouth if the parotid gland is affected. It is off-label, temporary and requires repetition. MedlinePlus also notes a rare risk of toxin spreading to cause swallowing or breathing difficulty.
What are the most common masseter botox side effects?
The most frequent effects are minor and short-lived: pinpoint bruising, tenderness or swelling at the injection sites, headache, and mild chewing fatigue as the muscle weakens. NHS and Mayo Clinic list these for botulinum toxin injections generally. Less common but more noticeable are smile asymmetry and uneven contour, both of which usually resolve as the treatment wears off.
How does a clinician find the masseter muscle before injecting?
They ask you to clench your teeth so the muscle bulges, then palpate its borders: the lower jawbone below, the palpable front edge, and the area in front of the ear behind. They mark a safe zone beneath a line from the tragus of the ear to the corner of the mouth and place injections in the thickest lower portion of the muscle.
Does masseter botox for jaw clenching work?
For some people, and the evidence is limited. Mayo Clinic lists botulinum toxin among options for severe bruxism that has not responded to other treatments, while the NIH’s National Institute of Dental and Craniofacial Research notes that many treatments for jaw disorders lack rigorous testing. A fitted night guard remains a first-line way to protect teeth, and any decision sits with your clinician and dentist.
What does masseter botox aftercare involve on the first day?
NHS guidance advises avoiding rubbing or massaging the treated area, strenuous exercise, alcohol, and heat such as saunas or sunbeds on the day of botulinum toxin injections, to limit bruising and spread. Many clinicians also suggest staying upright for a few hours. Normal daily activities can usually resume immediately, and your clinician’s specific instructions take priority.
When will I see results from the masseter botox procedure?
Mayo Clinic notes botulinum toxin begins working within about one to three days, with the full effect taking a week or more, and NHS guidance describes two to three weeks for full effect. In the masseter, the muscle relaxes first and the visible slimming follows as it shrinks from reduced use, so the jawline change is judged at a follow-up review rather than in the first few days.
Can masseter Botox change the shape of my face permanently?
No. Botulinum toxin blocks nerve signals temporarily, and MedlinePlus and NHS guidance describe effects that wear off over months as nerve endings recover. Bone is unaffected, so a jaw that is wide because of the mandible itself does not change. A muscle relaxed repeatedly over time may rebuild more slowly, but the effect has no permanent phase and strength returns after stopping.
Who should not have masseter Botox?
MedlinePlus and NHS guidance advise against botulinum toxin injections during pregnancy or breastfeeding, in people with neuromuscular conditions such as myasthenia gravis, where there is infection at the injection site, and in anyone allergic to the product. Some medicines can increase its effect, so the prescriber reviews your full list. The final decision rests with the clinician who examines you.
References
- NHS: Botox injections (non-surgical cosmetic procedures)
- MedlinePlus: OnabotulinumtoxinA injection
- Cleveland Clinic: Botulinum toxin injections
- NIH National Institute of Dental and Craniofacial Research: TMD (Temporomandibular Disorders)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Is Surgical Tattoo Removal an Option for You? Size, Location and Skin Elasticity Explained
Yes, tattoos can be surgically removed, but excision suits a narrow group: small to medium tattoos on areas with loose, elastic skin, in people…

Fibroblast Plasma Skin Tightening Results: What Changes, How Gradually and How Long It Lasts
Fibroblast plasma treatment results tend to be modest and gradual rather than dramatic. Small dark crusts usually lift within one to two weeks, pinkness…

How Long Does a Thread Lift Last? Honest Longevity and Who It Suits
A thread lift typically lasts one to three years, depending on the suture material, your age, skin quality, and how much lift was attempted.…

Preparing for Microsurgery: Imaging, Fitness for Anesthesia and Specialist Consultations
Preparing for microsurgery usually means three things running in parallel: imaging such as CT angiography or Doppler ultrasound to map the tiny blood vessels…
Recovery After Retinal or Glaucoma Laser Treatment: Blurry Hours, Follow-Up and Milestones
After most retinal or glaucoma laser treatments, vision is blurry or dazzled for a few hours, mainly because of dilating drops, the bright treatment…

Flap or Graft? How Reconstructive Surgeons Choose Between the Two Ways to Rebuild Tissue
A skin graft is tissue detached completely from one site and laid onto a wound, where it must grow a new blood supply from…