

Living With a Cardiometabolic Disorder: What Regular Monitoring Visits Actually Track

Key Takeaways
- A1c reflects average blood sugar over about the past three months, so it is usually rechecked at least twice a year and about every three months when treatment is being adjusted.
- The American Heart Association classes 130–139 systolic or 80–89 diastolic as stage 1 hypertension and anything above 180 and/or 120 mm Hg as a crisis needing prompt care.
- Metabolic syndrome is identified when three of five features are present: large waist, high triglycerides, low HDL, blood pressure of 130/85 or higher, and fasting glucose of 100 mg/dL or higher.
- High triglycerides paired with low HDL on a lipid panel is a signature of insulin resistance and can prompt a closer look at blood sugar even when A1c is still normal.
- Yearly kidney tests, a dilated eye exam and a foot check protect organs that give no early warning; an eGFR below 60 lasting three months or more may indicate kidney disease.
- Home blood pressure readings are most useful with an upper-arm cuff, a few minutes of quiet sitting first, two readings a minute apart, and the device brought to a visit for comparison.
Regular monitoring visits for a cardiometabolic disorder track a small set of linked measures: blood pressure, blood sugar (usually A1c), a cholesterol panel, weight and waist size, and markers of kidney and liver health. Clinicians compare each result with your previous ones, not just against a cutoff, to judge whether current habits and any prescribed treatment are keeping combined heart and metabolic risk on a steady course.
The appointment letter lists five tests, two of them abbreviations she has to look up. She has been living with a cardiometabolic disorder for three years now, long enough to know the routine, yet not long enough to feel she understands why the same handful of numbers gets pulled again and again when she feels perfectly fine.
That gap between feeling fine and being measured anyway is the whole point of these visits. High blood pressure, rising blood sugar and drifting cholesterol rarely announce themselves. They move quietly, in the background, and they tend to move together. A monitoring visit is a way of catching drift early, while it is still a conversation rather than an emergency.
This explainer walks through what each measurement is for, how often it is usually repeated, what your care team is comparing it against, and which changes at home genuinely nudge the results. Every decision about treatment stays with the clinicians who know your history.
What does living with a cardiometabolic disorder mean day to day?
A cardiometabolic disorder is an umbrella term for conditions in which the way the body handles sugar, fat and blood pressure overlaps with the health of the heart and blood vessels. Type 2 diabetes, prediabetes, high blood pressure, unhealthy cholesterol patterns, metabolic syndrome and excess weight around the middle all sit under it. Clinicians group them because they share causes, feed one another and are checked with the same tests.
Most people carrying one of these labels will not feel different from one week to the next. That is why the phrase “living with” is more accurate than “suffering from” for many. The condition shows up in lab reports long before it shows up as symptoms, and the practical work is mostly ordinary: paying attention to meals, moving regularly, sleeping enough, and turning up for checks.
Metabolic syndrome is the clearest example of how the pieces fit together. According to Mayo Clinic, it is identified when at least three of five features are present: a large waist (about 35 inches or more in women, 40 inches or more in men), raised triglycerides, low HDL cholesterol, blood pressure of 130/85 mm Hg or higher, and a fasting blood sugar of 100 mg/dL or higher. Each feature alone is a modest concern; together they multiply.
Living with a cardiometabolic disorder, then, is less about a single disease and more about keeping a cluster of measurements in range over years. Monitoring visits are the scaffolding for that. They turn a vague sense of “trying to be healthier” into something you and your care team can actually see.
What actually happens at a monitoring visit?
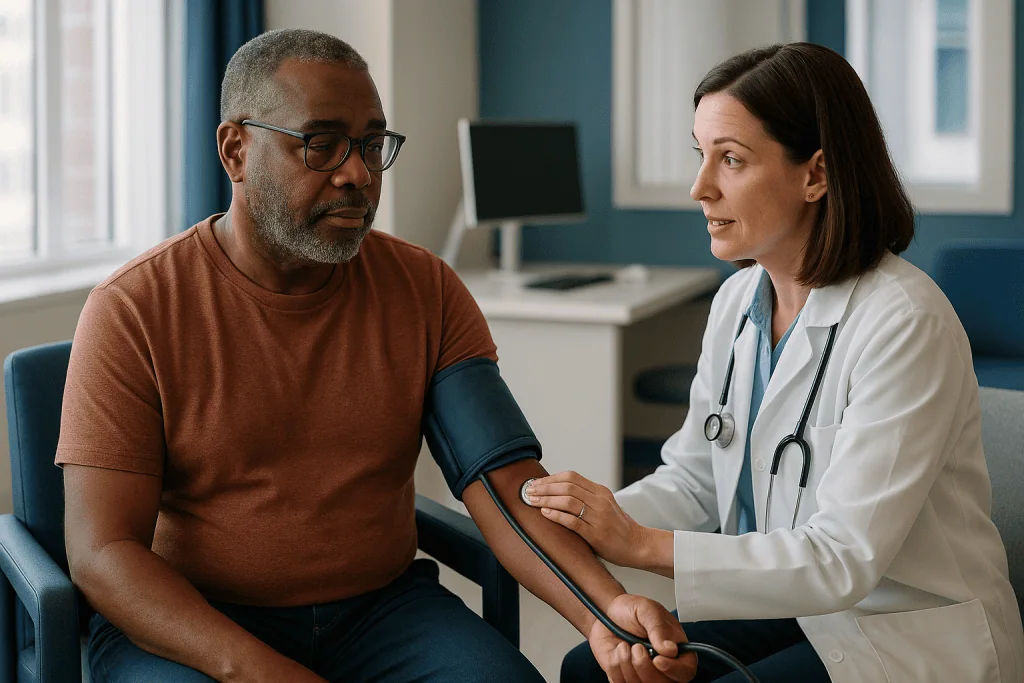
Picture the visit in three layers. The first is what a nurse or assistant does in the opening minutes: blood pressure, pulse, weight, sometimes a waist measurement and a quick foot check if diabetes is part of your picture. These are cheap, fast and repeated every time precisely because trends matter more than any single reading.
The second layer is blood and urine. A phlebotomist draws a sample, or you may have done this a few days earlier so results are ready. Typical panels include A1c (a measure of average blood sugar), a lipid panel (total cholesterol, LDL, HDL and triglycerides), kidney function (creatinine and estimated GFR), a urine test for albumin (a protein that leaks when kidney filters are stressed), and liver enzymes. Not every test is run at every visit; the schedule depends on your conditions and how stable the previous results were.
The third layer is the conversation. Your clinician places the new results beside the last two or three sets and looks for direction. Is LDL creeping up despite the same routine? Has A1c settled after a change in eating patterns? Are home blood pressure readings agreeing with the clinic cuff? This is also when side effects, missed doses, life events and sleep get discussed, because each can explain a shift in the numbers.
Nothing in that visit is a verdict. A single high reading is a prompt to recheck, not a diagnosis. The National Institute of Diabetes and Digestive and Kidney Diseases frames the core targets as the diabetes “ABCs”: A1c, blood pressure and cholesterol, plus not smoking. Most monitoring visits, whatever the specific label, orbit those same points.
Why is blood pressure checked at every visit?
Blood pressure is the one measurement almost nobody skips, and for good reason. It is the force of blood against artery walls, written as two numbers: systolic (pressure when the heart beats) over diastolic (pressure between beats). It changes minute by minute with stress, caffeine, pain and a full bladder, which is why one reading tells you little and a series tells you a lot.
The American Heart Association groups readings into ranges. Normal is below 120/80 mm Hg. “Elevated” is a systolic of 120 to 129 with a diastolic under 80. Stage 1 hypertension is 130 to 139 systolic or 80 to 89 diastolic. Stage 2 is 140 or higher, or 90 or higher. A reading above 180 and/or 120 is classed as a hypertensive crisis and needs prompt medical attention.
Those cutoffs are useful, but your clinician is really watching the trajectory. A person whose readings have hovered at 128/78 for two years and then climbs to 142/88 has more to discuss than someone who has always run at 135/85 and stays there. Context also matters: kidney health, age, diabetes and existing heart disease all shape what a comfortable target looks like for you, and that target is set by your care team.
Technique is half the battle. Sitting quietly for a few minutes first, feet flat, arm supported at heart level, no talking, and a cuff that fits your arm can shift a reading by several points. If your clinic number is consistently higher than what you see at home, that pattern itself is worth mentioning; it is common enough to have a name, white-coat hypertension, and it changes how the readings are interpreted.
What does A1c measure, and why do the numbers lag?
A1c, also called hemoglobin A1c or glycated hemoglobin, measures how much sugar has attached itself to the hemoglobin in your red blood cells. Because those cells live for roughly three months, the test reflects average blood sugar over that stretch rather than the moment the needle goes in. MedlinePlus describes it as a picture of the past three months, which is why a good week before the appointment will not rescue a poor quarter.

The reference ranges are consistent across major sources. A result below 5.7 percent is considered normal; 5.7 to 6.4 percent points to prediabetes; 6.5 percent or higher on two separate tests is used to diagnose diabetes, according to MedlinePlus. For people already living with diabetes, the individual goal is set by the care team and may sit higher or lower depending on age, other conditions and the risk of low blood sugar.
How often it is repeated depends on stability. MedlinePlus notes that people with diabetes are typically tested at least twice a year, and more often, about every three months, when treatment has changed or sugar levels are not yet where the team wants them. The three-month spacing is not arbitrary; testing sooner simply re-measures the same red cells.
A1c has limits worth knowing. Anemia, some hemoglobin variants, recent blood loss and pregnancy can push the result up or down independently of actual sugar levels. That is why a clinician may pair it with a fasting glucose or, for some, data from a continuous glucose monitor. If your A1c and your home readings seem to disagree, say so. The mismatch is information, not a failure on your part.
What does a lipid panel tell your care team?
A lipid panel is a blood test that measures the fats circulating in your bloodstream. It usually reports four things: total cholesterol, LDL cholesterol (the type that deposits in artery walls, often called “bad”), HDL cholesterol (which carries cholesterol away, often called “good”), and triglycerides (a fat the body stores and burns for energy). Some labs add non-HDL cholesterol, a simple subtraction that captures all the artery-clogging particles in one number.
MedlinePlus lists the general ranges. Total cholesterol under 200 mg/dL is considered desirable, 200 to 239 borderline high, and 240 or above high. LDL under 100 is optimal. HDL of 60 or higher is regarded as protective, while below 40 in men or 50 in women counts as a risk factor. Triglycerides under 150 are normal, 150 to 199 borderline high, and 200 or above high.
Here is where cardiometabolic thinking earns its name. High triglycerides paired with low HDL is a signature pattern of insulin resistance, the state in which cells respond sluggishly to insulin and the body compensates by making more. Seeing that pattern on a lipid panel can prompt a closer look at blood sugar even when A1c is still in the normal range. The tests inform one another.
Frequency is individualized. MedlinePlus suggests healthy adults may be checked every four to six years, but that interval shortens considerably for anyone with diabetes, heart disease, high blood pressure or a treatment that is being adjusted. Many teams recheck lipids alongside A1c so the two can be read together. Fasting used to be routine before the draw; many labs now accept non-fasting samples, though your clinic will tell you which it prefers.
Which organs are checked quietly: kidneys, liver, eyes and waistline
Some of the most consequential tests at a monitoring visit are the ones people rarely ask about. Kidneys sit at the top of that list. High blood sugar and high blood pressure both damage the tiny filters inside the kidney over years, and the damage is silent until it is advanced. Two tests catch it early: estimated GFR, a calculation from blood creatinine that estimates how well the kidneys filter, and urine albumin, which detects small amounts of protein slipping through. MedlinePlus notes that a GFR of 60 or higher is in the normal range, and that a level below 60 persisting for three months or more may indicate kidney disease. The NIDDK lists kidney testing among the checks people with diabetes should have at least yearly.
The liver enters the picture because fat accumulates there in many people with insulin resistance, a condition now called metabolic dysfunction-associated steatotic liver disease. Routine liver enzymes can hint at it, though normal enzymes do not rule it out, so some clinicians add imaging when risk is high.
Eyes and feet belong to the diabetes side of the family. A dilated retinal exam looks for damage to the small vessels at the back of the eye; a foot check looks for reduced sensation and skin changes. The NIDDK includes both on its list of yearly checks for people with diabetes.
The tape measure completes the set. Waist circumference is a better proxy for visceral fat, the metabolically active fat around the organs, than body weight alone. Mayo Clinic uses about 40 inches in men and 35 inches in women as the metabolic syndrome threshold. Weight can stay flat while waist shrinks with regular activity, and that shift counts.
How often is each test repeated? Metabolic syndrome monitoring at a glance
Schedules are not carved in stone. They flex with how stable your last results were, whether anything in your treatment has changed, and which conditions you carry. The table below gathers the typical rhythms that mainstream sources describe, so you can see the shape of a year rather than a single appointment. Your own team may test more or less often, and their schedule takes precedence.
| Measurement | What it reflects | Typical rhythm | Source |
|---|---|---|---|
| Blood pressure | Force on artery walls; stroke, heart and kidney risk | Every visit, plus home readings if advised | NIDDK, AHA |
| A1c | Average blood sugar over about three months | At least twice a year; about every three months if treatment is changing or targets unmet | MedlinePlus |
| Lipid panel | LDL, HDL, triglycerides; artery-clogging load | Every 4–6 years in healthy adults; considerably more often with diabetes, heart disease or treatment changes | MedlinePlus |
| Kidney function (eGFR, urine albumin) | Filtering capacity and early filter damage | At least yearly with diabetes | NIDDK, MedlinePlus |
| Dilated eye exam | Small-vessel damage at the back of the eye | Yearly with diabetes | NIDDK |
| Foot exam | Sensation, circulation, skin integrity | Yearly with diabetes; brief check at visits | NIDDK |
| Weight and waist | Visceral fat and overall trend | Every visit | Mayo Clinic |
Two patterns stand out. First, the blood-pressure cuff and the scale appear at every visit because they cost nothing and reveal drift fastest. Second, the yearly items are the ones that protect organs you cannot feel. Missing one dilated eye exam rarely matters; missing three in a row can.
If you are unsure which rhythm applies to you, ask for it in writing. A simple one-page schedule from your team turns a bewildering series of appointments into a plan you can actually follow.
Who needs closer monitoring, and who is usually asked to wait?
Not everyone with a cardiometabolic label is watched at the same intensity, and that is deliberate. Closer, more frequent checks are typically arranged for people whose results are outside target, whose treatment has recently changed, who have more than one condition stacking together, or who already show signs of organ involvement such as reduced kidney function or protein in the urine. Pregnancy, a recent heart event, and a new diagnosis also tend to pull visits closer together for a while.
Frequent review in these situations is not a sign that things are going badly. It is how a team confirms that a change is doing what they hoped and catches side effects early. The A1c pattern described by MedlinePlus is a good model: about every three months during adjustment, then relaxing to twice a year once things settle.
At the other end, people whose numbers have been steady for a long stretch, who are on unchanged treatment and feel well, are often asked to space visits out. Being told to come back in six months rather than three can feel like being left alone, but it usually reflects confidence. The trade-off is real, though: longer gaps mean any drift has more time to develop before it is seen, which is why home monitoring often fills the space between.
Some people are asked to wait for a different reason: a result needs repeating before it means anything. A single raised blood pressure reading, one A1c just over a threshold, or an eGFR that dipped during an illness are all examples where guidelines expect confirmation. MedlinePlus is explicit that a diabetes diagnosis rests on two separate A1c results. Waiting for the second test is not delay; it is the method.
Where you fall on this spectrum is a clinical judgment made by your treating team, and it will shift over time as your results do.
How do medicines fit into monitoring, and what do the tests actually show?
Medicines are a frequent reason monitoring visits happen at all. When a clinician prescribes something for blood pressure, cholesterol or blood sugar, the follow-up tests serve two purposes: to see whether the intended effect has arrived, and to check for the specific side effects that class is known for. Understanding the mechanism makes the tests make sense.
Statins reduce the liver’s production of cholesterol, so the lipid panel is the natural check, and liver enzymes are sometimes reviewed early on. Metformin lowers the amount of sugar the liver releases and improves the body’s response to insulin, so A1c is the readout, with kidney function checked because clearance depends on it. ACE inhibitors and angiotensin receptor blockers relax blood vessels and reduce pressure inside the kidney’s filters; blood pressure, potassium and creatinine are the usual companions. SGLT2 inhibitors cause the kidneys to pass more sugar into the urine; A1c, kidney function and hydration are watched. GLP-1 receptor agonists mimic a gut hormone that slows digestion and increases insulin release after meals; weight, A1c and digestive tolerance come up at review.
Timelines differ by class. A1c, as MedlinePlus explains, reflects a three-month window, so any glucose-lowering change is judged at that horizon rather than the next week. Blood pressure treatment is usually assessed against a run of readings over the following weeks. None of these are promises about how much any number will move; they are the intervals at which the test can meaningfully answer the question.
Nothing here is a recommendation to start, stop or alter anything. Which class fits you, whether it fits at all, and when to reassess are decisions for the prescribing clinician who can weigh your full history. The monitoring visit is where that conversation happens with data on the table.
What do the weeks between visits usually look like, including home blood pressure monitoring?
The interval between appointments is where most of the work of living with a cardiometabolic disorder actually happens, and it is quieter than people expect. For many, the routine settles into a few anchors: a home blood pressure reading at roughly the same time on set days, a glucose check if that is part of the plan, a weekly weigh-in, and attention to the things that move the numbers.
Home blood pressure monitoring deserves a word because it is so often done imprecisely. The American Heart Association recommends an upper-arm cuff over a wrist device, a few minutes of quiet sitting first, back supported, legs uncrossed, arm resting at heart level, and no smoking, caffeine or exercise in the half hour before. Two readings a minute apart, recorded with the date and time, give your clinician far more to work with than a single anxious check after a stressful commute. Bring the device to a visit so it can be compared with the clinic cuff.
Glucose checks at home, where advised, work best when tied to a question: what happens after this particular meal, or on the mornings after poor sleep. Random checks without context are harder to interpret. A continuous glucose monitor, where used, gives a fuller picture of overnight and post-meal patterns.
Then there is the ordinary fabric of the weeks. Planning meals around vegetables, whole grains and lean protein; walking most days; keeping alcohol modest; protecting sleep. None of this needs to be perfect. What your team wants at the next visit is not a confession but a pattern they can read. Keeping a short log, even a few lines a week about what changed and how you felt, turns the follow-up conversation from guesswork into detective work.
Living with cardiometabolic disorder: which habits move the numbers most?
Ask a clinician what moves blood pressure, blood sugar and lipids at the same time, and the answer is refreshingly short. Regular physical activity, a diet built around whole foods with less sodium and less added sugar, adequate sleep, and not smoking each act on all three. That overlap is why lifestyle sits at the base of every major guideline for these conditions, from the diabetes “ABCs” framed by the NIDDK to the components of metabolic syndrome described by Mayo Clinic.
Movement has a particularly direct mechanism on blood sugar. Working muscle pulls glucose out of the bloodstream with less dependence on insulin, which is why a walk after a meal blunts the spike. Over months, regular activity improves insulin sensitivity, raises HDL, lowers triglycerides and lowers resting blood pressure. It also trims the visceral fat that the waist measurement tracks, often before the scale notices.
Sodium is the lever for blood pressure that most people underestimate, largely because most of it arrives in processed and restaurant food rather than from the shaker. Reading labels for a few weeks is often eye-opening. Sugar-sweetened drinks are the parallel lever for triglycerides and A1c: liquid sugar arrives fast and in volume.
Sleep and stress are less glamorous but measurable. Short or fragmented sleep raises cortisol and next-day glucose and nudges blood pressure upward; untreated sleep apnea, common in people with a larger waist, does the same and is worth raising if you snore heavily or wake unrefreshed.
Smoking cessation is the single change with the largest effect on heart and vessel risk, which is why it appears as the “S” in the NIDDK’s framing. If you smoke, your care team can talk through support options; that conversation belongs at a monitoring visit as much as any lab result.
What people often get wrong about monitoring visits
The most common misunderstanding is that a normal-range result means the condition has gone away. It has not. A cardiometabolic disorder is managed, not removed; the good result means the current approach is working, and stopping the approach usually brings the numbers back. This applies equally to a lifestyle routine and to a prescribed medicine, and any change to either belongs in a conversation with your team, not a unilateral decision on a good lab day.
A second myth is that you can “study for the test.” A few days of clean eating before the draw does nothing to A1c, which MedlinePlus explains reflects three months of red cell history, and does little to LDL. Fasting for the lipid panel, if your lab asks for it, changes triglycerides but not your underlying pattern. The visit is not an exam; honest data is the only useful kind.
People also tend to read single numbers as verdicts. One blood pressure reading in the stage 1 range on a rushed morning, or an A1c a tenth of a point over a threshold, is a prompt to confirm, which is exactly what guidelines require. Panic and complacency are both misreadings of the same fact: one data point is a question, not an answer.
Then there is the belief that feeling well means the monitoring is unnecessary. Kidney filters, retinal vessels and coronary arteries do not send early warnings. The whole logic of yearly organ checks is that damage is reversible or slowable only in the window before symptoms appear.
Finally, some assume that the goal is the lowest possible number. It is not. Targets are individualized, and for some people, pushing blood sugar or blood pressure too low carries its own risks. The right range is the one your treating team sets for you.
Questions to ask your care team
A monitoring visit works best as a two-way exchange, and a few well-aimed questions can turn a hurried review into a plan you understand. Bring them written down; appointments move fast and the important ones evaporate at the door.
- Which of my numbers are you most focused on this year, and why that one rather than the others?
- What is my personal target for blood pressure, A1c and LDL, and how does it differ from the general ranges I read about?
- How do today’s results compare with my last two or three sets? Is anything trending, even if it is still in range?
- Which tests will be repeated at the next visit, and how far away should that visit be?
- When was my last kidney test, urine albumin, dilated eye exam and foot check, and are any due?
- If I am taking medicines, what exactly is each one meant to do to these numbers, and which side effects should prompt a call between visits?
- Is home blood pressure monitoring useful for me, and if so, how often and at what times of day would you like readings?
- Which one or two lifestyle changes would you expect to move my results the most given what you see today?
- Is there anything in my sleep, mood or stress that you think is affecting these results?
- Who do I contact, and how quickly, if a home reading looks very high or very low?
Ask, too, for a copy of your results. Watching your own trend across several visits is one of the more motivating things a person living with a cardiometabolic disorder can do, and it makes the next conversation sharper. If an answer is unclear, say so and ask for it in plain words; that request is always reasonable.
When to call your doctor
Most of what monitoring visits track unfolds slowly, and the right response to a slightly high reading is a recheck, not alarm. Certain signs, though, do not belong on a waiting list for the next scheduled appointment. Knowing them is part of living safely with these conditions.
Seek emergency care immediately for chest pain or pressure, pain spreading to the arm, jaw or back, sudden shortness of breath, sudden weakness or numbness on one side of the body, facial drooping, slurred speech, sudden confusion, sudden severe headache, or loss of vision in one or both eyes. These can indicate a heart attack or stroke, the very events this whole framework exists to prevent.
The American Heart Association classes a blood pressure reading above 180 and/or 120 mm Hg as a hypertensive crisis. If you see that on a home monitor, wait a few minutes and recheck; if it is still that high, or if it is accompanied by chest pain, breathlessness, back pain, numbness, weakness, vision change or trouble speaking, call emergency services rather than your clinic.
Contact your care team the same day for signs of very low blood sugar that do not settle with treatment you have been shown to use, such as confusion, shakiness or sweating; for very high blood sugar with excessive thirst, frequent urination, nausea or vomiting; for a new foot wound, redness or a sore that is not healing; for sudden swelling of the legs or face; or for any new eye floaters, blurring or dark patches.
Call within a few days, without waiting for the routine visit, if home readings are consistently outside the range your team set, if you suspect a medicine is causing side effects, or if something in your life has changed enough to affect your plan. Your treating team decides what to do next; your job is simply to make sure they know.
Frequently asked questions
What are the main cardiometabolic risk factors doctors monitor?
The core set is blood pressure, blood sugar (usually A1c), LDL and HDL cholesterol, triglycerides, waist circumference and weight, plus kidney function and urine albumin. Smoking status, sleep and physical activity are asked about because they influence all of the above. Clinicians track these together because each one raises heart and vessel risk on its own and they tend to worsen in clusters.
What does A1c measure and why is it only tested every three months?
A1c measures the percentage of hemoglobin in red blood cells that has sugar attached, giving an average blood sugar over about three months, the lifespan of those cells. Testing sooner mostly re-measures the same cells, so it adds little. MedlinePlus describes at least twice-yearly testing for people with diabetes, and roughly every three months when treatment is changing or targets are not yet met.
How often should cholesterol be checked if I have a cardiometabolic disorder?
More often than the general population. MedlinePlus suggests healthy adults may be checked every four to six years, but that interval shortens considerably for anyone with diabetes, high blood pressure, heart disease or a treatment being adjusted. Many care teams recheck lipids alongside A1c so both can be read together. Your clinician sets the interval based on your results and how stable they have been.
Is home blood pressure monitoring worth doing between visits?
For many people, yes, because a series of readings in your own environment shows patterns a single clinic check cannot. The American Heart Association recommends an upper-arm cuff, quiet sitting first, back and arm supported, and two readings a minute apart recorded with the time. Bring the monitor to an appointment to compare it with the clinic cuff, and ask your team how often they would like readings.
What does metabolic syndrome monitoring involve compared with diabetes monitoring?
They overlap heavily. Metabolic syndrome monitoring focuses on the five defining features: waist size, triglycerides, HDL, blood pressure and fasting glucose. Diabetes monitoring adds A1c as the central sugar measure and layers in yearly kidney tests, a dilated eye exam and a foot check because high sugar damages those organs over time. Someone with both conditions will typically have the combined set.
Why does my clinician measure my waist when I already stand on the scale?
Waist circumference estimates visceral fat, the metabolically active fat around the organs that drives insulin resistance and inflammation. Weight cannot distinguish that fat from muscle or from fat stored elsewhere. Mayo Clinic uses about 40 inches in men and 35 inches in women as the metabolic syndrome threshold. Waist can shrink with regular activity even when the scale barely moves, and that change is meaningful.
Can a good result mean I can stop treatment?
A good result means the current approach is working, not that the condition has gone. Cardiometabolic disorders are managed over years, and stopping a routine or a prescribed medicine usually lets the numbers drift back. Any change to treatment belongs in a conversation with your prescribing clinician, who can weigh your full history and decide whether adjustment is appropriate and how to monitor it.
What kidney tests are done and what do the numbers mean?
Two tests are standard: estimated GFR, calculated from blood creatinine to estimate how well the kidneys filter, and a urine albumin test that detects small amounts of protein leaking through stressed filters. MedlinePlus notes a GFR of 60 or higher is in the normal range, and a level below 60 persisting for three months or more may indicate kidney disease. The NIDDK lists kidney testing among yearly checks for people with diabetes.
Do I need to fast before my monitoring blood tests?
It depends on which tests are ordered and your lab’s practice. A1c does not require fasting. Many labs now accept non-fasting lipid panels, though triglycerides are affected by recent meals and some clinicians still prefer a fasting sample. A fasting glucose, by definition, requires it. Your clinic will tell you what to do; if the instructions are unclear, call before the appointment rather than guessing.
What should I do if one reading is just over a threshold?
Treat it as a question to confirm, not a verdict. Guidelines expect repeat testing before a diagnosis is made; MedlinePlus is explicit that a diabetes diagnosis rests on two separate A1c results, and blood pressure categories rely on a pattern of readings rather than one. Note the result, keep your routine steady, and let your care team decide whether to recheck sooner or wait for the next scheduled visit.
References
- MedlinePlus – A1C Test
- MedlinePlus – Cholesterol Levels: What You Need to Know
- NIH NIDDK – Managing Diabetes
- MedlinePlus – Glomerular Filtration Rate (GFR) Test
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Permanent Pacemaker Recovery: Why Your Arm Stays Below Shoulder Level for Several Weeks
After a permanent pacemaker is implanted, most people are asked to keep the arm on the device side below shoulder height for roughly four…

The First 48 Hours After Carotid Angiography: Rest, Fluids and the Lifting Limit
After a carotid angiogram, most people lie flat for a few hours while the puncture site seals, drink extra fluids to help the kidneys…

What Coronary Angiography Results Lead To: Medication, Angioplasty, Stenting or Surgery
Coronary angiogram results usually lead to one of three paths: medication and risk-factor control when narrowings are mild or stable; angioplasty with a stent…

When Is an Aortic Problem Watched, Medicated or Repaired? How Doctors Decide the Path
Doctors decide by asking three questions: is the problem a bulge (aneurysm) or a tear (dissection), where on the aorta does it sit, and…

Comparing Heart Rhythm Disorder Treatments: Medication, Ablation or a Device?
The main types of arrhythmia treatment are medicines that slow or steady the heartbeat or lower stroke risk, catheter ablation that scars the small…

Pacemakers and Defibrillators in Cardiac Sarcoidosis: When a Device Becomes Part of Care
An ICD, an implantable cardioverter-defibrillator, is usually considered in cardiac sarcoidosis when someone has survived a dangerous ventricular rhythm, has a weakened heart pump…