

Microsuction or Irrigation for Earwax Build Up: Which Does Your ENT Recommend and Why?
Key Takeaways
- Earwax is protective and self-clearing; guidance from the NHS, Mayo Clinic and Cleveland Clinic is to remove it only when it blocks the canal or causes symptoms.
- Microsuction removes wax under direct magnified vision without water, which is why it is preferred when the eardrum may be perforated, after ear surgery, with grommets, or during infection.
- Modern irrigation uses an electronic low-pressure device with body-temperature water and remains a standard, widely available option for healthy ears with intact eardrums.
- No large head-to-head trial proves one method superior for everyone; the choice depends on your ear examination, history and what equipment is available.
- The NHS advises softening drops for roughly 3–5 days before irrigation, and in many people the wax then clears without any procedure.
- Cotton buds are a leading cause of impaction and ear candling has documented harms and no evidence of benefit, according to Mayo Clinic and the NHS.
Microsuction and irrigation both remove impacted earwax, and neither is right for everyone. Microsuction uses a small vacuum under direct magnified view and is usually preferred when the eardrum may be damaged, when there is an ear infection or previous ear surgery, or when the wax is very hard. Irrigation flushes the canal with body-temperature water and remains a reasonable option for healthy ears. Your ENT chooses based on your ear history, the wax itself, and what is available locally.
The waiting-room conversation goes something like this. One neighbor swears by the tiny vacuum the ear specialist used, over in minutes, no water anywhere near her head. The other had his ears “washed out” for years and never had a problem. Now you are the one with a muffled left ear, a feeling of a cotton ball lodged somewhere behind the jaw, and an appointment to weigh microsuction vs irrigation earwax removal.
Both methods have been around for decades. Both work. The interesting part is that ear, nose and throat clinicians do not pick between them by preference or fashion; they pick by looking at your ear canal, your eardrum and your medical history, then matching the tool to what they see.
Understanding that logic is what turns you from a passenger into a participant in the decision. So let us walk through what actually happens in each procedure, where the evidence is solid, where it is thin, and what to ask before anyone reaches for an instrument.
Why the microsuction vs irrigation earwax question comes up at all
Earwax is not dirt. Cerumen, the medical term for it, is a blend of skin cells, oil and sweat-gland secretions that coats the outer part of the ear canal, traps dust, discourages bacteria and keeps the skin from cracking. According to the NHS, it normally works its way outward on its own, helped by jaw movement when you chew and talk, and simply falls out unnoticed.
The trouble starts when production outpaces clearance. Narrow or unusually shaped canals, a lot of hair in the canal, hearing aids or earbuds that block the exit, ageing skin that produces drier wax, and the habit of pushing cotton buds inward all tilt the balance toward build-up. Mayo Clinic notes that attempts to clean the ear at home are one of the most common reasons wax ends up packed deep against the eardrum, where it was never meant to sit.
Once wax fully blocks the canal, sound cannot reach the eardrum properly. People describe muffled hearing, a plugged feeling, ringing, earache or a nagging itch. Mayo Clinic also lists dizziness and cough as occasional companions, because the canal shares nerve supply with the throat and balance structures.
This is the moment two very different tools come into view. Microsuction lifts the wax out with gentle suction while the clinician watches through a microscope or magnifying loupes. Irrigation, sometimes still called syringing, loosens and floats the wax out with a controlled stream of warm water. Each has a distinct safety profile, and that profile, not brand loyalty or habit, is what your ENT is weighing when they recommend one over the other.
What actually happens during microsuction
Microsuction is closer to a dental hygiene visit than to a medical procedure. You sit upright or lie on your side, the clinician gently straightens the canal by pulling on the outer ear, and a speculum, a small funnel-shaped viewing tube, is placed at the entrance. Under a binocular microscope or a headband magnifier with a bright light, the wax becomes clearly visible, along with the skin of the canal and, once the way is clear, the eardrum itself.
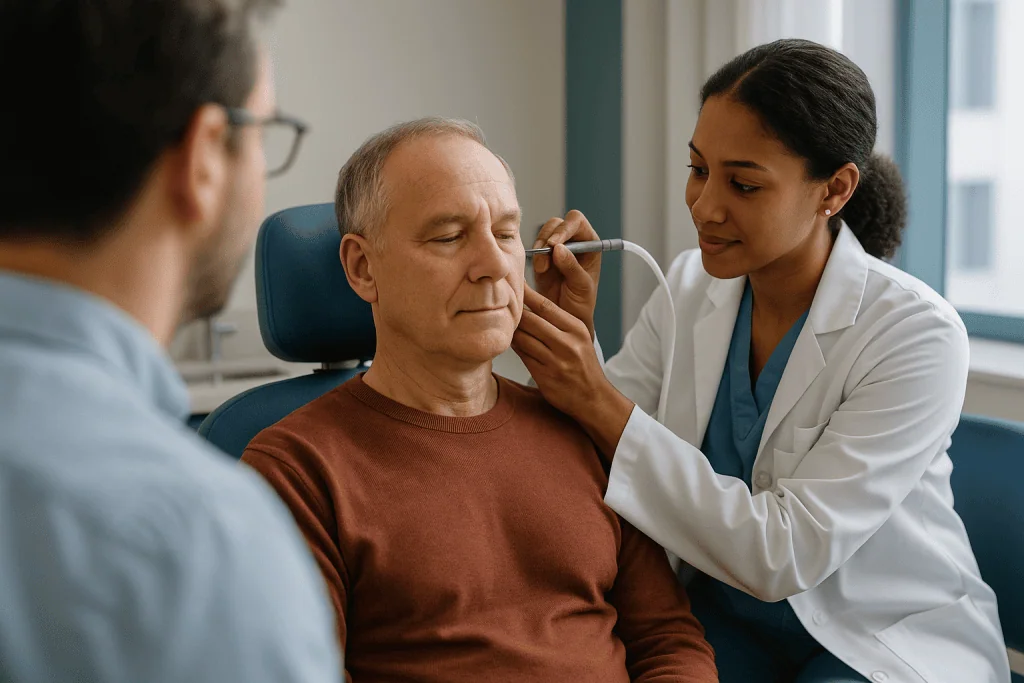
A fine suction tube, roughly the width of a drinking straw’s tip, is connected to a low-pressure pump. The clinician touches the wax with the tip and it is drawn into the tube in pieces. For stubborn plugs, small instruments such as a curette (a tiny scoop) or forceps may be used to lift a fragment before suction takes over. Cleveland Clinic describes this combination of visualization and manual removal as the standard approach in specialist settings.
Two sensations dominate the experience. The first is noise: the suction tube produces a whistling or crackling sound that is loud simply because it is inches from the eardrum. The second is the cold-air feel of moving air on the canal skin. Neither is harmful, but both catch people off guard, so a good clinician warns you before starting.
Because everything is done under direct vision, the clinician stops the instant they see the eardrum or a spot of irritated skin. That visibility is the reason microsuction is described as the safer choice when there is any doubt about the state of the eardrum. A typical session lasts a few minutes per ear, though very hard or deeply packed wax sometimes calls for a second visit after softening drops, a point we return to below.
What actually happens during ear irrigation (and how it differs from old-style syringing)
Irrigation works on a completely different principle: rather than pulling the wax out, it floats it out. Water at approximately body temperature is directed along the roof of the ear canal so that it flows behind the wax plug and pushes it forward toward the opening. A curved basin held below the ear catches the water and the fragments that come with it.
The word syringing survives in everyday speech, but modern practice has changed. The NHS explains that irrigation is now performed with an electronic irrigator that delivers a controlled, adjustable stream, replacing the large metal syringe of past decades that relied entirely on the operator’s hand pressure. The lower, steadier pressure is a meaningful safety step, because the eardrum is a membrane thinner than paper and does not tolerate sudden force.
The temperature detail matters more than most people expect. Behind the eardrum sits the inner ear, which houses both hearing and balance organs. Water that is noticeably warmer or cooler than the body sets up a temperature gradient across the balance canals and can trigger a brief but intense spinning sensation. Mayo Clinic and MedlinePlus both stress body-temperature water for exactly this reason.
Irrigation is generally well tolerated. You feel a rush of water, a sense of pressure, and often a sudden clearing of sound as the plug shifts. Some people need the process repeated a few times within the same appointment. The clinician then inspects the canal with an otoscope, a handheld lighted viewer, to confirm the wax has gone and the eardrum looks healthy. Unlike microsuction, that inspection happens after the fact rather than continuously, which is the crux of the comparison.
Microsuction vs irrigation earwax removal: the side-by-side view
Laid out side by side, the two approaches trade off visibility, equipment and comfort in ways that explain almost every recommendation an ENT makes.

| Feature | Microsuction | Irrigation |
|---|---|---|
| How wax is removed | Gentle suction and fine instruments under magnified direct vision | Body-temperature water flushed behind the plug to float it out |
| Clinician sees the canal during the procedure | Yes, continuously | No, inspection before and after |
| Water enters the ear | No | Yes |
| Usable with a perforated eardrum or grommets | Often yes, at clinician’s judgement | No; listed as a contraindication by Mayo Clinic and NHS |
| Usable with an active ear infection | Often yes | Generally avoided |
| Main sensations reported | Loud suction noise, cool air, occasional brief dizziness | Pressure, water sound, occasional dizziness if temperature is off |
| Pre-softening with drops | Helpful for hard wax, not always required | Usually recommended for several days first |
| Equipment and setting | Microscope or loupes, suction unit; typically specialist or trained nurse settings | Electronic irrigator; commonly available in primary care |
Read the table as a map of risk rather than a scorecard. Where the eardrum is intact, the ear is healthy and the wax is soft, both columns lead to the same destination, and the choice may reasonably come down to availability and your own comfort. Where anything about the eardrum is uncertain, the “sees the canal continuously” row does most of the deciding, and microsuction becomes the safer route.
The last row is often the deciding factor in the real world. The NHS points out that microsuction is not routinely available in every primary care setting, so a healthy ear with a straightforward plug may simply be offered irrigation first because it is on hand.
Is microsuction better than irrigation? What the evidence actually shows
The honest answer is that high-quality head-to-head trials are scarce. Most of what we know comes from observational studies, clinical experience and guideline consensus rather than large randomized comparisons. Harvard Health summarizes the position plainly: irrigation, manual removal and microsuction are all accepted methods, and no single technique has been proven clearly superior for every patient.
What the evidence does support is a set of situational advantages. Microsuction’s edge is safety in ears that cannot tolerate water. Because the clinician can see the eardrum throughout, the risk of unknowingly flushing water through a perforation into the middle ear, or of pushing a plug harder against a fragile membrane, is largely removed. That is why specialist guidance consistently reserves it for people with a history of perforation, ear surgery, grommets (small ventilation tubes placed in the eardrum) or chronic ear discharge.
Irrigation’s edge is practicality. It requires less specialized equipment, can be delivered by trained nurses in community settings, and for a healthy ear with softened wax it is effective in most cases within a single visit. MedlinePlus lists irrigation alongside manual removal as standard care.
Where the evidence is genuinely uncertain is on comfort and on completeness after one session. Small studies suggest people often prefer the dry approach of microsuction, and some report that irrigation leaves the ear feeling waterlogged for a while, but these findings are not consistent enough to be stated as fact. Your ENT’s recommendation, therefore, is less a verdict on which method wins and more a judgement about which method carries the smallest downside for your particular ear. Treat the phrase “microsuction is better” as shorthand for “microsuction is safer when the eardrum is in doubt,” and the comparison becomes far clearer.
Who is usually offered microsuction, and who is asked to wait
Clinicians tend to reach for microsuction first in a recognizable set of circumstances. Anyone with a known or suspected hole in the eardrum tops the list, along with people who have had ear surgery of any kind, those with grommets in place and those who currently have, or frequently get, an outer ear infection. In each of these situations, water in the canal is the hazard, and a dry technique sidesteps it entirely.
Very hard, dry wax that has resisted a course of softening drops is another common reason. Suction combined with a fine curette can remove pieces that water simply flows around. People with narrow or unusually curved canals, and hearing-aid users who need reliable, complete clearance to keep their devices working, are also frequently steered toward microsuction because the clinician can confirm the canal is truly empty.
Who is asked to wait? The most frequent answer is: anyone whose wax is not actually causing a problem. Mayo Clinic and Cleveland Clinic both note that wax that is not blocking the canal or producing symptoms does not need removing at all, and that unnecessary cleaning strips away a protective layer. An ENT who looks in and says “leave it” is not brushing you off; they are following the evidence.
Another group asked to pause are people whose wax is packed so tightly that suction would need to work against it for an uncomfortably long time. The NHS advises softening drops for several days before removal in this situation, so a first appointment may end with an instruction to return rather than with a cleared ear. Finally, a small number of people find the noise or the sensation of microsuction distressing, particularly children and some adults with sensory sensitivities. For them, a gentler pace, a second visit, or irrigation in a healthy ear may be the kinder choice.
Who irrigation suits, and when clinicians steer away from it
Irrigation is a good fit for the most common scenario of all: an adult with an otherwise healthy ear, an intact eardrum, no history of ear surgery, and a soft or pre-softened wax plug. In that setting it is effective, quick and widely available, and many people have it done periodically for years without incident.
The list of reasons to avoid it is short but firm. Mayo Clinic and the NHS both state that irrigation should not be used if there is a known perforation, if grommets are present, if there has been ear surgery, or if there is a current infection or discharge. Water reaching the middle ear through an opening in the drum can carry bacteria inward and set up a middle ear infection, and in some circumstances can cause lasting hearing damage.
A previous bad experience with irrigation, especially severe dizziness, pain or bleeding, is also a reason to choose a different method. So is a history of unexplained hearing loss in only one ear, because the clinician will want to protect the better-hearing side and may prefer the certainty of direct vision.
Children are a special case. Their canals are small, their eardrums are closer to the surface, and they may not hold still or report pain reliably. Many clinicians favor microsuction or manual removal in young children for those reasons, though a calm older child with a healthy ear can often have irrigation without difficulty.
People taking medicines that thin the blood do not have an absolute barrier to either procedure, but a clinician may prefer the controlled visibility of microsuction to minimize the chance of unnoticed bleeding from a scraped canal. As always, mention every medicine and every previous ear problem before the appointment starts; the decision belongs to the treating team, and it is only as good as the information they have.
Microsuction earwax removal risks: what can go wrong and how it is kept rare
No procedure that involves placing an instrument inside the ear canal is entirely without risk, and it would be dishonest to present microsuction as risk-free. The reassuring part is that the risks are mostly minor, mostly short-lived, and well understood.
The most frequently reported issue is temporary dizziness. The rapid movement of cool air across the canal produces the same small temperature shift that makes irrigation water feel disorienting. It usually settles within minutes once the suction stops. A brief increase in tinnitus, the ringing or buzzing sound in the ear, can follow the noise of the suction tube; for most people it fades within hours, though anyone with pre-existing tinnitus should mention it beforehand so the clinician can work at a gentler pace.
Minor scratches to the canal skin can occur, occasionally with a spot of blood, particularly when a curette is used on hard wax. These heal on their own. The canal skin is also slightly more vulnerable to infection for a few days after any instrumentation, which is why keeping the ear dry immediately afterwards is standard advice.
Rarer harms include damage to the eardrum and, exceptionally, a small drop in hearing attributed to the loud suction noise. Because the clinician is watching throughout, contact with the eardrum is far less likely than with a blind technique, which is the whole safety argument for the method. Cleveland Clinic advises that any removal involving instruments should be done only by a trained professional for exactly this reason.
Finally, there is the risk of incomplete clearance on the first attempt. This is not a complication so much as an expectation to manage: very compacted wax sometimes needs softening and a second session. A clinician who stops early to avoid pressing hard against a fragile canal is exercising good judgement, not failing at the job.
Ear irrigation side effects people actually report
Irrigation has a longer track record than microsuction, which means its side effects are well catalogued. Most are minor. A feeling of water trapped in the ear for a few hours is common and tends to resolve as the canal dries. A brief spell of dizziness during or immediately after the procedure is the next most familiar complaint, almost always linked to water that was slightly too warm or too cool. Mild discomfort or a dull ache for the rest of the day is also reported, especially when several passes were needed.
The less common but more consequential problems are the ones that shape clinical guidance. Otitis externa, an infection of the canal skin often called swimmer’s ear, can follow if the canal stays damp or was scratched. Perforation of the eardrum is uncommon with modern low-pressure irrigators but not impossible, particularly if the water is directed straight at the drum rather than along the canal wall, or if the drum was already thin or scarred. Mayo Clinic lists perforation, infection and, rarely, hearing loss among the possible complications.
A distinctive irrigation-specific issue is pushing the plug further inward. If the water cannot get behind the wax, the pressure can compact it against the eardrum, making the blockage worse and turning an easy job into a harder one. Pre-softening with drops for several days, as the NHS recommends, greatly reduces this problem by loosening the plug so water can pass around it.
People occasionally describe a cough during irrigation. That is a reflex, not a warning sign: a branch of the vagus nerve supplies both the ear canal and the throat, so stimulating one can tickle the other. Knowing this in advance saves a moment of alarm in the chair.
Do you need to soften the wax first, and how long does that take?
Softening drops are the unglamorous supporting act in almost every wax-removal story, and skipping them is one of the commonest reasons a first appointment ends without a cleared ear.
The idea is simple. Wax that has sat in the canal for weeks dries into a hard, sticky mass. Oily drops such as plain olive or almond oil work by lubricating the plug and the canal wall so the wax can slide outward. Water-based drops, often containing sodium bicarbonate or similar agents, work by drawing moisture into the wax and swelling it, which loosens the structure. Cerumenolytic is the technical word for a wax-softening agent; the term simply means “wax dissolver.”
The NHS advises using drops for several days, typically 3–5, before irrigation, and notes that in many people the wax then falls out on its own and no procedure is needed at all. Mayo Clinic gives a similar picture: softening alone, followed by gentle rinsing at home, resolves a meaningful share of uncomplicated blockages within a couple of weeks. Neither source promises this outcome, and neither should you expect it, but it is a legitimate first step for a healthy ear.
Two cautions apply. First, drops are not appropriate if there is any suspicion of a perforation, infection or discharge, because the liquid can reach the middle ear; Mayo Clinic is explicit on this point. Second, hearing often gets briefly worse while the wax swells and the plug becomes more complete before it loosens, which alarms people who were not warned.
Which drops, whether to use them at all, and for how long are decisions for your clinician, who has looked inside the ear and knows what the canal can tolerate. Do not choose a product based on a recommendation from a friend whose ears may be nothing like yours.
What the following days usually look like after either procedure
For most people, the aftermath is anticlimactic in the best way. Hearing typically returns to normal immediately or within a few hours, and the sudden clarity can be startling; sounds feel sharper and louder for a day or so while the brain recalibrates to the volume it had been missing. Some people notice their own voice sounds different for a short while.
After irrigation, the ear may feel damp or full for the rest of the day. Tilting the head and letting gravity do its work is usually enough. Clinicians generally advise keeping the canal dry for a day or two, which in practice means avoiding swimming and being careful in the shower, to reduce the chance of an outer ear infection while the skin recovers.
After microsuction, the ear is already dry, so the main after-effect is the occasional lingering awareness of the noise, or a brief increase in tinnitus that fades over hours. A small scratch may leave a faint pink tinge on a cotton wool plug the same day and nothing thereafter.
Mild soreness that eases over 24–48 hours is within the normal range for both methods. What is not normal is pain that worsens, discharge that appears after the first day, a fever, or hearing that was clear afterwards and then deteriorates again quickly. Those belong in the “call your doctor” category discussed later.
The longer timeline is about recurrence. Wax will come back; that is what ears do. The NHS notes that people who are prone to build-up may need periodic removal, while Cleveland Clinic emphasizes that between visits the best prevention is simply to stop inserting anything into the canal. Hearing-aid users are often advised to have the canal checked at routine device appointments so that a plug is caught before it interferes with sound.
What people often get wrong about earwax removal
Myths about earwax are stubborn, and several of them actively cause the blockages they claim to prevent.
The biggest is that ears need cleaning inside. They do not. The canal is self-cleaning, and cotton buds, hairpins, keys and the corner of a towel all do the same thing: they push wax inward, past the point where jaw movement can carry it out, and compact it against the eardrum. Cleveland Clinic and the NHS both single out cotton buds as a leading cause of impaction. Clean the outer bowl of the ear with a washcloth and leave the canal alone.
Ear candling deserves a firm correction. The practice involves placing a hollow candle in the ear and lighting the far end, supposedly to draw wax out by suction. Studies have found it produces no measurable suction and removes no wax; the residue people see afterward is candle wax. Mayo Clinic lists burns, canal blockage from dripping candle wax and perforation among its documented harms. There is no version of this that is safe or effective.
Another misconception is that irrigation is old-fashioned and therefore dangerous, or that microsuction is new and therefore always better. Both are mainstream, both are supported by guidance, and each has situations where it is the wiser choice. Modern irrigators are not the metal syringes of memory.
People also assume that a lot of visible wax means a problem. Colour and quantity vary enormously between individuals and with age; drier, flakier wax in older adults is normal, not a sign of disease. Only wax that blocks the canal or causes symptoms needs attention.
Finally, home suction gadgets and “spiral” removal tools are sold with confident claims. None of the allowed evidence bodies endorse them, and any device used blind in the canal carries the same risk of pushing wax inward or scratching the skin.
Questions to ask your care team before microsuction or irrigation
A five-minute conversation before the instrument comes out prevents most surprises. These questions are worth having in your pocket.
- What did you see when you looked in? Is the eardrum intact and healthy, and does the wax actually need removing?
- Which method are you recommending for me, and what about my ear or history led you to that choice rather than the other?
- Should I use softening drops first, for roughly how long, and is there any reason I should not use them?
- What will I feel and hear during the procedure, and how do I signal you to pause if I need a break?
- If it cannot all be removed today, what happens next?
- What should I do or avoid in the first couple of days afterwards, especially regarding water and hearing aids?
- What symptoms afterwards would mean I should contact you, and how quickly?
- Given how my ears behave, is periodic removal likely, and is there anything I can change to slow the build-up?
Bring a short list of your own: any previous perforation or ear surgery, grommets in childhood, recurring infections, single-sided hearing loss, tinnitus, dizziness problems and every medicine you take. Each of these can tip the decision, and clinicians rely on you to volunteer them.
If you have hearing aids, take them along. The team may want to check the fit and the wax filters, since a device that sits deep in the canal is a frequent contributor to recurrence.
Notice what a good answer sounds like. It ties the recommendation to something specific about your ear, acknowledges that the other method exists, and explains what would change the plan. A recommendation that is not anchored to your examination is a reasonable thing to query politely. The final decision sits with the treating team, but a well-informed patient makes that team better at its job.
When to call your doctor: red-flag signs before and after wax removal
Most earwax stories end quietly, but a handful of signs should move you from “wait and see” to a same-day call, whether they appear before any treatment or in the days following it.
Before treatment, seek prompt advice if you have sudden hearing loss in one ear, particularly if it arrived over hours rather than weeks. Sudden hearing loss has causes that need urgent assessment and should never be assumed to be wax. Severe ear pain, any discharge from the canal, bleeding, a fever, or dizziness with vomiting also warrant a clinician’s eyes and are reasons not to use softening drops or attempt anything at home. Mayo Clinic and MedlinePlus both advise against self-treatment if a perforation is possible.
After microsuction or irrigation, contact your care team the same day if you notice pain that increases rather than settles, discharge that is cloudy, bloody or foul-smelling, a fever, or a marked drop in hearing after an initial improvement. Persistent or worsening spinning dizziness, new or dramatically louder tinnitus, or facial weakness on the side of the treated ear are uncommon but need urgent review.
Seek emergency care for severe dizziness with vomiting that prevents standing, sudden complete deafness in the treated ear, or heavy bleeding. These are rare events, described here so that you recognize them, not because they are expected.
Children need a lower threshold. A child who is unusually irritable, holds the ear, develops a fever or has fluid on the pillow after a procedure should be seen the same day.
If in doubt, call. The team that performed the procedure would rather hear from you about a small worry than learn of a bigger one later, and every decision about further treatment rests with them.
Frequently asked questions
Is microsuction better than irrigation for earwax?
Neither is better for everyone. Microsuction is safer when the eardrum may be damaged, when there is infection, grommets or previous ear surgery, because no water enters the ear and the clinician watches throughout. Irrigation is effective and widely available for healthy ears with soft wax. High-quality comparative trials are limited, so your ENT chooses based on your examination and history rather than on a universal ranking.
What is the difference between microsuction vs syringing?
Syringing is the older name for irrigation. Historically it used a hand-pressed metal syringe; today it is done with an electronic irrigator that delivers a controlled, low-pressure stream of body-temperature water. Microsuction is a dry method that lifts wax out with gentle suction under a microscope or magnifying loupes. The key practical difference is that microsuction gives the clinician continuous direct vision of the canal and eardrum.
Does microsuction hurt?
Most people describe it as odd rather than painful. The suction tube is loud because it sits close to the eardrum, and moving air feels cool in the canal. Brief dizziness or a temporary increase in ringing can occur. Mild soreness may follow if hard wax needed instruments. Tell the clinician immediately if you feel sharp pain, since they can pause or change approach.
What are the main microsuction earwax removal risks?
Reported risks are mostly minor: short-lived dizziness, a temporary rise in tinnitus from the noise, small scratches to the canal skin and a slightly raised chance of outer ear infection for a few days. Rarely, the eardrum can be damaged or hearing affected. Because the procedure is performed under direct vision by a trained clinician, serious complications are uncommon, which is the central safety argument for the method.
What ear irrigation side effects should I expect?
Common effects are a feeling of trapped water for a few hours, brief dizziness if the water temperature was slightly off, and mild aching the same day. Less common problems include outer ear infection, wax being pushed deeper if it was not softened first and, rarely, eardrum perforation. Mayo Clinic advises against irrigation altogether if a perforation, grommets, surgery history or infection is present.
How long should I use ear drops before wax removal?
The NHS suggests softening drops for several days, typically 3–5, before irrigation, and notes that wax often clears on its own during this time. Your clinician decides which drops, if any, are appropriate and for how long, because drops should not be used if a perforation or infection is possible. Expect hearing to feel briefly worse as the wax swells before it loosens.
Can I have earwax removed if I have a perforated eardrum?
Often yes, but irrigation is not the right method. Water flushed into the canal can pass through the perforation into the middle ear and cause infection or hearing damage, so both Mayo Clinic and the NHS list perforation as a reason to avoid irrigation. Microsuction under direct vision, or careful manual removal by a specialist, is the usual approach. Always tell the team about any known eardrum problem.
How often does earwax build-up need removing?
There is no fixed schedule. Many people never need removal, while hearing-aid users, people with narrow canals and older adults with drier wax may need it periodically. The NHS notes that build-up tends to recur in those prone to it. The best way to lengthen the interval is to stop inserting anything into the canal, since cotton buds push wax inward and compact it.
Is ear candling a safe alternative to microsuction or irrigation?
No. Studies have found that ear candles create no measurable suction and remove no wax; the residue seen afterwards is candle wax. Mayo Clinic documents burns to the ear and face, canal blockage from dripping wax and eardrum injury among its harms. Home spiral tools and suction gadgets are also unendorsed by mainstream guidance and carry the risk of pushing wax deeper.
Do children have microsuction or irrigation for earwax?
Both are possible, but many clinicians prefer microsuction or gentle manual removal in young children because their canals are small, the eardrum is closer to the surface and they may not report pain reliably. A calm older child with a healthy ear can often have irrigation. Preparation matters: explain the noise and sensations in advance, and let the clinician set a pace the child can tolerate.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Painful Is Septoplasty? What the First Days Feel Like and How Discomfort Is Managed
Septoplasty is usually described as uncomfortable rather than severely painful. Mainstream surgical guidance rates typical post-operative pain as mild to moderate, dominated by nasal…

How Long Do Ear Tubes Stay In? What Follow-Up Visits Check and What Happens When They Come Out
Most ear tubes stay in for about 6 to 18 months and then fall out on their own as the eardrum heals and gradually…

Voice Therapy or Microsurgery for Vocal Cord Polyps and Nodules: How Do ENT Teams Decide?
ENT teams usually start with voice therapy for vocal nodules, because nodules are callus-like and often shrink once the vocal habits that caused them…

Otosclerosis and Stapedectomy Surgery: How Does a Fixed Stapes Bone Cause Hearing Loss?
Otosclerosis is abnormal bone remodeling in the middle ear that gradually freezes the stapes, the smallest bone in the body, so it can no…
How Does Glottoplasty Raise Vocal Pitch? Endoscopic Pitch-Raising Surgery Explained
Glottoplasty raises vocal pitch by shortening the part of the vocal folds that vibrates. Working through the mouth with an endoscope, a surgeon removes…

Traveling With CPAP: What International Patients Ask About Flights and Device Settings
A CPAP machine can travel with you on most commercial flights. Aviation and security authorities in the US and many other countries treat it…