

Pneumonia and Tdap Boosters: The Adult Vaccines Most People Forget

Key Takeaways
- US pertussis cases exceeded 35,000 in 2024, roughly six times the 2023 count and the highest annual total since 2012.
- Since October 2024, CDC recommends a pneumococcal conjugate vaccine for every adult aged 50 and older, down from the previous routine age of 65.
- Tdap can be given regardless of how long ago your last Td was, so adults who have never had Tdap do not need to wait out a 10-year interval.
- Observational studies estimate that Tdap given between 27 and 36 weeks of pregnancy prevents about three in four pertussis cases in infants under two months old.
- Tdap effectiveness against pertussis falls from roughly 70 percent in the first year to 30 to 40 percent by year four, while its tetanus and diphtheria protection remains durable.
- A randomized trial of about 85,000 adults aged 65 and older found conjugate pneumococcal vaccine reduced vaccine-type pneumonia by 45 percent and invasive disease by 75 percent.
Adults need a Tdap booster, or a Td booster, every 10 years, with Tdap given during each pregnancy, ideally between 27 and 36 weeks. Pneumococcal vaccination is now recommended for all adults 50 and older, and for younger adults with certain health conditions. Both vaccines are well studied and usually cause only a sore arm; your clinician can confirm which you are due for.
A grandmother in a pediatric waiting room, asked by the nurse when she last had a tetanus shot, laughs and says, “Probably when I stepped on a nail in 1998.” The nurse does not laugh. She has spent the past year watching whooping cough move through the community again, and she knows that a Tdap booster for the adults around a newborn is one of the few tools that works before the baby is old enough to be vaccinated.
That scene explains why these two unglamorous adult vaccines are trending. As of January 2026, pertussis counts in the United States have climbed to levels not seen in over a decade, and in late 2024 federal advisers lowered the recommended age for routine pneumococcal vaccination from 65 to 50. Both changes have sent people to search engines asking what they missed.
The honest answer is that most adults have missed something, usually not through refusal but through quiet drift. Childhood shots have a schedule. Adult shots rely on someone remembering to ask.
What changed recently with the Tdap booster and pneumonia vaccine advice
Two developments, both dated and documented, pushed these vaccines back into view.
The first is a disease trend. Pertussis, the bacterial infection better known as whooping cough, had been unusually quiet during the pandemic years because masking and distancing interrupted its spread. It came back fast. CDC surveillance recorded more than 35,000 reported cases in 2024, roughly six times the 2023 total and the highest annual figure since 2012. Cases continued at elevated levels into 2025, with outbreaks reported in schools and, more worryingly, among infants too young to be vaccinated. Several infant deaths were confirmed. That pattern is exactly what the adult Tdap booster, and especially Tdap in pregnancy, is designed to blunt.
The second is a guideline change. In June 2024 the US Food and Drug Administration approved a new 21-valent pneumococcal conjugate vaccine (PCV21), designed around the bacterial strains that cause most adult disease rather than the strains that dominate in children. Then, in October 2024, the CDC adopted its advisory committee’s recommendation that every adult aged 50 and older receive a pneumococcal conjugate vaccine, where the previous routine age had been 65. Adults aged 19 to 49 with certain risk conditions were already eligible and remain so.
Neither change was a reaction to a single viral claim. They reflect ordinary public health machinery: surveillance showing a rising threat, and a committee reviewing new trial and modeling data on who gets sick and at what age. The practical upshot for a 52-year-old reading this is that your eligibility may have changed since your last check-up, even if nothing about your health did.
Everything that follows is written against those two anchors: a resurgent respiratory infection, and a broadened recommendation for a vaccine that many adults still associate only with their grandparents.
What is a Tdap booster, and how is it different from DTaP and Td?
The alphabet soup is the main reason people tune out, so it is worth decoding once.
Tdap is a combination vaccine that protects against three bacterial diseases: tetanus, diphtheria and pertussis. Tetanus is a nervous-system illness caused by bacteria that enter through wounds and produce a toxin that locks muscles. Diphtheria is a throat infection whose toxin can damage the heart and nerves. Pertussis, or whooping cough, is a prolonged respiratory infection that is mostly miserable in adults and genuinely dangerous in young infants.
The capital and lowercase letters are not decorative. A capital letter means a full-strength component; a lowercase letter means a reduced amount. DTaP, with three capitals, is the children’s formulation given in early childhood when the immune system is building protection from scratch. Tdap, with a capital T and lowercase d and p, carries full tetanus protection but reduced diphtheria and pertussis components, because an already-primed adult immune system needs only a reminder and because the lower amounts cause fewer sore arms. Td is the older adult booster that covers tetanus and diphtheria but leaves pertussis out entirely.
The small “a” in both DTaP and Tdap stands for acellular. Earlier whooping cough vaccines used whole, inactivated bacterial cells and caused more fevers and local reactions. Acellular versions, introduced for US children in the 1990s, use purified pieces of the bacterium instead. They are gentler, which is why they replaced the older type, and they are also the reason protection against pertussis fades sooner than it once did. That trade-off, gentleness against durability, sits behind most of the confusion covered later in this article.
For an adult, the practical distinction is simple: a Tdap booster is the version that includes whooping cough protection, and current guidance favors it over plain Td whenever pertussis protection matters.
When to get a Tdap booster as an adult
The CDC’s adult schedule has three triggers, and most people only know the first.
The routine trigger is the calendar. Adults should receive a tetanus-and-diphtheria-containing booster every 10 years, and either Td or Tdap satisfies that interval. Any adult who has never had a dose of Tdap, which includes most people who finished school before the vaccine was licensed in 2005, should receive Tdap for their next booster regardless of when their last Td was given. There is no need to wait out the remaining years of an old Td interval; CDC guidance specifically says Tdap can be given regardless of time since the last tetanus-containing vaccine.
The second trigger is pregnancy. Tdap is recommended during every pregnancy, ideally early in the third trimester, so that antibodies cross the placenta and protect the newborn through the first weeks of life. This is repeated with each pregnancy, even if the pregnancies are close together, because antibody levels drop within a year or two.
The third trigger is a wound. Clinicians assess tetanus risk whenever someone arrives with a deep cut, puncture, burn or animal bite. For a clean, minor wound, a booster is advised if more than 10 years have passed since the last dose. For a dirty or deep wound, that window shrinks to five years. People who cannot remember their last dose are generally treated as overdue, because an unnecessary booster is far less risky than untreated exposure.
There is also an informal fourth trigger that matters right now: becoming a grandparent, a new parent’s partner, or a caregiver for an infant. Guidance encourages adults in close contact with babies under 12 months to be up to date before the baby arrives, a strategy sometimes called cocooning. It does not replace maternal vaccination, but it narrows the circle of people who could bring pertussis home.
How is the DPT vaccine administered in adults?
People still search for “DPT,” the whole-cell vaccine that US children received until the 1990s. That product is no longer used in the United States, so the real question is how its modern descendants, DTaP for children and Tdap for adolescents and adults, are given.
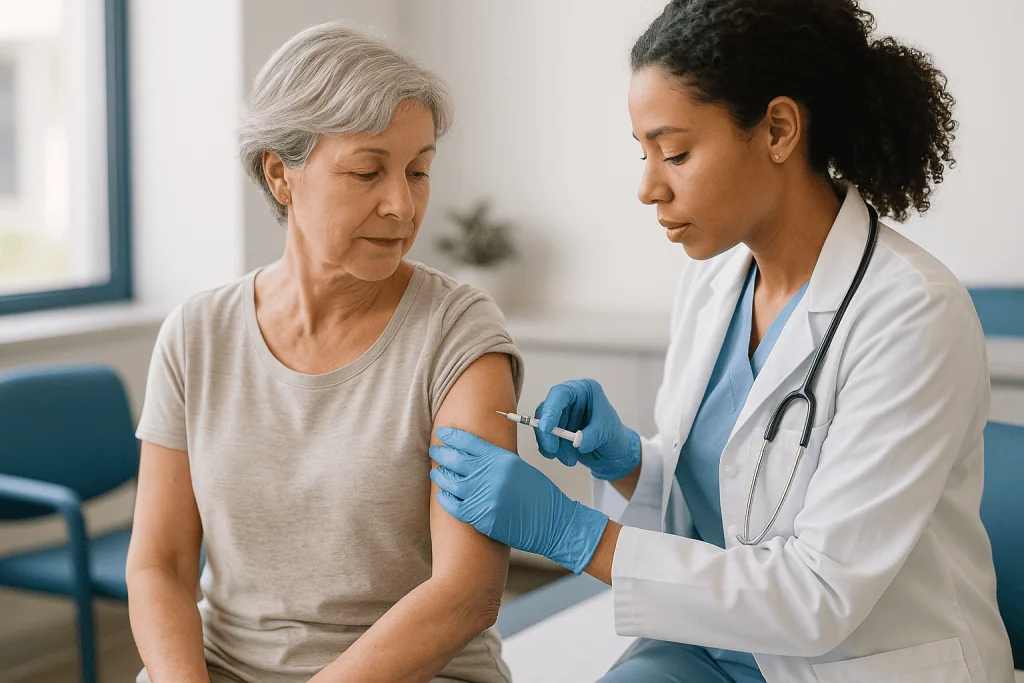
Tdap is an intramuscular injection, meaning it is delivered into muscle rather than under the skin. In adults the usual site is the deltoid, the rounded muscle at the top of the upper arm. The whole appointment takes a few minutes, and most of that is paperwork and the brief observation period afterward.
Why muscle? The immune system’s surveillance cells gather readily in well-supplied muscle tissue, and the aluminum-based adjuvant in Tdap, a substance that helps the immune system notice and respond to the vaccine components, works best there. Injecting too shallowly can cause more local irritation and a weaker response, which is why nurses pay attention to needle length and to relaxing the arm.
A few practical points reduce next-day soreness. Keep the arm moving in the hours after the shot rather than babying it; gentle use helps disperse the fluid. A cool compress is reasonable if the site feels warm. Choose the non-dominant arm if you have a physical job the next day. None of these are medical requirements, just the collected wisdom of people who give a lot of injections.
Tdap can be given at the same visit as other adult vaccines, including influenza, COVID-19 and pneumococcal vaccines, typically in separate arms or at separate sites. There is no need to space them out, and CDC guidance explicitly supports giving them together to avoid missed opportunities.
People taking blood thinners can still receive intramuscular vaccines; the usual practice is a finer needle and firm pressure on the site for a couple of minutes. Tell the vaccinator if this applies to you, and if you have ever had a severe reaction to a previous tetanus-containing vaccine, because that history changes what is offered.
Is the Tdap vaccine safe to get during pregnancy?
This is the question with the highest stakes and, fortunately, one of the deepest evidence bases in adult vaccination.
The purpose is specific. A baby cannot start its own pertussis vaccine series until two months of age, and protection does not become substantial until several doses in. Those early weeks are when pertussis kills. When a pregnant person receives Tdap in the third trimester, antibody levels peak within a couple of weeks and are actively transported across the placenta, so the infant is born carrying borrowed protection. The CDC and the NHS both recommend vaccination in every pregnancy for this reason; the CDC window is 27 to 36 weeks, and the UK program offers it from 16 weeks, ideally before 32 weeks.
Does it work? Observational studies from the United States and the United Kingdom, which compare infants of vaccinated and unvaccinated mothers, consistently show large effects. CDC analyses estimate that maternal Tdap prevents roughly three in four pertussis cases in infants under two months, and about nine in ten hospitalizations. The UK, which introduced the program during a 2012 outbreak, saw infant deaths fall sharply in the following years.
Is it safe? Large safety studies covering hundreds of thousands of pregnancies, including a UK analysis of around 20,000 vaccinated women and several US health-system cohorts, found no increase in stillbirth, preterm birth, low birth weight, pre-eclampsia or birth defects compared with unvaccinated pregnancies. The most common finding was the expected sore arm. The evidence here is observational rather than from randomized trials, because deliberately withholding a recommended vaccine from pregnant participants would be unethical, but the consistency across countries and health systems is what gives clinicians confidence.
One nuance worth knowing: receiving Tdap in pregnancy slightly dampens the infant’s own antibody response to early pertussis doses, a phenomenon called blunting. Studies so far show no increase in infant disease because of it, and the net benefit remains clearly in favor of vaccinating. Your prenatal clinician is the right person to time the dose.
What are the potential side effects of the whooping cough vaccine?
Most people who get Tdap report exactly one thing: an arm that complains when they roll over in bed that night.
In the trials that supported licensing, roughly two in three adults had pain at the injection site, about one in five had redness or swelling, and smaller proportions reported headache, tiredness or body aches for a day or two. Mild fever occurred in a minority. These are signs of an immune system doing its work, and they resolve on their own. Nausea and mild stomach upset appear in a small percentage of recipients and are also short-lived.
Less common reactions deserve a plain description rather than reassurance alone. Extensive limb swelling, where the whole upper arm becomes red and puffy, happens in a small number of people, more often in those who have had many tetanus-containing doses, and it settles without treatment. A rare, intensely painful local reaction called an Arthus reaction has been described in people with very high pre-existing tetanus antibody levels; it is one reason clinicians avoid giving boosters more frequently than guidelines suggest. Brachial neuritis, a nerve inflammation causing shoulder pain and weakness, has been linked to tetanus-containing vaccines at a rate of roughly one in 100,000 doses or less, and most people recover fully.
Severe allergic reaction, anaphylaxis, occurs after vaccines at a rate on the order of one in a million doses. It typically begins within minutes, which is why the 15-minute wait exists, and clinics are equipped to treat it.
Guillain-Barré syndrome, a temporary paralysis caused by the immune system attacking nerves, comes up in searches. A possible association with older tetanus vaccines was reported decades ago; large modern surveillance studies have not confirmed an increased risk with Tdap. Someone who developed Guillain-Barré within six weeks of a previous tetanus-containing vaccine should discuss it with their clinician, who will weigh that history before recommending another dose.
Side effects are reported to national safety systems, and those systems are what allow rare events to be detected across tens of millions of doses.
Why does Tdap protection fade, and does that make the booster pointless?
One of the most-shared headlines about this vaccine says protection “doesn’t last very long.” The claim is partly true, and the conclusion people draw from it is mostly wrong.
The three components behave differently. Tetanus and diphtheria protection is robust and long-lasting; the 10-year interval is conservative, and tetanus remains vanishingly rare in the United States, with around 30 reported cases a year, almost all in people who were unvaccinated or long overdue. That part of the booster earns its keep quietly.
Pertussis protection is the weak link. Observational studies from large US health systems followed adolescents and adults after Tdap and found that effectiveness against confirmed whooping cough starts around 70 percent in the first year, then falls to roughly 30 to 40 percent by the fourth year. The acellular formulation, chosen for its gentler side-effect profile, appears to produce shorter-lived immunity than the whole-cell vaccines it replaced, and it may be better at preventing illness than at preventing silent carriage and transmission.
So what is the point? Three things. First, even partial protection matters during an outbreak; a vaccine that halves your risk of a weeks-long cough is not nothing. Second, the dose given in pregnancy is timed precisely so that peak antibody levels coincide with birth; its short duration is irrelevant because the goal is the first two months of the baby’s life. Third, the tetanus and diphtheria protection in the same syringe lasts for years, so the booster is never wasted even if the pertussis component wanes.
Researchers are actively studying whether more frequent pertussis boosting or next-generation vaccines would help. Until that evidence exists, guidelines do not recommend adults seek extra Tdap doses outside the 10-year interval, pregnancy, or wound care, and the decision to deviate from that belongs to a clinician, not to a headline.
Pneumonia vaccine for adults: which types exist and what do they target?
“Pneumonia vaccine” is shorthand. What adults actually receive protects against Streptococcus pneumoniae, a bacterium commonly called pneumococcus, which is a leading cause of bacterial pneumonia and also causes bloodstream infections and meningitis. It does not protect against viral pneumonia or pneumonia caused by other bacteria, which is worth knowing so expectations stay honest.
Pneumococcus comes in roughly 100 serotypes, which are variants distinguished by the sugar coat on the bacterial surface. Vaccines target a selection of the serotypes that cause the most severe disease. Two broad technologies exist.
Polysaccharide vaccines use purified sugar coats alone. PPSV23 covers 23 serotypes and has been available since 1983. It produces a reasonable antibody response in healthy adults but a weaker one in people with compromised immunity, and it does not generate long-term immune memory.
Conjugate vaccines chemically attach those sugars to a carrier protein, which lets the immune system respond with the memory-forming machinery it normally reserves for proteins. This is the same trick that made childhood pneumococcal vaccines so effective in the early 2000s. For adults, the conjugate options now include PCV15, PCV20 and, since 2024, PCV21. The numbers refer to serotypes covered, and the serotype lists differ: PCV21 was built specifically around strains responsible for most adult invasive disease rather than reusing the pediatric selection.
Why does this matter to a patient? Because the choice between products is now a clinical decision rather than a one-size answer. Under current CDC guidance, an eligible adult may receive a single conjugate vaccine that completes their protection, or a conjugate vaccine followed later by PPSV23, depending on which product is used and what they have had before. Someone who received PPSV23 years ago may still need a conjugate dose. The clinician’s job is to look at the record and apply the schedule; your job is to bring the record, or at least an honest memory of it.
Who should get the pneumonia vaccine as an adult under the new guidance?
The headline change is the age. Since October 2024, CDC guidance recommends pneumococcal conjugate vaccination for all adults aged 50 and older who have not previously completed a pneumococcal series. Previously, healthy adults waited until 65.
The reasoning was not that a 50-year-old suddenly became frail. Advisers looked at surveillance showing that rates of invasive pneumococcal disease begin climbing in the fifties, that Black adults in particular reach the risk level of the general 65-and-over population at a younger age, and that many adults in their fifties have undiagnosed conditions that would already have made them eligible. Lowering the age was a simpler rule that captured more at-risk people without asking them to know their own risk status.
Younger adults, aged 19 to 49, are recommended for vaccination if they have a condition that raises their risk. The CDC list includes chronic heart disease, chronic lung disease including asthma, chronic liver disease, diabetes, alcohol use disorder, current cigarette smoking, a cochlear implant, a cerebrospinal fluid leak, a missing or non-functioning spleen, sickle cell disease, HIV, chronic kidney disease, cancer, and any treatment that suppresses the immune system. Smoking surprises people; it damages the airway lining that normally sweeps pneumococcus out.
Adults who already completed a series with the older PCV13-plus-PPSV23 approach are generally considered protected under current guidance, though CDC offers an option to discuss a newer conjugate vaccine with a clinician. Adults who received only PPSV23 are advised to receive a conjugate vaccine as well, with timing set by the clinician.
The disease burden justifies the attention. Pneumococcal pneumonia leads to an estimated 150,000 US hospitalizations each year, and CDC estimates that about one in 20 adults who develop it die, with higher fatality for bloodstream infection and meningitis. Those are older adults disproportionately, but not exclusively.
Tdap booster vs pneumonia vaccine: a side-by-side summary
The two vaccines are often offered in the same visit, which invites comparison. The table below condenses current CDC guidance and the main evidence features; it is a map, not a prescription, and the details for any individual depend on their record and health history.
| Feature | Tdap booster | Pneumococcal vaccine (adult) |
|---|---|---|
| Protects against | Tetanus, diphtheria, pertussis (whooping cough) | Streptococcus pneumoniae, selected serotypes |
| Vaccine type | Inactivated toxoids plus acellular bacterial components | Conjugate (PCV15, PCV20, PCV21) or polysaccharide (PPSV23) |
| Routine adult eligibility | Every 10 years (Td or Tdap); Tdap once if never received | All adults 50 and older; ages 19 to 49 with risk conditions |
| Pregnancy | Recommended in every pregnancy, 27 to 36 weeks | Only if a risk condition applies; clinician decides |
| Wound-related use | Yes, based on wound type and time since last dose | Not applicable |
| Strongest evidence | Observational, large health-system cohorts | Randomized trial for PCV13 in older adults; observational for others |
| Durability | Tetanus and diphtheria long-lasting; pertussis wanes over 2 to 4 years | Conjugate protection expected to last years; exact duration still being measured |
| Most common side effect | Injection-site pain in about two thirds | Injection-site pain, fatigue, muscle ache |
| Can be given with flu or COVID-19 vaccine | Yes | Yes |
Two things stand out. The pneumococcal column has the single randomized trial, which is a stronger form of evidence, while the Tdap column rests on consistent observational data. And the Tdap column has the only recurring schedule; pneumococcal vaccination for most adults is a one-time or two-step event, after which current guidance does not call for routine repeat boosters.
Use the table to check which column applies to you, then let the clinician fill in the specifics.
What the evidence actually says, and how strong it is
A vaccine recommendation is only as good as the studies beneath it, so here is an honest grading using the usual hierarchy: randomized trials strongest, then large observational cohorts, then expert opinion.
Tetanus and diphtheria protection: strong, mostly historical. The toxoid vaccines were adopted before the modern randomized trial era, but the natural experiment was dramatic. US tetanus cases fell more than 95 percent after routine vaccination, and diphtheria, which killed thousands of American children annually in the 1920s, now causes a handful of cases in a decade. Antibody studies confirm durable protection. Grade: strong observational and immunological evidence.
Tdap against pertussis in adults: moderate. Effectiveness has been measured in large health-system cohorts rather than randomized trials. Those studies agree on the shape of the curve: good early protection that declines within a few years. Grade: consistent observational evidence, with a known limitation on durability.
Tdap in pregnancy: strong observational. Multiple national programs, hundreds of thousands of pregnancies, consistent infant protection and no safety signal. Randomized trials were small and focused on immune response, not outcomes. Grade: strong for safety and effectiveness by observational standards.
Pneumococcal conjugate vaccine in older adults: strong, including randomized data. A Dutch trial of about 85,000 adults aged 65 and older randomized participants to PCV13 or placebo and found 45 percent efficacy against vaccine-type pneumonia and 75 percent against vaccine-type invasive disease. Newer conjugate vaccines were licensed on immune-response comparisons to that product, which is standard practice but means their clinical efficacy is inferred rather than directly measured. Grade: strong for the class, moderate for individual newer products.
PPSV23: moderate for invasive disease, weak for pneumonia. Observational studies and meta-analyses support protection against bloodstream infection; evidence for preventing pneumonia itself is inconsistent. Grade: moderate.
Lowering the pneumococcal age to 50: expert judgment on observational data. The change rests on surveillance and modeling, not a new trial. That is a legitimate basis for a guideline, but it is fair to call it the least settled item on this list.
Common myths about adult boosters, corrected
Outbreaks generate claims. These are the ones circulating most, with what the evidence supports.
“Adults don’t get whooping cough.” They do, constantly; they just rarely get diagnosed. In adults pertussis looks like a cold that turns into a cough lasting six to ten weeks, often without the characteristic whoop. Studies that test adults with prolonged cough find pertussis in a meaningful minority. Adults are the main reservoir that infects infants.
“If you had whooping cough as a child, you’re immune for life.” Natural infection gives longer protection than vaccination, but it still fades, typically within a couple of decades. Reinfection is well documented.
“The vaccine is failing because vaccinated people get sick.” A vaccine that is 70 percent effective in year one will, in a highly vaccinated population, produce many vaccinated cases simply because almost everyone is vaccinated. Waning is real and discussed openly above; it is a reason for timed boosters, not evidence of failure.
“Tdap in pregnancy is new and untested.” The US recommendation dates to 2011 and the UK program to 2012. The safety literature now covers well over a decade and hundreds of thousands of pregnancies.
“You only need a tetanus shot when you get a dirty wound.” Wound care is one trigger, but antibody levels fall regardless of injuries, and many tetanus cases follow minor wounds people did not think worth reporting. The 10-year routine interval exists for exactly that reason.
“The pneumonia vaccine prevents all pneumonia.” It prevents disease from specific pneumococcal serotypes. You can still get pneumonia from viruses, other bacteria, or serotypes outside the vaccine. It remains worthwhile because pneumococcus is the single most common bacterial cause.
“I got the pneumonia shot once, so I’m done forever.” Possibly, possibly not. It depends on which product you received and when. A clinician reviewing your record can tell in a minute.
Can you get a Tdap booster and the pneumonia vaccine at the same visit?
Yes, and for most adults this is the sensible way to do it, because the biggest obstacle to adult vaccination is not reluctance but logistics.
CDC guidance supports giving inactivated vaccines together without any minimum interval between them. Tdap, pneumococcal conjugate or polysaccharide vaccines, inactivated influenza vaccine, COVID-19 vaccines and the recombinant shingles vaccine can all be administered at a single visit, in separate limbs or at sites spaced apart on the same limb. Studies of co-administration have looked for two problems, reduced immune response and increased side effects, and have generally found neither to a clinically meaningful degree. Some combinations produce slightly more injection-site soreness or fatigue the next day, which is the predictable sum of two vaccines rather than an interaction.
There is a practical case for bundling. Every adult who leaves a clinic with the intention of “coming back for the other one” is a coin flip, and the data on return visits are not encouraging. Receiving everything you are due in one appointment removes the coin.
A few situations warrant a different plan, and the clinician will raise them. Someone with a current moderate or severe illness with fever is usually asked to wait until recovered, mainly so that symptoms of the illness are not confused with vaccine reactions. Someone with a history of severe reaction to a specific vaccine component needs that history reviewed before any dose. People on immune-suppressing treatment may be advised about timing relative to their therapy, because the goal is to vaccinate when the immune system can respond best. None of these are reasons to avoid vaccination; they are reasons to schedule it thoughtfully.
If you take a blood thinner, mention it so the vaccinator can use a finer needle and apply pressure. If you faint easily with needles, say so and sit or lie down; fainting after vaccination is common in adolescents and young adults and is harmless except for the fall.
Ask for a printed or electronic record of what was given. Future clinicians, and future you, will need it.
When to see a doctor: red flags after vaccination and signs of the diseases themselves
Two sets of warning signs matter here: reactions to the vaccines, and symptoms of the infections they prevent.
After a Tdap or pneumococcal vaccine, seek care promptly for:
- Hives, swelling of the face or throat, wheezing, difficulty breathing, a racing heartbeat or dizziness within minutes to hours of the injection. These can indicate a severe allergic reaction and need emergency treatment.
- Redness or swelling that keeps spreading after 48 hours, streaks running up the arm, pus, or a fever above 102°F that does not settle; these may signal infection at the site, which is rare but treatable.
- New weakness, numbness or tingling in the arms or legs, trouble walking, or facial weakness in the weeks after vaccination.
- Severe shoulder pain with weakness that begins days after the injection and limits movement.
- Any reaction that worries you. Clinicians would rather field a call about a normal sore arm than miss something.
See a doctor for possible pertussis if: a cough lasts more than two to three weeks, comes in violent fits, ends in vomiting or gasping, or if you have had any cough after contact with a confirmed case. Early antibiotic treatment shortens the period during which you can infect others, even though it does little for the cough itself. For infants, any pauses in breathing, blue or gray color, or difficulty feeding are emergencies.
See a doctor for possible pneumonia if: you have fever with a cough producing discolored sputum, chest pain when breathing, shortness of breath, or confusion in an older adult. Pneumonia in people over 65 can present with little more than tiredness and confusion.
See a doctor for any deep, dirty or puncture wound, particularly if you cannot recall your last tetanus booster. Jaw stiffness, muscle spasms or trouble swallowing in the days after a wound are emergencies.
Every decision about whether, when and which vaccine to receive, and about managing any reaction, belongs with your treating clinician, who can see your full record and history.
Frequently asked questions
When should I get a Tdap booster?
Adults need a tetanus-and-diphtheria booster every 10 years, and Tdap should be used at least once if you have never received it, regardless of when your last Td was. Tdap is also recommended during every pregnancy and after certain wounds if enough time has passed since your last dose. Your clinician can check your record and tell you which trigger applies.
How is the DPT vaccine administered to adults?
The original DPT whole-cell vaccine is no longer used in the United States; adults receive Tdap instead. It is given as an intramuscular injection, usually into the deltoid muscle of the upper arm, and the visit takes only a few minutes including a short observation period. It can be administered at the same appointment as flu, COVID-19 or pneumococcal vaccines.
Is the Tdap vaccine safe to get during pregnancy?
Yes, according to CDC and NHS guidance and more than a decade of safety data covering hundreds of thousands of pregnancies. Large observational studies found no increase in stillbirth, preterm birth, low birth weight or birth defects. Vaccination between 27 and 36 weeks passes protective antibodies to the baby for the first vulnerable months. Discuss timing with your prenatal clinician.
What are the potential side effects of the whooping cough vaccine?
About two in three adults get a sore arm, and smaller numbers notice redness, swelling, headache, tiredness or mild fever for a day or two. Rare effects include extensive arm swelling, nerve inflammation in the shoulder, and severe allergic reaction at roughly one per million doses. Large surveillance studies have not confirmed an increased risk of Guillain-Barré syndrome with Tdap.
What is the difference between Tdap and DTaP?
DTaP is the full-strength children’s vaccine used in early childhood; Tdap is the reduced-strength version for adolescents and adults. Capital letters mean full components, lowercase means reduced, so Tdap has full tetanus protection but smaller diphtheria and pertussis components to act as a reminder dose with fewer side effects. Td is an older adult booster that omits pertussis.
At what age do adults need the pneumonia vaccine?
Under CDC guidance updated in October 2024, all adults aged 50 and older should receive a pneumococcal conjugate vaccine if they have not completed a series. Adults aged 19 to 49 are recommended for vaccination if they have conditions such as diabetes, chronic heart, lung, liver or kidney disease, alcohol use disorder, current smoking, or a weakened immune system.
Does the pneumonia vaccine for adults prevent all pneumonia?
No. It protects against selected serotypes of Streptococcus pneumoniae, the most common bacterial cause of pneumonia, and is especially effective against bloodstream infection and meningitis from those strains. It does not prevent viral pneumonia or pneumonia from other bacteria. A randomized trial in older adults found it reduced vaccine-type pneumonia by about 45 percent.
How long does a Tdap booster last?
The tetanus and diphtheria components provide durable protection, which is why the routine interval is 10 years. The pertussis component is shorter-lived; observational studies show effectiveness around 70 percent in the first year, falling to 30 to 40 percent by year four. That waning is why Tdap is repeated in each pregnancy rather than relied on from a previous one.
Do grandparents need a Tdap booster before visiting a newborn?
CDC guidance encourages adults who will have close contact with an infant under 12 months to be up to date on Tdap, ideally at least two weeks before contact, a strategy called cocooning. It does not replace maternal vaccination in pregnancy, which protects the baby directly, but it reduces the chance an adult brings pertussis into the home. Ask your clinician to check your record.
Can I get the pneumonia vaccine and Tdap booster at the same time as a flu shot?
Yes. CDC guidance allows inactivated vaccines, including Tdap, pneumococcal, influenza and COVID-19 vaccines, to be given at the same visit in separate sites with no required spacing. Studies of co-administration show no meaningful loss of immune response, though you may have slightly more soreness or fatigue the next day. Your clinician will confirm what you are due for.
References
- CDC: Pertussis Surveillance and Trends
- CDC: Adult Immunization Schedule by Age
- CDC: Pneumococcal Vaccination
- MedlinePlus: Tdap Vaccine (Tetanus, Diphtheria, Pertussis)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Travelers’ Diarrhea: Prevention, Treatment and the Antibiotic Question
Travelers' diarrhea is a food- and water-borne gut infection, usually bacterial, that affects roughly 30 to 70 percent of people visiting high-risk regions. Most…

How a Lumbar Puncture Diagnoses Meningitis: What the Spinal Fluid Test Shows Doctors
A lumbar puncture diagnoses meningitis by drawing a small sample of cerebrospinal fluid from the lower back so a laboratory can check its appearance,…

Cold, Flu or Sinus Infection? How Doctors Tell Them Apart and What Changes the Plan
A cold builds gradually with a runny nose and sore throat and usually eases within 7 to 10 days. Flu arrives suddenly with fever,…

Motion Sickness: Why the Brain Gets Confused and What Prevents It
Motion sickness happens when the brain receives mismatched signals about movement from the inner ear, the eyes and the body, most often when you…

Tick Bites: Safe Removal and the Signs of Infection to Watch For
Tick bites are best handled by removing the tick as soon as you find it: grasp it close to the skin with fine-tipped tweezers,…

Salmonella Infection: When Doctors Order a Stool Test and How the Result Changes Treatment
Doctors usually order a salmonella stool test when diarrhea is severe, bloody, lasting more than a few days, accompanied by high fever, or occurring…