

Questions to Ask Before Your First Botulinum Toxin (Botox) Treatment: Goals and Repeat Timing

Key Takeaways
- Botulinum toxin blocks the nerve signal that makes a muscle contract, which is why it softens movement lines but cannot fill hollows or lift loose skin.
- The NHS says effects begin within about two to three days and reach full strength at two to three weeks, so a result should be judged at a review, not on the day.
- Both the NHS and Mayo Clinic place typical duration at around three to four months, and repeat timing is set by the prescriber's reassessment rather than a fixed calendar.
- There is no reversal agent for cosmetic over-treatment; a conservative first treatment with a planned review is the main safeguard against a result you must simply wait out.
- Pregnancy, breastfeeding, neuromuscular conditions such as myasthenia gravis, and certain antibiotics or muscle relaxants are recognized reasons a prescriber may decline or postpone treatment.
- Difficulty swallowing, speaking or breathing, or weakness away from the treated area, are rare but serious signs of toxin spread that need emergency care, not a wait-and-see approach.
Before a first botulinum toxin (Botox) treatment, ask what result is realistic for your face, who will perform the injections and their medical qualifications, which product is being used, what side effects are possible, how long effects typically last (around three to four months), when a repeat is reasonable, and how any complication would be handled. Bring your full medication list, and let the clinician decide whether treatment is appropriate for you.
The appointment is booked for Thursday. She has read the reviews, screenshotted a photo of a stranger’s forehead, and written exactly one note on her phone: “don’t look frozen.” What she has not written down is anything to ask. That is the usual pattern. Most people spend more time choosing the day than choosing the questions to ask before Botox, and then sit in the chair nodding while a clinician talks quickly about muscles they cannot name.
It matters, because botulinum toxin is a prescription medicine with a real mechanism, real side effects, and a shelf life inside your body of only a few months. The result you get depends far more on what is agreed in the ten minutes before the first injection than on anything that happens after.
So here is the conversation, laid out in advance: what the drug does, who it suits, what the honest timelines are, and which questions separate a considered decision from a hopeful one.
How does botulinum toxin actually work on a wrinkle?
Every time you frown, a nerve releases a chemical messenger called acetylcholine onto the muscle between your eyebrows, and the muscle contracts. Do that thousands of times a year, and the skin above it folds along the same line until the crease stays even when your face is at rest. Botulinum toxin does not touch the skin. It works one step earlier, at the point where nerve meets muscle.
The purified protein is injected in tiny amounts into a specific muscle. Inside the nerve ending, it blocks the release of acetylcholine, so the signal to contract never arrives. The muscle relaxes, the overlying skin stops being folded, and the line softens. Mayo Clinic describes it plainly: the drug temporarily prevents a muscle from moving.
The word to hold onto is temporary. The nerve is not damaged. Over weeks and months it sprouts new connections and the muscle gradually regains its strength, which is why the effect fades rather than switching off. Nothing is dissolved or filled; the crease is simply no longer being reinforced.
This mechanism explains two things people find surprising. First, botulinum toxin is best at dynamic lines, the ones that appear when you move your face. A line that is etched deeply enough to show at complete rest may soften but usually will not vanish, because the skin itself has changed. Second, the drug cannot lift or add volume. If the concern is hollowing or sagging rather than movement, the clinician may explain that a different approach, or none, is the more honest answer.
Understanding this before the appointment changes the conversation from “make this go away” to “which muscle is causing this, and what happens if it relaxes?” That is the question a good clinician wants to hear.
Why "what is my goal?" is the first of the questions to ask before Botox
Ask a room of first-timers what they want and the answers sound alike: to look less tired, less angry, more like themselves. Those are feelings, not treatment plans. A useful consultation translates a feeling into a muscle and a movement, and that translation is where most disappointment is prevented.

Bring the concern, not the fix. “People ask if I’m annoyed when I’m concentrating” points a clinician toward the frown muscles between the brows. “My forehead looks heavy in photos” might point somewhere else entirely, and in some faces relaxing the forehead can lower the brows and make heaviness worse. Mayo Clinic notes that cosmetic use commonly targets frown lines, forehead lines and lines around the eyes, but which of those suits you depends on how your face moves.
Three goal questions are worth asking out loud:
- “Which muscle is responsible for the thing I dislike, and what will my face do differently when it relaxes?”
- “Is this line present at rest, or only when I move? How much can I realistically expect it to soften?”
- “Would you recommend treating less than I’m asking for at a first visit, and why?”
That last question matters. Many clinicians prefer a conservative first treatment, because a result can be adjusted upward at a review but cannot be undone once injected. The NHS advises that the practitioner should explain what the treatment can and cannot achieve and give you time to think before proceeding.
Agree on a definition of success before you leave. “Softer frown lines while still being able to raise my eyebrows” is a goal a clinician can aim for and you can judge. “Look ten years younger” is not a goal; it is a hope, and no ethical clinician will promise it.
Who is botulinum toxin usually for, and who is usually asked to wait?
Cosmetic botulinum toxin is approved for adults, and in practice the typical first-time patient is someone bothered by lines that show with expression. Age alone is a poor guide. A person in their late twenties with a strong frown may be a reasonable candidate; a person in their sixties whose main concern is loose skin may not benefit much at all, because loose skin is not a movement problem.
Certain situations lead most clinicians to decline or postpone. MedlinePlus lists the medical history a prescriber needs to know before treatment, and several items on that list are reasons to wait or avoid:
- Pregnancy, or trying to become pregnant, and breastfeeding. The NHS states the treatment is not recommended during pregnancy or breastfeeding, because safety data are limited.
- Conditions that affect nerves and muscles, such as myasthenia gravis (a condition causing muscle weakness), amyotrophic lateral sclerosis or Lambert-Eaton syndrome, which can make the effects of the drug stronger or more widespread.
- A previous allergic reaction to any botulinum toxin product.
- Infection, inflammation or a skin condition at the planned injection site.
- Swallowing or breathing difficulties, or previous surgery to the face that changed muscle position.
Medicines matter too. Certain antibiotics, muscle relaxants and other drugs can interact with botulinum toxin, and blood-thinning medicines raise the chance of bruising. None of these means you must change what you take; it means the prescriber needs the complete list, including supplements, to make the decision.
In the UK it is illegal to give cosmetic botulinum toxin to anyone under 18, and the NHS flags this as a safeguard rather than a formality. Wherever you are, being asked to wait is not a rejection. It is the treating team weighing a temporary cosmetic benefit against a risk they cannot fully quantify for you.
What actually happens at a first appointment?
The most useful part of a first visit is often the least dramatic: a conversation and a mirror. A clinician who is doing the job properly will ask you to frown, raise your brows, squint and smile, and will watch how the muscles move rather than where the lines sit. They will ask about your medical history, your medicines and supplements, any previous cosmetic treatments, and what has prompted the visit now.
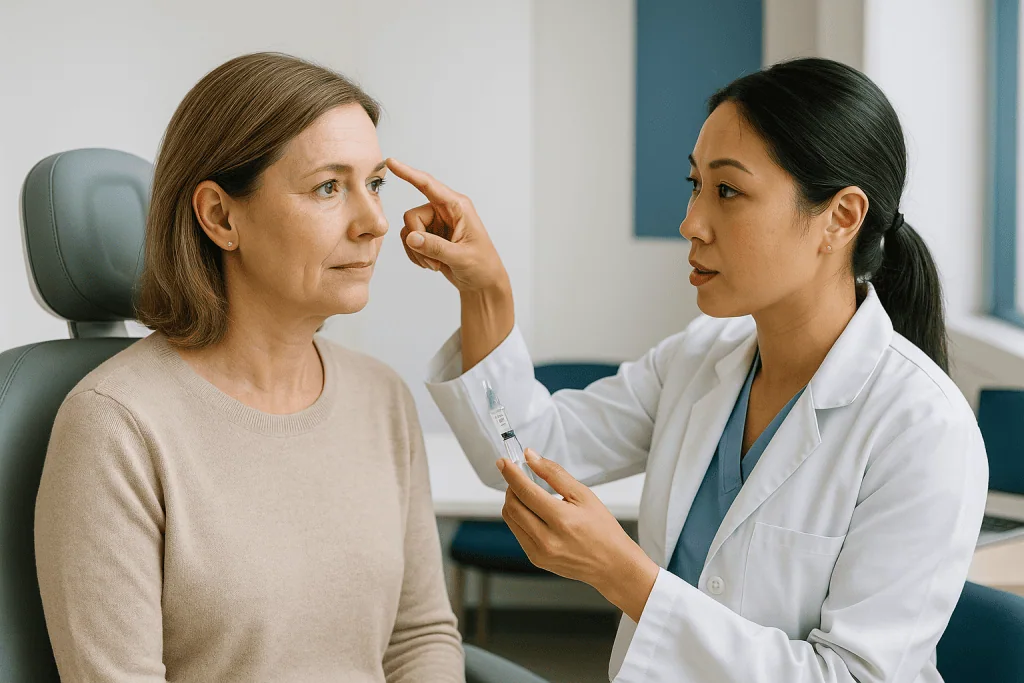
The NHS recommends that the person injecting be a trained, registered healthcare professional, and that the medicine be prescribed following a face-to-face assessment. Ask who is prescribing and who is injecting; in some settings these are different people, and you are entitled to know both.
The injections themselves are quick. The skin is cleaned, sometimes a topical numbing cream or ice is offered, and a fine needle delivers a series of small injections into the chosen muscles. Cleveland Clinic describes the sensation as a brief pinch or sting. Most people are in and out within a short appointment, and no bandage is needed.
What you should leave with is more than a tissue. A reasonable standard includes:
- A record of which product was used and where it was placed.
- Written aftercare advice, including what to avoid and for roughly how long.
- A contact number for problems, and clarity about who will answer it.
- A planned review, since the full effect is not visible on the day.
If any of those are missing, ask. The NHS specifically advises checking that the practitioner has insurance and a clear complaints and complications process. This is a medical procedure delivered in a cosmetic setting; the standards of the former should apply to the latter.
How long does Botox last, and when does it start working?
Nothing happens in the car on the way home, and that unnerves people. Botulinum toxin has to be taken up into the nerve endings before it can block anything, and that takes time. The NHS says it can take two to three days for the effect to begin and two to three weeks to see the full result. Mayo Clinic gives a similar picture, with early changes within one to three days and the complete effect over the following weeks.
Duration is the other half of the question, and the answer is consistent across sources: the NHS states that effects usually last around three or four months, and Mayo Clinic gives a range of three to four months or longer depending on the problem being treated and the individual. The fade is gradual. Movement creeps back, often noticed first in the strongest muscles, and lines that were softened begin to reappear with expression.
Several things influence where you fall within that range, and none can be predicted precisely:
- How strong the treated muscle is. Larger, more active muscles tend to recover movement sooner.
- How much was used, a decision that belongs to the prescriber and is balanced against side-effect risk.
- Individual metabolism and, for some people, the pattern of previous treatments.
The honest framing is this: duration is a typical range drawn from clinical experience and product labeling, not a guarantee for your face. A first treatment is partly a diagnostic exercise. Your clinician learns how your muscles respond and how long the effect holds, and that information shapes the plan for the second visit far more than any average does.
Ask at the consultation: “When will you review me, and what will you be looking for?” The answer should sit inside the two-to-three-week window when the full effect is visible.
How often can you get Botox? Repeat timing explained
Repeat timing is where marketing and medicine most often part ways. The temptation, once the effect starts to fade, is to top up early so movement never returns. Most clinicians resist that, and there are reasons beyond the calendar.
The first is that the drug is still active. Injecting again while the previous treatment is working means stacking one dose on another, which raises the risk of over-relaxation, asymmetry or a heavy brow without adding much duration. The second is a theoretical one that clinicians take seriously: very frequent repeat exposure to any protein medicine may, in a small number of people, encourage the immune system to produce antibodies that reduce its effect over time. Spacing treatments sensibly is one of the ways prescribers try to limit that possibility.
In practice, repeat timing tends to track the typical duration described by the NHS and Mayo Clinic, which is roughly every three to four months, with the exact interval set by how you respond and reviewed each time. Some people find they can go longer between treatments after several cycles; others do not. Your clinician, not a reminder text, should decide.
| Stage | Typical timing (NHS, Mayo Clinic) | What is usually happening |
|---|---|---|
| Effect begins | Around 2 to 3 days | Nerve uptake starting; movement begins to soften |
| Full effect | Around 2 to 3 weeks | Best time for a review or small adjustment |
| Plateau | Weeks to months | Stable result; skin not being creased by movement |
| Fade | Around 3 to 4 months | Nerve connections recover; movement returns gradually |
| Repeat considered | When effect has largely worn off | Prescriber reassesses goals and response |
Bring two questions: “How will we decide when the next treatment is due?” and “What would make you suggest waiting longer?” Both signal that you understand this is a plan, not a subscription.
What should you not do before Botox?
Preparation is mostly about bruising and honesty. The needle is fine and the injections shallow, but the face is rich in small blood vessels, and anything that thins the blood or dilates those vessels makes a bruise more likely. Cleveland Clinic notes that alcohol, aspirin, anti-inflammatory painkillers and some supplements can increase bruising, and many clinicians ask patients to avoid these in the days beforehand where it is safe to do so.
The critical qualifier is where it is safe. If you take aspirin, an anticoagulant or any other blood-thinning medicine on prescription, do not stop it for a cosmetic appointment. A bruise fades; a clot does not. Tell the injecting clinician what you take and let them decide whether to proceed, adjust technique, or ask you to check with your prescribing doctor first.
Beyond medicines, a few practical points come up repeatedly:
- Arrive with a clean face and no heavy makeup over the treatment area, so the skin can be assessed and cleaned properly.
- Mention any recent facial treatments, skin infections, cold sores or dental work, which can change the plan.
- Do not book it the day before something important. The full effect takes weeks, and any bruise is most visible in the first days.
- Eat normally. Fainting from skipped meals and nerves is more common than any reaction to the drug.
Then there is the honesty part. Say if you are pregnant, might be, or are breastfeeding. Say if you have a neuromuscular condition or have had a reaction to any injectable before. Say if you had botulinum toxin elsewhere recently, even if you are embarrassed about the result. The single most avoidable complication is one caused by information the clinician never had.
What you should not do is arrive with a fixed idea of amount or placement copied from someone else’s face. Muscles differ; so should plans.
What is the 4-hour rule for Botox, and what is the rule of 3?
Both phrases circulate widely, and neither appears in any clinical guideline. That does not make them useless; it means you should know what they are and what they are not.
The “4-hour rule” refers to common aftercare advice to stay upright and avoid lying down, bending forward for long stretches, or pressing on the treated area for the first few hours after injection. The reasoning is mechanical: the drug is placed in a specific muscle, and the concern is that pressure or position could encourage it to drift into a neighboring one, such as the muscle that lifts the eyelid. The NHS advises avoiding rubbing or massaging the treated area for a few days after treatment. The specific figure of four hours is convention rather than evidence; studies testing exactly how long position matters are limited. Following the clinician’s written aftercare is sensible, and the risk of breaking it once is small.
The “rule of 3” is vaguer still and means different things in different places. Some use it to describe the timeline: effects begin at roughly three days, settle over three weeks, and last about three months, which is a loose summary of the NHS and Mayo Clinic figures. Others use it to mean treating three areas at once, or waiting three months between treatments. It is a memory aid, not a rule. If someone quotes it to you, ask which version they mean and why.
Questions worth asking on aftercare, because they turn folklore into instructions you can trust:
- “What exactly should I avoid after treatment, and for how long?”
- “Is it a problem if I exercise, fly, or have a facial this week?”
- “If I accidentally rub the area, what should I watch for?”
The answers will vary slightly between clinicians, and that is fine. What matters is that they come from the person who knows where the drug was placed.
What do the first two weeks after treatment usually look like?
Day one is anticlimactic. Small raised bumps at the injection sites, like insect bites, flatten within an hour or so. A pinprick bruise or two may appear. Mayo Clinic lists mild pain, swelling or bruising at the injection site and headache or flu-like symptoms among the common, short-lived side effects. Your face moves exactly as it did that morning, and you may wonder whether anything was injected at all.
Somewhere between the second and fourth day, according to NHS timelines, the change begins. Frowning feels slightly effortful, as though the muscle is answering late. This is the period when people over-scrutinize the mirror and worry about asymmetry; one side often responds a day before the other, and that difference usually evens out.
By the end of the second week, and sometimes into the third, the effect is complete. This is when the result should be judged and when most clinicians schedule a review. The NHS advises a follow-up in this window if adjustment is needed. Small tweaks, such as balancing a brow that has settled unevenly, are simpler to make now than to live with for three months.
Things that are usually normal in this period:
- A mild, tight or heavy feeling in the forehead as you adjust to reduced movement.
- Brief headache in the first day or two.
- A bruise that yellows and fades over a week or so.
- Noticing you use other muscles differently, which typically settles.
Things that are not part of the normal course, and belong in the “call your clinician” category, are covered below. The practical advice for these two weeks is patience: photograph your face at rest and in expression on the day, then again at the review, and compare those rather than your memory.
What are the risks and side effects of botulinum toxin injections?
Botulinum toxin has a long safety record when prescribed and injected properly, and the NHS describes it as generally safe when given by a suitably trained professional. Safe is not the same as risk-free, and a first-time patient deserves the full list rather than the reassuring half.
Common and usually short-lived effects, as listed by Mayo Clinic and MedlinePlus, include bruising, swelling or tenderness where the needle went in, headache, and temporary flu-like symptoms. Less common but well recognized are effects of the drug reaching a muscle it was not intended for: a drooping eyelid or brow, an uneven smile, a crooked expression, dry or watering eyes. These are not dangerous, but they can last for weeks to months because the drug wears off on its own schedule. There is no reversal agent.
Rare and serious effects are why this is a prescription medicine. MedlinePlus carries the regulator’s warning that botulinum toxin can, in rare cases, spread beyond the injection area and cause symptoms of botulism: muscle weakness elsewhere in the body, double or blurred vision, drooping eyelids, hoarseness, difficulty speaking clearly, trouble swallowing, or trouble breathing. These have been reported mainly in medical rather than cosmetic uses, but the warning applies to all. Allergic reactions, including itching, rash, wheezing or dizziness, are also possible.
Alternatives exist, and a fair consultation mentions them. For movement lines the options are essentially to treat or to accept; for lines present at rest, skin-directed approaches or, for some concerns, dermal fillers (injectable gels that add volume rather than relax muscle) may be discussed. None is universally better. Each has its own profile, and the clinician’s job is to match one to the actual problem.
Ask directly: “What is the most likely thing to go wrong in my face, and what would you do about it?” A confident, specific answer is reassuring. A dismissive one is information too.
What people often get wrong about Botox
“It will freeze my face.” A frozen look is a result of amount and placement, not the drug itself. The mechanism is the same whether a muscle is relaxed slightly or completely; the difference lies in the prescriber’s plan. Preserving some movement is a legitimate goal to state out loud.
“If I stop, my wrinkles will be worse than before.” There is no mechanism for this. When the effect fades, the muscle regains its previous strength and the lines return to roughly where they would have been anyway. Some people feel they look worse because they have grown used to a smoother version of themselves, which is a perception problem, not a rebound.
“It’s a filler.” Botulinum toxin adds nothing. It relaxes. Fillers are a different class of product with different risks. Confusing the two leads people to expect plumping from a drug that cannot deliver it.
“It prevents aging.” By reducing repeated creasing, it may slow the deepening of specific movement lines while it is active. It does nothing for sun damage, volume loss, skin laxity or gravity. The evidence for long-term prevention is limited and observational.
“More is better, and earlier repeats keep it working.” Larger amounts raise the risk of drooping and heaviness without proportionally extending duration, and early repeats stack effects. The NHS and Mayo Clinic timelines of three to four months reflect how the nerve recovers, and no schedule changes that biology.
“It’s just a beauty treatment, so who injects it doesn’t matter.” It is a prescription-only medicine with a regulator’s warning about spread beyond the injection site. The NHS is explicit that it should be prescribed and given by trained, registered healthcare professionals in a setting equipped to manage complications.
“A bad result can be reversed.” It cannot. There is no antidote for cosmetic over-treatment; time is the only remedy, which is the strongest argument for a conservative first treatment and a proper review.
Botox consultation questions: what to ask your care team
A good consultation should feel a little like a job interview in which you are the employer. These questions, grouped by theme, are the ones that most reliably reveal whether the person in front of you is thinking about your face or about the next appointment.
About the person and the product
- “Who is prescribing this, who is injecting it, and what are your professional registrations?”
- “Which botulinum toxin product will you use, and where is it sourced?” (Licensed products are regulated; the NHS warns against unlicensed or counterfeit supply.)
- “How many treatments of this kind do you carry out, and how do you keep your training current?”
About my face
- “Which muscles do you propose treating, and why those?”
- “What will I be able to do and not do with my face afterward?”
- “Is there anything about my anatomy that raises the risk of a drooping eyelid or heavy brow?”
- “Would you suggest a smaller first treatment and a review?”
About safety
- “Is there anything in my medical history or medicines that should make us pause?”
- “What complications have you seen, and how were they handled?”
- “If something goes wrong tonight or at the weekend, who do I contact?”
- “Are you insured for this procedure?”
About time
- “When will I see the full effect, and when will you review me?”
- “How long do effects typically last in someone with muscles like mine?”
- “How will we decide the timing of any repeat?”
Write the answers down. The NHS advises taking time to think after a consultation rather than proceeding the same day, and a written record lets you compare what was promised with what happened. Any clinician who is impatient with this list has told you something useful about how they will handle a problem later.
What I wish I knew before getting Botox: lessons from second-timers
Ask people who have had botulinum toxin more than once what they would tell their first-time self, and the answers cluster around a few themes that rarely make it onto clinic websites.
It is a commitment, not an event. The NHS and Mayo Clinic duration of three to four months means that if you like the result, you are choosing a recurring medical appointment. Decide before the first injection whether that suits your life, your budget and your tolerance for needles, rather than discovering it when the effect fades.
Photographs beat memory. Take pictures at rest and mid-expression before treatment and again at the two-to-three-week review. People consistently misremember their own baseline, and a photo settles the question of whether the treatment did what was agreed.
The first treatment is information. A conservative plan may leave you wanting slightly more, and that is the point. Your clinician learns how your muscles respond and how long the effect holds; the second visit is usually where the plan becomes precise.
Someone will notice, and it will not be who you expect. Most people report that friends do not comment, but that they themselves catch a stillness in video calls or photos. Deciding in advance how much movement you want to keep avoids that small shock.
The aftercare paper matters. The advice to avoid rubbing the area, the review date and the emergency contact number are the parts people lose. Photograph the sheet.
It does not change the things it cannot reach. Sleep, sun protection, smoking and skin care shape how the face ages far more than a drug that relaxes a few muscles for a season. Second-timers often say the treatment made them pay more attention to those basics, which is the quietest good outcome of all.
Above all, they say: I wish I had asked more and agreed to less at the first visit.
When to call your doctor
Most people need nothing more after botulinum toxin than patience and a review appointment. A small number will need to make a phone call, and knowing which symptoms justify it is part of being properly prepared. MedlinePlus and Mayo Clinic list the signs below, and they fall into two groups.
Contact the injecting clinician promptly if you notice, in the days or weeks after treatment:
- A drooping eyelid or brow, or one eye that will not close fully.
- Marked asymmetry of expression or a smile that has changed.
- Persistent dry, gritty or watering eyes.
- Redness, warmth, increasing pain or pus at an injection site, which can indicate infection.
- A headache that is severe or does not settle.
These are unlikely to be dangerous, but they may need assessment, eye protection or a planned adjustment, and the clinician who placed the drug is best placed to advise.
Seek emergency care immediately if any of the following develop, whether hours or weeks after the injections, because they may indicate the drug has spread beyond the intended area or an allergic reaction is occurring:
- Difficulty swallowing, speaking clearly, or breathing.
- Generalized muscle weakness, or weakness away from the treated area.
- Double vision, blurred vision or severe drooping of both eyelids.
- Hoarseness or loss of voice.
- Itching, rash, swelling of the face or throat, wheezing, faintness or dizziness.
The regulator’s warning carried by MedlinePlus notes that these serious effects are rare, and that difficulty swallowing may last for weeks and carries a risk of choking or inhaling food, so it should never be waited out at home. Tell the emergency team exactly what was injected, where, and when; the record you were given at the appointment is for this moment.
Whatever the symptom, the decision about what happens next belongs to the treating team, not to a forum or a message thread. Call.
Frequently asked questions
What are the most important questions to ask before Botox?
Ask who is prescribing and injecting and what their registrations are, which licensed product is being used, which muscles will be treated and why, what your face will and will not be able to do afterward, what side effects are realistic for your anatomy, when you will be reviewed, and who to contact if something goes wrong. Write the answers down and take time before deciding.
How long does Botox last for first-time patients?
The NHS states that effects usually last around three or four months, and Mayo Clinic gives a similar range. First-timers sometimes notice movement returning a little sooner in strong muscles. Duration varies with muscle size, the amount used and individual response, so a first treatment is partly a way for your clinician to learn how long the effect holds in your face.
How often can you get Botox safely?
Most clinicians time repeats to when the previous effect has largely worn off, which typically means roughly every three to four months based on NHS and Mayo Clinic duration figures. Injecting earlier stacks doses, raising the risk of heaviness or asymmetry, and very frequent exposure may in some people encourage antibodies that reduce effect. The interval is a prescriber’s decision, reviewed at each visit.
What should you not do before Botox?
Avoid alcohol and, where safe, over-the-counter painkillers and supplements that increase bruising, but never stop a prescribed blood thinner or any other prescription medicine for a cosmetic appointment without asking the prescriber. Arrive without heavy makeup, eat normally, and disclose pregnancy, breastfeeding, neuromuscular conditions, allergies and any recent injectable treatments so the clinician has complete information.
What is the 4-hour rule for Botox?
It refers to common aftercare advice to stay upright and avoid lying down, bending forward for long periods or pressing on the treated area for the first few hours, to reduce the chance of the drug drifting into a neighboring muscle. The four-hour figure is convention rather than guideline; the NHS more broadly advises not rubbing or massaging the area for a few days. Follow your clinician’s written instructions.
What is the rule of 3 in Botox?
It is a memory aid, not a medical rule, and it means different things to different people. The most common version summarizes the timeline: effects begin at around three days, settle over about three weeks and last roughly three months, which loosely matches NHS and Mayo Clinic figures. Others use it to mean treating three areas or waiting three months between visits. Ask which version is meant.
What do people wish they knew before getting Botox?
That it is a recurring commitment rather than a one-off, that the full effect takes two to three weeks and should be judged at a review, that before-and-after photographs beat memory, that a conservative first treatment is information rather than a disappointment, and that there is no reversal agent, so agreeing on how much movement to keep matters more than anything decided afterward.
Can Botox be reversed if I don't like the result?
No. There is no antidote for the cosmetic effects of botulinum toxin; the result fades only as the nerve endings recover over roughly three to four months, according to NHS and Mayo Clinic timelines. Small imbalances can sometimes be improved at the two-to-three-week review by treating an opposing muscle, but over-relaxation itself must be waited out. This is the strongest argument for a cautious first visit.
Who should not get botulinum toxin injections?
People who are pregnant or breastfeeding, those with neuromuscular conditions such as myasthenia gravis or amyotrophic lateral sclerosis, anyone with a previous allergic reaction to a botulinum toxin product, and anyone with infection at the injection site are commonly advised against or asked to wait. Certain antibiotics and muscle relaxants can interact. The prescriber makes the final decision after reviewing your full medical history.
What are the warning signs after Botox that need urgent care?
Difficulty swallowing, speaking or breathing, generalized or distant muscle weakness, double or blurred vision, severe drooping of both eyelids, hoarseness, or signs of allergy such as facial swelling, wheezing, rash or faintness need emergency assessment, because they can indicate the toxin has spread or a reaction is occurring. A drooping eyelid, asymmetry, dry eyes or an infected injection site should prompt a call to the injecting clinician.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Why Skin Grafts Sometimes Fail: Pressure, Infection, Smoking and the Signs Your Team Watches
Skin grafts fail most often because something separates the graft from the wound bed before new blood vessels can grow into it: a pocket…
Caring for the Skin After Cryotherapy: Dressings, Showering and Leaving the Crust Alone
After cryotherapy, keep the treated spot clean, let any blister flatten on its own, and leave the crust in place until it separates by…

Reconstructive Surgery Recovery: Drains, Dressings and the Weeks of Swelling Explained
Recovery after reconstructive surgery moves in stages: drains usually come out within the first one to three weeks once output falls, dressings are reduced…
Dermabrasion Risks Explained: Pigment Changes, Scarring and Infection Signs to Report
Dermabrasion risks include temporary redness and swelling, changes in skin color that can be lasting in deeper skin tones, scarring when treatment goes deep,…

Facial Reconstruction After Trauma: How Bone, Nerve and Soft-Tissue Repairs Are Sequenced
Facial trauma reconstruction surgery is sequenced by priority, not by appearance. Life-threatening problems come first: the airway, bleeding, the brain and the neck. Sight-threatening…

Ablative vs Non-Ablative Laser Resurfacing: Depth, Downtime and Results Compared
Ablative laser resurfacing removes the skin's outer layer and heats the layer beneath, giving larger changes in wrinkles, scars and texture in exchange for…