

Recent Antibiotics, Kidney Disease or Allergies: How They Shape Acute UTI Treatment

Key Takeaways
- Antibiotics taken for any reason in roughly the previous three months are one of the strongest predictors that a urinary infection will resist the same drug or class.
- Some UTI antibiotics work only because the kidneys concentrate them in urine, so reduced kidney function can leave urine levels too low while blood levels rise.
- The CDC reports that most people carrying a penicillin allergy label are not truly allergic on testing, and unverified labels push prescribers toward broader, less ideal drugs.
- Recurrent UTI is defined as two culture-confirmed infections in six months or three in a year, and the first step is distinguishing relapse from reinfection from mimics.
- Bacteria in the urine without symptoms is generally not treated outside pregnancy, because treating it does not prevent future infections and does drive resistance.
- A urine culture typically reports the organism and its susceptibility within 24–72 hours, which is why a mid-course change of antibiotic is the system working, not failing.
Recent antibiotic use, reduced kidney function and drug allergies each narrow which antibiotics are likely to work safely for an acute urinary tract infection. Antibiotics taken in roughly the past three months raise the odds of resistant bacteria, kidney disease changes how some drugs reach the urine, and a documented allergy rules out certain classes. Clinicians weigh all three, often with a urine culture, before prescribing.
The pharmacy bag from last month is still on the counter. A sinus infection, seven days of capsules, done and forgotten. Now the burning is back, the bathroom trips are relentless, and the nurse on the phone asks a question that seems oddly specific: “Have you taken any antibiotics recently?”
That question is not small talk. Recent antibiotic use before a UTI is one of the strongest predictors that the bacteria involved will shrug off the usual first choice. Add a kidney condition, or a penicillin allergy noted in a chart years ago, and the standard script quietly rewrites itself.
Most people never see that reasoning. They see a prescription and a pharmacist. This article walks through what happens between the two, so the choices your care team makes look less like guesswork and more like what they are: a short, structured piece of detective work.
Why recent antibiotic use changes how a UTI is treated
Bacteria are not passive. Every course of antibiotics, for any reason, applies selection pressure to the trillions of microbes living in the gut, where most urinary pathogens start out. The susceptible strains die; the few carrying resistance genes survive and multiply into the space left behind. When some of those survivors later travel the short distance to the urethra and bladder, the infection they cause is more likely to resist the same drug, or drugs that work in a similar way.
This is why a clinician treating an acute UTI will ask not only whether you have taken antibiotics, but which one and when. A recent course of a fluoroquinolone (a class that blocks bacterial DNA copying) predicts fluoroquinolone resistance in particular. A recent course of trimethoprim-sulfamethoxazole (a combination that starves bacteria of folate) predicts resistance to that combination. The pattern is drug-specific, not random.
Guidelines from major infectious disease bodies, summarized by sources such as the National Institute of Diabetes and Digestive and Kidney Diseases, encourage clinicians to think about local resistance patterns and individual risk before choosing an empiric antibiotic, meaning one started before culture results are back. Recent antibiotic exposure sits near the top of that risk list.
The practical consequence is not that you will be denied treatment. It is that the first drug chosen may differ from the one a friend received, a urine culture becomes more valuable, and the clinician may plan a follow-up check on whether the culture result matches the drug already started. The CDC’s broader message on antimicrobial resistance applies at the level of a single bladder: yesterday’s antibiotic shapes today’s options.
What actually happens when a clinician chooses your UTI antibiotic
Picture a decision tree with four branches, all evaluated in a few minutes. The first branch is location: is this a bladder infection (cystitis) or has it climbed to the kidneys (pyelonephritis)? Kidney involvement, suggested by fever, flank pain or feeling systemically unwell, calls for antibiotics that reach high concentrations in kidney tissue and blood, not just in urine.

The second branch is the patient. Sex, pregnancy, age, diabetes, a urinary catheter, structural problems in the urinary tract and kidney function all influence which drugs are safe and which infections count as “complicated,” a label that generally lengthens treatment and widens the antibiotic net.
The third branch is the microbe’s likely identity. Escherichia coli (E. coli), a gut bacterium, causes the large majority of uncomplicated bladder infections, according to Cleveland Clinic and the NIDDK. Others, such as Klebsiella, Proteus, Enterococcus and Staphylococcus saprophyticus, appear less often but matter because they respond to different drugs.
The fourth branch is history: previous cultures, previous antibiotics and any allergy record. A culture from six months ago showing a resistant organism is a strong hint about what is growing now.
Only after these branches are weighed does a clinician pick an empiric drug, usually from a short list of first-line agents for uncomplicated cystitis that includes nitrofurantoin (which concentrates in urine and damages several bacterial systems at once), fosfomycin (which blocks cell-wall building) and trimethoprim-sulfamethoxazole. If a urine sample was sent for culture, the laboratory typically reports the organism and its susceptibility pattern within 24–72 hours, per Mayo Clinic, and the plan is adjusted if needed. Nothing about this is a one-size template; it is pattern matching against your specific record.
Recent antibiotic use and UTI resistance: how long does the effect last?
The clinical shorthand is the three-month window. Antibiotic exposure within roughly the previous 90 days is the period most consistently linked in studies to higher rates of resistant urinary bacteria, and it is the timeframe that appears in infectious disease guidance on when to avoid re-using a drug empirically. The effect does not switch off on day 91; it fades gradually as the gut microbiome recovers, and heavy or repeated courses leave a longer shadow.
Why three months? Research summarized by the NIH and CDC on the gut microbiome suggests that after a single course, the overall community of bacteria rebounds over weeks, but the proportion carrying resistance genes can stay elevated for months. Those genes also move between species on small circular pieces of DNA called plasmids, which means resistance selected by treating one infection can end up in an entirely different bacterium.
Not every recent antibiotic carries the same weight. Exposure to broad-spectrum agents (drugs that kill many bacterial families at once) tends to matter more than a narrow-spectrum drug aimed at one organism. A single topical treatment matters far less than a systemic course. Hospital stays, nursing-home residence and recent travel to regions with high resistance rates add further risk, which is why intake questions sometimes feel like a travel diary.
What this means at the bedside is straightforward. If your last UTI was treated three weeks ago and symptoms are back, most clinicians will not simply repeat the same prescription. They will send a culture, consider a different class, and look for reasons the first treatment may have fallen short, whether that is resistance, incomplete clearance, or a different problem altogether. Recent antibiotic use before a UTI is a reason to test more, not to treat blindly.
UTI antibiotics and kidney disease: why filtration changes the choice
The kidneys are not just the organs at risk in a UTI; they are also the exit route for most UTI antibiotics. Many of these drugs work precisely because the kidneys concentrate them in urine, delivering far higher levels to the bladder than to the rest of the body. Chronic kidney disease (CKD), a long-term reduction in the kidneys’ filtering capacity, interferes with that arrangement in two directions.
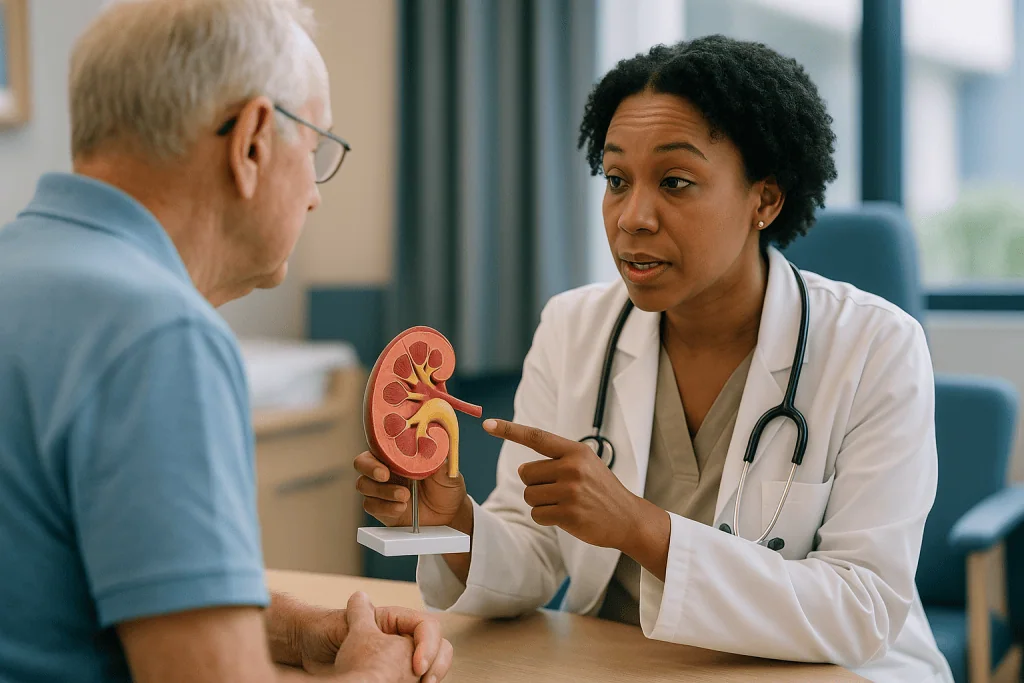
First, less filtration means less drug reaches the urine. Nitrofurantoin is the classic example: its usefulness depends on being concentrated in urine, and clinicians generally avoid it when kidney function is significantly reduced because urinary levels may be too low to work while blood levels rise, according to the NIDDK and Mayo Clinic. Second, drugs that are cleared by the kidneys can accumulate in the bloodstream when clearance is slow, raising the risk of side effects. Some antibiotics, including the aminoglycoside class, can themselves injure kidney tissue, so they are used cautiously and with monitoring in anyone whose kidneys are already under strain.
Kidney function is estimated with a blood test called eGFR (estimated glomerular filtration rate), reported as a number that roughly corresponds to the percentage of normal filtering capacity. Prescribers use that number, alongside age and body size, to decide whether a drug is suitable and whether the amount needs adjusting. Those adjustments are individual and belong to the prescriber; the point for patients is simply to make sure the clinician treating the UTI knows about the kidney diagnosis and has a recent eGFR.
People with CKD, a transplant kidney, kidney stones or a single kidney are also more likely to be treated as having a complicated UTI, which often means a culture, closer follow-up and a lower threshold for imaging. It is not alarmism. It reflects that the organ most likely to be harmed is the same one the medicine relies on.
UTI antibiotics with a penicillin allergy: what "allergic" really means
Allergy records are sticky. A rash in childhood, a stomach upset in college, a grandparent’s reaction remembered secondhand: all of these can become a permanent “penicillin allergy” flag in a medical chart. The CDC notes that although roughly one in ten Americans report a penicillin allergy, the great majority are not truly allergic when formally evaluated, because many reactions were never allergic in the first place and true allergy often fades over time.
That distinction matters for UTIs. Penicillin-family drugs and their relatives, the cephalosporins (both belong to the beta-lactam group, which attacks the bacterial cell wall), are common choices for kidney infections, for UTIs in pregnancy, and for children. A recorded allergy pushes prescribers toward alternatives that may be broader than needed, less effective against the likely organism, or more likely to fuel resistance. Studies summarized by the CDC link unverified penicillin allergy labels with more resistant infections and longer hospital stays.
Clinicians sort allergies by type. An immediate reaction with hives, swelling of the lips or face, wheezing or a drop in blood pressure suggests a true, potentially serious allergy. A delayed, mild rash days into a course, or nausea and diarrhea, usually does not. A severe skin or organ reaction is a third category with its own rules. Where the history is unclear, referral for allergy testing can clarify the record and reopen options for future infections.
Sulfonamide allergy is the other one that frequently surfaces in UTI care, since trimethoprim-sulfamethoxazole contains a sulfonamide component. Fluoroquinolone intolerance, and rarer reactions to nitrofurantoin, also shape the list. Bring the details: what happened, how soon after the first dose, and how long ago. A precise story is worth more to your prescriber than a one-word label, and the decision on what to use next always rests with them.
Who is usually treated right away, and who is usually asked to wait
Not every positive test earns a prescription, and not every prescription is written on day one. Guidelines from bodies including NICE and the NHS draw a line between people who need antibiotics promptly and people for whom waiting, or not treating at all, is the safer course.
Prompt treatment is typical for anyone with signs of a kidney infection, for pregnant people (untreated bacteria in the urine during pregnancy raises the risk of kidney infection and preterm birth, per MedlinePlus), for men (whose UTIs are treated as complicated because the prostate may be involved), for children, and for anyone with a catheter, diabetes, a weakened immune system or a known urinary tract abnormality. Older adults with confusion or a fall alongside urinary symptoms are also assessed quickly, because infection in this group can present atypically.
Watchful waiting, sometimes with a “back-up” prescription to fill only if symptoms worsen or fail to settle within about 48 hours, is an option the NHS describes for otherwise healthy, non-pregnant women with mild bladder symptoms. Many mild bladder infections improve on their own, and delaying the antibiotic by a day or two, with fluids and pain relief advised by the clinician, avoids exposure for those who recover without it.
A third group is asked not to treat at all: people who have bacteria in the urine but no symptoms, a state called asymptomatic bacteriuria. Outside pregnancy and certain urological procedures, treating it does not prevent future infections and does drive resistance, according to guidance summarized by Harvard Health. This is why a routine urine dip showing bacteria in an older adult who feels fine is often, correctly, left alone.
Where you fall on this spectrum is a clinical judgment. Recent antibiotic use, kidney disease and allergies all nudge that judgment toward earlier culture and closer follow-up rather than toward less care.
How each factor shifts the plan: a side-by-side view
Three different histories, three different conversations. The table below summarizes, in guideline-level terms, how each factor tends to change the approach to an acute UTI. It is a map of the reasoning, not a prescription; the specifics belong to the clinician who knows your record.
| Factor | What changes in the assessment | What often changes in treatment | Why it matters |
|---|---|---|---|
| Antibiotics in the past ~3 months | Urine culture strongly favored; prior culture results reviewed | Avoid re-using the same drug or class empirically; plan to adjust once the culture result is back | Recent exposure selects for resistant gut bacteria that seed the bladder |
| Chronic kidney disease or reduced eGFR | Recent kidney function checked; infection more likely classed as complicated | Some urine-concentrated drugs avoided; kidney-toxic classes used cautiously with monitoring | Less filtration means lower urine drug levels and higher blood levels |
| Documented penicillin or sulfonamide allergy | Reaction type and timing clarified; allergy testing considered for unclear histories | Beta-lactam or sulfonamide-containing drugs avoided when the allergy is genuine; alternatives chosen | Mislabelled allergies push toward broader, less ideal drugs |
| Signs of kidney infection | Urgent assessment; blood tests and sometimes imaging | Drugs that reach kidney tissue and blood; longer course; occasionally intravenous start | Bladder-only agents do not treat the kidney adequately |
| Pregnancy, male sex, catheter, diabetes | Treated as complicated; culture routine | Longer course; specific drug classes preferred or avoided | Higher risk of progression and different likely organisms |
Two patterns stand out. First, every factor increases the value of a urine culture, because it replaces guesswork with a laboratory answer. Second, none of these factors removes treatment options entirely; they redirect them. Someone with a true penicillin allergy and moderate kidney disease who took antibiotics last month still has effective choices. The route to them just involves more information and, sometimes, a call from the clinic when the culture returns.
What is the hardest UTI bacteria to get rid of, and what is antibiotic resistant UTI treatment like?
The question people type into search bars has a real answer, and it is less about a single villain than about a set of resistance mechanisms. The most troublesome urinary pathogens are gut bacteria, chiefly E. coli and Klebsiella, that produce extended-spectrum beta-lactamases (ESBLs), enzymes that break down most penicillins and cephalosporins. The CDC lists ESBL-producing Enterobacterales as a serious threat because they leave few oral options.
One step further along are carbapenem-resistant Enterobacterales (CRE), which resist even the carbapenems, a class usually held in reserve for the hardest infections. The CDC classifies CRE as an urgent threat. Pseudomonas aeruginosa, more common in people with catheters or recent hospital stays, and vancomycin-resistant Enterococcus (VRE) round out the list. These organisms are hard to treat not because they cause worse symptoms but because the medicines that reach them safely are limited.
Antibiotic resistant UTI treatment therefore looks different from a routine prescription. The culture and susceptibility report becomes essential, since it shows which drugs the specific organism still responds to. Treatment may involve an older drug revived for the purpose, an intravenous antibiotic given in a clinic or at home through an outpatient infusion program, or a newer agent designed to evade a particular resistance enzyme. An infectious disease specialist is often involved. Follow-up cultures, and a search for a reservoir such as a stone, a catheter or incomplete bladder emptying, are more likely.
Resistance is not the same as being untreatable. Even highly resistant organisms usually remain susceptible to something; the work is in finding it quickly and safely. What patients can control is the input side: taking antibiotics only when prescribed, finishing the course as directed unless told otherwise, and giving prescribers a full history so the first choice is more likely to be the right one.
Is there a new antibiotic for UTIs, and who is it usually for?
Headlines about the “first new UTI antibiotic in decades” are accurate in one sense: regulators have approved oral antibiotics for uncomplicated urinary infections that come from entirely new chemical classes, working on bacterial enzymes that older drugs do not target. That novelty is genuinely useful, because bacteria that have evolved around older mechanisms have not yet had the chance to evolve around these.
The more important context is how such medicines are positioned. New antibiotics are, by design, held back. The CDC and WHO both describe antimicrobial stewardship, the deliberate effort to use antibiotics only when needed and to preserve the effectiveness of newer ones, as central to slowing resistance. A newly approved drug is typically reserved for people with documented resistance to first-line agents, or for whom first-line agents are unsuitable because of allergy, kidney function or intolerance. It is not a general upgrade, and the evidence supporting each new agent comes from trials in specific populations that may not include people with kidney infections, pregnancy or severe kidney disease.
Older first-line drugs remain the guideline recommendation for uncomplicated cystitis in most people for a reason. Decades of data support their safety, resistance rates to some of them remain relatively low in community settings, and using them first keeps newer options in reserve for when they are truly needed. Mayo Clinic and the NIDDK both emphasize matching the drug to the organism and the patient, not to the calendar.
Asking your clinician whether a newer agent is appropriate is a reasonable question, especially if you have a culture showing resistance to the usual choices. The answer will depend on what grew, what your kidneys can handle, what you have reacted to before and what local resistance data show. As with everything in this article, that judgment belongs to the prescribing clinician.
What mimics a UTI but isn't one?
Here is an uncomfortable truth behind many “the antibiotics didn’t work” stories: the problem was never a bacterial bladder infection. Urinary urgency, burning and pelvic discomfort are shared by a long list of conditions, and a urine culture that grows nothing, or grows only small amounts of mixed skin bacteria, is a strong signal to look elsewhere.
Vaginal conditions are the most common mimics. Yeast infections and bacterial vaginosis can both cause external burning with urination because urine passes over irritated tissue. After menopause, falling estrogen thins the lining of the vagina and urethra, a change called genitourinary syndrome of menopause, which produces urgency, burning and a genuinely higher UTI risk, according to Harvard Health. Sexually transmitted infections such as chlamydia and gonorrhea inflame the urethra and are easily mistaken for cystitis.
Bladder conditions without infection include interstitial cystitis, also called bladder pain syndrome, a chronic pain condition whose hallmark is pressure or pain that worsens as the bladder fills and eases with emptying, and overactive bladder, in which nerve and muscle signaling produces urgency without infection. Kidney stones passing down the ureter can cause urgency and blood in the urine. In men, prostatitis, inflammation of the prostate that may or may not be bacterial, is a frequent alternative. Irritants such as certain soaps, spermicides and some bladder-irritating foods and drinks can produce symptoms, and so can pelvic floor muscle tension.
None of this is a self-diagnosis list; several of these conditions overlap, and a few coexist with true infection. It is a reason to ask your clinician for a culture before a second or third round of antibiotics, and to expect questions about vaginal symptoms, sexual health, menopause status and pain patterns. Treating a mimic with antibiotics does not help it, does expose you to side effects, and adds to the resistance pressure described earlier.
Why have I had three UTIs in two months even after antibiotics? Recurrent UTI after antibiotics explained
Clinicians define recurrent UTI as two or more culture-confirmed infections in six months, or three or more in a year, according to Cleveland Clinic and Harvard Health. Three episodes in two months lands firmly in that territory, and the first task is to untangle which of three different things is happening.
The first possibility is relapse: the original infection was never fully cleared, and the same organism returned within days or a couple of weeks of finishing treatment. Relapse points toward resistance to the drug used, a course that was too short for the site of infection, or a hidden reservoir. Kidney stones, a bladder that does not empty completely, a urethral diverticulum (a small pouch off the urethra) or, in men, the prostate can all shelter bacteria where antibiotics reach poorly.
The second possibility is reinfection: a new organism, or the same species acquired fresh from the gut, after a symptom-free interval. Reinfection is the more common pattern and is driven by risk factors rather than treatment failure. Sexual activity, spermicide use, menopause-related tissue changes, diabetes, constipation and a family history of UTIs all raise the odds, per the NIDDK. Recent antibiotic use itself can contribute by disturbing the protective vaginal and gut bacteria that normally keep uropathogens in check.
The third possibility is that some or all of the episodes were mimics, treated presumptively without a culture.
Sorting this out means culturing every episode, comparing organisms and susceptibility patterns, and often imaging the urinary tract or measuring how much urine remains after voiding. Depending on the cause, options a clinician may discuss include addressing a reservoir, vaginal estrogen after menopause, behavioral changes, or preventive strategies that guidelines describe for recurrent UTI. Recurrent UTI after antibiotics is a pattern to investigate, not a reason to keep cycling through prescriptions.
What the following days and weeks usually look like
Timelines help because they tell you when something is off. For an uncomplicated bladder infection treated with an appropriate antibiotic, the NHS notes that symptoms usually start to improve within a day or two of starting treatment, and short courses of a few days are typical for otherwise healthy women. Courses for men, pregnant people and anyone with a complicated infection are generally longer, often around a week, and a kidney infection can take up to two weeks to fully settle, according to NHS guidance. Your prescriber sets the length; these ranges simply describe what is common.
If a culture was sent, expect the laboratory result within roughly one to three days, per Mayo Clinic. This is the point at which plans sometimes change. A call from the clinic saying “the bacteria are resistant to what you started; here is a different prescription” is not a sign anything went wrong. It is the system working as designed, especially when recent antibiotic use, kidney disease or an allergy made the initial choice harder.
Side effects worth anticipating include nausea, loose stools and, with some drugs, a dark or unusual urine color that is harmless. Yeast infections can follow antibiotics because the drug also suppresses protective vaginal bacteria. A rash, hives, facial swelling or breathing difficulty is different and needs immediate attention, as covered in the final section.
Over the following weeks, the aim is to stay symptom-free. A routine follow-up culture is not usually needed if you feel well, except in pregnancy and certain complicated cases, per Harvard Health. If symptoms return within about two weeks of finishing treatment, that timing itself is informative and should prompt a culture rather than a repeat of the same drug. Keep any leftover paperwork from cultures; a pattern across episodes is worth more than any single result.
What people often get wrong about UTIs and antibiotics
Myth one: a stronger antibiotic means a faster fix. “Strength” is not a property antibiotics have in a general sense. A drug either reaches the site of infection at a level that kills the specific organism or it does not. A broad-spectrum drug that covers many species is not more effective against susceptible E. coli than a narrow one; it simply does more collateral damage to gut and vaginal bacteria, which raises the risk of yeast infections, antibiotic-associated diarrhea and future resistance, according to the CDC.
Myth two: if antibiotics helped last time, the same ones should be repeated. Recent use is precisely what makes the same drug less likely to work the second time, as the earlier sections explained. Prescribers who switch classes are following evidence, not being contrary.
Myth three: cranberry products or extra water can replace antibiotics for an active infection. Evidence reviewed by the NIH Office of Dietary Supplements and Harvard Health suggests cranberry may modestly reduce recurrence in some groups, but no major guideline supports it, or any supplement, as treatment for a symptomatic bacterial infection. Hydration is sensible; it is not an antibiotic.
Myth four: a positive urine dip always means infection. Dipsticks detect white blood cells and chemical byproducts, both of which can appear without infection and can be absent with it. In older adults, bacteria in urine without symptoms is common and generally not treated, per Harvard Health.
Myth five: a listed drug allergy is permanent and precise. Many recorded penicillin allergies are not allergies at all, and true ones can fade. Clarifying the record can widen future options.
Myth six: kidney disease means UTIs cannot be treated safely. It means the choice of drug and monitoring are adjusted. Effective options exist for almost every level of kidney function; they are chosen with the eGFR in hand.
Questions to ask your care team
A good consultation about an acute UTI is a two-way exchange, and specific questions get specific answers. These are the ones worth bringing, particularly if recent antibiotics, kidney disease or an allergy is part of your story.
- Are you sending a urine culture, and if the result shows resistance to the antibiotic I am starting, how and when will I be contacted?
- Does the antibiotic I took recently change which one you are choosing now, and why?
- Given my kidney function, is this drug expected to reach my urine well, and is there anything about my kidneys you need to monitor during treatment?
- My allergy record says penicillin. Based on what I remember about the reaction, does that rule out beta-lactam antibiotics, and would allergy testing be worthwhile before my next infection?
- Does this look like a bladder infection or a kidney infection, and what would make you change that assessment?
- How soon should I expect to feel better, and at what point should I call if I do not?
- Is watchful waiting with a back-up prescription an option for me, or do my circumstances make prompt treatment the safer choice?
- Could anything else be causing these symptoms, and do you want to check for vaginal or sexually transmitted infections?
- Since this is my second or third infection recently, should we be looking for a cause, such as incomplete bladder emptying or a stone?
- Are there prevention strategies, medical or behavioral, that fit my situation and my kidney function?
Bring your medication list, the names and approximate timing of any antibiotics in the past few months, your most recent kidney blood test if you have one, and any previous culture results. Clinicians can often look these up, but a patient who arrives with the pattern already in hand shortens the path to the right decision. Write down the answers; the days after a UTI diagnosis are not the moment most people remember details clearly.
When to call your doctor
Most bladder infections settle without drama once appropriate treatment starts. The situations below are the ones that should not wait for a routine appointment. Contact your clinician the same day, or seek urgent care, if any of the following apply.
- Fever, chills, shaking or feeling generally unwell alongside urinary symptoms; these can signal that infection has reached the kidneys or the bloodstream.
- Pain in the back or side, just below the ribs, particularly on one side.
- Nausea or vomiting that stops you keeping fluids or medication down.
- Symptoms that are no better, or worse, after about 48 hours of antibiotics, which the NHS lists as a reason to be reassessed.
- Visible blood in the urine that persists, or an inability to pass urine at all.
- New confusion, drowsiness or agitation, especially in an older adult.
- A rash, hives, swelling of the face or lips, wheezing or difficulty breathing after starting an antibiotic; call emergency services if breathing is affected.
- You are pregnant and develop any urinary symptoms, or you have a kidney transplant, a single kidney, advanced kidney disease or a weakened immune system and symptoms are not improving quickly.
- Severe diarrhea, particularly if watery, frequent or accompanied by abdominal cramps and fever during or after antibiotics, which can indicate a Clostridioides difficile infection.
Call emergency services immediately for very low blood pressure, a racing heart, cold or mottled skin, or severe breathlessness; these can be signs of sepsis, a life-threatening response to infection that the CDC describes as a medical emergency.
Nothing in this article replaces the judgment of the team treating you. They have your culture results, your kidney function and your allergy history in front of them, and every decision about which antibiotic to use, for how long, and what to do if it does not work belongs with them. What you can bring is the history, the questions and a low threshold for picking up the phone.
Frequently asked questions
Does recent antibiotic use make a UTI harder to treat?
Often, yes. Antibiotics taken in roughly the past three months select for resistant bacteria in the gut, which is where most urinary pathogens originate. The effect is drug-specific: a recent fluoroquinolone predicts fluoroquinolone resistance, for example. Clinicians respond by sending a urine culture and usually avoiding the same class empirically, then adjusting once the laboratory result arrives.
Which UTI antibiotics are avoided in kidney disease?
Drugs whose effectiveness depends on being concentrated in urine, such as nitrofurantoin, are generally avoided when kidney function is significantly reduced, because urine levels fall while blood levels rise. Classes that can injure the kidney, such as aminoglycosides, are used cautiously with monitoring. The specific choice depends on your eGFR and is made by the prescribing clinician.
Can I take UTI antibiotics with a penicillin allergy?
Yes, effective options exist, but the choice narrows. A genuine penicillin allergy removes beta-lactam drugs, which are common choices for kidney infections and in pregnancy. Because most recorded penicillin allergies are not true allergies, according to the CDC, it is worth describing exactly what happened and when. Your clinician may suggest allergy testing to clarify the record for future infections.
What is the newest antibiotic available to treat UTIs?
Regulators have approved oral antibiotics for uncomplicated UTI from new chemical classes that target bacterial enzymes older drugs do not. Guidelines position such agents for people with documented resistance or intolerance to first-line drugs, not as a general upgrade, in line with stewardship principles from the CDC and WHO. Whether one is appropriate for you depends on culture results, kidney function and allergy history.
What is the hardest UTI bacteria to get rid of?
The most difficult urinary pathogens are gut bacteria such as E. coli and Klebsiella that produce ESBL enzymes, and especially carbapenem-resistant Enterobacterales, which the CDC classifies as an urgent threat. Pseudomonas and vancomycin-resistant Enterococcus also pose challenges. They are hard to treat because few safe drugs reach them, not because they cause worse symptoms; culture-guided treatment usually finds an option.
What mimics a UTI but isn't a UTI?
Vaginal yeast infections, bacterial vaginosis, sexually transmitted infections, menopause-related thinning of urinary tissue, interstitial cystitis, overactive bladder, kidney stones and prostatitis in men can all produce urgency, burning or pelvic discomfort without bacterial bladder infection. A urine culture that grows nothing is a strong signal to look for one of these rather than to repeat antibiotics.
Why have I had 3 UTIs in 2 months even after antibiotics?
Three infections in two months meets the definition of recurrent UTI. The cause may be relapse of an incompletely cleared infection, reinfection driven by risk factors such as menopause, sexual activity or diabetes, or mimics treated without a culture. Culturing every episode, checking bladder emptying and sometimes imaging the urinary tract help your clinician tell these apart and target prevention.
How does antibiotic resistant UTI treatment differ from a normal prescription?
It relies on the culture and susceptibility report rather than an empiric guess, since it shows which drugs the specific organism still responds to. Treatment may involve an older revived drug, an intravenous antibiotic given as an outpatient, or a newer agent designed to evade a resistance enzyme, often with an infectious disease specialist involved and a search for a reservoir such as a stone or catheter.
How long after starting antibiotics should a UTI improve?
For an uncomplicated bladder infection, the NHS notes symptoms usually begin to ease within a day or two of starting an appropriate antibiotic. Kidney infections can take up to two weeks to settle fully. If you are no better after about 48 hours, or feel worse at any point, contact your clinician; a culture result may show the organism is resistant to the drug started.
Should recurrent UTI after antibiotics be investigated?
Yes. Repeated infections warrant more than another prescription. Clinicians typically culture each episode, compare organisms and resistance patterns, and check for causes such as incomplete bladder emptying, kidney stones, structural abnormalities or, in men, prostate involvement. Depending on findings, prevention strategies described in guidelines may be discussed. Recent antibiotic use itself can contribute by disrupting protective vaginal and gut bacteria.
References
- NIDDK (NIH): Bladder Infection (Urinary Tract Infection) in Adults
- NHS: Urinary tract infections (UTIs)
- Cleveland Clinic: Urinary Tract Infections
- CDC: About Antimicrobial Resistance
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Medication, Injections, Traction or Surgery: How a Peyronie’s Disease Plan Is Chosen
A Peyronie's disease plan is chosen mainly by timing and severity. During the active phase, when pain and curvature are still changing, clinicians usually…

Is a Fever After a Cystoscopy Normal? Which Symptoms Need a Same-Day Call to Your Urologist
A true fever after cystoscopy is not part of a normal recovery. Mild burning, pink-tinged urine and needing to pee more often usually settle…

Renal Tubular Acidosis in Children: How Growth and Treatment Are Monitored Over Time
Renal tubular acidosis in children is monitored with a repeating cycle of growth measurements, blood tests for bicarbonate and potassium, urine tests, and periodic…

Ureteral Stricture Repair Recovery: Living With the Stent and the Follow-Up Scans Ahead
Ureteral stricture surgery recovery usually unfolds in two stages: healing from the repair itself, then living with a temporary internal stent that splints the…

After Urethritis Treatment: Follow-Up Testing and When Symptoms Are Expected to Settle
After urethritis treatment, guidelines recommend a repeat chlamydia or gonorrhea test about three months later to check for reinfection, rather than an immediate test…

How Are Renal Therapies Chosen? Medical Care, Dialysis Planning and Transplant Evaluation
Kidney disease treatment is chosen in stages, guided by how much filtering function remains, how fast it is falling, the underlying cause and a…