

Saturated Fat: Where the Evidence Actually Stands in 2026

Key Takeaways
- The 2020 Cochrane review of 15 randomized trials found that lowering saturated fat cut combined cardiovascular events by about 17 percent but showed no clear effect on total mortality.
- The WHO, US Dietary Guidelines and NHS all cap saturated fat at under 10 percent of daily calories, roughly 22 grams on 2,000 calories, while the American Heart Association advises under 6 percent for people lowering LDL.
- Replacing saturated fat with polyunsaturated fat was associated with about 25 percent lower coronary heart disease risk in Harvard cohorts; replacing it with refined carbohydrate changed nothing.
- Coconut oil is 80 to 90 percent saturated and raised LDL by about 10 mg/dL versus other vegetable oils across 16 randomized trials, despite its medium-chain marketing.
- Cheese and yogurt raise LDL less than butter with the same saturated fat content, while processed meat shows the strongest link to heart disease among animal sources.
- LDL response to saturated fat varies widely between individuals, so anyone making a major dietary change should retest their lipids after about three months.
Saturated fat raises LDL cholesterol, and randomized trials show that replacing it with unsaturated fat lowers the risk of cardiovascular events by roughly 17 percent, though effects on death are less clear. Major guidelines still advise keeping saturated fat below about 10 percent of daily calories, with the American Heart Association suggesting under 6 percent for people with high cholesterol. What replaces it matters as much as how much you remove.
The clip is thirty seconds long. A man in a kitchen drops a full stick of butter into a pan, looks into the camera and says the whole saturated fat scare was invented. Millions of views, thousands of comments, and the same question landing in clinic inboxes all spring: so was it all wrong?
As of March 2026 the argument has a fresh edge. The United States is in a new dietary guideline cycle, debate over whether the long-standing cap on saturated fat should be loosened has spilled from scientific committees into social feeds, and the butter, tallow and coconut oil content that follows every such debate is doing numbers again. Meanwhile the World Health Organization’s 2023 guideline and a large Cochrane review of randomized trials are sitting quietly in the background, saying something far less dramatic than either camp.
What follows is an attempt to read those documents the way a careful editor would: slowly, with the numbers in front of us, and with an honest grade on how strong each piece of evidence really is.
What changed recently in the saturated fat debate
Three dated events explain why the subject feels live again, and none of them is a bombshell.
In July 2023 the World Health Organization published its first formal guideline on saturated and trans fat. It recommended that adults and children keep saturated fat below 10 percent of total energy and, crucially, that the calories removed be replaced with polyunsaturated fat, plant-based monounsaturated fat, or carbohydrates from whole grains, vegetables, fruit and pulses rather than with refined starch or sugar. The WHO panel graded the evidence as moderate for cardiovascular outcomes, which is unusually candid language for an international body.
Before that, in May 2020, the Cochrane Collaboration updated its systematic review of randomized trials that cut saturated fat for at least two years. Pooling 15 trials and 56,675 participants, it found a 17 percent relative reduction in combined cardiovascular events when saturated fat was lowered, with no clear effect on total mortality or cardiovascular mortality. That split, fewer heart attacks and strokes but no proven change in deaths, is the single most important nuance in this whole story, and it is the one both the butter influencers and their critics tend to skip.
The American Heart Association’s 2017 presidential advisory, which concluded that swapping saturated for polyunsaturated fat lowers cardiovascular disease about as much as a statin does in trials, has not been withdrawn. Its guidance of under 6 percent of calories for people who need to lower LDL cholesterol still stands.
What has changed in 2026 is the volume of the conversation, not the underlying trial data. The current US guideline process is reviewing the 10 percent threshold alongside everything else, and until a final document is published, the existing limits remain the official advice.
What is saturated fat, and which foods contain the most?
Saturated fat is a type of dietary fat whose carbon chains carry no double bonds, which is why it stays solid at room temperature. Butter holds its shape on the counter; olive oil does not. That physical difference tracks a biological one.
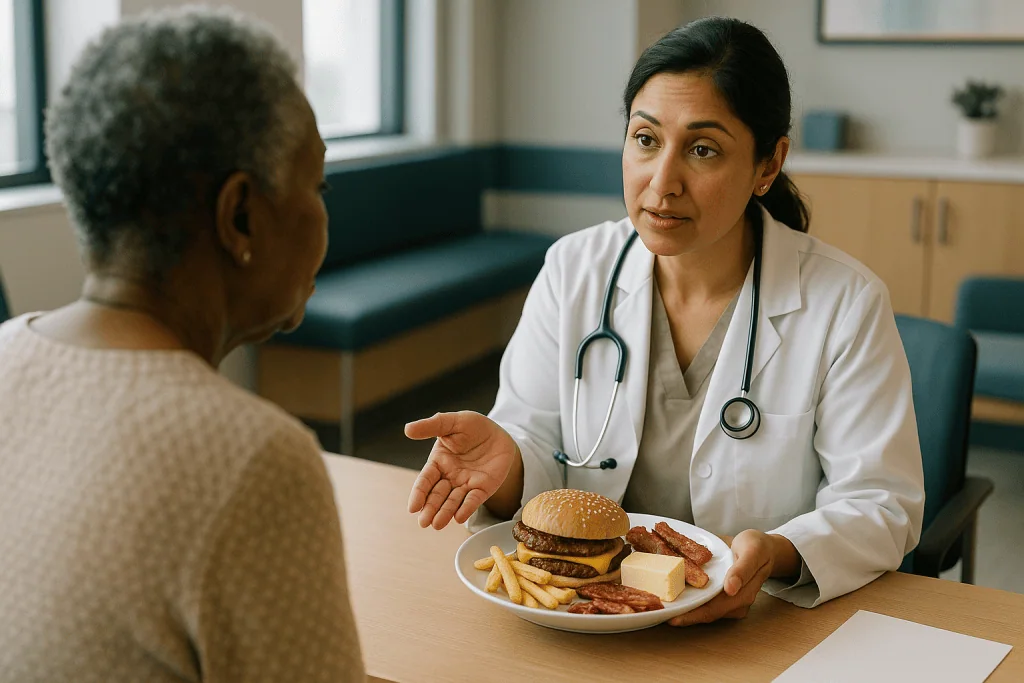
No food is purely one kind of fat. Butter is roughly two-thirds saturated, lard about 40 percent, olive oil around 14 percent. The practical sources in a typical US diet, according to the Centers for Disease Control and the National Institutes of Health, are mixed dishes and processed foods rather than a single villain: pizza, burgers, sandwiches, cheese, full-fat dairy, fatty cuts of beef and pork, sausage and bacon, baked goods made with butter or palm oil, and coconut and palm oils themselves.
A saturated fat foods list worth memorizing is short:
- Coconut oil: about 12 g per tablespoon, the most concentrated common source
- Butter: about 7 g per tablespoon
- Cheddar cheese: about 6 g per ounce
- 80 percent lean ground beef: about 6 g per 3-ounce cooked portion
- Whole milk: about 4.5 g per cup
- Dark chocolate: about 7 g per ounce, much of it stearic acid, which behaves differently
Within the family, individual fatty acids are not interchangeable. Lauric, myristic and palmitic acids, the dominant ones in coconut oil, dairy fat and meat, raise LDL cholesterol in controlled feeding studies. Stearic acid, abundant in cocoa butter and present in beef fat, has a near-neutral effect on LDL. Nutrition labels lump them together, which is one reason a gram of saturated fat from chocolate and a gram from coconut oil are not quite the same proposition.
How saturated fat raises LDL cholesterol: the mechanism
LDL cholesterol, often called low-density lipoprotein, is the particle that carries cholesterol out to tissues and, when present in excess, deposits it in artery walls. The link between saturated fat and LDL is not a statistical guess; it has been reproduced in controlled feeding studies for sixty years, which is why it sits at the top of the evidence hierarchy for this topic.
The mechanism runs through the liver. Liver cells display LDL receptors on their surface that pull LDL particles out of the blood for recycling. Diets high in palmitic and myristic acid reduce the number and activity of those receptors, so LDL lingers in circulation longer. Replace those fatty acids with polyunsaturated fat and receptor activity rises again; LDL falls within weeks. This is the same receptor that statins and PCSK9 inhibitors act on, which is why clinicians treat diet and medication as two routes to one target rather than as rivals.
The size of the effect is modest per gram but adds up. Classic predictive equations suggest that every 1 percent of daily calories shifted from saturated to polyunsaturated fat lowers LDL by a few milligrams per deciliter. For a person swapping 5 percent of calories, that can mean a drop in the range of 10 mg/dL, comparable to adding a daily serving of soluble fiber.
Saturated fat also nudges HDL cholesterol upward, and this is the fact most often used to argue it is harmless. The problem is that raising HDL through diet or drugs has never been shown in randomized trials to reduce heart attacks, whereas lowering LDL has, repeatedly. Most lipid specialists now look past HDL to apolipoprotein B, a single protein present on every atherogenic particle; saturated fat raises that too.
What the evidence actually says, graded by strength
Evidence comes in tiers, and the honest answer on saturated fat differs by tier.

Strongest: controlled feeding trials on cholesterol. Dozens of randomized crossover studies show that saturated fat raises LDL and apolipoprotein B relative to unsaturated fat. This is settled, consistent across populations, and not seriously disputed by anyone who reads the primary literature.
Strong but with gaps: randomized trials on cardiovascular events. The 2020 Cochrane review pooled 15 trials lasting two years or longer. Lowering saturated fat cut combined cardiovascular events by 17 percent, and the benefit was larger in trials that achieved bigger LDL reductions and that replaced saturated fat with polyunsaturated fat. Yet neither all-cause mortality nor cardiovascular mortality fell to a statistically meaningful degree. Many of these trials are old, some combined diet changes with other advice, and participants were mostly middle-aged men, so the certainty is moderate rather than high.
Moderate: large prospective cohorts. Harvard’s Nurses’ Health Study and Health Professionals Follow-up Study, following more than 120,000 people for decades, found that replacing 5 percent of energy from saturated fat with polyunsaturated fat was associated with about a 25 percent lower risk of coronary heart disease, while replacing it with refined carbohydrate changed nothing. Observational data cannot prove causation, but when it points the same direction as the trials and the mechanism, it earns weight.
Weakest: single meta-analyses of observational studies that found no association. A handful of widely shared analyses compared high versus low saturated fat intake without asking what replaced it. In populations where the usual swap is white bread and sugar, no difference appears. That is a finding about refined carbohydrate, not a vindication of butter.
Put together, the grade is this: lowering saturated fat in favor of unsaturated fat probably prevents heart attacks and strokes, with moderate certainty, and does not have proven effects on how long people live.
Is saturated fat bad for you? The replacement question
The most useful reframing of the past decade is that no single nutrient is good or bad in isolation, because calories do not disappear. Remove saturated fat and something fills the gap. Whether the result helps or harms depends almost entirely on what that something is.
The table below summarizes what the Cochrane trials, the WHO review and the Harvard cohorts collectively suggest when about 5 percent of daily calories from saturated fat are swapped for another energy source. The direction of effect is consistent across sources; the exact size varies by study.
| Replacement for saturated fat | Effect on LDL cholesterol | Association with coronary heart disease | Evidence strength |
|---|---|---|---|
| Polyunsaturated fat (sunflower, soybean, corn, walnut oil, fatty fish) | Falls clearly | Lower risk, roughly 25 percent in cohorts; benefit seen in randomized trials | Moderate to strong |
| Plant monounsaturated fat (olive oil, avocado, nuts) | Falls | Lower risk, around 15 percent in cohorts | Moderate |
| Whole-grain carbohydrate | Falls modestly | Lower risk, around 9 percent in cohorts | Moderate |
| Refined carbohydrate and added sugar | Falls slightly, triglycerides rise | No improvement; some studies show slightly higher risk | Moderate |
| Trans fat | Rises | Higher risk | Strong |
Two lessons sit in that grid. First, the 1980s low-fat era failed not because the cholesterol science was wrong but because food manufacturers replaced fat with sugar and white flour, the one swap that buys nothing. Second, the viral claim that “saturated fat was never the problem” draws its entire support from studies of that failed swap.
So is saturated fat bad for you? On its own, it is a nutrient that raises LDL and apolipoprotein B. In the context of a plate, the question is what you would eat instead. If the alternative is olive oil, nuts, fish and whole grains, the evidence favors the alternative. If the alternative is a low-fat cookie, keep the cheese.
Does the food source matter? Dairy, meat, coconut oil and the food matrix
Here the evidence genuinely gets more interesting, and it is where thoughtful nutrition scientists and influencers both have a point.
The food matrix is the idea that nutrients behave differently depending on the whole food they arrive in. Cheese is the cleanest example. In controlled trials, cheese raises LDL less than butter containing the same amount of saturated fat, probably because cheese’s calcium and protein bind some fatty acids in the gut and because fermentation changes its structure. Prospective cohorts, including large European studies, have found that yogurt and cheese are associated with neutral or slightly lower cardiovascular risk, while butter is roughly neutral and processed meat is associated with higher risk.
Meat divides along similar lines. Unprocessed red meat raises LDL modestly in feeding studies; processed meat such as bacon, ham and sausage carries added sodium and preservatives and shows the strongest links to heart disease and colorectal cancer in cohort data. The WHO’s 2023 guideline singled out processed meat separately for that reason.
Coconut oil is where the matrix argument runs out of road. Roughly 80 to 90 percent saturated, it is dominated by lauric acid, which raises LDL more than any other common fatty acid. A 2020 meta-analysis of 16 randomized trials found coconut oil raised LDL by about 10 mg/dL compared with nonlauric vegetable oils. The marketing claim that its medium-chain fats are burned rather than stored rests on studies of purified medium-chain triglyceride oil, a different product; lauric acid, with 12 carbons, behaves metabolically like a long-chain fat. The American Heart Association advises against it for cardiovascular purposes, and Harvard Health describes the health halo as unsupported.
The practical takeaway from the matrix research is not that saturated fat is fine, but that fermented dairy and unprocessed meat in modest portions are lower on the worry list than butter, coconut oil and processed meat.
How much saturated fat per day do guidelines actually allow?
The numbers are less contested than the social-media debate suggests, and they overlap more than they differ.
The World Health Organization and the current US Dietary Guidelines both cap saturated fat at less than 10 percent of total daily energy. On a 2,000-calorie diet that is under 22 grams a day, about three tablespoons of butter or two ounces of cheddar. The UK’s NHS translates the same percentage into grams: no more than 30 g a day for men and 20 g for women, which reflects differing average energy needs rather than a different standard.
The American Heart Association sets the lowest bar, recommending that saturated fat stay under 6 percent of calories, about 13 grams on 2,000 calories, for people who need to lower their LDL cholesterol. That advice is built on the trial data showing that bigger reductions in saturated fat produce bigger reductions in events, and it mirrors what cardiac rehabilitation dietitians have taught for decades.
How much saturated fat per day Americans actually eat is a separate question. National surveys put the average adult at around 11 to 12 percent of calories, modestly above the ceiling, with children slightly higher. The gap between typical intake and the guideline is therefore smaller than the drama implies: for most people it means a few swaps a week, not a diet overhaul.
These are population targets, not personal prescriptions. A 25-year-old endurance athlete with an LDL of 80 mg/dL and a 55-year-old with an LDL of 190 and a parent who had a heart attack at 50 are not facing the same risk from the same slice of pizza. If your cholesterol is high, or you have diabetes, kidney disease or existing heart disease, the right number for you is a conversation with the clinician who can see your blood work.
Saturated fat vs unsaturated fat: why one is solid and one flows
The saturated fat vs unsaturated fat distinction comes down to double bonds, and it pays to understand it once because every label and every argument hangs on it.
A fatty acid is a chain of carbon atoms. In a saturated fatty acid, every carbon is “saturated” with hydrogen and the chain is straight, so molecules pack tightly and the fat is solid at room temperature. A monounsaturated fatty acid has one double bond that puts a kink in the chain; a polyunsaturated fatty acid has two or more. Kinked chains cannot stack neatly, so these fats stay liquid. Olive oil, canola oil, avocado and most nuts are rich in monounsaturated fat. Sunflower, soybean and corn oils, walnuts, flaxseed and fatty fish supply polyunsaturated fat, which includes the essential omega-6 and omega-3 families the body cannot make.
Trans fat is the exception that proves the rule. Industrial hydrogenation adds hydrogen to liquid oils to make them solid, creating an unnatural double-bond shape. Trans fat raises LDL and lowers HDL, and it is the one dietary fat with unambiguous evidence of harm, which is why the US Food and Drug Administration removed partially hydrogenated oils from the generally-recognized-as-safe list and the WHO has run a global elimination campaign since 2018.
The biological consequence of the double bond is what matters for the heart. Unsaturated fats increase LDL receptor activity and lower apolipoprotein B; saturated fats do the opposite. Omega-3 fats from fish also lower triglycerides. None of this makes unsaturated fat a free pass, since all fats carry nine calories per gram, and deep-frying degrades polyunsaturated oils. But as a direction of travel, from the solid toward the liquid, the evidence is consistent across mechanism, trials and cohorts.
Why some people's LDL jumps far more than others
Two people eat the same high-fat breakfast for a month. One sees LDL creep up by 5 mg/dL; the other watches it climb by 60. Clinicians have known about this variability for decades, and it is the kernel of truth inside many online testimonials.
Genetics drive a large share of the difference. Variants in genes governing cholesterol absorption and LDL receptor function make some people hyper-responders to dietary saturated fat and cholesterol. The APOE4 variant, carried by roughly a quarter of people of European ancestry, is associated with a stronger LDL rise on high-saturated-fat diets. Familial hypercholesterolemia, an inherited condition affecting about 1 in 250 people in which LDL receptors are defective from birth, means LDL stays high regardless of diet, though saturated fat still pushes it higher.
Body composition adds another layer. A pattern labeled the lean mass hyper-responder phenotype, documented in case series and a small 2025 cohort of people on ketogenic diets, describes lean, metabolically healthy individuals whose LDL rises dramatically on very low carbohydrate intake, sometimes above 200 mg/dL. The proposed mechanism involves the liver exporting more fat-carrying particles when glycogen is depleted. Whether this LDL is as dangerous as LDL in a person with metabolic syndrome is an open research question; a 2025 coronary CT study in this group found plaque progression tracked with baseline plaque rather than LDL level over one year, but the study was short, uncontrolled and funded in part by advocacy sources. Mainstream lipidology, reflected in Cleveland Clinic and Mayo Clinic guidance, continues to treat high LDL as a risk regardless of how it was produced, because decades of genetic and trial data link the particle itself, not its origin, to arterial plaque.
The practical implication is simple and often ignored: if you change your diet substantially in either direction, retest your lipids in about three months. Averages describe populations; your blood describes you.
Saturated fat on low-carb and ketogenic diets
The current wave of saturated fat enthusiasm rides largely on the ketogenic diet, so it is worth separating what that eating pattern does from what the fat inside it does.
A ketogenic diet restricts carbohydrate to roughly 20 to 50 grams a day so that the liver produces ketones, an alternative fuel. Randomized trials show it can lower triglycerides, raise HDL, improve blood glucose in type 2 diabetes and produce short-term weight loss comparable to other calorie-restricted diets over a year. Those benefits are real and are supported by trial evidence of moderate quality.
LDL is where the diet’s composition decides the outcome. In trials where participants built their fat intake around olive oil, nuts, avocado and fish, LDL changed little or fell. In trials and case series where butter, cream, bacon and coconut oil dominated, LDL rose, often substantially. A ketogenic diet does not neutralize the effect of saturated fat on LDL receptors; it simply removes the carbohydrate variable that confused older studies.
The claim circulating in 2026 that LDL “does not matter” when triglycerides are low and HDL is high rests on a handful of small studies and on the observation that insulin resistance amplifies LDL’s harm. Insulin resistance does make LDL more dangerous, which is a reason to care about blood sugar, not a reason to ignore cholesterol. Mendelian randomization studies, which use inherited gene variants as a natural experiment, consistently show that lifelong lower LDL means lower heart disease risk independent of HDL or triglycerides.
If someone chooses a low-carbohydrate pattern for weight, glucose control or seizure management, the evidence supports leaning its fat profile toward unsaturated sources and checking LDL and apolipoprotein B after a few months. Any decision to continue the diet with a markedly elevated LDL belongs with the treating clinician, not a forum.
Common myths about saturated fat, checked against the evidence
The viral claims rarely come with sources, so here are the five that circulate most, each held up to the trials.
“The studies linking saturated fat to heart disease were debunked.” The studies most often cited as debunking, two meta-analyses of observational data from 2010 and 2014, found no association when saturated fat was compared with everything else, mostly refined carbohydrate. Trials that compared it specifically with polyunsaturated fat, pooled by Cochrane in 2020, found fewer cardiovascular events. The claim confuses a null result for one swap with a verdict on the nutrient.
“Ancel Keys cherry-picked his countries.” The famous six-country graph was indeed selective. The Seven Countries Study that followed used standardized methods across 16 cohorts, and its findings have since been echoed in cohorts of hundreds of thousands. Whatever one thinks of the 1950s graph, the modern evidence base does not depend on it.
“Saturated fat raises HDL, so it balances out.” It does raise HDL slightly. But five large trials of HDL-raising drugs failed to reduce heart attacks, and genetic studies show that inherited high HDL does not protect. HDL is a marker of a healthy pattern, not a lever.
“Coconut oil’s fats are different.” They are mostly lauric acid, which raises LDL in every head-to-head trial. The medium-chain story belongs to a purified product coconut oil does not resemble.
“Our ancestors ate mostly animal fat.” Anthropological estimates for most hunter-gatherer groups put saturated fat at 10 to 15 percent of energy, from wild game far leaner than farmed livestock, with no butter, cream or coconut oil in sight. The ancestral diet, where it can be reconstructed, looked more like the guidelines than like the videos.
What a lower-saturated-fat plate looks like in practice
Advice that lives only in percentages tends to die on the way to the grocery store, so here is what the trial diets actually looked like translated into a week of meals.
The Cochrane trials and the Mediterranean-diet trials did not banish fat. Participants typically ate 30 to 40 percent of calories as fat, but the sources shifted. Oil-based dressings replaced creamy ones. Fish appeared twice a week. Nuts became the default snack. Red meat shrank to a few servings a week and processed meat became occasional. Full-fat dairy was reduced rather than eliminated, with yogurt and cheese kept and butter and cream trimmed.
Concrete swaps that each remove several grams of saturated fat without making a meal joyless:
- Cook in olive or canola oil instead of butter; one tablespoon saved is about 5 g
- Choose 93 percent lean ground beef, poultry or fish over 80 percent lean beef; roughly 4 g per serving
- Spread avocado or nut butter on toast rather than butter
- Pick Greek yogurt over sour cream in dips and on baked potatoes
- Keep cheese but let a strong-flavored one do the work in smaller amounts
- Read the label on baked goods and coffee drinks, where palm and coconut oil hide
Two cautions keep this from becoming the 1990s again. Fat-free cookies, crackers and flavored yogurts replace fat with sugar, the one trade the evidence rejects; a label reading “low fat” is not an endorsement. And calories still count: a handful of almonds is a better choice than a slice of cheddar, but three handfuls are not.
For people who find a Mediterranean-style pattern unappealing, the DASH diet, developed by the NIH and tested in randomized trials for blood pressure, reaches the same saturated fat target through a different route built on vegetables, fruit, low-fat dairy and whole grains.
Who should be more careful with saturated fat
Population guidelines are written for the middle of the curve. Several groups sit at the edge, where the same gram of saturated fat carries more weight.
People with established cardiovascular disease, a prior heart attack, stroke, bypass or stent, have the most to gain from LDL reduction, and dietary saturated fat is one of the two modifiable inputs alongside medication. Cardiac rehabilitation programs typically teach the American Heart Association’s 6 percent target for this reason.
Anyone with familial hypercholesterolemia faces lifelong high LDL from birth. Diet alone will not bring the level into range, and clinicians generally recommend lipid-lowering medication from early adulthood, but saturated fat still adds to the baseline and is worth limiting.
People with type 2 diabetes or metabolic syndrome carry a particular hazard: insulin resistance produces smaller, denser LDL particles that penetrate artery walls more easily, so a given LDL number represents more risk. Guidelines from the American Diabetes Association and the AHA both prioritize unsaturated fat in this group.
Chronic kidney disease accelerates atherosclerosis and often comes with abnormal lipids; dietitians in nephrology routinely address saturated fat alongside sodium and phosphorus.
People taking statins sometimes assume the tablet makes diet irrelevant. Trials show the two add together: diet does not replace the medication, and the medication does not cancel the diet. Any change to a prescribed lipid medicine, including stopping it because a new diet feels healthy, is a decision for the prescribing clinician, since LDL typically returns to baseline within weeks of stopping.
At the other end, people who are underweight, frail, or recovering from illness may need calorie density more than LDL optimization. Guidelines from the NHS and others explicitly note that saturated fat limits are not meant for people who are struggling to eat enough.
When to see a doctor about cholesterol and saturated fat
Diet articles cannot see your blood work, and cholesterol produces no symptoms until it has done damage. That makes testing, not guessing, the only honest starting point.
The CDC and the American Heart Association recommend that most adults have a lipid panel at least every four to six years from age 20, more often if results are abnormal, if there is a family history of early heart disease, or if diabetes, high blood pressure or kidney disease are present. Children with a family history of high cholesterol or early heart attacks are generally screened between ages 9 and 11 and again at 17 to 21, according to pediatric guidelines summarized by MedlinePlus.
Book a routine appointment if any of the following apply:
- Your LDL cholesterol is above 160 mg/dL, or above 100 mg/dL with diabetes or existing heart disease
- A parent or sibling had a heart attack, stroke or bypass before age 55 in men or 65 in women
- You have changed to a very low-carbohydrate, carnivore or high-butter diet and have not had lipids checked in the past three months
- You are considering stopping or reducing a prescribed cholesterol medicine for any reason
- You notice yellowish deposits around the eyelids or on tendons, which can signal very high inherited cholesterol
Call emergency services immediately, do not drive yourself, if you experience red-flag signs of a heart attack or stroke: chest pressure or tightness lasting more than a few minutes or coming and going, pain spreading to the arm, jaw, neck or back, sudden shortness of breath, cold sweat with nausea, sudden weakness or numbness on one side of the body, facial drooping, slurred speech, sudden confusion, or sudden severe headache. Women and people with diabetes more often present with fatigue, indigestion-like discomfort or breathlessness rather than classic chest pain.
Every number in this article describes populations. The decision about your saturated fat target, your LDL goal and whether medication belongs in the picture rests with the clinician who has your results, your history and your preferences in front of them.
Frequently asked questions
Is saturated fat bad for you if your cholesterol is normal?
It still raises LDL and apolipoprotein B, but the absolute risk from a modest intake is small when cholesterol, blood pressure and blood sugar are all in range. Guidelines keep the under 10 percent of calories target for everyone because cardiovascular risk accumulates over decades and LDL tends to drift upward with age. Someone with normal lipids has more room for flexibility than someone with an LDL of 180, but not a blank check.
How much saturated fat per day is safe?
The WHO, US Dietary Guidelines and NHS set the limit at less than 10 percent of daily calories, which is under about 22 grams on a 2,000-calorie diet, or 30 g for men and 20 g for women in NHS terms. The American Heart Association recommends under 6 percent, roughly 13 grams, for people who need to lower LDL. The right figure for you depends on your lipid results and overall risk.
What is on a saturated fat foods list?
Coconut and palm oil, butter, cream, cheese, whole milk, fatty cuts of beef, pork and lamb, sausage, bacon and other processed meats, pastries and baked goods made with butter or palm oil, and chocolate. In the typical US diet the biggest contributors are mixed dishes such as pizza, burgers and sandwiches rather than any single ingredient, which is why reading labels on prepared foods matters as much as the butter dish.
Saturated fat vs unsaturated fat: which is healthier?
Unsaturated fat, from olive oil, canola oil, nuts, seeds, avocado and fatty fish, is consistently associated with lower LDL cholesterol and lower cardiovascular risk in both randomized trials and large cohorts. Saturated fat, which is solid at room temperature, raises LDL by reducing LDL receptor activity in the liver. Trans fat is worse than either. All fats supply nine calories per gram, so portion size still matters.
Does saturated fat cause heart disease?
The evidence shows it contributes to risk by raising LDL, and randomized trials show replacing it with polyunsaturated fat reduces cardiovascular events by about 17 percent. Heart disease has many causes, including blood pressure, smoking, diabetes, genetics and inactivity, so no single nutrient causes it alone. The certainty is moderate for events and low for mortality, which is why guidelines use measured language rather than absolute claims.
Is butter back, as the viral videos claim?
Not according to the trial data. Butter is about two-thirds saturated fat and raises LDL more than cheese, yogurt or olive oil in controlled studies. Large cohorts find butter roughly neutral for heart disease compared with the average diet, but worse than plant oils. A modest amount in a diet otherwise built on unsaturated fat is not alarming; daily sticks of it are not what the evidence supports.
Is coconut oil a healthy saturated fat?
The randomized trial evidence says no. Coconut oil is dominated by lauric acid, which raised LDL by about 10 mg/dL compared with other vegetable oils across 16 trials pooled in 2020. The medium-chain triglyceride claims come from studies of a purified product that coconut oil does not resemble. The American Heart Association and Harvard Health both advise against using it as a heart-healthy cooking fat.
Why did my LDL go up on a keto diet?
Very low carbohydrate diets often shift fat intake toward butter, cream, bacon and coconut oil, all of which raise LDL, and some lean individuals show a large rise even on moderate saturated fat, possibly because the liver exports more fat-carrying particles when glycogen is low. Rechecking lipids after three months and shifting fat sources toward olive oil, nuts and fish is reasonable; whether to continue the diet with a high LDL is a question for your clinician.
Does saturated fat from cheese count the same as from butter?
Gram for gram it appears to count less. Controlled trials show cheese raises LDL less than butter with equal saturated fat, likely because calcium and protein in the cheese matrix bind some fatty acids in the gut. Cohort studies link cheese and yogurt to neutral or slightly lower cardiovascular risk. This does not make cheese unlimited, but it places fermented dairy lower on the worry list than butter or processed meat.
Can I stop my statin if I cut saturated fat?
That decision belongs with the clinician who prescribed it. Diet and statins act on the same liver receptor pathway and their effects add together rather than substitute for one another; a strict diet typically lowers LDL by 10 to 15 percent while statins lower it by 30 to 50 percent. LDL usually returns to baseline within weeks of stopping a statin, so any change should be planned and monitored with repeat blood tests.
References
- WHO guideline: Saturated fatty acid and trans-fatty acid intake for adults and children (2023)
- NHS: Fat: the facts
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Robotic Heart Surgery Recovery: Light Activity in Weeks and Full Exertion Over Two Months
Robotic heart surgery recovery time is usually shorter than recovery after open-chest surgery because the breastbone is left intact. Most people leave the hospital…

Dehydration, Stress and Palpitations: The Everyday Triggers
Yes, dehydration can cause heart palpitations. When you lose fluid, your blood volume drops, so the heart beats faster and harder to keep blood…

Cardiovascular Toxicology: How Heart Effects of Cancer Therapies and Chemicals Are Managed
Cardiovascular toxicology is the study of how medicines, cancer treatments and environmental chemicals can harm the heart and blood vessels, and how that harm…

What Transplant Cardiology Covers: Heart Transplant Evaluation and Lifelong Follow-Up Care
Transplant cardiology is the branch of heart medicine that assesses people with advanced heart failure for a heart transplant or a mechanical heart pump,…
How Transcatheter Mitral Clip Repair Reduces Regurgitation by Joining the Valve Leaflets
Transcatheter mitral clip repair, also called transcatheter edge-to-edge repair or TEER, treats a leaking mitral valve without open-heart surgery. A cardiologist threads a catheter…

Life After a Stent: Antiplatelet Medicines, Lifting Limits and Cardiac Rehab
Life after stent placement usually means taking two antiplatelet medicines for a period set by your cardiologist, often 6 to 12 months for the…