

SMR (Submucous Resection) Step by Step: How the Deviated Septum Is Corrected From Inside
Key Takeaways
- In a submucous resection the septal lining is lifted intact, the crooked cartilage and bone beneath are removed or reshaped, and the lining is laid back down, so there is no external incision or visible scar.
- The classic SMR removed most of the central septum, while modern septoplasty preserves cartilage wherever possible, which lowers the long-term risk of a saddle bridge or septal perforation.
- Mayo Clinic and Cleveland Clinic give a typical operating time of 30 to 90 minutes, and MedlinePlus notes most people go home the same day.
- Strict bed rest is not recommended; sleeping with the head raised and walking gently from day one are advised, with strenuous exercise avoided for up to five weeks according to Mayo Clinic.
- Turbinate reduction is a short, low-risk procedure, but removing too much tissue can leave a nose that feels dry and blocked despite being wide open, so conservative technique matters more than extent.
- Nasal tissues are relatively stable by three to six months, but cartilage can keep shifting for up to a year, so surgeons wait before judging the final airway.
A submucous resection (SMR) corrects a deviated septum from inside the nose. The surgeon lifts the septal lining, removes or reshapes the bent cartilage and bone underneath, then lays the lining back down, so no external cut is made. Modern versions preserve as much cartilage as possible and are usually called septoplasty. It is typically a day-case operation under general or local anesthesia.
He has slept on his right side for as long as he can remember. Not out of habit, exactly. Lying on the left, the air just stops. His partner noticed the mouth-breathing years before he did; the dentist noticed the dry gums. Now, sitting in a clinic chair with a small camera having just toured the inside of his nose, he hears the phrase for the first time: a submucous resection procedure, or SMR.
The words sound more alarming than the operation usually is. “Resection” suggests something being cut out, and something is, but the work happens entirely under a lining that is peeled away and then replaced, a bit like lifting a carpet to fix a warped floorboard and then laying the carpet back.
This explainer walks through that work step by step, separates the older, more aggressive SMR from the cartilage-sparing septoplasty most surgeons perform today, and answers the turbinate questions that almost always come up alongside it.
What is the submucous resection procedure, in plain words?
The nasal septum is the wall of cartilage and thin bone that divides the nose into two passages. Its surface is covered on each side by mucosa, the moist pink lining that warms and humidifies the air you breathe. Beneath the mucosa lies a tougher membrane, the mucoperichondrium over cartilage and mucoperiosteum over bone, which is the layer the surgeon actually works under. “Submucous” simply means “beneath that lining.”
A submucous resection procedure therefore means removing deviated cartilage or bone from the septum while leaving the lining on both sides intact. The lining is lifted like a flap, the crooked framework is taken away or reshaped, and the flaps are laid back against each other. Because the lining is preserved, the nose still has a functional inner surface, and the septum heals as a thinner but continuous partition.
The classic SMR was described more than a century ago by surgeons including Killian and Freer. In its original form it removed a generous central plate of cartilage and bone, keeping only a rim along the top and front to support the bridge and tip. That approach relieved obstruction but occasionally left the septum too weak, leading to a saddle-shaped bridge or a hole between the two sides.
Over the following decades the operation evolved into what is now usually called septoplasty, in which the surgeon removes only the segments that are truly in the way and repositions or reinforces the rest. Mayo Clinic describes septoplasty as straightening the septum by trimming, repositioning, and replacing cartilage or bone, with the lining lifted and then put back in place. Many ear, nose and throat surgeons still use the letters SMR loosely for any septal operation of this type, which is why you may hear both names for what is, in practice, a closely related procedure.
Submucous resection vs septoplasty: what's the actual difference?
Patients often arrive with two names for what sounds like one operation, and they are right to be a little confused. The distinction is one of philosophy and degree rather than of a completely different technique.
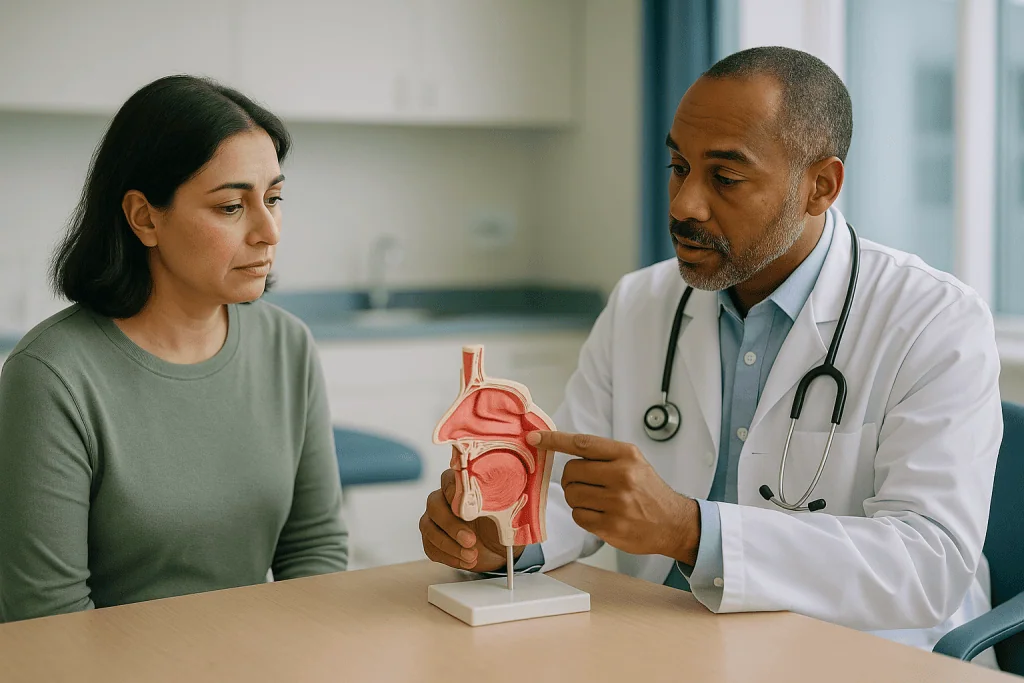
In a traditional submucous resection, the surgeon’s goal is to clear the airway by removing most of the deviated central septum in one piece, leaving a supporting L-shaped strut of roughly one centimeter along the bridge and the front edge. Think of it as taking a warped panel out of a door and leaving only the frame. It is direct and effective at opening the airway, but it removes tissue that cannot be put back.
Septoplasty is the conservative descendant. The surgeon still works under the lining, but the aim is to preserve cartilage wherever possible: scoring it so it bends straight, trimming only the crooked strip at its base, removing a bony spur, or taking a segment out, straightening it on a side table and returning it as a graft. Cleveland Clinic describes the modern operation in exactly these terms, noting that the surgeon reshapes or removes only the parts of the septum that block airflow.
Why does the difference matter to you? Preserving cartilage lowers the long-term risk of the bridge sinking or the septum perforating, and it leaves material for any future nasal surgery. The trade-off is that a severely twisted septum sometimes cannot be fully straightened by conservative means alone, and the surgeon may need to remove more.
Your operation note may say SMR, septoplasty, or both. The honest answer to “which one am I having?” is usually that your surgeon will do as little as possible and as much as necessary, deciding the exact extent once the lining is lifted and the true shape of the cartilage can be seen.
Why does a deviated septum block breathing in the first place?
Almost nobody has a perfectly straight septum. Mayo Clinic notes that a deviated septum is common and that many people have some degree of displacement without symptoms. The problem arises when the bend narrows one passage enough to disturb the physics of airflow.
Air moving through the nose behaves like water through a pipe: the narrower the channel, the faster and more turbulent the flow, and the greater the resistance. A septum that bows into the left passage leaves less room on that side, so the left nostril feels blocked, especially when lying down, when blood vessels in the lining naturally swell.
The body then adds a second problem. The turbinates are shelf-like structures on the outer wall of each nasal passage, covered in richly vascular tissue that swells and shrinks to regulate airflow. On the wider side, the inferior turbinate often enlarges over years to fill the extra space, a change called compensatory hypertrophy. The result can be a nose that is narrow on one side because of cartilage and narrow on the other because of soft tissue.
Deviation can be present from birth or from pressure during delivery, but many cases follow an injury, sometimes one so minor that the person barely remembers it. Mayo Clinic lists a broken nose, contact sports, and falls as common causes, and adds that the normal aging process can worsen an existing bend.
The consequences extend beyond a stuffy nostril. A chronically obstructed passage drains poorly, which can contribute to recurrent sinus infections. Nighttime mouth breathing dries the mouth and can disturb sleep. Some people notice one-sided nosebleeds because turbulent air dries the lining over the bend. None of these features alone proves that surgery is needed, which is why the assessment described below matters.
Who is SMR nose surgery usually for, and who is usually asked to wait?
The decision rests on a simple pairing: a visible deviation on examination, and symptoms that the deviation plausibly explains and that have not settled with non-surgical treatment. One without the other is rarely enough.

Surgeons typically consider a septal operation for adults with persistent one-sided or alternating nasal obstruction, obstruction that disturbs sleep, recurrent sinus infections linked to poor drainage, or repeated nosebleeds from a dry, exposed bend. Access is another reason: Mayo Clinic notes that a deviated septum is sometimes corrected to allow the surgeon to reach the sinuses during other nasal or sinus surgery.
Several groups are commonly asked to wait or to consider other options first. Children and younger teenagers are the clearest example. The septum is a growth center for the midface, and removing cartilage before growth is complete can affect how the nose and upper jaw develop. Most surgeons therefore delay elective septal surgery until facial growth has largely finished, generally in the mid to late teens, unless obstruction is severe.
People whose blockage is mainly caused by swollen lining rather than crooked cartilage are usually offered medical treatment first, because straightening the septum will not shrink inflamed tissue. Someone with untreated allergic rhinitis, for instance, may find that a course of anti-inflammatory nasal spray prescribed by their clinician changes the picture entirely.
Timing also matters for anyone with an active nasal or chest infection, poorly controlled blood pressure, or a bleeding disorder, and for people taking blood-thinning medicines, whose prescribing clinician will advise whether and how these are managed around surgery. Never adjust such medicines yourself.
Finally, expectations count. Surgery aims to open the airway; it will not change the outside appearance of the nose unless combined with a rhinoplasty, and it does not treat allergy. Your surgeon will want to be sure that what you hope for matches what the operation can do.
Step by step: what actually happens during a submucous resection procedure
Once you are anesthetized, the surgeon injects a solution of local anesthetic and a vasoconstrictor into the septal lining. This numbs the area for afterward, shrinks blood vessels to limit bleeding, and, usefully, begins to separate the lining from the cartilage beneath.
The first cut is made inside the nose, typically a short incision just inside one nostril along the front edge of the septum. Nothing is cut on the outside, so there are no visible scars. Through this opening, a blunt instrument called an elevator is slid between the mucoperichondrium and the cartilage. Working in this plane, the surgeon lifts the lining away from the cartilage on one side, then makes a small window through the cartilage to lift the lining on the other side as well. Both flaps are now tented away from the framework, which is exposed between them.
Now the corrective work begins. A bony spur at the base is chiselled or nibbled away with fine forceps. A bowed section of cartilage may be scored on its concave side so that it springs straight, or a thin strip may be removed along its bottom edge to release the tension holding it crooked. Where a segment is too twisted to save, it is removed, and in a septoplasty it may be straightened on a side table and slid back between the flaps as a supporting graft. Throughout, the surgeon preserves the L-shaped strut along the bridge and front that holds up the nose.
The flaps are then laid back together. Some surgeons place a fine quilting stitch through both flaps to press them against each other and prevent blood pooling between them; others use soft silicone splints, small sheets placed on either side of the septum and removed at a follow-up visit. Dissolvable stitches close the incision.
Mayo Clinic and Cleveland Clinic both give a typical operating time of 30 to 90 minutes, longer if turbinate work or other procedures are added.
Anesthesia, packing, and going home the same day
Most septal operations are performed under general anesthesia, meaning you are fully asleep. Local anesthesia with sedation is an option in some centers for straightforward cases, and Mayo Clinic notes that the choice depends on the complexity of the surgery and on what you and your surgeon prefer after discussing your medical history. Neither option is inherently better; the anesthesia team will recommend what suits you.
The question of packing worries people more than almost anything else, often because a relative remembers yards of gauze being pulled out decades ago. Practice has changed. Many surgeons now rely on the quilting stitch or on soft splints instead of packing. Where packing is used, it is usually a soft, sometimes dissolvable material, and MedlinePlus notes that non-dissolving packing is generally removed within about 24 to 36 hours. If splints are placed, they typically stay in for roughly a week and are lifted out in clinic in a few seconds; the sensation is odd rather than painful for most people.
The operation is usually a day case. MedlinePlus states that most people go home the same day, though an overnight stay is sometimes planned for people with other medical conditions, for those having several procedures at once, or if bleeding needs watching. You will not be allowed to drive yourself home after a general anesthetic, so an adult companion is needed.
Before discharge, the nursing team will show you how to sit with your head raised, how to use a small gauze pad under the nose to catch the expected pink ooze, and what to do if bleeding increases. You will usually be given a follow-up appointment and written instructions covering activity, nasal rinsing, and any prescribed medicines. Those instructions, tailored to your operation, take precedence over anything in a general article, including this one.
Is turbinoplasty a major surgery, and why is it so often added?
Because compensatory turbinate enlargement is common on the wider side of a deviated septum, surgeons frequently propose reducing the inferior turbinate in the same session. The umbrella term for these procedures is turbinate reduction; turbinoplasty is a specific form that reshapes the turbinate while preserving its lining.
Several techniques exist, and it helps to know the vocabulary. In a submucosal turbinate reduction, sometimes also called an SMR of the turbinate, the surgeon makes a small incision at the front of the turbinate and removes or shrinks the soft tissue and sometimes a sliver of bone beneath the lining, leaving the surface intact. Radiofrequency or coblation techniques deliver controlled energy through a fine probe into the turbinate, causing the tissue to scar and shrink over the following weeks. A microdebrider is a small suction-cutting instrument that removes soft tissue from inside the turbinate. Partial turbinectomy removes a strip of the turbinate itself and is used more sparingly today.
Is this major surgery? In clinical terms, no. Turbinate reduction is generally a short procedure, often performed under local anesthesia when done alone, and it does not involve external incisions, bone cutting of the face, or a hospital stay in most cases. When combined with a septal operation it adds relatively little to the total time.
“Minor” is not the same as trivial, however. The turbinates do real work: they humidify air, filter particles, and provide the sensation of airflow that tells the brain the nose is open. Removing too much tissue can leave a nose that is wide open on a scan yet feels blocked, dry, and crusty, a condition sometimes called empty nose syndrome. This is why most surgeons favor conservative, lining-preserving methods and why the question is not whether turbinate reduction is major but whether it is necessary and how much is done.
Septal and turbinate procedures side by side: what is being treated and the downsides
People are often booked for two or three procedures at once and struggle to keep them apart. The table below summarizes what each addresses and the drawbacks discussed in mainstream sources, including the turbinate reduction side effects people search for most.
| Procedure | What is corrected | How it is done | Downsides commonly discussed |
|---|---|---|---|
| Classic submucous resection (SMR) | Crooked septal cartilage and bone | Lining lifted; large central plate of cartilage and bone removed; supporting strut kept | Higher chance of weakened septum, saddle deformity, or septal perforation than conservative methods |
| Septoplasty | Same structures, treated selectively | Lining lifted; only obstructing segments trimmed, scored, or repositioned | Residual deviation if cartilage springs back; small perforation risk; temporary numbness of front teeth |
| Submucosal turbinate reduction | Enlarged inferior turbinate soft tissue and bone | Small incision; tissue removed beneath intact lining | Crusting, bleeding, dryness; over-reduction can cause paradoxical blocked feeling |
| Radiofrequency or coblation turbinate reduction | Enlarged turbinate soft tissue | Energy probe shrinks tissue; effect develops over weeks | Milder recovery; regrowth over time is possible, so repeat treatment is sometimes discussed |
| Partial turbinectomy | Turbinate bulk | Strip of turbinate removed with its lining | More bleeding and crusting; greater dryness risk; now used selectively |
Two points deserve emphasis. First, no technique is universally “best”; the choice depends on whether the bulk is soft tissue, bone, or both, and on your surgeon’s training. Second, the downsides of turbinate surgery cluster around one theme, which is removing too much. A surgeon who explains why they plan to be conservative is telling you something reassuring.
Septoplasty recovery time: what the first week usually looks like
The first evening is mostly about congestion. With swollen lining and possibly splints in place, the nose feels completely blocked, and you will breathe through your mouth. A thin, blood-tinged discharge is expected and is caught by a gauze “mustache dressing” taped under the nostrils, which you change as it soaks. Pain is usually described as a dull ache or pressure across the bridge and behind the upper front teeth rather than sharp pain; the teeth may also feel slightly numb because nerves that supply them run near the septum. Mayo Clinic notes this numbness is usually temporary.
How many days of bed rest are needed after septoplasty? Strict bed rest is not generally recommended. Mayo Clinic advises keeping the head elevated when sleeping to reduce swelling and bleeding, and avoiding strenuous activity, but gentle walking around the house is encouraged from the first day because it lowers the risk of blood clots and helps you feel human again. Most people spend the first two or three days resting at home with frequent short walks, not lying flat.
Several instructions are consistent across mainstream sources. Do not blow your nose; Mayo Clinic suggests avoiding this for several weeks. Sneeze with your mouth open. Wear clothing that buttons rather than pulls over your head. Avoid bending, lifting, and anything that raises blood pressure in the face. Saline rinses or sprays are commonly recommended to keep the passages moist and lift crusts; your team will tell you when to start.
Around the end of the first week, splints are removed if they were placed. Many people describe a sudden, almost startling improvement in airflow at that visit, though swelling means the final result is still months away. Mayo Clinic and Cleveland Clinic both indicate that many people return to desk work or school within about a week, depending on how they feel and what their job involves.
Weeks two to six, and why the final result takes months
By the second week, the mustache dressing is gone and the discharge has thinned to clear mucus with occasional crusts. Breathing improves in steps rather than steadily; a good morning may be followed by a congested afternoon, particularly after exertion or in dry air. This is swelling, not failure, and it is the phase where saline rinsing earns its keep by softening and clearing crusts that would otherwise block the passage.
Physical activity returns gradually. Mayo Clinic advises avoiding strenuous activities such as running, weight training, and contact sports for up to five weeks after surgery, because raising blood pressure can trigger bleeding from healing surfaces and because a blow to the nose before the cartilage has firmed could displace the repair. Swimming is usually delayed until the lining has healed and your surgeon confirms it is safe. Air travel is generally possible after the early recovery period, but the pressure changes and dry cabin air can be uncomfortable, so ask your team about timing before booking.
Sense of smell can be dulled for several weeks while swelling blocks airflow to the olfactory area high in the nose, and it usually recovers as the swelling settles. Some people notice the tip of the nose feels stiff or slightly numb; this too tends to ease.
The longer timeline surprises people. Mayo Clinic states that nasal tissues are relatively stable by three to six months after surgery, but that cartilage and tissue can continue to shift or reshape for up to a year. The airway you have at week six is therefore not necessarily the airway you will have at month twelve, and surgeons generally wait at least this long before judging whether any further intervention is worth discussing. Patience during this stretch is not passivity; it is part of the treatment.
Risks and complications, described honestly
Every operation carries risk, and the septum has a few specific ones worth understanding rather than merely signing for. The general risks are those of any surgery under anesthesia: bleeding, infection, and a reaction to the anesthetic. Mayo Clinic lists these alongside the septum-specific problems below.
Bleeding is the most common early issue. A steady pink ooze for a day or two is normal; brisk bleeding that soaks dressings is not, and it is one of the red flags in the final section. Infection is uncommon in the nose because the lining has a good blood supply, but it can occur, particularly around splints.
Septal hematoma is a collection of blood between the two lining flaps. If unrecognized, it can lift the lining off the cartilage and starve it of blood supply, which is one reason surgeons use quilting stitches or splints and why sudden severe blockage or pain after surgery needs prompt review.
Septal perforation is a hole through the septum connecting the two passages. It can follow a tear in both flaps at the same point or a hematoma. Small perforations may cause no symptoms; larger ones can cause whistling, crusting, and nosebleeds. Conservative cartilage preservation reduces but does not eliminate this risk.
Change in nasal shape, particularly a slight dip of the bridge, is more associated with the older extensive SMR than with modern septoplasty but remains possible if support is weakened. Mayo Clinic also lists decreased sense of smell, temporary numbness of the upper gum or teeth, and persistence or recurrence of the blockage, since cartilage has a memory and can drift back toward its old position.
Very rarely, a leak of cerebrospinal fluid can occur if instruments reach the roof of the nose. Your surgeon will discuss which risks are most relevant to your anatomy; the consent conversation is a dialogue, not a formality.
Alternatives to a submucous resection procedure
Surgery is rarely the first step, and for many people it is never needed. Mayo Clinic notes that the initial treatment for a deviated septum is usually aimed at managing symptoms rather than at the septum itself, because the lining, not the cartilage, is often what swells and closes the passage.
Medical treatments prescribed by a clinician work on that lining. Intranasal corticosteroid sprays reduce inflammation in the mucosa and typically take days to a few weeks to reach full effect; they do not change the shape of the septum but can make the narrow side feel wider. Antihistamines help where allergy drives the swelling. Nasal decongestant sprays shrink blood vessels quickly but are generally limited to short courses because prolonged use can cause rebound congestion, a point every mainstream source emphasizes. How any of these are used, and for how long, is a decision for the prescribing clinician.
Saline irrigation is a low-risk measure that clears mucus and allergens and keeps the lining moist. External nasal dilator strips lift the sides of the nose and can help some people at night, particularly if the narrowing is at the nostril valve rather than deeper along the septum; they cannot straighten a bend.
Where the turbinate rather than the septum is the main problem, turbinate reduction alone, sometimes under local anesthesia, may be enough. Where the blockage is at the internal nasal valve, the narrow angle between septum and outer wall, procedures that support the sidewall are considered instead of or alongside septal work.
Doing nothing is also a legitimate choice for someone whose symptoms are mild and who prefers to live with them. A septal deviation is not dangerous in itself. The decision hinges on how much the obstruction affects daily life and sleep, weighed against the risks and recovery described above, and it belongs to you and your treating team together.
What people often get wrong about SMR and turbinate surgery
“It will fix my snoring or sleep apnea.” Nasal obstruction can contribute to snoring, and opening the nose may make a positive airway pressure mask more comfortable, but obstructive sleep apnea is mainly a problem of the throat collapsing during sleep. Septal surgery alone is not a treatment for it, and anyone with suspected apnea needs a sleep assessment regardless of nasal findings.
“It will change how my nose looks.” A septoplasty or SMR is an internal operation. Unless it is deliberately combined with rhinoplasty, the outside of the nose should look the same, and a visible change would be a complication rather than an intended effect.
“The bones are broken.” This confuses septal surgery with rhinoplasty. Thin bone at the back of the septum may be trimmed, but the nasal bones that form the bridge are not fractured in a standard septal procedure.
“Recovery means a black-and-blue face and yards of packing.” Bruising is uncommon after purely internal surgery, and, as described above, many surgeons now avoid packing altogether.
“It’s painful for weeks.” Most people describe pressure and congestion rather than severe pain, and the worst of it is usually in the first few days. Turbinoplasty recovery is often described similarly, with crusting and dryness more prominent than pain.
“Once the septum is straight, the nose stays open forever.” Cartilage can drift, turbinates can regrow, and allergy or infection can swell the lining just as before. Surgery removes a structural cause; it does not make the nose immune to everything else.
“More removed means more relief.” This is the most consequential misunderstanding, particularly for turbinates. Over-resection is the route to a paradoxically blocked, dry nose. The goal is a balanced airway, not a hollow one, and surgeons who remove less are usually acting on good evidence rather than caution for its own sake.
Questions to ask your care team before agreeing to surgery
A good consultation leaves you knowing not just what will be done but why, and what would happen if you did nothing. The questions below are the ones patients most often wish they had asked.
- What exactly did you see on examination, and how confident are you that the septum, rather than swollen lining or the nasal valve, is the main cause of my blockage?
- Will you be performing a classic submucous resection or a cartilage-preserving septoplasty, and what determines how much cartilage you remove?
- Are you planning to reduce my turbinates as well? If so, which technique, how conservative will you be, and what would change if we left them alone?
- Which non-surgical treatments should I try or optimize first, and for how long, before we decide?
- Will I have packing, splints, or a quilting stitch, and when and where will anything be removed?
- What is your plan for my regular medicines around the operation, particularly anything that affects bleeding? (Follow the prescribing clinician’s instructions rather than changing anything yourself.)
- Which of the risks you have listed are most relevant to my anatomy, and how would each be recognized and managed?
- When can I return to my particular job, drive, exercise, and fly, and what should I avoid in the first weeks?
- How will we judge whether the operation has helped, and at what point after surgery would you assess that?
- Whom do I contact, and by what route, if something worries me at night or over a weekend?
Write the answers down or bring someone to listen with you. The details that matter most, such as how conservative the turbinate plan is, are easy to lose in a busy clinic, and they are the details you will want later.
When to call your doctor after a submucous resection
Recovery from septal surgery is usually uneventful, but a small number of problems need prompt attention, and knowing them in advance removes the guesswork. Your surgical team will have given you a contact route; use it rather than waiting for the scheduled follow-up if any of the following occur.
Bleeding is the most common reason to call. A slow pink ooze that lightens over the first couple of days is expected. Bright red blood that runs steadily, soaks through a gauze pad in minutes, or continues despite sitting upright and applying gentle pressure to the soft part of the nose for ten to fifteen minutes is not, and needs same-day assessment. Swallowing repeated mouthfuls of blood or vomiting blood is a reason to seek emergency care.
Fever, worsening pain after the first few days, spreading redness or swelling of the nose or face, or foul-smelling discharge can signal infection. Sudden severe blockage on one side with increasing pain and a bulging feeling may indicate a septal hematoma, which is treated by draining it promptly. A persistent clear, watery drip from one nostril, especially one that worsens when you lean forward, or a new severe headache with a stiff neck, needs urgent evaluation.
Vision changes, double vision, or swelling around the eye are rare but should never be ignored. Nor should difficulty breathing, chest pain, or a swollen, painful calf, which may point to a blood clot after any surgery. Call emergency services for any of these.
Less dramatic symptoms also deserve a call: breathing that becomes worse rather than better after week two, a whistling sound when you breathe, or crusting and dryness that saline rinsing does not ease. None of these means something has gone wrong, but each is best judged by the team that knows your operation. When in doubt, ask; a short phone call is always the right call.
Frequently asked questions
What is SMR nose surgery, and is it the same as septoplasty?
SMR nose surgery is a submucous resection of the septum: the lining is lifted and crooked cartilage or bone beneath it is removed. Septoplasty is the modern, cartilage-preserving version of the same idea, trimming or reshaping only the obstructing parts. Many surgeons use the terms interchangeably, and the exact extent of removal is usually decided during the operation once the septum is exposed.
How painful is turbinoplasty recovery?
Most people describe turbinoplasty recovery as uncomfortable rather than severely painful, with congestion, crusting, dryness, and a pressure sensation dominating the first week. Pain is usually managed with medicines your clinician prescribes or advises, and saline rinsing helps with crusts. When turbinoplasty is combined with septal surgery, the septal component tends to account for more of the ache across the bridge and upper teeth.
How many days of bed rest are needed after septoplasty?
Strict bed rest is not generally recommended after septoplasty. Mayo Clinic advises resting with your head elevated and avoiding strenuous activity, but gentle walking from the first day is encouraged because it reduces clot risk. Most people rest at home for the first few days and return to desk work within about a week, with vigorous exercise delayed for up to five weeks as directed by their surgeon.
Is turbinoplasty a major surgery?
No, turbinoplasty is generally considered a minor procedure. It is short, involves no external incisions, is often done under local anesthesia when performed alone, and rarely requires an overnight stay. That said, the turbinates humidify and filter air, so removing too much tissue can cause long-term dryness and a paradoxical blocked feeling. Conservative, lining-preserving technique is what most surgeons aim for.
What are the downsides of turbinate reduction surgery?
Common turbinate reduction side effects include crusting, dryness, temporary bleeding, and congestion during healing. Tissue can regrow over time, so repeat treatment is sometimes discussed. The most serious downside is over-reduction, which can leave the nose feeling blocked and dry despite being anatomically open, sometimes called empty nose syndrome. Surgeons reduce this risk by removing only as much tissue as needed and preserving the lining.
What is the difference between submucous resection vs septoplasty in terms of risk?
Classic submucous resection removes a larger plate of septal cartilage and bone, which historically carried a higher risk of a weakened septum, a sunken bridge, or a hole between the two nasal passages. Septoplasty preserves more cartilage, lowering those long-term structural risks, though residual deviation is possible if the cartilage springs back. Both share the general risks of bleeding, infection, and anesthesia.
How long is septoplasty recovery time before I can breathe normally?
Breathing usually improves noticeably once swelling begins to settle and any splints are removed around the end of the first week, but it fluctuates for several weeks afterward. Mayo Clinic notes that nasal tissues are relatively stable by three to six months and that cartilage can continue to shift for up to a year. Surgeons generally wait this long before assessing the final airway.
Will a submucous resection change the shape of my nose?
It should not. Submucous resection and septoplasty are internal operations performed through incisions inside the nostril, and the outside of the nose is expected to look the same afterward. A visible change, such as a dip in the bridge, would be a complication rather than an intended effect, and it is more associated with the older extensive resection than with modern cartilage-preserving technique. Cosmetic change requires a separate rhinoplasty.
Do I need nasal packing after SMR?
Not necessarily. Many surgeons now avoid traditional packing, using a quilting stitch through the septal flaps or soft silicone splints instead. Where packing is used, MedlinePlus notes it is generally removed within about 24 to 36 hours, and dissolvable materials are common. Splints, if placed, typically stay in for around a week and are removed quickly in clinic. Your surgeon will tell you which approach they plan.
Can a deviated septum be treated without surgery?
Often, yes, at least in terms of symptoms. Mayo Clinic notes that initial treatment usually targets the swollen lining rather than the cartilage, using clinician-prescribed nasal corticosteroid sprays, antihistamines where allergy is involved, and saline irrigation. These cannot straighten the septum but may open the passage enough that surgery is unnecessary. Surgery is generally considered when symptoms persist despite such treatment.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Does Vertigo Need an ENT Specialist Rather Than Waiting for It to Pass?
See a doctor promptly for any first episode of vertigo, and seek same-day or emergency care if spinning arrives with a severe new headache,…

When Is Earwax Build Up a Job for an ENT Specialist Rather Than Ear Drops?
Most earwax build up clears on its own or with a few days of softening ear drops, so an ENT is not the first…
After an Intratympanic Steroid Injection: Ear Fullness, Dizziness and What to Report
After an intratympanic steroid injection, most people notice temporary ear fullness, muffled hearing and brief dizziness that settle within hours to a few days,…

Living With an Implantable Hearing Aid: Swimming, Skin Care Around the Post and Daily Use
Living with an implantable hearing aid usually means a short daily routine: the external sound processor comes off before swimming, bathing or sleeping, and…

Flying and Pressure Changes After Stapedectomy Surgery: What International Patients Ask
Most surgeons ask patients to avoid flying after stapedectomy for a period of weeks, not days, because cabin pressure changes stress the healing eardrum…
Mastoid Surgery Recovery: Dressings, Ear Drops and When Dizziness and Fullness Settle
Mastoidectomy recovery usually means a padded head dressing for the first day or so, dissolvable or removable packing in the ear canal for several…