

Sun Protection After Dermabrasion: Why Strict Cover Matters for Months, Not Days

Key Takeaways
- New skin usually covers a dermabrasion wound in about 5 to 8 days, but the pink color that signals ongoing healing takes roughly three months to fade, according to Mayo Clinic.
- Pigment changes after dermabrasion, both darkening and lightening, are more common in people with darker skin and can sometimes be permanent, which is why strict sun avoidance is treated as part of the procedure.
- Sunscreen is not applied to open skin; it starts once the surface has closed and then belongs on the face every day, reapplied at least every two hours outdoors as advised by the CDC and NHS.
- Mayo Clinic advises avoiding unprotected sun for about two months before dermabrasion as well, because recently sun-exposed pigment cells are primed to react unevenly to the injury.
- The World Health Organization recommends protective measures whenever the UV index reaches 3 or above, a threshold reached on many cool or cloudy days, not only in high summer.
- Ordinary window glass lets much of the UVA through, so a long drive or a sunny desk counts as exposure for skin that is still remodeling in the months after resurfacing.
Sun protection after dermabrasion needs to continue for months, not days, because the newly grown skin is thin and its pigment cells are easily overstimulated by ultraviolet light. Strict shade and covering apply while the surface is still raw; once it has closed, usually within about a week, daily broad-spectrum sunscreen, hats and shade are advised until the pink color has fully faded, often three months or longer.
The dressings came off a week ago. In the bathroom mirror the treated cheeks look like the inside of a seashell: smooth, pink, almost translucent. Then the phone buzzes. A friend is hosting lunch in the garden on Saturday, the forecast says clear skies, and the obvious question arrives before the reply does: is it really such a big deal to sit outside for an hour?
That hesitation is the right instinct. Sun protection after dermabrasion is the part of recovery that quietly decides how the result looks a year from now, and it is the part people most often shorten. Skin that has been resurfaced down to the upper dermis rebuilds its surface in days, but it rebuilds its pigment control over a far longer stretch.
This explainer walks through what the procedure does to the skin, why ultraviolet light is such a specific threat during the months that follow, what the evidence says about timing, and which warning signs deserve a call to your care team.
What dermabrasion actually does to the skin
Dermabrasion is a controlled sanding of the skin. A clinician uses a rapidly rotating instrument, usually a wire brush or a diamond-coated wheel, to remove the outer layer of skin (the epidermis) and reach into the upper part of the layer beneath it (the dermis). It is done under local anesthetic, often with sedation, and sometimes under general anesthesia for larger areas, according to Mayo Clinic.
It helps to picture what is left behind. The treated area is an open wound, similar in depth to a deep graze. Healing happens from below and from the sides: skin cells migrate out of the hair follicles and sweat gland openings that survive in the deeper dermis, and they spread across the surface until the wound closes. Mayo Clinic notes that new skin typically covers the area in about 5 to 8 days, while the pink color that follows takes roughly three months to fade.
Two definitions matter here. Re-epithelialization is the process of new surface skin growing across a wound. Remodeling is the slower phase afterward, when collagen in the dermis is reorganized and the skin’s thickness, color and texture settle. The first phase is quick and visible. The second is slow and invisible, and it is the one sun exposure interferes with.
Dermabrasion is not the same as microdermabrasion. Microdermabrasion is a light exfoliation that removes only the dead outer cells, needs little or no downtime, and does not create the long sun-sensitive window described in this article. Laser resurfacing and deep chemical peels, by contrast, reach similar depths to dermabrasion and share many of the same aftercare principles, including prolonged sun avoidance.
Why freshly resurfaced skin reacts so strongly to ultraviolet light
Normal skin has two layers of defense against the sun. The outermost layer, the stratum corneum, is a dense sheet of dead cells that scatters and absorbs some ultraviolet (UV) light. Beneath it, pigment cells called melanocytes make melanin, the brown pigment that acts as a built-in filter, and hand it to surrounding cells in tidy, even amounts.
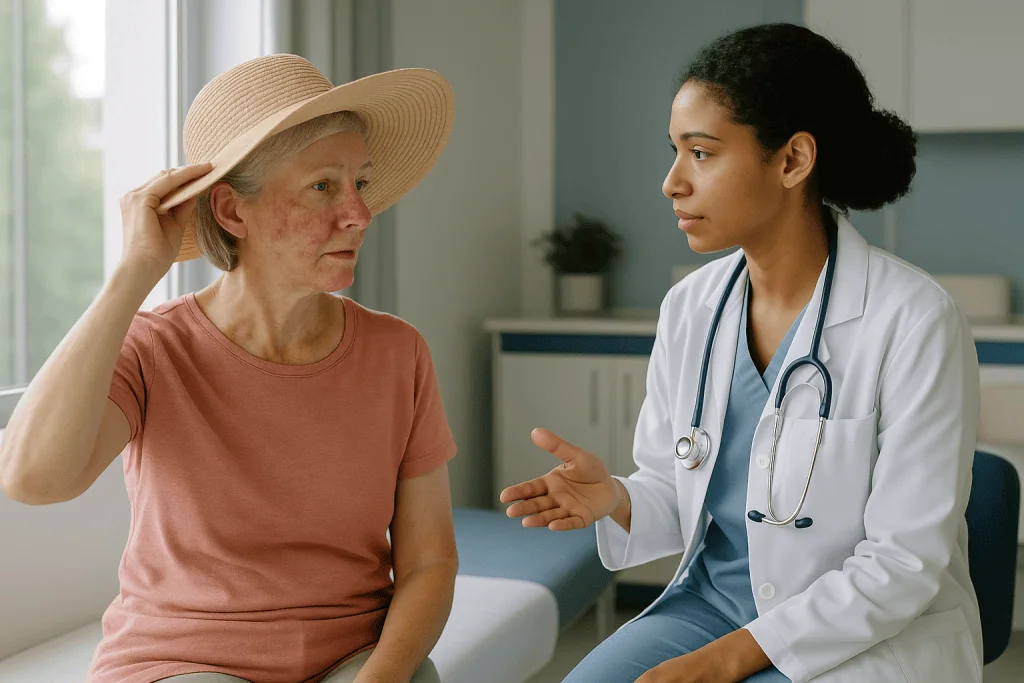
Dermabrasion removes both. The new epidermis that grows back in the first week is thinner than the original and its stratum corneum is immature. More UV reaches the living cells underneath. At the same time the melanocytes are repopulating the area and are already primed by inflammation; the chemical signals that drive wound healing also tell pigment cells to switch on. Add UV exposure, which is the strongest trigger for melanin production the skin knows, and those cells can respond unevenly, producing darker patches in some spots and little pigment in others.
The two outcomes have clinical names. Post-inflammatory hyperpigmentation is darkening of skin after injury or inflammation. Hypopigmentation is loss of normal color, which can occur when melanocytes themselves are damaged. Mayo Clinic lists both as recognized risks of dermabrasion, notes they are more common in people with darker skin, and warns that they can sometimes be permanent.
The dermis is exposed too. For months after the procedure, collagen is being laid down and reorganized. UVA, the longer-wavelength part of sunlight, penetrates to this depth and activates enzymes that break collagen down, which is the same mechanism behind ordinary photoaging. Resurfacing is meant to improve texture and scarring; sunlight during remodeling pulls in the opposite direction.
None of this is theoretical. It is why every mainstream aftercare protocol for deep resurfacing treats sun avoidance as a core instruction rather than a courtesy reminder.
How long after dermabrasion can I go in the sun?
The honest answer has three parts, because the risk changes as the skin changes.
While the surface is open, the answer is not at all. During the first week, before new skin has grown across the wound, the area should be kept out of direct sunlight entirely. Sunscreen is generally not applied to raw skin; cover comes from staying indoors, dressings as directed, a wide-brimmed hat and full shade for any unavoidable time outside. Mayo Clinic’s guidance is to avoid sun exposure until the treated area has healed over.
Once the skin has closed, usually around days 5 to 8 according to Mayo Clinic, the answer becomes brief, protected exposure only. Daily broad-spectrum sunscreen starts at this point, and deliberate sunbathing, sports in open sun and beach days remain off the table. The skin is sealed but it is pink, thin and reactive.
After that, the answer is tied to color rather than the calendar. Mayo Clinic advises protecting treated skin from the sun until its color has returned to normal, and describes the pinkness as taking about three months to fade. Pink skin is a visible sign that blood flow and inflammation are still elevated, which is exactly the state in which pigment cells overreact. Many care teams extend strict precautions beyond the point where pinkness fades, particularly for people with deeper skin tones, a history of uneven pigmentation, or treatment on areas that catch a lot of light such as the cheekbones and upper lip. How long that window runs is their call, based on what your skin is doing.
So the garden lunch in the opening scene is possible, but only in the shade, under a hat, with sunscreen applied on closed skin and a willingness to move indoors when the shadows shift.
Sun protection after dermabrasion, phase by phase
Recovery is easier to manage when the rules are matched to what the skin is doing at each stage. The ranges below come from Mayo Clinic’s description of dermabrasion healing and from general sun-safety guidance from the CDC and NHS; your own team’s instructions override any general timeline.

| Phase | What the skin is doing | Sun approach |
|---|---|---|
| Days 1–7 | Open, weeping, then crusting; new cells migrating in from follicles | No direct sun. Indoors or deep shade only; dressings and ointment as directed; sunscreen not applied to open skin |
| Around days 5–8 | New epidermis closes over the surface (Mayo Clinic) | Begin daily broad-spectrum sunscreen once your team confirms the skin is sealed; hat and shade for any time outdoors |
| Weeks 2–4 | Swelling settles; skin bright pink, thin and easily irritated | Sunscreen every morning and reapplied at least every two hours outdoors (CDC); avoid peak UV hours; no sports or long outings in sun |
| Months 1–3 | Pinkness gradually fades (about three months, Mayo Clinic); collagen remodeling under way | Continue daily protection without exceptions; shade and hat remain the primary tools |
| Month 3 onward | Color settling; remodeling continues quietly | Keep strict cover until your team confirms color has normalized; a daily sunscreen habit is then worth keeping for life |
Two patterns are worth noticing. First, the protection intensity does not drop sharply at any stage; it shifts from physical avoidance to layered protection. Second, the phase most people treat casually, months one to three, is the one in which the skin looks healed to a friend but is still biologically unsettled. The pink color is doing you a favor by making that visible.
Hyperpigmentation after dermabrasion: the outcome strict cover is guarding against
Ask a clinician what they most want to prevent in the months after resurfacing and the answer is usually the same: uneven color. A scar that was softened or a wrinkle that was smoothed can be undone, in the viewer’s eye, by a patch of darker skin sitting right where the treatment was.
Post-inflammatory hyperpigmentation, defined earlier as darkening after injury or inflammation, tends to show up weeks rather than days after the trigger. It appears as flat tan, brown or grayish patches that follow the shape of the treated area or of whatever part caught the sun. Cleveland Clinic describes this kind of hyperpigmentation as something that can fade over months once the trigger is removed, and notes that continued sun exposure makes it darker and more persistent.
Hypopigmentation is the mirror image and in some ways the harder one. When melanocytes are damaged, the area may heal lighter than the surrounding skin, and the contrast becomes most obvious in summer when untreated skin tans and the treated zone does not. Mayo Clinic flags that both darkening and lightening can be permanent in some people.
If color changes do develop, there are options, and they belong to your treating team. Clinicians may consider topical agents that slow pigment production, such as retinoids or other prescription lightening preparations, or further procedures once the skin has fully settled. The evidence for these is strongest when sun protection continues alongside them; without it, pigment tends to return. No topical product is a substitute for shade, and none should be started on healing skin without the prescriber’s direction.
The practical point is that prevention is cheap in effort and correction is slow and uncertain. That imbalance is the whole argument for treating sun protection after dermabrasion as part of the procedure itself.
Who dermabrasion is usually for, and who is usually asked to wait
Dermabrasion is most often offered for acne scars, surgical or injury scars, fine lines around the mouth, rough sun-damaged texture and some types of uneven skin color, according to Mayo Clinic. It is a surgical procedure with real downtime, which is partly why it is chosen for specific, well-defined problems rather than general skin refreshing.
A number of situations lead clinicians to recommend waiting or choosing another approach. Mayo Clinic’s list includes:
- Use of the acne medication isotretinoin within the past year, because of concerns about delayed healing and scarring; the exact waiting period is set by the prescriber.
- A tendency to form keloids or thick raised scars.
- Active acne, a current cold sore outbreak or other skin infection in the treatment area.
- Recent radiation treatment, a burn, or a chemical peel on the same skin.
- Skin conditions that flare with injury, and bleeding disorders or medicines that affect clotting, which the team will review individually.
Skin tone shapes the conversation rather than ending it. People with darker skin carry a higher risk of pigment changes after any deep resurfacing, and a careful clinician will discuss that openly, may suggest a test area, and may prefer gentler alternatives.
One factor rarely appears on formal lists but matters enormously for this topic: your life for the next several months. Someone who works outdoors, coaches a weekend sports team, has a sun holiday booked or simply knows they will not keep up daily sunscreen is, in practical terms, not a good candidate right now. Delaying the procedure to a season when strict sun protection after dermabrasion is realistic is a legitimate medical decision, and many teams will raise it themselves.
Sunscreen after dermabrasion: what to look for and how to use it
Sunscreen is the second line of defense, after shade and clothing, but it is the one that travels with you, so it is worth getting right.
Start only when the skin has closed. Products should not be applied to raw or weeping skin, and most teams will tell you when the surface is sealed enough. Until then, physical cover does the job.
Choose broad spectrum, which means the product filters both UVB (the burning wavelengths) and UVA (the deeper, aging wavelengths). The CDC advises a broad-spectrum product with SPF 15 or higher for general use, and the NHS recommends at least SPF 30 with a high UVA rating; after resurfacing, the higher end of those ranges is the sensible choice. Fragrance-free formulations reduce the chance of irritating skin that is already reactive.
Mineral filters, meaning zinc oxide and titanium dioxide, sit on the surface and reflect or scatter light, and clinicians often favor them on recently healed skin because they are less likely to sting. Chemical filters absorb UV and are also effective; the preference for mineral filters early on is based mainly on tolerability and clinical experience rather than a difference in protection. A patch test on untreated skin, such as the inner forearm, is a reasonable precaution with any new product.
Quantity and timing are where most people fall short. The NHS suggests roughly two teaspoons of sunscreen for the head, neck and arms, applied about half an hour before going out, and advises reapplying at least every two hours, immediately after swimming or heavy sweating, and after towel drying. The CDC gives the same two-hour reapplication interval. A thin smear applied once at breakfast gives a fraction of the labeled protection.
Treat sunscreen as a daily habit on this skin, not an outdoor accessory. Short walks, school runs and time near windows all count.
Beyond sunscreen: shade, hats, windows and the UV index
If sunscreen is the only tool in use, the plan is too thin. The CDC’s ordering is instructive: shade first, then clothing and hats, then sunglasses, with sunscreen covering what the others miss.
Timing is the simplest lever. UV intensity peaks in the middle of the day; the CDC describes the strongest rays as falling between about 10 a.m. and 4 p.m., and the NHS points to roughly 11 a.m. to 3 p.m. in its guidance. Scheduling errands early or late changes the dose more than any product can.
The UV index is a daily forecast of how strong ultraviolet radiation will be. The World Health Organization advises that protection is needed when the index reaches 3 or above, and that UV can be high even on cool or overcast days. Most weather apps display it; during the months after resurfacing, checking it is as useful as checking for rain.
Hats need a brim that shades the face, ears and neck all the way around, which rules out most baseball caps. Clothing with a UPF label (ultraviolet protection factor, a fabric rating comparable to SPF) covers treated skin on the neck or chest reliably. Sunglasses matter if the eyelids or the skin around the eyes were treated, and they help in any case.
Windows deserve a specific mention. Ordinary glass blocks most UVB but lets a large share of UVA through, which is why a long drive or a desk by a sunny window counts as exposure for healing skin. Reflected light counts as well: WHO notes that water, sand and snow bounce UV back onto the face, raising the dose even in the shade of an umbrella.
Finally, tanning beds are off limits, now and ideally forever. The CDC classes them as a source of harmful UV with no safe level of use.
Dermabrasion aftercare instructions that work alongside sun protection
Sun care does not operate in isolation. Several other aftercare habits either protect the skin’s new surface directly or keep it in a state where it tolerates light better. Mayo Clinic’s recovery guidance covers most of the following; your team’s written sheet is the version to follow.
Keep the surface moist as directed. Many clinicians use an ointment or a specialized dressing in the first days so that new cells can migrate across a hydrated wound. Dry, cracked skin heals more slowly and is easier to injure, including by light. After the skin closes, a bland, fragrance-free moisturizer under the morning sunscreen serves the same purpose.
Do not pick at crusts or flaking skin. Pulling off a crust reopens the wound beneath it, resets the clock in that spot, and creates a small island of skin that is even more prone to uneven color.
Hold off on active skincare. Retinoids, exfoliating acids, scrubs and anything that tingles are generally paused until the team clears them, because they thin or irritate a surface that is already thin. The same goes for makeup, which Mayo Clinic advises only once the new skin has fully covered the area; mineral makeup can then add a little extra physical cover.
Avoid chlorinated pools, saunas and strenuous sweating for the period your team specifies. Chlorine and heat irritate healing skin, and swimming combines that with intense reflected sunlight.
Take prescribed medicines as directed. Some teams prescribe a short course of an antiviral to prevent cold sore virus from reactivating on raw skin, or an antibiotic in selected cases. These are decisions for the prescriber, and starting, stopping or adjusting them is theirs to make.
Finally, stopping smoking before and after the procedure improves wound healing, a point Mayo Clinic makes for dermabrasion specifically.
Does sun protection after dermabrasion change by skin tone or season?
The principles do not change. The margin for error does.
Clinicians often describe skin tone using the Fitzpatrick scale, a six-point system based on how skin burns and tans in the sun. People at the deeper end of the scale have melanocytes that are more responsive to any stimulus, which is why they tan readily and why Mayo Clinic identifies darker skin as carrying a higher risk of pigment changes after dermabrasion. For these patients, a lapse that would leave a fair-skinned person slightly pinker can leave a persistent dark patch. Strict cover for the full duration is non-negotiable, and many teams add precautions before the procedure as well.
Fair skin is not exempt. It burns more easily, and a sunburn on freshly healed skin is a second injury layered on the first; it can also produce hypopigmentation when melanocytes are damaged. Fair skin simply shows the earliest warning sign, redness, more readily.
Season matters less than people assume. The UV index drops in winter at temperate latitudes, but it rarely reaches zero in daylight hours, and the World Health Organization notes that snow reflects a high proportion of UV, that altitude raises intensity, and that light cloud lets much of it through. A winter ski weekend is one of the highest-exposure environments a healing face can meet. Conversely, a summer recovery is not impossible; it just demands tighter planning around the midday hours.
Geography adds another layer. Closer to the equator, the UV index stays high year-round, so the idea of a safe season disappears entirely. Someone who travels for the procedure and then recovers somewhere sunnier than home needs to adjust expectations accordingly.
The through-line is that sun protection after dermabrasion is a fixed requirement; skin tone, season and location only decide how unforgiving a slip will be.
Why sun exposure before dermabrasion matters too
Most attention goes to the weeks after the procedure, but the weeks before set the stage. Mayo Clinic advises avoiding unprotected sun exposure for about two months beforehand and warns that recent sun can cause permanent irregular pigmentation in the treated area.
The mechanism is the same one that applies afterward, just in a different order. Sun exposure activates melanocytes and leaves them in an alert state for weeks after the tan fades. If the skin is then injured by resurfacing, those already stimulated cells are more likely to respond to the inflammation with excess, patchy pigment. A tan also masks the skin’s true baseline color, which makes it harder for the clinician to judge depth and predict how the area will match its surroundings.
This is why many care teams build a preparation phase into the plan. It may include daily sunscreen on the treatment area for several weeks, and for some patients, particularly those with deeper skin tones, a period of prescribed topical treatment intended to calm pigment cells before surgery. Whether that is appropriate, and which agents are used, is a decision for the prescribing clinician; the point for readers is that a pre-treatment sunscreen habit is not optional window dressing.
There is a practical benefit as well. People who have already practiced two months of consistent daily protection arrive at the procedure with the habit formed, the right products identified and any irritation issues sorted out. The hardest part of a long aftercare window is not any single day; it is the persistence. Starting before the procedure makes the months afterward feel like a continuation rather than a new regime imposed on a sore face.
If the preparation period has been interrupted by an unplanned burn or a tanned holiday, tell the team. Postponing is far less costly than resurfacing primed skin.
What people often get wrong
The myths around this topic are not exotic. They are reasonable-sounding shortcuts, which is what makes them dangerous.
Once the skin has closed, the risk is over. Closure around a week is the start of the sun-sensitive period, not the end. Pigment cells and collagen keep remodeling for months, and Mayo Clinic ties protection to color returning to normal, not to the wound sealing.
Sunscreen in makeup or moisturizer is enough. Tinted products are usually applied far too thinly to deliver the labeled SPF, and they are rarely reapplied. They can supplement a dedicated sunscreen; they cannot replace it.
Cloudy days do not count. The CDC and WHO both note that UV passes through cloud cover, and a cool, bright day is a classic setting for an unplanned burn because nothing feels hot.
A base tan protects the new skin. A tan is a sign of UV damage, offers only minimal protection, and leaves melanocytes primed to overreact. There is no version of deliberate tanning that helps after resurfacing.
Higher SPF means staying out longer. SPF describes how much UVB is filtered when the product is applied generously; it is not a timer. Reapplication every two hours applies regardless of the number on the bottle, per the CDC and NHS.
A hat replaces sunscreen. A brimmed hat shades the forehead and nose well, but reflected light from pavement, water and sand reaches the cheeks, chin and neck from below. Both are needed.
If there is no sunburn, there was no harm. Pigment changes are triggered by doses of UV well below the burn threshold, and they appear weeks later, long after the day in question has been forgotten.
Mineral sunscreen is the only safe option. Mineral filters are often better tolerated early on, but broad-spectrum chemical filters are also effective; the right choice is the one that is used generously every day.
Questions to ask your care team
A good consultation leaves you with specifics rather than reassurance. These questions tend to produce useful answers, and writing down the responses saves second-guessing later.
- On which day do you expect my skin to be closed enough for sunscreen, and how will I know?
- For how many months do you want me to follow strict sun avoidance, and what signs will tell you it can relax?
- Given my skin tone and history, how high do you consider my risk of hyperpigmentation or hypopigmentation, and does that change your plan?
- Should I be using anything on the treatment area in the weeks before the procedure, and for how long?
- Which type of sunscreen do you suggest for my skin at each stage, and are there ingredients you would prefer I avoid early on?
- How should I protect the area indoors, in the car and at a desk by a window?
- What is your advice on swimming, outdoor exercise and travel during recovery, and when can each resume?
- If I develop darker or lighter patches, at what point should I contact you, and what might the options be?
- Is there a season you would prefer for my procedure, given my work and plans?
- Who do I call if I have a concern outside clinic hours?
Two further points are worth raising even if they feel awkward. First, be honest about your lifestyle: if you know that daily sunscreen and midday shade are unlikely for six months, say so, because the team may suggest a different treatment or a different time rather than a result compromised by exposure. Second, ask for the aftercare instructions in writing, including the sun protection timeline, so that the plan does not depend on memory during a week when you are sore and tired. The decisions sit with the treating team; the questions make sure you understand them.
When to call your doctor
Most recoveries are uneventful, but healing skin can get into trouble quickly, and sun-related problems in particular are easier to manage early. Contact your care team promptly if you notice any of the following on or around the treated area:
- Redness that spreads outward, increasing warmth or swelling, or pain that worsens after the first few days instead of easing.
- Yellow or green discharge, a foul smell, or a fever, which can signal infection.
- Clusters of small blisters or a tingling, burning patch, which can indicate cold sore virus reactivating on raw skin and usually needs prompt treatment.
- Sunburn on the treated skin: new redness, heat or blistering after time outdoors.
- Patches that are becoming noticeably darker or lighter than the surrounding skin, especially if they appear weeks after the procedure.
- Areas that feel thick, raised or firm, which may be early scarring.
- Itching, stinging, swelling or a rash after applying sunscreen or any other product, which can indicate irritation or allergy.
- Any crust that has been knocked off and left a raw, bleeding or weeping spot that is not settling.
Seek urgent care, rather than waiting for a routine call-back, if you develop a high fever with rapidly spreading redness, if swelling involves the lips, tongue or throat, or if you have difficulty breathing after using a product; these can indicate a serious infection or a severe allergic reaction.
When in doubt, make the call. Clinicians who perform resurfacing expect questions during recovery, and a short conversation about a pink patch is far better than a long course of treatment for a dark one. What happens next, including any change to your aftercare or medicines, is a decision for the team looking after you.
Frequently asked questions
How long after dermabrasion can I go in the sun without worrying?
Not until your care team says the color has returned to normal, which Mayo Clinic describes as taking about three months for the pinkness alone. In the first week, before the skin has closed, direct sun should be avoided completely. After that, brief outings are possible with shade, a wide-brimmed hat and broad-spectrum sunscreen, but deliberate sun exposure stays off the table for months.
What kind of sunscreen after dermabrasion do clinicians usually suggest?
A broad-spectrum, fragrance-free product with a high SPF, applied generously once the skin has sealed. Mineral filters such as zinc oxide and titanium dioxide are often preferred early because they are less likely to sting, though broad-spectrum chemical filters also protect well. The NHS suggests at least SPF 30 with a high UVA rating; your team may name a preferred type for your skin.
Why does hyperpigmentation after dermabrasion happen even without a sunburn?
Because pigment cells respond to UV doses far below the burn threshold, and after resurfacing they are already activated by inflammation. Melanin production then becomes uneven, producing darker patches that typically appear weeks later. Cleveland Clinic notes that this post-inflammatory darkening can fade over months once the trigger is removed, but ongoing sun exposure makes it deeper and more persistent.
Are dermabrasion aftercare instructions different for darker skin tones?
The core instructions are the same, but the stakes are higher. Mayo Clinic identifies darker skin as carrying a greater risk of both darkening and lightening after dermabrasion. Teams often add precautions, such as a longer period of prescribed preparation before the procedure, a test area, or stricter and longer sun avoidance afterward. The specifics are tailored by the treating clinician.
Do I need sun protection indoors after dermabrasion?
Near windows, yes. Standard glass blocks most UVB but allows a substantial share of UVA to pass, and UVA reaches the dermis where collagen is being rebuilt. A desk beside a sunny window or a long car journey counts as exposure for healing skin. Away from direct window light, the dose is low, but a daily morning sunscreen habit removes the guesswork.
Can I use makeup with SPF instead of sunscreen while my skin heals?
Not as the main protection. Makeup is applied far more thinly than the amount used to test SPF and is rarely reapplied, so the real protection is a fraction of the label. Mayo Clinic advises waiting until new skin fully covers the area before using any makeup at all. Once cleared, tinted mineral products can add a little cover on top of a proper sunscreen layer.
What happens if I get sunburned on skin treated with dermabrasion?
Contact your care team. A burn on newly healed skin is a second injury on top of the first and raises the risk of persistent darkening, lightening or scarring. Move indoors, keep the area cool and moisturized as your team directs, and avoid any further exposure. The clinician may want to see the area and adjust your aftercare; that decision is theirs to make.
Is sun exposure before dermabrasion really a problem?
Yes. Mayo Clinic advises avoiding unprotected sun for about two months before the procedure and warns that recent exposure can cause permanent irregular pigmentation in the treated area. Sun leaves pigment cells in an alert state for weeks, so they overreact when the skin is then injured. If you have had a burn or a tanning holiday, tell the team; postponing is a reasonable option.
Does a cloudy or cold day mean I can skip protection after dermabrasion?
No. The CDC and WHO both note that UV penetrates cloud cover, and the World Health Organization advises protection whenever the UV index is 3 or above, which happens on many overcast or cool days. Snow, water and sand reflect additional UV onto the face. Checking the daily UV index is a more reliable guide than temperature or how bright the sky looks.
How can I tell whether a dark patch is normal healing or hyperpigmentation?
You often cannot tell reliably on your own, which is why new darkening or lightening should be reported to your care team rather than watched for weeks. Early pinkness and mild blotchiness are expected while blood flow is high; flat brown or gray patches appearing later, especially where light reached the face, are the pattern clinicians want to assess early.
References
- CDC: Sun Safety
- NHS: Sunscreen and sun safety
- MedlinePlus: Sun Exposure
- WHO: Radiation: The ultraviolet (UV) index
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What Happens During an IPL Photorejuvenation Session: Cooling Gel, Flashes and Timing
During an IPL photorejuvenation session, a clinician cleanses the skin, applies a cool clear gel, gives you protective eyewear, and passes a handpiece across…

Why Your Cold Sore History Matters Before Laser Resurfacing and How Doctors Prepare for It
Your cold sore history matters before laser resurfacing because the herpes simplex virus that causes cold sores stays dormant in facial nerves and can…

What to Stop Before a Chemical Peel: Retinoids, Scrubs, Waxing and Sun Exposure
Before a chemical peel, people are usually asked to pause topical retinoids and exfoliating acids, stop facial scrubs, masks and exfoliating devices, avoid waxing,…

Laser Resurfacing Results: What Fine Lines and Acne Scars Realistically Look Like Afterward
Laser resurfacing results are usually a partial, gradual softening rather than a complete erasure. Fine lines around the eyes and mouth commonly look shallower,…

Blood Thinners, Anti-Inflammatories and Mesotherapy: What Your Doctor Checks First
Blood thinners and anti-inflammatory medicines matter for mesotherapy because the treatment relies on many shallow needle punctures, and anything that slows clotting raises the…

Masseter Botox vs a Night Guard for Bruxism: How Dentists and Doctors Weigh the Two
A night guard shields teeth from the force of grinding but does not reduce the clench itself; masseter botulinum toxin (widely known as Botox)…