

The MRI Visit: Duration, Preparation and What Happens in the Tube
Key Takeaways
- A single-region MRI usually takes 30–45 minutes, but cardiac and full-spine studies can run 60–90 because they image moving targets or multiple areas.
- MRI uses a powerful magnet and radio waves — no ionizing radiation — which is why the safety rules are about metal, not dose.
- Skip antiperspirant before breast or underarm imaging: aluminum particles can smudge the images, though they pose no danger with the magnet.
- The knocking can exceed 110 decibels — rock-concert territory — so hearing protection is mandatory, and sudden changes in the sound just mean a new sequence started.
- Holding still is the biggest factor you control: one cough mid-sequence can force a repeat and add ten or more minutes to the scan.
- Unless you were sedated, no rest is needed afterward — you can drive home and return to normal activities immediately.
Most MRI scans take between 15 and 90 minutes, depending on the body part, the number of imaging sequences, and whether contrast dye is used. A knee or brain scan often finishes in 30 to 45 minutes, while multi-region spine, abdominal, or cardiac studies can run an hour or more. Plan roughly two hours door to door to allow for check-in, safety screening, and changing.
The first thing most people remember about an MRI isn’t the tube. It’s the sound — a rhythmic hammering, like someone testing a jackhammer two rooms away, filtered through foam earplugs while a voice on an intercom cheerfully says, “Doing great, four minutes left on this one.”
If you’ve never had one, the unknowns pile up fast. Can you eat breakfast? Does the deodorant question people whisper about actually matter? Will you be in there for twenty minutes or two hours? The honest answer is that timing varies more than most articles admit, and the variables are knowable in advance.
So here’s the full picture: what determines the clock, what happens minute by minute once the table slides in, what genuinely helps beforehand, and what’s just folklore — all of it grounded in what major medical sources actually say.
How long does an MRI take, honestly?
The range you’ll see everywhere — 15 to 90 minutes — is accurate, but it hides the mechanics. An MRI isn’t one continuous picture. It’s a stack of separate imaging runs called sequences, each lasting roughly one to six minutes, and each capturing the tissue in a different way: one sequence highlights fluid, another shows fat, another reveals fresh inflammation. A typical study strings together four to ten of these, with brief pauses in between while the technologist checks image quality.
That structure explains why estimates wobble. A straightforward knee scan might need five short sequences — done in half an hour. A brain study looking for something subtle may need more sequences, thinner slices, and a contrast injection partway through, pushing past the hour mark. Per the NHS, most scans land between 15 and 90 minutes depending on the area imaged and how many pictures are needed.
Then there’s everything around the scan. Safety screening takes ten minutes if your paperwork is done, longer if it isn’t. Changing into a gown, having an IV placed for contrast, getting positioned on the table with the right coil — none of it is scan time, but all of it is your time. A realistic door-to-door estimate for a routine appointment is 90 minutes to two hours. Build that into your day and the visit feels unhurried; assume 30 minutes total and you’ll spend the scan worrying about your parking meter, which is exactly the wrong headspace for lying perfectly still.
What body part takes the longest to MRI?
Cardiac MRI and multi-region spine studies usually sit at the long end. The heart is a moving target — the scanner has to sync its pictures to your heartbeat and often to your breathing, with repeated breath-holds — so 60 to 90 minutes is common. A full spine (cervical, thoracic, and lumbar imaged together) is really three scans stacked into one appointment.
| Body area | Typical scan time | Why it varies |
|---|---|---|
| Knee, shoulder, other joints | 30–45 min | Small field, fewer sequences |
| Brain | 30–60 min | Longer with contrast or detailed protocols |
| Spine (one region) | 30–45 min | Each additional region adds ~30 min |
| Abdomen or pelvis | 45–90 min | Breath-holds and motion correction add time |
| Breast | 30–60 min | Usually includes contrast |
| Heart (cardiac MRI) | 60–90 min | Images gated to heartbeat and breathing |
Two caveats keep this honest. First, protocols differ between imaging centers, so your appointment letter beats any table. Second, the estimate assumes clean images on the first pass. If you move during a sequence — a cough, a shifted leg, an involuntary swallow at the wrong moment — that sequence often gets repeated, and five minutes becomes ten. Stillness is the one variable you control, and it’s worth more than any other preparation on this list.
What's actually happening while you lie there?
No radiation, for a start. MRI works on an entirely different principle from X-rays and CT scans, and understanding it takes some of the strangeness out of the experience.
Your body is mostly water, and every water molecule carries hydrogen atoms whose protons behave like microscopic compass needles. The scanner’s main magnet — thousands of times stronger than Earth’s magnetic field — pulls those protons into alignment. Then the machine sends in pulses of radio waves, briefly knocking the protons out of line. When each pulse stops, the protons snap back, releasing tiny radio signals as they do. Protons in fat relax at a different speed than protons in fluid or muscle, and a computer translates those timing differences into remarkably detailed cross-sectional images, as MedlinePlus explains.
This is why MRI excels at soft tissue — brain, spinal cord, ligaments, organs — where X-rays see mostly shadows. It’s also why the scan takes so long: each sequence interrogates the tissue with a different pulse pattern, and physics won’t be rushed.
And it’s why the metal rules exist. The magnet is always on, even between patients. It doesn’t care whether you’re mid-scan; a ferromagnetic object in the room becomes a projectile, and certain implants can heat or malfunction. Every question on that screening form traces back to this one fact: you are about to share a room with an extraordinarily powerful magnet.
A minute-by-minute walkthrough of the appointment
Check-in looks like any medical visit until the screening form arrives — a detailed inventory of every implant, surgery, injury involving metal, and device you’ve ever had. Answer it completely; the technologist will review it with you verbally, too.
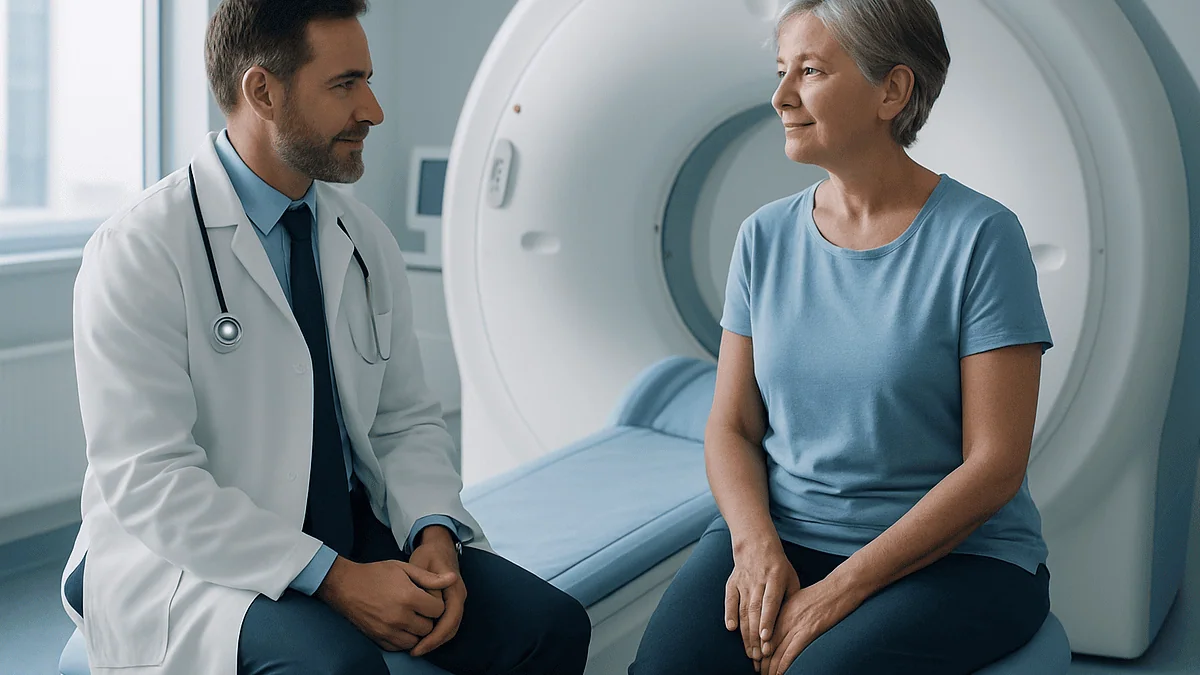
You’ll change into a gown or metal-free clothing and lock up your phone, watch, cards, and jewelry. In the scan room, you lie on a padded table, usually on your back. The technologist positions a coil — a plastic frame containing antennas — over the body part being imaged, hands you foam earplugs or headphones, and places a squeeze ball in your hand. Press it and the scan pauses; someone comes in. You are never sealed off: a microphone and speaker connect you to the control room the entire time, per the Mayo Clinic.
The table glides into the bore. Then comes the rhythm of the next half hour or more: a warning from the intercom, a burst of loud knocking or buzzing lasting one to six minutes, a pause, another sequence. Some scans include instructions — hold your breath, don’t swallow for a moment. If contrast is planned, the table slides out partway through for the injection, then back in for the final sequences.
When it ends, the table slides out, the coil comes off, and you’re free to change. There’s no recovery room, no observation period for a routine scan. Most people are back in their own clothes within five minutes.
Why is the machine so loud?
The noise is not malfunction and not optional — it’s physics doing its job audibly.
Inside the scanner, gradient coils rapidly switch electrical current on and off to vary the magnetic field across your body, which is how the machine knows where each signal comes from. But a wire carrying current inside a strong magnetic field experiences force. Switch that current hundreds of times per second and the coils physically vibrate against their mountings — hard. The result is the signature knocking, buzzing, and chirping, which can exceed 110 decibels on some sequences. For comparison, that’s the territory of a rock concert or a chainsaw at close range, which is why hearing protection is mandatory rather than a courtesy.
A few useful things follow from this:
- Different sequences make different sounds. A sudden change from knocking to a high-pitched buzz doesn’t mean something went wrong — it means a new sequence started.
- Many centers offer headphones with music piped in. It won’t drown out the loudest sequences, but it fills the silences and helps the time pass.
- Newer scanners run some “quiet” protocols that reduce noise substantially, though not to silence. Worth asking about if sound is a particular concern.
The steadiness of the rhythm becomes oddly hypnotic for some people. Plenty of patients — genuinely — fall asleep in the tube, and for most scans that’s perfectly fine, as long as you don’t shift position while drifting off.
What should you not do before an MRI?
For most scans, remarkably little. Eat normally, take your usual medications, drink your coffee — unless your appointment instructions say otherwise, and that exception matters. Some abdominal and pelvic scans require fasting for a few hours so the digestive tract stays quiet; certain cardiac protocols ask you to skip caffeine. The instructions attached to your booking always override general advice.
The genuine don’ts cluster around metal and information:
- Don’t wear metal you can avoid. Leave jewelry, watches, and hair clips at home. Choose clothing without zippers, underwires, metallic threads, or snaps — some athletic wear contains metallic microfibers, which is one reason centers prefer gowns.
- Don’t withhold anything on the screening form. An old shrapnel injury, a forgotten surgical clip, work history involving metal grinding (tiny fragments can lodge in the eyes) — all of it matters to safety, none of it is judged.
- Don’t guess about pregnancy. Tell the team if you are or might be pregnant. MRI is often still possible, but the decision belongs to your clinicians, per the Cleveland Clinic.
- Don’t arrive dehydrated if contrast is planned. A well-hydrated arm makes IV placement easier and faster.
One thing you emphatically should do: empty your bladder right before the scan. Forty-five motionless minutes is long enough without adding urgency to the experience.
Can I wear deodorant for an MRI?
Skip it — but for a more interesting reason than most people assume. Your antiperspirant is not going to fly across the room or heat up. The magnet is indifferent to it. The images are not.
Many antiperspirants contain aluminum compounds, and some cosmetics contain metallic particles. On an MRI, these can create artifacts — smudges, distortions, or signal voids in the picture. For most scans of a knee or a brain, deodorant under your arms is irrelevant. But for breast MRI, chest imaging, or anything near the underarm, those artifacts can land exactly where the radiologist is looking, potentially obscuring detail or mimicking something that isn’t there. Imaging centers ask everyone to skip it because it’s simpler than sorting scans into “matters” and “doesn’t.”
The same logic extends further than deodorant:
- Some eye makeup, particularly certain mascaras and glittery shadows, contains metallic pigments — go bare-faced if the scan involves your head.
- Hair products with shimmer or metallic content are worth skipping for brain and cervical spine imaging.
- Certain medication patches have metallic backing layers; mention any patch you wear so the team can advise whether it stays on.
If you forget and arrive fully deodorized, say so. Centers keep wipes on hand for exactly this, and it costs two minutes — far cheaper than a repeat scan because an artifact muddied the one image that mattered.
What about metal — implants, piercings, and tattoos?
The screening form exists because “metal” covers wildly different risk levels, and honesty here is a safety issue, not a formality.
Some devices historically ruled out MRI entirely — older pacemakers, certain aneurysm clips, some cochlear implants. The landscape has improved: many modern cardiac devices are “MRI-conditional,” meaning they’re safe under specific, documented conditions, sometimes requiring the device to be reprogrammed before and after the scan. That coordination takes time, which is why implants should be disclosed when the appointment is booked, not in the waiting room. Bring your implant card if you have one.
Most everyday metal is less dramatic than people fear, according to Johns Hopkins Medicine and other major sources:
- Dental fillings and crowns are fine, though they can distort images of the immediate area.
- Joint replacements and surgical screws placed in recent decades are generally MRI-safe; the team will confirm specifics.
- Most IUDs pose no problem, but mention yours so it can be verified.
- Piercings come out — they can heat, pull, and distort images.
- Tattoos rarely cause trouble; a small number of people report mild warmth or tingling in older tattoos with metallic pigments. Report any sensation immediately via the squeeze ball, and the sequence can be stopped.
The theme throughout: almost nothing automatically cancels your scan, but everything must be known in advance. Surprises are the only true enemy in an MRI suite.
Will I need contrast dye, and how much time does it add?
Roughly speaking, contrast is used when the question is about blood supply, inflammation, infection, or distinguishing one kind of tissue from another — tumors, active inflammation in joints or bowel, blood vessel anatomy. Many scans don’t need it at all; your referring clinician and the radiologist decide based on what they’re trying to answer.
When it’s used, expect the appointment to run 15 to 30 minutes longer. Here’s where the time goes:
- An IV line is placed in your arm or hand before you enter the scanner — a few minutes, similar to a blood draw.
- The scan typically runs a set of sequences without contrast first, establishing a baseline.
- The contrast is injected through the IV — you may feel brief coolness along your arm, occasionally a metallic taste — and the key sequences are repeated while the material circulates.
If you have kidney disease or reduced kidney function, tell the team beforehand; a recent blood test may be checked, because the contrast material is cleared by the kidneys, per the Mayo Clinic. Serious reactions to MRI contrast are uncommon, and mild ones — brief nausea, a headache, coolness at the injection site — usually pass quickly. Drink fluids normally afterward; no special flushing regimen is required for people with healthy kidneys.
One practical note: contrast is another reason to confirm your appointment details in advance. “With and without contrast” on the order is the difference between a 45-minute visit and a 75-minute one.
What if I'm claustrophobic? Be honest — does it help to know in advance?
Yes, enormously — because nearly every effective accommodation requires planning, and none of them are available if you first mention it while lying on the table.
Anxiety in the scanner is common enough that imaging teams have a well-worn toolkit. Depending on the scan, options can include:
- Going in feet-first. For knee, hip, or lumbar spine imaging, your head may stay near or outside the bore’s opening entirely.
- An eye mask or a washcloth over your eyes. Simple and surprisingly effective — much of the distress comes from watching the ceiling of the bore, and what you can’t see, you tend not to fixate on.
- Music through headphones, a mirror on the head coil angled toward the room, or a prism that lets you see out.
- A wide-bore or open scanner, where available and appropriate for the body part.
- A companion in the room. Many centers allow a screened friend or family member to stand nearby and rest a hand on your ankle.
- A calming medication arranged through your doctor — this must be prescribed in advance, and you’ll need someone to drive you home.
Two anchoring facts help most people: the tube is open at both ends with air moving through it, and you hold a call ball that stops everything instantly. You are monitored, audible, and in control the entire time. Slow breathing — in through the nose, long exhale — between sequences genuinely helps, and counting the sequences down gives the experience a finish line.
Do you have to rest after an MRI?
No. A routine MRI requires zero recovery time. You can drive yourself home, return to work, go to the gym, pick up the kids. The magnetic field and radio waves don’t linger in your body, deposit anything, or leave you weakened — the moment the table slides out, the scan’s physical interaction with you is over. The NHS is plain on this point: after a standard scan, you can resume normal activities immediately.
The exceptions are about what accompanied the scan, not the scan itself:
- If you were given a sedative, the rules change completely. You’ll need someone to drive you home, and you should skip driving, operating machinery, alcohol, and important decisions for the rest of the day while the medication wears off.
- If you had contrast, you may be asked to wait briefly before leaving, and nursing parents sometimes have questions — current guidance from major medical organizations supports continuing breastfeeding after standard contrast in people with normal kidney function, but ask your own care team, since your situation is theirs to assess.
- If you feel unusual afterward — dizzy, itchy, short of breath — tell staff before you leave rather than pushing through.
The lingering effect most people actually notice is muscular: mild stiffness from holding one position for 45 minutes. A stretch in the parking lot fixes it. Feeling tired afterward is usually the adrenaline of anticipation draining away — real, but not medical.
How long until you get the results?
Here’s the part nobody warns you about: the scan is the fast part. The waiting comes after.
Your images don’t get read while you dress. A radiologist — a physician who specializes in interpreting medical imaging — reviews the full study, often comparing it against any prior scans, and writes a formal report. That report goes to the clinician who ordered the test, who then interprets it in the context of your history, your exam, and your other results. The technologist who ran your scan cannot give you findings, and their friendly neutrality on the way out means nothing about what the images show. They are not allowed to interpret, and reading anything into their expression is a reliable way to ruin a week for no reason.
Typical timelines run from a couple of days to about two weeks, depending on the setting; the NHS cites a week or two as common for routine scans, while urgent studies — a suspected stroke, spinal cord compression — are read within hours. Many health systems now release reports to patient portals quickly, sometimes before your doctor has called. If you read your own report, expect dense technical language and terms like “unremarkable” (which is good news) — and hold your conclusions until someone who knows your case walks you through it.
Before you leave the imaging center, ask two questions: when will the report be ready, and how will I hear about it? Knowing the plan shrinks the wait considerably.
Open MRI vs. closed: does the machine change the timing?
Sometimes, and the tradeoff is worth understanding before you request one.
The classic closed scanner is the tube everyone pictures. Open designs vary — some are open on the sides with the magnet above and below you; “wide-bore” scanners keep the tube shape but widen the opening to roughly 70 centimeters, a difference that sounds small and feels significant. For people with claustrophobia or larger bodies, these designs can be the difference between completing a scan and abandoning one, which makes them genuinely valuable.
The physics tradeoff: image quality depends heavily on magnetic field strength, measured in teslas. Many closed scanners operate at 1.5 or 3 tesla; many fully open designs run lower. Lower field strength means weaker signal, and the machine compensates by scanning longer or accepting somewhat less detailed images. In practice, this means:
- An open scanner may take modestly longer for the same body part, or may not be recommended at all when fine detail is essential — small joint structures, certain brain protocols.
- A wide-bore scanner often splits the difference: full field strength, more breathing room, same timing as a standard closed machine.
- The right machine depends on the clinical question. Your referring clinician and the radiologist can tell you whether an open scanner would answer it adequately.
The best scan is the one that gets a diagnostic-quality answer on the first attempt. A slightly longer or slightly snugger scan you complete beats a comfortable one that has to be repeated elsewhere.
When should you talk to a doctor before — or after — your scan?
Most MRI visits are uneventful. A short list of situations deserves a conversation with your doctor or the imaging team before the appointment rather than on the day:
- You have a pacemaker, defibrillator, cochlear implant, medication pump, neurostimulator, aneurysm clip, or any implanted device — even one you believe is MRI-safe. Verification takes time and sometimes device reprogramming.
- You are pregnant, might be pregnant, or are breastfeeding.
- You have kidney disease or a history of reduced kidney function and contrast is planned.
- You’ve ever had metal fragments in your eyes or body — welders, machinists, and anyone with old shrapnel injuries may need a quick X-ray first.
- You’ve previously reacted to contrast material, or you know confinement triggers significant panic. Both are manageable with advance notice, and only with advance notice.
Afterward, contact your care team promptly if you develop hives, swelling, worsening dizziness, or trouble breathing in the hours following a contrast injection — serious reactions are rare but treatable, and speed matters. Seek emergency care for any significant breathing difficulty. Redness or soreness at the IV site that worsens rather than fades over a day or two is also worth a call.
And if two weeks pass with no word on results, don’t assume silence means good news. Reports occasionally stall in transit between systems. Call and ask. You had the scan to get an answer — make sure the answer completes its journey back to you.
Frequently asked questions
How long does an MRI take from start to finish?
The scan itself takes 15 to 90 minutes depending on the body part and whether contrast dye is used, but plan roughly 90 minutes to two hours door to door. Check-in, the metal-safety screening, changing into a gown, IV placement if contrast is needed, and positioning on the table all add time around the scan. A single joint often finishes in about 30 minutes; multi-region spine or cardiac studies run longest.
What should you not do before an MRI?
Don’t wear metal — leave jewelry, watches, and clothing with zippers or underwires at home — and don’t withhold anything on the safety screening form, including old injuries involving metal fragments. Most scans require no fasting, so eat and take medications normally unless your appointment instructions say otherwise; some abdominal scans do require an empty stomach. Tell the team about implants, possible pregnancy, and kidney problems well before scan day.
Can I wear deodorant for an MRI?
It’s best to skip it. Many antiperspirants contain aluminum compounds that can create artifacts — smudges or distortions — on the images, which matters most for breast, chest, or underarm imaging. It isn’t a magnet-safety issue; the concern is purely image quality. The same applies to metallic makeup and shimmery hair products for head scans. If you forget, tell the technologist — centers keep wipes on hand for exactly this situation.
Do you have to rest after an MRI?
No. A routine MRI requires no recovery time — you can drive home, return to work, and exercise immediately, because the magnetic field and radio waves leave nothing behind in your body. The exception is sedation: if you took a calming medication for the scan, you’ll need a driver and should rest for the remainder of the day. Mild stiffness from lying still is common and resolves with a quick stretch.
What body part takes the longest to MRI?
Cardiac MRI and multi-region spine studies typically take the longest, often 60 to 90 minutes. The heart is constantly moving, so the scanner must synchronize images to your heartbeat and use repeated breath-holds. A full spine is effectively three separate scans — cervical, thoracic, and lumbar — performed in one appointment. By contrast, a single joint like a knee or shoulder usually finishes in 30 to 45 minutes.
Does an MRI use radiation?
No. MRI uses a strong magnetic field and radio waves to create images — there is no ionizing radiation, unlike X-rays and CT scans. The scanner aligns hydrogen protons in your body’s water, nudges them with radio pulses, and reads the signals they release, translating timing differences between tissues into detailed pictures. That’s why MRI safety rules focus entirely on metal and implants rather than on radiation exposure.
Can I fall asleep during an MRI?
For many scans, yes — and some people do, lulled by the rhythmic noise. The only requirement is that you stay in the same position, so falling asleep is fine as long as you don’t shift, twitch, or roll. For scans requiring instructions — breath-holds during abdominal or cardiac imaging, for example — you’ll need to stay awake and responsive. The technologist speaks to you between sequences, which naturally keeps most people alert.
What happens if I move during the scan?
Movement blurs the images, and the affected sequence usually has to be repeated, adding five to ten minutes or more. Small involuntary motions like breathing and swallowing are expected and accounted for; the problem is shifting position, coughing fits, or fidgeting. If you need to move — an itch, a cramp, rising panic — squeeze the call ball instead of moving silently. Pausing deliberately wastes far less time than ruining a sequence.
Can I eat and drink before an MRI?
Usually yes — most MRI scans require no fasting, so eat normally and take your regular medications. The exceptions are specific: some abdominal and pelvic scans require an empty stomach for several hours so the digestive tract stays quiet, and certain cardiac protocols ask you to avoid caffeine. Your appointment instructions override general advice, so read them carefully. If contrast is planned, arriving well hydrated makes the IV placement easier.
How long does it take to get MRI results?
Typically a few days to about two weeks for routine scans, though urgent studies are read within hours. A radiologist reviews the images and writes a formal report, which goes to the clinician who ordered the test — that clinician then discusses the findings with you in context. The technologist cannot share results on the day. Before leaving, ask when the report will be ready and how you’ll be notified.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Can a CT Scan Detect Cancer? What It Shows, What It Misses and the Tests That Follow
A CT scan can detect many tumors, especially solid masses in the lungs, liver, kidneys, pancreas, bones and lymph nodes, often when they are…

The Holter Monitor: Living With a 24-48 Hour Heart Recorder
A Holter monitor is a small, portable device that records every heartbeat for 24 to 48 hours through adhesive chest electrodes. It helps doctors…
What an Echocardiogram Shows (and the Five Abnormalities It Looks for)
An echocardiogram is an ultrasound scan of the heart that shows its size, the thickness of its walls, how strongly it pumps, and whether…

Abdominal and Carotid Ultrasounds: What Each Scan Screens For
An abdominal ultrasound uses sound waves to examine the liver, gallbladder, pancreas, spleen, kidneys, and abdominal aorta, detecting problems such as gallstones, cysts, fluid…
MRCP Scan: The Non-Invasive Look at Bile Ducts That Replaced Diagnostic ERCP
An MRCP (magnetic resonance cholangiopancreatography) test is a non-invasive MRI scan that creates detailed pictures of the bile ducts, gallbladder, and pancreatic duct without…

Neurophysiology Tests: EMG, EEG and Nerve Conduction in Plain Language
Neurophysiology tests measure the electrical activity of nerves, muscles, and the brain. An EMG records signals inside muscle, a nerve conduction study times impulses…