

Tympanoplasty vs Myringoplasty: Which Eardrum Repair Do You Need?

Key Takeaways
- Myringoplasty closes the eardrum hole only, while tympanoplasty also inspects the middle ear and rebuilds the hearing bones if they are damaged.
- A type I tympanoplasty and a myringoplasty often describe nearly the same operation, and the label varies by country and surgeon more than by technique.
- The NHS and Mayo Clinic report that most eardrum perforations heal on their own within a few weeks, so fresh tears are usually watched rather than operated on.
- Cleveland Clinic quotes a typical tympanoplasty operating time of around two to three hours, usually as a same-day procedure, with grafts taken from the patient's own fascia or cartilage.
- Mastoidectomy is a separate operation on the bone behind the ear, added mainly when cholesteatoma or chronic infection has spread beyond the middle ear.
- Hearing after repair can improve, stay the same or occasionally worsen, and the pre-operative audiogram is the best guide to how much the perforation explains.
Myringoplasty repairs only the torn eardrum membrane, usually with a small graft of the patient's own tissue. Tympanoplasty repairs the eardrum and also lets the surgeon look into the middle ear and, if needed, rebuild the tiny hearing bones behind it. Which one you need depends on whether the perforation is the only problem or whether infection, scarring or damaged bones are involved; your ENT team decides after examination and hearing tests.
The consent form lands on the kitchen table with two words circled on it. One is tympanoplasty. The other, a few lines down, is myringoplasty. Your surgeon used both in the clinic, almost interchangeably, and you nodded along because it was hard to ask a question while someone was peering into your ear with a microscope. Now the house is quiet and the difference suddenly seems to matter a great deal.
The tympanoplasty vs myringoplasty question comes up more than you might think, and not only from patients. Surgeons in different countries use the terms slightly differently, textbooks group them into numbered types, and online explanations tend to either oversimplify or drown the reader in Latin. The honest version sits somewhere in between: both are operations to close a hole in the eardrum, but one of them stops there and the other keeps going.
Understanding where that line falls will make your next appointment far more useful, because the decision about which repair suits your ear belongs to the team that has actually examined it.
Tympanoplasty vs myringoplasty: what the two words actually mean
Start with the anatomy, because the names are built from it. The tympanic membrane is the medical term for the eardrum: a thin, three-layered sheet of tissue roughly the size of a fingernail that separates the ear canal from the middle ear. The Greek root myringa also means eardrum, which is why two words that sound so different point at the same structure.
A myringoplasty is the simpler of the two. The surgeon closes a perforation, a hole or tear in the eardrum, by placing a graft over or under the defect and leaves the middle ear itself alone. Nothing behind the membrane is inspected or rebuilt. Think of it as patching a torn drumhead without opening up the drum.
A tympanoplasty repairs the eardrum too, but the definition includes the middle ear. The surgeon lifts the membrane, examines the space behind it, and if the three tiny hearing bones (the ossicles: malleus, incus and stapes) are eroded, fixed or missing, reconstructs the chain so sound can travel to the inner ear again. The operation is graded by how much of that chain needs work, in a system often described as types I through V, where type I involves an intact bone chain and higher numbers mean progressively more reconstruction.
Here is where the confusion begins. A type I tympanoplasty and a myringoplasty both end with a repaired eardrum and untouched hearing bones. Many surgeons, particularly in the United States, use “tympanoplasty” as the umbrella term for any eardrum repair; others reserve “myringoplasty” for repairs that never enter the middle ear at all. When your surgeon writes one word rather than the other, they may be describing a different technique, or simply following local habit. The way to find out is to ask exactly what will be examined and what will be repaired, which is a question worth taking to the clinic in writing.
How does a torn eardrum heal on its own, and when does it stop healing?
The eardrum is a remarkably self-repairing structure. Its outer layer is skin, and like skin elsewhere it migrates and regrows. According to the NHS, most perforations caused by infection, pressure changes or minor injury close on their own within a few weeks, though some take a few months, and the usual advice during that time is to keep the ear dry and avoid pushing anything into it. Mayo Clinic gives the same picture: the majority of ruptured eardrums heal without treatment, and surgery is generally considered only when healing stalls.

Why would healing stall? Several things get in the way. Repeated or persistent infection keeps the edges of the hole inflamed rather than knitting. A very large perforation, or one at the rim of the membrane, leaves too little scaffold for new tissue to bridge. Chronic middle-ear disease can cause the skin layer to grow inward around the edges, sealing the hole open rather than closed. And a eustachian tube (the narrow passage that equalizes pressure between the middle ear and the back of the nose) that never works well leaves the middle ear chronically under pressure, which discourages closure.
When a perforation has been present for months with no sign of shrinking, clinicians describe it as chronic, and that is the point at which the tympanoplasty vs myringoplasty conversation typically begins. Before any operation, an ENT specialist will usually examine the ear under a microscope, measure hearing with an audiogram (a formal hearing test that plots the quietest sounds you can detect at each pitch), and often arrange a CT scan if there is any suspicion of disease in the middle ear or the mastoid bone behind it. Those findings, not the size of the hole alone, steer the choice of repair. A clean, dry, medium-sized hole with normal hearing bones is a very different starting point from a wet, foul-smelling ear with a large hearing loss, even if both are technically “a perforation.”
What actually happens during a myringoplasty?
Picture the operating microscope swinging over your ear. Most myringoplasties are done under general anesthesia, though some smaller repairs can be performed under local anesthesia with sedation, a decision made by the anesthetic team based on the approach and your health. The surgeon reaches the eardrum either through the ear canal itself or through a small cut in the fold of skin behind the ear.
The first task is to prepare the edges of the hole. Chronic perforations develop a rim of stable, non-growing tissue, and the surgeon gently roughens or trims this edge so it will accept a graft. Then comes the graft itself. The most commonly used materials are the patient’s own tissue: a thin sheet of temporalis fascia (the fibrous covering of the chewing muscle above the ear), perichondrium (the lining of cartilage), or a sliver of cartilage from the tragus, the small flap in front of the ear canal. Cleveland Clinic lists these as the standard options, and each has trade-offs. Fascia is thin and vibrates freely; cartilage is stiffer and resists collapse when the middle ear pressure is poor.
The graft is laid across the hole, usually tucked under the remaining eardrum in what surgeons call an underlay technique, or placed on top in an overlay. Absorbable packing material is then placed on both sides to hold everything still while the eardrum grows onto the graft over the following weeks. The packing dissolves or is removed at a follow-up visit.
What makes this a myringoplasty rather than a tympanoplasty is what the surgeon does not do. The eardrum is not lifted as a flap to explore the middle ear, and the hearing bones are not touched. That keeps the operation shorter and the recovery generally simpler, but it also means the surgeon is relying on pre-operative tests to be confident that nothing behind the membrane needs attention. If the middle ear is wet, scarred or suspicious on the scan, most teams will plan the fuller operation from the start.
What actually happens during a tympanoplasty?
A tympanoplasty begins the same way, with the microscope, the anesthetic and the approach through the canal or from behind the ear. The difference is that the surgeon raises the eardrum, or what remains of it, as a hinged flap and looks directly into the middle ear.
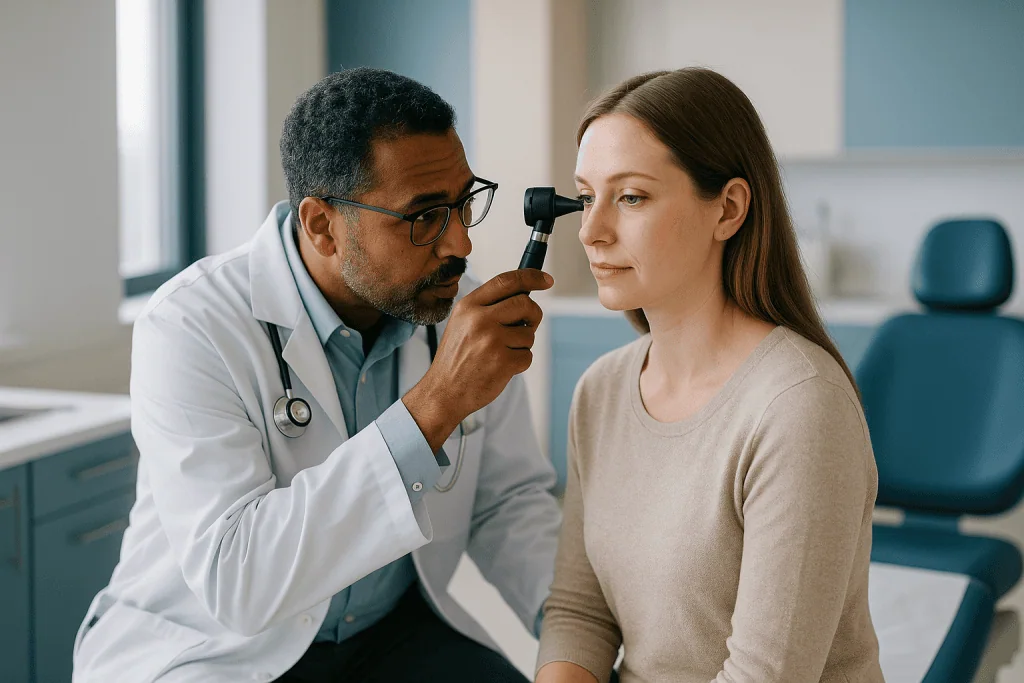
This is the diagnostic heart of the operation. Under magnification the surgeon checks the three hearing bones for erosion, checks whether they move freely, and looks for scar tissue, retained infection or a cholesteatoma, an abnormal collection of skin cells that can grow in the middle ear and slowly damage bone. The NHS describes cholesteatoma as a condition that needs surgical removal because it does not resolve on its own and can erode the structures around it. Finding one changes the plan considerably.
If the bones are intact and mobile, the surgeon repairs the eardrum with a graft, and the result is a type I tympanoplasty, functionally close to a myringoplasty. If the incus, the middle of the three bones, has been eaten away, the surgeon may bridge the gap with a reshaped piece of the patient’s own bone or cartilage or with a small prosthesis made from biocompatible material, restoring the connection between eardrum and inner ear. The more of the chain that needs rebuilding, the higher the numbered type.
Once the middle ear work is done, the graft is placed and packed exactly as in a myringoplasty. Cleveland Clinic gives a commonly quoted operating time of around two to three hours for tympanoplasty, and notes that it is usually performed as a day-case procedure, though the exact duration depends on what is found and whether the ossicular chain is reconstructed. Because the operation involves the hearing mechanism itself, hearing results are not judged on the day; the ear needs the graft to heal and the packing to clear before an audiogram means anything, which is why the first meaningful hearing test is typically scheduled weeks after surgery.
Myringoplasty vs type 1 tympanoplasty: why surgeons argue over the label
If you search for a clear dividing line between these two you will find surgeons disagreeing with each other, and that disagreement is genuine rather than sloppy. The classical definition says a myringoplasty repairs the eardrum without entering the middle ear, while a type I tympanoplasty repairs the eardrum after lifting it to inspect an intact bone chain. In practice, though, many surgeons who perform an “underlay myringoplasty” do lift the edge of the membrane to slide the graft beneath it, which technically means they have looked into the middle ear.
So the boundary is blurred by technique. It is also blurred by geography. In much of North America, “tympanoplasty” has become the default word for any eardrum grafting, and the term myringoplasty is used mostly for very minor procedures such as placing a paper or gel patch over a small fresh hole. In parts of Europe, Asia and Australasia, myringoplasty remains the standard name for the full graft operation on an otherwise healthy middle ear, with tympanoplasty reserved for cases that involve bone work.
Does the naming matter to you as a patient? It matters in three practical ways. First, the name on your paperwork may drive how the anesthetic and recovery are planned, so it is reasonable to ask which technique and which approach are intended. Second, if you read about outcomes online, studies comparing “myringoplasty” with “type I tympanoplasty” are often comparing very similar operations under different labels, which is why their results tend to look alike. Third, and most important, the label tells you nothing about the thing that actually shapes your recovery and hearing prospects: the condition of your middle ear. A dry, uninfected ear with normal bones is favorable ground whichever word the surgeon prefers. A wet ear with erosion is harder work whatever it is called. Ask about your ear, not about the word.
Tympanoplasty vs myringoplasty at a glance
Sometimes the clearest way to see two procedures is side by side. The table below summarizes the typical distinctions as they are usually described in mainstream patient information; individual surgeons adapt every element to the ear in front of them, so treat this as orientation rather than a contract.
| Feature | Myringoplasty | Tympanoplasty |
|---|---|---|
| What is repaired | The eardrum only | The eardrum plus, if needed, the middle-ear hearing bones |
| Middle ear inspected | Not as a deliberate step | Yes, the eardrum is lifted to examine the space behind it |
| Hearing bones reconstructed | No | Possibly, depending on findings (types II to V) |
| Typical candidate | Chronic dry perforation, normal bones, hearing loss explained by the hole alone | Perforation with suspected bone damage, scarring, retraction or cholesteatoma |
| Graft material | Own fascia, perichondrium or cartilage | Same, plus bone or a prosthesis for the ossicles when required |
| Usual anesthetic | General or local with sedation | Usually general |
| Reported operating time | Generally shorter | Around two to three hours per Cleveland Clinic, longer with reconstruction |
| Main goals | Close the hole, allow swimming and bathing, reduce infections | Close the hole, remove disease, restore sound transmission |
Two rows deserve a second look. The “typical candidate” line explains why the question in the title cannot be answered by the size of your perforation alone; it is answered by what the audiogram, examination and any scan reveal about the space behind it. And the “main goals” line shows something patients often miss: closing the hole is only part of the point. A dry, sealed ear that can be dunked in a bath without a week of infection afterward is, for many people, the larger quality-of-life gain, and both operations aim for it.
Who is usually offered eardrum repair, and who is usually asked to wait?
Surgeons are generally more interested in what an ear has been doing over the past year than in what it looks like on a single afternoon. A perforation that has been present and unchanged for months, with an ear that is dry and free of discharge, is the classic situation in which a myringoplasty or type I tympanoplasty is discussed. Reasons to offer repair usually include repeated infections whenever water gets in, a hearing loss that the audiogram attributes to the hole, a wish to swim or bathe freely, or a need to protect the middle ear in someone whose work or hobbies involve water.
The fuller tympanoplasty tends to be proposed when the story includes persistent discharge that does not settle, a hearing loss larger than the perforation can explain, a retraction pocket (part of the eardrum sucked inward into the middle ear), or imaging or examination that suggests cholesteatoma. In that last situation the operation is not really elective in the ordinary sense, because untreated cholesteatoma can gradually erode bone and, per the NHS, may lead to complications affecting balance, the facial nerve or hearing.
Who is asked to wait? Fresh perforations, first. Mayo Clinic and the NHS both describe a period of watchful waiting with the ear kept dry, because most acute tears close on their own and operating on a hole that would have healed anyway exposes a patient to surgical risk for no gain. An actively infected ear is usually treated first, since grafts placed into wet, inflamed tissue are more likely to fail; this is the context in which a clinician may prescribe topical antibiotic drops, which work by delivering the drug directly to the lining of the middle ear, with all decisions about their use left to the prescribing team.
Children are a special case. Many ENT teams prefer to wait until the eustachian tube has matured and the child has grown out of the years of frequent colds and ear infections, because operating too early risks a repaired eardrum being pushed open again by the next episode of middle-ear fluid. The timing is individual, and the pediatric team weighs hearing, speech development and infection frequency before recommending a date.
Is tympanoplasty a major surgery? Is myringoplasty?
The honest answer is that “major” is not a category surgeons formally use, but the question behind it is fair: how much is this going to ask of my body? By most practical measures, both operations sit in the middle of the spectrum. They are delicate rather than large. The incision, if there is one behind the ear, is short. Blood loss is small. Cleveland Clinic describes tympanoplasty as a procedure that is typically done as an outpatient, meaning you go home the same day, and the same is true of myringoplasty in most settings.
What makes them feel significant is the anesthetic and the microscope work. A general anesthetic is a general anesthetic, whatever the operation, and your anesthetist will assess your heart, lungs, medicines and previous reactions in the same way they would for anything else. The operation itself is performed under high magnification on structures measured in millimeters, which is why it takes the two to three hours that Cleveland Clinic quotes for tympanoplasty rather than the few minutes a lay person might expect for “patching a hole.” Myringoplasty without middle-ear work is generally quicker, though your surgeon is the only person who can estimate your specific case.
The recovery is also middle-of-the-road. You will not be immobilized, but you will be asked to protect the ear from water, pressure and heavy exertion for several weeks while the graft takes, and to expect a blocked, muffled sensation from the packing until it clears. Compared with, say, a joint replacement or abdominal surgery, the physical toll is modest; compared with a tooth filling, it is considerably more.
So when people ask whether myringoplasty or tympanoplasty is major surgery, a reasonable framing is this: it is a real operation under a real anesthetic on a delicate organ, with real though uncommon risks, and it deserves the same preparation and follow-up as any surgery. It is not, for most healthy patients, an operation that involves a hospital stay or a long period off your feet.
Tympanoplasty vs mastoidectomy: a different job entirely
A third word often appears on the same consent form, and it confuses people because it sounds like a synonym. It is not. A mastoidectomy is an operation on the mastoid bone, the honeycombed part of the skull you can feel as a bump behind your ear. That bone contains air cells that connect to the middle ear, and when chronic infection or cholesteatoma spreads into them, the surgeon drills them open to clear the disease.
Tympanoplasty, by contrast, is about the eardrum and the hearing bones. The two procedures address neighboring spaces, and they are frequently combined in a single operation, sometimes written as “tympanomastoidectomy” or “tympanoplasty with mastoidectomy.” When that happens, the mastoid part removes disease and the tympanoplasty part reconstructs the hearing mechanism and seals the ear.
Why would a surgeon add a mastoidectomy? The most common reason is cholesteatoma that has extended beyond the middle ear, which the NHS notes generally requires surgical removal to prevent it from damaging surrounding structures. Other reasons include chronic infection that keeps draining despite treatment, or the need to create better airflow behind a repaired eardrum. Mastoid surgery involves more bone work, a longer operation and often a longer recovery, and it carries its own considerations, including the possibility of a cavity behind the ear that needs periodic cleaning if the surgeon chooses a technique that removes the back wall of the ear canal.
The practical point for a patient is simple: if your paperwork mentions mastoidectomy, you are not facing a variation on myringoplasty. You are facing a two-part operation, and it is reasonable to ask the surgeon to walk you through each part separately, what it aims to achieve, and how it changes the days and weeks afterward. A myringoplasty for a clean dry hole and a tympanomastoidectomy for cholesteatoma share a graft and a microscope and almost nothing else.
What are the risks, and what are the alternatives to surgery?
Every operation on the ear carries risks that are uncommon but worth understanding before you sign. Cleveland Clinic and Mayo Clinic list the main ones for eardrum repair, and they fall into a few groups.
- Graft failure. The new tissue may not take, leaving a residual or recurrent perforation that sometimes requires a second procedure. Wet or infected ears, large perforations and poor eustachian tube function make this more likely.
- Hearing changes. Most patients hope for improvement, but hearing can also stay the same or, rarely, worsen, including a small risk of inner-ear damage that is permanent.
- Tinnitus and dizziness. Ringing or imbalance can appear or change after surgery; they usually settle but occasionally persist.
- Taste disturbance. A nerve carrying taste from one side of the tongue runs through the middle ear and can be stretched or cut, producing a metallic taste or numbness that is often temporary.
- Facial nerve injury. The nerve that moves the face passes close to the operative field. Injury is rare, and surgeons take specific steps to protect it, but it is on every consent form for a reason.
- Infection and bleeding, as with any surgery.
Alternatives depend on the ear. For a small, recent perforation, watching and waiting with the ear kept dry is the standard first approach, per both the NHS and Mayo Clinic. For a small persistent hole, some clinicians offer an office-based patch procedure, in which the edges are freshened and a paper or gel patch placed to encourage closure; Mayo Clinic describes this as an option that may be tried before formal surgery, sometimes more than once. For someone whose main concern is hearing rather than infection, a hearing aid is a legitimate alternative that avoids surgery altogether. And for a person who simply lives comfortably with a dry perforation, using earplugs for bathing and swimming, not operating at all is a perfectly reasonable choice. The comparison of these paths for your particular ear is a conversation for your treating team, who can weigh what you want against what the examination shows.
Eardrum repair surgery recovery time: what the first weeks usually look like
The first thing most people notice on waking is that the operated ear is blocked. That is the packing, not a failed graft, and it is meant to be there. Hearing on that side will be muffled, sounds may echo, and there may be a dull ache that responds to the pain relief your team advises. If an incision was made behind the ear, it will be dressed, and you may go home with a head bandage that comes off within a day or so.
The days that follow are quiet by design. Cleveland Clinic and Mayo Clinic describe a recovery in which the ear must be kept completely dry, nose-blowing is avoided or done very gently with the mouth open, sneezing is done with the mouth open, and heavy lifting, straining and vigorous exercise are paused because they raise pressure in the middle ear and can shift the graft. Air travel and swimming are typically off the table until the surgeon confirms the eardrum has healed. A small amount of blood-tinged drainage from the canal in the first days is common; a lot, or anything foul-smelling, is not.
Around one to two weeks in, most patients have a first follow-up at which the outer packing is checked or removed. Hearing often improves noticeably at that point simply because the canal is clearer, but it is not yet the final result. Cleveland Clinic notes that the graft continues to heal over several weeks and that full recovery can take a few months, with the definitive audiogram scheduled once the ear is dry and the packing has fully cleared. Mayo Clinic gives a similar picture for healing after surgical repair.
Return to desk work is often possible within a week or two, depending on how you feel and what your surgeon advises; physically demanding jobs take longer. The tympanoplasty vs myringoplasty distinction matters here too, in that a repair involving bone reconstruction generally comes with a slower, more cautious timeline than a simple graft. Every one of these ranges is typical rather than promised, and your team’s specific instructions override anything written here.
What people often get wrong about eardrum repair
Some beliefs about these operations travel from patient to patient with remarkable persistence, and several of them are wrong in ways that affect decisions.
“Once the hole is closed, my hearing will be normal.” Closing a perforation removes one cause of hearing loss, but the audiogram before surgery is what tells you how much of your loss the hole explains. Inner-ear hearing loss from age, noise or infection is not changed by repairing the eardrum, and Cleveland Clinic is clear that hearing may improve, stay the same or occasionally worsen. Ask your team what the pre-operative test suggests.
“A bigger operation means a better result.” A tympanoplasty with bone reconstruction is not an upgrade on a myringoplasty. It is a response to a different problem. Doing more in a middle ear that does not need it adds risk without benefit, which is exactly why surgeons examine, test and sometimes scan before choosing.
“Kids should have it done as soon as possible.” Many pediatric teams deliberately wait until a child has grown past the peak years of ear infections and the eustachian tube functions better, because a repaired eardrum in a young child with frequent middle-ear fluid is at higher risk of reopening. The right timing is individual.
“The graft is a piece of plastic.” The standard grafts are the patient’s own fascia, perichondrium or cartilage, harvested through the same incision. Synthetic material is generally reserved for reconstructing the hearing bones, not the membrane.
“If it fails, that was the only chance.” Graft failure is disappointing but not final; repeat repairs are performed, sometimes with a different graft material or approach.
“Any perforation should be operated on.” The NHS and Mayo Clinic both describe most perforations closing on their own within weeks, and some chronic ones are lived with comfortably using water precautions. Surgery is one option among several, chosen with your team.
Questions to ask your care team before eardrum surgery
The most productive pre-operative consultations happen when patients arrive with specific questions rather than a general sense of worry. These are the ones that tend to unlock the clearest answers for tympanoplasty and myringoplasty.
- Which operation are you planning for my ear, and in plain terms, what will you examine and what will you repair?
- Do you expect my hearing bones to need reconstruction, and what would change your mind during the operation?
- What does my hearing test suggest about how much of my hearing loss the perforation explains?
- Will the approach be through the ear canal or through an incision behind the ear, and why?
- Which graft material do you intend to use, and where will it be taken from?
- Is a mastoidectomy part of the plan, and if so, what does that add to the operation and the recovery?
- What are the specific risks in my case, given the state of my middle ear, and how likely is the graft to take?
- What would you do if I chose not to have surgery, and what would that mean for infections, hearing and water exposure?
- How long should I expect to be off work, and when can I fly, swim and exercise again?
- What symptoms after surgery should prompt me to call the clinic straight away rather than wait for follow-up?
- When will the first hearing test after surgery be, and when will we know the final result?
Write the answers down or bring someone to listen with you. Anesthetic and the strangeness of a consultation room make details slippery, and the answer to the very first question, what exactly will be repaired, is the one that resolves the tympanoplasty vs myringoplasty puzzle for your own ear. If any answer is unclear, ask the surgeon to draw it. Most will happily sketch an eardrum, a graft and three tiny bones on the back of a leaflet, and the drawing often explains more than the terminology ever could.
When to call your doctor after eardrum repair
Most recoveries are uneventful, but a few signs mean the ear should be looked at promptly rather than at the next scheduled visit. Mayo Clinic and Cleveland Clinic list the warning features to watch for after eardrum surgery, and they are worth pinning to the fridge.
Call your surgical team or seek urgent care the same day if you notice any of the following:
- Fever, or increasing pain that is not controlled by the pain relief you were advised to use.
- Heavy bleeding from the ear canal, or discharge that becomes thick, yellow-green or foul-smelling.
- Sudden or severe dizziness, spinning sensation or vomiting, particularly if it is new or worsening rather than settling.
- Sudden drop in hearing on the operated side after an initial improvement, or a new loud tinnitus.
- Any weakness or drooping of the face on the operated side, difficulty closing the eye or smiling evenly. This needs same-day assessment.
- Redness, swelling or opening of the incision behind the ear, or a spreading warm area of skin.
- Severe headache, stiff neck or confusion, which are rare but can signal infection spreading toward the lining of the brain and require emergency care.
Before surgery, the same principle applies to a perforated eardrum that has not yet been treated. The NHS advises seeing a doctor if an ear perforation is accompanied by persistent discharge, worsening hearing, spinning dizziness or if the symptoms have not started to settle within a few weeks, and seeking urgent help if there is a high temperature, severe pain or facial weakness.
None of these signs should be waited out to see if they improve overnight. Ear surgery sits close to the facial nerve, the balance organ and the inner ear, and the difference between a good and a poor outcome for a complication is often how quickly it is examined. Your treating team would far rather hear from you about something that turns out to be nothing than miss something that mattered, and every decision about what to do next, from a simple change in drops to a return to theatre, belongs with them.
Frequently asked questions
What is the difference between tympanoplasty and mastoidectomy?
Tympanoplasty repairs the eardrum and, when needed, the tiny hearing bones behind it, while mastoidectomy removes infected bone or cholesteatoma from the mastoid, the bony bump behind the ear. They address neighboring spaces and are often combined in one operation when disease has spread beyond the middle ear. Mastoid surgery involves more bone work and usually a longer recovery, so ask your surgeon to explain each part separately if both appear on your consent form.
Is tympanoplasty considered a major surgery?
It is a genuine operation under general anesthesia on delicate structures, but it is usually done as a same-day procedure without an overnight stay, according to Cleveland Clinic. The physical demand is modest compared with abdominal or joint surgery, yet the risks to hearing, balance, taste and the facial nerve are real though uncommon. Treat it with the preparation and follow-up any surgery deserves, and discuss your individual risk with the anesthetic and surgical team.
Is myringoplasty a major surgery?
Myringoplasty is generally considered a smaller procedure than tympanoplasty because it repairs the eardrum without exploring the middle ear or touching the hearing bones. It may be done under general anesthesia or under local anesthesia with sedation, and most patients go home the same day. It still requires several weeks of protecting the ear from water and pressure while the graft heals, and it carries the same core risks as any ear operation, including graft failure and hearing change.
How many hours is tympanoplasty surgery?
Cleveland Clinic gives a typical operating time of around two to three hours for tympanoplasty. The actual duration depends on the approach, whether the hearing bones need reconstruction and whether a mastoidectomy is added, so an operation involving cholesteatoma removal can run longer. A myringoplasty without middle-ear work is usually shorter. Your surgeon can give an estimate for your specific ear, and the anesthetic and recovery time in the unit add to the overall day.
What is the difference between myringoplasty vs type 1 tympanoplasty?
Both repair the eardrum with a graft and leave the hearing bones untouched, so the end result is very similar. Classically, myringoplasty means the middle ear is not entered, while type I tympanoplasty means the eardrum is lifted to inspect an intact bone chain before grafting. In practice many surgeons use the terms interchangeably, and usage varies by country. The condition of your middle ear matters far more to your outcome than which label appears on the form.
How long is eardrum repair surgery recovery time?
Cleveland Clinic describes a recovery in which the outer packing is checked within the first weeks, the graft heals over several weeks, and full recovery can take a few months, with the definitive hearing test done once the ear is dry. Desk work is often possible within a week or two, while swimming, flying and strenuous exercise wait for the surgeon’s clearance. Repairs involving bone reconstruction generally follow a slower, more cautious timeline. These are typical ranges, not promises.
Will my hearing return to normal after tympanoplasty or myringoplasty?
Not necessarily, and no surgeon can promise it. Closing the perforation removes one cause of hearing loss, but any inner-ear loss from age, noise or past infection is not changed by repairing the membrane. Cleveland Clinic notes that hearing can improve, stay the same or occasionally worsen after surgery. Your pre-operative audiogram is the best indicator of how much of your loss the hole explains, so ask your team to walk you through it.
Can a perforated eardrum heal without surgery?
Yes, in most cases. The NHS states that a perforated eardrum usually heals on its own within a few weeks, sometimes taking a few months, and Mayo Clinic gives the same picture. During healing the ear should be kept dry and nothing inserted into it. Surgery is generally considered only when a perforation persists for months, causes repeated infections or comes with hearing loss or middle-ear disease that will not settle on its own.
What graft material is used to repair the eardrum?
The most common grafts are the patient’s own tissue: temporalis fascia, the fibrous covering of the muscle above the ear; perichondrium, the lining of cartilage; or a thin piece of cartilage from the tragus, the small flap in front of the ear canal. Cleveland Clinic lists these as standard options. Fascia is thin and vibrates freely, while cartilage is stiffer and resists collapse in ears with poor pressure regulation. Synthetic material is mainly used for rebuilding the hearing bones, not the membrane.
Is eardrum repair surgery done in children, and when?
Yes, but timing is individual. Many pediatric ENT teams prefer to wait until a child has grown past the peak years of ear infections and the eustachian tube works more reliably, because a repaired eardrum in a young child with frequent middle-ear fluid is more likely to reopen. The team weighs hearing, speech development, infection frequency and the condition of the other ear before recommending a date. Preparation and comfort planning are discussed with parents in advance.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

From Surgery to Switch-On: The Cochlear Implant Activation Timeline and Early Sound Mapping
After cochlear implant surgery, the device is usually switched on at a first programming visit a few weeks later, commonly around two to four…

Recurrent Sinusitis and Daily Life: Irritants, Fluids and Habits Your ENT Will Ask About
For recurrent sinusitis, the most useful things to avoid are inhaled irritants such as tobacco smoke and strong fumes, prolonged use of decongestant nasal…

Ear Tube Surgery Step by Step: What Happens in the Operating Room and How Long It Takes
Ear tube surgery (myringotomy with tympanostomy tube placement) is one of the shortest common operations. The procedure itself usually takes about 15 minutes per…
How Do ENT Specialists Find the Cause of Vertigo? Timing, Triggers and Hearing Clues
Vertigo is diagnosed mainly through a careful history and a hands-on examination rather than a single test. Clinicians ask how long spells last, what…

Earwax Build Up With Hearing Aids or a Perforated Eardrum: Why Removal Needs an ENT
If you wear hearing aids or have a perforated eardrum, earwax removal is usually best done by an ENT clinician or trained ear specialist…

Stapedectomy Surgery Explained: How a Tiny Prosthesis Replaces the Fixed Stapes Bone
A stapedectomy treats hearing loss from otosclerosis, a condition in which the stapes, the smallest bone in the middle ear, becomes fixed and cannot…