

What a Microdermabrasion Session Involves: Crystals or Diamond Tip, Suction and Timing

Key Takeaways
- Microdermabrasion removes the stratum corneum, the dead outermost layer, and does not reach the dermis where deep wrinkles and pitted scars live.
- Crystal systems blast and vacuum aluminum oxide particles, while diamond tips rely on a coated wand and operator pressure; neither has shown clearly superior results.
- Suction, not the abrasive, is what causes most pinkness and pinpoint bruising, which is why settings are lowered around the eyes and neck.
- A facial session typically takes about 30 to 40 minutes, with redness usually fading within a day, according to Cleveland Clinic.
- Active acne, cold sores, recent isotretinoin, fresh peels and sunburn are standard reasons to postpone, and any changing skin spot should be examined first.
- Results are temporary because normal cell turnover replaces the treated layer, so maintenance and daily broad-spectrum sunscreen are part of the deal.
A microdermabrasion procedure uses either a stream of fine crystals or a diamond-coated wand, combined with gentle vacuum suction, to lift away the outermost layer of dead skin cells. A clinician cleans the face, passes the handpiece across the skin in overlapping strokes, then applies moisturizer and sunscreen. One session typically takes about 30 to 40 minutes, with little or no downtime.
The appointment reminder arrives, and with it a small question that was not there when she booked: crystals or diamond tip? The receptionist mentioned both as if everyone already knew the difference. She did not, and a quick search produced more adjectives than answers.
That gap is worth closing, because a microdermabrasion procedure is one of the most common skin treatments offered in aesthetic settings, and also one of the most casually described. People hear “exfoliation” and picture a scrub. What actually happens involves a vacuum, a controlled abrasive surface, a fairly precise depth of skin, and a clock.
This explainer walks through each of those parts in order: what the device removes, how the two handpiece types differ, why the suction setting matters more than most people realize, how long a session and a course usually run, and which signs afterward mean a call to your clinician rather than another day of moisturizer.
What a microdermabrasion procedure actually does to the skin
Think of the skin as a wall built in layers. The outermost layer, the stratum corneum, is a sheet of flattened, dead cells that the body sheds and replaces on its own, roughly every few weeks in young adults and more slowly with age. Microdermabrasion is a mechanical way of hurrying that shedding along. It removes some or most of the stratum corneum and, at higher settings, may reach the upper edge of the living epidermis just beneath it. It does not reach the dermis, the deeper layer where collagen, blood vessels and scar tissue sit.
That depth is the whole story. Because the treatment stays superficial, it carries little bleeding risk, needs no anesthetic, and heals quickly. For the same reason, it cannot do what deeper resurfacing does. The Mayo Clinic’s description of dermabrasion, the surgical cousin of this treatment, makes the contrast plain: dermabrasion is performed under anesthesia, removes skin down into the dermis, and takes weeks to heal, precisely because it is treating problems that live deeper than the surface.
Two things happen after the top layer is lifted. First, light reflects more evenly off the smoother surface, which is why skin often looks brighter the same day. Second, the mild injury signals the epidermis to produce new cells, and some laboratory studies have measured modest, short-lived changes in the upper dermis after repeated sessions. Whether those changes translate into visible, lasting improvement is where the evidence becomes thin, and later sections return to that honestly.
The practical point for anyone booking a session: this is a surface treatment, chosen for texture, dullness and mild unevenness, not a repair tool for deep lines or pitted scars.
What are the steps for microdermabrasion, from cleanse to sunscreen?
People searching “what are the steps for microdermabrasion” usually want the sequence in the room, so here it is in the order most clinics follow.
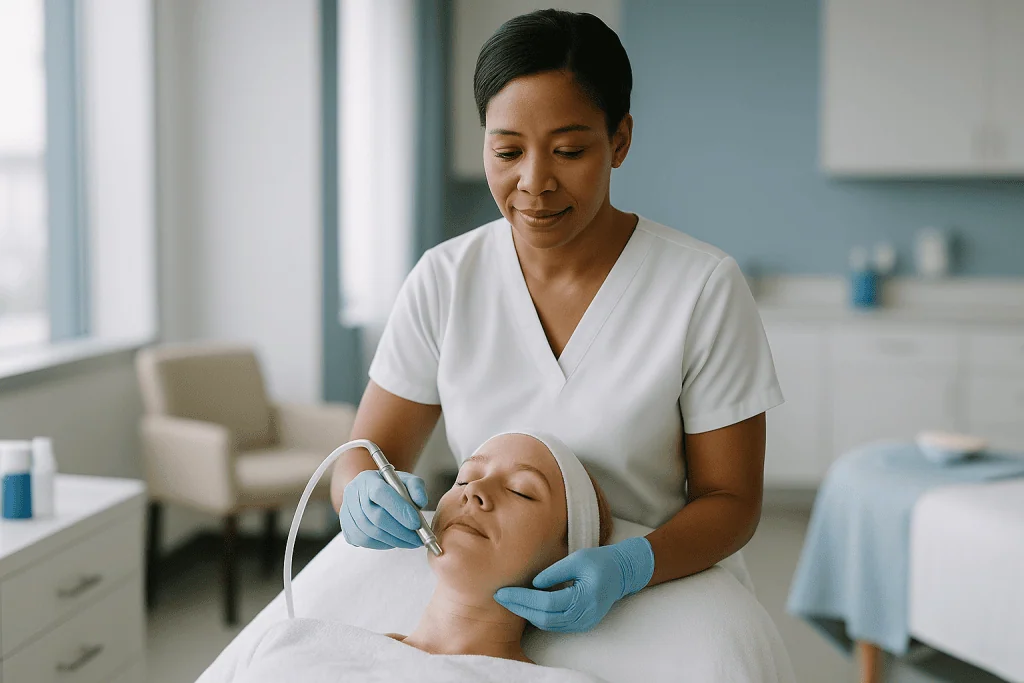
- Consultation and skin check. The clinician asks about recent retinoid use, acne medication, cold sores, chemical peels, waxing and sun exposure, then looks at the skin for active breakouts, open areas or rashes that would mean postponing.
- Cleansing and degreasing. Makeup, sunscreen and surface oil are removed so the abrasive surface meets dry skin evenly. Oil left behind makes the suction grip inconsistently.
- Eye protection. Goggles or pads cover the eyes, especially with crystal devices, where stray particles are a real concern.
- Test pass. Many practitioners do a short stroke on the jawline or forehead to confirm the suction level is tolerable.
- Treatment passes. The handpiece moves in overlapping strokes, typically horizontal then vertical, section by section. Thicker areas such as the forehead and chin may receive more passes than the thinner skin near the eyes.
- Removal of debris. Residual crystals or skin cells are wiped or vacuumed away.
- Calming and protection. A soothing moisturizer goes on, followed by a broad-spectrum sunscreen, because the freshly exposed layer burns more easily.
The order is not ceremonial. Skipping the degreasing step, for example, is one reason some people report patchy results, and skipping the test pass is how a first-timer ends up with unexpected bruising along the cheekbone. Cleveland Clinic’s overview describes the same broad sequence and notes that the treatment is normally done without numbing, since most people describe the sensation as a scratchy, pulling feeling rather than pain.
Crystals or diamond tip: what is the difference, and does it matter?
The two main device types reach the same goal by different routes.
Crystal microdermabrasion is the original method. A handpiece fires a stream of fine crystals, most often aluminum oxide, sometimes sodium bicarbonate, against the skin. The crystals knock off dead cells, and the same handpiece vacuums both crystals and debris into a waste canister. The abrasiveness depends on crystal flow rate, handpiece speed and vacuum strength. Because the crystals do the work, the practitioner’s pressure matters less, but control is harder: crystals scatter, can irritate the eyes and airway, and leave a gritty residue that must be cleaned off thoroughly.
Diamond-tip microdermabrasion replaces loose particles with a wand whose head is coated in diamond grit. Heads come in different coarseness grades and sizes, so a fine head can be used near the eyes and a coarser one on the forehead. Nothing is sprayed, so there is no particle risk and less mess. The trade-off is that depth now depends heavily on the operator’s hand pressure and the number of passes, which makes technique and training more important.
Does one work better? Comparative evidence is limited and mostly small. Both remove the stratum corneum; neither reaches deeper. The practical differences are about safety and comfort rather than superior outcomes: diamond tips suit people who dislike the sensation of crystals or who have sensitive eyes, while crystal systems can be useful on very uneven textures where a free-flowing abrasive conforms to contours. If you have a strong preference, ask which the clinic uses and why. If you have none, it is reasonable to let the practitioner choose based on your skin.
How does the suction work, and why is it the setting people underestimate?
Suction is the part of the device that almost nobody asks about, yet it decides more about how the session feels and how the skin looks the next morning than the choice of crystals or diamond.
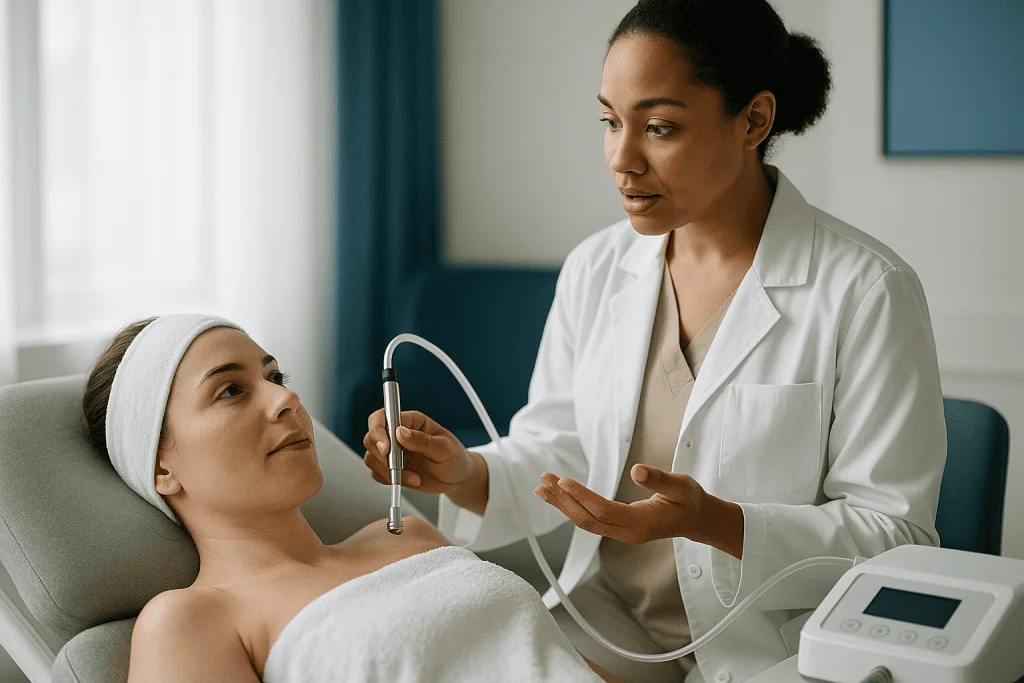
Every microdermabrasion handpiece is attached to a vacuum pump. The vacuum does two jobs at once. It draws the skin up into the tip so the abrasive surface meets it under tension, which is what allows a shallow, even layer to be removed rather than a few scattered scratches. It also pulls away the loosened cells, oil and, in crystal systems, the spent crystals.
Turn the vacuum up and three things change. The skin is pulled harder against the abrasive, so more layers come off per pass. Blood flow to the area rises, which is where the pink flush comes from. And the small capillaries near the surface are stressed, which on thin or fragile skin can produce pinpoint bruising, a pattern sometimes called petechiae. This is why practitioners lower suction around the eyes and on the neck, and why people taking blood-thinning medicines or with a history of easy bruising are asked to mention it beforehand.
Some patients hear that a higher setting means a “stronger” treatment and ask for it. The honest answer is that past a certain point, more suction adds bruising and irritation without adding benefit, because the device still cannot reach the dermis. A skilled operator adjusts the vacuum zone by zone rather than running one setting across the whole face.
Cleveland Clinic’s overview lists temporary redness, mild swelling and small bruises among the expected short-term effects, and most of those trace back to suction rather than to the abrasive itself.
How long does a microdermabrasion procedure take, and how many sessions are typical?
Timing has two layers: the clock in the room and the calendar across a course.
For a single session, Cleveland Clinic describes a facial treatment as taking roughly 30 to 40 minutes, with the neck adding about 20 minutes when it is included. Add consultation and cleansing and most appointments run under an hour. There is no anesthetic to wear off and no bandaging, so people routinely return to work or errands directly afterward.
Across a course, the same source notes that practitioners often suggest a series of sessions, commonly spaced a week or two apart, because each visit removes only a thin layer and the skin needs time to regenerate between them. The number proposed depends on the concern: a brightening treatment before an event might be a single session, while mild texture or pigment irregularity is usually approached as a series followed by occasional maintenance. Any specific count should come from the person examining your skin, not from a package size.
| Stage | Typical range reported in patient references | What drives the variation |
|---|---|---|
| Single facial session | About 30–40 minutes | Area treated, number of passes, device type |
| Neck add-on | About 20 minutes | Thinner skin, lower suction, more care |
| Interval between sessions | Roughly 1–2 weeks | How quickly redness settles, skin sensitivity |
| Visible surface change | Same day to a few days | Mostly smoother light reflection, not structural change |
| Duration of effect | Temporary; maintenance usually suggested | Normal skin turnover replaces the treated layer |
The last row matters most. Because the treatment removes cells the body was going to shed anyway, the surface returns to its baseline as turnover continues. That is not a failure of the treatment; it is what a superficial treatment is.
Who is microdermabrasion usually for, and who is usually asked to wait?
The people for whom this treatment makes most sense share a profile: skin that is basically healthy but looks dull, feels rough, has mild unevenness in tone, enlarged-looking pores, or very fine surface lines, and a goal that is modest and short term. Cleveland Clinic lists dull complexion, uneven tone and texture, age spots, melasma, fine lines and mild acne scarring among the reasons people seek it, with the caveat that benefit on the deeper items is limited.
Because the treatment is mechanical and shallow, it works across skin tones, and it avoids the heat-related pigment risks that some light-based treatments carry in deeper complexions. Even so, any abrasive treatment can trigger post-inflammatory darkening in skin prone to it, which is one reason gentle settings and strict sun protection are emphasized.
Several situations usually lead a careful practitioner to postpone or decline:
- Active acne with pustules or cysts, where abrasion can spread bacteria and worsen inflammation.
- Active cold sores, impetigo, eczema, psoriasis or rosacea flares in the treatment area.
- Recent oral isotretinoin, a retinoid prescribed for severe acne, because skin heals abnormally for months afterward; the prescribing clinician should advise on timing.
- Recent chemical peels, laser resurfacing, waxing or strong topical retinoid use, which already thin the surface.
- Open wounds, sunburn, or a tendency toward raised (keloid) scarring.
- Unexplained or changing skin lesions, which need medical assessment before anything is done to the surface.
Pregnancy is not a stated absolute barrier for a purely mechanical treatment, but many clinics defer it and most clinicians would rather you ask your obstetric provider first. None of these lists replaces an in-person look at your skin; they explain why that look is required.
Microdermabrasion vs chemical peel vs dermabrasion: a plain comparison
Three treatments share the word “resurfacing” and little else. Putting them side by side clears up most of the confusion patients bring to a consultation.
| Feature | Microdermabrasion | Superficial chemical peel | Dermabrasion |
|---|---|---|---|
| How it removes skin | Mechanical: crystals or diamond tip plus suction | Chemical: an acid solution loosens surface cells | Mechanical: a rotating wire brush or burr |
| Depth reached | Stratum corneum, sometimes upper epidermis | Epidermis; medium and deep peels go further | Into the dermis |
| Anesthesia | None | Usually none for superficial peels | Local, regional or general |
| Typical downtime | Hours to a day of pinkness | Days of flaking for superficial peels | Weeks; skin may stay pink for months |
| Usual aims | Dullness, rough texture, mild tone unevenness | Fine lines, mild pigment, mild acne | Deeper scars, deeper lines, surgical scars |
| Who performs it | Trained aestheticians or clinicians | Aestheticians for mild peels; clinicians for deeper | Dermatologists or plastic surgeons |
The Mayo Clinic’s dermabrasion page and the Johns Hopkins description both stress that true dermabrasion is a surgical procedure with a real recovery period and risks such as infection, color change and scarring, and that it is a different intervention from the microdermabrasion offered in spas. Patients sometimes arrive expecting dermabrasion-level results from a microdermabrasion appointment, and the mismatch is the source of much disappointment.
Chemical peels sit in between and overlap most directly. A superficial peel and a microdermabrasion session treat similar concerns at a similar depth; the choice often comes down to skin sensitivity, tolerance for flaking versus suction, and the practitioner’s judgment. Neither is “stronger” in a way that makes it automatically better, and some clinics alternate them. Whatever is proposed, the decision belongs with the person who has examined your skin and knows your history.
What the following days usually look like after a session
Recovery from a surface treatment is measured in hours, not weeks, but the skin is still doing real work underneath.
The first few hours. Expect pinkness similar to a brisk walk in cold air, a feeling of tightness, and heightened sensitivity to anything applied. Cleveland Clinic describes redness that typically fades within a day. Some people notice slight puffiness, especially under the eyes where suction has pulled on thin skin. Makeup is usually fine once the skin feels settled, though many people prefer to wait until the next morning.
Days one to three. The surface may feel dry or faintly rough as the next layer of cells reaches the top. A plain, fragrance-free moisturizer used more often than usual is the standard advice. Active ingredients that exfoliate or irritate, including retinoids, alpha and beta hydroxy acids, benzoyl peroxide and vitamin C serums, are generally paused for a few days; your practitioner should tell you how long for your skin. Avoid picking at any flaking.
Sun protection, every day. This is the step that decides whether a treatment helps or harms pigmentation. The freshly exposed layer has less of its protective dead-cell shield, so it burns faster and darkens more readily. The CDC’s sun safety guidance, a broad-spectrum sunscreen reapplied every two hours outdoors, shade in the middle of the day, and a wide-brimmed hat, applies with extra force in the week after treatment.
Heat and sweat. Saunas, hot yoga, swimming in chlorinated pools and heavy workouts are usually deferred for a day or two, because heat and friction prolong redness.
By the end of the first week, skin typically feels back to normal, which is also when a follow-up session is commonly scheduled if a series was planned.
Microdermabrasion side effects, and the five disadvantages people search for
“What are 5 disadvantages of microdermabrasion?” is one of the most typed questions on this topic, and it deserves a straight list rather than reassurance.
- Results are modest and temporary. Because the treatment stays in the surface layer, it cannot change deep wrinkles, pitted scars or sagging. Improvement in brightness and texture fades as normal turnover resumes, so maintenance is built in.
- Short-term irritation is common. Redness, tightness, dryness, mild swelling and occasional pinpoint bruising are expected effects, listed as such by Cleveland Clinic. They usually settle within a day or so but can last longer on sensitive skin.
- Pigment changes can occur. Skin that darkens after inflammation may develop patches of hyperpigmentation, particularly with aggressive settings or sun exposure afterward. Less often, lighter patches appear.
- Infection and flare-ups are possible. Abrading skin with active acne or a dormant cold sore can spread bacteria or reactivate the herpes virus. Poorly maintained equipment adds risk, which is one reason to ask how handpieces and tips are cleaned.
- Eye and airway exposure with crystals. Stray aluminum oxide particles can scratch the cornea or be inhaled, hence the goggles and the preference some clinics have for diamond tips.
Beyond these five, two practical drawbacks matter. The treatment requires a pause from the very ingredients, such as retinoids and acids, that have better long-term evidence for the same concerns, so timing has to be coordinated. And the appeal of “no downtime” can encourage overly frequent sessions that leave skin chronically sensitized. A reasonable practitioner will say no to a weekly habit that is not helping.
None of this makes microdermabrasion unsafe in trained hands. It makes it a treatment with a defined ceiling, which is a different thing.
Is microdermabrasion actually good for your skin? What the evidence shows
This is the question underneath all the others, and the answer has two halves.
The first half is physiological and reasonably secure. Removing the outermost dead cells smooths the surface, improves how light reflects, and can temporarily improve how well some topical products penetrate. Small studies using skin biopsies have observed thickening of the epidermis and signs of early remodeling in the upper dermis after a series of sessions. The mechanism is plausible: a controlled mild injury prompts a repair response.
The second half is clinical, and here the published literature is honest about its limits. Reviews of the research describe mostly small trials, short follow-up, inconsistent devices and settings, and outcomes often rated by the treating practitioner rather than measured objectively. Where improvement is reported for photoaged skin, fine lines, mild pigment unevenness and superficial acne scarring, it tends to be described as mild to modest. For deeper scarring and established wrinkles, evidence of meaningful benefit is weak. The Mayo Clinic and Cleveland Clinic patient pages reflect this, listing texture and tone as the realistic targets and pointing toward deeper resurfacing for deeper problems.
So is it “good for your skin”? For healthy skin treated at sensible settings with proper sun protection, it is a low-risk way to achieve a short-lived improvement in surface appearance. It is not a treatment that builds skin health over time in the way consistent sunscreen use does, and it does not substitute for a dermatologist’s assessment of a concerning spot or persistent acne. The NHS acne guidance, for instance, lists microdermabrasion among options that some people use but notes that benefit for acne itself is uncertain.
If a provider promises more than that, the gap between promise and evidence should prompt questions.
Does microdermabrasion help acne scars, melasma or age spots?
These three concerns bring many people through the door, and each deserves its own realistic framing.
Acne scars. Scars come in types. Flat, discolored marks left after a breakout are not true scars but post-inflammatory pigment, and they often fade on their own over months; surface exfoliation may slightly speed that. Shallow, rolling depressions sit in the upper dermis and may soften modestly with repeated sessions in some studies, though results vary widely. Deep ice-pick or boxcar scars extend well below anything a microdermabrasion handpiece reaches, and treatments such as subcision, fillers, microneedling, fractional lasers or surgical dermabrasion are what dermatologists typically consider for them. Asking a practitioner which scar type you have is the single most useful question before paying for a series.
Melasma. This brown, often symmetrical facial pigmentation is driven by hormones and ultraviolet light and sits at variable depths. Surface removal may lighten superficial pigment temporarily, but melasma is notoriously quick to return and can worsen with inflammation and sun. Dermatology guidance treats sun avoidance and prescribed topical agents as the foundation; microdermabrasion is at most an adjunct, and an aggressive session can make melasma darker.
Age spots. Solar lentigines, the flat brown marks of long-term sun exposure, are largely epidermal, so repeated gentle treatments can reduce their contrast for a while. Any spot that is new, changing, irregular or itchy is a different matter: it should be examined by a clinician before it is abraded, because surface treatment can disguise a lesion that needed diagnosis.
The thread connecting all three is the same: the shallower the problem, the more sense this treatment makes, and the more important daily sun protection becomes in holding any gain.
What people often get wrong about the microdermabrasion procedure
Myths cluster around any treatment that sounds more dramatic than it is. These are the ones that most often shape expectations.
“It is a mini version of dermabrasion.” The names overlap; the procedures do not. Dermabrasion is surgery into the dermis with a recovery measured in weeks and a risk profile that includes scarring, as the Mayo Clinic and Johns Hopkins pages describe. Microdermabrasion removes dead surface cells. Expecting one to deliver the results of the other is the most common disappointment.
“More suction and more passes mean better results.” Past a modest threshold, extra intensity adds bruising, pigment risk and prolonged redness without added depth. The device physically cannot reach deeper tissue by being run harder.
“Home devices do the same thing.” Consumer units are built with far weaker vacuums and finer abrasives, for good reason. They offer gentle exfoliation; they are not equivalent to a professional session, and overusing them irritates skin.
“No downtime means no precautions.” The surface is genuinely more vulnerable for several days. Skipping sunscreen or restarting a retinoid the same night is how people end up worse off than before.
“It is a treatment for acne.” Abrading inflamed, infected skin spreads bacteria. Active acne is a reason to postpone, and the underlying condition is managed with treatments a clinician prescribes.
“Results are permanent after a course.” They are not, because the treated layer is replaced by normal turnover. Maintenance is standard, and anyone selling a permanent outcome is selling something the biology does not support.
“Crystals are old-fashioned and diamond is better.” They are different tools with different trade-offs. Neither has shown clearly superior outcomes in comparative studies.
Questions to ask your care team before you book
A good consultation answers most of these unprompted. Where it does not, asking is reasonable, and the quality of the answers tells you a great deal about the practitioner.
- Looking at my skin today, what specifically do you expect this to improve, and what will it not change?
- Which device do you use, crystal or diamond tip, and why do you prefer it for my skin?
- How do you adjust the suction for thinner areas such as around my eyes and on my neck?
- Given my skin tone and history, what is my risk of darkening afterward, and what settings will you use to limit it?
- I use (or recently used) a retinoid, acne medication, or had a peel or waxing. How long should I pause before and after, and should I check with the clinician who prescribed it?
- I get cold sores. Do you want me to speak to my doctor before treatment?
- How are handpieces and tips cleaned or replaced between clients?
- What should the next three days look like, and what would make you want me to call?
- If you recommend a series, what change would you expect to see between sessions, and at what point would you stop if it is not helping?
- Would a superficial chemical peel, prescription topical treatment or a different procedure address my concern better, and who could assess that?
Two cautions on cost, since many people also search for it. This article does not publish prices, and no responsible source can quote a meaningful one, because fees vary by region, setting, area treated and what is bundled. What you can do is ask for a written breakdown of exactly what a quoted package includes, how many sessions, over what period, and what happens if you stop early. A clinic comfortable answering that question in writing is usually comfortable being held to it.
When to call your doctor after microdermabrasion
Most sessions end with a pink face and nothing to report the next day. A small number do not, and the signs that separate normal from not normal are worth knowing before you leave the clinic rather than searching for at midnight.
Contact the practitioner who treated you, or your own doctor, promptly if you notice any of the following:
- Redness, swelling or pain that is getting worse after the first 24 to 48 hours rather than settling.
- Warmth, spreading redness, yellow crusting, pus or a foul smell, which can indicate bacterial infection.
- Clusters of small painful blisters, particularly around the lips or nose, which may be a cold sore outbreak triggered by the treatment.
- Oozing, raw or open areas, or any bleeding beyond a few pinpoints.
- Fever, chills or feeling generally unwell in the days afterward.
- Eye pain, a gritty sensation, light sensitivity or blurred vision following a crystal treatment, which could mean a corneal scratch and needs same-day assessment.
- Hives, wheezing, facial or lip swelling or difficulty breathing, which can signal an allergic reaction to a product used and is an emergency.
- New dark or light patches that persist beyond a couple of weeks, or any pre-existing spot that looks different after treatment.
Call emergency services for breathing difficulty, swelling of the tongue or throat, or sudden severe eye pain. Everything else on the list can usually wait for an urgent same-day or next-day appointment, but it should not wait for the next scheduled session.
One further point. If you have a skin spot that is changing, bleeding, itching or simply looks unlike the others, show a clinician before any cosmetic treatment touches it. Abrading the surface of a lesion that needed diagnosing helps no one. Your treating team, not a booking page, should be the ones deciding whether you are ready for this procedure and what happens if your skin reacts.
Frequently asked questions
What are the steps for microdermabrasion in a typical session?
A session runs through consultation and skin check, thorough cleansing to remove oil and makeup, eye protection, a short test pass to set suction, overlapping treatment passes across each area, removal of debris or crystals, then moisturizer and broad-spectrum sunscreen. No numbing is needed. Most people describe a scratchy, pulling sensation rather than pain, and leave with pink skin that usually settles within a day.
How long does microdermabrasion take, including the appointment?
Cleveland Clinic describes a facial treatment as about 30 to 40 minutes, with the neck adding roughly 20 minutes. Allow extra time for consultation and cleansing, so most appointments finish within an hour. Because there is no anesthetic, people usually return to normal activities straight afterward, apart from avoiding heat, sweat and sun exposure for the rest of the day.
Is microdermabrasion actually good for your skin?
For healthy skin treated at sensible settings, it is a low-risk way to produce a short-lived improvement in brightness and texture. The published evidence consists mostly of small studies showing mild to modest benefit for surface concerns, and weak evidence for deep lines or scars. It does not build long-term skin health the way daily sun protection does, and it is not a substitute for medical assessment of skin problems.
What are 5 disadvantages of microdermabrasion?
The main drawbacks are that results are modest and temporary; short-term redness, dryness and occasional pinpoint bruising are common; skin prone to pigment change can darken afterward; abrading active acne or a dormant cold sore can spread infection or trigger an outbreak; and crystal systems carry a small risk of eye or airway irritation from stray particles. It also requires pausing retinoids and acids around each session.
What is diamond microdermabrasion, and is it better than crystals?
Diamond microdermabrasion uses a wand with a diamond-grit head instead of a spray of loose crystals, so there is no particle residue and no risk to the eyes from stray crystals. Depth depends more on the operator’s pressure and passes. Comparative studies are small and do not show one method producing clearly better results; the choice is usually about comfort, sensitivity and the practitioner’s training.
What microdermabrasion side effects are normal, and which are not?
Pinkness, tightness, mild swelling, dryness and occasional pinpoint bruising are expected and usually settle within a day or two. Worsening pain or redness after 48 hours, pus or crusting, clusters of blisters, fever, eye pain after a crystal treatment, or hives and breathing difficulty are not normal and warrant prompt contact with your practitioner or doctor.
Microdermabrasion vs chemical peel: which should I choose?
Both treat similar surface concerns at a similar depth. Microdermabrasion is mechanical with suction and tends to cause brief pinkness; a superficial peel is chemical and tends to cause a few days of flaking. Sensitivity, tolerance for each sensation and your skin history usually decide it. The practitioner examining your skin should recommend one, and some alternate them over a course.
Can microdermabrasion remove acne scars?
It depends on the scar type. Flat discolored marks and very shallow rolling depressions may improve modestly with a series, while deep ice-pick or boxcar scars sit far below the treatment depth and need options such as microneedling, fillers, lasers or surgical dermabrasion, assessed by a dermatologist. Active acne is a reason to postpone rather than treat.
What's the average cost of microdermabrasion?
This article does not publish prices, and no reliable source can give a meaningful average, because fees depend on region, setting, the area treated, the number of sessions and what is bundled in. The useful step is to request a written breakdown of exactly what a quoted package includes and what happens if you stop partway through a course.
How soon can I wear makeup and go in the sun after a session?
Many people wait until the next morning for makeup, once tightness has eased, though a mineral sunscreen can go on immediately. Direct sun should be avoided for several days, with broad-spectrum sunscreen reapplied every two hours outdoors as the CDC advises, because the freshly exposed layer burns and darkens more easily. Your practitioner will tailor the timing to your skin.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Hand Rejuvenation Results: How Long Volume and Texture Improvements Tend to Last
Hand rejuvenation results are temporary and vary by method. Hyaluronic acid fillers used to restore volume on the backs of the hands generally last…

Supporting a Loved One After Trauma Reconstruction: Splints, Wound Care and Follow-Up Visits
A caregiver after trauma reconstruction mainly helps with three jobs: protecting splints, wires or plates while facial bone knits over roughly six weeks, cleaning…
Scar Treatment Side Effects: Temporary Darkening, Redness and What to Report to Your Doctor
Most scar treatment side effects are temporary and expected: redness, swelling, tenderness, mild crusting or peeling, and sometimes a patch of darker skin called…

Laser Eye Surgery (LASIK) Step by Step: Drops, the Flap, the Laser and the Minutes It Takes
LASIK reshapes the cornea to reduce dependence on glasses or contacts. After numbing drops, a suction ring steadies the eye, a thin corneal flap…

What to Avoid Before Dermal Fillers: Alcohol, Blood Thinners and Supplements That Bruise
Before dermal fillers, most injectors ask you to avoid alcohol for about a day, to swap aspirin or ibuprofen taken for minor aches for…

Tissue Expansion Timeline: Weekly Fills, the Stretching Phase and Second-Stage Reconstruction
A tissue expander timeline usually runs in three phases. The expander is placed in a first operation; once the incision has healed over the…