

What Happens During an Ultrasound Scan? The Gel, the Probe and How Long Each Exam Takes
Key Takeaways
- Ultrasound uses sound vibrating millions of times per second, far above the roughly 20,000 vibrations per second that human hearing can detect, which is why the scan is silent.
- The gel is water-based and medication-free; its job is to eliminate the air layer between probe and skin, because even a hair-thin gap reflects almost all of the sound.
- The NHS puts most scans at 15 to 45 minutes, with heart and internal exams tending toward the longer end.
- Abdominal scans commonly require 8 to 12 hours without food so the gallbladder stays full and the bowel stays quiet, while external pelvic scans need a full bladder to act as an acoustic window.
- Sound cannot pass through bone or gas, so lungs, adult skull contents and structures behind air-filled bowel are usually imaged with CT or MRI instead.
- The NHS routine pregnancy schedule offers a dating scan between 10 and 14 weeks and an anomaly scan between 18 and 21 weeks, and a normal anomaly scan does not rule out every condition.
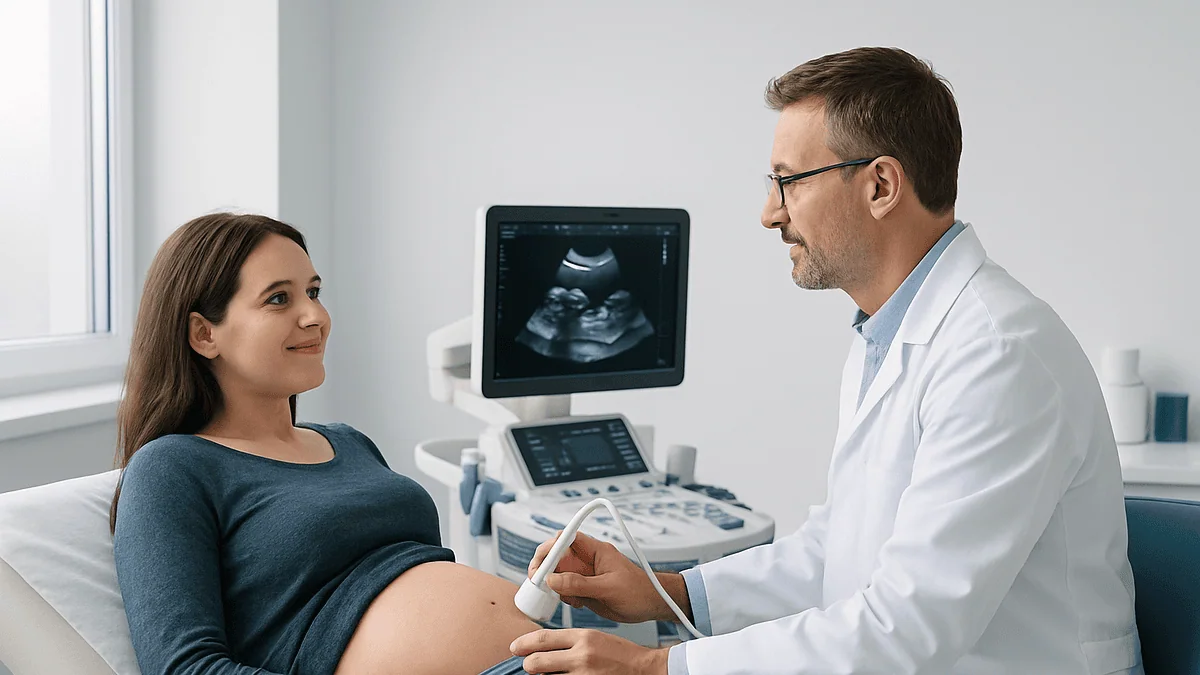
During an ultrasound scan you lie on a couch while a sonographer spreads water-based gel on your skin and moves a handheld probe over the area being examined. The probe sends high-frequency sound waves into the body and listens for echoes, which a computer turns into live images. Most scans are painless, use no radiation, and typically take 15 to 45 minutes; some internal scans use a slim probe instead.
The appointment letter arrives with two instructions that seem to contradict each other: do not eat for several hours, but drink a liter of water and hold it. Somewhere between the kitchen and the parking lot, most people start wondering what, exactly, they have agreed to. A dark room? A cold jelly? Someone frowning at a screen while saying nothing?
That quiet uncertainty is worth taking seriously, because ultrasound is one of the most common tests in medicine and one of the least explained. If you want to know what happens during an ultrasound, from the moment you sit on the paper-covered couch to the moment you are handed a tissue for the gel, this is the walk-through your letter left out.
Along the way we will cover why the gel matters more than it looks, what the probe is actually doing when it presses a little harder than you expected, how long the different exams usually take, and what the honest next step is once the screen goes dark.
How does an ultrasound work? Sound pitched far above hearing
Ultrasound is sound, nothing more exotic than that. The difference is pitch. Human ears give out at roughly 20,000 vibrations per second; the probe used in a medical scan vibrates millions of times per second, which is why you hear nothing during the exam. The National Institute of Biomedical Imaging and Bioengineering, part of the NIH, describes the technology as a pulse-and-echo system: the probe fires a brief burst of sound into the body, then switches to listening mode and waits for the echoes to return.
Every time sound crosses from one kind of tissue into another, from blood into a vessel wall, say, or from liver into the fluid of a cyst, some of it bounces back. The computer knows how fast sound travels through soft tissue, so by timing each echo it can calculate exactly how deep the boundary sits. Thousands of these timed echoes, arriving every fraction of a second, are plotted as dots of varying brightness. Stack them side by side and you get the familiar gray, moving picture.
Fluid returns almost no echoes and appears black. Bone and air reflect nearly everything and appear bright white, with a dark shadow behind them because little sound gets through. That is the single most useful thing to understand about ultrasound: it is excellent at fluid-filled and solid soft tissue, and poor at anything behind bone or gas. A gallbladder, a bladder, a kidney, a growing baby in amniotic fluid, a beating heart: these are ideal subjects. Lung and bowel full of air are not.
Doppler ultrasound adds one more trick. Sound bouncing off moving red blood cells comes back at a slightly altered pitch, the same shift that makes an ambulance siren change tone as it passes. Software converts that shift into color overlays and a whooshing audio signal, letting the operator see which way blood is flowing and how fast.
What happens during an ultrasound, from the waiting room to the couch
The person running your scan is usually a sonographer, a clinician trained specifically in ultrasound imaging, or sometimes a radiologist, a doctor who specializes in interpreting medical images. They will check your name and date of birth, confirm which part of the body is being scanned, and ask about the symptoms or question that prompted the referral. That short conversation matters more than it looks: the operator tailors the exam to what the referring doctor wants answered.

Next comes positioning. For most external scans you lie on your back on a padded couch, sometimes with a pillow under your knees or hips. You may be asked to move clothing aside or change into a gown, and the room lights are usually dimmed so the screen is easier to read. Paper towels get tucked around the edge of your clothing to catch stray gel.
Then the gel goes on, and the probe follows. According to the NHS, the operator moves the probe across the skin with light to moderate pressure, pausing to freeze the image, take measurements and save pictures. You will hear occasional clicks from the keyboard and, if Doppler is used, a rhythmic whooshing from the speaker. Expect requests to take a deep breath and hold it, which pushes the liver and kidneys down from under the ribs, or to roll onto one side so an organ falls into a better position.
Many people notice that the sonographer says very little while scanning. The silence is concentration, not concealment. Measurements are being compared against normal ranges and images are being labeled for the report. At the end the gel is wiped off, you dress, and in most settings you are free to leave immediately.
Why is the gel cold, and what is actually in it?
Nobody forgets the gel. It arrives cooler than skin temperature, slightly sticky, and in quantities that feel excessive until you understand its job. Sound travels well through water and tissue but very badly through air. Even a paper-thin layer of air between the probe and your skin will reflect almost the entire pulse straight back, leaving the screen a wash of static. The gel fills every microscopic gap so the sound has an unbroken, watery path into the body.
The material itself is a water-based, hypoallergenic gel, usually made from water, a thickening agent such as a cellulose or carbomer polymer, a humectant to stop it drying out, and a preservative. It contains no medication and no dye. Mayo Clinic notes that it is designed to wash off easily and will not stain most clothing, although it can leave a damp patch, so loose, washable clothing is the sensible choice for scan day.
Why cold? Many departments keep bottles at room temperature, which feels chilly against warm skin, and a cool gel also tends to hold its consistency better. Some rooms use a gel warmer, especially for pregnancy scans and for children, so warmth is worth asking about if you are sensitive to cold.
The gel also acts as a lubricant, letting the probe glide without dragging on the skin, and this is why the operator applies more as the exam moves to new areas rather than relying on one dab. If you have an open wound, rash or recent surgical incision in the area, mention it before the gel goes on. The operator can use a sterile gel or a protective cover, or adjust the approach entirely.
After the exam you will be handed paper towel to wipe off. A quick wash with soap and water at home removes any residue.
The probe, the pressure and the different types of transducer
The handheld device is called a transducer, a part that converts electrical energy into sound and back again. Inside are crystals that flex when a voltage is applied, producing the sound pulse, and generate a tiny voltage when returning echoes squeeze them. The NIH describes several shapes, each suited to a different depth and body region.
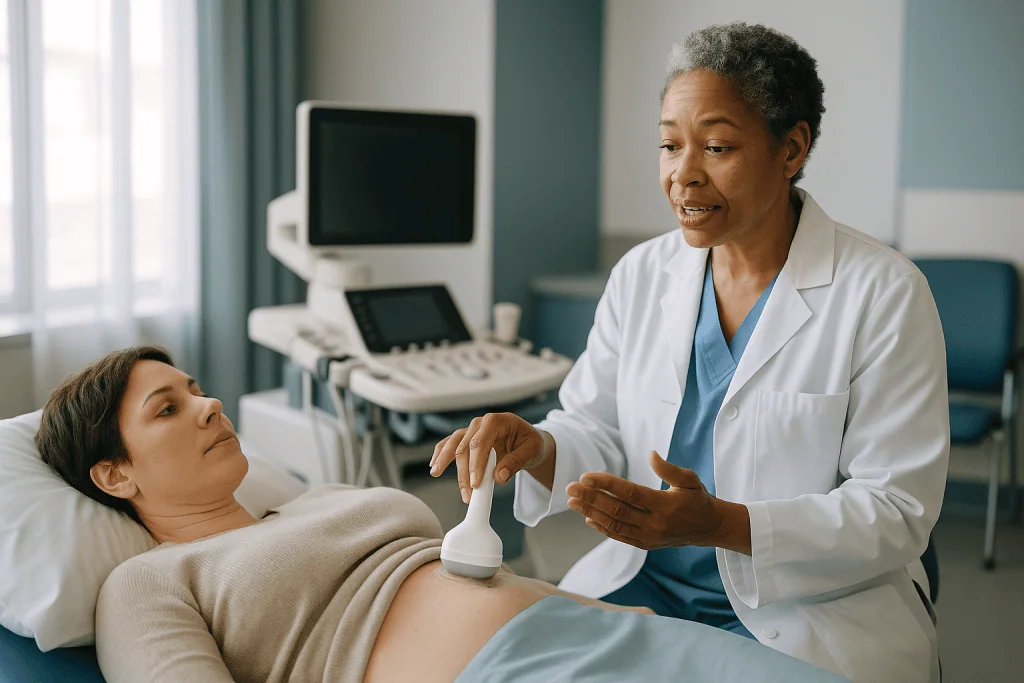
A curved, wide-faced probe uses lower frequencies that travel deeper, which suits abdominal and pregnancy scans. A flat, narrow probe uses higher frequencies that give sharper detail but fade within a few centimeters, which is ideal for the thyroid, breast tissue, tendons and veins in the arm or leg. A small, square-faced probe fits between the ribs to view the heart. Lower frequency buys depth; higher frequency buys detail. The operator is constantly trading one for the other.
Some exams use internal probes. A transvaginal probe is a slim, covered wand placed a short distance into the vagina to image the uterus and ovaries from close range. A transrectal probe examines the prostate. For an endoscopic ultrasound, a tiny transducer sits on the tip of a flexible camera tube passed into the digestive tract, usually with sedation. The NHS notes these internal scans may be uncomfortable but are not usually painful, and you can ask for the exam to stop at any point.
About the pressure: the operator presses firmly when they need to push bowel gas aside or bring a deep organ closer. If the scan is for pain, pressing on the sore spot is often deliberate, because confirming that the tenderness sits exactly over an inflamed gallbladder or appendix is itself a finding. Say so if it hurts; a good operator will ease off and work around it.
How long does an ultrasound take? Typical times by exam
Timing depends on how many structures need measuring, how easily they can be seen, and whether blood flow is being assessed. The NHS gives an overall range of 15 to 45 minutes for most scans, while Mayo Clinic quotes 30 to 60 minutes once check-in and positioning are included. Internal exams and heart scans tend toward the longer end because more views and measurements are needed. The table below summarizes what usually distinguishes one exam from another.
| Exam | Usual preparation | Probe and position | Typical duration |
|---|---|---|---|
| Abdominal (liver, gallbladder, pancreas, kidneys) | Fasting for several hours, often 8–12 hours (MedlinePlus) | Curved external probe; lying on back and sides, breath-holds | Within the 15–45 minute range (NHS) |
| Pelvic, external | Full bladder, drinking water about an hour before | Curved probe over lower abdomen | Often at the shorter end of the range |
| Pelvic, transvaginal | Empty bladder | Slim covered internal probe | Within the 15–45 minute range (NHS) |
| Pregnancy dating scan | Full bladder may be requested early in pregnancy | External curved probe, sometimes transvaginal | Within the 15–45 minute range (NHS) |
| Echocardiogram (heart) | Usually none | Small probe between ribs; lying on left side | Tends toward the longer end, up to about an hour (Mayo Clinic) |
| Leg vein Doppler | None | Flat probe along the leg with compression | Within the 15–45 minute range (NHS) |
A few things stretch the clock: a baby lying in an awkward position, bowel gas hiding part of the pancreas, or a finding that the sonographer wants to document from several angles. A longer scan does not mean something is wrong. It usually means the operator is being thorough or is waiting for a better view.
What to do before an ultrasound: fasting, water and what to wear
The rules before an ultrasound exist for one reason, acoustics. Food and drink set off digestion, which fills the stomach and bowel with gas and causes the gallbladder to contract and empty. Both ruin the view. MedlinePlus advises that patients having an abdominal ultrasound are commonly asked not to eat or drink for 8 to 12 hours beforehand, so the gallbladder stays distended and the upper abdomen stays quiet. Your own department’s instructions take precedence; some allow sips of water, others ask you to avoid chewing gum and smoking too, because both make you swallow air.
Pelvic scans through the abdominal wall ask for the opposite. The NHS explains that a full bladder lifts the uterus and ovaries into view and acts as a window of fluid through which sound travels cleanly. Departments typically ask you to drink several glasses of water about an hour before and not to empty your bladder. It is uncomfortable, and that discomfort is normal; tell the operator if it becomes unbearable and they may scan quickly or let you partially empty.
For most other scans there is no special preparation. Wear two-piece clothing that lets the area be uncovered without full undressing, and leave jewelry at home if the neck or wrist is being examined. Take your usual medicines unless the referring team has specifically told you otherwise; the scan itself does not interact with medication, and any instruction to pause a medicine should come only from the clinician who prescribes it.
Bring a list of your current medicines and any previous imaging reports if you have them, since comparing with an earlier scan is often the most informative thing the radiologist can do. If you have a latex allergy, say so; internal probe covers and gloves can be swapped for latex-free alternatives.
Three common reasons an ultrasound is ordered
Ask why ultrasound is done and you will get a long list, but most requests fall into three categories.
The first is to look for a structural cause of symptoms. Pain under the right ribs after meals prompts a gallbladder scan looking for stones; a palpable lump in the neck prompts a thyroid scan; a swollen calf prompts a vein scan for clots. The Cleveland Clinic lists abdominal pain, abnormal blood tests, swelling and unexplained bleeding among the most frequent triggers. Ultrasound is often the first imaging test precisely because it is quick, radiation-free and good at distinguishing fluid from solid tissue.
The second is to monitor something already known. A pregnancy is the obvious example, but the same logic applies to a kidney cyst being checked for growth, an aortic aneurysm being measured annually, or a liver being assessed in someone with long-standing liver disease. Here the question is not what is this but has it changed, which is why bringing previous reports matters.
The third is to guide a procedure. Because the image is live, a doctor can watch a needle travel toward a target in real time. Biopsies of the thyroid, breast and liver, drainage of fluid collections, and placement of lines into deep veins are all routinely performed under ultrasound guidance. MedlinePlus notes this makes procedures safer and more accurate than working by feel alone.
Two smaller categories deserve a mention. Doppler studies assess blood flow through arteries in the neck or legs. And in emergency settings, a rapid bedside ultrasound can check for internal bleeding or fluid around the heart within minutes. None of these uses changes what you experience on the couch; the gel, the probe and the dim room are the same.
Pelvic ultrasound: what to expect and what a pelvic scan is used for
A pelvic scan images the organs between the hip bones. In women this means the uterus, the lining of the uterus, the ovaries and the surrounding space; in men, the bladder and prostate. The question behind the request is usually one of a handful: heavy or irregular periods, pelvic pain, a suspected cyst or fibroid, difficulty conceiving, bleeding after menopause, or trouble emptying the bladder. The NHS also lists it as a standard way to investigate early pregnancy bleeding.
There are two routes, and you may have both in one visit. The transabdominal scan is done through the lower belly with a full bladder, as described earlier, and gives a wide overview. The transvaginal scan uses the slim internal probe and is performed with an empty bladder, so you will be asked to visit the toilet in between. The probe is covered with a fresh protective sheath and gel, inserted a few centimeters, and angled gently to view each ovary and the uterus in turn. The Cleveland Clinic describes the sensation as pressure rather than pain, similar to a pelvic exam, and the internal part is usually brief.
You are in control throughout. You can ask for a chaperone, ask the operator to explain each step, or ask to insert the probe yourself, which some people prefer. The scan can be stopped at any point.
What the operator measures: the size and shape of the uterus, the thickness of its lining, the volume of each ovary and any follicles or cysts, and the presence of free fluid. Fibroids, which are benign muscle growths, appear as rounded masses in the uterine wall. Simple cysts appear as clean black circles. Anything more complex is described in detail for the referring doctor rather than interpreted on the spot.
Pregnancy ultrasound: what the dating and anomaly scans look for
Pregnancy is where most people first meet ultrasound, and the two routine scans have very different purposes. The NHS describes the first, usually offered between 10 and 14 weeks, as the dating scan. The sonographer measures the length of the fetus from crown to rump, which at this stage is a reliable gauge of how far along the pregnancy is, and uses it to estimate the due date. The scan also confirms the heartbeat, checks whether there is more than one baby, and, if you have chosen combined screening, measures the fluid at the back of the neck as part of an assessment for chromosomal conditions.
The second routine scan, between 18 and 21 weeks according to NHS guidance, is the anomaly scan. This is a longer, more methodical exam in which the operator works through the baby’s anatomy structure by structure: brain, face, spine, heart chambers, kidneys, bladder, limbs, abdominal wall and the position of the placenta. It can detect some conditions and cannot detect others, and the NHS is explicit that a normal anomaly scan does not guarantee a baby is free of all problems.
Practically, both scans use an external curved probe over the lower abdomen. Early on, a full bladder helps; later in pregnancy the uterus is large enough that it is rarely needed. A transvaginal view may be offered at the dating scan if the pregnancy is very early or the view is poor.
You can usually bring one companion. The operator will often turn the screen toward you and point out what is visible, but will also need stretches of quiet to take measurements. If something needs a closer look, you may be asked to walk around for a few minutes and return, or be offered a repeat scan on another day, which is common and does not by itself signal a problem.
Who ultrasound is usually for, and when another scan is chosen instead
Ultrasound suits almost everyone. There is no radiation, so it is the first-line choice in pregnancy and in children, and there is no injected dye, so kidney function and allergies are not an obstacle. People with pacemakers or metal implants, who may be unable to have an MRI, can have ultrasound without concern. The exam can be done at the bedside, in an emergency department or in a clinic, which is why the Cleveland Clinic describes it as one of the most widely used imaging tests in medicine.
Its limits are physical rather than medical. Sound cannot pass through air or bone, so the lungs, the inside of the skull in adults, and anything hidden behind a loop of gas-filled bowel are better imaged with CT or MRI. Sound also weakens as it travels, so deep structures in a larger body may be harder to resolve clearly; the operator compensates with a lower-frequency probe and firmer pressure, and will note in the report if the view was limited rather than guess.
Some people are asked to wait or reschedule, not because ultrasound is unsuitable but because the preparation did not work out. An abdominal scan after a large breakfast, or a pelvic scan with an empty bladder, often yields images too poor to answer the question, and the department may offer another slot rather than issue an inconclusive report. If fasting is hard for you, because of diabetes for example, tell the booking team in advance so timing can be adjusted with your prescribing clinician.
Ultrasound is also sometimes a stepping stone. If it finds something that needs characterizing, such as a solid liver lesion, the next test is often MRI or CT. That sequence is normal practice, not a sign that the first scan failed.
Is ultrasound safe? What the evidence shows about risk
Diagnostic ultrasound has been used for several decades and has an excellent safety record. The NHS states that there are no known risks from the sound waves used in a standard scan, and Mayo Clinic makes the same point, adding that it is the imaging method of choice during pregnancy for exactly this reason. Unlike X-ray and CT, it involves no ionizing radiation, so there is no cumulative dose to track.
The physics still deserves respect. Sound energy deposits a small amount of heat in tissue, and at high intensities it can cause tiny gas bubbles to oscillate. Diagnostic machines operate well below the levels at which these effects cause harm, and every scanner displays indices that let the operator keep exposure low. The NIH describes the guiding principle as using the lowest output and shortest time needed to answer the clinical question, which is why professional guidance discourages non-medical scans performed purely to produce keepsake images or videos.
The realistic risks are practical ones. A transvaginal or transrectal scan may cause brief discomfort or light spotting. Firm pressure over an inflamed organ can hurt. Gel can irritate very sensitive skin, though this is uncommon. Endoscopic ultrasound carries the small risks of any sedated endoscopy, which the team performing it will explain and consent you for separately.
The more subtle risk is interpretive. Ultrasound is operator-dependent, meaning image quality and what is noticed depend on the skill of the person holding the probe. It can also find incidental things, small cysts or nodules that would never have caused trouble, which then need follow-up. Neither is a reason to avoid the test; both are reasons to have it done in a department where the results feed back to a clinician who knows your history.
What is the next step after an ultrasound? Results and the following days
The scan ends, the gel comes off, and the most common question follows: did you see anything? In most settings the sonographer will not give a diagnosis. The images and measurements go to a radiologist, who writes a formal report for the clinician who requested the test. The NHS explains that results are therefore usually sent to your referring doctor rather than handed to you, and that this can take from a few days to a couple of weeks depending on the department. Some services do give an immediate verbal result, particularly in pregnancy or emergency settings; ask at the start what to expect so the silence does not feel ominous.
Physically, the following days look like any other days. There is no recovery period after an external scan, you can eat immediately if you were fasting, and you can drive, work and exercise straight away. After a transvaginal scan a little spotting can occur and should settle within a day. After an endoscopic ultrasound with sedation, the usual advice applies: someone to take you home and no driving or signing important documents until the next day.
The clinical next step depends entirely on the question asked. A normal scan may close the matter or redirect attention elsewhere. A finding may lead to a blood test, a repeat scan in a few months to check for change, a different imaging test such as MRI or CT, or a referral to a specialist. A scan done to guide a biopsy will be followed by the pathology result, which has its own timeline.
Whatever the outcome, the report belongs in a conversation with the clinician who ordered it. That discussion is where the images meet your symptoms, history and preferences, and where decisions are made.
What people often get wrong about ultrasound
Several durable myths cling to this exam, and most of them add needless anxiety.
The sonographer went quiet, so something must be wrong. Quiet is the normal working state. Measuring a kidney to the millimeter or counting heart chambers requires attention, and many departments have a policy that results are given by the referring clinician. Silence is procedure, not verdict.
Ultrasound is a lesser test than CT or MRI. It is a different test. For gallstones, ovarian cysts, leg clots, thyroid nodules and the developing fetus, ultrasound is frequently the preferred first exam, as both Mayo Clinic and the NHS note. CT and MRI win when sound cannot reach the target.
It uses radiation. It does not. The confusion comes from the word scan, which also covers X-ray-based tests. Ultrasound uses sound, which is why it is used freely in pregnancy.
A normal scan means nothing is wrong. A normal scan means nothing was visible to ultrasound in the area examined on that day. Small lesions, early disease and problems behind bowel gas can be missed. If symptoms persist, go back; the clinical picture outranks a single image.
More gel or more pressure means the operator is struggling. Gel is reapplied constantly as it dries and spreads, and pressure is a tool for displacing gas. Neither signals a problem.
Pregnancy scans can confidently see everything. The anomaly scan detects some conditions well and others poorly; the NHS lists detection rates for individual conditions in its own patient materials, and they vary widely. A reassuring scan is good news, but it is not a guarantee.
You will get the full result before you leave. Sometimes, but usually not. Ask at check-in how and when results will reach you, and who to contact if you have not heard.
Questions to ask your care team
A few minutes of questions before and after the scan can turn a confusing episode into a useful one. Write them down; appointments move quickly.
- What question is this scan meant to answer, and what will happen if the answer is normal or abnormal?
- Do I need to fast or arrive with a full bladder, and for how long? Can I take my usual medicines as normal?
- Will the exam be external, internal or both, and can I have a chaperone?
- Roughly how long should I allow, including check-in and waiting?
- Will I be told anything at the time, or will results go to my referring doctor? How long should that take, and whom do I contact if I have not heard?
- If something is found, what is the likely next step: a repeat scan, another type of imaging, a blood test or a referral?
- Should I bring previous scan reports or images for comparison?
- For pregnancy scans: what can this scan detect, and what can it not detect?
- For guided procedures: what are the specific risks, and what aftercare will I need?
Two of these matter most. The first is the purpose question, because knowing what the scan is for helps you interpret both the result and any follow-up suggested. The second is the results question, because the most common frustration people report about ultrasound is not the gel or the probe but the uncertainty afterward. Agreeing on a timeline and a contact point before you leave the department removes most of it.
Finally, if anything about the exam itself concerns you, whether discomfort during an internal scan, a worry about the operator pressing on a painful area, or a wish to have the screen explained, say so at the start. Sonographers adjust their approach routinely; they can only do it if they know.
When to call your doctor
Ultrasound itself almost never causes harm, so the red flags here are mostly about the symptoms that led to the scan, and about not letting a pending report delay care when something changes. Contact your doctor, or seek urgent care, if any of the following occur before or after your scan:
- Severe or rapidly worsening abdominal or pelvic pain, especially with fever, repeated vomiting or a rigid, tender belly.
- Heavy vaginal bleeding, bleeding with clots, or bleeding with pain in pregnancy, or more than light spotting lasting beyond a day after a transvaginal scan.
- A swollen, painful, warm calf, or sudden breathlessness or chest pain, which can signal a clot that has moved to the lung and needs emergency assessment.
- Fainting, dizziness on standing, a racing heart or confusion.
- Yellowing of the skin or eyes, dark urine or pale stools, suggesting a blocked bile duct.
- After endoscopic ultrasound: severe chest or abdominal pain, difficulty swallowing, vomiting blood or black stools, or a fever.
- Reduced or absent fetal movements in later pregnancy, which should never wait for a scheduled scan.
Call your doctor’s office, rather than emergency services, if you have not received your results within the timeframe you were given, if your symptoms have continued despite a normal report, or if you develop new symptoms that were not present when the scan was requested. A normal ultrasound examines one region at one moment; persistent symptoms are a reason for reassessment, not reassurance by default.
If you are unsure whether something counts as urgent, treat it as urgent. The treating team would far rather hear from you about a symptom that turns out to be minor than learn afterward that a report sat unread while a situation changed.
Frequently asked questions
How long does an ultrasound take from start to finish?
Most ultrasound scans take between 15 and 45 minutes according to the NHS, while Mayo Clinic allows 30 to 60 minutes once check-in and positioning are counted. Heart scans and internal pelvic scans tend toward the longer end because more measurements are needed. A longer scan usually reflects thoroughness or a difficult view rather than a worrying finding.
How does an ultrasound work in simple terms?
The probe sends short pulses of high-pitched sound into the body and listens for the echoes that bounce back from boundaries between tissues. By timing each echo, the computer calculates how deep each boundary sits and builds a live grayscale image. Fluid looks black because it returns few echoes; bone and air look white and cast shadows.
What are the rules before getting an ultrasound?
Preparation depends on the area. Abdominal scans commonly require no food for 8 to 12 hours so the gallbladder stays full, per MedlinePlus. External pelvic scans ask you to arrive with a full bladder. Most other scans need no preparation. Take your usual medicines unless your prescribing clinician says otherwise, and wear two-piece clothing.
What are three reasons why an ultrasound is done?
The three most common reasons are to find a structural cause for symptoms such as pain, swelling or a lump; to monitor something already known, such as a pregnancy, cyst or aneurysm, for change over time; and to guide a procedure such as a biopsy or fluid drainage in real time. Doppler studies of blood flow are a frequent fourth.
What is a pelvic scan used for?
A pelvic ultrasound images the uterus, uterine lining, ovaries and surrounding space in women, and the bladder and prostate in men. It is used to investigate heavy or irregular periods, pelvic pain, suspected cysts or fibroids, difficulty conceiving, bleeding after menopause, early pregnancy bleeding and problems emptying the bladder.
Pelvic ultrasound: what to expect if an internal probe is used?
A transvaginal scan uses a slim, covered probe inserted a few centimeters with an empty bladder. The Cleveland Clinic describes the sensation as pressure similar to a pelvic exam, and the internal part is usually brief. You can request a chaperone, ask to insert the probe yourself, and stop the exam at any time.
What is the next step after an ultrasound?
The images go to a radiologist who writes a report for the doctor who requested the scan; the NHS notes this can take from a few days to a couple of weeks. The next step depends on the result and may be nothing further, a repeat scan, a blood test, a different imaging test such as MRI or CT, or a specialist referral.
Why does the sonographer not tell me the results?
In most departments the sonographer acquires the images and a radiologist interprets them, with results delivered by the referring clinician who knows your history. Quiet during the scan reflects concentration on measurements, not concealment. Ask at check-in whether any verbal feedback will be given and when the written report should reach your doctor.
Is ultrasound safe during pregnancy and for children?
Yes, by current evidence. Ultrasound uses sound rather than ionizing radiation, and the NHS and Mayo Clinic state there are no known risks from standard diagnostic scans. Operators keep output as low as reasonably achievable, and professional guidance discourages non-medical scans done purely for keepsake images.
Does an ultrasound hurt?
External scans are painless, though firm pressure over an already tender organ can be uncomfortable, and a full bladder for a pelvic scan can feel urgent. Internal scans may cause brief pressure or discomfort. Tell the operator at any point if something hurts; they can ease pressure, change position or pause the exam.
References
- NHS: Ultrasound scan
- NHS: Ultrasound scans in pregnancy
- MedlinePlus: Abdominal ultrasound
- Cleveland Clinic: Ultrasound
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
What Doppler Ultrasound Adds: How Blood-Flow Imaging Changes a Vascular or Pregnancy Exam
Doppler ultrasound is a form of ultrasound that measures how blood moves through vessels, not just how tissue looks. It uses the Doppler effect:…

Why a Doctor Orders a Liver Ultrasound, and What It Can Find
A doctor usually orders a liver ultrasound to look for a physical explanation for abnormal liver blood tests, pain or fullness under the right…

Who Benefits From a Comprehensive Check-Up? How Age and Family History Shape the Test List
Most adults benefit from a periodic comprehensive check-up, but the right test list depends on age, sex, family history, and existing conditions rather than…

EMG vs Nerve Conduction Study vs MRI: Which Test Finds the Cause of Numbness and Weakness
EMG, nerve conduction studies and MRI answer different questions. Nerve conduction studies measure how fast and how strongly a nerve carries electrical signals; EMG…

Before a Comprehensive Check-Up: Fasting Rules, Medical Records and Questions Worth Bringing
To prepare for a health check up, confirm which tests are booked, then follow the fasting instruction you are given, usually 8–12 hours with…
How Long a CT Scan Takes: Preparation, the Scan Itself and the Wait for Results
A CT scan itself usually takes about 10 to 20 minutes, and the moment the X-ray beam is actually on often lasts under a…