

Who Is IVIG Therapy For? Immunodeficiency, Autoimmune Conditions and How Doctors Decide

Key Takeaways
- IVIG is used for two opposite purposes: replacing antibodies people cannot make, and calming an immune system that is attacking the body's own nerves, platelets or blood vessels.
- For antibody deficiency, a poor antibody response to vaccination is often the finding that tips the decision, because low IgG numbers alone do not prove the immune system is failing.
- Guillain-Barré syndrome is usually treated with a single hospital course; the NHS and Mayo Clinic describe IVIG and plasma exchange as broadly equivalent options.
- The NHS stresses starting IVIG for Kawasaki disease within the first ten days of illness to reduce the risk of coronary artery damage.
- IVIG carries boxed warnings for blood clots and kidney injury, so kidney function, clotting history, hydration and previous reactions are checked before each course.
- Live vaccines such as measles-mumps-rubella are delayed for many months after IVIG because donor antibodies can neutralize them; the treating team sets the interval.
IVIG therapy is used for two broad groups: people whose bodies cannot make enough working antibodies, such as those with primary immunodeficiency, and people with certain autoimmune or inflammatory conditions, including Guillain-Barré syndrome, chronic inflammatory demyelinating polyneuropathy, immune thrombocytopenia and Kawasaki disease. Doctors decide based on a confirmed diagnosis, infection or symptom history, laboratory results and whether alternatives are unsuitable; the treating team makes the final call.
The word arrives before the explanation does. A specialist says “immunoglobulin,” a nurse says “infusion day,” and someone finds themselves at the kitchen table that evening typing who needs IVIG treatment into a search bar, hoping for a straight answer. What comes back is a jumble: a neurology page about nerves, a pediatric page about fever in toddlers, a forum thread about headaches. All of them are talking about the same clear liquid in the same kind of bag.
That confusion is not a failure of reading. IVIG genuinely does different jobs for different people, and the reasoning a doctor uses to offer it to a child with recurrent pneumonia is almost the mirror image of the reasoning used for an adult whose legs suddenly stopped working.
This explainer walks through both logics, what happens in the chair, who is asked to wait, how long people typically stay on it, and the questions worth asking before the first drip starts.
Who needs IVIG treatment? The short version
Ask a hematologist, a neurologist and an immunologist who needs IVIG treatment and you will hear three overlapping answers, because the same pooled antibodies do different jobs in different hands. Immunoglobulin is the medical name for antibodies, the proteins your immune system makes to recognize and neutralize germs. IVIG, short for intravenous immunoglobulin, is a concentrated preparation of those proteins collected from the plasma of thousands of healthy donors and infused into a vein.
The first group are people who cannot make enough working antibodies of their own. Primary immunodeficiency is the umbrella term for inherited conditions in which part of the immune system is missing or faulty; the National Institute of Allergy and Infectious Diseases describes hundreds of distinct forms. Some people also develop antibody shortages later in life from blood cancers, certain treatments or protein loss. Here IVIG is replacement: it supplies what the body lacks, in the same spirit as insulin for someone whose pancreas has stopped producing it.
The second group has plenty of antibodies but an immune system attacking the wrong target. In Guillain-Barré syndrome, chronic inflammatory demyelinating polyneuropathy, immune thrombocytopenia and Kawasaki disease, a large surge of donor antibodies appears to quiet the misdirected attack. This is immunomodulation, and it usually runs as a defined course rather than lifelong therapy.
Two things separate a candidate from someone who is not: a diagnosis confirmed by history and laboratory testing, and a judgment that the likely benefit outweighs the risks and the alternatives. Both belong to the treating team. What follows explains the reasoning behind that judgment, so the conversation in the consulting room feels less like a verdict and more like a plan you understand.
How IVIG works, in plain language
Picture a river of blood carrying billions of Y-shaped proteins. Each antibody has two arms that grip a specific target and a stem that signals other immune cells to act. IgG, the most abundant antibody class in blood, is what IVIG is made of, and it is the class that lingers longest and moves most easily into tissues.
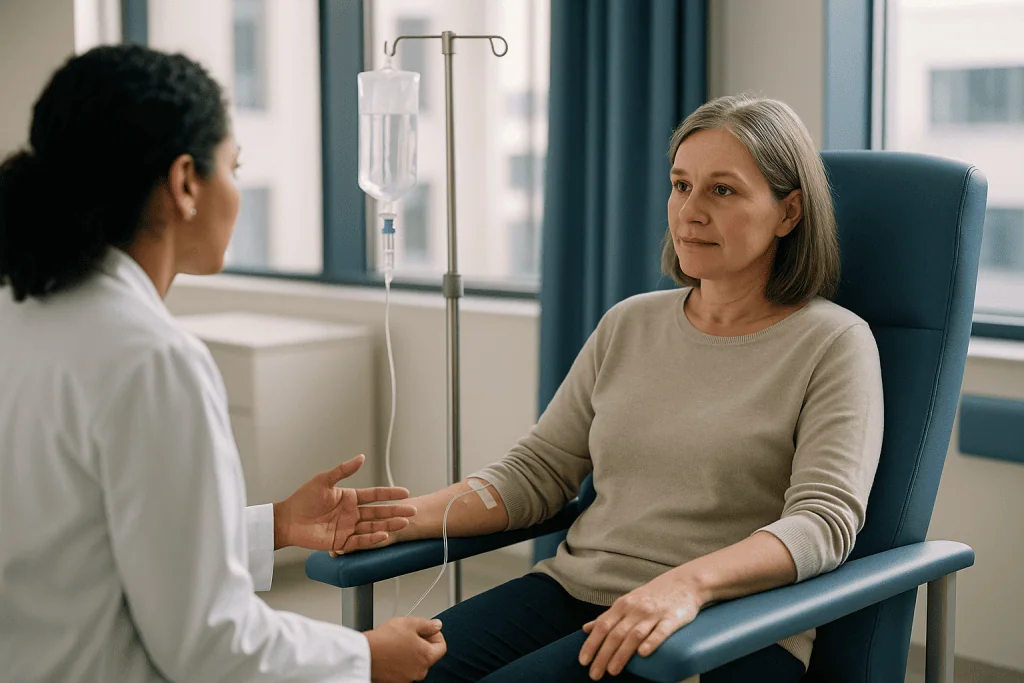
For someone with antibody deficiency, the mechanism is almost literal. Donor IgG circulates, binds bacteria and viruses the recipient could not otherwise recognize, and flags them for destruction. Because the pool comes from thousands of donors, it carries a broad memory of common infections, wider than any single person’s. The catch is that donated IgG is slowly broken down, so protection falls over weeks and the infusion has to be repeated; NIAID notes that replacement is typically given every three to four weeks.
The autoimmune story is less tidy, and honest sources say so. Several mechanisms have been proposed and probably act together. A flood of donor IgG appears to saturate the recycling system that normally keeps antibodies in circulation, so the patient’s own harmful antibodies are cleared faster. Donor antibodies can also block receptors on immune cells, dampen complement (a cascade of proteins that punches holes in cells marked for attack) and soak up inflammatory signals. In immune thrombocytopenia, where the spleen destroys platelets coated with self-antibodies, IVIG seems to occupy the spleen’s receptors so more platelets survive.
What matters for a patient is the shape of the benefit. Replacement works quietly and continuously, with success measured as fewer serious infections over years. Immunomodulation is meant to produce a visible change over days to weeks: a rising platelet count, returning strength or a falling fever. Knowing which of the two your team is aiming for tells you what to watch and how patient to be.
What actually happens on an IVIG infusion day
Most first infusions happen in a hospital day unit or infusion center, with a nurse who does this every day. Expect baseline checks: temperature, pulse, blood pressure and usually weight, since the amount infused is calculated by the prescriber from body size. A small cannula goes into a vein in the hand or forearm. Many people are asked to drink well beforehand, because good hydration is one of the simplest protections for the kidneys, which filter the extra protein load.
The bag is started slowly. Nurses raise the rate in steps only if you feel well, because most immediate reactions, chills, headache, flushing, back pain and nausea among them, are linked to speed rather than to the product itself. Slowing or pausing the drip usually settles them. Some teams offer a premedication such as an antihistamine; that is an individual prescribing decision, not a rule.
How long does it take? MedlinePlus describes IVIG infusions as lasting several hours, and a first infusion is often the longest because the team deliberately goes gently. Bring a charger, a book and a snack. Vital signs are checked at intervals, and you will be observed for a period after the last drop.
Later infusions tend to move faster once the team knows how you respond, and some patients eventually receive home infusions from a specialist nurse. Whether that is appropriate depends on your reaction history, your veins, your condition and local services. For autoimmune uses, a course may run on consecutive days during an admission; the NHS describes the Guillain-Barré syndrome course as spread over about five days.
One practical point people rarely hear in advance: the infusion is only part of the appointment. Blood tests, a conversation about how you have been since last time and paperwork recording the batch all add time. Plan for a day, not an hour.
What qualifies you for IVIG when antibodies are missing
A recurring pattern of infections is the doorway, but it is not the diagnosis. The classic history is repeated bacterial infections of the ears, sinuses and lungs, or infections that are unusually severe, persistent or keep returning despite appropriate treatment. People with these stories are referred to an immunologist, a specialist in the immune system.

Laboratory testing then does the real work. Blood levels of the main antibody classes, IgG, IgA and IgM, are measured, and a low IgG raises the possibility of antibody deficiency. Numbers alone are not enough, because some people with low readings fight infection perfectly well. So the immunologist checks function: after a vaccine, does the body mount a rising antibody response? A poor response despite vaccination is often the deciding finding. Genetic tests may follow to pinpoint a specific disorder, from common variable immunodeficiency to rarer conditions in which B cells, the antibody factories, are almost absent.
Secondary antibody deficiency, meaning a shortage caused by something else, is assessed differently. Blood cancers such as chronic lymphocytic leukemia and multiple myeloma, treatments that deplete B cells, and conditions that leak protein can all lower IgG. Here the question is whether infections are actually happening and whether more targeted measures, including vaccination and preventive antibiotics, have been tried or are unsuitable.
What qualifies you for IVIG, then, is the combination: a documented deficiency, evidence that it is causing harm, and a judgment that replacement is the right tool. Immunologists usually think about the trend over time rather than a single blood test, and about the burden infections are placing on your lungs, hearing, school or work. If you have been told your levels are borderline, ask what would change the decision and what the plan is meanwhile.
Why IVIG is used for autoimmune conditions too
The autoimmune uses of IVIG grew out of an accident of observation. Decades ago, clinicians giving replacement IVIG to a child with both antibody deficiency and immune thrombocytopenia noticed the platelet count rise. That single observation opened a second career for the product, and today several autoimmune and inflammatory conditions have IVIG written into mainstream guidance.
Guillain-Barré syndrome is the clearest example. It is a rapid-onset condition in which the immune system attacks the peripheral nerves, causing weakness that can climb from the feet upward over days. The NHS and Mayo Clinic both list IVIG and plasma exchange (a procedure that filters harmful antibodies out of the blood) as the two main treatments, and both describe them as broadly equivalent, so the choice often rests on availability and the patient’s circumstances. Timing matters because the aim is to shorten the attack while it is still active.
Chronic inflammatory demyelinating polyneuropathy, or CIDP, is a slower cousin of the same process, with weakness and numbness building over months. IVIG is one of the first-line options alongside corticosteroids and plasma exchange, and some people need repeated courses to hold the condition steady.
Immune thrombocytopenia, or ITP, is a condition in which antibodies mark platelets, the blood’s clotting cells, for destruction. IVIG is used when counts are dangerously low, bleeding is present or a fast rise is needed, for instance before surgery, because the effect is quick but temporary.
Kawasaki disease is an inflammation of blood vessels in young children that can damage the arteries supplying the heart. The NHS describes IVIG as the main treatment and stresses giving it early, ideally within the first ten days of illness, to reduce the risk of coronary artery damage.
Other uses, in some muscle inflammation disorders, certain neuromuscular junction diseases and specific skin conditions, rest on thinner evidence and are decided case by case by specialists.
How doctors decide who needs IVIG treatment
Behind the decision sits a set of questions that most specialists work through in roughly the same order, whatever the condition.
Is the diagnosis secure? IVIG is a pooled human blood product with real risks and a finite global supply, so guidelines reserve it for conditions where the evidence is strongest. A neurologist will want nerve conduction studies and often a spinal fluid sample before treating CIDP; an immunologist will want repeated antibody levels and vaccine responses before starting replacement.
Is harm happening now, or is the risk of it high? Low antibody numbers without infections, or a modest platelet drop without bleeding, may be watched rather than treated. A child with Kawasaki disease or an adult losing the ability to walk from Guillain-Barré syndrome is treated promptly, because the cost of waiting is measured in permanent damage.
Have the alternatives been considered? For replacement, that means vaccination and preventive antibiotics where appropriate. For autoimmune conditions, it means corticosteroids, plasma exchange or other immune-targeting medicines, each with its own trade-offs. IVIG is often chosen when those are unsuitable, have failed or would act too slowly.
Is this person safe to receive it? Kidney function, heart function, clotting history, previous reactions to blood products and any known IgA deficiency are checked, because each changes the risk calculation. Age and body size also shape how the infusion is planned.
What does success look like, and when will we review? Good teams set a marker in advance, such as fewer infections over a year, a platelet count above a safe threshold or measurable improvement in strength, and agree a point at which they will stop or change course if the marker is not met.
When you hear “we think you need IVIG,” those questions have already been asked. You are entitled to hear the answers.
Conditions treated with IVIG at a glance
The table below groups the main conditions by why IVIG is used and what the team watches. It is an orientation aid, not a treatment menu; eligibility for each row is decided individually, and other treatments are often used first or alongside.
| Condition | Why IVIG is used | Typical pattern | What teams monitor |
|---|---|---|---|
| Primary antibody deficiency | Replace missing IgG | Ongoing, repeated infusions | Infection frequency, IgG trend, lung health |
| Secondary antibody deficiency | Replace IgG lowered by illness or treatment | Ongoing while the deficiency persists; reviewed | Infections, IgG trend, cause of deficiency |
| Guillain-Barré syndrome | Shorten the immune attack on nerves | Single hospital course | Strength, breathing, swallowing |
| CIDP | Control ongoing nerve inflammation | Course, often repeated | Strength, sensation, walking |
| Immune thrombocytopenia | Rapid but temporary platelet rise | Short course when bleeding or urgency | Platelet count, bleeding signs |
| Kawasaki disease | Calm blood vessel inflammation early | Single course early in illness | Fever, heart ultrasound |
Two patterns stand out. The top two rows describe replacement, where the goal is steady protection and the measure of success is what does not happen: the pneumonia that never develops, the hospital admission avoided. The lower rows describe immunomodulation, where the goal is a visible turn in an active disease and the team expects to see change within days to weeks.
Notice also how often IVIG shares its row with alternatives. Plasma exchange sits beside it for Guillain-Barré syndrome and CIDP in both NHS and Mayo Clinic guidance; corticosteroids are frequently the first choice in CIDP and ITP. Being offered IVIG rarely means it is the only option. It means your team has weighed the alternatives and, for your situation, judged this the better fit.
Who should not have IVIG, and who is asked to wait
“Who should not have IVIG” is a question specialists take seriously, and the honest answer has two layers: absolute barriers, which are rare, and situations that call for caution, delay or a different formulation.
The clearest barrier is a history of anaphylaxis, a rapid whole-body allergic reaction with breathing difficulty and a drop in blood pressure, to immunoglobulin products. It is uncommon, but people with selective IgA deficiency who have developed antibodies against IgA are at higher risk, because trace IgA in most preparations can trigger the reaction. Teams screen for this and may choose a low-IgA product or a different route under close observation.
Kidney disease prompts caution. MedlinePlus carries a prominent warning that IVIG can cause kidney dysfunction, acute kidney injury and, rarely, kidney failure, with higher risk in people who already have impaired kidneys, diabetes, dehydration, advanced age or other kidney-stressing medicines. That does not always mean no; it may mean a slower infusion, a different product, more fluids and closer blood tests.
Clotting risk is the other headline warning. IVIG thickens the blood temporarily and has been linked to clots in veins and arteries, including strokes and heart attacks in vulnerable people. A history of clots, heart disease, prolonged immobility or estrogen use makes the team weigh things carefully.
People are asked to wait, rather than refused, in several everyday scenarios: an active infection with fever on infusion day, dehydration, a recent live vaccine, or a diagnosis still being confirmed. Waiting can also mean trying a lower-risk alternative first. Pregnancy is not a barrier in itself; IVIG is used in pregnancy when needed, with the obstetric team involved.
None of these judgments can be made from a list. If any applies to you, raise it before the first infusion so the plan can be shaped around it.
IVIG vs SCIG: what the choice is really about
SCIG stands for subcutaneous immunoglobulin, the same antibody product delivered into the fatty tissue under the skin, usually of the abdomen or thigh, through a small needle and a pump. The IVIG vs SCIG choice is mainly relevant to replacement therapy, because immunomodulation for conditions like Guillain-Barré syndrome requires a large amount delivered quickly, which only a vein can handle.
The trade-offs are practical rather than about which is “better.” Intravenous delivery gives a large amount in one sitting on a cycle of a few weeks, so it suits people who prefer infrequent appointments, would struggle with needles at home or need levels raised quickly. The pattern is a peak straight after infusion and a slow decline before the next one; some people notice tiredness or more infections in the final week of the cycle, the so-called wear-off.
Subcutaneous delivery uses smaller amounts more often, commonly on a weekly rhythm according to NIAID, producing a steadier level without peaks and troughs. Because it bypasses the bloodstream initially, whole-body reactions such as headache and chills are less frequent, and it can be done at home after training. The cost is local: swelling, redness and itching at the needle site are common, though they usually fade within a day or two, and some people dislike the routine of frequent self-infusion.
Who tends toward each? People with difficult veins, previous systemic reactions to IVIG or a wish for independence from clinic schedules often lean subcutaneous. Those with kidney concerns may be steered that way too, because smaller, steadier amounts are gentler on the kidneys. People who value a monthly rhythm and dislike self-injection often stay intravenous. Children’s teams weigh family routines heavily.
Switching in either direction is common and reversible. The right question is not which route is superior but which fits your life, your veins and your risk profile.
How long do you stay on IVIG?
The answer splits cleanly along the line drawn earlier. For replacement, the honest expectation is long term, often lifelong, because the underlying deficiency does not go away. A person with common variable immunodeficiency who stops replacement usually sees IgG fall back within weeks and infections return. That said, “long term” is not “unreviewed.” Immunologists typically reassess at least yearly, checking infection records, IgG trends, lung function and quality of life, and adjusting the plan.
Secondary deficiency can be different. If the cause resolves, for instance once a treatment that depleted B cells has worn off and antibody production recovers, some people can stop under supervision. Teams may pause replacement in a low-infection season and watch whether infections reappear. That is a legitimate strategy, but only with the prescriber’s guidance and a plan for what happens if illness returns.
For acute autoimmune conditions, the stay is short. Guillain-Barré syndrome is usually a single course over several consecutive days in hospital, as the NHS describes; the nerves then recover on their own timetable, which Mayo Clinic notes is often measured in months. Kawasaki disease is likewise generally a single course, with a second considered only if fever persists. Immune thrombocytopenia may need one course or intermittent courses at moments of bleeding risk, because the platelet rise fades within weeks.
CIDP sits in between. Because the inflammation is chronic, many people need repeated courses at intervals set by their neurologist, and specialists periodically test whether the condition has gone quiet by spacing infusions out or pausing them. A relapse after a pause is information, not failure; it tells the team that treatment is still doing work.
Whatever your condition, ask two things early: what marker tells us this is working, and what would prompt us to stop? Those answers frame the timeline better than any general figure.
Is IVIG a high-risk medication?
Yes and no, and both halves matter. IVIG carries boxed warnings on its US labeling for blood clots and kidney injury, which places it among medicines requiring careful patient selection and monitoring. At the same time, it has been used for decades, is a purified human protein rather than a synthetic drug with unfamiliar chemistry, and most infusions pass with nothing worse than a headache. Holding both facts at once is the accurate position.
Common effects are mostly infusion-related: headache, chills, fever, flushing, nausea, muscle aches, tiredness and mild blood pressure changes. They tend to occur during or within a day of the infusion, respond to slowing the drip, and become less frequent as the team learns your tolerance.
Less common but important effects include aseptic meningitis, an inflammation of the lining of the brain not caused by infection, which produces severe headache, stiff neck and light sensitivity, typically within a couple of days; hemolysis, the breakdown of red blood cells, more likely in people with certain blood groups receiving larger amounts; skin reactions; and transient rises in liver tests. Rarely, IVIG can cause fluid overload in people with heart or kidney weakness.
The serious rare risks are the ones on the warning label. Kidney injury has historically been linked to certain stabilizers in older formulations and to dehydration, and is watched with blood tests. Clots can occur in the legs, lungs, brain or heart, particularly in older people, those with prior clots or those who are immobile. Anaphylaxis is rare and most associated with anti-IgA antibodies.
Because IVIG is made from human plasma, there is a theoretical risk of transmitting infection. MedlinePlus notes that donor screening, testing and manufacturing steps make this risk very small, though no plasma product can be called zero-risk.
So the risk is real, mostly manageable, and concentrated in the first infusions and in people with existing kidney, heart or clotting vulnerabilities. That is precisely why the selection questions exist.
The days and weeks after an IVIG infusion
The first day or two after an infusion is the window for most delayed effects. A dull headache is the most frequent, sometimes with fatigue and low-grade achiness that people compare to the day after a flu shot. Fluids, rest and any simple pain reliever your team has agreed to are usually enough. A severe headache with neck stiffness or light sensitivity is different and belongs in the red-flag section below.
Over the first week, teams sometimes repeat blood tests, especially after early infusions, checking kidney function and, where relevant, red cell counts. For autoimmune uses, this is also when the target marker starts to move: a platelet count may climb within days in immune thrombocytopenia, while nerve conditions change more slowly, with strength returning over weeks to months as the nerve coating repairs.
For replacement, the weeks between infusions have their own rhythm. IgG peaks after the infusion and drifts down before the next one. Some people notice more colds or lower energy in the final days of the cycle; that pattern is worth recording, because it can inform a change in interval or route. Trough levels, meaning the IgG measured just before the next infusion, are one tool immunologists use to judge whether the plan is adequate.
Practical points for the weeks ahead: keep a simple diary of infections, temperatures and any reactions alongside each infusion date; tell any clinician who orders a vaccine or a blood test that you receive immunoglobulin, because donor antibodies can distort some test results. Live vaccines such as measles-mumps-rubella and chickenpox are usually delayed for many months after IVIG, since donor antibodies can neutralize them; your team will give the specific interval.
Recovery after an acute autoimmune course is a longer arc. Mayo Clinic notes that recovery from Guillain-Barré syndrome commonly takes months and involves rehabilitation; IVIG shortens the attack but does not do the rebuilding. Physiotherapy, sleep and a gradual return to activity are part of the treatment, not an afterthought.
What people often get wrong about IVIG
“IVIG boosts the immune system.” Not quite. Replacement tops up one missing component; it does not strengthen a healthy immune system, and it would not help someone with normal antibody levels fight colds. For autoimmune conditions its job is closer to the opposite, quieting an overactive response. The word “boost” leads people to request it for fatigue or frequent minor viruses, where the evidence does not support it.
“It is a one-time fix.” Only sometimes. Guillain-Barré and Kawasaki disease are usually single courses; replacement therapy is ongoing; CIDP and ITP fall in between. Expecting a single infusion to settle a lifelong deficiency sets people up for disappointment.
“It is basically a blood transfusion.” It is a blood product, but a purified, pooled protein fraction, not whole blood or red cells. Blood group matching is not required the way it is for transfusion, although blood group does influence the small risk of hemolysis.
“If I feel worse after the first infusion, it is not working.” Infusion reactions and benefit are unrelated. Headache and chills on day one say nothing about whether infections will fall over the coming year or whether nerves will recover.
“Home infusion means it is safe enough not to worry.” Home programs are for people whose tolerance is established and who are trained to recognize reactions. The product is the same; the surveillance has moved, not disappeared.
“Everyone with low IgG should get it.” Low numbers without infections or poor vaccine responses are often monitored instead. Guidelines exist partly because IVIG is a finite resource made from donated plasma; using it where evidence is weak deprives someone whose need is proven.
“IVIG and SCIG are different medicines.” Same protein, different route. What changes is the rhythm of levels and the side-effect profile.
The thread through all of these is expectation. IVIG is a precise tool with a specific job in each condition, and understanding that job is the best protection against both false hope and unnecessary fear.
Questions to ask your care team before starting IVIG
Bring these to the appointment where IVIG is first raised, and revisit the relevant ones at each review. Writing down the answers turns an abstract plan into something you can hold your team to.
- Which of my test results led you to recommend IVIG, and is the diagnosis confirmed or still being clarified?
- Is this replacement for something I lack, or is it meant to calm an immune attack? What does that mean for how long I will need it?
- What alternatives did you consider, and why is IVIG the better fit for me now?
- What will tell us it is working, and when will we check?
- What would make you stop or change the plan?
- Given my kidneys, heart, clotting history and any previous reactions, what specific precautions will you take?
- Should I have blood tests before or after infusions, and what are they looking for?
- How should I prepare for infusion day, including fluids, food and my usual medicines?
- Which reactions are expected and manageable, and which mean I should call immediately?
- Is subcutaneous immunoglobulin an option for me, now or later, and what would that involve?
- Could home infusion be appropriate, and what training and support would come with it?
- How does this affect vaccines, including live vaccines, and any surgery or dental work I have planned?
- Who do I contact between appointments, and out of hours?
A few of these have uncomfortable answers, particularly the ones about stopping. Ask them anyway. Teams who are confident in the decision welcome the questions, and teams who are uncertain should say plainly that the evidence is thin in your situation. Either way, you leave with a shared understanding of why the treatment is being offered, which is the best foundation for a plan you can stick with and speak up about when something changes.
When to call your doctor
Most IVIG reactions are mild and settle with slowing the infusion or resting afterward. A small number are emergencies, and knowing the difference is part of being on this treatment.
Call emergency services or go to the nearest emergency department immediately, during or after an infusion, for: difficulty breathing, wheezing, or swelling of the face, lips or throat, which can signal anaphylaxis; chest pain or pressure, or a racing, irregular heartbeat; sudden weakness or numbness on one side of the body, facial droop, slurred speech, confusion or loss of vision, which can indicate a stroke or clot; a swollen, painful, warm leg or arm, or sudden breathlessness with sharp chest pain on breathing, which can indicate a clot in a limb or lung; a severe headache with neck stiffness, vomiting or sensitivity to light, especially within two days of an infusion, which can indicate aseptic meningitis.
Contact your care team the same day for: passing much less urine than usual, dark urine, ankle swelling or sudden weight gain, which can point to kidney strain or fluid overload; fever above the threshold your team has set, or any fever if you have antibody deficiency, since infections can move quickly when defenses are low; yellowing of the skin or eyes, or unusual paleness and tiredness, which can suggest red cell breakdown; a widespread rash, hives or blistering; and any reaction that is worse than your previous infusions, even if you cannot name it.
Between infusions, people on replacement therapy should have a low threshold for calling about a cough that is not clearing, sinus pain that keeps returning or any infection not responding as expected. People treated for nerve conditions should report new or worsening weakness, trouble swallowing or breathlessness lying flat, which can mean the condition is progressing and needs urgent review.
Keep the team’s contact details, including out-of-hours numbers, where you and the people you live with can find them. Every decision about continuing, pausing or changing IVIG belongs to your treating team; your job is to give them accurate, timely information so they can make it well.
Frequently asked questions
What qualifies you for IVIG?
You qualify when a specialist confirms a condition where IVIG has strong evidence and judges that benefit outweighs risk. For antibody deficiency, that means low IgG plus a poor response to vaccination and a history of infections causing harm. For autoimmune conditions such as Guillain-Barré syndrome, CIDP, immune thrombocytopenia or Kawasaki disease, it means a confirmed diagnosis with active disease where alternatives are unsuitable or too slow. The treating team makes the final decision.
How long do you stay on IVIG?
It depends on why you receive it. Replacement for primary immunodeficiency is usually long term, often lifelong, because the underlying deficiency persists, though plans are reviewed regularly. Guillain-Barré syndrome and Kawasaki disease are typically single courses. CIDP often needs repeated courses over months or years, with periodic attempts to space them out. Immune thrombocytopenia may need intermittent courses because the platelet rise is temporary. Ask your team what marker will guide stopping.
Who should not have IVIG?
The clearest barrier is a previous severe allergic reaction to immunoglobulin products, which is more likely in people with IgA deficiency who have antibodies against IgA. Significant kidney disease, a history of blood clots, heart failure and dehydration all call for caution, slower infusion or a different product rather than an automatic no. People with active fever, a recent live vaccine or an unconfirmed diagnosis are often asked to wait. Your team weighs each factor individually.
Is IVIG a high-risk medication?
IVIG carries boxed warnings for blood clots and kidney injury, so it is treated as a medicine requiring careful selection and monitoring. In practice most infusions cause only mild effects such as headache, chills or fatigue that settle by slowing the drip. Serious reactions, including anaphylaxis, aseptic meningitis and clots, are uncommon and concentrated in people with existing kidney, heart or clotting vulnerabilities, which is why those are checked beforehand.
What is the difference between IVIG vs SCIG?
They are the same antibody product delivered by different routes. IVIG goes into a vein in larger amounts every few weeks, creating a peak and a gradual decline. SCIG goes under the skin in smaller, more frequent amounts, often at home, producing steadier levels with fewer whole-body reactions but more local swelling and redness. The choice for replacement therapy depends on your veins, reaction history, kidney health and lifestyle; acute autoimmune conditions generally require the intravenous route.
Does IVIG boost the immune system?
Not in the everyday sense. For people with antibody deficiency, IVIG replaces a missing component so they can recognize germs they otherwise could not; it does not strengthen a healthy immune system. For autoimmune conditions, its role is closer to the opposite, dampening an immune attack directed at the body’s own tissues. It is not supported as a general remedy for fatigue, frequent colds or general wellness in people with normal antibody levels.
How long does an IVIG infusion take?
MedlinePlus describes IVIG infusions as lasting several hours. First infusions are usually the longest because nurses start slowly and increase the rate in steps only if you feel well, since most immediate reactions are linked to speed. Later infusions often run faster once your tolerance is known. Allow a full day for the appointment, including baseline checks, blood tests, observation afterward and paperwork recording the product batch.
Can I have vaccines while on IVIG?
Most non-live vaccines can be given, though people with antibody deficiency may not respond to them well, which is one reason they need replacement. Live vaccines such as measles-mumps-rubella and chickenpox are usually delayed for many months after IVIG because the donor antibodies can neutralize the vaccine virus and blunt the response. Always tell whoever is giving a vaccine that you receive immunoglobulin, and follow the interval your treating team specifies.
Is IVIG used during pregnancy?
Yes, when a clear indication exists. Pregnancy is not in itself a reason to avoid IVIG, and it is used for conditions such as immune thrombocytopenia and ongoing replacement therapy for antibody deficiency. Decisions are shared between the specialist and the obstetric team, with attention to hydration, kidney function and clot risk, which is already higher in pregnancy. As with any treatment in pregnancy, the prescribing clinician weighs the specific situation.
Does IVIG work for Guillain-Barré syndrome?
The NHS and Mayo Clinic list IVIG as one of the two main treatments for Guillain-Barré syndrome, alongside plasma exchange, and describe them as broadly equivalent in effect. Treatment aims to shorten the immune attack on the nerves while it is active, and is usually given as a single course over several days in hospital. Recovery of strength then follows the nerves’ own timetable, which Mayo Clinic notes is often measured in months and typically involves rehabilitation.
References
- Immune Globulin Intravenous (Human) Injection: MedlinePlus Drug Information
- Immunodeficiency disorders: MedlinePlus Medical Encyclopedia
- Guillain-Barré syndrome: Treatment, NHS
- Kawasaki disease: Treatment, NHS
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Hysterectomy Recovery: Two Weeks, Three Months, Walking and Driving
Most people need 2 to 6 weeks to recover from a hysterectomy, depending on how it was done. Vaginal or laparoscopic surgery typically allows…

Constipation After Surgery: Why It Happens and Safe Ways to Get Moving Again
Constipation after surgery is common and usually temporary. Anesthesia, opioid pain relievers, less movement, and disrupted eating all slow the bowel; most people pass…

Weight-Bearing Status Explained: NWB, PWB, TTWB and WBAT
Weight-bearing status describes how much of your body weight an injured or surgically repaired leg may carry. Non-weight bearing (NWB) means none at all;…

Itching After Surgery: Why Healing Itches and What Is Safe to Do About It
Itching after surgery is usually a normal part of healing. Histamine released during tissue repair and regrowing nerve endings both trigger the sensation, which…
Hyperbaric Oxygen Therapy Side Effects: Ear Pressure, Sinus Discomfort and Tiredness
The most common hyperbaric oxygen therapy side effects are ear pressure or pain from the changing air pressure, sinus discomfort, tiredness after a session,…

How Long Conjunctivitis Lasts and When It Is Contagious
Viral pink eye, the most common kind, usually clears on its own in about 7 to 14 days, though some cases linger for two…