

Are You Stone-Free After Laser Lithotripsy? What Follow-Up Imaging Checks and Why It Matters

Key Takeaways
- Stone free means no fragments on follow-up imaging, and surgeons disagree on whether tiny "clinically insignificant" pieces count, which is why published rates vary so much.
- Dusting deliberately leaves fine powder to pass after surgery, so a follow-up scan is standard practice rather than a sign that something went wrong.
- Non-contrast CT detects fragments that plain X-ray and ultrasound can miss, so the test used largely determines whether you are called clear.
- Uric acid stones are invisible on plain X-ray, so a normal KUB does not rule them out and CT or ultrasound is needed instead.
- Most residual fragments cause no symptoms, and a kidney can lose function behind a slow, painless blockage, which is the main argument for imaging people who feel fine.
- A confirmed clear scan is the baseline for future surveillance and the trigger for stone analysis and, where indicated, a metabolic workup to prevent recurrence.
Being stone free after laser lithotripsy means no fragments remain in the kidney or ureter on follow-up imaging, not just that the surgeon saw a clear field at the end of the operation. Urologists usually confirm this with an ultrasound, a plain abdominal X-ray or a low-dose CT scan several weeks after surgery, because leftover fragments can grow, block urine flow or seed a new stone. Your treating team decides which test and when.
The discharge paperwork says the procedure went well. The surgeon, still in scrubs, said the stone “broke up nicely.” And yet, three weeks later, sitting in the car outside the imaging center, a lot of people find themselves asking a quieter question: is it actually gone?
That question is the whole point of follow-up imaging. Whether you are truly stone free after laser lithotripsy is not something anyone can settle in the operating room. A laser turns a stone into pieces, and some of those pieces are smaller than a grain of table salt. They hide in the lower pole of the kidney, behind a swollen ureter wall, or in a cluster of dust that looks like nothing on a camera screen but shows up plainly on a scan.
This guide walks through what surgeons mean by “stone free,” which tests they use to check, why timing matters, and what the answer changes about your next few months.
What does "stone free after laser lithotripsy" actually mean?
Ask three urologists to define stone free and you may get three answers. Some mean no visible fragment of any size on a CT scan. Others accept fragments under a certain size, often described as “clinically insignificant,” on the reasoning that very small pieces usually wash out on their own. The research literature is candid about this inconsistency, which is one reason published success figures for laser procedures vary so widely between studies.
For you as a patient, the practical definition is simpler. Stone free means your follow-up imaging shows nothing left that could grow, cause pain, block the flow of urine or act as a nucleus for a new stone. A fragment is a fragment; the debate is about which ones matter.
Laser lithotripsy, in plain terms, is a procedure in which a thin telescope called a ureteroscope is passed through the bladder and up the ureter to the stone, and a laser fiber is used to break the stone apart. No incision is involved. The ureter is the tube that carries urine from each kidney to the bladder.
Why does the definition matter so much? Because residual fragments are the main reason people return with a second episode of pain or a repeat procedure. The National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) notes that ureteroscopy is often chosen precisely because the surgeon can see and remove fragments, yet the same source is clear that stones commonly recur and that ongoing follow-up is part of care. Confirming a clear kidney is the first step in that follow-up, not an optional extra.
How laser lithotripsy works: dusting, fragmenting and basketing
Picture a stone the size of a pea sitting in a space no wider than a drinking straw. The surgeon threads a flexible scope up to it, and a hair-thin laser fiber is advanced until its tip nearly touches the stone. When the laser fires, energy is absorbed at the stone surface, creating tiny bursts of vapor and pressure that crack the crystal structure. Repeat this thousands of times and the stone comes apart.
There are two broad strategies, and they matter for the stone-free question.
- Fragmenting and basketing. The laser breaks the stone into a handful of chunks, each small enough to be caught in a tiny wire basket and pulled out through the scope. The upside is that what comes out is gone for certain. The downside is time, and the risk that some chunks are too small to grab yet too large to pass comfortably.
- Dusting. Lower energy, faster pulses turn the stone into fine powder that is meant to flush out with urine over the following days. It is quicker in the operating room, but by design it leaves material behind at the end of surgery, and dust can settle in the lower kidney and clump.
Most surgeons use a mixture, dusting the bulk and basketing anything that remains visible. Mayo Clinic describes ureteroscopy as breaking the stone into pieces “that will pass in your urine,” which is an honest summary: some clearing is expected to happen after you go home.
The laser choice, and whether the lower pole of the kidney is involved, influence how much dust is left. None of that is a judgment on the surgeon. It is simply the physics of breaking rock inside a living organ, and it is exactly why imaging afterward is standard rather than a sign that something went wrong.
Why the surgeon's view at the end of surgery is not the final word
At the end of the operation the surgeon looks around the kidney with the scope and, ideally, sees clear pink tissue and no fragments. That inspection is valuable. It is also limited, for reasons that have nothing to do with skill.
The kidney’s collecting system is a branching set of cups called calyces, and a flexible scope cannot always reach into every one, especially the lower pole, which sits at a sharp angle. Irrigation fluid used during surgery clouds with dust and blood, so visibility drops precisely when the stone has just been broken. Fragments displaced into a calyx during treatment can be out of the camera’s line of sight entirely.
Then there is scale. A fragment of one to two millimeters is roughly the size of a sesame seed. On a screen showing a magnified, moving image, that is easy to miss. On a CT scan, which detects stones by their density rather than their appearance, it is usually obvious.
Studies comparing the surgeon’s stated impression with later imaging consistently find that a portion of patients declared clear in the operating room have fragments on follow-up. The size of that gap varies with the imaging used, which is a theme throughout this article: the more sensitive the test, the more residual stone it finds.
This is not a reason for alarm. A small residual fragment is often left deliberately because chasing it would mean more time under anesthesia and more trauma to the ureter. It is a reason to take the follow-up appointment seriously, and to ask your team which test they are using to make the call.
Which imaging checks confirm you are stone free after laser lithotripsy?
Three tests do most of the work, and each has a distinct trade-off between accuracy, radiation and convenience. Your surgeon will weigh those against your stone type, your kidney anatomy and how much residual stone was expected.
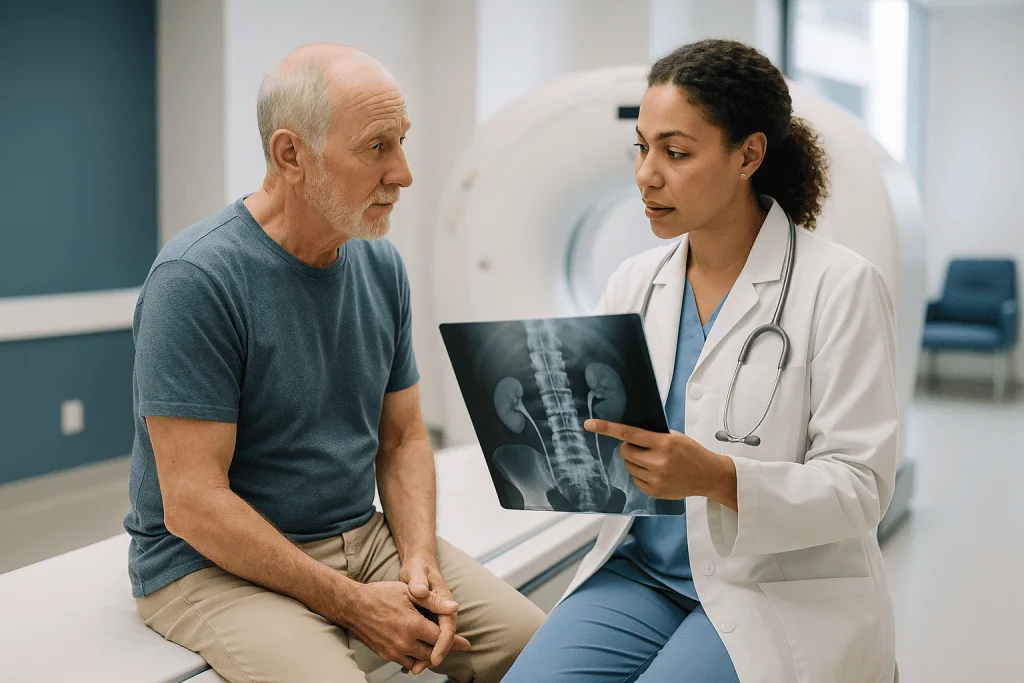
| Test | What it shows well | What it can miss | Radiation |
|---|---|---|---|
| Kidney ultrasound | Fluid build-up (hydronephrosis), larger stones, kidney shape | Small fragments; stones in the mid-ureter | None |
| Plain abdominal X-ray (KUB) | Calcium-containing stones, position of a stent | Uric acid stones (invisible on X-ray); tiny fragments; stones hidden by bowel gas | Low |
| Low-dose non-contrast CT | Nearly all stone types and sizes, exact location | Very little; it is the reference standard | Moderate, reduced with low-dose protocols |
Mayo Clinic lists all three among the imaging tests used to evaluate kidney stones and notes that CT can reveal even tiny stones while simple X-rays can miss small ones. That single fact explains most of the variation in published stone-free rates: an X-ray-based follow-up will call more people clear than a CT-based one, because it sees less.
Ultrasound is attractive because it involves no radiation, which is why it is often the first choice for children, for pregnant patients and for people who have already had several scans. Its weakness is that it can label a kidney clear while a small fragment sits undetected, and it struggles with the middle stretch of the ureter.
The pairing many teams use is ultrasound plus a plain X-ray, reserving CT for cases where the answer genuinely changes management: a stone type that does not show on X-ray, persistent symptoms, or a plan to stop follow-up altogether. The choice is your urologist’s, and it is a fair question to ask why one test was picked over another.
When is follow-up imaging usually done, and what happens if a stent is in place?
Timing is a balance. Scan too early and you photograph dust that was always going to wash out, which may lead to an unnecessary second procedure. Scan too late and a fragment that was quietly blocking a ureter has had weeks to swell the kidney above it.
Most urologists schedule imaging a few weeks after surgery, often timed with or shortly after stent removal, so that any fragments still present have had a chance to pass. A ureteral stent is a soft plastic tube placed from the kidney to the bladder to keep the ureter open while swelling settles; NIDDK describes it as a temporary measure that the urologist removes at a later visit. Your own interval is set by your team based on the stone burden, your anatomy and any symptoms you report.
If a stent is still in when you are scanned, the X-ray will show it clearly, which is useful for confirming position. It also means dust and small fragments may still be held up around the stent, so a truly definitive “clear” reading often waits until the stent is out and you have had a couple of weeks of unobstructed drainage.
A few situations shift the timing earlier:
- New or worsening flank pain that does not settle with the measures your team advised.
- Fever, which raises concern for infection behind a blockage.
- A single kidney, a transplanted kidney or reduced kidney function, where even brief obstruction carries more weight.
The kidney itself, by contrast, is a patient healer. Mild bruising of the ureter lining from the scope typically settles over days to a few weeks, which is the window most teams describe when they talk about kidney healing after lithotripsy. Reassurance on that point does not remove the need for the scan; it just means the scan is about stone, not damage.
What the first days and weeks usually look like
The first two days are usually the most uncomfortable, and mostly because of the stent rather than the kidney. Expect urgency, the sensation of needing to urinate often, a dull ache in the flank when the bladder empties, and pink or rust-colored urine. Mayo Clinic notes that people may have blood in the urine and mild pain after ureteroscopy, and that these typically settle.
By the end of the first week most people are back to desk work and light activity. The urine clears, though it may briefly turn pink again after exertion or when a fragment passes. Gritty sediment in the toilet is normal and is, in a real sense, the point of the procedure.
The stent-removal visit, whether at days or a few weeks depending on your surgeon’s plan, is a turning point. Removal takes seconds if a string was left attached, or a few minutes with a small camera in the clinic if not. The stent symptoms usually fade within a day or two afterward, and many people describe this as the moment they “feel like themselves.”
Weeks two to six are when residual dust and fragments do most of their passing, and when the follow-up scan is typically arranged. Hydration matters here. Mayo Clinic advises drinking enough fluid to pass about 2 liters (roughly 2.1 quarts) of urine a day for people prone to stones, both to help flush fragments and to dilute the urine that forms new ones.
Healing of the ureter lining, and of the kidney tissue if the scope was passed into the kidney, is largely complete within this window in uncomplicated cases. If your team has asked you to avoid strenuous exercise or heavy lifting for a period, that is usually about bleeding risk and stent movement rather than a fragile kidney.
How long does it take for stone fragments to pass after lithotripsy?
The honest answer is: it depends on the size of what was left, where it sits and how your ureter behaves. Fine dust often clears in the first few days. Fragments of a millimeter or two typically follow over the next several weeks. Pieces at the upper end of what surgeons consider passable can take longer, and some never move at all, which is the scenario the follow-up scan is designed to catch.
The NHS, describing stones generally, notes that small stones usually pass in urine and that larger ones are the ones needing intervention; the same logic applies to fragments after a laser procedure. Location matters as much as size. A fragment already in the ureter has a short, gravity-assisted route. A fragment in the lower pole of the kidney has to be lifted uphill by urine flow before it can even begin the journey, which is why lower-pole dust is the classic reason a scan shows residual stone weeks later.
Several factors that you can partly influence:
- Fluid intake. Higher urine volume increases the chance that dust is carried out rather than settling.
- Movement. Ordinary walking and changes of position help fragments shift out of dependent calyces. Some teams suggest specific positioning; follow their advice rather than anything read online.
- The stent. While it is in place, the ureter is held open, which often helps fragments pass, though dust can also cling to it.
What you cannot influence is the kidney’s anatomy or a fragment’s exact shape, and no amount of water will move a piece that is wedged. That is why a scan, not a calendar, decides whether you are clear. If several weeks have passed and you still see sediment, that is not a failure; it is information for your team.
Is it painful to pass fragments after laser lithotripsy?
Often it is far less painful than the original stone, and sometimes it is not noticed at all. The stone that brought most people to the emergency department was a solid object stretching the ureter. Dust and small fragments, by contrast, tend to travel with urine rather than plugging the tube.
That said, three sources of discomfort are common in the weeks after a laser procedure, and it helps to tell them apart.
The first is the stent itself: bladder irritation, urgency and a flank ache with urination. This is a foreign-body sensation rather than a stone passing, and it typically resolves within a day or two of removal.
The second is a fragment moving through the ureter. This can produce a wave of cramping in the side that radiates toward the groin, lasting minutes to a couple of hours, sometimes with a fresh tinge of blood in the urine. It usually settles once the fragment drops into the bladder. Mayo Clinic describes this pattern of fluctuating pain for stones in general.
The third is inflammation of the ureter lining from the scope, which feels like a low-grade soreness rather than colic and fades as the tissue heals.
Pain relief after these procedures is usually managed with medicines from the anti-inflammatory and simple analgesic classes, and some urologists prescribe an alpha-blocker, a class of medicine that relaxes the smooth muscle of the ureter, to ease fragment passage. Whether any of these is right for you, and for how long, is a decision for your prescribing clinician; do not adjust anything on your own.
Pain that is severe, unrelenting or paired with fever is a different matter entirely, and it is covered in the red-flag section below. The rule of thumb many teams give is that pain you can walk around with is expected, and pain you cannot is a phone call.
What not to do after laser lithotripsy
Most post-procedure instructions are about protecting the healing ureter, keeping a stent in place and making sure fragments leave rather than settle. The specifics come from your surgeon, but the themes are consistent across mainstream guidance.
- Do not let yourself run dry. Low urine volume lets dust settle and concentrates the salts that form new crystals. Aim for the fluid target your team gave you; Mayo Clinic’s general advice for stone formers is enough fluid to produce about 2 liters of urine daily.
- Do not ignore a fever. A raised temperature after urinary surgery can mean infection trapped behind a fragment or a stent, and it is not something to sleep on.
- Do not strain, lift heavy or take up vigorous exercise before your team clears you. Straining can provoke bleeding from the raw ureter lining and, if a stent string is present, can dislodge it.
- Do not pull a stent string yourself unless you were specifically instructed to, and on the date you were told. Early removal can leave the ureter to swell shut.
- Do not skip the follow-up scan because you feel fine. Fragments are frequently silent, and the kidney above a slow blockage can lose function without a single twinge.
- Do not start, stop or change any prescribed medicine on your own. That includes blood thinners, pain medicines and anything given to help fragments pass. Talk to the prescriber.
A common question is about alcohol, coffee and diet. There is no procedure-specific ban in mainstream guidance; the relevant point is that anything that dehydrates you works against fragment clearance, and that long-term dietary changes are best based on the stone analysis rather than guesswork. Send the fragments you catch to your team for analysis if they asked for them; that small jar shapes the prevention plan more than anything else.
Who is usually offered laser lithotripsy, and who is asked to wait?
Ureteroscopy with laser has become the workhorse treatment for stones that are too large or too stubborn to pass on their own but not so large that a keyhole operation through the back is needed. NIDDK lists it alongside shock wave lithotripsy and percutaneous nephrolithotomy as the main procedures, and notes that the choice depends on the stone’s size, location and composition.
People commonly offered laser lithotripsy include those with:
- Stones in the ureter that have not passed with time and medical management.
- Kidney stones of small to moderate size, particularly hard stones or those in a location where shock waves work poorly.
- Stones that failed to clear after shock wave lithotripsy.
- Anatomy or body habitus that makes external shock waves impractical.
- A need for certainty, for example airline pilots or people with a single kidney, where leaving fragments carries a higher cost.
Who is usually asked to wait, or offered something else?
- People with an active urinary infection. Operating on an infected system risks spreading bacteria into the bloodstream, so infection is treated first and the stone addressed later; a temporary stent or drain may be placed in the meantime.
- Those with a small stone likely to pass, for whom a period of observation with hydration and, where appropriate, medicine to relax the ureter is standard.
- People on blood-thinning medicines that cannot safely be paused, in whom ureteroscopy is often still possible but requires planning with the prescribing team.
- Those with a very large stone burden, for whom a percutaneous approach through the back may clear more stone in one sitting.
Shock wave lithotripsy, which breaks stones with focused sound waves from outside the body, remains an alternative for some stones, with the trade-off that it often needs more than one session and cannot remove fragments directly. Which route is right is a conversation, not a formula.
Residual fragments after ureteroscopy: watch, retreat or repeat?
So the scan shows something left. What happens next depends on three questions your urologist will be asking: how big is it, where is it, and is it doing any harm?
Small fragments in the kidney that are causing no symptoms and no obstruction are often watched. Many will pass unnoticed. Some will sit quietly for years. The risk of watching is that a fragment can slowly enlarge, since it offers a ready surface for new crystals, and that it may eventually move into the ureter and cause a fresh episode of colic. Surveillance imaging at intervals is the usual compromise, and its frequency is set by your team.
Fragments in the ureter are treated with more urgency, because anything in that narrow tube can block it. If a fragment is small and you are comfortable, a short period of observation with hydration is reasonable. If it is not moving, causing pain or associated with a swollen kidney on ultrasound, a second look with the scope is commonly offered.
Larger residual pieces in the kidney, or fragments in a lower-pole calyx that are unlikely to pass on their own, may prompt a planned second procedure. This is sometimes staged from the start when the stone burden was large, so a “second session” is not necessarily a sign that the first one failed.
Stone composition also steers the plan. Uric acid fragments, for example, do not show on plain X-ray and can sometimes be shrunk with measures that make the urine less acidic; that approach is prescribed and monitored by a clinician and is not something to attempt with supplements or diet alone. Calcium-based fragments respond only to mechanical removal or passage.
None of these decisions has a single right answer, and reasonable urologists differ. What should not vary is that you know the fragment exists, its approximate size and the plan for it.
What people often get wrong about being stone free
“The surgeon said it went well, so I’m clear.” A smooth operation and a clear kidney are related but not identical. The surgeon’s comment describes what happened in the room; the scan describes what is there afterward. Both are true and neither replaces the other.
“If I had fragments, I would feel them.” Most residual fragments are silent. Kidney stones cause pain when they block flow, not when they sit in a calyx. A kidney can lose function behind a slow, painless obstruction, which is the strongest argument for imaging people who feel fine.
“An X-ray is as good as a CT.” Mayo Clinic is explicit that simple abdominal X-rays can miss small stones and that CT may reveal tiny ones. An X-ray is a reasonable screening tool, especially for calcium stones, but a normal X-ray is not the same as a normal CT.
“Dust always washes out.” Much of it does. Dust that settles in the lower pole can clump into a fragment large enough to matter, particularly in people who drink little or have a dependent lower-pole anatomy.
“Once I’m stone free, I’m done.” NIDDK is direct that kidney stones often recur and that prevention depends on understanding why they formed. A clear scan closes one chapter and opens the prevention one: stone analysis, blood and urine tests where indicated, and dietary changes matched to the stone type.
“More water is always better.” Adequate urine volume is the single most useful habit, but extreme intake brings its own problems and does not move a wedged fragment. Aim for the target your team set.
“The laser type guarantees a better result.” Newer laser technologies have changed how surgeons dust stones, and the research is active, but no device removes the need for follow-up imaging, and none can be described as guaranteeing a clear kidney.
Why stone-free status matters beyond the next scan
It is tempting to treat the follow-up scan as an administrative box. It carries more weight than that, for three reasons.
First, obstruction. A fragment that slips into the ureter and lodges can back up urine into the kidney. The kidney tolerates this for a while, but prolonged blockage causes pressure damage, and blockage combined with infection is a genuine emergency. Knowing whether anything is left tells your team how alert to be about new symptoms.
Second, recurrence. Stones tend to form on existing stones. A residual fragment is a scaffold on which new crystals deposit, so the person with a fragment is, statistically, more likely to be back than the person with a clear kidney. NIDDK’s prevention guidance rests on the observation that stones commonly return, and residual fragments tilt the odds the wrong way.
Third, the prevention plan itself. A confirmed clear scan is the baseline against which future imaging is compared. If a scan two years later shows a 4 mm stone, it matters enormously whether the previous scan was clean (new stone, prevention not working) or showed a 2 mm fragment (old fragment growing, different conversation).
This is also the moment to ask about a metabolic evaluation. For people with recurrent stones, multiple stones, or stones at a young age, mainstream guidance supports blood tests and a 24-hour urine collection to look for the underlying drivers: high urinary calcium, low citrate, high oxalate or uric acid, low urine volume. Cleveland Clinic and NIDDK both describe this workup as the basis for tailored prevention, whether that is dietary change or, for some, a preventive medicine prescribed and monitored by a clinician.
Being stone free after laser lithotripsy, in other words, is not the end of treatment. It is the cleanest possible starting line for preventing the next one.
Questions to ask your care team
Bringing a short list to the follow-up appointment turns a five-minute check into a plan. These are the questions that tend to matter most.
- Which imaging test will confirm I am stone free, and why that one? If the answer is ultrasound or X-ray, ask what would prompt a CT.
- Was any stone or dust left deliberately at the end of surgery? Surgeons often make this choice for good reasons; knowing about it sets expectations for the scan.
- Where was the stone, and does that location tend to hold fragments? Lower-pole stones behave differently from ureteral ones.
- When will my stent come out, and what should I expect that day? Ask whether there is a string and who removes it.
- What symptoms should make me call before my scheduled appointment? Get specifics on pain, fever and bleeding.
- Did you send the stone for analysis, and when will I get the result? Composition steers everything downstream.
- Do I need a metabolic evaluation? Especially if this is not your first stone, or if you are young or have a family history.
- If a fragment is found, what are the likely options? Watching, a second scope and medical measures each have trade-offs worth hearing in advance.
- How often should I be imaged in future, and with what? Surveillance intervals vary; ask what yours will be and why.
- Are any of my current medicines relevant to stone risk? Some common prescriptions influence urine chemistry; the prescribing clinician is the person to review this with, not the internet.
Write the answers down. Stone care stretches over years, often across different clinicians, and the person who keeps the best record of their own imaging and stone analysis is the one whose future decisions are made on the best information.
When to call your doctor after laser lithotripsy
Most recovery is uneventful, and most symptoms are the expected nuisances of a stent and a healing ureter. A short list of signs, however, should prompt a same-day call to your urology team or, out of hours, a visit to urgent or emergency care. Do not wait for the scheduled scan.
- Fever or shaking chills. Infection behind a fragment or a stent can progress quickly to bloodstream infection. Any raised temperature after urinary surgery deserves prompt assessment.
- Severe flank or abdominal pain that does not ease with the measures your team advised, or pain that keeps you from sitting still. This may signal an obstructing fragment or a blocked stent.
- Inability to pass urine, or passing only small amounts despite a strong urge.
- Heavy bleeding: urine the color of red wine rather than pink, clots, or bleeding that worsens instead of clearing over the first days.
- Persistent nausea and vomiting that prevents you from keeping fluids down, which both dehydrates you and can indicate obstruction.
- A stent that has visibly moved, for example a string that has come out or a tube visible at the urethra.
- Symptoms of a kidney infection such as fever with back pain, especially if you have one kidney or reduced kidney function.
Mayo Clinic’s general advice for stone symptoms echoes these red flags: seek immediate care for pain so severe you cannot sit still, pain with nausea and vomiting, pain with fever and chills, blood in the urine, or difficulty passing urine.
Less urgent but still worth a call: pink urine that persists past the timeframe your team described, new pain that starts after the stent is removed, or fragments still appearing many weeks on. These are not emergencies, but they are information that may change the timing or type of your follow-up imaging, and every decision about that sits with your treating team.
Frequently asked questions
How long does it take for a kidney to heal after laser lithotripsy?
In uncomplicated cases the ureter lining and kidney tissue settle over days to a few weeks. Early symptoms such as pink urine and flank soreness mostly reflect the stent and minor bruising from the scope, and they typically ease within the first week or two. Full healing is usually assumed by the time follow-up imaging is done, though your surgeon sets the exact interval based on your procedure and any complications.
How long does it take for stone fragments to pass after lithotripsy?
Fine dust often clears within days, while small fragments commonly pass over the following several weeks. Larger or lower-pole fragments may take longer or not move at all, which is what the follow-up scan is designed to detect. Hydration and ordinary movement help, but no timeframe is a guarantee, so imaging rather than the calendar decides whether you are clear.
What not to do after laser lithotripsy?
Avoid running short on fluids, ignoring a fever, heavy lifting or strenuous exercise before your team clears you, pulling a stent string on your own, and skipping the follow-up scan because you feel well. Do not start, stop or change any prescribed medicine without speaking to the prescriber. Most of these precautions protect the healing ureter and help fragments leave rather than settle.
Is it painful to pass stones after lithotripsy?
Usually far less than the original stone, and often unnoticed, because dust and small fragments travel with urine rather than blocking the ureter. A moving fragment can still cause a brief wave of cramping in the side that eases once it reaches the bladder. Severe, unrelenting pain, or pain with fever, is different and should prompt a same-day call to your care team.
What is the best imaging to confirm I am stone free after laser lithotripsy?
Non-contrast CT is the most sensitive test and is considered the reference standard, detecting fragments that X-ray and ultrasound can miss. Many urologists start with ultrasound plus a plain abdominal X-ray to limit radiation and reserve CT for when the answer would change management. The choice depends on your stone type, anatomy and symptoms, and it is your surgeon’s decision.
Can an ultrasound miss residual fragments after ureteroscopy?
Yes. Ultrasound is good at showing a swollen kidney and larger stones, but it can miss small fragments and struggles with stones in the middle of the ureter. Its advantage is that it involves no radiation, which makes it a sensible first check for many people. A normal ultrasound is reassuring but is not equivalent to a normal CT.
Why did my surgeon say the stone was cleared but the scan shows fragments?
The surgeon’s inspection at the end of surgery is limited by cloudy irrigation fluid, calyces the scope cannot reach and the tiny size of some fragments. Dusting also leaves powder behind by design. Studies consistently find a gap between operating-room impression and later imaging, so a fragment on the scan reflects the limits of visibility, not a mistake or a failed procedure.
What happens if I have residual fragments after ureteroscopy?
It depends on size, location and whether they are causing harm. Small, silent fragments in the kidney are often watched with periodic imaging. Fragments in the ureter, or those causing pain or blockage, may prompt a second scope. Some stone types can be managed medically under clinician supervision. Your urologist will explain the options, and the decision rests with your treating team.
Does kidney healing after lithotripsy mean I can go back to exercise?
Most people return to light activity within a week, but heavy lifting and vigorous exercise are usually held off until your team clears you, often after stent removal. The concern is bleeding from the healing ureter and stent displacement rather than a fragile kidney. Ask your surgeon for a specific timeline, since it varies with the procedure and your circumstances.
Will being stone free stop kidney stones from coming back?
No. A clear scan removes the scaffold on which new crystals form, which lowers risk, but kidney stones commonly recur. Prevention depends on knowing the stone type from analysis, adequate fluid intake, and for people with repeated stones a metabolic evaluation to identify the underlying cause. Your care team uses the clear scan as the baseline for that longer-term plan.
References
- NIDDK (NIH): Treatment for kidney stones
- NHS: Kidney stones, treatment
- Cleveland Clinic: Kidney stones
- MedlinePlus: Kidney stones
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Recovery After Phimosis Surgery: Wound Care, Loose Clothing and When Swimming Is Allowed
Recovery after phimosis surgery, most often a circumcision or a foreskin-widening procedure, typically takes about 10 days for the wound to knit and several…
Medication, Injections, Traction or Surgery: How a Peyronie’s Disease Plan Is Chosen
A Peyronie's disease plan is chosen mainly by timing and severity. During the active phase, when pain and curvature are still changing, clinicians usually…

Is a Fever After a Cystoscopy Normal? Which Symptoms Need a Same-Day Call to Your Urologist
A true fever after cystoscopy is not part of a normal recovery. Mild burning, pink-tinged urine and needing to pee more often usually settle…

Renal Tubular Acidosis in Children: How Growth and Treatment Are Monitored Over Time
Renal tubular acidosis in children is monitored with a repeating cycle of growth measurements, blood tests for bicarbonate and potassium, urine tests, and periodic…

Ureteral Stricture Repair Recovery: Living With the Stent and the Follow-Up Scans Ahead
Ureteral stricture surgery recovery usually unfolds in two stages: healing from the repair itself, then living with a temporary internal stent that splints the…

Recent Antibiotics, Kidney Disease or Allergies: How They Shape Acute UTI Treatment
Recent antibiotic use, reduced kidney function and drug allergies each narrow which antibiotics are likely to work safely for an acute urinary tract infection.…