

Before Ureteral Stricture Surgery: Treating Infection First, CT Urography and Kidney Checks

Key Takeaways
- A ureteral stricture blocks the tube between kidney and bladder, not the urethra, and advice written for urethral strictures does not apply.
- Operating on an infected, obstructed kidney can trigger urosepsis, which is why a positive urine culture can legitimately move a surgery date.
- A ureteral stent or nephrostomy tube drains the kidney and clears infection before repair, but it does not treat the stricture itself.
- CT urography measures the location and length of the narrowing in millimeters, and that measurement largely decides between an endoscopic and a reconstructive operation.
- A nuclear renal scan reports the share of work each kidney does, and a kidney that has lost most of its function may be discussed for removal rather than repair.
- The repair is only truly tested after the stent comes out, so follow-up imaging in the months afterwards is part of the treatment, not an optional extra.
Preparation for ureteral stricture surgery usually has three parts. Any urinary infection is identified with a urine culture and treated first, sometimes after placing a stent or drainage tube, because operating on an infected, blocked kidney raises the risk of sepsis. CT urography maps the narrowing. Blood tests and often a nuclear renal scan measure how well each kidney works, which shapes the surgical plan.
The appointment letter says the operation is on hold. Not cancelled, the nurse explains on the phone, just paused: the urine sample grew bacteria, and the surgeon wants that cleared before anyone touches the ureter. For a person who has spent weeks with a dull ache in one flank and a stent that reminds them of itself every time they stand up, another delay feels like a setback.
It is not. Ureteral stricture surgery preparation is where much of the safety of the whole procedure is decided. The ureter is the slim muscular tube, roughly the width of a drinking straw, that carries urine from each kidney to the bladder. When scar tissue narrows it, urine backs up and the kidney above it swells. Operating on that kidney while it is infected, or without knowing how much function it has left, turns a routine repair into a gamble.
So the pause is the plan. Here is what fills it, and why each step earns its place.
What a ureteral stricture is, and why ureteral stricture surgery preparation takes weeks
A stricture is a segment of scar tissue that has replaced the ureter’s normal stretchy wall. Scar does not relax the way muscle does, so urine has to squeeze through a fixed narrowing. Above that point the pressure rises, the ureter dilates, and the kidney’s collecting system balloons. Doctors call this swelling hydronephrosis, which means water inside the kidney, and it is the finding on a scan that usually starts the whole conversation.
Strictures have causes that matter for planning. Some follow a stone that sat in one spot for weeks. Others form after earlier ureteroscopy, pelvic surgery, radiation therapy, or a long stretch of inflammation. A small number are caused by something pressing on the ureter from outside, or by a growth within it, which is one reason imaging is never skipped. Mayo Clinic groups all of these under ureteral obstruction and notes that the treatment depends entirely on the cause, location and length of the block.
That dependence is why preparation is not a formality. A surgeon deciding between an internal telescope procedure and an open or robotic reconstruction needs three pieces of information: whether the urine is sterile, exactly where and how long the narrowing is, and how much the affected kidney still contributes. None of those can be assumed. Each is measured, and the measurements can change the operation, postpone it, or occasionally replace it with a different plan altogether.
Patients often describe this phase as waiting. Clinicians describe it as staging. The difference in language reflects a real difference in what is happening: the team is building the case for a specific repair, and a repair matched to the anatomy tends to hold up better than one chosen in a hurry.
Why infection has to be treated before any ureteral surgery
A blocked ureter and a urinary infection are each manageable on their own. Together they are one of the few genuine emergencies in urology. Urine trapped above a stricture is a warm, still pool where bacteria multiply. Instruments passed through that pool, or incisions made near it, can push bacteria into the bloodstream. The result can be urosepsis, the body’s overwhelming response to infection, which the CDC describes as a life-threatening medical emergency that can progress quickly.

This is why surgeons treat an infected, obstructed kidney as a two-stage problem. First, drain the pressure and clear the infection. Only then reconstruct the ureter. The logic is the same one plumbers use: relieve the backed-up system before you rebuild the pipe.
Infection is also bad for the tissue the surgeon is about to sew. Inflamed ureter is friable, bleeds easily and holds sutures poorly. Repairs made in that environment are more likely to leak or scar again. Waiting for the inflammation to settle gives the anastomosis, the point where two cut ends are joined, a better chance of healing as a smooth tube rather than another ring of scar.
There is a third reason that gets less attention. Antibiotics chosen without a culture are a guess. The urine culture grown before surgery tells the team which organism is present and which antibiotic classes it responds to. That information guides the single dose given at the start of the operation, a standard step across urological surgery, and it means the infection being treated is the one the patient actually has.
None of this is fear-marketing. It is the reason a positive urine result can move a surgery date, and why patients are asked to report fevers, chills or new flank pain in the days before an operation rather than waiting to mention them at the door.
How infection is found and cleared: urine culture, antibiotics and a ureteral stent before surgery
The process starts with a midstream urine sample sent for culture. A culture grows whatever bacteria are present over one to a few days and then tests them against antibiotics; MedlinePlus describes it as the standard way to confirm a urinary infection and identify the organism. A dipstick alone is not enough for surgical planning, because it cannot say which drug will work.
If the culture is positive, the treating clinician prescribes an antibiotic matched to the result. How long it is taken depends on whether the infection involves the bladder alone or has reached the kidney. NHS guidance on kidney infection describes courses that typically run from several days up to two weeks, with a repeat culture sometimes used to confirm clearance before elective surgery. The exact drug, dose and duration are the prescriber’s decision and vary with kidney function, allergies and local resistance patterns.
When the kidney is significantly blocked, antibiotics alone struggle to reach trapped urine. That is where drainage comes in. A ureteral stent is a soft, hollow plastic tube threaded up the ureter from the bladder, usually under a short anesthetic, so urine can bypass the narrowing. The alternative is a nephrostomy tube, a thin catheter placed through the skin of the back directly into the kidney under imaging guidance. Surgeons choose between them based on how tight the stricture is, whether a stent can pass, and how sick the person is.
Either device is temporary. Both can cause bladder irritation, urgency and a pink tinge to the urine, effects that are unpleasant but expected. What they buy is time: a decompressed, clean kidney, a culture that turns negative, and a ureter whose swelling has settled enough to be measured accurately. Many surgeons will not schedule definitive repair until those three boxes are ticked.
What the CT urography procedure shows and what actually happens during the scan
CT urography is a CT scan timed to catch iodine-based contrast dye as the kidneys filter it and pass it down the ureters. Mayo Clinic describes it as an exam that images the kidneys, ureters and bladder in one sitting, used to look for blockages, stones, scarring and growths. For stricture planning it answers the questions a surgeon cannot answer with an ultrasound: where exactly does the narrowing start, how long is it, and is anything outside the ureter causing it?
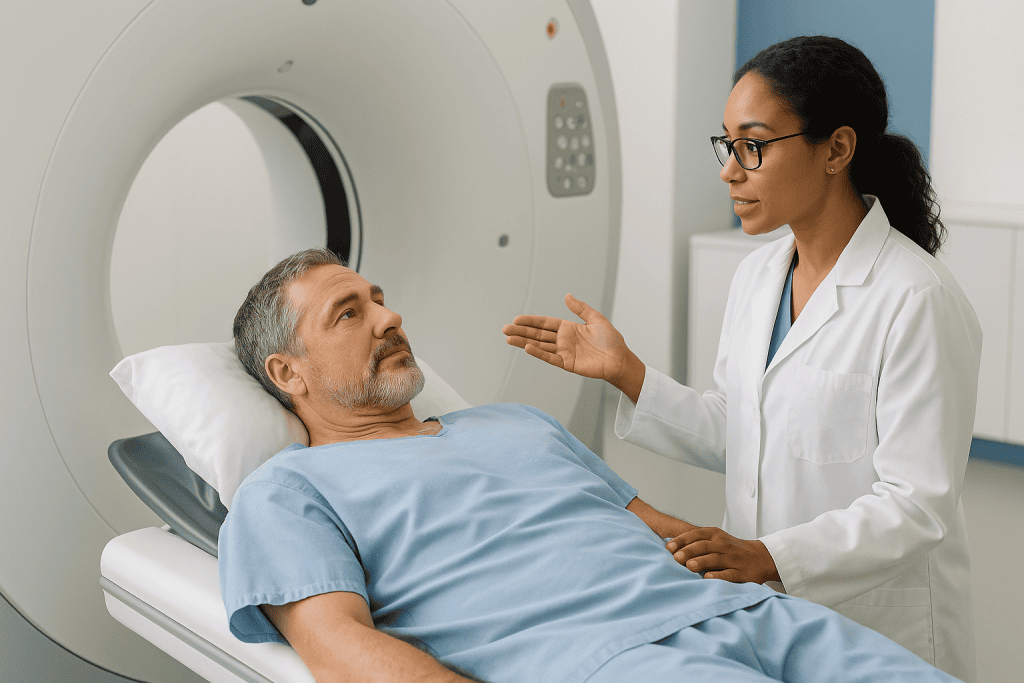
On the day, a small cannula is placed in a vein. The first pictures are taken without contrast, which shows stones and calcification. Contrast is then injected; most people feel a brief warm flush and sometimes a metallic taste. Further scans follow at set intervals, including a delayed phase, often several minutes later, when the dye has reached the ureters and outlines them from inside. Lying still on the table for the whole appointment is the main effort required.
Because the dye is cleared by the kidneys, a recent blood creatinine result is usually required before the scan. People with reduced kidney function, a previous contrast reaction, or who take certain diabetes medicines are flagged in advance, and the radiology team decides whether to proceed, adjust the protocol, or use an alternative test. That decision is theirs and the referring surgeon’s, not something to work out alone.
The images are reconstructed into three-dimensional views that let the surgeon measure the stricture in millimeters and see how much healthy ureter remains above and below it. That measurement is the hinge of the whole plan. A short segment near the bladder may be handled with an internal procedure or by reimplanting the ureter into the bladder. A long segment, or one in the middle of the ureter, often needs tissue brought in from elsewhere. CT urography is how the team finds out which situation they are facing.
Kidney function tests before surgery: creatinine, eGFR and the nuclear renal scan
Two kidneys share the job of filtering blood, so a person can feel entirely well while one kidney quietly loses function behind a blockage. Blood tests alone cannot separate the two. That is why ureteral stricture surgery preparation includes both an overall check and a side-by-side comparison.
The overall check is a blood creatinine and an estimated glomerular filtration rate, or eGFR. Creatinine is a waste product from muscle; when kidneys filter less, it accumulates in the blood. MedlinePlus explains that eGFR uses creatinine together with age and sex to estimate how many milliliters of blood the kidneys clear each minute. The result tells the team whether the person can safely receive contrast, how anesthetic drugs will be handled, and whether the combined kidney reserve is already reduced.
The side-by-side comparison usually comes from a nuclear renal scan, often called a MAG3 scan after the tracer used. A small amount of radioactive tracer is injected into a vein and a gamma camera watches each kidney take it up and drain it over about half an hour. The report gives a split function: the percentage of total work each kidney does. It can also show whether drainage remains sluggish even after a stent, which distinguishes a fixed mechanical stricture from a ureter that is simply floppy after long dilation.
The split function shapes the operation more than any other single number. A kidney contributing a healthy share is worth an elaborate reconstruction. A kidney that has fallen to a very small fraction may not recover even after a perfect repair, and in that case the team may raise removal of the kidney as an option to discuss, since it may otherwise become a source of pain and repeat infection. That conversation is difficult, and it is exactly why the scan is done before surgery rather than after.
Pre-operative tests at a glance: what each one adds
Patients frequently ask why so many appointments are needed when a single scan has already shown the blockage. The answer is that each test answers a question the others cannot. The table below sets out the usual sequence; not everyone needs every item, and the treating team decides the order.
| Test | What it involves | Question it answers |
|---|---|---|
| Urine culture | Midstream sample grown in a laboratory | Is there infection, and which antibiotic works? |
| Blood creatinine and eGFR | Single blood draw | How much total kidney function remains? Is contrast safe? |
| Ultrasound | Probe on the skin, no radiation | How swollen is the kidney? Has drainage relieved it? |
| CT urography | Contrast injection, scans over several minutes | Where is the stricture, how long is it, what is around it? |
| Nuclear renal scan | Tracer injection, camera imaging | What share of work does each kidney do? Does it drain? |
| Retrograde pyelogram | Dye injected up the ureter via cystoscope, often during stent change | Precise length and shape of the narrowing from below |
| Anesthetic assessment | Medical history, examination, sometimes ECG | Is the person fit for the planned anesthetic and position? |
Two items deserve a note. The retrograde pyelogram is often combined with a stent exchange so that one anesthetic serves two purposes, and it gives the clearest picture of exactly where a scope or suture line will need to go. The anesthetic assessment matters more than it might appear: reconstructive ureteral surgery can involve lying on one side for a prolonged period, and heart, lung and clotting history change how that is managed. Skipping any row to save time tends to cost more time later.
Who is usually offered surgery now, and who is usually asked to wait
Surgeons broadly sort people into three groups after the workup, and understanding which group you are in explains most of the scheduling decisions.
The first group is ready. Their urine culture is negative, the kidney is decompressed and no longer tender, blood tests show stable function, and imaging has defined a stricture with a clear surgical answer. For them the remaining preparation is the ordinary pre-operative routine: fasting instructions, a medicines review, and arrangements for the recovery period.
The second group is asked to wait for a defined reason. Most often it is infection: a positive culture, a recent fever, or a stent that has become colonized. It can also be inflammation. Some surgeons deliberately leave a stent out for a period before repair so the ureter’s true caliber can be judged rather than the stretched shape it takes around a tube. Others wait for swelling after a recent stone procedure or radiation to settle. Each of these pauses has an end point that the team can usually describe, even if not to the day.
The third group is redirected. Their nuclear scan shows the kidney above the stricture has lost most of its function, or CT has revealed that the narrowing is caused by something outside the ureter that needs its own treatment first. For them the original operation may no longer be the right one, and the conversation shifts to alternatives.
Where does watchful waiting fit? NHS guidance on hydronephrosis notes that mild swelling with preserved function can sometimes be monitored rather than operated on. A short, soft narrowing that drains well on a nuclear scan may be reviewed with repeat imaging rather than repaired. That is a legitimate choice, and the treating urologist is the person to weigh it against the risks of leaving a stricture in place.
How ureteral stricture surgery actually works, in plain language
The operations fall into two families, and the preparation described above is what decides between them.
Endoscopic procedures work from inside the urinary tract with no external incision. A fine telescope is passed through the urethra and bladder up to the stricture. The surgeon can then stretch the narrowing with a balloon or cut through the scar with a laser or small blade, a procedure called endoureterotomy, and leave a stent in place while the widened segment heals. These procedures are shortest and recovery is quickest. Their limitation is durability: dense or long scars tend to reform, so they suit short, thin strictures in kidneys that still drain reasonably well.
Reconstructive procedures remove or bypass the scarred segment and rebuild the ureter with healthy tissue. They are done through small keyhole incisions, often with robotic assistance, or occasionally through a larger open incision. Which technique is used depends on where the stricture sits. Near the kidney, the surgeon may cut out the narrowing and rejoin the ends, a pyeloplasty or ureteroureterostomy. Near the bladder, the ureter may be reimplanted into a new opening in the bladder wall, sometimes with a flap of bladder fashioned into a tube to bridge a gap. For long segments in the middle, surgeons may borrow a strip of lining from inside the cheek, a buccal graft, or in extensive cases replace the ureter with a segment of small bowel.
In every reconstruction the goal is the same: a wide, tension-free join between two well-supplied pieces of tissue. That is why infection, inflammation and poor kidney function are dealt with first. Each of them undermines the blood supply and healing that the join depends on, and the preparatory tests exist to make sure the surgeon is sewing into the best tissue available.
Ureteral stricture surgery preparation in the final weeks: medicines, fasting and practical steps
Once the tests are done and a date is set, the focus shifts from the ureter to the whole person. This part of preparation is where patients have the most influence, and where the treating team will give specific instructions that override anything written here.
The medicines review comes first. Every prescription, over-the-counter product and supplement is listed, because several affect surgery. Anticoagulants and antiplatelet drugs, the classes that thin the blood, may need to be paused or bridged, and that decision is made jointly by the surgeon and the doctor who prescribed them; stopping them independently can cause a stroke or clot. Certain diabetes medicines are held around contrast studies and fasting. Herbal products that affect clotting are usually stopped. The prescriber decides each one. The patient’s job is to disclose everything, including things that feel trivial.
Long-term conditions are optimized. Blood glucose that is poorly controlled slows healing and raises infection risk, so diabetes management is often tightened in the weeks beforehand. Blood pressure is checked. People who smoke are strongly encouraged to stop, because nicotine narrows small blood vessels and the ureteral repair depends on them; the anesthetic team can refer to support services.
Fasting instructions arrive with the admission letter and are followed exactly, since a full stomach under anesthesia is dangerous. Many centers now allow clear fluids closer to surgery than in the past, but the timing is set by the anesthetist. Bowel preparation is only needed if a bowel segment might be used, and the surgeon will say so.
Practically, someone should be available to drive home and stay the first night if discharge is planned early. Loose clothing is easier with a stent or drain in place. A written list of current symptoms, including any fever or change in urine in the preceding days, saves time on the morning of admission and can prevent a last-minute cancellation.
What the days and weeks after surgery usually look like
Recovery has a shape that most people recognize once it is described, even though the timeline shifts with the type of operation.
After an endoscopic procedure, the person usually goes home the same day or the next morning with a stent in place. Stent irritation, meaning urgency, a frequent need to pass urine and a pulling sensation in the flank when the bladder empties, is the dominant complaint for the first days. Urine may be pink. Ordinary activity resumes within days, with the stent removed at a clinic visit several weeks later, at a time the surgeon chooses based on how the ureter looks on follow-up imaging.
After keyhole or open reconstruction, the hospital stay is longer and there is more to manage: a urinary catheter for the first days, sometimes a small drain near the repair, a stent that stays for several weeks, and incision care. Pain is usually controlled with a combination of medicines chosen by the team, and getting up to walk from the first day is encouraged to reduce clot risk and help the bowel wake up. Lifting and strenuous exercise are restricted until the incisions have healed, typically for a period of weeks that the surgeon will specify.
The real test comes after the stent is removed. Only then does the ureter drain on its own, and only then can the repair be judged. Most teams arrange a follow-up ultrasound or nuclear scan in the months after stent removal to confirm the kidney is no longer swelling and that function has stabilized or improved. Because scar can reform slowly, surveillance often continues for a year or more, and any return of flank pain or infection is treated as a reason to re-image rather than wait.
Figures for how often repairs hold vary widely by stricture type and technique, and this article deliberately gives none; the surgeon can quote the numbers that apply to the specific operation planned.
Risks, side effects and alternatives, described plainly
Every operation on the ureter carries a common set of risks, and knowing them before consent makes the discussion with the surgeon more useful.
Infection is the most frequent, which is why so much of preparation aims to prevent it. Bleeding is usually minor with endoscopic procedures and more relevant with reconstruction. Urine leak at the anastomosis can occur while the join heals; a stent and drain are there to manage it, and most leaks settle with time. Injury to nearby structures such as bowel or blood vessels is uncommon but is part of every consent form. Anesthetic risks depend on general health and are assessed beforehand.
The risk most specific to this surgery is recurrence. Scar tissue can reform at the repair, sometimes months later. Endoscopic treatments carry a higher recurrence rate than reconstruction across the published literature, which is why surgeons reserve them for favorable strictures and follow everyone with imaging. Reconstruction has its own specific concerns: a bladder flap can reduce bladder capacity slightly, a buccal graft leaves a healing patch inside the cheek, and a bowel segment used as ureter can produce mucus and affect blood chemistry.
Alternatives exist and deserve equal airtime. Long-term stent exchange, where a stent is replaced under anesthetic at intervals, avoids reconstruction but commits the person to repeat procedures and stent side effects. A permanent nephrostomy tube does the same from above. Observation with repeat imaging is reasonable for mild, stable, well-draining narrowings. Removal of a kidney that no longer functions is a definitive option when reconstruction cannot restore anything worth preserving.
None of these is universally better. The right one depends on the length and location of the stricture, the function of the kidney, the person’s other health conditions and their own priorities. The treating team lays out the options; the decision is made together, and it is legitimate to ask for time to think.
What people often get wrong about ureteral stricture surgery
Confusion about this condition is common, and some of it comes from a single letter.
Ureteral is not urethral. The ureters run from the kidneys to the bladder; the urethra runs from the bladder out of the body. Urethral strictures are far more commonly searched, mostly affect men, and are treated with different operations such as urethrotomy or urethroplasty. Recovery timelines, side effects and diet advice written for urethral surgery do not transfer to ureteral surgery. If a search result mentions the penis or difficulty starting the stream, it is about the other tube.
A stent is not the treatment. Many people assume that once a stent is in and the pain has eased, the problem is solved. The stent is a bridge that relieves pressure and clears infection; the stricture is still there behind it. Stents left in for very long periods without exchange can encrust and cause problems of their own.
Feeling well does not mean the kidney is fine. A blocked kidney can lose function silently while the other kidney compensates. Blood tests can be normal with one kidney working hard. This is exactly why the nuclear scan is ordered even when the person feels healthy.
Diet cannot dissolve scar tissue. No food, juice or supplement opens a ureteral stricture, and there is no reliable evidence for any product marketed for that purpose. Sensible hydration and a diet that supports overall health and blood glucose control help recovery; they do not replace the operation.
Small incisions do not mean a small operation. Robotic reconstruction leaves tiny scars but is still major surgery inside the abdomen, with real recovery time. Conversely, the internal procedures that look like nothing from outside still involve an anesthetic and a stent.
Finally, the delay for infection treatment is not the team being cautious for its own sake. It is the single most evidence-backed safety step in the whole pathway.
Questions to ask your care team before ureteral stricture surgery
Consultations move quickly, and the most useful questions are the ones prepared in advance. These are the ones that tend to change what a person understands about their own plan.
- Where exactly is my stricture, how long is it, and what do you think caused it?
- What share of my total kidney function does the affected kidney provide, and does that change what you recommend?
- Was my urine culture negative, and will it be repeated before the operation?
- Which operation are you planning, and why that one rather than the alternatives for my anatomy?
- If you find something unexpected during surgery, what would you do, and what would you need my permission for in advance?
- How long do you expect my stent to stay in, and how will you decide when to remove it?
- Which of my regular medicines should I stop, when, and who is making that decision?
- What is the plan if the stricture comes back?
- How will you check the kidney after the stent is out, and for how long will you follow me?
- Who do I call, at any hour, if I develop a fever after I go home?
It helps to bring someone along to take notes, and to ask the surgeon to draw the ureter and mark the stricture; a sketch clarifies more than most explanations. Asking for the written results of the CT and nuclear scan is reasonable and routine.
One question worth asking of yourself as well as the team: what matters most to you? Some people prioritize the fewest procedures overall and accept a longer recovery from reconstruction. Others want the least invasive option now and accept a higher chance of needing something later. Neither is wrong. Saying it aloud lets the surgeon tailor the recommendation to the person rather than to the scan.
When to call your doctor: red-flag signs before and after surgery
A blocked kidney with infection can deteriorate within hours, and the window for safe action is widest early. The signs below apply whether the operation is still weeks away, a stent has just been placed, or surgery was last week.
Seek urgent care, by emergency services if needed, for a fever with shaking chills, especially with flank pain; a fast heartbeat, breathlessness or feeling faint; confusion, drowsiness or being difficult to rouse; cold, clammy or mottled skin; or severe pain that is not relieved by the medicines prescribed. The CDC lists these among the signs of sepsis, and a person with a known urinary blockage who develops them should not wait to see whether they settle.
Contact the treating team the same day for a new fever without the features above; urine that is cloudy, foul-smelling or contains clots rather than a pink tinge; passing much less urine than usual, or none, particularly if only one kidney functions well; vomiting that prevents fluids from staying down; a stent or drain that appears to have moved or has stopped draining; or redness, swelling or discharge at an incision.
Before surgery, report any of these even if they seem minor, because they may mean the operation needs to be rescheduled rather than proceed with an active infection. After surgery, the discharge paperwork should include a direct contact number for the urology team, and that number exists to be used. Emergency departments will also see anyone with a stent or recent ureteral surgery who is unwell.
Not everything needs a call. Stent irritation, mild ache on emptying the bladder, and slightly pink urine are expected and were covered at discharge. The distinction is fever, worsening pain, falling urine output and any change in alertness. Those four are never treated as routine, and the treating team would rather hear about them early than late.
Frequently asked questions
Is a ureteral stricture the same as a urethral stricture?
No. The ureters carry urine from each kidney down to the bladder; the urethra carries urine from the bladder out of the body. Ureteral strictures cause kidney swelling and flank pain and are repaired through the abdomen or from inside the ureter. Urethral strictures mostly affect men, cause a weak stream, and are treated with different operations. Search results about one rarely apply to the other.
What are the first ureteral stricture symptoms people notice?
Many people notice a dull, persistent ache in the flank or back on one side, sometimes worse after drinking a lot of fluid. Others have repeated urinary infections, blood in the urine, or no symptoms at all until a scan done for another reason shows a swollen kidney. Because the other kidney compensates, feeling well does not rule out significant blockage.
Why do I need a ureteral stent before surgery if the surgery will fix the problem?
The stent is a bridge, not the repair. It relieves pressure on the kidney, lets trapped infected urine drain, and allows antibiotics to work, so the surgeon operates on a clean, decompressed system. It also gives inflammation time to settle so the tissue holds sutures well. Some surgeons remove the stent for a period before repair to judge the ureter’s true width.
What does the CT urography procedure feel like, and is the contrast dye safe for my kidneys?
Most people feel a brief warm flush and a metallic taste as contrast is injected, then lie still for scans taken over several minutes. The dye is filtered by the kidneys, so a recent creatinine result is checked first. People with reduced kidney function or previous reactions are flagged, and the radiology team decides whether to adjust the protocol or use another test.
Which kidney function test before surgery matters most?
Both matter for different reasons. Blood creatinine and eGFR show total kidney function and whether contrast and anesthetic drugs are safe. The nuclear renal scan shows how the work is split between the two kidneys and whether the blocked one still drains. The split function is the number that most often changes the surgical plan, because it shows whether the affected kidney is worth reconstructing.
How long does it take to heal from ureteral stricture surgery?
It depends on the operation. After an endoscopic procedure, ordinary activity usually resumes within days, with the stent removed several weeks later. After keyhole or open reconstruction, the hospital stay is longer, lifting is restricted for weeks, and the stent stays in until the surgeon judges the repair has healed. The repair is only confirmed by imaging months after stent removal.
What are the side effects of ureteral stricture surgery?
The most common are stent-related: urgency, frequent urination, flank pulling when the bladder empties, and pink urine. Reconstruction adds incision pain, a temporary catheter and sometimes a drain. Less common risks include infection, bleeding, urine leak at the join, and injury to nearby structures. The risk most specific to this surgery is the stricture re-forming, which is why follow-up imaging continues afterwards.
Which food is good for a ureteral stricture?
No food opens or shrinks scar tissue, and no supplement has evidence for doing so. What helps recovery is the same diet that supports healing generally: adequate fluids unless the team restricts them, enough protein, and steady blood glucose if you have diabetes. If a bowel segment is used in reconstruction, the surgeon may give specific dietary guidance.
How serious is a ureteral stricture?
Left untreated, a significant stricture can cause progressive, sometimes silent loss of function in the kidney above it, along with repeated infections and pain. Combined with infection it can cause sepsis, which is an emergency. Diagnosed and staged properly, most strictures have a well-defined surgical option, and mild, well-draining narrowings can sometimes be monitored rather than operated on.
Can I stop my blood thinner myself before the operation?
No. Anticoagulants and antiplatelet medicines protect against stroke and clots, and stopping them without a plan can be dangerous. The surgeon, anesthetist and the doctor who prescribed the medicine decide together whether to pause, bridge or continue it, and when. Your role is to list every medicine and supplement you take so that decision is made with full information.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Urinary Symptoms Need a Urologist: Which Diagnostic Tests Usually Come First
Most people can start with their primary care clinician, who usually orders a urinalysis and, if needed, a urine culture and basic kidney blood…

How Blood and Urine Tests Reveal Kidney Damage From Medicines, Metals or Contrast
Kidney damage from medicines, heavy metals or contrast dye is usually picked up with two kinds of tests: a blood test measuring creatinine, used…

Why an Acute UTI Sample Is Taken Before Antibiotics Start: Culture, Sensitivity and Timing
A urine sample is taken before antibiotics start because antibiotics begin killing or suppressing bacteria within hours, which can leave a culture falsely negative…

Urinary Incontinence in Older Adults: How Treatment Is Tailored to Health and Mobility
Incontinence in older adults is treated in steps matched to the person's overall health, mobility and memory. Clinicians first look for reversible causes such…

Sling Surgery Recovery: Lifting Limits, Spotting and When Exercise and Intimacy Resume
After sling surgery for stress urinary incontinence, most people are walking the same day and back to light daily routines within about two weeks,…

Can You Take Over-the-Counter Painkillers With Kidney Disease? Why Every Item Is Checked
Some over-the-counter painkillers can be used by people with kidney disease, but only after the treating team has checked them. Non-steroidal anti-inflammatory drugs, the…