

Central Venous Port Warning Signs: Redness, Swelling, Fever and When to Call Your Team

Key Takeaways
- A port site infection can present in two ways: locally, with redness, warmth, swelling or pus at the skin, or systemically, with fever and chills while the skin looks completely normal.
- MedlinePlus and Cleveland Clinic advise calling the care team for a temperature of 100.4°F (38°C) or higher in anyone with a port, and chills after a flush strongly suggest bacteria inside the catheter.
- The direction of travel matters more than the size of a change: healing redness fades over the first week or two, while infected redness spreads, tightens and warms.
- Swelling of the arm, neck or face on the port side more often points to a clot around the catheter than to infection, yet still requires same-day assessment.
- The CDC lists confusion, fast heart rate, shortness of breath, extreme pain, shivering and clammy skin as sepsis warning signs, and any of them alongside a suspected infection is an emergency.
- Whether an infected port can be kept or must be removed depends on the organism, the site of infection and how unwell the person is, and that judgment belongs entirely to the treating team.
Port site infection warning signs include new or spreading redness over the port or along the catheter path, swelling, warmth, tenderness, pus or cloudy fluid from the incision, and a fever of 100.4°F (38°C) or higher, especially with chills soon after the port is used. Any of these, or suddenly feeling very unwell, means contacting the treating team the same day rather than waiting for the next appointment.
Three weeks after the small operation that placed a port under her collarbone, a woman sits at her kitchen table with her shirt pulled aside, pressing gently around the coin-sized bump. Yesterday it looked fine. This morning the skin above it is pink, a little shiny, and warmer than the skin an inch away. She has a chemotherapy appointment in two days. Is this something to mention then, or something to call about now?
That question sits at the heart of port site infection warning signs, and the honest answer is that most people with a port will face a version of it. Ports are designed to be forgotten between treatments, which is exactly why a change in the skin over one can feel so unsettling.
The good news is that the signs that matter are few, they are consistent, and the rule for responding to them is simple. What follows is the evidence behind that rule.
How a central venous port works, and what actually sits under the skin
A central venous port is a small device, roughly the size of a quarter, implanted under the skin of the upper chest or occasionally the arm. It has two parts. The first is a reservoir with a tough silicone top, called the septum, which a special needle can pass through many times. The second is a thin, flexible tube, the catheter, that runs from the reservoir under the skin and into a large vein near the heart, so that medicines and fluids dilute quickly in a fast flow of blood.
Because the whole system is closed under intact skin, a port carries a lower day-to-day infection risk than a line that exits the body through a dressing. MedlinePlus notes that ports can stay in place for months or years, which is why they are common for chemotherapy, long courses of intravenous nutrition or antibiotics, and frequent blood sampling.
The skin, though, is the only barrier. Every time the port is “accessed,” a needle crosses that barrier, and every time the needle comes out the skin has to seal again. Bacteria that normally live harmlessly on the skin surface can slip along the needle track into the pocket that holds the reservoir, or along the catheter into the bloodstream. When the pocket becomes infected, doctors call it a pocket infection. When bacteria travel into the blood via the catheter, it is a central line-associated bloodstream infection, often shortened to CLABSI.
Understanding those two routes explains the two clusters of warning signs: local changes at the skin, and whole-body changes such as fever and chills. The rest of this article follows that split.
Port site infection warning signs: the changes worth noticing first
Ask a nurse who accesses ports all week what tips them off, and the answer is rarely dramatic. It is usually a small mismatch: skin over the port that looks or feels different from the skin around it, or a patient who says the last flush “felt off.” The earliest port site infection warning signs cluster around a handful of observations.

- Redness that appears after the incision has already settled, or redness that grows day on day rather than shrinking.
- Warmth: the area feels noticeably hotter than the mirror-image spot on the other side of the chest.
- Swelling or a new firmness around the reservoir, sometimes with the skin looking tight or shiny.
- Tenderness or pain when the port is touched, when clothing brushes it, or during access.
- Drainage: any pus, cloudy fluid, or persistent wetness at the incision line or the needle site.
- Fever, chills or shaking, particularly in the hour or two after the port is flushed or used.
Patient guidance from MedlinePlus and Cleveland Clinic both treat these as reasons to contact the care team rather than watch and wait, and the reasoning is practical. A localized pocket infection caught early is a very different problem from one that has spread into the bloodstream, and the interval between the two can be short.
One more sign is easy to miss because it does not look like infection at all: the port simply stops working well. Difficulty flushing, inability to draw blood, or pain when fluid goes in can accompany infection, clot, or a mechanical problem. None of these are safe to troubleshoot at home, and all of them belong in a same-day phone call.
What does an infected port site look like?
People searching for photographs of infected ports usually find extremes: angry, weeping wounds that have clearly been neglected for days. Real early infection is quieter than that, and worth describing plainly.
In lighter skin, the first change is typically a pink or red flush over the reservoir that does not follow the neat line of the incision. Instead it forms a rough circle or oval, sometimes with a slightly raised edge, and it may creep outward over a day or two. In darker skin, redness is harder to see; the area may look darker, purplish or grayish, and warmth, swelling and tenderness carry more of the diagnostic weight. Comparing the port side with the opposite side of the chest in good light is a useful habit.
Swelling shows as loss of the crisp outline of the device. A healthy port feels like a firm disc you can trace with a fingertip. An inflamed pocket blurs that outline, and the overlying skin may look stretched. If fluid has collected, the area can feel soft or boggy.
Drainage is the sign that removes most doubt. A dot of clear fluid on the dressing in the first day or two after placement is common. Yellow, green or cloudy fluid, a foul smell, or an incision that reopens and weeps is not.
Two less familiar patterns also matter. A red streak tracking upward from the port toward the neck follows the catheter tunnel and suggests a tunnel infection. Skin over the reservoir that thins, turns dark, or breaks down so the device becomes visible is called erosion, and it is a reason for prompt assessment even without obvious redness. Cleveland Clinic lists visible device, skin breakdown and drainage among the reasons to call.
Redness and swelling: normal healing versus spreading trouble
Every port begins with an incision, and every incision produces some inflammation. The challenge is telling the ordinary from the ominous, so it helps to know what expected healing looks like before anything goes wrong.
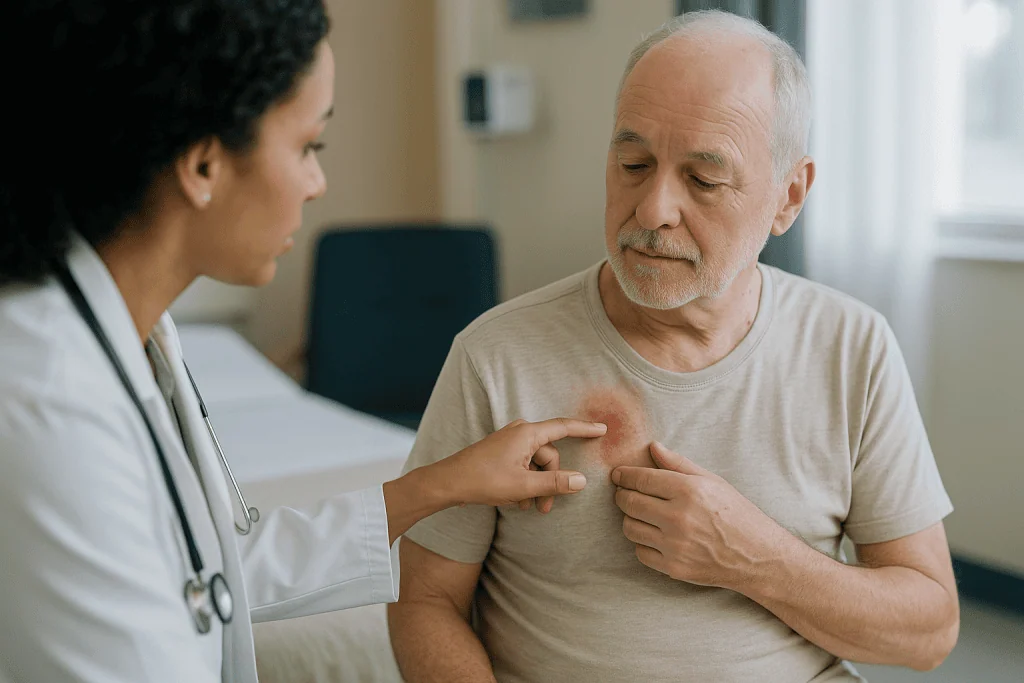
In the first several days, mild pinkness hugging the incision line, slight bruising in the pocket, and a firm ridge along the wound edges are all part of normal repair. Bruising may spread downward with gravity and turn yellow-green as it fades. Soreness is expected, especially when reaching overhead or wearing a seat belt across the site. According to Cleveland Clinic’s patient guidance, discomfort generally eases over the first week or so, and the team will explain when the outer dressing can come off and when showering is allowed.
Concern begins when the trajectory reverses. Healing redness fades; infected redness spreads. Post-operative swelling softens; an infected pocket becomes tighter, hotter and more tender. Pain that was improving and then worsens on day five or day ten is a classic pattern, and it deserves a call even if nothing else has changed.
Swelling in the wrong place is a separate flag. Puffiness of the arm, hand, neck or face on the side of the port, a feeling of fullness in the neck, or new visible veins across the chest can indicate a clot around the catheter rather than infection. MedlinePlus lists arm or neck swelling among the reasons to contact the provider. Clots and infection can coexist, and both need imaging or blood tests to sort out.
The practical test is direction of travel. Anything that is getting better can usually wait for the next scheduled visit. Anything getting worse, or appearing fresh weeks after the wound has closed, should be reported the same day.
Fever with a port: why it is never "just a fever"
A fever is the body’s most reliable, and least specific, alarm. In someone without a port and with a normal immune system, a mild fever after a cold is rarely urgent. Add a catheter sitting in a central vein, and the calculus changes completely.
The catheter offers bacteria a highway from the skin surface straight into fast-moving blood. Once there, they can seed heart valves, bones, joints or the port pocket itself, and the immune response can tip into sepsis, the life-threatening overreaction described in the next section. MedlinePlus advises people with a port to call the provider for a fever of 100.4°F (38°C) or higher, and most cancer centers use the same threshold because chemotherapy can lower the white blood cell count that normally fights infection.
Timing gives clues. Fever or shaking chills that begin within an hour or two of the port being flushed or used strongly suggests bacteria living on the inside of the catheter, released into the blood by the flow of fluid. Fever with a red, tender pocket points toward a local infection that may also have entered the blood. Fever with no local change at all does not rule the port out; the catheter tip lies far from the skin, and infection there produces no visible sign.
Two cautions from the evidence. First, people who are older, on steroids, or receiving chemotherapy may not mount a high temperature, so chills, sweats, a racing heart or simply feeling profoundly unwell can substitute for the number on the thermometer. Second, taking a fever-reducing medicine before calling can mask the very sign the team needs to know about. Check the temperature, write it down, and call.
Early warning signs of sepsis after surgery or port placement
Sepsis is the body’s extreme, disorganized response to an infection, in which the chemicals released to fight germs begin damaging the body’s own tissues and organs. It can follow any infection, including one that starts at a port pocket or a surgical incision, and it can move fast. Recognizing it early is the single most important skill this article can offer.
The CDC groups the warning signs into a short list: a high heart rate or weak pulse; confusion or disorientation; extreme pain or discomfort; fever, shivering or feeling very cold; shortness of breath; and clammy or sweaty skin. Mayo Clinic adds a change in mental status, fast shallow breathing, and lightheadedness. The NHS highlights signs that are especially urgent: skin that is blotchy, blue, gray or pale; a rash that does not fade when a glass is pressed against it; difficulty breathing; slurred speech; and passing no urine for a day.
Several of these are easy to explain away. “Confused” can look like a spouse being unusually vague on the phone. “Extreme discomfort” can be a person who suddenly cannot find a comfortable position. “Feeling very cold” can be someone piling on blankets in a warm room. Family members often notice these changes before the patient does, which is why the CDC and NHS both encourage relatives to speak up.
The message from every major body is the same: sepsis is a medical emergency. If someone with a recent port placement or any surgical site has a suspected infection plus any of the signs above, the appropriate response is emergency care, not a message left with the clinic. Mayo Clinic is explicit that early treatment improves the chance of recovery, and that delay increases the risk of septic shock, where blood pressure falls dangerously.
Who is more likely to develop a port infection, and who is usually asked to wait
Infection risk is not spread evenly. Knowing where you sit helps calibrate how quickly to react to a small change.
The largest factor is the immune system. Chemotherapy regimens that suppress white blood cells, particularly in blood cancers such as leukemia and lymphoma, leave fewer defenders at the skin and in the blood. People receiving intravenous nutrition through a port carry a higher risk because the fluid itself can support bacterial growth. Diabetes that is not well controlled, long-term steroid use, kidney failure, and very low body weight all appear repeatedly in guideline-level discussions of catheter infection.
How often the port is used matters too. A port accessed daily for infusions is crossed by a needle far more often than one used monthly for blood tests. Each access is a chance for skin bacteria to enter, which is why sterile technique during access is stressed in CDC prevention guidance for central lines.
Skin problems over the site raise risk in their own right. Eczema, psoriasis, radiation changes, or a previous infection in the same pocket make the barrier less reliable. A history of a prior port removed for infection is a recognized flag, and teams often choose the opposite side of the chest for a replacement.
Placement itself is sometimes delayed. Teams commonly ask people to wait when there is an active infection anywhere in the body, when blood counts are at their lowest point in a chemotherapy cycle, when the skin over the planned site is broken or irritated, or when a blood infection has been treated very recently and cultures have not yet come back clear. The reasoning is straightforward: a new device is most vulnerable in its first days, and seeding it with bacteria already in the blood is a risk worth avoiding. The timing decision rests with the treating team, weighing the urgency of treatment against that risk.
Expected healing, same-day call, or emergency: a side-by-side guide
Words like “some redness” and “a bit of swelling” are hard to act on. The table below organizes the common observations by the response that patient guidance from MedlinePlus, Cleveland Clinic, the CDC and the NHS supports. It is a guide to conversation with the care team, not a substitute for it.
| Observation | Often part of normal healing | Call the team the same day | Seek emergency care |
|---|---|---|---|
| Redness | Faint pink along the incision line, fading over the first days | Redness spreading beyond the incision, a red streak toward the neck, or new redness weeks after placement | Rapidly spreading redness with fever, confusion or fast breathing |
| Swelling | Mild puffiness or bruising in the pocket that softens over time | Tight, hot, increasingly tender swelling; swelling of the arm, neck or face on the port side | Swelling with breathing difficulty or facial swelling |
| Drainage | A small spot of clear fluid or blood on the first dressing | Any pus, cloudy or foul-smelling fluid, or an incision that reopens | Drainage accompanied by fever and feeling very unwell |
| Temperature | None expected | 100.4°F (38°C) or higher, or chills without a recorded fever | Fever or chills plus confusion, low blood pressure symptoms, blotchy or blue-tinged skin |
| Pain | Soreness easing over the first week | Pain that returns or worsens after improving; pain during flushing | Extreme, unmanageable pain with other sepsis signs |
| Port function | Works normally | Hard to flush, cannot draw blood, resistance during access | Not an emergency on its own; report the same day |
Two patterns cut across every row. Anything that is improving can usually wait for a scheduled visit. Anything that is worsening, or that combines a local change with a whole-body sign such as fever, chills, confusion or breathlessness, has moved out of the “watch” category.
What the first days and weeks after port placement usually look like
Knowing the ordinary course makes deviations obvious. Port placement is typically done as a day procedure under local anesthetic with sedation, and most people go home the same day, according to Cleveland Clinic’s patient guidance.
The first 24 to 48 hours bring the most soreness. A dressing covers the incision, sometimes with a small strip of adhesive closures or skin glue beneath it. Bruising is common, and the outline of the device is often masked by swelling at first. Teams generally ask people to keep the site dry until the dressing is removed and to avoid heavy lifting or vigorous overhead movement on that side while the wound settles. Cleveland Clinic and MedlinePlus both describe following specific instructions from the team about showering and dressing care rather than a fixed universal rule, because techniques differ.
Over the following week or two, soreness fades, bruising yellows and clears, and the incision line flattens. Some ports are used within a day or two of placement; others are rested until the incision has healed. Once the wound has closed and any remaining closures have fallen away or been removed, there are no further dressings; the port lives silently under intact skin.
After that, the routine is maintenance. When a port is not being used regularly, it is flushed with saline, and sometimes a clot-preventing solution, to keep the catheter clear. MedlinePlus describes this as happening roughly every 4–6 weeks, though the interval depends on the device and the team’s protocol.
The point at which infection tends to declare itself is either early, within the first couple of weeks while the pocket is still healing, or later in connection with frequent access. A calm, uneventful first month does not mean the topic can be filed away; it means the baseline has been established against which any later change can be judged.
How do doctors tell if a port is infected?
When someone calls with a red or painful port site, the assessment follows a fairly predictable path, and knowing it in advance removes some of the anxiety.
The first step is a physical examination of the site and a review of recent temperatures, chills, and any relationship between symptoms and port use. The team will also ask about other possible sources of infection, such as a cough, urinary symptoms or a dental problem, because a fever in someone with a port is not automatically caused by the port.
Blood cultures are the cornerstone test. Blood is drawn into bottles that encourage any bacteria present to grow, so the laboratory can identify the organism and test which antibiotics affect it. Commonly a sample is drawn through the port and a second from a vein in the arm at the same time. If bacteria grow faster or in greater numbers from the port sample, that points to the catheter as the source. Results typically take a day or more, so decisions about initial treatment are often made before the organism is known.
If there is fluid or pus at the site, a swab may be sent for culture as well. A complete blood count looks at white cells, which may be high in infection or very low after chemotherapy, and other blood tests gauge how the kidneys and other organs are coping.
Imaging has a role when the picture is unclear. Ultrasound can reveal a collection of fluid in the pocket or a clot around the catheter. If a bloodstream infection is confirmed, further tests such as an echocardiogram, an ultrasound of the heart, may be considered to check whether bacteria have settled on a heart valve.
The team weighs all of this together with the type of organism and how unwell the person is, and that combination drives the treatment decision described next.
How port infections are treated, and when a port has to come out
Treatment depends on where the infection sits and what is growing. This section describes the general approach so that the conversation with the team makes sense; every specific choice belongs to the prescribing clinician.
Antibiotics are the foundation. If the person is feverish and a bloodstream infection is suspected, treatment usually starts intravenously before culture results are back, using broad-spectrum antibiotics, meaning drugs that act against a wide range of likely bacteria. Once the laboratory identifies the organism and its sensitivities, the choice is narrowed. The duration is set by the team based on the organism, whether the port stays in, and whether the infection has spread anywhere else.
Whether the port can be saved is the central question. Guideline-level practice generally favors removing the device when the pocket itself is infected with pus or skin breakdown, when there is a tunnel infection along the catheter path, when the person is severely unwell or has sepsis, or when certain organisms are involved that are notoriously hard to clear from plastic surfaces, such as some staphylococci, fungi, and certain resistant bacteria. Attempts to keep the port with antibiotics alone are more commonly considered for uncomplicated bloodstream infections with organisms that respond well, in someone who is stable, and sometimes with a technique in which a concentrated antibiotic solution is left inside the catheter between uses.
Removal is usually a short procedure under local anesthetic. A new port, if still needed, is generally placed on the other side after the infection has been treated and blood cultures have cleared, with the timing set by the team.
None of this can be judged from home, and none of it should be. The role of the patient is to report early and accurately; the role of the team is to weigh the evidence and decide.
What people often get wrong about port infections
Ports have been in use for decades, long enough for a folklore to build up around them. Several common beliefs deserve correcting.
“If there is no redness, it cannot be infected.” The catheter tip sits in a vein deep in the chest. Infection inside the catheter produces fever, chills and feeling unwell, often with a perfectly normal-looking skin site. Fever alone is enough reason to call.
“A little pus is normal after the needle comes out.” It is not. A drop of clear fluid or blood at the moment of de-access is expected; anything cloudy, yellow or green that appears later is a warning sign.
“I should take a fever reducer and see if it settles.” Masking a fever removes the information the team needs. Record the temperature first and make the call. The team may well suggest something for comfort afterward, but that is their decision.
“It is the weekend, so it can wait until Monday.” Infection does not observe office hours, and bloodstream infections can worsen over hours rather than days. Cancer centers and infusion services maintain after-hours numbers precisely for this situation.
“Once the port is out, the problem is over.” Removal treats the source, but antibiotics generally continue for a period set by the team, and follow-up cultures may be needed to confirm the blood is clear.
“Ports get infected all the time.” Most people with a port never develop an infection. Awareness is about responding well to an uncommon event, not living in fear of an inevitable one.
“Any arm swelling means infection.” Swelling of the arm or neck on the port side more often signals a clot around the catheter. It still needs same-day attention, but for a different reason.
Questions to ask your care team about your port
The best time to learn how to recognize a problem is before one occurs, ideally at the placement appointment or the first access. These questions tend to produce the most useful answers.
- What temperature should prompt me to call, and is that number different during the low point of my chemotherapy cycle?
- Which number do I call during working hours, and which one at night or on weekends? Who answers it?
- What should the incision and the skin over the port look like at one week and at one month?
- When can I shower, swim or soak in a bath, and does that change while the port is accessed?
- How often does my port need flushing when it is not being used, and what happens if I miss a flush?
- Should I expect to feel anything during a flush, and what sensations would you want to hear about?
- If I develop a fever, will you culture the port and a peripheral vein at the same time?
- In my situation, how likely is it that a port infection would mean removing the device?
- Are there activities, clothing or seat-belt positions I should adjust to protect the site?
- Is there anything about my other conditions or medicines that raises my infection risk, and what does that change about how quickly I should react?
- Who is my point of contact if I notice something small and simply want a second opinion on whether it matters?
Writing the answers on a card kept with the port identification information gives family members the same clarity. Several of the sepsis signs described earlier are easier for a relative to notice than for the patient, and a relative who knows which number to call and what threshold applies is a genuine safety measure.
When to call your doctor: red-flag signs with a port
Call the treating team the same day, using the after-hours line if necessary, for any of the following.
- A temperature of 100.4°F (38°C) or higher, or chills, shaking or sweats even without a measured fever.
- New or spreading redness, warmth or swelling over the port or along the path of the catheter toward the neck.
- Pus, cloudy or foul-smelling fluid, or persistent wetness at the incision or needle site, or an incision that reopens.
- Pain over the port that returns or worsens after it had been improving, or pain during flushing.
- Swelling of the arm, hand, neck or face on the port side, or new prominent veins across the chest.
- Skin over the port that thins, darkens, breaks down, or through which the device becomes visible.
- A port that cannot be flushed, will not give blood, or feels different in position.
Call emergency services or go to the nearest emergency department if infection is suspected and there is also any of: confusion, unusual sleepiness or difficulty waking; fast or difficult breathing; a racing heart, dizziness or fainting; blotchy, pale, blue, gray or mottled skin, or a rash that does not fade under pressure; extreme pain; passing little or no urine over a day. The CDC, Mayo Clinic and the NHS all describe these as signs of possible sepsis, a medical emergency where every hour counts.
Do not remove the needle if the port is accessed, do not attempt to flush the port yourself unless you have been trained and instructed to, and do not take a fever-reducing medicine to “see if it settles” before calling. Tell whoever answers that you have a central venous port; it changes how quickly you are seen.
Every decision about testing, antibiotics and whether the port stays or goes rests with the treating team. Your part is to notice early and report clearly.
Frequently asked questions
How can you tell if your port is infected?
The most reliable signs are new or spreading redness, warmth, swelling or tenderness over the port, pus or cloudy fluid at the incision, and a fever of 100.4°F (38°C) or higher or chills, particularly soon after the port is used. Infection inside the catheter can cause fever with no skin change at all, so a fever alone is enough to call the team the same day.
What does an infected port site look like?
Early on it usually looks like a pink or red patch over the device that spreads beyond the incision line, often shiny, warm and tender, with the outline of the port becoming harder to feel. In darker skin the area may look darker or purplish rather than red. Yellow or green drainage, a red streak toward the neck, or skin thinning until the device shows through are later and more urgent signs.
What are the early warning signs of sepsis after surgery or port placement?
According to the CDC, the key signs are a high heart rate or weak pulse, confusion or disorientation, extreme pain or discomfort, fever or shivering or feeling very cold, shortness of breath, and clammy or sweaty skin. The NHS adds blotchy or bluish skin, a rash that does not fade under pressure, slurred speech and passing no urine for a day. Any of these with a suspected infection is an emergency.
How do I tell if my surgical site is infected rather than just healing?
Healing incisions get steadily better: pinkness fades, soreness eases and bruising clears over the first week or two. Infected incisions reverse that course, with redness that spreads, pain that worsens after improving, increasing warmth or swelling, and any pus or foul-smelling fluid. A fever or chills alongside those changes shifts the situation from routine to same-day contact with the surgical team.
Can a port be infected without any redness?
Yes. The catheter tip lies in a large vein deep in the chest, so bacteria growing on the inside of the tube cause fever, chills and feeling unwell while the skin over the reservoir can look entirely normal. Chills or shaking that begin within an hour or two of the port being flushed are a particularly strong clue and warrant a same-day call.
What chemo port infection symptoms should I watch for during treatment?
During chemotherapy, watch for fever of 100.4°F (38°C) or higher, chills or sweats, redness or swelling over the port, pain during access or flushing, and any drainage at the needle site. Because chemotherapy can lower white blood cells, infection may progress quickly and fever may be blunted, so feeling suddenly very unwell, dizzy or confused should be treated with the same urgency as a measured temperature.
Does an infected port always have to be removed?
Not always. Removal is generally favored when the pocket or tunnel itself is infected, when the person is severely unwell, or when certain organisms are involved that are difficult to clear from the device. Uncomplicated bloodstream infections with responsive bacteria in a stable person are sometimes managed with antibiotics while the port stays in. The decision rests with the treating team after cultures and assessment.
Should I take something for a fever before calling about my port?
It is generally better to record the temperature and call first. A fever-reducing medicine can mask the sign the team needs in order to judge how urgently to see you, and patient guidance from MedlinePlus treats fever with a port as a reason to contact the provider promptly. The team can then advise on comfort measures once they know the situation.
Is arm or neck swelling on the port side a sign of infection?
More often it signals a blood clot forming around the catheter in the vein, which can cause swelling of the arm, hand, neck or face on that side and sometimes new visible veins on the chest. Infection and clot can occur together, and both need same-day assessment with imaging or blood tests, so the swelling should be reported promptly whatever the cause.
How long after placement does redness around a port usually settle?
Cleveland Clinic’s patient guidance describes soreness and mild redness along the incision easing over roughly the first week, with bruising fading over the following days. Redness that is still spreading after the first few days, or that appears fresh weeks or months after the wound has healed, does not fit normal recovery and should be reported to the team the same day.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Long Does an IVIG Infusion Take? Monitoring, Slow Starting Rates and the Session Itself
A single IVIG infusion usually takes several hours; many patient resources describe roughly two to four hours as typical, with first-ever infusions and larger…

Sleeping After Joint Surgery: Positions for Knee, Hip and Shoulder
After knee replacement, most people sleep best on their back with the leg elevated on pillows placed under the calf and ankle, never under…

Comparing Countries for Hip Replacement: Price Is Only Half the Question
Turkey is currently among the cheapest countries for a total hip replacement, with guide prices for international patients of roughly EUR 9,100-16,900, compared with…
Hematoma After Surgery: How It Differs From a Bruise and When It Is Urgent
A hematoma after surgery is a collection of blood that pools under the skin or deeper in the surgical site, forming a firm, often…

Hysterectomy Recovery: Two Weeks, Three Months, Walking and Driving
Most people need 2 to 6 weeks to recover from a hysterectomy, depending on how it was done. Vaginal or laparoscopic surgery typically allows…

Constipation After Surgery: Why It Happens and Safe Ways to Get Moving Again
Constipation after surgery is common and usually temporary. Anesthesia, opioid pain relievers, less movement, and disrupted eating all slow the bowel; most people pass…