

Day to Day With FND: Prescribed Exercises, Stress Management and Rebuilding Routines

Key Takeaways
- FND is diagnosed on positive examination findings such as Hoover's sign and tremor entrainment, not by ruling everything else out.
- FND physiotherapy works by redirecting attention and using automatic movement, and repetitive strengthening drills can make functional symptoms worse.
- The Mayo Clinic states that no medicine treats FND itself; medicines are used only for conditions that travel alongside, such as depression, pain or insomnia.
- Functional seizures are diagnosed with tools such as video-EEG, and antiseizure medicines do not target them, so any change is a prescriber's decision.
- ME/CFS is defined by post-exertional malaise and fatigue lasting at least six months, whereas FND is defined by positive neurological signs, and the pacing rules differ.
- There is no good-quality trial evidence that CBD improves FND, and it can interact with other medicines by affecting how the liver processes them.
Living with FND means treating symptoms as real but retrainable. Day-to-day care usually combines prescribed physiotherapy that redirects attention away from the affected limb, psychological strategies for stress and dissociation, and a steady routine of sleep, paced activity and rest. Progress is measured over weeks to months, flares are expected, and every change to therapy or medicine is agreed with the treating team.
The strange part, she said, was the dog walk. Twenty minutes around the block, leash in hand, no trouble at all. Then she reached the kitchen, thought about her left leg, and it folded under her like wet cardboard. A scan the month before had been clean. The neurologist had spent a long appointment explaining a diagnosis she had never heard of and handed her a physiotherapy referral instead of a prescription.
That is the reality of living with FND for many people: a body that works when it is not being watched and stalls when it is, a diagnosis that sounds like a shrug but is actually quite specific, and a treatment plan built from exercises, routines and stress skills rather than a single pill.
This explainer walks through what those exercises involve, why stress management sits alongside them, how routines get rebuilt, and which warning signs still need a doctor.
What living with FND means once the diagnosis is made
Functional neurological disorder, or FND, is a condition in which the nervous system’s structure is intact but the brain’s control of movement, sensation, speech or awareness goes wrong. The NHS describes it as a problem with how the brain sends and receives signals, and the NIH’s neurological institute lists it among the more common conditions seen in neurology clinics.
The diagnosis is not a leftover label after everything else has been ruled out. Neurologists look for positive signs. Hoover’s sign is one: a person who cannot push the affected leg down on request will often do so automatically when asked to lift the other leg. Tremor entrainment is another, where a shaking hand falls into rhythm with a tapping task performed by the other hand. Signs like these show that the movement pathways still work, which is precisely why the plan is retraining rather than protection.
That distinction shapes everything that follows. Someone with nerve damage may be asked to protect a limb; someone with FND is usually encouraged to move it, though in specific, guided ways. A person with a structural seizure disorder may be prescribed antiseizure medicine; a person with functional seizures generally is not, because those medicines do not target the mechanism.
Living with FND also means living with a name that many friends, employers and even some clinicians have never met. Part of the day-to-day work is learning to explain it plainly: real symptoms, working hardware, a software problem that can be trained. The good news inside that explanation is that the same brain producing the symptom is the one that can learn to stop producing it, with the right help.
How FND actually works in the brain
Think of a pianist who plays a difficult passage effortlessly until asked to explain exactly which finger moves next. Attention breaks the automatic program. FND behaves in a similar way, on a larger scale and without the person choosing it.

Movement, balance and even sensation normally run on prediction. The brain guesses what the body should feel and do, then checks the guess against incoming signals. In FND, research summarized by the NIH and the Mayo Clinic suggests that these predictions and the attention paid to the body become distorted. The brain expects a leg to be weak, monitors it closely, and produces the weakness it expects. The person is not imagining it or performing it; the motor system is genuinely misfiring at the level of control rather than wiring.
Several things can tip the system into that state. A physical injury, an infection, a migraine, an operation, a panic attack or a stressful period can each act as a trigger. So can nothing identifiable at all. The NHS and the Mayo Clinic are both clear that a psychological cause is not required for the diagnosis, which corrects an older idea that FND was always a reaction to hidden trauma.
Dissociation is a related mechanism worth defining: a state in which awareness detaches from the body or surroundings, such as feeling far away or watching yourself from outside. It is common in functional seizures and in some sensory symptoms.
Understanding this model matters for daily life because it explains the treatment logic. Physiotherapy works by getting movement to happen while attention is elsewhere. Psychological therapy works by changing how the brain interprets bodily signals and by lowering the threat level that keeps the system on alert.
Who is usually referred for FND rehabilitation, and who is asked to wait
Referral for prescribed exercises and psychological support normally follows three things: a confident diagnosis from a neurologist, an explanation the person has heard and broadly accepts, and symptoms that interfere with daily life. The Mayo Clinic and the NHS describe treatment as most helpful when the person understands the diagnosis, because the exercises only make sense if you know why the limb is being distracted rather than strengthened.
People commonly referred include those with functional weakness or gait problems, functional tremor or dystonia (a term for sustained abnormal posture), functional seizures, functional speech difficulties, and persistent dizziness or sensory change with a functional pattern. Many have more than one symptom, and many also have pain, fatigue, poor sleep, anxiety or low mood alongside.
Some people are asked to wait, and the reasons are practical rather than dismissive. If investigations are still under way for another condition, therapists may hold off until the picture is clear, because FND and a structural disorder can coexist. If a person is medically unstable, in crisis, or has severe untreated depression, post-traumatic stress or an eating disorder, the treating team may address that first so that rehabilitation has a fair chance. Someone who has not yet had the diagnosis explained in a way they can accept is often offered a further consultation before therapy starts.
Children and adolescents follow a similar pathway, with family involvement and school liaison built in, and with an emphasis on comfort and gradual return to normal routines rather than medicine.
None of these decisions belongs to a leaflet. Who starts, who pauses and who is offered a specialist program depends on the local team’s assessment, and the plan should be revisited as circumstances change.
What do prescribed FND physiotherapy exercises actually involve?
A first surprise for many people is how little FND physiotherapy resembles a gym program. Repeated strengthening drills can make functional symptoms worse, because they focus attention exactly where it does harm. Instead, physiotherapists trained in FND work on getting normal movement to happen automatically and then building on it.
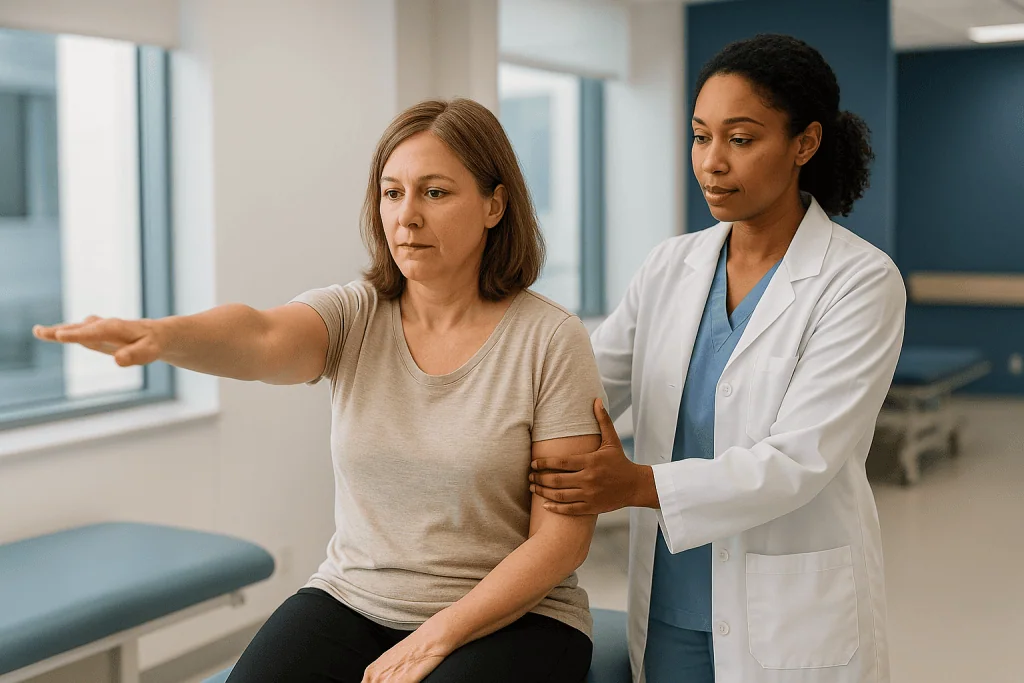
Sessions typically begin with education, often repeating a demonstration of the positive signs so the person can see their own leg working. From there, common strategies include moving while attention is redirected, such as walking while counting backwards or carrying a tray; using rhythm, like stepping to a beat or sliding the feet in a skating pattern; and changing the movement enough that the brain’s faulty program does not engage, for example walking sideways or backwards before walking forwards. Video feedback is sometimes used so that people can watch normal movement and recalibrate their sense of what the body is doing.
Home practice is usually short and frequent rather than long and exhausting, and it is agreed with the therapist rather than downloaded from the internet.
| Symptom type | What the person usually notices | Typical rehabilitation principle |
|---|---|---|
| Functional weakness | Limb gives way or feels heavy when concentrated on | Automatic movement first, attention elsewhere, gradual weight-bearing |
| Functional tremor | Shaking that changes with distraction | Entrainment tasks, rhythm, relaxed posture |
| Functional gait disorder | Unsteady or dragging walk despite good balance sitting | Altered patterns such as sideways or backward walking, then normal walking |
| Functional seizures | Episodes with warning feelings or dissociation | Warning-sign recognition, grounding, safety planning |
| Functional speech change | Stuttering, whisper or accent change | Speech therapy using automatic speech and singing |
Occupational therapists cover the same ground for daily tasks, and speech and language therapists for voice and swallowing. The table is a map, not a prescription; the treating team decides which route applies.
Rebuilding routines: pacing, sleep and the boom-and-bust trap
Ask people living with FND what wrecks a week and the answer is rarely one dramatic event. It is the good Tuesday. Symptoms ease, the backlog beckons, they clean the whole house and answer forty emails, and by Wednesday afternoon the leg is dragging again. Therapists call this boom and bust, and breaking the cycle is one of the most useful things a person can learn.
Pacing means setting an activity level you can sustain on a middling day and holding it steady, then increasing in small planned steps rather than in response to how you feel that morning. It is not about doing less forever. It is about doing a predictable amount so the nervous system stops swinging between overload and collapse.
Routine matters for a second reason. FND symptoms tend to worsen when attention turns inward, and an empty day invites exactly that. Getting up at a set time, eating at regular intervals, scheduling one purposeful task and one enjoyable one, and building in genuine rest gives attention somewhere else to go. The Mayo Clinic lists regular exercise, sleep and structured daily activity among the self-care measures that support treatment.
Sleep deserves its own attention. Poor sleep amplifies pain, fatigue, dizziness and dissociation, and many people find episodes cluster after bad nights. Standard sleep habits apply: a consistent wake time, daylight in the morning, screens and caffeine tapered in the evening, the bed reserved for sleep. If insomnia is entrenched, mention it, because it is treatable and often overlooked.
Rebuilding routines also includes work and study. Phased returns, adjusted hours and written explanations from the care team are ordinary requests, not special pleading, and planning them early tends to go better than improvising after a setback.
Stress management when living with FND
Being offered psychological therapy for a neurological diagnosis can feel like a contradiction, or worse, like an accusation. It is neither. Stress does not have to be the cause of FND for stress skills to help, in the same way that a person with asthma benefits from breathing techniques without their lungs being a psychological problem.
The link runs through the same mechanism described earlier. A nervous system on high alert monitors the body more closely, predicts threat more readily, and is more likely to trip into a functional symptom or a dissociative episode. Lowering that alert level widens the margin.
Cognitive behavioral therapy, usually shortened to CBT, is a structured talking therapy that examines how thoughts, attention and behavior feed one another. Applied to FND, it often focuses on how a person responds to early sensations, how avoidance narrows life, and how catastrophic predictions about symptoms can bring them on. Both the NHS and the Mayo Clinic list CBT among the psychological treatments offered.
Day-to-day tools are simpler than the theory. Slow breathing with a longer exhale, grounding through the senses, brief scheduled worry time instead of all-day rumination, and honest limits on commitments all help. So does naming the grief. Many people mourn the version of themselves who did not have to think about walking, and unspoken grief has a way of surfacing as symptoms.
Where past trauma is present, and it is for some people, trauma-focused therapy may be offered by a specialist. Where it is absent, no one should go looking for it. The therapist’s job is to work with the life in front of them, and the person’s job is to say plainly what is and is not on the table.
Functional seizures coping strategies for ordinary days
Functional seizures, also called dissociative seizures or non-epileptic attacks, are episodes of shaking, collapse or unresponsiveness that arise from a dissociative mechanism rather than the abnormal electrical bursts of epilepsy. The Cleveland Clinic notes they can look very similar to epileptic seizures from the outside, which is why the diagnosis is usually made by a neurologist, often with video-EEG monitoring, a test that records brain electrical activity on camera during an episode. Nobody should try to sort one type from the other at home.
Once the diagnosis is secure, day-to-day coping rests on three things. The first is noticing warning signs. Many people have a lead-in, sometimes a feeling of unreality, a rising heat, tunnel vision or a sense of dread, that lasts seconds to minutes. Learning to spot it creates a window.
The second is grounding during that window. Techniques include pressing the feet firmly into the floor, naming five things you can see and four you can hear, holding something cold, or focusing on a slow out-breath. Therapists rehearse these until they become reflexive, because a technique you have to remember is no use when dissociation is already under way.
The third is a written plan for the people around you. It usually says: keep the person safe from sharp edges, do not restrain or shout, speak calmly, note the time, and follow the agreed threshold for calling emergency services. Repeated ambulance trips are exhausting and often unnecessary, but the threshold belongs in the plan, set by the treating team, not in the moment.
Antiseizure medicines do not target functional seizures. If a person has been taking them because epilepsy was suspected earlier, any change is a decision for the prescribing clinician, since some people have both conditions.
FND vs chronic fatigue syndrome: what is the difference?
The two conditions are often confused because they share fatigue, brain fog, pain and a history of being disbelieved. They are not the same, and the difference changes how a person is asked to pace.
Chronic fatigue syndrome, also called myalgic encephalomyelitis or ME/CFS, is defined by profound fatigue that is not relieved by rest, has lasted at least six months according to the CDC’s description, and comes with post-exertional malaise, a worsening of symptoms after physical or mental effort that can arrive a day later and last for days. There is no positive neurological sign on examination; diagnosis rests on the pattern of symptoms and the exclusion of other causes.
FND, by contrast, is diagnosed on positive findings. The weakness, tremor or gait problem shows characteristic features when examined, such as Hoover’s sign or entrainment, that reveal intact pathways. Fatigue is common in FND but is not its defining feature.
The practical difference lies in exertion. In ME/CFS, pushing through post-exertional malaise tends to cause crashes, so pacing is about staying within an energy envelope. In FND, graded activity with attention redirected is a core treatment, and gentle challenge is usually encouraged. Someone with both, which happens, needs a plan that respects both rules, and that is a conversation for the treating team rather than a choice between camps.
Overlap is also why a person should not reassign their own diagnosis after reading online. If fatigue is the main problem and effort brings a delayed crash, say so at the next appointment. If a limb behaves differently when distracted, say that too. Accurate description helps the clinician decide whether one label, the other or both fit.
Medicines, supplements and CBD: what the evidence shows
People are often surprised to leave a neurology appointment without a prescription. The Mayo Clinic states plainly that no medicine has been shown to treat FND itself. Physiotherapy, occupational therapy and psychological therapy are the mainstays, and medicine enters the picture only for conditions that travel alongside.
Those companions are common. Depression and anxiety can maintain the alert state that feeds symptoms; chronic pain and migraine can act as triggers; insomnia worsens everything. Where a clinician judges that treating one of these will help, they may discuss medicine classes such as antidepressants, which act on brain chemical signaling and are also used for some pain conditions, or migraine preventives. How they are chosen, how long they take to work and whether they are worth the side effects are decisions for the prescribing clinician, weighed against the individual’s history. Starting, stopping or adjusting anything without that conversation carries real risk, particularly for antiseizure medicines in someone who might have both epilepsy and functional seizures.
CBD, short for cannabidiol, comes up constantly. It is a compound from the cannabis plant that does not cause a high and is sold widely as oils and gummies. There are no good-quality clinical trials showing that CBD improves FND symptoms. Some people report feeling calmer, which is plausible but not proven, and CBD can interact with other medicines by affecting how the liver processes them. Products also vary in content. Anyone considering it should tell their team first so that interactions can be checked.
The same caution applies to supplements marketed for nerves, energy or brain fog. Where a deficiency is found on testing, correcting it makes sense. Where it is not, the evidence for benefit in FND is absent, and the money is usually better spent on a good pair of walking shoes.
What is the relationship between COVID-19 and FND?
Clinicians began noticing functional neurological symptoms after COVID-19 infection early in the pandemic, and published case reports and small series have described weakness, tremor, gait problems and functional seizures emerging after the illness. This fits a pattern already known: infections, hospital stays and periods of fear and disruption are recognized triggers for FND, and COVID-19 supplied all three at once for millions of people. Similar reports followed vaccination in a small number of individuals, and expert commentary has framed these as functional reactions to the injection experience rather than damage from the vaccine contents.
What the evidence does not support is treating long COVID and FND as the same thing. Long COVID is a broad label for symptoms persisting after infection, and it includes changes in breathing, heart rhythm, smell, exercise tolerance and thinking that have their own mechanisms under investigation. Some people with long COVID also develop a functional overlay, particularly of movement or dizziness, and some have post-exertional malaise more typical of ME/CFS. Others have neither. Sorting this out requires examination for positive functional signs, not assumption in either direction.
For someone already living with FND, the practical questions are simpler. Any infection can provoke a flare, so it is sensible to plan for a temporary drop in activity during and after illness and to return to the pacing baseline afterwards rather than trying to catch up in a rush. Fever, dehydration and disrupted sleep all lower the threshold for episodes.
If new neurological symptoms appear after any infection, they need proper assessment. A previous FND diagnosis does not make a person immune to a stroke, a nerve injury or an inflammatory condition, and clinicians should examine each new symptom on its own terms.
What the first weeks and months of FND rehab usually look like
Recovery from FND rarely follows a straight line, and knowing the usual shape in advance saves a good deal of discouragement.
The first phase is understanding. Expect one or more appointments devoted to explaining the diagnosis, showing the positive signs, and answering the question everyone asks: are you saying I am making this up? The answer is no, and hearing it clearly is part of the treatment.
Therapy usually follows in blocks. The NHS and the Mayo Clinic describe rehabilitation taking place over weeks to months rather than days, with sessions spaced to allow home practice between them. Early gains can be quick, particularly for weakness and gait, because the moment a person sees their own leg move normally under distraction is itself therapeutic. Those gains are often uneven. A good fortnight is followed by a bad week, or the leg improves while a new tremor appears. Symptom migration is common and does not mean the approach has failed.
Psychological work, where it is part of the plan, tends to run on a longer clock and to feel slower, because attention habits and threat responses shift gradually. Sleep and pacing improvements often show up first as fewer terrible days rather than more brilliant ones.
MedlinePlus notes that symptoms may ease over time for many people and may return for some, sometimes years later, often around another trigger. A returning symptom is not a return to square one; the skills learned the first time usually work again, and a brief refresher with the therapist is a common arrangement.
Review points matter. Ask when progress will be formally reassessed, what would prompt a change of plan, and who to contact between appointments if things slide.
What people often get wrong about FND
The myths around FND do more day-to-day damage than most of the symptoms, so they deserve direct correction.
The first is that FND means faking. It does not. Faking is deliberate; FND is involuntary. The positive signs used for diagnosis, such as Hoover’s sign, depend on movements the person genuinely cannot produce on command yet does produce automatically, which is the opposite of what someone pretending would show.
The second is that FND is a diagnosis of exclusion, reached only when scans are normal and the doctor is out of ideas. The NHS and the Mayo Clinic both describe it as a diagnosis made on characteristic findings. A normal MRI supports the diagnosis but does not make it.
The third is that a clean scan means nothing is wrong. Something is wrong; it is at the level of brain function rather than structure, which standard scans do not measure.
The fourth is that rest is the treatment. Prolonged rest generally entrenches functional symptoms by narrowing life and increasing attention on the body. Movement, guided and paced, is the treatment.
The fifth is that FND always comes from childhood trauma. Trauma is a risk factor for some people and irrelevant for others, and insisting on a hidden cause can delay useful therapy.
The sixth is that FND is rare. The NIH’s neurological institute describes it as one of the more common reasons for a neurology consultation, which is why so many people recognize the story once they hear it.
The seventh is that a medicine will fix it. None treats the core condition. That is not a failure of the person or the doctor; it is a reason the plan is built from therapy and routine.
Correcting these ideas at home, at work and in the clinic is not a distraction from treatment. For many people it is where treatment begins.
FND support groups and other resources
Nobody rebuilds a routine alone, and the range of help available is wider than most people realize at diagnosis.
Within healthcare, the core team commonly includes a neurologist, a physiotherapist, an occupational therapist, a speech and language therapist where speech or swallowing is affected, and a psychologist or psychiatrist. Some regions offer specialist FND programs that bring these together; others rely on referrals between departments. Asking your neurologist or primary care clinician which route applies locally, and who coordinates it, is the first practical step.
Written information matters because the diagnosis is hard to explain to others. Reliable, neutral sources include the NHS, the Mayo Clinic, the Cleveland Clinic, MedlinePlus and the NIH’s neurological institute, all of which have plain-language pages that can be printed for family, employers or teachers. Patient organizations dedicated to FND exist in several countries and often run peer support groups, both in person and online.
Support groups help in specific ways. Hearing someone else describe the dog-walk paradox is a relief. Practical tips on pacing, on talking to a manager, on managing a functional seizure in a supermarket, tend to be more grounded than anything in a textbook. Two cautions apply: online groups can drift toward comparing worst days, which raises threat and attention in exactly the wrong direction, and they are not a place for medical advice about medicines or diagnoses. Take what steadies you and leave the rest.
Workplaces and schools can offer adjustments such as phased hours, rest breaks, written instructions and a quiet space for grounding. A short letter from the care team usually smooths the conversation.
Family and partners carry their own load. Many FND services offer a session for carers, and asking for one is reasonable.
Questions to ask your care team
Appointments are short and the diagnosis is unfamiliar, so a written list helps. These are the questions that tend to unlock the most useful answers.
- Which positive signs did you find on examination, and can you show me so I can recognize them myself?
- Are there any other conditions you are still checking for, and what would prompt further tests?
- Which of my symptoms are functional, and which, if any, have a different cause?
- Who will provide my physiotherapy, and do they have experience with FND specifically?
- What should my home exercises focus on, and what should I avoid doing between sessions?
- How should I pace activity on good days and bad days, and how will I know when to step up?
- Is psychological therapy part of my plan, what kind, and what would it focus on?
- If I have functional seizures, what should my written plan say about when to call emergency services?
- Are any of my current medicines being continued or reviewed because of this diagnosis, and what is the reasoning?
- Should I tell the driving authority, my employer or my school, and can you provide a letter?
- When will we formally review progress, and what would make you change the plan?
- Who do I contact between appointments if symptoms worsen or something new appears?
Bring someone with you if you can. A second set of ears catches what the first misses, and a partner or friend who has heard the explanation directly is far better placed to help at home. Ask for a copy of the clinic letter, and read it before the next visit. Decisions about tests, therapy and medicine rest with the team, but they are made better when the person in the chair arrives with the right questions.
When to call your doctor
An FND diagnosis does not switch off the rules that apply to everyone else. New symptoms deserve fresh assessment, and some patterns need urgent care regardless of history.
Call emergency services for sudden facial drooping, one-sided weakness or numbness that is new for you, sudden trouble speaking or understanding speech, sudden loss of vision, or the worst headache of your life. These can signal stroke or bleeding and cannot be distinguished from a functional flare without examination. The same applies to a seizure-like episode that runs far longer than your usual pattern or your written plan allows, episodes that follow one another without recovery, an episode with a serious injury, or breathing difficulty during or after one.
Seek same-day care for a high fever with a stiff neck or confusion; new loss of bladder or bowel control with back pain or numbness in the saddle area; chest pain, a racing or irregular heartbeat, or fainting; a head injury followed by vomiting or drowsiness; or any symptom that is clearly progressing hour by hour.
Contact your care team promptly, though not necessarily as an emergency, if symptoms change character, if a new symptom appears that you have not discussed, if you have become unable to leave the house, eat or care for yourself, if pain or sleep problems are escalating, or if you have started or stopped any medicine or supplement on your own.
Reach out immediately to your clinician or a crisis line if you have thoughts of harming yourself. Low mood is common alongside FND and is treatable, and it is never a sign of weakness to say so.
When in doubt, the safest rule is simple: a previous diagnosis explains previous symptoms. New ones get their own hearing.
Frequently asked questions
Can CBD help manage symptoms of FND?
There is no good-quality clinical evidence that CBD improves FND symptoms. Some people report feeling calmer, which is plausible but unproven, and calm alone does not retrain movement. CBD can also interact with other medicines by changing how the liver processes them, and products vary widely in content. Anyone considering it should tell their care team first so interactions and safety can be checked.
What is the difference between FND and CFS?
FND is diagnosed on positive neurological signs that show intact pathways, such as weakness that disappears under distraction. ME/CFS is diagnosed on a symptom pattern of profound fatigue lasting at least six months with post-exertional malaise, according to the CDC. The practical difference is exertion: FND rehabilitation encourages graded, distracted movement, while ME/CFS pacing avoids triggering crashes. Some people have both and need a combined plan.
What resources are available for people with FND?
Core resources are the clinical team: neurologist, physiotherapist, occupational therapist, speech therapist where needed, and a psychologist. Plain-language information from the NHS, Mayo Clinic, Cleveland Clinic, MedlinePlus and the NIH’s neurological institute can be shared with family and employers. Patient organizations in several countries run peer support groups, and workplaces and schools can provide adjustments with a letter from the care team.
What is the relationship between COVID-19 and FND?
Published case reports describe functional neurological symptoms emerging after COVID-19 infection, consistent with infection and stress being recognized triggers for FND. Long COVID is a broader condition with its own mechanisms and is not the same as FND, although some people have both. Any new neurological symptom after an infection should be examined on its own terms rather than assumed to be functional.
What are the best FND physiotherapy exercises to do at home?
The right home exercises are the ones your physiotherapist prescribes after examining you, because FND rehabilitation uses distraction, rhythm and altered movement patterns rather than strengthening. Common examples include walking while counting backwards, stepping to a beat or sideways walking before forward walking. Generic online routines that focus attention on the weak limb can make symptoms worse, so agree the plan in person.
Which functional seizures coping strategies work during an episode?
Coping rests on recognizing your personal warning signs, then grounding before dissociation takes hold: pressing feet into the floor, naming things you can see and hear, holding something cold, or slowing the out-breath. A written plan for bystanders should say to keep you safe, stay calm, avoid restraint, note the time and follow the emergency threshold set by your care team.
Does FND get better?
Many people improve with rehabilitation, and MedlinePlus notes that symptoms may ease over time for many while returning for some, often around a new trigger. Progress is typically uneven, with symptoms sometimes shifting from one form to another during treatment. A returning symptom does not mean starting over; skills learned the first time usually work again, sometimes with a short refresher. Outcomes cannot be promised for any individual.
Is FND all in my head?
No, not in the sense people mean. FND symptoms are involuntary and are produced by a genuine problem in how the brain controls movement, sensation or awareness. The positive signs used for diagnosis depend on movements a person cannot produce on command yet does produce automatically, which is the opposite of pretending. The brain is involved because it is the organ that controls the body, not because the symptoms are imagined.
Can I drive or work with FND?
It depends on your symptoms, and the rules on driving vary by country and state, so ask your care team and check the licensing authority’s requirements, particularly if you have functional seizures or episodes of loss of awareness. Many people continue working with adjustments such as phased hours, rest breaks and a quiet space for grounding. A short letter from the care team usually makes those conversations easier.
Should I stop my medicines now that I have an FND diagnosis?
No change should be made without the prescribing clinician. Although no medicine treats FND itself, you may be taking medicines for conditions that coexist, such as migraine, depression or pain, and some people have both epilepsy and functional seizures. Stopping suddenly can be harmful. Ask at your next appointment which medicines are being continued, which are under review, and why.
References
- NIH National Institute of Neurological Disorders and Stroke: Functional Neurologic Disorder
- MedlinePlus: Conversion disorder
- CDC: About ME/CFS
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What Do Lumbar Puncture, Imaging and Blood Tests Show in Neuroinfectious Disease Care?
In neuroinfectious disease care, a lumbar puncture samples cerebrospinal fluid, the clear liquid around the brain and spinal cord, so laboratories can count cells,…

What to Expect After a Neuroendoscopic Procedure: Blocked Nose, Headache and No-Lifting Weeks
Recovery after neuroendoscopic surgery, most often performed through the nose to reach the pituitary gland or skull base, typically involves a hospital stay of…

Medication-Overuse Headache: Why Headache Medicine Plans Watch Pain Reliever Use Closely
Medication-overuse headache is a near-daily headache that develops when acute pain relievers are taken on many days each month for several months, so the…

What Does an MRI Show in Spinal Cord Disorders, and Which Other Tests Follow?
An MRI shows the spinal cord itself in fine detail: swelling, inflammation, compression from a disc or bone, tumors, bleeding, fluid-filled cavities and scarring.…

Living With Peripheral Neuropathy: Foot Care, Balance Training and Daily Safety
Living with peripheral neuropathy is usually a matter of protecting what you cannot fully feel and strengthening what you can still control. Daily foot…
MRI, Lumbar Puncture or Evoked Potentials: Which Tests Confirm a Demyelinating Disease?
No single test confirms a demyelinating disease. Doctors combine a neurological examination with MRI of the brain and spinal cord, which shows areas of…