

Doppler Ultrasound and Ankle-Brachial Index: How Peripheral Vascular Disease Is Staged

Key Takeaways
- An ankle-brachial index of 0.90 or below is consistent with peripheral artery disease, while a value above 1.4 means the ankle arteries are too stiff to measure and a toe pressure or imaging is needed instead.
- Duplex Doppler ultrasound combines a gray-scale picture of the artery wall with a measurement of blood speed, so it can show both where plaque sits and how much flow it is costing.
- A resting ABI can be normal in someone with genuine claudication; walking on a treadmill and re-measuring ankle pressure immediately afterward is how that hidden disease is exposed.
- Fontaine stages I to IV and Rutherford categories 0 to 6 describe the same spectrum, from silent narrowing through walking pain to rest pain and tissue loss, and the last two stages are called chronic limb-threatening ischemia.
- A Doppler leg exam typically takes about 30 to 60 minutes, needs no fasting or dye, and has no recovery period, which is why it is repeated to track progress rather than replaced by CT or catheter angiography.
- A low ABI is a marker of atherosclerosis throughout the body, so results usually prompt a conversation about heart and stroke risk, not just the leg.
Peripheral artery disease is staged by combining what a person feels with what two painless tests measure. The ankle-brachial index compares blood pressure at the ankle with pressure at the arm; a ratio of 0.9 or below suggests narrowed leg arteries. Doppler ultrasound for PAD then maps where flow slows and by how much. Clinicians place these findings on a staging scale, such as Fontaine or Rutherford, to guide next steps.
The walk to the end of the driveway used to take no thought at all. Lately the left calf tightens after fifty paces, like a fist closing, and eases only when he stops to pretend he is checking the mailbox. His primary care clinician listened, pressed two fingers against the top of his foot for a pulse she could barely find, and ordered something called a Doppler ultrasound for PAD along with an ankle-brachial index.
The referral slip raised more questions than it answered. Is this a big test? Does it hurt? Will someone tell him, at the end, how bad things are?
Those are the right questions, because these two tests do more than confirm that leg arteries are narrowed. Together they give clinicians a staging language: a way to describe how far the disease has progressed, how urgently it needs attention, and which options make sense. This article walks through both tests, the numbers they produce, and what those numbers mean for what happens next.
Can ultrasound detect PAD? What Doppler ultrasound for PAD actually shows
Yes. Ultrasound can detect peripheral artery disease, and in most vascular laboratories it is the first imaging test used once a simple pressure test raises suspicion. Peripheral artery disease, or PAD, is the buildup of fatty plaque inside the arteries that carry blood to the legs, the same process that narrows heart arteries. According to the American Heart Association, people with PAD carry a higher risk of heart attack and stroke, which is one reason clinicians take a cramping calf seriously.
A standard ultrasound bounces sound waves off tissue and turns the echoes into a gray picture. Doppler ultrasound adds a second layer: it measures how sound changes pitch when it reflects off moving red blood cells, the same effect that makes a siren rise and fall as an ambulance passes. That shift is converted into a speed. When the two techniques run together, clinicians call it duplex ultrasound, meaning one image shows the artery wall and plaque while the other shows the flow within it.
The result is a map. A sonographer can follow the main leg artery from the groin down past the knee, watching flow speed up sharply where the channel narrows and fall off or disappear where it is blocked. A narrowing is called a stenosis; a complete block is an occlusion. MedlinePlus describes Doppler ultrasound as a noninvasive way to estimate blood flow through vessels without needles, dye or radiation, which is why it sits ahead of CT or catheter angiography in the usual sequence.
What ultrasound cannot do is measure how the whole leg is coping. That is where the ankle-brachial index comes in, and why the two tests are nearly always read together.
What is the ankle brachial index test, and why is it usually done first?
The ankle brachial index test is the simplest measurement in vascular medicine, and arguably the most useful. Brachial refers to the upper arm, where blood pressure is normally measured. Ankle pressure is taken the same way, with a cuff, except the technician uses a small handheld Doppler probe instead of a stethoscope to hear the pulse return as the cuff deflates. The two pressures are divided: ankle over arm.
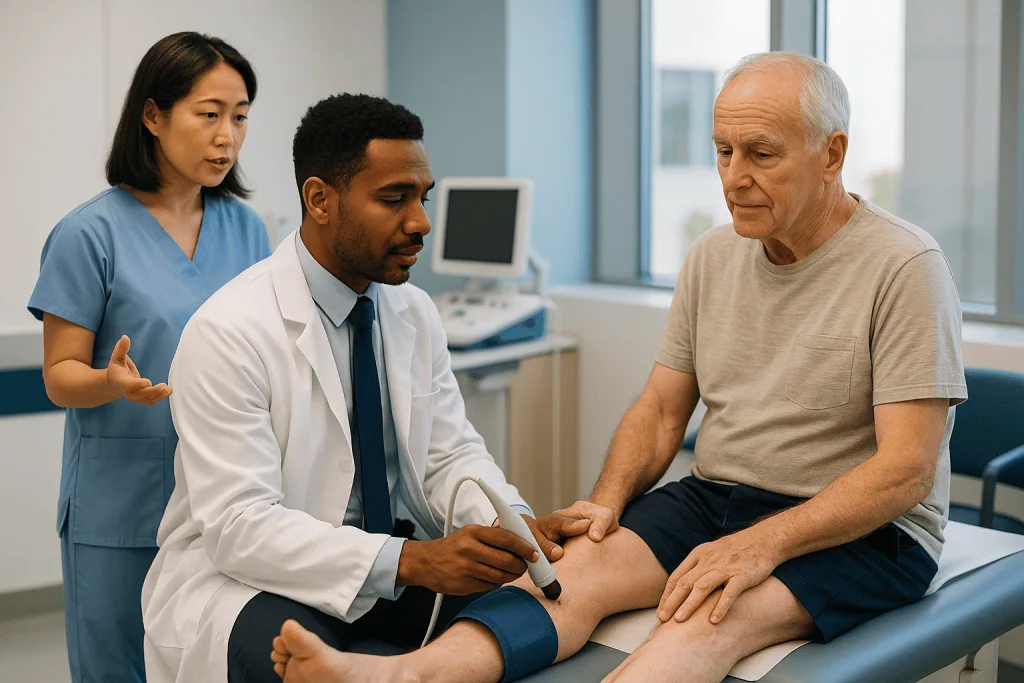
The logic is elegant. In healthy arteries the pressure at the ankle is roughly the same as, or slightly higher than, at the arm, because the vessels are open highways all the way down. Plaque acts like a partly closed valve; the further downstream you measure, the more pressure has been lost. A low ankle reading relative to the arm is therefore indirect proof of a narrowing somewhere above it.
Mayo Clinic describes the ankle-brachial index as a quick, noninvasive test that most people can have without any preparation, usually lying flat for a few minutes while cuffs are inflated on both arms and both ankles. Each leg is scored separately, so a person can have a normal reading on one side and an abnormal one on the other, which itself is a clue about where the problem sits.
Clinicians favor the ABI as a first step for three reasons. It is fast. It puts a single number on overall leg circulation rather than describing one segment of one artery. And it is reproducible, so the same measurement repeated after months of treatment or after a procedure can show whether circulation has changed. Doppler imaging answers where; the ABI answers how much, for the leg as a whole.
ABI results explained: what the number on the report means
Most reports print a decimal for each leg. Reading it is not difficult once you know the ranges clinicians use, which Mayo Clinic summarizes as follows.
| ABI value | Usual interpretation | What typically follows |
|---|---|---|
| 1.0 to 1.4 | Normal, no significant narrowing detected | Risk-factor review; repeat only if symptoms change |
| 0.91 to 0.99 | Borderline | Often an exercise ABI or closer follow-up |
| 0.90 or below | Consistent with PAD | Duplex Doppler to locate the narrowing; staging |
| Above 1.4 | Arteries too stiff to compress; result unreliable | Toe pressures or imaging instead |
Two points deserve emphasis. First, the lower the number, the more severely the leg is deprived of pressure, and the more concerned a vascular team becomes about the survival of skin and tissue, particularly if there is a wound. Second, a normal ABI at rest does not close the door. Some people with genuine claudication, the medical term for muscle pain brought on by walking and relieved by rest, have normal resting pressures because the narrowing only matters when the muscle demands more blood. That is the scenario the borderline row is designed to catch, and it is why walking tests exist.
The value above 1.4 puzzles many patients, who assume a higher number must be better. It is not. It means the ankle arteries have become so hardened, often by calcium in long-standing diabetes or kidney disease, that the cuff cannot squeeze them shut. The test has not shown good circulation; it has failed to measure it. In that situation clinicians switch to a different approach, described later.
Doppler ultrasound for PAD: what actually happens in the room
The room is usually dim, and there is a padded table, a monitor angled so the sonographer can watch it, and a bottle of warm gel. You will be asked to remove trousers or roll them well above the knee, and to lie on your back. There are no needles and no injection of dye.

The sonographer, a technologist trained in vascular imaging, spreads gel along the groin crease and rests a smooth handheld probe against the skin. The gel is there to eliminate the air gap that would otherwise scatter the sound waves. The probe is moved slowly downward along the inner thigh, behind the knee, and along the calf toward the ankle, pausing at each segment of artery.
Three things are being recorded at each stop. The gray-scale image shows the artery wall and any plaque, which appears as a pale or speckled thickening inside the channel. The color overlay paints flow moving toward the probe one color and away another, and turns a mottled mosaic where flow becomes turbulent, which happens just beyond a narrowing. The spectral waveform, the jagged graph you may see scrolling at the bottom of the screen, plots speed against time for each heartbeat.
Healthy leg arteries produce a crisp three-part waveform: a sharp forward surge, a brief backward flick, then a small forward bump. Downstream of a significant blockage the waveform flattens and rounds off, and the audible Doppler signal, which the sonographer may turn up, softens from a whip-crack to a low whoosh. Speeds are also compared: a marked jump in velocity at one point, relative to the segment just above it, marks the narrowing. You may feel firm pressure, and the probe may need to be angled around the knee, but the exam is not painful.
How long does an arterial Doppler leg test take, and how do you prepare?
Set aside an hour. MedlinePlus notes that a Doppler ultrasound usually takes about 30 to 60 minutes, and a full arterial Doppler leg test of both legs sits toward the longer end because each artery segment is imaged and measured separately. If the ankle-brachial index is done in the same visit, which is common, add the time it takes to inflate and deflate four cuffs while lying still.
Preparation is minimal, which surprises people used to fasting for other scans. There is no need to stop eating or drinking. Wear loose clothing that can be pushed above the knee, or expect a gown. Most laboratories ask that you avoid nicotine for an hour or two beforehand, because nicotine narrows small arteries and can lower ankle pressures enough to muddy the result; if you use tobacco, ask the booking team what they prefer rather than guessing. Caffeine is sometimes restricted for the same reason.
Continue taking prescribed medicines as usual unless the ordering clinician tells you otherwise. This test does not require any changes, and stopping a blood thinner or blood pressure medicine on your own initiative would introduce a risk without improving the scan.
Bring a list of your current medicines and, if you have them, any previous vascular reports. If your legs cramp when you walk, tell the sonographer how far you can go before the pain starts; some laboratories will add a short treadmill walk followed by a repeat ankle pressure, and knowing your typical distance helps them plan it safely.
Results are not usually discussed in detail by the sonographer. The images and measurements go to a physician who reads vascular studies, and the ordering clinician then talks them through with you.
PAD staging classification: Fontaine and Rutherford in plain language
Staging means placing a disease on a scale so that clinicians in different places describe the same thing the same way. For PAD, two scales are in wide use. The Fontaine classification, used often in European guidelines, has four stages. The Rutherford classification, more common in North American practice, has seven categories that map onto Fontaine with finer subdivisions. Both are built on symptoms and examination findings; the ABI and Doppler results are used to confirm and quantify what the stage describes.
- Fontaine I, Rutherford 0: narrowing is present on testing, but the person has no leg symptoms. Many people sit here for years.
- Fontaine II, Rutherford 1 to 3: intermittent claudication, the walking-induced cramp that stops within minutes of rest. Fontaine splits this into IIa, pain after a longer walk, and IIb, pain after a short one. Rutherford grades it mild, moderate or severe.
- Fontaine III, Rutherford 4: rest pain, typically in the foot or toes, often worse at night when the leg is level and eased by dangling it over the edge of the bed. Blood supply is now insufficient even for a muscle at rest.
- Fontaine IV, Rutherford 5 and 6: tissue loss, meaning an ulcer that will not heal or an area of gangrene, which is tissue that has died from lack of blood. Rutherford distinguishes minor from major tissue loss.
Stages III and IV together are called chronic limb-threatening ischemia. Ischemia simply means a shortage of blood supply. The label signals that the limb itself, not just walking distance, is at risk, and it changes the pace of decision-making from months to weeks or days.
Why stage at all? Because treatment intensity should match the threat. Someone at Fontaine I needs risk-factor management and monitoring; someone at Fontaine IV needs a vascular team looking at restoring flow promptly. The stage keeps that proportion honest.
When the ABI misleads: stiff arteries, diabetes, toe pressures and the treadmill test
Every measurement has blind spots, and the ankle-brachial index has two that matter.
The first is arterial stiffness. In long-standing diabetes and in chronic kidney disease, calcium can deposit in the muscular wall of the ankle arteries until they behave like garden hose left out for a decade. The blood pressure cuff cannot flatten them, so the Doppler signal never disappears and the recorded ankle pressure is falsely high. This is the mechanism behind an ABI above 1.4. The person may in fact have severe disease hidden behind a reassuring number. Vascular laboratories handle this by measuring pressure at the big toe instead, using a tiny cuff, because the small toe arteries are far less likely to calcify. Dividing toe pressure by arm pressure gives the toe-brachial index, which is read on its own scale. Waveform shape from the Doppler exam adds further evidence: a flattened, rounded signal at the ankle argues for disease regardless of what the cuff says.
The second blind spot is the resting normal. Muscle at rest needs relatively little blood, so a moderate narrowing may leave resting ankle pressure untouched. Ask that muscle to work and the story changes. In an exercise ABI, described by both Mayo Clinic and the NHS, the person walks on a treadmill at a set pace and gentle incline until symptoms appear or a time limit is reached, then lies down while ankle pressures are quickly re-measured. A pressure that drops sharply after walking, and takes several minutes to recover, unmasks disease that a resting test missed. It also gives a useful baseline: the walking distance at which pain begins can be compared at later visits.
Neither workaround makes the ABI redundant. They are refinements that a good laboratory reaches for when the plain reading does not fit the person in front of them.
Who is usually offered Doppler ultrasound for PAD, and who is asked to wait
Referral generally follows one of three routes. The most common is symptoms: cramping, aching or fatigue in the calf, thigh or buttock that arrives with walking and leaves with rest, or a foot sore that has not closed after weeks of ordinary care. The second is examination: a clinician who cannot feel a foot pulse, hears a whooshing sound over the groin artery, or notices one foot cooler and paler than the other. The third is risk: Cleveland Clinic lists smoking, diabetes, high blood pressure, high cholesterol, kidney disease and older age as the main drivers of PAD, and clinicians may test people with several of these even without complaints, particularly before certain surgeries or when a foot ulcer needs a healing forecast.
People asked to wait, or not tested at all, tend to fall into other groups. Someone with leg pain that is present at rest from the start, worse with standing still and eased by sitting or bending forward, is more likely to have a spinal nerve problem than an arterial one, and is usually pointed toward a different evaluation first. Someone whose ankle swelling and aching improve with elevation is being assessed for vein rather than artery disease, which uses a related but distinct ultrasound protocol. Younger people with no risk factors and pain confined to a joint are often watched or referred to musculoskeletal care.
A borderline ABI in a person without symptoms is a common gray zone. Many teams choose to repeat the measurement after an interval, or to add an exercise test, rather than move straight to full imaging. That is not neglect; it is matching the intensity of testing to the likelihood of finding something that would change the plan. The ordering clinician makes that call, and it is reasonable to ask why they have chosen the path they have.
From stage to plan: what the results usually lead to
Stage does not dictate a single treatment, but it sets the range of options a team will discuss. The NHS and Mayo Clinic describe the same broad architecture.
For early and moderate disease, the foundation is risk-factor control and structured walking. Supervised exercise programs, in which people walk to the point of moderate claudication, rest, and repeat over a session several times a week, are recommended by the NHS as a first-line measure. The mechanism is partly improved muscle efficiency and partly the encouragement of collateral vessels, small side channels that widen over time to route blood around a blockage. Stopping smoking is the single intervention with the largest effect on disease progression, according to both sources.
Medicines are usually discussed at every stage. The NHS lists cholesterol-lowering statins, which slow plaque growth and stabilize existing plaque, and antiplatelet agents, which make blood cells less likely to clump on a roughened artery wall, as commonly prescribed classes, along with treatment for blood pressure and diabetes. Whether any of these is right for a given person, and how it is started, is a decision for the prescribing clinician who knows the whole medical picture; this article describes the categories only so the conversation is easier to follow.
When symptoms limit daily life despite these measures, or when the stage reaches rest pain or tissue loss, the team considers restoring flow. Angioplasty threads a small balloon through the artery to a narrowing and inflates it, sometimes leaving a mesh stent to hold the channel open. Bypass surgery sews a vein or synthetic tube around a long blockage. Each carries risks and each has situations in which it is more or less suitable, and the Doppler map is what tells the team which, if either, is anatomically feasible.
When imaging goes further: CT, MR and catheter angiography as the next steps
Duplex Doppler answers most staging questions, but it has limits. Sound waves struggle to penetrate heavily calcified plaque, which casts a shadow, and the arteries below the knee can be hard to trace in a swollen or very muscular leg. When a procedure is being planned, surgeons also want a single continuous picture of the whole arterial tree from the aorta to the foot. Mayo Clinic lists three tools for that.
Computed tomography angiography, or CT angiography, injects iodine-based contrast dye through an arm vein and takes rapid X-ray slices as it flows through the legs. It is quick and detailed, but it involves radiation and the dye can strain kidneys that are already weak, a real consideration since kidney disease and PAD often travel together.
Magnetic resonance angiography uses magnetic fields rather than radiation, with or without a different contrast agent. It avoids X-ray exposure and shows soft tissue well, but the scan is longer, the machine is confining, and certain implanted devices and metal fragments rule it out.
Catheter angiography is the oldest and most direct method: a thin tube is inserted into an artery, usually at the groin or wrist, and dye is injected while X-ray images are taken. Because the catheter is already in place, a narrowing found this way can sometimes be treated with angioplasty in the same session. The trade-off is that it is invasive, with a small risk of bleeding, artery damage or contrast reaction at the puncture site.
None of these replaces the ABI or Doppler for follow-up. Once a plan is made, the noninvasive tests remain the way progress is tracked, precisely because they can be repeated as often as needed without harm.
What the following days and weeks usually look like
The tests themselves leave no trace. There is no recovery period from an ABI or a Doppler exam; people drive themselves home and return to work the same day. The only thing to wipe off is the gel.
The waiting is the harder part. Images are read by a physician and a written report goes to the clinician who ordered the study. Depending on how the laboratory is organized, that can happen the same day or take a week or more, and the results conversation is usually a scheduled follow-up rather than a phone call. If you have not heard anything within the period you were told to expect, it is reasonable to call the ordering office rather than assume no news means good news.
The shape of the weeks that follow depends on stage. A normal or borderline result generally leads to a discussion of risk factors and perhaps a repeat test after a defined interval. A result consistent with claudication usually opens a conversation about walking programs, smoking, and whether medicines should be started or adjusted, with a plan to re-measure the ABI and walking distance after some months. The NHS notes that symptoms of PAD often develop slowly and that many people stabilize or improve with these measures over time, though the pace varies widely from person to person.
A result that places someone in the limb-threatening range moves faster. Referral to a vascular specialist is typically arranged promptly, further imaging is booked, and wound care, if there is an ulcer, begins in parallel rather than waiting for the imaging to finish. Ask, at the results visit, which of these paths you are on and what the expected interval to the next step is, so that the timeline is something you hold rather than something that happens to you.
What people often get wrong about Doppler, the ABI and PAD
“A higher ABI means better circulation.” Only up to a point. Above 1.4, the number signals arteries too stiff to compress and says nothing reliable about flow. Treat it as a request for a different test, not a clean bill of health.
“If the ultrasound is normal, my legs are fine.” Duplex Doppler is excellent at what it images, but a resting exam in a person whose pain only appears after several hundred meters of walking may miss a narrowing that matters only under load. That is why the exercise ABI exists, and why a normal test in someone with a convincing story usually prompts a second look rather than reassurance.
“Doppler and Doppler are the same thing.” The small handheld probe used to hear the pulse during an ABI and the full imaging system used for a duplex exam share a physical principle but do very different jobs. One listens; the other maps. A report that says only “Doppler pulses present” is not the same as an arterial duplex study.
“Leg pain from PAD feels like a pulled muscle.” Claudication is predictable and mechanical: it comes at roughly the same distance each time and goes away with rest. Pain that is there before you stand up, or that changes with posture, points elsewhere.
“Staging is about the leg only.” The AHA emphasizes that PAD is a marker of atherosclerosis throughout the body. A low ABI raises the question of heart and brain artery health as well, and the follow-up plan usually reflects that.
“A stent fixes the problem.” Restoring flow through one segment does not stop plaque forming elsewhere. The same risk-factor work continues afterward, and the ABI is how the team checks that the repaired channel stays open.
Questions to ask your care team
A results visit goes better with a short list in hand. These questions are phrased so the answers will tell you something you can act on.
- What was my ABI in each leg, and which row of the interpretation table does it fall into?
- Did the Doppler show a narrowing or a complete blockage, and roughly where along the leg is it?
- Which stage, on Fontaine or Rutherford, best describes my situation right now?
- Was my resting ABI enough, or would an exercise test or toe pressures add information?
- Do I have signs that the limb itself is at risk, or is this about walking distance and long-term prevention?
- What is the plan for the next few months, and what result at the follow-up test would change it?
- Are you recommending a supervised exercise program, and how do I get into one?
- Which of my current medicines are relevant to PAD, and are you proposing any changes? If so, what is each one meant to do?
- What symptoms should make me call before the scheduled follow-up?
- Do these results say anything about my heart or stroke risk, and does that change any other testing?
- If a procedure is on the table, what would it involve, what are the alternatives, and what happens if I choose to wait?
Write down the numbers as they are given. A future clinician comparing readings will want the exact ABI and the segment where flow was abnormal, not a recollection that it was “a bit low.” It is also fair to ask for a copy of the written report; most laboratories can provide one, and having it makes every subsequent conversation more precise.
When to call your doctor
Most people with PAD move through testing and follow-up on a schedule set by their team. A few situations should prompt a call the same day, or emergency care if the office is closed, because they suggest that blood supply to the leg has fallen suddenly or that tissue is beginning to fail.
Seek urgent help if a leg or foot becomes suddenly pale, cold, numb or weak, particularly if the pain is severe and arrived over minutes to hours rather than months. This pattern can mean an artery has blocked completely, often from a clot, and the window for restoring flow is short. Do the same if you cannot move the foot or toes normally, or if the skin turns a mottled blue-gray.
Call promptly, within a day, if foot or toe pain begins to wake you at night and is eased only by hanging the leg down; if a sore, crack or blister on the foot fails to improve after a week or two; if any wound develops redness that spreads, a foul smell, or discharge; or if an area of skin darkens toward black. In someone with diabetes, whose nerves may not register pain, any new foot wound deserves a call regardless of how it feels.
Contact your team also if walking distance shortens noticeably over weeks, if you develop chest pain, breathlessness or sudden weakness or speech difficulty, which point to the heart and brain arteries the AHA links to PAD, or if a scheduled follow-up test has not been arranged when you were told it would be. The staging described in this article is a tool for the treating team, and every decision about testing, medicines and procedures rests with them and with you together. When in doubt about a symptom, the safest reading of this article is: make the call.
Frequently asked questions
Can an ultrasound detect peripheral artery disease?
Yes. Duplex Doppler ultrasound is the standard first imaging test for suspected PAD. It shows plaque inside the leg arteries on a gray-scale image and measures how fast blood moves through each segment, so a narrowing appears as a sharp rise in speed and a blockage as an absence of flow. Its main limits are heavily calcified vessels and moderate narrowings that only matter during exercise, which is why it is read alongside the ankle-brachial index.
How long does an arterial Doppler take?
Plan for roughly 30 to 60 minutes, according to MedlinePlus, with a two-leg arterial study usually toward the longer end because each artery segment is imaged and measured separately. If the ankle-brachial index is done in the same visit, add the few minutes needed for cuff readings on both arms and both ankles. There is no recovery time afterward and you can drive yourself home.
What is an ankle brachial index test and does it hurt?
The ankle brachial index test compares blood pressure at the ankle with blood pressure at the arm, using an ordinary cuff and a small handheld Doppler probe to detect the pulse. Dividing ankle pressure by arm pressure gives a ratio; 1.0 to 1.4 is considered normal and 0.9 or below suggests PAD. The cuff squeezes firmly for a few seconds at each site, much like a routine blood pressure check, but the test is not painful.
What are three signs of peripheral arterial disease that lead to testing?
The pattern clinicians look for is muscle pain in the calf, thigh or buttock that comes on with walking and fades within minutes of rest; a foot or toe wound that does not heal over several weeks; and a foot that is noticeably cooler or paler than the other, sometimes with a pulse that is hard to feel. None of these confirms PAD on its own, which is why the ABI and Doppler exist; they are reasons to be assessed, not a self-diagnosis.
What does the PAD staging classification mean on my report?
Staging places your disease on a shared scale so every clinician describes it the same way. Fontaine uses stages I to IV: no symptoms, walking pain, rest pain, and tissue loss. Rutherford covers the same ground in categories 0 to 6 with finer steps. The stage is set mainly by symptoms and examination, then confirmed and quantified by the ABI and Doppler findings, and it guides how quickly and how intensively the team acts.
Why was my ABI above 1.4 if my legs hurt?
A reading above 1.4 does not mean excellent circulation. It means the ankle arteries were too stiff, usually from calcium deposits linked to diabetes or kidney disease, for the cuff to compress them, so the pressure recorded is falsely high. In that situation the test has failed to measure flow rather than shown it to be good. Teams typically switch to toe pressures, look closely at the Doppler waveform shape, or move to imaging.
Do I need to fast or stop my medicines before an arterial doppler leg test?
No fasting is needed and you should continue your usual prescribed medicines unless the ordering clinician says otherwise. Most laboratories ask you to avoid nicotine, and sometimes caffeine, for an hour or two beforehand because both can narrow small arteries and lower ankle pressures. Wear clothing that can be pushed above the knee, and tell the sonographer how far you can walk before pain begins, in case a treadmill test is added.
How much does an arterial Doppler test for legs cost?
This article does not quote prices, because the amount a person actually pays depends on the setting, whether the ABI and imaging are billed together, and the details of their insurance or health system. The practical route is to ask the ordering office for the procedure codes being requested and then check coverage with your insurer or the laboratory’s billing department before the appointment, so there are no surprises afterward.
Can a Doppler ultrasound be normal and I still have PAD?
Yes. A resting duplex exam images the arteries well, but a moderate narrowing that only limits flow when muscles are working hard may look unremarkable at rest. If your symptoms are typical of claudication and the resting tests are normal or borderline, clinicians often add an exercise ABI, in which ankle pressure is re-measured immediately after a treadmill walk. A pressure that drops sharply after walking reveals disease the resting study missed.
What happens after the Doppler and ABI if PAD is confirmed?
The stage guides the plan. Early or moderate disease usually leads to structured walking, smoking cessation and a review of medicines such as cholesterol-lowering and antiplatelet classes, with a repeat ABI after some months to track change. Rest pain or a non-healing wound moves faster, with prompt vascular referral and often CT or MR angiography to plan a procedure. Every one of those decisions is made by your treating team with you.
References
- MedlinePlus: Doppler Ultrasound
- NHS: Peripheral arterial disease (PAD)
- Cleveland Clinic: Peripheral Artery Disease (PAD)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Chronic Total Occlusion (CTO) of a Coronary Artery: How Treatment Is Chosen and Why
Chronic total occlusion treatment options fall into three groups: medicines with risk-factor control, a specialized catheter procedure (CTO PCI) that reopens the artery and…

Can Atrial Fibrillation Be Cured, and Can Anxiety Cause It?
Atrial fibrillation is usually described as manageable rather than curable. Treating triggers, restoring rhythm with cardioversion, or catheter ablation can keep some people free…

Daily Life With Pulmonary Hypertension: Supervised Exercise, Oxygen and Pacing Your Day
Living with pulmonary hypertension usually means combining three things under medical supervision: a structured exercise program adapted to your limits, oxygen when tests show…

Questions to Ask Your Electrophysiologist Before Starting Cardiac Arrhythmia Treatment
Before starting cardiac arrhythmia treatment, ask your electrophysiologist exactly which rhythm problem you have and what is driving it, how urgent treatment is, what…

Cardiometabolic Disorders: Why Weight, Blood Sugar and Blood Pressure Are Treated as One Plan
Cardiometabolic disorders are a linked group of conditions, including excess abdominal fat, insulin resistance and type 2 diabetes, high blood pressure and abnormal cholesterol…

When Do Heart Rhythm Disorders Need a Cardiologist? How Treatment Is Planned Step by Step
Most heart rhythm disorders are first assessed by a primary care clinician, who refers to a cardiologist when an ECG shows an abnormal rhythm,…