

Fever, Pain or Low Urine Output After Hydronephrosis Treatment: When to Call Your Team

Key Takeaways
- A ureteral stent or nephrostomy relieves pressure by bypassing a blockage; it does not remove the cause, so fever after placement is treated as a possible sign of failed drainage until imaging shows otherwise.
- A brief low-grade temperature within the first 24 hours can follow instrumentation, but a fever of 38°C (100.4°F) or higher at any point, or chills after day one, should be reported the same day.
- Flank twinges during urination are caused by urine pushing back up the open ureter with each void and are an expected stent sensation, whereas pain that steadily builds over hours is not.
- Not passing urine, or a nephrostomy bag that stays empty for several hours while you drink normally, is listed by the NHS and CDC among possible sepsis signs and warrants urgent contact.
- Sepsis signs include fever or feeling very cold, fast heart rate, fast breathing, confusion, clammy or mottled skin, and extreme pain, and they require emergency services rather than a routine call.
- Kidney recovery from hydronephrosis depends mainly on how long pressure was present; prompt relief usually preserves function, while prolonged obstruction can cause permanent scarring in that kidney.
A mild, short-lived temperature in the first day after a ureteral stent or nephrostomy can occur, but a fever of 38°C (100.4°F) or higher, shaking chills, worsening flank pain, or urine output that falls sharply or stops should be reported to your treating team the same day. Fever combined with confusion, fast breathing, or a racing heart may signal sepsis and needs emergency care.
It is two in the morning, three days after the stent went in, and the thermometer reads a shade over 38. The discharge sheet is somewhere in the kitchen. The pain in the flank feels a little different from yesterday, though whether that is the stent shifting or something worse is impossible to know from a bed. This is the moment most people who have had hydronephrosis treated actually worry about: not the procedure, but the quiet uncertainty afterward.
Hydronephrosis fever after stent placement sits at the center of that uncertainty because it can mean two very different things. Some warmth in the first 24 hours is a common reaction to instruments passing through the urinary tract. A true fever a few days later, especially with chills or pain, can mean infection behind a blockage that has not fully cleared.
This explainer walks through what a stent or drainage tube does, what the first days usually feel like, what low urine output really means, and exactly which signs should prompt a phone call or an emergency visit. Every decision about your care stays with the team that placed the device.
What hydronephrosis treatment actually does inside the kidney
Hydronephrosis is the swelling of a kidney because urine cannot drain away and backs up. The kidney itself is not the problem in most cases; the pipe leaving it is. The ureter, the narrow tube that carries urine from kidney to bladder, may be blocked by a stone, squeezed by a tumor or pregnancy, scarred, or kinked. Urine collects, pressure inside the kidney climbs, and the filtering tissue is slowly squeezed. The NHS notes that prompt relief of the pressure is what protects long-term kidney function.
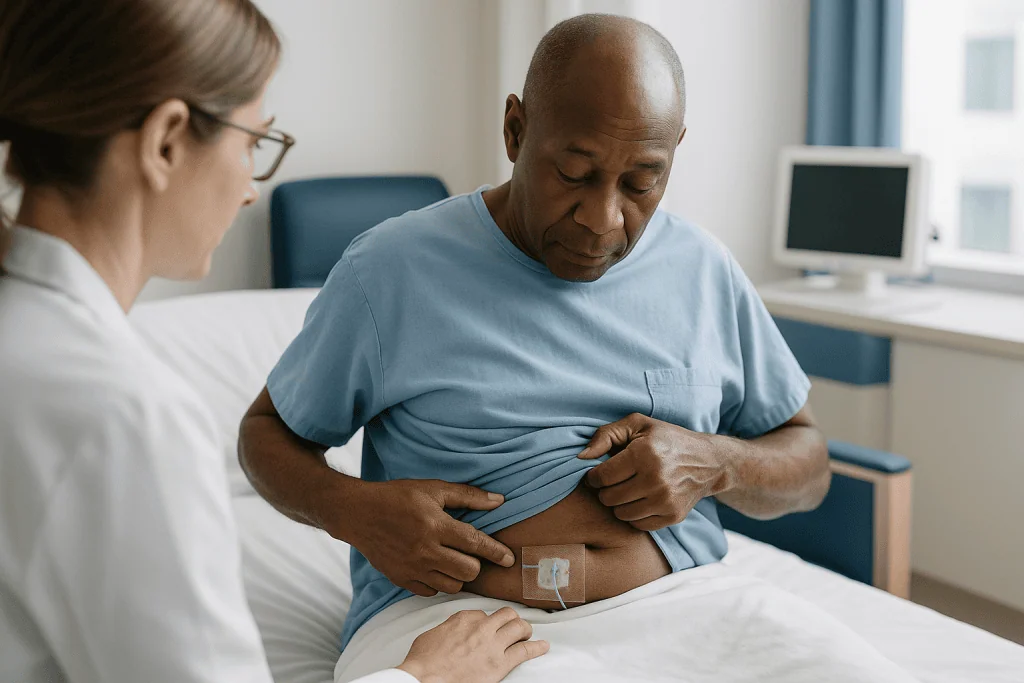
Treatment in the acute phase is therefore about drainage, not repair. Two tools do most of this work. A ureteral stent is a soft, hollow plastic tube, roughly the width of a piece of spaghetti, threaded from the bladder up the ureter into the kidney so urine can flow past or around the blockage. A percutaneous nephrostomy is a thin tube placed through the skin of the back directly into the kidney, draining urine into an external bag. Both bypass the obstruction; the difference is whether urine exits through the bladder or through a bag.
The Cleveland Clinic describes the stent as a temporary measure that keeps the ureter open while the underlying cause is addressed later, for example by breaking up or removing a stone. Think of it as a scaffold, not a fix.
Once pressure drops, the kidney usually resumes filtering, sometimes producing a brisk increase in urine over the following hours. That surge is one reason clinicians watch fluid balance closely early on. The reverse pattern, a kidney that stays swollen or a tube that produces little, is the signal that something still needs attention.
Hydronephrosis fever after stent: why it happens
Fever after a stent has several possible sources, and they carry very different weight. The least concerning is the body’s inflammatory response to instruments passing through the urethra, bladder, and ureter. A cystoscope, the thin camera used to place the stent, disturbs the lining of the urinary tract, and a brief low-grade temperature in the first day is a recognized response to that irritation rather than a sign of infection.

The more important cause is bacteria. Urine sitting behind a blockage is stagnant, and stagnant fluid grows bacteria the way a blocked drain does. When the stent opens the ureter, some of that colonized urine can enter the bloodstream through tiny breaks in the tract lining. The NHS describes kidney infection, called pyelonephritis, as an infection that has traveled up from the bladder or is trapped behind an obstruction; both conditions apply after hydronephrosis, which is why antibiotics are often given around the procedure.
Timing matters. A temperature that peaks within the first 24 hours and settles is usually the procedural pattern. A fever that appears or climbs on day two, three, or later, or one that comes with shaking chills, cloudy or foul-smelling urine, or a new ache over the kidney, points more toward infection. The stent itself can also become coated with bacterial film over weeks, which is one of the reasons stents are not left in indefinitely.
A final possibility, more common with nephrostomy tubes, is that the drainage device has stopped working. If the tube kinks or blocks, urine backs up again, pressure returns, and fever can follow within hours. The lesson is that fever after drainage is never something to interpret alone; it is information your team wants the same day.
Can hydronephrosis itself cause a fever?
Uncomplicated hydronephrosis, meaning swelling without infection, usually does not cause fever. The pressure produces flank pain, sometimes nausea, and sometimes reduced urine output, but the body does not generally mount a temperature in response to stretch alone. The Mayo Clinic lists fever among the symptoms that suggest an infection has joined the obstruction, rather than as a feature of swelling by itself.
That combination, an infected and obstructed kidney, is one of the genuine emergencies in urology. The kidney becomes a closed, pressurized chamber of infected urine with a direct route into the blood. Antibiotics alone struggle to work because they cannot reach a space with no drainage, and the pressure keeps pushing bacteria outward. Emergency drainage, by stent or nephrostomy, is the standard response, which is why many people first meet a stent during an urgent admission rather than a planned appointment.
After treatment, the same logic applies in reverse. If fever develops, the questions your team will ask are: Is the kidney draining? Is there still urine backed up? Has the stent moved or blocked? A quick ultrasound often answers these. Hydronephrosis that persists on the scan alongside fever is treated far more urgently than either finding alone.
This is also why a fever should never be waited out on the assumption that the procedure fixed the problem. Stents can migrate, stones can shift, and a kidney that was draining on the day of discharge may not be draining a week later. Fever is the kidney’s way of flagging that the plumbing needs rechecking.
What ureteral stent symptoms are normal in the first days?
A stent is a foreign object in a sensitive place, and the bladder rarely ignores it. The Cleveland Clinic lists the common experiences: a frequent or urgent need to urinate, a burning or stinging sensation when passing urine, blood tinting the urine pink, and a dull ache in the flank or lower abdomen, particularly during or just after urination. These are described as expected side effects, not complications.
The flank ache with urination has a specific mechanism worth understanding because it reassures many people. Normally a valve at the bottom of the ureter closes when the bladder contracts. A stent props that valve open, so a small amount of urine pushes back up toward the kidney each time you urinate. The brief pressure wave is felt as a twinge in the back. It fades as the bladder empties and is not a sign of damage.
Blood in the urine follows the same pattern of being alarming but usually benign. The stent rubs the lining of the bladder and ureter with movement, so pink urine after activity is common and often clears with rest and fluids. Bright red urine with clots, or bleeding that gets steadily heavier, is different and belongs on the call-the-team list.
Bladder spasms, a sudden cramping urge with little urine, also occur. Clinicians sometimes prescribe medicines that relax the bladder muscle to ease this; whether one is appropriate for you is a decision for the prescribing team, and any such medicine should be used only as directed.
Symptoms tend to be most noticeable in the first several days, then become more tolerable as the body adjusts, though some discomfort typically continues until the stent is removed.
Pain after a stent or nephrostomy: expected discomfort versus a warning sign
Pain is the symptom people find hardest to judge, because some pain is guaranteed and some pain is a red flag, and both live in the same part of the back. A useful frame is pattern rather than intensity. Expected stent pain is positional and intermittent: a twinge with urination, an ache after a long walk, discomfort that eases when you rest or when the bladder is empty. Warning pain is progressive: it builds over hours, does not settle with rest, and arrives alongside fever, vomiting, or a change in urine output.
With a nephrostomy, the entry site on the back is typically sore for a few days as the skin and muscle heal around the tube. Redness spreading outward from the site, warmth, pus, or increasing tenderness suggests a site infection and should be reported. Sudden severe pain at the kidney with a sharp drop in what the bag collects raises the possibility that the tube has blocked or slipped, which is a same-day call.
A specific type of pain deserves mention: colicky pain, the wave-like cramping of a ureter squeezing against something. After a stent this can mean a stone fragment moving, which may be expected if you had a stone broken up. It can also mean the stent has migrated. Your team can distinguish these with a plain X-ray or ultrasound.
Pain relief is usually planned before discharge. The NHS notes that hydronephrosis pain is managed alongside treatment of the cause; the choice of medicine, and any change to it, rests with the prescribing clinician. Reaching for extra doses of anything, including over-the-counter products, to mask pain that is escalating is the one thing to avoid, because it hides the very signal your team needs.
Low urine output after hydronephrosis treatment: what counts and why it matters
Urine output is the most objective signal you have at home, and the one most often misread. Oliguria is the medical term for producing abnormally little urine; anuria means producing almost none. Neither is defined by how the bladder feels but by volume over time. If you have a nephrostomy bag, you can measure this directly. If you have a stent, you are judging by how often you pass urine and how much, which is less precise but still informative.
Several things can lower output after drainage. The simplest is dehydration: nausea, poor appetite, and a reluctance to drink because urination stings can add up quickly. The more serious causes involve the device or the kidney. A blocked or kinked nephrostomy tube stops draining abruptly; the bag stays empty while the kidney refills. A stent that has become encrusted or displaced can obstruct again more gradually. If both kidneys were affected, or if you have only one functioning kidney, a return of blockage means the body has no backup and output can fall to nearly nothing within a day.
Both the NHS and the CDC list not passing urine, or passing very little, among the signs of possible sepsis in adults, which is why output is asked about early when fever appears.
Practical thresholds your team will likely give you include: a nephrostomy bag that has collected nothing for several hours despite drinking normally, urine that becomes very dark and scant, or a stretch of many hours without urinating at all. Any of these, especially with pain or fever, warrants a call rather than a wait. Bag output that suddenly turns from clear to frankly bloody or cloudy belongs in the same category.
Symptom-by-symptom: what to expect, what to report, what is an emergency
People consistently ask for a single reference they can glance at when unsure. The table below summarizes typical guidance drawn from the Cleveland Clinic, the NHS, and the CDC. Your own discharge instructions take precedence if they differ.
| Symptom | Commonly expected | Call your team the same day | Seek emergency care |
|---|---|---|---|
| Temperature | Brief low-grade rise in the first 24 hours | 38°C (100.4°F) or higher, or chills, at any time | Fever with confusion, fast breathing, racing heart, or feeling very unwell |
| Flank or back pain | Twinge with urination; ache after activity that settles with rest | Pain steadily increasing over hours; new colicky waves | Severe pain with fever or vomiting you cannot keep fluids down |
| Urine color | Pink tinge, often after activity | Cloudy, foul-smelling, or persistently red urine | Heavy bleeding with clots or difficulty passing urine |
| Urine output | Frequent small voids from bladder irritation | Noticeably less urine; nephrostomy bag empty for several hours | Little or no urine over many hours, especially with one kidney |
| Nephrostomy site | Mild soreness for a few days | Spreading redness, discharge, tube feels loose | Tube has fallen out, or bleeding from the site will not stop |
| General state | Tired for several days | Nausea, poor appetite, feeling worse rather than better | Mottled or cold skin, drowsiness, slurred speech |
Two patterns matter more than any single row. First, direction: symptoms that are improving day by day are reassuring; symptoms that are worsening are not, regardless of the starting point. Second, combination: a mild fever alone and mild pain alone are each a phone call; the two together, or either with falling urine output, moves you toward urgent assessment.
Sepsis after kidney stent placement: the signs that cannot wait
Sepsis is the body’s overwhelming and damaging response to infection, in which the immune reaction begins to injure the body’s own organs. After urinary drainage it is uncommon, but urinary sources are among the leading triggers of sepsis generally, and an obstructed infected kidney is exactly the scenario that can produce it. Recognizing the early picture matters because treatment works best when started early.
The CDC lists the signs to watch for: high heart rate or weak pulse; fever, shivering, or feeling very cold; confusion or disorientation; shortness of breath; extreme pain or discomfort; and clammy or sweaty skin. The NHS adds, for adults, slurred speech, not passing urine for a day, skin that is mottled, bluish, or very pale, and a rash that does not fade when a glass is pressed against it.
What makes sepsis dangerous after a stent is that its first hours can feel like a bad case of the expected symptoms. Chills feel like being cold. A fast heart rate feels like anxiety. Confusion in an older adult may be dismissed as tiredness. The distinguishing feature is usually the whole picture: someone who looks and feels distinctly unwell, is worsening quickly, and has more than one of the signs above.
Treatment involves intravenous antibiotics, fluids, and, critically, confirming that the kidney is draining. If a stent or tube has failed, restoring drainage is part of treating the infection, because antibiotics cannot clear a closed, pressurized space. MedlinePlus describes sepsis as a medical emergency; if you or someone with you recognizes this pattern, the correct response is emergency services, not a routine call and not waiting until morning.
Who usually gets a stent, who gets a nephrostomy, and who is asked to wait
Not everyone with hydronephrosis needs a drainage device. The NHS notes that mild hydronephrosis, especially the kind found on routine scans in pregnancy or in babies, is often monitored rather than treated, because it frequently settles on its own once the cause resolves. Pregnancy-related hydronephrosis, caused by the uterus pressing on the ureters, commonly improves after delivery. In these situations the treating team may recommend repeat ultrasound scans rather than a procedure, and the decision to wait is an active clinical choice, not neglect.
Drainage is generally pursued when the blockage is causing pain that cannot be controlled, when infection is present or suspected, when kidney function is falling, when both kidneys are affected, or when the person has only one working kidney. In those settings, the risks of leaving pressure in place outweigh the discomfort of a device.
Choosing between a stent and a nephrostomy depends on anatomy and circumstances. A stent is placed from inside via the bladder and leaves nothing external, which many people prefer for daily life. It requires that a wire can be passed through or past the blockage, which is not always possible with a tight tumor or large stone. A nephrostomy is placed from outside under imaging guidance and can be done when the ureter cannot be navigated, or when a person is too unwell for the anesthetic a stent may need. It is also chosen when the team wants to measure output directly.
Neither device treats the cause. A stone still needs removing; a stricture still needs assessing; a tumor still needs its own plan. The Cleveland Clinic frames the stent as a bridge to definitive treatment, and your team will explain what that next step is likely to be in your case.
How long does hydronephrosis take to resolve after a stent?
This is the most searched question about stents, and the honest answer has two parts, because pressure and appearance resolve on different clocks. Pressure relief is fast. Once the stent is in place and urine is flowing, pressure inside the kidney drops within hours, and pain from stretch often eases over the first day or two. Kidney function, measured by blood tests, commonly begins improving in the days that follow if the obstruction was recent.
The swelling seen on ultrasound is slower and less predictable. A kidney that has been stretched for weeks does not spring back to shape immediately, and a stent itself can keep the collecting system slightly dilated because urine flows more freely. It is common for a follow-up scan to show residual dilation even when the kidney is draining perfectly well. Clinicians interpret this alongside blood tests and symptoms rather than treating the scan alone.
The NHS emphasizes that outcomes depend heavily on how long the blockage was present and how severe it was before treatment: short, partial obstructions tend to resolve more completely than long-standing severe ones. Where the underlying cause is something that will lift on its own, such as pregnancy, the swelling usually settles once that cause is gone.
For most people the practical timeline is set by the stent plan. The Cleveland Clinic describes stents as typically remaining for a period ranging from days to several weeks, with longer durations in specific circumstances; the exact interval is set by your team and depends on why the stent was placed. Imaging is usually repeated after removal to confirm the kidney drains without help. That post-removal scan, not the day the stent went in, is the real marker of whether the hydronephrosis has resolved.
Kidney recovery from hydronephrosis: can the kidney fully recover?
Often, yes, and the deciding factor is time under pressure. Kidney tissue tolerates a rise in pressure for a while; the filtering units are compressed but not destroyed, and when pressure is relieved they resume work. The Mayo Clinic notes that with prompt treatment most people recover without lasting damage, while delayed or untreated obstruction can lead to permanent loss of function in the affected kidney.
The mechanism behind that permanence is scarring. Prolonged pressure reduces blood flow through the kidney and triggers a slow replacement of working tissue with fibrous tissue. Scar does not filter, and it does not convert back. This is why urologists move quickly when hydronephrosis is severe, bilateral, or accompanied by infection: the goal is to relieve pressure before scarring sets in.
Recovery is also not all-or-nothing. A kidney may regain most but not all of its function, and because most people have two kidneys, the other one compensates. Someone can lose a meaningful fraction of one kidney’s capacity and have entirely normal blood tests, because overall function reflects both organs. A nuclear medicine scan that measures each kidney separately is sometimes used when the team wants to know how much the affected side contributes.
Children deserve a separate word. Hydronephrosis found before birth or in infancy behaves differently: many cases are mild and resolve as the child grows, and specialists monitor with serial ultrasound rather than intervening early. The pathway there is watchful and unhurried, in contrast to the urgency of an infected obstruction in an adult.
If you want a clear picture of your own recovery, the questions to ask are which blood markers are being followed, whether a split-function scan is planned, and what the team expects the follow-up ultrasound to show. Those answers are individual; no article can supply them.
What the days and weeks after hydronephrosis treatment usually look like
The first 24 hours are the most eventful. Pressure relief often produces a brisk increase in urine as the kidney unloads, and staff will typically monitor fluid balance closely, sometimes replacing fluid if output is very high. A low-grade temperature, bladder irritation, and pink urine are common during this window. If you go home the same day, you will usually be told to drink steadily, note how often you urinate, and take your temperature if you feel unwell.
Days two through seven are when the body adjusts to the device. Urgency and frequency are typically at their most noticeable, then ease. Flank twinges with urination persist. Fatigue is normal; the combination of pain, disturbed sleep, and the aftermath of an acute illness takes time to lift. This is also the period when a fever means the most and should always be reported, because procedural fevers should have settled and infection is the leading alternative.
The following weeks are quieter and more administrative. If a stone was the cause, definitive treatment is usually scheduled within the stent’s planned lifespan. Blood tests may be repeated to track kidney function. With a nephrostomy, the site is cleaned and the dressing changed on a schedule; the bag is emptied and output recorded. Mild persistent discomfort is expected until removal.
Stent removal is usually a brief outpatient step. Some stents have a thread left attached that allows removal in clinic; others are removed with a cystoscope. The Cleveland Clinic notes that stents are not intended for indefinite use, and a forgotten stent can encrust and cause its own blockage, which is why the removal date is treated as part of the treatment rather than an afterthought.
After removal, a repeat ultrasound is commonly arranged to confirm the kidney drains on its own. Symptoms typically fade within days of the stent coming out.
What people often get wrong about fever and pain after a stent
“The procedure fixed the blockage, so a fever must be something else.” A stent bypasses a blockage; it does not remove one. Stents can migrate, kink, or block, and stones can move. Fever after drainage is treated as a possible sign that drainage has failed until a scan says otherwise.
“Some fever is normal, so I should wait it out.” A brief low-grade rise in the first day is a recognized response to instrumentation. A fever of 38°C or higher, or any fever with chills after that first day, is not something the NHS guidance on kidney infection suggests waiting on. Time matters when infection sits behind an obstruction.
“Blood in the urine means the stent has damaged something.” Pink urine after activity is among the most common stent experiences and usually reflects surface irritation. Heavy bleeding with clots is a different matter, but tinted urine alone is rarely a sign of harm.
“Drinking less will make the burning stop.” Concentrated urine irritates a stented bladder more, not less, and dehydration lowers output in a way that can mask a blockage. Steady fluid intake is usually encouraged unless your team has given you a specific restriction.
“If my scan still shows swelling, the treatment failed.” Residual dilation on ultrasound is common while a stent is in and for some time after long-standing obstruction. Clinicians judge success by blood tests, symptoms, and drainage on later imaging, not by one picture.
“Stents can stay in as long as I like.” They cannot. Stents encrust over months and can themselves obstruct; the removal or exchange date is part of the plan.
“Sepsis feels dramatic and obvious.” Early sepsis can look like a bad day: cold, tired, a little confused, a fast heart. The CDC signs are worth knowing precisely because they are easy to explain away.
Questions to ask your care team before you go home
The best time to sort out what counts as an emergency is before you need to know. Written answers to the following, ideally on the discharge sheet, remove most of the guesswork at two in the morning.
- What temperature should prompt a call, and what should prompt an emergency visit? Is the threshold different in the first 24 hours?
- Who do I call out of hours, and what number? Is there a direct line to the urology team or do I go through the emergency department?
- Which of my symptoms right now are expected from the stent or tube, and which would be new?
- How much urine, or how little, should concern me? If I have a nephrostomy bag, how many hours of an empty bag is too many?
- Do I have one functioning kidney or two? Does that change how quickly I should act if output drops?
- Was infection found or suspected? Am I on antibiotics, for how long, and what should I do if I cannot keep them down?
- Is there a thread on my stent, and what should I do if I see or feel it?
- When is the stent or tube due to be removed or exchanged, and what happens if that appointment is missed?
- What is the plan for the underlying cause, and roughly when?
- Which blood tests or scans will track my kidney’s recovery, and when are they scheduled?
- Can I bathe, swim, exercise, or travel with this device, and are there positions or activities that make displacement more likely?
- Are there medicines I already take that need adjusting while my kidney recovers?
The last question is worth asking directly, because some routine medicines are handled differently when kidney function is reduced. Any change, however, is for the prescribing clinician to make; do not stop or alter anything on your own based on a general article.
When to call your doctor: red flags after hydronephrosis treatment
Call your treating team the same day, or the out-of-hours number they gave you, if any of the following occur after a stent or nephrostomy: a temperature of 38°C (100.4°F) or higher; shaking chills; flank or back pain that is steadily increasing rather than easing; urine that becomes cloudy, foul-smelling, or persistently red; a nephrostomy bag that has collected nothing for several hours while you are drinking normally; a noticeable fall in how much urine you pass; spreading redness, warmth, or discharge at a nephrostomy site; a tube that feels loose or has shifted; or nausea and vomiting that stop you keeping fluids down. These are the situations in which the NHS advises prompt medical assessment for suspected kidney infection, and in which your team will want to check that the kidney is still draining.
Seek emergency care immediately, by calling emergency services, if fever comes with any of the sepsis signs listed by the CDC and the NHS: confusion, disorientation, or slurred speech; fast breathing or shortness of breath; a racing heart or weak pulse; skin that is mottled, bluish, very pale, cold, or clammy; not passing urine for a day; severe pain or a feeling of being extremely unwell; or a rash that does not fade under pressure. Emergency care is also warranted if a nephrostomy tube falls out, if bleeding is heavy with clots or will not stop, or if you cannot pass urine at all and have pain.
Two principles apply in every case. First, worsening beats waiting: a symptom that is getting worse over hours is a reason to act, regardless of the hour. Second, combinations escalate: fever plus pain, or fever plus low output, moves a situation from a phone call to an urgent assessment. Every judgment about your specific situation, including whether to re-image, adjust antibiotics, or exchange a device, belongs to the team responsible for your care.
Frequently asked questions
How long does hydronephrosis take to resolve after a stent?
Pressure inside the kidney typically drops within hours of a stent opening the ureter, and pain from stretch often eases over the first day or two. The swelling seen on ultrasound resolves more slowly and can persist while the stent is in place. Clinicians judge resolution by blood tests, symptoms, and a follow-up scan after stent removal rather than by the appearance of the kidney immediately after the procedure. Recovery is faster when the blockage was recent and partial.
Can hydronephrosis cause a fever on its own?
Uncomplicated hydronephrosis, meaning swelling without infection, usually does not cause fever; it causes flank pain, sometimes nausea, and sometimes reduced urine output. Fever in someone with hydronephrosis generally signals that infection has developed behind the blockage. That combination is a urological emergency because antibiotics cannot reach a closed, pressurized space, and drainage is needed alongside them. This is why fever after a stent is always taken seriously by the treating team.
What are the symptoms of sepsis after a kidney stent?
Sepsis signs listed by the CDC and NHS include fever, shivering or feeling very cold, a fast heart rate or weak pulse, fast breathing or breathlessness, confusion or slurred speech, extreme pain, clammy or mottled skin, and not passing urine for a day. Early sepsis can feel like a bad case of ordinary post-stent symptoms, which is why the combination of several signs, and a sense of rapidly worsening, matters. It requires emergency care.
Is a ureteral stent fever in the first 24 hours normal?
A brief low-grade rise in temperature in the first day after stent placement is a recognized response to instruments passing through the urinary tract and usually settles on its own. It becomes concerning if it reaches 38°C (100.4°F) or higher, comes with shaking chills, persists beyond the first day, or is joined by worsening pain, cloudy urine, or reduced urine output. Your discharge instructions will specify the thresholds your team wants you to use.
Can a kidney recover from hydronephrosis?
Often yes, particularly when the pressure is relieved promptly. Kidney tissue tolerates compression for a time and resumes filtering once urine can drain. Prolonged obstruction, however, reduces blood flow and leads to scarring that does not reverse, which can cause permanent loss of function in that kidney. Recovery is also a matter of degree; a kidney may regain most but not all capacity, and the other kidney often compensates so blood tests remain normal.
Why does my back hurt when I urinate with a stent?
A stent props open the valve at the bottom of the ureter, so a small amount of urine pushes back toward the kidney each time the bladder contracts. That brief pressure wave is felt as a twinge in the flank during or just after urination. It is one of the most common stent sensations and is not a sign of damage. Pain that builds steadily over hours without settling, or that comes with fever, is a different pattern and should be reported.
How little urine is too little after a nephrostomy or stent?
Your team will usually give you a specific threshold, but common triggers for a same-day call include a nephrostomy bag that has collected nothing for several hours despite normal drinking, urine that becomes very dark and scant, or many hours without urinating at all. Not passing urine for a day is listed among possible sepsis signs by the NHS. Falling output combined with pain or fever should be treated as urgent, especially if you have only one functioning kidney.
Is blood in the urine after a stent a problem?
Pink-tinged urine, especially after physical activity, is among the most common stent side effects and usually reflects the device rubbing the lining of the bladder and ureter. It often clears with rest and steady fluid intake. Bright red urine with clots, bleeding that gets progressively heavier, or difficulty passing urine because of clots is different and should prompt a call to your team the same day, or emergency care if heavy and unrelenting.
How long can a ureteral stent stay in?
Stents are temporary devices intended to remain for a period set by your treating team, commonly ranging from days to several weeks depending on the reason for placement, with longer intervals in specific circumstances. They are not designed for indefinite use because they gradually encrust with mineral deposits and bacterial film and can themselves cause blockage. The removal or exchange date is part of the treatment plan and should not be missed.
Should I keep taking my antibiotics if the fever has gone?
Antibiotic courses are prescribed for a set duration based on the type and site of infection, and stopping early because you feel better is generally not advised. Any question about continuing, stopping, or changing an antibiotic, including what to do if you vomit a dose or develop side effects, should go to the prescribing clinician. A fever that returns after antibiotics have been completed is a new signal and should be reported to your team promptly.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Prostatitis Is Diagnosed: Urine Tests, Prostate Examination and When Imaging Is Added
Prostatitis is diagnosed mainly through a detailed history, a urine test with culture, and a digital rectal examination of the prostate. Blood tests may…

What Happens After an Elevated PSA? From a Repeat Test to MRI and Urology Review
After an elevated PSA result, the usual next step is a repeat blood test once temporary causes such as infection, ejaculation or vigorous cycling…

Why Interstitial Cystitis Is Called a Pain Syndrome and How Care Is Personalized
Interstitial cystitis is called a pain syndrome because its defining feature is bladder-related pain or pressure with urinary urgency and frequency, usually lasting more…

Hypospadias Repair Recovery Day by Day: The Dressing, the Stent and Returning to Nursery
Hypospadias surgery recovery time is usually measured in days for the hardest part and weeks for the rest. Most children go home the same…

Catheter Hygiene, Fluids and Follow-Up: Daily Life After Bladder Drainage for Retention
Living with a urinary catheter after urinary retention means keeping the tube and bag clean with daily soap-and-water washing, drinking enough fluid that urine…

How Does Ureteroscopy Reach a Kidney Stone Without an Incision? A Step-by-Step Look
Ureteroscopy reaches a kidney stone by following the body's own urinary channel rather than cutting through skin. Under anesthesia, a urologist passes a thin,…