

Gynaecomastia Explained: Hormonal and Medical Causes and How Male Breast Reduction Is Planned

Key Takeaways
- Gynaecomastia reflects a shift in the estrogen-to-testosterone ratio, not necessarily high estrogen, which is why falling testosterone alone can trigger it.
- Cleveland Clinic reports that 50 to 60 percent of adolescent boys develop some gynaecomastia, and Mayo Clinic notes most cases resolve within six months to two years without treatment.
- Mayo Clinic states that at least one in four men aged 50 to 69 is affected, largely because fat tissue converts testosterone to estrogen through the enzyme aromatase.
- Pseudogynaecomastia is fat without gland; it responds to weight loss, whereas true glandular tissue does not shrink with exercise or diet.
- Medical therapy with estrogen-blocking drugs is most effective within about the first 12 months, before the gland becomes fibrotic, according to the NIH's StatPearls review.
- Male breast cancer makes up less than 1 percent of all breast cancers, and gynaecomastia itself is benign, though a hard, one-sided, fixed lump still needs examination.
Gynaecomastia is a benign enlargement of glandular breast tissue in men and boys, caused by a shift in the balance between estrogen and testosterone. Triggers include puberty, aging, certain medicines, alcohol, liver, kidney or thyroid disease, and rarely hormone-producing tumors. Many cases settle once the cause is addressed. When tissue persists, surgery combining liposuction and gland excision is planned individually by a specialist team.
He noticed it in a changing-room mirror, not at home. A fullness under one nipple, a little tender when the gym bag strap crossed his chest, and a question he could not quite bring himself to ask anyone: is this normal, and is it something?
That private moment is where most conversations about gynaecomastia causes and treatment begin. Men rarely volunteer the worry. Teenage boys hide it under hoodies through two summers. Older men assume it is weight, or age, or nothing. Yet the condition is common at every one of those life stages, and in most cases the biology behind it is understandable, measurable and, often, reversible.
This explainer walks through what is happening in the tissue, why hormones and medicines are the usual suspects, how clinicians separate true breast tissue from fat or anything more serious, and how a male breast reduction is planned when enlargement outlasts its cause. No myths, no promises; just what the evidence shows.
What actually happens in the breast when gynaecomastia develops?
Every man carries a small amount of breast gland behind each nipple. It is normally dormant, kept quiet by testosterone. Gynaecomastia, spelled gynecomastia in US English, is what happens when that gland is nudged awake.
The nudge comes from a shift in hormone balance. Estrogen, the hormone that drives breast development, and testosterone, the hormone that suppresses it, are both present in men; what matters is the ratio between them. When estrogen activity rises relative to testosterone, the ducts behind the nipple lengthen and branch, the tissue around them thickens, and a firm, rubbery disc forms under the areola, the darker skin circling the nipple. Mayo Clinic describes this as an imbalance rather than an excess of any single hormone, which is why a man with perfectly normal estrogen can still develop it if his testosterone falls.
Early on, the tissue is in a proliferative phase, meaning the cells are actively multiplying and the gland is often tender or sore. If the trigger is removed during this window, the tissue frequently shrinks. Left in place for a long stretch, the gland tends to become fibrotic: the active cells are gradually replaced by dense scar-like tissue that no longer responds to hormone changes. The NIH’s StatPearls review notes that this transition is why medical treatment works best in the first year and why longstanding enlargement usually needs surgery if the patient wants it changed.
Two further points matter. Gynaecomastia is often asymmetric, affecting one side more than the other, which is normal. And the gland itself is benign; it is not a precancerous growth, a point we return to below.
At what age is gynaecomastia most common?
There are three peaks across a male lifetime, and each has its own logic.
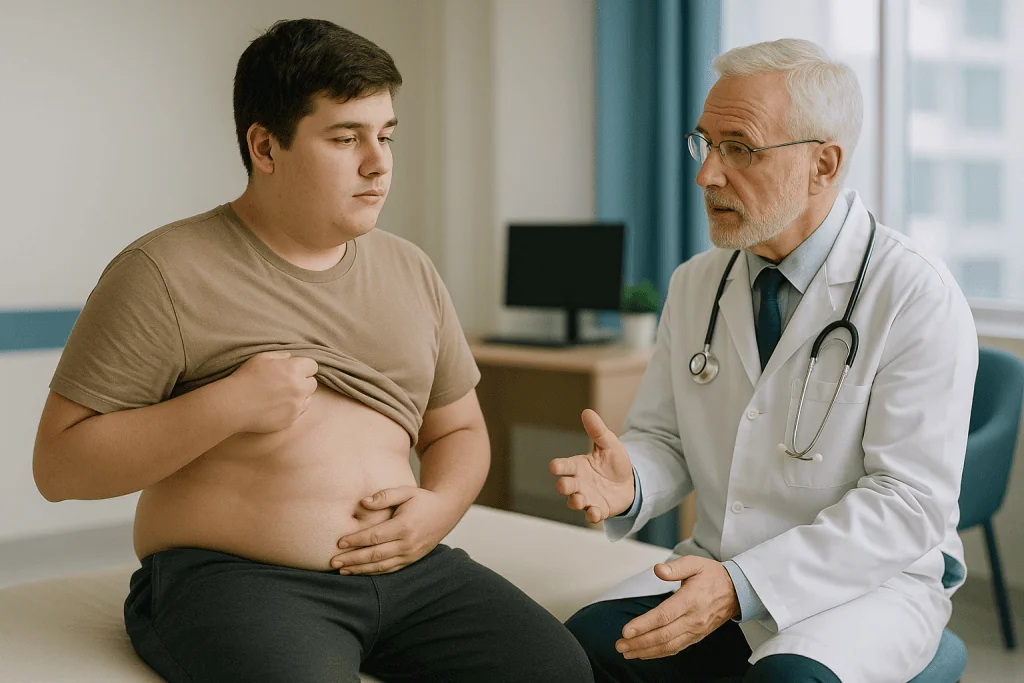
The first is at birth. Newborn boys are exposed to their mother’s estrogen across the placenta, and according to the NIH’s StatPearls review, 60 to 90 percent of newborns show a small amount of breast tissue. It fades within weeks as maternal hormones clear from the baby’s circulation, and it needs no treatment.
The second peak is puberty. Between roughly ages 12 and 16, testosterone and estrogen do not rise in step; estrogen often gets a head start. Cleveland Clinic reports that about 50 to 60 percent of adolescent boys develop some degree of gynaecomastia. This is the group most likely to feel distress and least likely to say so. Mayo Clinic notes that pubertal gynaecomastia usually goes away without treatment within six months to two years, which is why specialists generally advise watchful waiting before any intervention in teenagers.
The third peak arrives in later adulthood. Testosterone production declines gradually from middle age, body fat tends to rise, and fat tissue contains an enzyme called aromatase, which converts testosterone into estrogen. More fat means more conversion. Mayo Clinic states that between ages 50 and 69, at least one in four men is affected. Older men are also more likely to take the medicines discussed below, so several causes often stack together.
Outside these peaks, new gynaecomastia in a man in his twenties or thirties is less expected and deserves a more careful look for a specific cause, such as a medicine, a substance, or a hormone-producing condition. Age, in other words, is part of the diagnosis.
Gynaecomastia causes and treatment start with hormones: the medical conditions behind it
When a clinician hunts for a cause, the question is always the same: what has tipped the estrogen-to-testosterone balance? Several medical conditions can do it, through different routes.
Hypogonadism, meaning the testicles produce too little testosterone, is a common thread. It may be primary, where the testicles themselves are the problem, or secondary, where the pituitary gland in the brain fails to send the signal. Klinefelter syndrome, a genetic condition in which a boy is born with an extra X chromosome, is a classic primary cause and is often first suspected because of gynaecomastia in adolescence, according to MedlinePlus.
Liver disease, particularly cirrhosis, reduces the liver’s ability to break down estrogen and raises a protein that binds testosterone, lowering the free, active fraction. Kidney failure disturbs the hormone system in a similar direction. Hyperthyroidism, an overactive thyroid, increases that same binding protein and speeds the conversion of androgens to estrogen. Mayo Clinic lists all three among recognized causes.
Tumors are rare but important. Some testicular tumors secrete estrogen or a pregnancy-type hormone that stimulates estrogen production; some adrenal tumors do the same; and a pituitary tumor that produces prolactin, the milk hormone, can suppress testosterone. This is why examination of the testicles and targeted blood tests are part of a proper assessment rather than an optional extra.
Malnutrition and recovery from it also appear on the list. During starvation testosterone falls sharply; when eating resumes, hormone production rebounds unevenly and breast tissue can appear. The same pattern is seen after major illness.
Treating the underlying condition is the first treatment. In many men, once the hormonal environment is corrected, the gland quiets down on its own.
Which medications cause gynaecomastia, and what about alcohol and other substances?
Medicines are among the most common identifiable causes in adult men, and the list is long because many drugs touch hormone pathways by accident rather than design. The explanation below describes mechanisms only; nobody should stop or change a prescribed medicine on the basis of an article, because the condition being treated may matter far more than the side effect.

Anti-androgens, used in prostate cancer and some prostate enlargement treatments, block testosterone’s action directly, so the estrogen side of the balance wins by default. Anabolic steroids and some testosterone preparations can cause gynaecomastia too, which surprises many users; excess androgen is partly converted to estrogen by aromatase, and the body’s own testosterone production shuts down.
Mayo Clinic and the NHS list several further classes with a recognized association: a potassium-sparing diuretic widely used for heart failure, some calcium channel blockers used for blood pressure, certain acid-suppressing medicines for ulcers and reflux, some antidepressants and antipsychotics, some antibiotics and antifungals, chemotherapy agents, and some HIV medicines. For many of these the mechanism is only partly understood.
Substances outside the pharmacy matter as well. Alcohol in heavy, sustained amounts damages the liver and lowers testosterone. Marijuana, heroin and amphetamines have all been linked to gynaecomastia in Mayo Clinic’s summary, though the quality of evidence varies.
Plant products appear too. Mayo Clinic notes that tea tree oil and lavender oil in skin products have been associated with gynaecomastia in boys, possibly through weak estrogen-like activity, and some herbal supplements are poorly characterized.
The practical point: a thorough medication and substance history, including supplements and over-the-counter products, is one of the most valuable parts of the first consultation.
What is mistaken for gynaecomastia? Gynecomastia vs chest fat and other look-alikes
Not every enlarged male chest is gynaecomastia, and the distinction changes everything about treatment.
The most frequent look-alike is pseudogynaecomastia, sometimes called lipomastia: an accumulation of ordinary fat over the chest without any growth of the breast gland. It is common with higher body weight and feels soft and diffuse, like the fat elsewhere on the torso, rather than forming a distinct firm disc under the nipple. Cleveland Clinic points out that the two often coexist, so a man may have real glandular tissue sitting within a layer of fat. Fat responds to weight loss; gland does not.
Clinicians separate the two with a simple examination. With the patient lying flat, the thumb and forefinger are brought together from either side of the breast toward the nipple. A rubbery, mobile disc that meets the fingers beneath the areola suggests gland; fingers that slide together without resistance suggest fat alone.
Other conditions occasionally cause confusion. A lipoma is a benign fatty lump that can sit anywhere on the chest and is usually off-center from the nipple. A breast abscess or infection causes redness, heat and pain. Overdeveloped pectoral muscle in a trained athlete has a firm, broad feel and moves with the arm. And male breast cancer, discussed next, has features that distinguish it from benign gland.
Why this matters for planning: a chest that is mostly fat may be addressed with liposuction alone or with weight management, while true gland requires removal of the gland itself. Treating fat with a technique designed for gland, or the reverse, leaves patients disappointed. Getting the label right is the foundation of everything that follows.
Can gynaecomastia turn to cancer?
This is the question underneath most of the others, so it deserves a direct answer. Gynaecomastia itself is benign and is not considered a precancerous condition. The enlarged gland does not transform into cancer. Mayo Clinic reports that male breast cancer accounts for less than 1 percent of all breast cancers, and the overwhelming majority of breast lumps in men are gynaecomastia or fat.
Two caveats keep clinicians careful. First, the same hormonal environment that produces gynaecomastia can, in a small number of men, also raise breast cancer risk. Klinefelter syndrome is the clearest example: men with the condition have both a high rate of gynaecomastia and an elevated lifetime risk of breast cancer. The link runs through the shared hormonal cause, not through the gland turning malignant.
Second, a cancer can be mistaken for gynaecomastia if nobody examines it properly. The features that raise concern are quite different from benign gland. Gynaecomastia is typically centered directly beneath the nipple, rubbery, somewhat mobile and often on both sides, even if unevenly. A cancer is more often a hard, irregular, painless lump that sits to one side of the nipple, fixed to the skin or the chest wall. Skin dimpling, nipple retraction or inversion, a bloody or clear discharge from one nipple, ulceration, or swollen lymph nodes in the armpit all point away from benign enlargement, according to MedlinePlus and Mayo Clinic.
When any of those features are present, or when a lump is new in an older man, imaging and often a needle biopsy are arranged to settle the question. The reassurance is real for most men. The examination is what earns it.
How is gynaecomastia diagnosed and what tests are usually ordered?
Assessment follows a logical sequence that most patients find reassuringly thorough.
The conversation comes first. When did the enlargement start, has it grown, is it tender, is it one side or both? Which medicines, supplements, protein powders, oils and recreational substances are in the picture? Has there been weight change, a recent illness, a change in sex drive or erections, or a loss of body hair? Those last questions are not intrusive; they screen for low testosterone, one of the most common underlying causes.
Examination follows: the chest, as described above, to distinguish gland from fat and to check for worrying features; the armpits for lymph nodes; the abdomen for liver enlargement; the thyroid; and the testicles, for size and for any mass. Signs of chronic liver disease are also noted.
Blood tests are tailored rather than standardized. Mayo Clinic lists testosterone, estrogen, luteinizing hormone, prolactin, thyroid function, liver and kidney function, and tumor markers when a testicular tumor is possible. In a teenager with a typical pubertal pattern and a normal examination, many specialists order few or no tests and simply review in a few months. In a man whose enlargement is new, rapid or one-sided, testing is more extensive.
Imaging is used selectively. Mammography and ultrasound of the breast are reserved for cases where the examination is unusual or cancer is a concern. A testicular ultrasound is arranged if a mass is felt or hormone tests suggest a tumor. A biopsy, in which a fine needle samples the tissue, is uncommon but definitive when needed.
The aim throughout is to find a reversible cause before anyone talks about surgery.
Does gynaecomastia go away on its own, and what can medicines do?
Often, yes, and the deciding factor is how long the tissue has been there.
In puberty, Mayo Clinic reports that most cases settle without treatment within six months to two years as hormone levels find their adult balance. In adults, when a medicine or substance is responsible and can safely be changed by the prescribing clinician, the gland frequently shrinks over the following months. When an underlying condition such as hyperthyroidism or hypogonadism is treated, the same can happen. Weight loss removes the fat component and reduces aromatase activity, though it will not remove established gland.
Medicines are sometimes considered for men with painful or distressing gynaecomastia that has not resolved. Two classes have been studied. Selective estrogen receptor modulators, such as tamoxifen, block estrogen’s action at the breast tissue. Aromatase inhibitors reduce the conversion of testosterone to estrogen. Neither class is formally licensed for gynaecomastia in most countries; the NHS describes their use as off-label, and the evidence base consists mainly of small studies rather than large trials.
Timing is the limiting factor. The NIH’s StatPearls review notes that medical therapy is most effective within roughly the first 12 months, during the proliferative phase, before fibrosis sets in. Tissue that has been present for years and feels firm has generally stopped responding to hormones, and medicines are unlikely to change it meaningfully.
Whether to try a medicine, which one, for how long, and how to weigh side effects is a decision for the treating clinician with knowledge of the individual’s full history. What can be said generally is that watchful waiting, cause correction and medicines all sit before surgery in the usual sequence.
Who is male breast reduction usually for, and who is usually asked to wait?
Surgery is the final step in the pathway, not the first, and surgeons apply fairly consistent criteria when deciding whether a man is a good candidate.
The men most often offered male breast reduction share several features. The gynaecomastia has been present and stable for a long period, typically more than a year, so the tissue is fibrotic and unlikely to regress. A reversible cause has been looked for and either excluded or already corrected. Any underlying medical condition is under control. Body weight is stable, because significant future weight change alters the chest and can undo a careful result. And the enlargement is causing genuine physical or psychological distress, whether pain, difficulty with clothing or exercise, or a persistent effect on confidence and daily life.
Several groups are usually asked to wait. Teenagers are the largest: because pubertal gynaecomastia so often resolves, Mayo Clinic and the NHS both describe observation as the standard approach, with surgery generally deferred until growth is complete and the tissue has persisted for a prolonged period. Men whose enlargement is recent and still tender may be in the proliferative phase, where cause correction or medicines could still work. Men who are actively losing weight are often advised to reach a stable weight first so the surgeon can plan against the chest they will actually have. Men taking a medicine known to cause gynaecomastia may be asked to discuss alternatives with the prescriber before anything is removed, since the tissue could return.
Men with uncontrolled diabetes, active smoking, bleeding disorders or anticoagulant treatment, or significant heart or lung disease will have those issues addressed first, as with any elective operation. Candidacy is a shared judgment between patient and team, never a formula.
How male breast reduction surgery is planned: liposuction, gland excision or both
Planning begins with three questions: how much of the enlargement is fat, how much is gland, and is there excess skin? The answers determine the technique.
Surgeons commonly grade severity. Mild cases show a small gland with no extra skin; moderate cases have more volume with little or mild skin excess; severe cases involve a large volume with marked skin redundancy and a nipple that has dropped below its natural position. Each grade points toward a different combination of methods.
| Approach | What it removes | Typical use | Trade-offs described in guidance |
|---|---|---|---|
| Liposuction alone | Fat | Mostly fatty enlargement, good skin elasticity | Does not remove firm gland; small access incisions |
| Gland excision | Breast gland | Firm disc under the nipple | Incision usually at the areola edge; risk of a hollow if too much is taken |
| Combined liposuction and excision | Fat and gland | Most adult cases with both components | Most common approach; two techniques, one operation |
| Excision with skin reduction | Fat, gland and skin | Large volume or after major weight loss | Longer scars; nipple may be repositioned |
Liposuction uses a thin hollow tube inserted through small incisions to suction out fat and, in newer variants, to loosen fibrous tissue. Gland excision removes the disc directly through an incision usually hidden along the lower border of the areola, leaving a thin rim of tissue behind the nipple so the chest does not look scooped. Skin reduction adds incisions around the areola or across the chest when elasticity alone cannot retract the skin.
Mayo Clinic describes liposuction and mastectomy, the surgical term for removing breast gland tissue, as the two core options. Which combination is used, and whether the operation is done under general or local anesthesia, is decided by the surgeon after examination, imaging where needed, and a frank discussion of what the patient wants to change.
Gynecomastia surgery recovery time: what the days and weeks after usually look like
Recovery follows a recognizable arc, even though the exact intervals depend on the technique used and the surgeon’s protocol.
The first days bring swelling, bruising and soreness across the chest, most noticeable with arm movement. Small drains are sometimes placed to carry away fluid and are removed at an early follow-up visit. A compression garment, a firm elastic vest, is typically fitted at the end of the operation; it limits swelling, supports the skin as it settles against the new contour and reduces the chance of fluid collecting under the skin. Surgeons specify how long it should be worn, and that period varies, so the instruction given on the day is the one to follow.
Through the first weeks, swelling gradually recedes and the chest begins to look flatter, though the final shape takes longer. Numbness or altered sensation around the nipple is common early on and usually improves over time, although Cleveland Clinic notes that some change in sensation can persist. Light walking is encouraged from the first day to keep blood moving and lower clot risk, while lifting, chest exercise and contact sport are held back until the surgical team clears them.
Scars pass through a predictable sequence: pink and slightly raised at first, then softening and fading over many months. Scar care advice, including sun protection, comes from the team.
Patients often ask when they will see the result. The honest answer is that early appearance is distorted by swelling, and judgment should wait until the team says the tissues have settled. Follow-up appointments are not a formality; they are where seromas, asymmetry or wound problems are caught early, when they are easiest to manage.
Risks, limits and alternatives in plain language
Male breast reduction is a well-established operation, but it is still surgery, and an honest explainer names what can go wrong.
General risks include bleeding, infection, reaction to anesthesia and blood clots, as with any procedure. Risks specific to this operation, listed by Cleveland Clinic and Mayo Clinic, include a hematoma, which is a collection of blood under the skin that may need draining; a seroma, a collection of clear fluid, which is more common after liposuction; changes in nipple or chest sensation; asymmetry between the two sides; contour irregularities, including a hollow under the nipple if too much gland is removed or residual fullness if too little is taken; visible scarring; and, rarely, loss of blood supply to the nipple. Revision surgery is occasionally needed to correct asymmetry or irregularity.
The operation has limits worth stating. It removes tissue that exists today; it does not prevent new tissue forming if the underlying hormonal driver, a medicine or significant weight gain returns. It will not change chest muscle shape, and it cannot guarantee a particular appearance. Surgeons who show their own patients’ photographs are illustrating a range of outcomes, not a promise.
Alternatives deserve equal airtime. Watchful waiting suits adolescents and recent-onset cases. Correcting a cause, whether a medicine change by the prescriber, treatment of thyroid or liver disease or hormone replacement for confirmed hypogonadism, can be sufficient. Weight management addresses the fat component. Medicines may help in the early phase, with the caveats described above. Doing nothing is also legitimate; gynaecomastia is benign, and a man who is not bothered by it needs no treatment at all.
Weighing these against each other is the conversation the treating team is there to have.
What people often get wrong about gynaecomastia causes and treatment
A handful of myths circulate so widely that correcting them is worth a section of its own.
The first is that gynaecomastia is simply a weight problem and the gym will fix it. Exercise and weight loss reduce chest fat and can help pseudogynaecomastia considerably, but no amount of bench pressing shrinks glandular tissue. Building the pectoral muscle beneath a gland can even make the fullness more prominent. Fat and gland are different tissues with different fixes.
The second is that it signals low masculinity or a hormonal “problem” in some permanent sense. Most pubertal cases occur in entirely healthy boys; most adult cases reflect an ordinary medicine, an age-related shift or a treatable condition. It is a sign to investigate, not a verdict.
The third is that taking testosterone will reverse it. In men with confirmed hypogonadism, replacement prescribed by a specialist may help. In men with normal testosterone, adding more is converted partly to estrogen and can worsen the problem, which is precisely why anabolic steroid users develop it.
The fourth is that supplements or creams marketed for enlarged male breasts have evidence behind them. They do not. No over-the-counter product has been shown in mainstream trials to shrink glandular tissue, and some herbal products have been associated with causing the condition rather than relieving it.
The fifth is that any breast lump in a man is probably cancer. The reverse is true: the great majority are benign gynaecomastia or fat, though every new lump still earns an examination.
The last is that surgery is always the answer. It is an answer, for the right person at the right time, after the right workup. The sequence matters more than the scalpel.
Questions to ask your care team
A consultation moves fast, and the questions that matter most are easy to forget in the room. These are the ones experienced patients wish they had asked.
About the diagnosis: Is this glandular tissue, fat or both, and how did you tell? Do my blood tests point to a cause? Is there a medicine, supplement or substance in my history that could be responsible, and who should I speak to about it? Is any further imaging or a biopsy needed, and why or why not?
About waiting: Given my age and how long this has been present, how likely is it to improve on its own? What would make you want to see me again sooner? If a medicine were considered, what is the realistic chance of benefit at this stage and what side effects should I weigh?
About surgery, if it is on the table: Which technique do you propose for my chest, and what led you to it? Will there be excess skin, and how would you manage it? Where would the scars be, and how do they usually mature? How do you avoid a hollow under the nipple? How many of these operations do you and your team perform, and how do you handle a hematoma or seroma if one develops?
About recovery: What restrictions will I have, and who decides when they lift? How long is the compression garment usually worn in your practice? When will the result be judged final? What is the plan if the two sides heal differently?
About the bigger picture: Is anything in my history likely to bring the tissue back? Should my weight be stable before surgery? Is there any reason not to operate at all?
Write the answers down. Decisions this personal deserve a record.
When to call your doctor
Most gynaecomastia is benign and unhurried, but some features should prompt a prompt appointment rather than watchful waiting at home. A hard, irregular or fixed lump, particularly if it sits to one side of the nipple rather than directly beneath it, needs examination. So does any discharge from the nipple, especially if it is bloody or comes from one side only; skin dimpling, puckering or ulceration over the breast; a nipple that has newly turned inward; swelling or a lump in the armpit; or rapid enlargement over weeks rather than months. MedlinePlus and Mayo Clinic list these among the signs that distinguish possible cancer or infection from ordinary enlargement.
Symptoms beyond the chest matter too. Breast enlargement alongside a testicular lump or swelling, a marked drop in sex drive, erectile difficulty, loss of body hair, unexplained weight loss, headaches with vision changes, or yellowing of the skin or eyes should all be mentioned, because each points toward an underlying cause that deserves its own assessment.
After surgery, the team will give specific instructions, but certain signs call for a same-day call to them: sudden swelling or tightness on one side of the chest, which can indicate bleeding under the skin; spreading redness, warmth, pus or a fever, suggesting infection; a nipple that becomes dark, dusky or very pale; wound edges that separate; or calf pain, swelling, chest pain or breathlessness, which can signal a blood clot and warrant emergency care.
Finally, distress is a reason to seek help in its own right. Gynaecomastia can weigh heavily on confidence and mood, especially in adolescence. Raising that with a clinician is as legitimate as raising the lump itself, and it belongs in the conversation about what, if anything, to do next. Every decision described in this article rests with the treating team who can examine you.
Frequently asked questions
What makes gynecomastia go away?
Removing or correcting the cause is what most often makes gynaecomastia go away. In puberty, time does the work as hormones settle. In adults, a medicine change made by the prescriber, treatment of thyroid, liver or testosterone problems, or weight loss can shrink early, soft tissue. Longstanding firm tissue has usually become fibrotic and rarely regresses without surgery.
What is mistaken for gynecomastia?
Chest fat, called pseudogynaecomastia, is the most common look-alike and feels soft and diffuse rather than forming a firm disc under the nipple. Lipomas, abscesses, well-developed pectoral muscle and, rarely, male breast cancer can also be confused with it. A clinician distinguishes them by examination, sometimes with ultrasound or mammography when the findings are unusual.
Can gynecomastia turn to cancer?
No, gynaecomastia is benign tissue and does not transform into cancer. Male breast cancer is rare, under 1 percent of all breast cancers according to Mayo Clinic. Conditions such as Klinefelter syndrome raise both gynaecomastia and breast cancer risk through a shared hormonal cause, which is why a hard, irregular, one-sided lump or nipple discharge is always examined rather than assumed benign.
At what age is gynecomastia most common?
There are three peaks: newborns, where 60 to 90 percent show temporary breast tissue from maternal estrogen; puberty, affecting roughly half of boys; and later adulthood, where Mayo Clinic reports at least one in four men aged 50 to 69 is affected. The pubertal and newborn forms usually resolve on their own; the adult form often relates to medicines, weight or declining testosterone.
What is the difference between gynecomastia vs chest fat?
Gynaecomastia is glandular breast tissue, felt as a firm, rubbery, mobile disc centered beneath the nipple. Chest fat is soft, spread evenly across the chest and feels like fat elsewhere on the body. Fat responds to diet and exercise; gland does not. Many men have both, which is why combined liposuction and gland excision is the most common surgical plan.
Does gynecomastia go away with exercise?
Exercise reduces the fat component and can noticeably improve a chest where fat is the main issue, but it does not shrink glandular tissue. Building the pectoral muscle beneath a gland can even make the fullness more visible. If a firm disc remains after weight is stable, a clinician can confirm whether it is gland and discuss other options.
Which medications cause gynecomastia?
Recognized classes include anti-androgens used for prostate conditions, anabolic steroids, a potassium-sparing diuretic used in heart failure, some calcium channel blockers, certain acid-suppressing ulcer medicines, some antidepressants and antipsychotics, some antibiotics and antifungals, chemotherapy and some HIV medicines. Never stop a prescribed medicine on your own; raise the concern with the prescribing clinician, who can weigh alternatives.
How long is gynecomastia surgery recovery time?
Recovery varies with the technique and the surgeon’s protocol, so the team’s instructions are the ones to follow. In general, swelling and bruising dominate the first days, a compression garment is worn for a period the surgeon specifies, light walking starts early, and heavier chest exercise waits for clearance. The final contour is judged only once swelling has fully settled, which takes longer than most people expect.
Can gynecomastia come back after surgery?
Surgery removes the tissue present at the time, but it cannot prevent new growth if the underlying driver persists or returns, such as an ongoing medicine, anabolic steroid use, significant weight gain or an untreated hormonal condition. Surgeons leave a thin rim of tissue behind the nipple to avoid a hollow, and that small remnant can enlarge if hormones push it to. Addressing the cause first lowers that risk.
Is gynecomastia painful?
It can be, particularly in the early proliferative phase when the gland is actively growing; tenderness, soreness and sensitivity to clothing or pressure are common then. Longstanding, fibrotic tissue is usually painless. New pain with redness and warmth may indicate infection, and a painless hard lump off to one side of the nipple needs examination for other causes, so either pattern is worth reporting.
References
- Cleveland Clinic: Enlarged male breast tissue (gynecomastia)
- NIH StatPearls: Gynecomastia
- MedlinePlus: Breast enlargement in males
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Breast Augmentation Incision Options: Under the Fold, Around the Areola or in the Armpit
Breast augmentation incision options are the inframammary incision in the fold beneath the breast, the periareolar incision along the edge of the areola, and…

Can You Breastfeed After Nipple Aesthetics Procedures? Sensation, Ducts and Planning Ahead
Many people can breastfeed after nipple surgery, but how much milk they make depends on which structures the operation touched: the milk ducts running…

Can Breast Reduction Relieve Neck and Back Strain? How the Decision Is Made With Your Surgeon
Breast reduction surgery can ease neck, shoulder and upper back strain for many people whose symptoms are linked to heavy breast tissue, and major…
When Breast Reconstruction Needs a Revision: Asymmetry, Capsule Changes and Fat Grafting
Breast reconstruction revision surgery is a follow-up operation that adjusts an earlier reconstruction when problems develop: a difference in size or position between the…

How Is Discomfort Managed After Breast Reduction? Tightness, Drains and Sleeping Positions
Breast reduction pain after surgery is usually described as soreness and tightness rather than sharp pain, and it is typically most noticeable in the…
What Breasts Look Like After Prosthesis Removal: Volume, Skin and When a Lift Is Discussed
After implant removal without replacement, breasts usually look smaller and softer at first, with loose or deflated-looking skin, a lower nipple position and some…