

How Catheter Techniques Reopen a Chronically Blocked Coronary Artery in CTO Treatment

Key Takeaways
- A chronic total occlusion is a coronary artery that is completely blocked with no forward flow and judged to have been closed for at least three months, which distinguishes it from the fresh clot of a heart attack.
- Expert consensus in Circulation reports that a CTO is found in roughly one in five people undergoing coronary angiography, so it is a common finding rather than a rare one.
- The J-CTO score grades difficulty from 0 to 5 using cap shape, calcium, bends over 45 degrees, length of 20 millimeters or more, and any prior failed attempt.
- Retrograde CTO PCI approaches the blockage from behind by threading a wire through a collateral channel, most often a septal branch, because the far cap is frequently softer than the near one.
- Randomized trials summarized in the 2021 ACC/AHA/SCAI guideline show symptom and quality-of-life improvement from CTO PCI but no reduction in death or heart attack, which is why the guideline grades it Class 2b for symptom relief.
- The NHS advises not driving for a week after planned angioplasty and the Mayo Clinic advises avoiding heavy lifting for about a week, with longer restrictions possible after complex or prolonged cases.
A CTO PCI procedure reopens a coronary artery that has been completely blocked for at least three months. Working through a small puncture in the wrist or groin, an interventional cardiologist steers specialized guidewires through or around the hardened plug, sometimes approaching from the far side through natural collateral channels, then widens the path with balloons and places drug-eluting stents to hold it open.
The report says one word that stops most people cold: occluded. Not narrowed, not partially blocked. Occluded. Then the cardiologist adds something that sounds almost contradictory. This artery, she says, has probably been shut for a year or more, and your heart has been quietly rerouting blood around it the whole time.
That is the strange starting point for anyone trying to understand how a CTO PCI procedure works. A chronic total occlusion is not an emergency in the way a heart attack is. It is a slow, hardened closure that the body has partly compensated for, and the question is never simply whether it can be opened, but whether opening it will make a real difference to how you feel and function.
What follows is a plain account of what actually happens on the table, why these cases take longer than ordinary stenting, what the trials do and do not show, and where the honest uncertainties lie.
What is a chronic total occlusion of a coronary artery?
A chronic total occlusion, or CTO, is a coronary artery that is 100 percent blocked, with no forward flow of blood through the blocked segment, and that is judged to have been closed for at least three months. That definition comes from a global expert consensus document published in the American Heart Association journal Circulation, and the three-month threshold matters because it separates a hardened, mature blockage from the soft clot of a recent heart attack.
These are not rare. The same consensus document reports that a CTO is found in roughly one in five people who undergo coronary angiography for suspected coronary artery disease. Many of them never knew it was there.
How can a fully blocked artery go unnoticed? Because closure happens slowly, and the heart responds. Over months, small bridging vessels called collaterals enlarge and carry blood from healthy arteries into the territory beyond the blockage. Collaterals are the body’s own bypass. At rest they may deliver enough. Under exertion, when the heart muscle asks for two or three times more oxygen, they often fall short, and that shortfall shows up as chest tightness on the stairs, breathlessness, or a fatigue that has no obvious explanation.
Inside the artery itself, the blockage has a structure. There is a proximal cap, the entry point facing the heart’s main pump, and a distal cap at the far end where normal vessel resumes. Between them sits a plug of fibrous tissue, cholesterol debris and, in older occlusions, calcium that can be as hard as bone. Tiny microchannels sometimes thread through it. Whether a wire can find and follow those channels is the first question every operator asks.
CTO PCI procedure: how it works, step by step
PCI stands for percutaneous coronary intervention, meaning treatment of a coronary artery from inside the vessel through a skin puncture rather than open surgery. In a CTO case, the sequence is the same as for any angioplasty, but every step is slower and more deliberate.
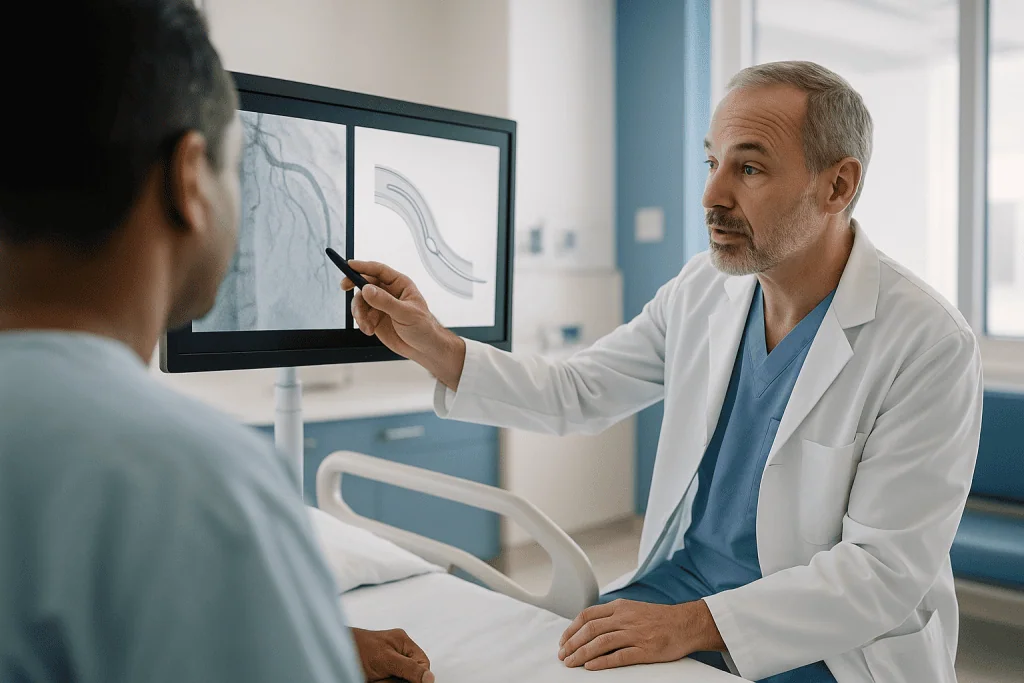
You are awake but sedated, with local anesthetic numbing the wrist or groin. A thin sheath is placed in an artery there, and a guide catheter, a hollow tube about the width of a cooked spaghetti strand, is advanced to the opening of the blocked coronary artery. Many CTO operators place a second sheath in a second artery so they can inject dye from both sides at once. This dual injection lights up the collateral vessels and shows exactly where the artery reappears beyond the block, which is information you cannot get from one side alone.
Then comes the crossing. A guidewire finer than a human hair is steered into the proximal cap, supported by a microcatheter, a slender tube that stiffens the wire and lets the operator exchange one wire for another without losing position. Wires range from soft and slippery, designed to find microchannels, to stiff, tapered tips built to puncture calcium.
Once the wire reaches the true channel beyond the blockage, the rest is more familiar. Balloons are inflated to open the path, imaging from inside the vessel checks the size of the artery, and one or more drug-eluting stents are placed. According to the Mayo Clinic, angioplasty in general can take anywhere from 30 minutes to a few hours; CTO cases sit at the longer end of that range, and several hours is not unusual.
Why is a totally blocked artery harder to open than a narrowed one?
In an ordinary narrowing, the operator can see a thin trickle of dye passing through and simply follows it. In a CTO, the dye stops at the proximal cap. The blocked segment, which may be a few millimeters or several centimeters long, is effectively invisible on the X-ray screen. The operator is navigating a tunnel with the lights off, guided by what the far side looks like through the collaterals and by the feel of the wire in the fingertips.
Four features make some occlusions far tougher than others, and the consensus document describes a widely used difficulty score, the J-CTO score, that adds one point for each: a blunt or ambiguous entry cap, calcium within the segment, a bend of more than 45 degrees, and a blocked length of 20 millimeters or more. A fifth point is added if a previous attempt failed. Zero is straightforward; four or five signals a long and technically demanding case.
The danger in a dark tunnel is leaving it. A stiff wire can slip out of the vessel wall entirely, which is called a perforation, or it can end up in a side branch rather than the main channel. Operators watch for both constantly, using multiple camera angles and, when the wire position is uncertain, intravascular ultrasound to confirm where the tip actually sits.
All of this takes X-ray time and contrast dye. The consensus document is explicit that radiation exposure and contrast volume are higher in CTO PCI than in standard PCI, which is why kidney function is checked beforehand and why teams set limits on both in advance rather than pushing on indefinitely.
What is retrograde CTO PCI, and how do dissection and re-entry work?
The simplest approach is called antegrade wire escalation: start at the proximal cap, try a soft wire, and step up to progressively stiffer ones until something crosses. It works often, especially for shorter, softer occlusions, and it is where most cases begin.
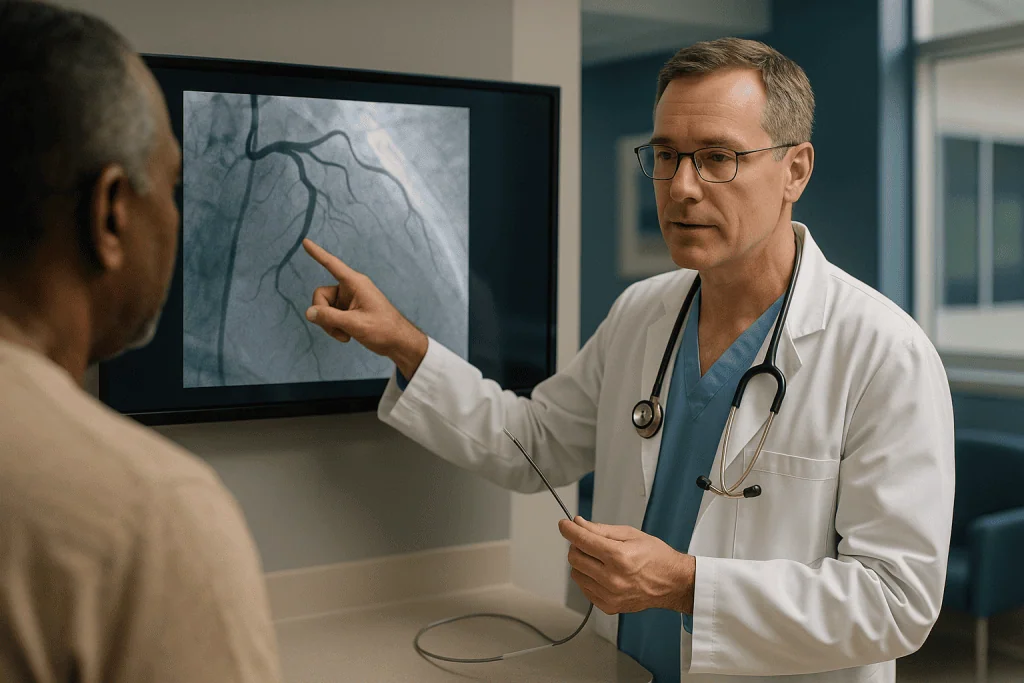
When the wire refuses to find the true channel but keeps sliding into the vessel wall, some operators use that to their advantage. Antegrade dissection and re-entry means deliberately tracking through the subintimal space, the layer between the artery’s inner lining and its muscular wall, along the length of the blockage, then using a dedicated re-entry device or a shaped wire to puncture back into the open vessel beyond the distal cap. It sounds alarming. In practice the artery wall is a controlled environment, and the segment is later covered by stents.
Retrograde CTO PCI reverses the direction of attack. A wire is steered from a healthy coronary artery through a collateral channel, most often a small septal branch running through the muscular wall between the heart’s two pumping chambers, and arrives at the distal cap from behind. The distal cap is frequently softer than the proximal one. Once the retrograde wire is through, it can be captured by the antegrade system so that a single wire spans the entire route, and the case is finished from the front.
The consensus document describes a hybrid approach in which the operator studies the anatomy, chooses the most promising first strategy, and switches promptly rather than persisting when one route stalls. That willingness to change course is, more than any single device, what separates modern CTO work from earlier eras.
Who is CTO PCI usually for, and who is usually asked to wait?
The clearest candidate is someone whose symptoms persist despite well-managed medical therapy. The 2021 coronary revascularization guideline from the American College of Cardiology, American Heart Association and Society for Cardiovascular Angiography and Interventions states that CTO PCI may be reasonable to improve symptoms in patients who still have angina after guideline-directed medicines. It grades this as a Class 2b recommendation, the guideline language for a benefit that is plausible but not firmly established, and it does not recommend the procedure to extend life.
Beyond symptoms, teams look at two other things. First, is the heart muscle beyond the blockage still alive? A territory that has scarred completely will not gain from restored blood flow, and a viability test, often cardiac MRI or a nuclear scan, helps answer this. Second, how large is the area at stake? A small branch feeding a sliver of muscle rarely justifies a several-hour procedure.
Who is asked to wait, or steered elsewhere? People with no symptoms and no evidence of oxygen shortfall on stress testing, since there is little to gain and real risk to accept. People whose blockage is one of several in different arteries, for whom bypass surgery may treat everything in one operation; the guideline favors a heart-team discussion in that setting. People with significant kidney disease, where the contrast load needs careful thought. And people whose overall health makes any long procedure hazardous.
None of these are absolute rules. They are the starting points of a conversation, and the decision belongs to you and your treating team together.
Can a chronic total occlusion be stented?
Yes, and in current practice almost every successfully crossed CTO is stented. The stent is not optional decoration; it is what keeps a long, fibrous, often calcified segment from collapsing back on itself in the days after the balloon comes out.
A drug-eluting stent is a fine metal mesh tube coated with a medicine that slowly releases into the artery wall and dampens the scar-tissue overgrowth that would otherwise renarrow the vessel. Because chronic occlusions are frequently long, more than one stent is often placed end to end, and the total stented length in a CTO can be several times that of a routine case. Operators try to keep stents as short as the anatomy safely allows, since longer stented segments carry a higher chance of renarrowing over time.
Sizing is where intravascular ultrasound earns its place. An artery that has been closed for a year shrinks. Judged by X-ray alone, it can look narrower than it truly is, and an undersized stent is more prone to failure. Ultrasound from inside the vessel measures the real diameter and confirms the stent has expanded fully against the wall.
After stenting, the metal is exposed to flowing blood until the lining grows over it. Antiplatelet medicines, which make blood platelets less sticky, are used during that healing window to lower the chance of a clot forming on the stent. How long that phase lasts depends on your bleeding risk, the stent length, and other conditions, and the prescribing cardiologist sets that plan. Never stop or shorten it on your own, and tell any dentist or surgeon that you have a recent stent before other procedures are scheduled.
How risky is a CTO procedure?
More risky than a routine stent, less risky than many people fear, and worth understanding in specifics rather than adjectives.
The signature complication is perforation, where a wire or device passes through the artery wall. Most perforations are small, self-sealing, or managed on the table with a prolonged balloon inflation or a covered stent. The serious version is bleeding into the sac around the heart, which can compress it, a condition called cardiac tamponade, and which requires urgent drainage. The consensus document, summarizing large contemporary registries, reports perforation in the low single-digit percentages of cases, with tamponade far less common, and in-hospital major adverse cardiac events, a combined measure of death, heart attack, stroke and emergency surgery, in the range of about 3 percent.
Other risks are shared with all angioplasty and described by MedlinePlus and the Mayo Clinic: bleeding or bruising at the puncture site, a heart attack caused by the procedure itself, injury to a collateral vessel during retrograde work, kidney strain from contrast dye, an allergic reaction to the dye, and, rarely, stroke. Longer X-ray exposure adds a small risk of skin injury at the beam entry site, which is one reason teams track radiation dose in real time.
Two points deserve emphasis. First, risk climbs with difficulty; a J-CTO score of 4 is a different proposition from a score of 1, and your team can tell you which yours resembles. Second, a failed attempt is not free. Contrast and radiation have already been spent, and a small proportion of complications occur in cases where the wire never crossed. That is why the pre-procedure judgment about whether to try at all matters as much as the technique.
What is the success rate of CTO angioplasty, and what does success mean?
Two very different things hide behind the word success, and conflating them is the most common misunderstanding in this field.
Technical success means the wire crossed, stents were placed, and normal flow was restored with minimal residual narrowing. The consensus document in Circulation reports technical success rates of approximately 85 to 90 percent in experienced centers using modern techniques, while noting that results are lower where these procedures are done infrequently and that anatomy heavily influences the odds. Those figures describe what happens in the room. They are not a guarantee for any individual artery, and yours may be simpler or harder than average.
Clinical success is whether you feel and function better afterward, and here the evidence is more measured. The 2021 revascularization guideline summarizes the randomized trials. In the EuroCTO trial, people assigned to CTO PCI plus medicines reported greater improvement in angina frequency and quality of life at one year than those on medicines alone. In the DECISION-CTO trial, adding CTO PCI to medical therapy did not reduce the combined rate of death, heart attack, stroke or repeat procedures over several years. The EXPLORE trial, which studied CTO PCI after a heart attack in a different artery, found no overall improvement in pumping function.
Put plainly: the strongest evidence supports symptom relief for people who remain limited despite good medical treatment. The evidence does not show that opening a CTO makes people live longer or prevents heart attacks. An honest team will tell you both halves of that sentence, and a reasonable decision can be made either way once you know them.
CTO PCI vs medicines alone vs bypass surgery: how the options compare
A chronic occlusion rarely presents a single path. Three broad strategies exist, and for many people more than one is reasonable.
| Option | What it involves | Where it usually fits | Main trade-offs |
|---|---|---|---|
| Medicines alone | Antianginal drugs, cholesterol-lowering and antiplatelet therapy, risk-factor control, cardiac rehabilitation | First step for nearly everyone; sufficient for many whose symptoms are mild or well controlled | Blockage remains; symptoms may persist on exertion; no procedural risk |
| CTO PCI | Catheter-based crossing and stenting of the occluded segment, often several hours | Persistent angina despite medicines, viable muscle beyond the block, anatomy judged crossable | Higher complication, contrast and radiation exposure than routine PCI; possibility of failure; no proven survival benefit |
| Coronary bypass surgery | Open operation grafting a vessel beyond the blockage, treating other arteries at the same time | Multiple diseased arteries, diabetes with extensive disease, or anatomy unsuitable for PCI | Longer recovery measured in weeks; surgical risks; durable graft to the CTO territory |
The guideline’s framing is useful here. Medical therapy is not the consolation prize; it is the foundation on which everything else is layered, and it continues after any procedure. Bypass surgery becomes more attractive as the number of diseased arteries rises, because a surgeon can address them all in one operation and the graft to a CTO territory does not depend on threading the occlusion itself. CTO PCI occupies the middle ground: a targeted fix for a single limiting blockage in someone who wants to avoid or is not suited to surgery.
What the table cannot capture is you: your symptoms, your other conditions, your tolerance for procedural risk, and your goals. Those are the inputs that turn a comparison into a choice.
How doctors plan a CTO procedure before the day arrives
Much of the work happens before anyone enters the catheterization laboratory. A CTO case attempted without a map is a CTO case more likely to fail, and planning is where experienced teams spend their effort.
The existing angiogram is reviewed frame by frame, ideally with injections from both sides so the collaterals and the far vessel are visible. Some teams add a CT coronary angiogram, a heart scan with contrast that shows the course of the blocked segment and the amount of calcium inside it, details that X-ray angiography cannot reveal because no dye flows through the block. From these images the team estimates the J-CTO score and sketches a primary strategy and a backup.
Functional testing answers whether the procedure is worth attempting. A stress test or nuclear scan shows whether the territory is short of oxygen under load, and a viability study shows whether the muscle there is alive enough to recover. Blood tests check kidney function, since contrast dye is cleared by the kidneys, and a plan is made for fluids and dye limits.
Your medicines are reviewed. Blood-thinning drugs and some diabetes medicines may need adjusting around the procedure, and the timing is set by the team, not guessed at home. You will be asked to fast for several hours beforehand and to arrange for someone to drive you home; the NHS notes that you should not drive yourself after angioplasty.
Finally there is consent. A good consent conversation for a CTO covers not only the general risks of angioplasty but the specific ones: the chance the artery cannot be crossed, the chance of perforation, the radiation and contrast involved, and what the plan is if the first strategy fails.
How long is CTO PCI recovery time, and what do the first weeks look like?
Physically, recovery from a CTO PCI resembles recovery from any angioplasty, with one caveat: the longer procedure means a longer stretch lying flat, more contrast to clear, and sometimes a second puncture site to protect.
Most people go home the same day or after one night, according to the NHS, with the stay depending on the access site used, kidney function afterward, and whether anything needed watching. If the groin was used, you will lie flat for several hours before sitting up; a wrist site allows earlier movement but is kept still and compressed.
The Mayo Clinic advises avoiding heavy lifting and strenuous exercise for about a week, and the NHS says not to drive for a week after a planned angioplasty; both stress checking your specific instructions, since long or complicated cases may warrant more caution. Most people return to desk work within roughly a week, and physically demanding jobs take longer.
Symptom change is not instant. Some people notice easier breathing on the first walk; others find angina fades gradually over weeks as the heart muscle adapts to blood arriving from the front rather than through collaterals. A stress test months later may be arranged if symptoms return, because renarrowing inside long stented segments does occur and is treatable.
Cardiac rehabilitation, a supervised exercise and education program, is recommended after PCI by the American Heart Association and is one of the most consistently underused parts of care. It is also where the medicines started or adjusted around the procedure, particularly antiplatelet therapy, become routine. Take them exactly as prescribed and bring any concerns about side effects to the prescriber rather than pausing them.
What people often get wrong about CTO treatment
Because the language is frightening and the evidence is nuanced, chronic occlusions attract more misunderstanding than most heart conditions.
A totally blocked artery means a heart attack is imminent. Not in this case. A CTO is by definition months old, and the muscle beyond it has either adapted through collaterals or already scarred. The risk of a future heart attack comes mainly from other, unstable plaques elsewhere, which is why cholesterol and blood pressure control matter regardless of what happens to the CTO.
Collaterals mean the blockage is harmless. Collaterals are remarkable, but the consensus literature is clear that they rarely match a native artery’s capacity during exertion. A person can be perfectly comfortable at rest and limited on a gentle hill for exactly this reason.
Opening it will prevent a heart attack or extend life. The randomized trials summarized in the 2021 guideline did not show this. Symptom relief is the demonstrated benefit; the rest remains unproven.
If the first attempt failed, nothing can be done. Failed attempts are common enough that the J-CTO score awards a point for them. Retrograde techniques and CT planning have opened arteries that earlier antegrade attempts could not, and bypass surgery remains an option in suitable candidates.
It is just a longer version of a normal stent. The complication profile, contrast load, radiation, and skill dependence are all genuinely different, which is why the consensus document emphasizes operator experience and case volume.
Medicines are what you get when doctors give up. Guideline-directed medical therapy is the treatment every trial participant received, in both arms. It is the floor, not the fallback.
Questions to ask your care team before a CTO PCI
A good conversation before this procedure takes longer than the consent form suggests, and a prepared list keeps it anchored on what matters to you. These are the questions experienced clinicians expect and welcome.
- How confident are you that this blockage is causing my symptoms, and have we exhausted what medicines can do?
- Is the heart muscle beyond the blockage still alive, and how do you know?
- How difficult does my anatomy look on the scale you use, and what does that mean for the chance of crossing and the chance of complications?
- What is the first strategy you plan to use, and what is the backup if it fails?
- Will you need two access sites, and which arteries will you use?
- How much contrast and radiation do you expect, and how does my kidney function affect the plan?
- What would make you stop the procedure rather than continue?
- Would bypass surgery treat this better, given everything else in my arteries?
- How many of these procedures does your team perform, and how are outcomes reviewed?
- What medicines will change before and after, and for how long, and who manages that?
- What symptoms after discharge should prompt a phone call, and what should send me to the emergency department?
- If the artery cannot be opened, what does my treatment look like from there?
The last question is the one most people skip and the one most worth asking. A team that has a clear, unhurried answer for what happens if the wire never crosses is a team that has thought about your case as a whole rather than as a technical puzzle. Bring someone with you if you can, write down the answers, and know that asking to think it over is always reasonable for a planned procedure.
When to call your doctor after CTO treatment: red-flag signs
Most recoveries are uneventful. The point of knowing the warning signs is not to worry about them but to act quickly on the rare occasion they appear, because the serious complications of this procedure are time-sensitive and treatable when caught early.
Call emergency services immediately if you develop chest pain or pressure that resembles your angina but does not settle with rest, or that is new, severe, or spreading to the arm, jaw or back; sudden shortness of breath, especially with light-headedness or a racing heartbeat; fainting or near-fainting; or sudden weakness, facial droop, or difficulty speaking, which are stroke signs. Chest pain in the first days after a CTO PCI can signal a clot forming inside a new stent or bleeding around the heart, and neither can wait.
Call your cardiology team the same day if the puncture site bleeds and does not stop after firm pressure for several minutes, or if it develops a rapidly growing lump, spreading bruise, or increasing pain. Do the same for a hand or leg below the access site that becomes cold, pale, numb or painful, which can indicate reduced blood flow. Fever, redness or discharge at the site suggest infection. A sharp drop in how much you are urinating, or new swelling, warrants a call because of the contrast load your kidneys handled.
Also contact the team about any bleeding that seems disproportionate, such as black or bloody stools, blood in urine, or nosebleeds that are hard to stop, since antiplatelet medicines raise bleeding risk and the plan may need review. And if your original symptoms return weeks or months later, that is worth reporting even if it feels like a step backward; renarrowing can be assessed and, where appropriate, treated.
Frequently asked questions
How long does it take to recover from a CTO PCI?
Most people leave hospital the same day or after one night and resume light activity within days, according to the NHS and Mayo Clinic, with heavy lifting and driving typically restricted for about a week. Longer CTO cases may warrant more caution, especially if two access sites were used or kidney function needs rechecking. Symptom improvement can be immediate or unfold over several weeks.
How risky is a CTO procedure compared with a regular stent?
It carries higher risk than routine angioplasty because the blocked segment is invisible on X-ray and stiffer wires are needed. Registries summarized in the Circulation consensus document report perforation in the low single-digit percentages and in-hospital major adverse events around 3 percent. Contrast and radiation exposure are also higher. Your individual risk depends heavily on anatomy, kidney function and overall health.
What is the CTO angioplasty success rate?
Technical success, meaning the wire crossed and flow was restored with stents, is reported at roughly 85 to 90 percent in experienced centers by the global consensus document in Circulation, and lower where these cases are done rarely. Clinical success, meaning you feel better, is a separate question; trials show symptom relief but not longer survival. No figure predicts your particular artery.
Can a chronic total occlusion stent stay open long term?
Stents placed across chronic occlusions can remain open for years, but long stented segments renarrow more often than short ones, and complete reclosure occasionally happens. Intravascular ultrasound sizing, full stent expansion and consistent antiplatelet therapy reduce that risk. Returning symptoms should prompt a call to your team rather than waiting, because renarrowing is usually treatable.
What is retrograde CTO PCI and why is it used?
Retrograde CTO PCI reaches the blockage from behind by steering a wire from a healthy artery through a collateral channel to the far end of the occlusion, where the cap is often softer. It is chosen when the entry cap is ambiguous, heavily calcified, or has resisted forward attempts. It adds complexity and time but has made many previously uncrossable arteries treatable.
Does opening a CTO prevent a heart attack?
The evidence does not show that it does. The DECISION-CTO trial, cited in the 2021 ACC/AHA/SCAI guideline, found no reduction in death, heart attack or stroke from adding CTO PCI to medicines. Future heart attacks usually come from other unstable plaques, so cholesterol and blood pressure control remain essential whatever happens to the occluded artery.
Why has my blocked artery not caused a heart attack already?
Because it closed slowly enough for collateral vessels to grow and supply the muscle beyond it, and any muscle that did lose supply has already adapted or scarred. That is what the word chronic means here. Collaterals often suffice at rest but not during exertion, which is why symptoms appear on hills or stairs rather than in a chair.
What is the J-CTO score my cardiologist mentioned?
It is a difficulty rating from 0 to 5 described in the Circulation consensus document. One point each is given for a blunt or unclear entry cap, calcium in the blocked segment, a bend of more than 45 degrees, a blocked length of 20 millimeters or more, and a previous failed attempt. Higher scores predict longer procedures and lower crossing rates.
Is bypass surgery better than CTO PCI?
Neither is universally better. The 2021 revascularization guideline favors a heart-team discussion when several arteries are diseased, where bypass can treat everything in one operation and does not depend on crossing the occlusion. For a single limiting blockage in someone unsuited to or wishing to avoid surgery, CTO PCI is a reasonable option. The right choice depends on your anatomy and health.
What happens if the CTO cannot be opened during the procedure?
The team stops, removes the equipment, and you recover as after any angioplasty, usually going home the next day. Failed attempts are common enough that the J-CTO score counts them. Options afterward include continuing medical therapy, a repeat attempt with different techniques or CT planning, or bypass surgery. Ask your team beforehand what their plan would be in that scenario.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Does Angina Need More Than Medication? How Cardiologists Decide on Stents or Bypass
Angina usually needs more than medication when symptoms keep limiting daily life despite well-adjusted medicines, when tests show a large area of heart muscle…

After Arrhythmia Treatment: Which Sensations Are Normal and When to Call Your Cardiologist
After arrhythmia treatment, mild palpitations, a faster resting pulse, fatigue, a bruised access site and skin soreness after cardioversion are common and usually settle…

TAVI Recovery Timeline: Early Walking, the Cardiac Unit Stay and the First Two Weeks Home
After TAVI, most people are helped to sit up and take their first steps within hours of the procedure, spend roughly one to three…

Statin Alternatives: Red Yeast Rice, Plant Sterols, Ezetimibe and PCSK9: What Works
Statin alternatives range from well-tested medicines to modest supplements. Ezetimibe, PCSK9 inhibitors and bempedoic acid have randomized trials showing they lower LDL cholesterol and…
Why Follow-Up Imaging Is Scheduled After Endovascular Surgery to Confirm Blood Flow
Follow-up imaging after endovascular surgery is scheduled because a stent graft can develop problems that cause no symptoms: blood leaking back into the aneurysm…

Heart Disease in Women: The Different Symptoms, Risk Factors and Tests
Heart disease is the leading cause of death in women, yet it is often recognized later than in men. Chest pain remains the most…