

How CT Planning Guides Robotic Hip Replacement: Implant Position and Leg Length Explained
Key Takeaways
- In CT-based robotic hip replacement, the scan is segmented into a three-dimensional model on which the surgeon virtually places the cup and stem and reads off predicted leg length and offset before any incision is made.
- The robotic arm constrains where the surgeon's reamer and cup impactor can move; it does not cut, decide or operate independently, and the surgeon can convert to conventional technique at any point.
- The most consistent finding in published comparisons is more reproducible cup positioning with fewer outliers; differences in pain, function and complication rates in the first years have been small or absent.
- A CT scan is not required for conventional hip replacement, which is planned from plain X-rays, and having no CT does not indicate a lesser operation.
- The NHS describes a typical recovery of walking aids for about 4–6 weeks and return to office work at roughly 6–12 weeks, with the same timeline for robotic and conventional surgery.
- A persistent long-leg sensation early after surgery is common even when measurements are equal, because shortened muscles and a tilted pelvis take weeks to adapt.
In robotic hip replacement, a CT scan taken before surgery is turned into a three-dimensional model of the pelvis and femur. The surgeon uses that model to plan the size, angle and depth of the implants and to estimate how the plan affects leg length and hip offset. During surgery, the robotic arm helps the surgeon carry out that plan, while every decision stays with the operating team.
The scanner room is cold, and the radiographer is asking someone with a hip that has hurt for three years to lie flat and hold still. It feels backward. The whole point of surgery is to stop lying awake because of that joint, and here is one more appointment before anything is fixed. Then the radiographer says something clarifying: the surgeon will build the operation around these pictures.
That is the quiet promise behind robotic hip replacement CT planning. A CT scan (a series of X-ray slices stitched into a detailed cross-section of the body) becomes a digital copy of your pelvis and thigh bone. On that copy, the surgical team rehearses the operation: which size of cup, which angle, how deep the stem sits, and what all of that does to the length of the leg you will stand on afterward.
This article explains what the scan does, what the robot does and does not do, what the evidence honestly shows, and which questions are worth asking before you sign the consent form.
What is robotic hip replacement CT planning, in plain terms?
A total hip replacement swaps a worn ball-and-socket joint for an artificial one. The socket (the acetabulum, a cup-shaped hollow in the pelvis) receives a metal shell with a liner. The ball at the top of the thigh bone (the femoral head) is removed and replaced with a stem that anchors inside the bone and carries a new ball. Mayo Clinic and MedlinePlus describe this as one of the most common elective operations for advanced hip arthritis.
Robotic-arm assisted surgery adds a layer of measurement to that familiar operation. The word “robotic” is doing a lot of work here and can mislead. The device does not perform the surgery on its own. It is a mechanical arm with sensors that the surgeon guides by hand, and it holds cutting or reaming tools within limits that were set in advance.
Those limits come from planning. In CT-based systems, the patient has a CT scan of the pelvis and femur before surgery. Software converts the slices into a three-dimensional model. On that model, the surgeon chooses implant sizes and positions, and the program reports the expected effect on leg length and on offset (the sideways distance between the center of the hip ball and the long axis of the femur, which affects how the muscles pull).
Think of it as the difference between hanging a shelf by eye and hanging it with a laser level and a pre-drawn template. A skilled person can do the first well. The second removes some of the guesswork, especially when the wall is uneven. The wall, in this case, is a pelvis that arthritis, previous injury or unusual anatomy may have reshaped, and the template is the CT plan.
Not every robotic or navigated hip system uses CT. Some rely on plain X-rays or on landmarks registered during surgery. This article is about the CT-based approach, because that is where the planning story is richest.
Is a CT scan required before hip replacement surgery?
For a conventional hip replacement, no. Most hip replacements around the world are planned from plain X-rays, and the NHS and Mayo Clinic list X-rays, blood tests and a general health assessment as the usual pre-operative workup. Surgeons trace templates over a standing pelvic X-ray, estimate implant sizes, and refine the plan by feel and by trial components during the operation. Decades of good results rest on that method.
A CT scan before hip replacement becomes part of the pathway when the chosen surgical system needs it. CT-based robotic platforms build their three-dimensional model from CT data, so in that setting the scan is not optional; it is the raw material for the plan. Some surgeons also request a CT outside robotic surgery, for example when a previous fracture, childhood hip disease or earlier surgery has changed the shape of the bone in ways a flat X-ray cannot show.
The scan itself is a routine imaging test. MedlinePlus explains that CT uses X-rays from many angles to create cross-sectional images, and that it exposes the body to more radiation than a single plain X-ray. For most adults having joint surgery, clinicians judge that added exposure to be small relative to the benefit of detailed anatomy, but it is a fair topic to raise, particularly for younger patients or anyone who has had many scans.
Two practical points follow. First, if you are having a conventional replacement and nobody has mentioned a CT, that is not a sign of a lesser operation. Second, if you are having a CT-planned robotic replacement, the scan is scheduled with a specific protocol: a defined set of slices through the pelvis, the hip, the knee and sometimes the ankle, so the software can measure rotation and length along the whole limb. A scan taken elsewhere for a different reason often cannot be reused, which explains why you may be asked to have a new one even if you had a CT recently.
What actually happens on the day of the planning scan
The appointment is usually shorter than the wait for it. You lie on a narrow table that slides through a ring-shaped scanner. Unlike MRI, the ring is open at both ends and the scan is quiet apart from a whirring sound. The NHS notes that a CT scan itself typically takes only a few minutes, though the whole visit is longer because of positioning and checks.
Positioning matters more than usual. The radiographer will straighten both legs, sometimes strap the feet so they do not rotate, and align the pelvis squarely. This is not fussiness. The software later measures angles to within a degree or two, and a pelvis tilted on the table introduces error that would follow the plan into the operating room. If arthritis makes it painful to lie flat, say so; padding under the knees or a different arm position can often help without spoiling the images.
No contrast dye is needed for bone planning, so there is normally no injection and no fasting. Metal in clothing is removed. If you have a previous implant on the other side, the radiographer will note it, because metal scatters X-rays and creates streaks that the software has to work around.
Afterward, the images travel to the planning software, where a technician or engineer segments them: tracing the outline of the pelvis and femur on each slice so the program can assemble a solid model. The surgeon reviews and adjusts that model. Some centers do this days ahead; others finalize the plan in the operating room after the patient is asleep. Ask which applies to you, because it shapes whether you can see the plan beforehand.
One myth is that a poor scan means poor surgery. In reality, if the images are inadequate, the scan is repeated or the team falls back to conventional templating. The plan is a tool the surgeon uses, not a switch that locks the operation into a fixed course.
How the CT becomes a 3D model: the engineering behind the plan
Segmentation is the first step, and it is the reason a CT can do things an X-ray cannot. A plain radiograph flattens the pelvis into a shadow, so a cup that looks well angled from the front may be tilted forward or back in a way the picture cannot reveal. The CT keeps the depth. Once the pelvis and femur are outlined on every slice, the software stacks them into a shape you can rotate on screen.
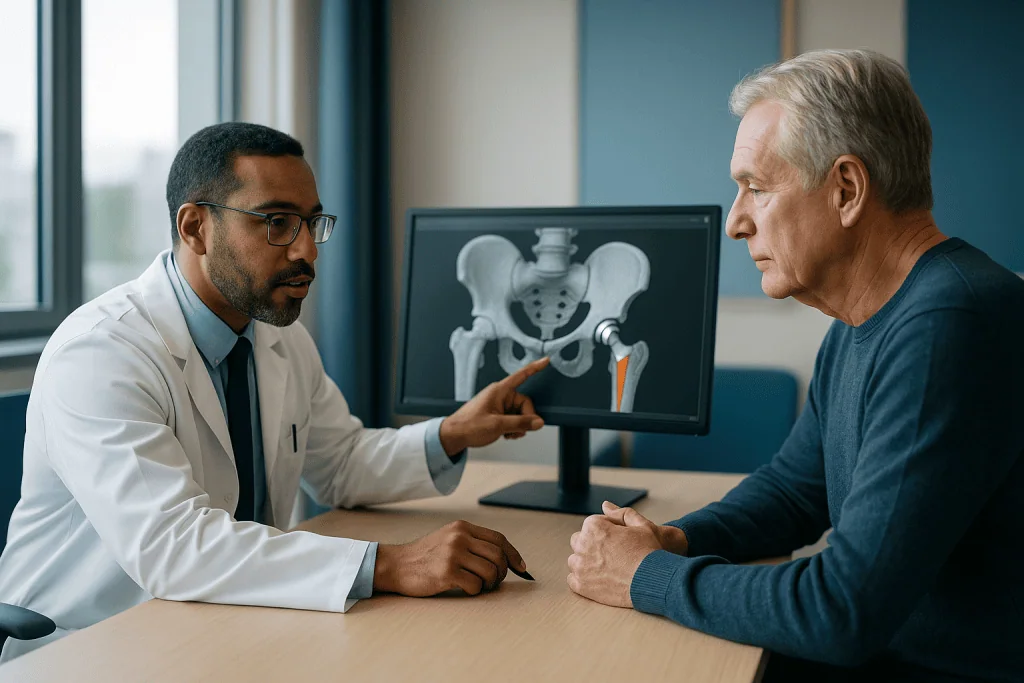
Next comes a virtual fit. The library of implant components exists as digital shapes with exact dimensions. The surgeon or engineer places a trial cup inside the modeled socket and adjusts three settings: size (how wide), inclination (how steeply the cup tilts from horizontal) and anteversion (how far it faces forward). On the femoral side, the stem is sized to the inside of the bone canal, and its depth and neck angle are chosen.
The software then reports consequences. Because the model includes both legs, it can compare the planned hip to the opposite hip and estimate the change in leg length. It also calculates offset and predicts, in a simplified way, how the new ball and socket would move through a range of motion, flagging positions where the neck of the stem might strike the rim of the cup. That collision, called impingement, is one of the mechanical routes to dislocation, so the plan is checked against it.
Some systems also account for how the pelvis tilts when you stand versus when you sit. A cup that is well placed for a person lying on an operating table may function differently for the same person slumped on a sofa, because the pelvis rolls backward in sitting and effectively opens or closes the cup. Adding standing and seated X-rays to the CT data lets the software estimate a functional position rather than a purely anatomical one.
All of this is calculation, not certainty. The model is only as good as the segmentation, and the predictions rest on assumptions about how soft tissue behaves. Surgeons treat the plan as a well-informed starting point.
Why hip replacement implant positioning matters more than most people realize
If you ask what makes a hip replacement last, most people guess the quality of the metal or plastic. Materials matter, but position is often the quieter determinant. A cup that is too steep or too open concentrates load on one edge of the liner, which can speed wear. A cup that faces too far forward or backward changes how far the leg can move before the ball levers out of the socket. Mayo Clinic and Cleveland Clinic list dislocation, wear and loosening among the recognized complications, and each has a link to how the parts sit.
Dislocation deserves particular attention. The artificial ball is held in place by the depth of the cup, the tension of the surrounding muscles and the absence of anything blocking the way. When implants are positioned so that the stem neck hits the cup rim during ordinary movements such as bending to tie a shoe, the ball can be pried out. Historically, surgeons have described target windows for cup angles that appear to reduce this risk, and much of the appeal of CT planning is that it aims to land consistently inside a chosen window rather than relying on eyeballing the angle in a patient lying on their side under drapes.
The femoral stem has its own considerations. Sitting it too deep shortens the leg; sitting it proud lengthens it. Rotating it a few degrees changes how the ball meets the cup. Combined anteversion (the forward tilt of cup and stem added together) is a concept many surgeons use to keep the pair working as a system rather than as two separate parts.
What CT planning cannot do is guarantee that the plan equals the result. Bone quality, the surgeon’s ability to see, and how the muscles and capsule feel when the trial hip is tested all inform final decisions. Position is a target, and a target is worth having precisely because reaching it every time is hard.
How CT planning aims to set leg length and offset
Leg length after hip replacement is one of the most common worries patients bring to follow-up clinics, and one of the more misunderstood. The sensation of one leg being longer is common in the first weeks, even when measurements show the legs are close to equal. Tight muscles that were shortened for years by arthritis, a pelvis that has learned to tilt to protect a sore hip, and swelling around the new joint can all create a lopsided feeling that settles as the body adapts.
That said, real differences do happen, and they are the thing planning tries to control. On a plain X-ray, surgeons measure from a line across the pelvis to a landmark on each femur. On a CT model, the software measures the whole bone from hip to knee, which removes some of the error introduced by rotation and pelvic tilt. It then shows how each candidate stem depth and neck length changes the total.
Offset is the sibling measurement. If offset is reduced, the hip muscles work at a mechanical disadvantage and the joint can feel loose or weak; the surgeon may be tempted to restore tension by lengthening the leg instead, which is where unintended length comes from. If offset is restored properly, tension can be achieved without extra length. A three-dimensional plan lets the surgeon see both numbers side by side and choose a component combination that balances them.
Inside the operating room, the plan is checked against reality. The team registers the patient’s actual bone to the model by touching known landmarks with a tracked probe, and the system then reports leg length and offset changes as the trial components are placed. If the leg is coming out long, a shorter neck or deeper stem can be tried before anything is final.
Everyone’s anatomy includes small natural asymmetries, and a plan aims for balance rather than perfect symmetry. Cleveland Clinic notes that persistent, bothersome length differences after surgery are usually first managed with time, physical therapy and, if needed, a simple shoe insert, with the surgical team deciding whether anything more is warranted.
Robotic hip replacement CT planning in the operating room: what the robot does and does not do
Once you are asleep and positioned, the first job is registration. Small pins or clamps carrying reflective markers are attached to the pelvis and femur so that an infrared camera can track them. The surgeon touches a series of points on the exposed bone with a probe, and the software matches those points to the CT model. If the match is not close enough, registration is repeated. Only when the digital pelvis and the real pelvis agree does the plan become usable.
The surgeon then prepares the socket with a reamer, a rotating tool that shapes the bone to receive the cup. Here the robotic arm plays its most visible role. It holds the reamer and resists movement outside the planned volume and angle. The surgeon still applies the force and feels the bone; the arm acts like a firm hand on the wrist that will not let the tool drift. When the cup is impacted into place, the arm again constrains the angle so the shell seats close to the planned inclination and anteversion.
On the femoral side, systems vary. Some track the stem position and report leg length and offset after each trial reduction without constraining the tools. Others help guide the neck cut. In every case, the removal of the femoral head, the broaching of the canal and the final impaction are done by the surgeon’s hands.
What the robot does not do is decide. It does not detect a fragile bone about to crack, judge whether the capsule is too tight, or notice a bleeding vessel. The surgeon does. If the operating team judges that the plan needs changing, the plan changes; if the system malfunctions, the operation continues conventionally. Patients are consented for that possibility as a matter of routine.
The closing steps look like any hip replacement: trial components are tested through a range of motion to check stability, final implants are placed, the wound is closed, and imaging confirms the result before you leave the recovery area.
Who is usually offered robotic hip replacement, and who is asked to wait
The people offered any hip replacement are, first of all, people for whom the operation is appropriate. The NHS describes candidates as those with severe hip pain and stiffness, usually from osteoarthritis, that interferes with sleep, work and daily activities despite non-surgical treatment such as pain relief medicines, physiotherapy and weight management where relevant. The decision rests on how much the hip limits life, not on age alone.
Within that group, whether the operation is robotic depends largely on what the treating surgeon uses and considers suitable. CT planning may have particular appeal when anatomy is unusual: a shallow socket from childhood hip dysplasia (a condition in which the socket never fully formed around the ball), a pelvis reshaped by an old fracture, marked deformity from advanced arthritis, or a spine that has been fused and no longer lets the pelvis tilt normally. In each of these, a flat X-ray hides information that a three-dimensional model shows.
Some patients are asked to wait rather than proceed, and the reasons are the same for robotic and conventional surgery. Active infection anywhere in the body, uncontrolled diabetes, recent heart or lung problems, poorly healing skin around the hip, or smoking that the team wants stopped first are common reasons for a pause. Mayo Clinic and Johns Hopkins both emphasize that optimizing general health before elective joint surgery reduces the chance of complications, and a few weeks of preparation is often a good investment.
A separate group may not be suitable for the CT-based robotic pathway specifically: for example, someone who cannot lie still for the scan, someone with extensive metal implants that would distort the images, or someone for whom the additional imaging is judged not worthwhile. In those cases, a conventional operation is not a downgrade. It is the standard against which everything else is measured.
Whoever you are, the recommendation should come with reasons. Ask why this technique for this hip, and expect an answer that refers to your anatomy and your health rather than to the technology itself.
CT-planned robotic vs conventional hip replacement: a side-by-side
The table below sets out what typically differs and what does not. It is a description of pathways, not a scorecard, and individual hospitals vary in detail.
| Step | CT-planned robotic replacement | Conventional replacement |
|---|---|---|
| Pre-operative imaging | Dedicated CT of pelvis, hip and knee, sometimes with standing and seated X-rays | Standing pelvic and hip X-rays |
| Planning method | Three-dimensional digital model with virtual implant placement and predicted leg length and offset | Two-dimensional templating on X-rays |
| In the operating room | Bone registered to the model with tracked pins; robotic arm constrains reaming and cup angle | Surgeon uses anatomical landmarks, alignment guides and experience |
| Leg length check | Live software readout plus clinical assessment | Clinical assessment, sometimes with manual jigs or X-ray |
| Extra steps | Pin sites in bone, registration time, possible conversion to conventional technique | None additional |
| Implants used | Standard hip components compatible with the platform | Standard hip components |
| Anesthesia, incision, recovery pathway | Same as conventional | Same as robotic |
Two rows deserve emphasis. The implants themselves are ordinary hip components; the robot changes how they are positioned, not what they are made of. And the recovery pathway, described by the NHS and Mayo Clinic in terms of early walking, physiotherapy and gradual return to activity, is the same for both approaches. Robotic surgery does not shorten bone healing or muscle recovery.
The extra steps row is where the honest trade-offs live. Pins placed in the pelvis or femur leave small additional wounds and carry a small risk of fracture or irritation at those sites. Registration adds time under anesthesia. Neither is dramatic, but neither is nothing, and both belong in an informed conversation.
What the evidence actually shows about robotic hip replacement so far
Here is the part that marketing tends to skip. The strongest and most consistent finding in studies of robotic-arm assisted hip replacement is about precision: cups tend to land closer to the planned angles, and there is less scatter from one patient to the next, compared with freehand placement. Fewer outliers in component position is a real and measurable result.
Whether that precision translates into outcomes patients feel is a different question, and the evidence is less settled. Randomized trials and registry studies comparing robotic and conventional hip replacement have generally found similar pain relief, function and complication rates in the first years. Some studies suggest fewer dislocations or better leg length matching with robotic assistance; others find no difference. Long-term data on whether more consistent positioning extends implant survival are still accumulating, because a modern hip implant is expected to last many years and the robotic systems in wide use are comparatively new.
Mayo Clinic frames the general picture accurately for any hip replacement: most people experience substantial pain relief and improved mobility, and the operation carries risks including infection, blood clots, dislocation, fracture, leg length difference and loosening over time. Nothing in the published literature suggests robotic assistance removes those risks. What it may do is reduce the variability of one contributor to them.
Guideline bodies have taken a cautious stance. Where they have commented, it has been to describe robotic assistance as an evolving technology whose added benefit over well-performed conventional surgery is not yet proven for routine cases, while acknowledging plausible advantages in complex anatomy. That is a reasonable summary.
The honest way to read this: if you are offered CT-planned robotic surgery, you are not being offered a proven better outcome. You are being offered a method that aims to make one part of the operation more reproducible. For some patients and some anatomies that reproducibility is valuable. For others, an experienced surgeon’s conventional technique reaches the same target. Your surgeon’s own familiarity with the method matters as much as the method itself.
How long does it take to recover from a robotic hip replacement? Robotic hip replacement recovery time explained
Recovery from a robotic hip replacement follows the same arc as recovery from any hip replacement, because the bone, muscle and skin have had the same operation. The NHS describes a typical pattern: most people are helped to stand and take steps with a frame or crutches on the day of surgery or the day after, go home once they can manage stairs and basic self-care, use walking aids for roughly 4–6 weeks, and return to office-based work in about 6–12 weeks depending on the job. Full strength and confidence continue to build over several months, and the NHS notes that complete recovery can take up to a year.
The first few days center on three things. Walking, early and often, because movement pumps blood through the calves and lowers the risk of clots. Pain control, so that walking is possible; the team will usually combine local anesthetic techniques with tablets, and any changes to that plan are for the prescribing clinician. And wound care, keeping the dressing clean and dry and watching for signs described in the section on when to call your doctor.
Weeks one to six are about physiotherapy. Exercises rebuild the hip abductors (the muscles on the side of the hip that keep the pelvis level when you stand on one leg) and restore the range of motion. Swelling and bruising down the thigh are expected. Sleep can be disrupted by positioning rules and by the joint’s own aching, and this usually eases as the weeks pass.
Mayo Clinic advises that driving is usually possible once you are off strong pain medicines and can control the pedals comfortably, often around the six-week mark for a right hip, and that most people resume low-impact activities such as walking, swimming and cycling within a few months, with high-impact sports discouraged long term to protect the implant.
None of this timeline is a promise. Age, fitness before surgery, other health conditions and how the tissues heal all shift it. The robot does not.
What is the 90 rule for hip replacement? Movement precautions explained
Ask this question in a physiotherapy gym and you will hear about hip precautions: a set of movement limits given after some hip replacements to protect the new joint while the soft tissues heal. The best-known is the instruction not to bend the hip beyond a right angle, which is where the “90” comes from. Sitting on a low chair, leaning forward to pull on socks, or drawing the knee up toward the chest can all take the hip past that point.
The logic is mechanical. Early after surgery the capsule and muscles around the joint have been cut or stretched and have not yet formed the scar tissue that will later help hold the ball in the socket. In deep flexion, particularly combined with turning the knee inward and crossing the legs, the neck of the implant can lever against the rim of the cup and push the ball out. Precautions aim to keep the hip away from those positions until the tissues recover.
Whether you are given precautions at all, and how strict they are, depends on the surgical approach and the surgeon’s practice. The posterior approach (entering from the back of the hip) has traditionally come with the strictest rules. The anterior approach (entering from the front) often comes with fewer or different restrictions. Some surgeons have relaxed precautions altogether, citing evidence that modern implants and careful positioning make routine restriction less necessary. Others keep them. Your own instructions come from your team, and they override anything general written here.
Where CT planning connects to this: the point of aiming for consistent implant position, and of checking for impingement on the model, is to reduce the mechanical vulnerability that precautions protect against. That is a reason some surgeons feel comfortable with lighter restrictions after planned surgery. It is not a reason to ignore the restrictions you are given.
Cleveland Clinic and Johns Hopkins both describe practical adaptations for the early weeks: raised toilet seats, firm high chairs, a long-handled shoe horn and reacher, and keeping the knees below the hips when sitting.
What people often get wrong about robotic hip surgery
The robot operates. It does not. Every cut, every reaming pass and every implant is placed by the surgeon’s hands. The arm restricts where a tool can go; it does not initiate movement. If the surgeon steps away, nothing happens.
Robotic means smaller incision. The incision length is determined by the surgical approach and what the surgeon needs to see, not by the presence of a robot. Minimally invasive techniques exist for conventional surgery, and robotic surgery may use a standard-length incision. Pins for tracking markers add small wounds of their own.
Robotic means faster recovery. The tissues undergo the same operation and heal at the same speed. The NHS recovery timeline does not distinguish between robotic and conventional replacement. Some studies report slightly less early pain or shorter hospital stay with robotic assistance, others do not, and any such difference is small compared with the effect of pre-operative fitness and diligent physiotherapy.
The implants are special. They are the same categories of cup, liner, stem and ball used in conventional surgery, made by the same processes. The plan changes where they sit.
A CT plan guarantees equal leg lengths. Planning improves the estimate and gives a live check during surgery, but the surgeon may deliberately accept a small difference to achieve a stable, well-tensioned hip. Stability and equal length occasionally compete, and stability usually wins that argument for good reason.
If the robot is available, it is always better. The evidence does not support this for every patient. The largest measured benefit is in the consistency of component position. For someone with straightforward anatomy and an experienced surgeon, conventional technique achieves comparable results in published studies.
You can feel the difference afterward. Patients cannot tell from the inside which method was used. What they feel is how well the hip works, and that depends on many things beyond the tool used to ream the socket.
Is robotic surgery the newest hip replacement technique? Trade-offs, risks and alternatives
People searching for the newest hip replacement technique often find robotic systems, and they are among the more recent additions to mainstream practice. Newer is not the same as better, and hip replacement has a long history of innovations that promised more than they delivered before careful follow-up sorted the durable from the fashionable. Robotic assistance is being evaluated in exactly that way now.
Other developments sit alongside it. Computer navigation without a robotic arm uses tracking and software to display angles during surgery. Patient-specific instruments are cutting guides printed to match an individual’s bone from CT or MRI data. Direct anterior approaches, improved bearing materials and enhanced recovery pathways that get people walking within hours have each changed practice over recent decades. Many of the biggest gains in hip replacement have come from these unglamorous process improvements rather than from any single device.
The specific risks of adding a robot and CT plan are modest but real: extra radiation from the scan, pin-site complications including rare fractures through the pin holes, slightly longer time under anesthesia for registration, and the possibility of converting to a conventional technique mid-operation if the system fails or the registration cannot be trusted. Set against these are the general risks of any hip replacement listed by Mayo Clinic and the NHS: infection, blood clots in the leg or lung, dislocation, fracture around the implant, nerve or blood vessel injury, leg length difference, and loosening or wear over the long term.
Alternatives to surgery itself remain relevant right up to the operating room door. Weight management where appropriate, structured exercise, walking aids, pain-relieving medicines and steroid injections into the joint can each control symptoms for a time, and the NHS recommends surgery only when these no longer allow an acceptable quality of life. A hip resurfacing, in which more of the natural bone is kept, is an alternative operation for a limited group of patients that a surgeon may discuss.
The right choice sits with you and your treating team, weighed against your anatomy, your health and your goals.
Questions to ask your care team about hip replacement implant positioning
A good consultation is a two-way exchange. These questions tend to produce informative answers about the technique and about the person proposing it.
- Why are you recommending a CT-planned robotic approach for my hip specifically, rather than a conventional replacement? What about my anatomy makes the three-dimensional plan useful?
- Will you be able to show me the plan before surgery, including the predicted change in leg length and offset? If the plan is finalized on the day, how will I learn what was decided?
- How many of these operations do you perform, and how long have you used this system? What is your process if the system cannot register my bone or stops working during the operation?
- Which surgical approach will you use, and will I have hip precautions afterward? For how long?
- What is your target for my leg length, and under what circumstances would you accept a small difference to achieve a more stable hip?
- Do standing and seated X-rays of my spine and pelvis form part of the plan? Is my spine mobility something you are taking into account?
- What are the pin-site risks, and where will the pins be placed?
- What will the hospital stay look like, and what determines when I go home?
- What signs after surgery should make me call the ward or my doctor rather than wait for a routine appointment?
- If I decide against robotic surgery, would you still perform my operation conventionally, and would anything else about the plan change?
Write the answers down or bring someone who will. The most useful answers are specific to you: they mention your socket shape, your spine, your previous operations or your bone quality. Answers that mainly describe the technology in general terms are a prompt to ask again, more directly, about your own hip.
Finally, ask what the team would advise a family member in your position. Surgeons are often candid in reply, and candor is what an informed decision needs.
When to call your doctor
Most recoveries are uneventful, and most days after surgery feel a little better than the one before. Some symptoms, though, need attention quickly rather than at the next scheduled visit. The NHS and Mayo Clinic describe the following as warning signs after hip replacement.
Call the ward, your surgeon’s office or the number you were given without delay if you notice: increasing redness, warmth, swelling or discharge from the wound, or the wound edges opening; a temperature or chills; pain in the calf, or swelling and tenderness in one leg that is new or worsening; a sudden feeling that the hip has given way, popped or shifted, particularly if you can no longer bear weight or the leg looks shortened or turned; or severe pain that is escalating despite the pain relief you were prescribed.
Seek emergency care immediately if you develop sudden breathlessness, chest pain, coughing up blood, or a racing heart, because these can indicate a blood clot that has traveled to the lung. Likewise for a fall onto the operated hip with new severe pain, or for numbness, weakness or loss of movement in the foot that was not present before.
Less urgent but still worth a call: persistent numbness or tingling around the incision that is not improving, a leg length feeling that has not settled by the time your team said it usually would, a clicking or grinding sensation in the joint, or difficulty passing urine or opening your bowels in the first days home.
Do not stop, start or change any medicine on your own, including blood thinners prescribed to prevent clots; ask the prescribing clinician. And if something worries you that is not on this list, the right move is still to call. Surgical teams would far rather answer an unnecessary question than hear about a delayed one.
Frequently asked questions
Is a CT scan required before hip replacement surgery?
Only when the chosen surgical system needs it. Conventional hip replacement is planned from plain X-rays, which the NHS lists as standard pre-operative imaging. CT-based robotic platforms build their three-dimensional plan from a dedicated CT of the pelvis, hip and knee, so in that pathway the scan is required. Surgeons may also request a CT for complex anatomy regardless of technique. Ask your team which applies to you.
What does a CT scan before hip replacement involve, and is the radiation a concern?
The scan is quick, painless and done without contrast dye. You lie flat with legs straightened while a ring-shaped scanner takes cross-sectional X-ray images. MedlinePlus notes that CT uses more radiation than a single plain X-ray. For most adults having joint surgery, clinicians judge the exposure acceptable against the benefit of detailed planning, but it is reasonable to discuss, especially if you are younger or have had many scans.
How long does it take to recover from a robotic hip replacement?
The same as any hip replacement, because the tissues have had the same operation. The NHS describes standing with a frame or crutches within a day, using walking aids for about 4–6 weeks, returning to office-based work in roughly 6–12 weeks, and full recovery taking up to a year. Robotic hip replacement recovery time depends on your fitness, health conditions and physiotherapy, not on the tool used in surgery.
What is the 90 rule for hip replacement?
It refers to a common post-operative precaution not to bend the hip beyond a right angle while the soft tissues heal, along with avoiding crossing the legs or turning the knee inward. The aim is to prevent the implant neck from levering the ball out of the socket. Whether you receive this rule, and for how long, depends on your surgical approach and your surgeon’s practice. Follow your own team’s instructions.
Does CT planning guarantee equal leg length after hip replacement?
No. It improves the estimate and gives a live readout during surgery, but the surgeon may deliberately accept a small difference to achieve a stable, well-tensioned hip. Many people also feel a temporary long-leg sensation after surgery even when measurements are equal, because shortened muscles and a tilted pelvis take weeks to adapt. Cleveland Clinic notes that persisting differences are usually managed first with time, physiotherapy and a shoe insert.
What is the newest hip replacement technique?
Robotic-arm assisted surgery with CT planning is among the more recent methods to enter mainstream use, alongside computer navigation, patient-specific cutting guides and refined anterior approaches. Newer does not automatically mean better. The evidence so far shows more consistent implant positioning with robotic assistance, while patient-reported outcomes in early years are broadly similar to well-performed conventional surgery. Long-term implant survival comparisons are still being gathered.
Does the robot perform the hip replacement?
No. The surgeon performs every step by hand. The robotic arm holds the reaming and impaction tools and resists movement outside the planned angle and depth, functioning like a firm guide rather than an operator. It cannot detect fragile bone, judge soft tissue tension or manage bleeding; those are the surgeon’s judgments. If the system fails or registration cannot be trusted, the operation continues using conventional technique.
What are the extra risks of robotic hip replacement compared with conventional surgery?
The additional elements are modest: radiation from the planning CT, small wounds where tracking pins are placed in the pelvis or femur with a rare risk of fracture or irritation at those sites, slightly longer anesthesia time for registration, and the possibility of converting to a conventional technique mid-operation. The general risks of hip replacement listed by Mayo Clinic, including infection, clots, dislocation and loosening, apply to both approaches.
How does hip replacement implant positioning affect dislocation risk?
The artificial ball stays in the socket through cup depth, muscle tension and the absence of anything blocking movement. If the cup or stem is angled so that the stem neck strikes the cup rim during ordinary bending or twisting, the ball can be levered out. Surgeons aim for target angle windows and for a balanced combined anteversion of cup and stem. CT planning tries to reach those targets more consistently.
Who is a good candidate for CT-planned robotic hip replacement?
Anyone who is a candidate for hip replacement in general: severe pain and stiffness, usually from osteoarthritis, that limits daily life despite non-surgical treatment. CT planning is often considered particularly useful for unusual anatomy such as hip dysplasia, previous fractures or a fused spine. People with active infection, uncontrolled medical conditions or extensive metal implants that would distort the scan may be asked to wait or offered a conventional operation.
References
- NHS: Hip replacement
- MedlinePlus: CT Scans
- MedlinePlus: Hip Replacement
- Cleveland Clinic: Hip Replacement
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Local, Regional or General? Anesthesia Options for Finger and Toe Surgery Explained
Most finger and toe operations can be done under local anesthesia, usually a digital block that numbs only the affected digit while you stay…

Who May Be a Candidate for Proximal Fibular Osteotomy When Inner-Knee Arthritis Is Mild?
Proximal fibular osteotomy is usually considered for adults whose knee osteoarthritis is confined mainly to the inner (medial) compartment, who have mild to moderate…

Knee Pain Causes: Why Knees Hurt (and Why It Differs in Women)
Knee pain in women most often comes from patellofemoral (front-of-knee) pain, osteoarthritis, tendon or bursa irritation, meniscus wear, or ligament injury. Women see certain…

Shoulder, Elbow, Wrist or Hand: How Upper Limb Surgery Is Planned for Each Joint
Upper limb surgery covers operations on the shoulder, elbow, wrist and hand, from nerve releases and tendon repairs to fracture fixation and joint replacement.…

Life After Adult Reconstruction Surgery: Why High-Impact Sport Is Limited and What Replaces It
After adult reconstruction surgery, the orthopedic term for hip and knee replacement, most care teams advise a long-term shift away from running, jumping and…
How Foot Surgery Is Performed: Bunion Correction, Fusion and Tendon Repair Step by Step
Foot surgery is usually performed as a day procedure under a nerve block, spinal or general anesthetic. The surgeon makes one or more small…