

How Dentists Read a Cavity X-Ray Before a Dental Filling: Judging the Depth of Decay

Key Takeaways
- Decay appears dark on an X-ray because demineralized tooth tissue blocks fewer X-rays than healthy enamel, so the image is a density map rather than a picture of a hole.
- Bitewing images are the standard view for cavities because they show the contact surfaces between back teeth that a mirror cannot reach.
- Dentists grade depth by how far the shadow reaches: outer or inner enamel, outer, middle or inner dentin, with the enamel-dentin junction as the usual line between monitoring and filling.
- Enamel-only lesions can often be hardened with fluoride and better plaque control, while decay in dentin does not regrow and usually needs restoration.
- Radiographs tend to underestimate lesion size and can miss chewing-surface decay, so the visual and tactile exam is combined with the image before any decision.
- Short-lived sensitivity after a filling is common and usually fades over days to a few weeks, but severe, spontaneous or worsening pain, swelling or fever needs prompt dental attention.
Before a filling, dentists usually read a bitewing X-ray, in which decay appears as a darker shadow because softened tooth tissue absorbs fewer X-rays. They judge depth by how far that shadow reaches: outer or inner enamel, outer or deeper dentin, or close to the pulp. Shallow enamel lesions are often monitored and strengthened with fluoride; lesions into dentin usually need a filling. Your dentist combines the image with a visual exam.
The dentist tilts the screen toward you, taps a gray smudge on the side of a molar and says, “That one needs a filling.” You squint. It looks like every other smudge. How does anyone tell a cavity from a shadow, let alone how deep it goes?
That moment, half curiosity and half unease, is where most questions about a cavity X-ray before filling begin. The image is small, black and white, and oddly abstract, yet it carries the single most useful piece of information in the appointment: how far the decay has traveled through the tooth. Depth decides almost everything that follows, from “let’s watch it” to “let’s numb you up today.”
This explainer walks through what dentists are actually looking at, why decay shows up the way it does, and how the read is turned into a plan. Nothing here replaces your own dentist’s judgment; it should simply make the next conversation easier to follow.
What a cavity X-ray before filling actually shows
A dental X-ray, or radiograph, is a picture made by passing a brief burst of X-rays through the tooth onto a sensor. Dense tissue blocks more of the beam and appears light; less dense tissue lets more through and appears dark. Enamel, the hard outer shell of the tooth, is the densest substance in the body, so it shows up almost white. Dentin, the softer layer beneath it, is a mid gray. The pulp, the living core of nerves and blood vessels, is a dark channel in the middle (MedlinePlus).
Tooth decay works by dissolving mineral. Acid produced by bacteria leaches calcium and phosphate out of enamel and dentin, leaving the tissue porous. Porous tissue blocks fewer X-rays, which is why a cavity shows as a darker patch, often called a radiolucency, inside the bright outline of the tooth (NHS; Mayo Clinic).
So the cavity X-ray before filling is really a map of lost mineral. The dentist is not looking for a hole in the ordinary sense; many early lesions have no visible hole at all. They are looking for a change in shade and a change in shape, typically a small triangle or notch that starts at the outer surface and points inward.
Three things are read from that smudge. First, where it sits: most hidden decay starts on the flat sides where two teeth touch, a spot a mirror cannot see. Second, how far in it reaches, which this article covers in detail below. Third, what lies around it: the thickness of healthy tissue still between the decay and the pulp, the bone level beside the root, and any older filling nearby whose edges might be leaking. Only when those three readings sit side by side does the picture become a decision.
Why decay looks dark on a film: the physics in plain words
Think of the X-ray beam as light shining through a stack of window blinds. A tightly closed blind, like enamel, lets little through and casts a bright area on the sensor. A blind with slats half open, like demineralized enamel, lets much more through and leaves that spot darker. The sensor simply records how much beam arrived at each point (Cleveland Clinic).
The practical consequence surprises many people: a cavity has to lose a fair amount of mineral before it becomes visible. Early demineralization that a dentist can sometimes spot on a dry, well lit surface as a chalky white spot may not show on the image at all, because enough mineral remains to keep the shade almost normal. The X-ray therefore tends to underestimate how far a lesion has crept, which is one reason dentists speak of “at least this deep” rather than exactly this deep.
Angle matters too. The beam travels straight through the tooth, so two overlapping tooth edges, a slightly rotated tooth or a crowded contact can produce a gray zone that mimics decay. Dentists learn to recognize these look-alikes, and a repeat image from a corrected angle sometimes settles the question.
A further quirk: a natural dip in density called cervical burnout appears near the gumline where enamel ends and the thinner root begins. It can resemble a cavity to an untrained eye. The giveaway is its position and shape, uniform and band-like rather than notched. Knowing that such artifacts exist explains why your dentist may pause over one spot, zoom in, adjust contrast and compare with an older image before saying anything at all. The pause is the read working properly, not a sign of doubt about the tooth.
Bitewing X-ray for cavities: why this angle is the workhorse
Dental offices use several kinds of images, but the one most tied to cavity detection is the bitewing. The name comes from the small tab the patient bites down on, which holds the sensor so that the crowns of upper and lower back teeth appear together on one picture (MedlinePlus; Cleveland Clinic).
The bitewing earns its place for a simple reason: it looks straight through the contact points between neighboring teeth, exactly where food and plaque sit trapped and where the mirror cannot reach. Decay that begins on those side surfaces, known as interproximal decay, can grow for a long time without any visible hole, sensitivity or discoloration. On a bitewing it reveals itself as that characteristic notch just below the point where the two teeth touch.
The same image also shows the top of the bone between teeth and the fit of existing fillings and crowns, so one picture serves several checks at once. A full set of bitewings for an adult usually means a pair on each side, four images in total, though the number varies with how many teeth a person has (Cleveland Clinic).
Other images answer other questions. A periapical view captures a single tooth from crown to root tip and is used when the dentist needs to see whether decay has reached the pulp or whether infection has formed at the root. A panoramic image sweeps the whole jaw in one frame but is too coarse for judging small cavities. The choice of image is itself part of the read: if a bitewing shows decay sitting close to the pulp, a periapical view may be added before any filling is planned, because what lies below the gumline changes the options.
How dentists judge the depth of decay, layer by layer
Depth is read against the tooth’s own anatomy. Enamel forms the outer cap, a few millimeters thick at its widest and tapering toward the gumline. Dentin fills the bulk of the tooth beneath it. The pulp chamber sits in the center. A radiolucency is placed into one of several bands depending on how far inward it reaches, a system widely taught in dental radiology and used in everyday charting.

| Where the shadow reaches | What it usually means | Common approach (set by your dentist) |
|---|---|---|
| Outer half of enamel | Early demineralization; surface may still be intact | Monitor, fluoride, hygiene and diet changes |
| Inner half of enamel, not yet at dentin | Lesion advancing; still often reversible | Monitor closely, repeat image at a set interval |
| Just past the enamel-dentin junction | Decay has entered dentin and tends to spread sideways | Filling usually discussed |
| Middle third of dentin | Established cavity; a true hole is likely | Filling, size and material chosen by dentist |
| Inner third, approaching pulp | Risk of pulp irritation or exposure | Filling with protective liner, or root canal evaluation |
The enamel-dentin junction deserves a sentence of its own. Enamel is dense and resists spread, so a lesion within it stays small and cone-shaped. Dentin is porous and threaded with microscopic tubules, so once decay crosses the junction it often fans out wider than the enamel opening suggests. That is why a tiny dark fleck at the junction can hide a much larger cavity underneath, and why dentists shift from “watch” to “treat” at that boundary (NIH NIDCR).
Depth is never read in isolation. The dentist also asks how fast the lesion has changed since the last image, how much decay the rest of the mouth shows, and whether the person’s risk factors, such as dry mouth or frequent sugar exposure, make progression more likely. Two identical shadows in two different mouths can reasonably lead to two different plans.
Do cavities show on X-rays every time? The honest limits
No. Radiographs are very good at the hidden side surfaces and reasonable at decay beneath old fillings, but they miss some lesions and exaggerate others. Knowing where the blind spots lie helps make sense of a dentist who takes an X-ray and then still reaches for a probe.
Chewing surfaces are the first blind spot. The grooves and pits on the top of a molar are surrounded by thick enamel on every side, so a small cavity in the groove can be hidden behind a wall of bright tissue. Many occlusal cavities are found by eye, by feel or with a light-based device rather than on film.
Early lesions are the second. As noted above, mineral loss has to be substantial before it changes the shade enough to see. A white spot caught during the exam may be the same age as a shadow on a neighboring tooth; the difference is only how much mineral is gone.
Overlap is the third. If two back teeth sit tightly together or slightly rotated, their edges can overlap on the image and hide, or mimic, decay at the contact. A second view from a different angle usually resolves this.
Finally, metal fillings and crowns block the beam entirely, so anything directly behind them is invisible. Decay creeping under the edge of an old restoration is often inferred from the margin, where a dark line or gap appears, rather than seen directly.
None of this makes the image less useful; it makes the combination essential. A cavity X-ray before filling tells the dentist where to look harder and how deep to expect trouble. The visual and tactile exam confirms, and sometimes overrules, what the picture suggests (Mayo Clinic; MedlinePlus).
Who usually gets a filling, and who is usually asked to wait
The dividing line most dentists use is the enamel-dentin junction. Decay confined to enamel is frequently managed without drilling, because enamel can regain mineral. Saliva, fluoride and a lower-acid diet together can harden a lesion back to the point where it stops progressing (NHS; NIH NIDCR). Decay that has crossed into dentin rarely reverses, and because dentin is soft and spreads the lesion sideways, waiting tends to mean a larger filling later.
People commonly asked to wait and watch include those with a shallow enamel shadow, a stable image compared with a previous one, good daily plaque control, and no symptoms. The waiting is active, not passive: a fluoride plan, cleaned contact points, and a repeat bitewing at an interval the dentist sets based on risk. Many dental guidelines frame this as monitoring, and the repeat image is the point at which the decision is revisited.
People more likely to be offered a filling include those whose shadow reaches dentin, whose lesion has visibly grown since the last image, who report sensitivity in that tooth, who have several active cavities at once, or whose risk factors, such as reduced saliva from medications or medical conditions, make progression likely. A visible break in the enamel surface, found with the probe or by eye, usually tips the balance toward treatment even when the X-ray looks modest.
Children and teenagers follow the same logic, with one twist: cavities in primary (baby) teeth and freshly erupted permanent teeth can move faster because the enamel is thinner and less mature, so the threshold for treating is often lower. Pregnant patients can safely have a cavity treated; dentists simply time elective work and shield the abdomen for any imaging (MedlinePlus).
The common thread is that the decision always sits with the treating dentist, who has the full picture, including the parts an article cannot see.
How a dental X-ray before filling shapes the plan
Once depth is read, the image keeps working. It influences four practical choices that follow.
The first is the size of the preparation, the cavity the dentist shapes after removing decay. A lesion that fans out under the enamel tells the dentist to expect more soft tissue than the surface suggests, so the appointment is booked for a larger filling rather than a quick one.
The second is how close the floor of the filling will come to the pulp. If the shadow stops in the middle third of dentin, a straightforward filling is likely. If it approaches the inner third, the dentist plans to leave a thin layer of firm, affected dentin over the pulp and place a protective base before the filling. This technique, sometimes called indirect pulp capping, aims to avoid exposing the nerve while still arresting the decay.
The third is material. Deep or wide cavities and heavy chewing surfaces may steer the dentist toward one filling material over another, or toward a partial crown instead of a filling when too little healthy tooth would remain to hold a filling securely. Material choices are made by the dentist for the specific tooth; no option is universally better.
The fourth is sequencing. When bitewings show several cavities, the deepest or the one nearest the pulp is often treated first, because that tooth is the one most likely to turn painful while waiting.
A cavity X-ray before filling also sets a baseline. The post-treatment image at a later check-up is compared to it, which is how dentists spot a filling that is settling well versus one with a gap at its edge. In other words, the picture taken today keeps earning its keep for years.
Why the image is only half the read: the clinical exam
Watch a dentist after they study the screen and you will usually see them pick up a mirror and a fine probe, dry the tooth with a puff of air, and look again. That sequence is not ceremony. It supplies the information the radiograph cannot.
Drying matters because wet enamel reflects light evenly and hides early change; dried enamel reveals the chalky white spot of demineralization or the brown stain of an older, slower lesion. Color and texture give clues about activity. A dull, rough white patch is often active; a smooth, shiny brown one may be arrested and need nothing but monitoring.
The probe, used gently, answers a different question: is the surface still intact? A lesion that looks worrying on the X-ray but has a hard, unbroken surface may be a candidate for remineralization. One with a soft, catching surface is a cavity in the everyday sense, whatever the image shows. Modern practice favors light pressure, since forcing a sharp probe into a weakened enamel surface can break it and turn a reversible lesion into one that needs a filling.
History fills in the rest. Does the tooth twinge with cold or sweets? Has the person noticed food packing between two teeth? Have they recently started a medication that dries the mouth? Is their diet heavy in acidic drinks sipped over hours? Each answer nudges the estimate of how fast the lesion is moving.
Some practices add a light-based or laser fluorescence device that reads the surface of chewing grooves. These tools are aids, not verdicts; their readings are interpreted alongside the X-ray and the exam rather than replacing either (Mayo Clinic; Cleveland Clinic).
What actually happens in the chair after the read
If the decision is a filling, the appointment follows a sequence that the X-ray has already sketched out.
Local anesthetic numbs the tooth and the surrounding gum. Depth on the image helps the dentist judge how much numbing the tooth will need; a lesion close to the pulp can be more sensitive during preparation, so the dentist may wait a little longer before starting or add a second injection if needed. Many people are offered a rubber dam, a small sheet that isolates the tooth, keeps it dry and stops debris reaching the throat.
Decay removal comes next. The dentist uses a rotating instrument, sometimes followed by hand tools, to remove softened tissue until firm dentin is reached. Depth is checked against the image as the work proceeds; a dentist who expected a shadow to stop mid-dentin will slow down when the preparation reaches that level and check the floor carefully.
When the cavity is deep, a thin liner or base is placed over the dentin nearest the pulp to insulate it. The filling material is then packed or layered into the cleaned space, shaped to match the tooth’s contours, and hardened. Bite is checked with marking paper and adjusted so the new surface meets its opposing tooth evenly (MedlinePlus; Mayo Clinic).
A single filling typically takes a part of an hour, though a deep, wide or multiple-surface cavity takes longer, and the dentist will say so at the time of planning.
Sometimes the plan changes mid-procedure. If the decay turns out to reach the pulp despite the image suggesting otherwise, the dentist will stop and explain the options, which may include a protective dressing and a later review, or root canal treatment. That conversation belongs to the treating dentist and the patient, not to a prediction made from a screen.
What the following days and weeks usually look like
Numbness from local anesthetic wears off over the hours after the appointment. Most dentists suggest avoiding chewing on that side until feeling returns, mainly to avoid biting the cheek or tongue (MedlinePlus).
Mild sensitivity to cold, heat or pressure in the filled tooth is common and generally fades over days to a few weeks as the pulp settles (Cleveland Clinic; Mayo Clinic). The deeper the cavity was, the closer the filling floor sits to the pulp and the more likely a short spell of sensitivity becomes; this is one reason the depth read matters for setting expectations before the appointment rather than after.
A filling that feels “high” when you bite, as if that tooth touches first, is worth a call. Adjustment is quick and prevents the ache that comes from a tooth being overloaded with each chew.
Brushing and flossing resume the same day. Flossing around a new filling on a side surface may feel slightly different for a day or two as the gum adjusts to the new contact.
At the next routine visit, the dentist examines the filling’s edges and, when due, repeats bitewings to confirm no shadow is reappearing at its margin. If the plan was to monitor a shallow enamel lesion rather than fill it, this repeat image is the decision point: a stable or smaller shadow supports continued monitoring, while a larger one usually means a filling is now advised. The interval between images is set by individual risk, not a fixed calendar, and the dentist should be able to explain the reasoning.
For most people the weeks after a filling are uneventful. The tooth is used normally, the sensitivity drifts away, and the appointment fades into the background of a dental history that the next X-ray will quietly document.
Is a cavity X-ray before filling safe? Radiation in perspective
The short answer is that dental radiographs use a very small amount of radiation, and the information they provide generally outweighs that exposure when the images are taken for a clear reason (MedlinePlus; Cleveland Clinic).
Several features keep the dose low. Modern digital sensors need far less exposure than older film. The beam is narrow and aimed at a small area of the jaw. A lead apron, often with a thyroid collar, shields the rest of the body, although current guidance from several professional bodies notes that with modern equipment the apron adds little protection and is increasingly optional; your dentist will follow their own protocol (Cleveland Clinic).
The guiding principle, sometimes abbreviated ALARA for “as low as reasonably achievable,” means images are taken when they are likely to change a decision, not on a fixed schedule for everyone. Someone with a history of frequent cavities or dry mouth may be imaged more often than someone with a long stable record. Asking why an image is being taken is a reasonable question, and a good answer sounds like “to check the contacts we can’t see” or “to compare with last time’s shadow,” not “because it’s been a year.”
Pregnancy does not rule out dental X-rays when they are needed to diagnose a problem; the beam is directed at the mouth and shielding is used. Many dentists still prefer to postpone purely routine imaging until after delivery, and the choice is made jointly with the patient (MedlinePlus).
Children receive smaller doses because the equipment is adjusted for their size, and the shorter exposure times of digital sensors help here too. For every age, the question is the same: does this image answer something that matters for the tooth in front of us? For a suspected cavity before a filling, it usually does.
What people often get wrong about cavity X-rays
“If it shows on the X-ray, it must be a hole.” Not necessarily. A shadow means lost mineral, and early lesions can have a completely intact surface. Some are managed without a filling at all (NHS).
“If it doesn’t show on the X-ray, there’s no cavity.” Chewing surfaces and very early lesions can be invisible on film. A dentist who finds a cavity by eye that the image did not show is not contradicting the X-ray; they are reading a surface the X-ray cannot see.
“The X-ray shows the exact size.” It usually underestimates. Decay has to remove a good deal of mineral before the shade changes, so the real lesion is often larger than the shadow, especially once it is in dentin.
“A cavity that doesn’t hurt can wait.” Pain usually arrives late, when decay nears the pulp. Many cavities that need filling have never caused a twinge (Mayo Clinic; NIH NIDCR).
“Fluoride can fix any cavity.” Fluoride and good hygiene can arrest and reharden enamel lesions. Once decay is established in dentin, it does not grow back, and a filling restores the tooth (NHS).
“Whitening or a filling hides decay on later X-rays.” Whitening does not change density. Fillings do block the beam, which is why the dentist studies their edges so carefully.
“More X-rays mean a more thorough dentist.” Images are taken when they will change a decision. Fewer, well timed pictures are the mark of careful practice, not neglect.
The thread running through these myths is a single misunderstanding: the X-ray is a density map, not a photograph of a hole. Once that clicks, most of the surprises in the dental chair stop being surprises.
Questions to ask your care team before the filling
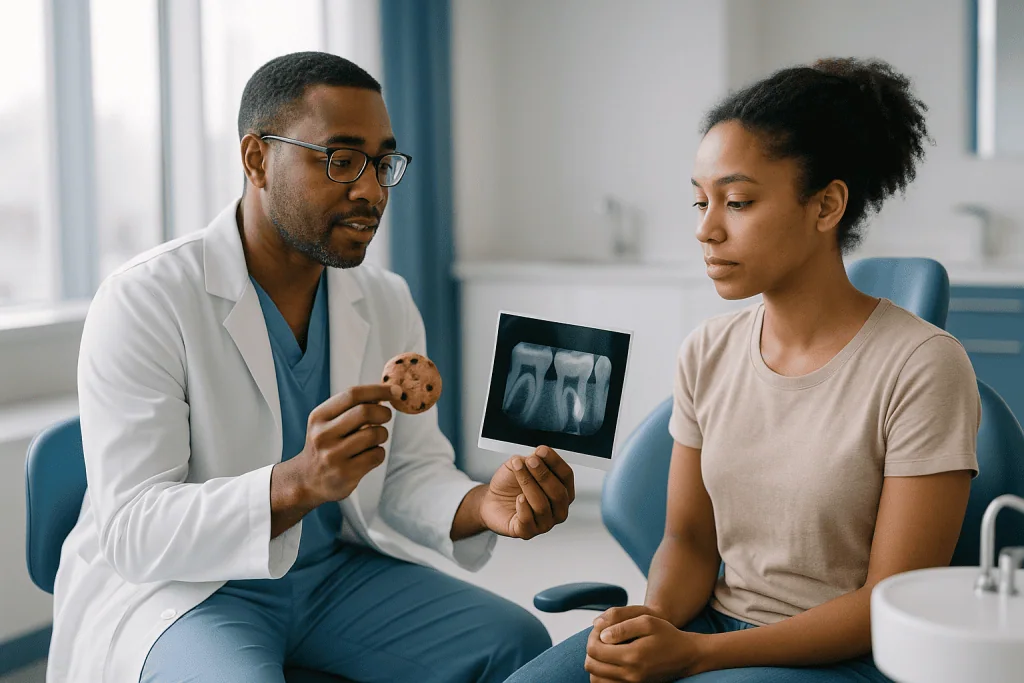
A good read is one you can follow. Ask to see the image on the screen and have the dentist point to the shadow; most are glad to do it, and seeing it yourself makes the rest of the conversation concrete.
- Where exactly is the decay, and which layer has it reached: enamel, outer dentin or deeper?
- Is the surface still intact, or did you feel a break with the probe?
- Has this spot changed compared with my last X-ray? Can we look at them side by side?
- Is this one that could be monitored and strengthened with fluoride, or has it passed that point?
- How close is it to the nerve, and what will you do if it turns out to be deeper than it looks?
- Which filling material are you planning for this tooth, and why that one here?
- How long should I expect sensitivity afterward, and what would be a sign that something is not right?
- Are there other shadows you are watching, and when would you want to image them again?
- Is there anything in my diet, medicines or habits that is making cavities more likely?
Two of these matter more than the rest. The question about the enamel-dentin junction tells you whether you are at the “watch” or “treat” stage, and the question about proximity to the nerve tells you whether the appointment might take an unexpected turn. A dentist who can answer both clearly, pointing at the image as they go, is giving you the same read they gave themselves.
Write the answers down or ask for a note in your record. At the next visit, with a fresh image on the screen, those notes are what turn two separate appointments into a story you can actually follow.
When to call your doctor or dentist
Most cavities and most fillings pass without drama. A few signs mean the situation has moved beyond routine and deserves a prompt call rather than waiting for the next check-up.
Contact your dentist, or an urgent dental or medical service if the practice is closed, if you notice any of the following (NHS; Mayo Clinic; MedlinePlus):
- Toothache that is severe, throbbing, or keeps you awake, especially if it starts without an obvious trigger or lingers for minutes after hot or cold.
- Swelling of the gum, face or jaw, or a pimple-like bump on the gum near a tooth, which can signal an abscess.
- Fever, feeling generally unwell, or swollen glands under the jaw alongside a tooth problem.
- Difficulty opening the mouth, swallowing or breathing with facial swelling; this needs emergency care immediately.
- A new filling that feels high, cracked or loose, or sensitivity that is worsening rather than fading after the first few weeks.
- A piece of tooth or filling that has broken away, leaving a sharp edge or an exposed cavity.
- Bleeding or discharge from the area that does not settle.
Pain on biting that appears days after a deep filling can mean the bite needs a simple adjustment, or it can mean the pulp is struggling; either way, the dentist needs to see it. Lingering, spontaneous pain is the symptom that most often changes a plan from filling to root canal evaluation, and the sooner it is assessed, the more options remain.
None of these signs can be judged from an article. The treating dentist, with the image, the exam and your history in front of them, is the person to make the call, and a quick phone description is usually enough for them to decide how soon you should be seen.
Frequently asked questions
Do cavities show on X-rays every time?
No. X-rays reliably show decay between back teeth and under the edges of old fillings, but they can miss small cavities in the grooves of chewing surfaces, where thick enamel on all sides hides the lesion. Very early mineral loss may also be invisible until enough tissue has softened. That is why dentists combine the image with drying, looking and gentle probing before deciding.
How deep is my cavity if the dentist says it is in the enamel?
It means the dark shadow stops before reaching the enamel-dentin junction, the boundary between the hard outer shell and the softer dentin beneath. Lesions at this depth often have an intact surface and can sometimes be hardened with fluoride and better plaque control rather than filled. Your dentist will usually suggest monitoring with a repeat image at an interval based on your risk.
What does a bitewing X-ray show for a cavity?
A bitewing shows the crowns of upper and lower back teeth together, with the contact points between neighboring teeth in clear view. Decay there appears as a small dark notch just below the point where two teeth touch. The same image shows the bone level between teeth and the fit of existing fillings, so one picture serves several checks at once.
Why does my dentist want a dental X-ray before filling if they can already see the cavity?
The visible hole is often the tip of the lesion. An X-ray shows how far decay has spread beneath the surface and how close it sits to the pulp, which shapes how large the filling will be, whether a protective base is needed, and whether a root canal evaluation might be necessary instead. It also provides a baseline image to compare at future check-ups.
Can a cavity seen on an X-ray reverse on its own?
Only if it is still within the enamel. Enamel can regain mineral from saliva and fluoride, so a shallow lesion with an intact surface may stop progressing or become harder. Once decay has crossed into dentin, that tissue does not regrow, and a filling is the usual way to restore the tooth. The dentist judges which stage applies from the image and the exam.
Is it safe to have a cavity X-ray before filling if I am pregnant?
Dental X-rays can be taken during pregnancy when they are needed to diagnose a problem; the beam is aimed at the mouth and shielding is used. Many dentists prefer to postpone purely routine imaging until after delivery, and the decision is made jointly with the patient and, where relevant, the obstetric team. Tell your dentist if you are or might be pregnant.
How often should cavity X-rays be taken?
There is no single schedule. The interval depends on individual risk: a history of frequent cavities, dry mouth, high sugar exposure or recent fillings generally leads to more frequent bitewings, while a long stable record allows longer gaps. The guiding principle is to take an image only when it is likely to change a decision, and your dentist should be able to explain the reasoning.
Why did the cavity turn out deeper than the X-ray suggested?
Because the image only shows tissue that has lost enough mineral to change shade, and decay in dentin spreads outward along microscopic tubules faster than the enamel opening suggests. The shadow is therefore a minimum estimate. Dentists plan for this and check the floor of the cavity as they work, which is why the plan can change during the appointment.
What is the dark area near the gumline on my X-ray that is not a cavity?
It is often cervical burnout, a normal drop in density where the thick enamel of the crown ends and the thinner root begins. It appears as a uniform band rather than a notch and sits at the same level on neighboring teeth. Dentists distinguish it from decay by its shape and position, and may compare with earlier images if there is any doubt.
Why is my tooth sensitive after a filling that was based on a deep cavity X-ray?
The floor of a deep filling sits close to the pulp, and the pulp can be irritated by the preparation and the new material. Mild sensitivity to cold, heat or pressure is common and usually fades over days to a few weeks. Pain that is severe, spontaneous, lingering or getting worse, or a bite that feels high, should be reported to the dentist promptly for assessment.
References
- MedlinePlus: Dental x-rays
- MedlinePlus: Dental cavities
- NHS: Tooth decay
- Cleveland Clinic: Dental X-rays
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Bruxism Myths: Only Stress Causes It, Night Guards Weaken Teeth and More Corrected
Bruxism, the clenching or grinding of teeth while awake or asleep, has several contributors beyond stress, including brief sleep arousals, certain medicines, caffeine, alcohol,…
Living With Teeth Veneers: Night Guards, Nail Biting and Habits That Protect the Bond
Living with veneers mostly means protecting the thin bond between porcelain or composite and your natural tooth. That means wearing a night guard if…
How Orthognathic Surgery Is Performed: Repositioning the Jaws From Inside the Mouth
Orthognathic surgery repositions the upper jaw, lower jaw or both by cutting the bone through incisions made inside the mouth, moving the segments into…

Orthodontic Treatment Stages: Alignment, Bite Correction, Finishing and Retention
Orthodontic treatment stages usually run in a fixed order: assessment and planning, alignment and leveling of crooked teeth, bite correction, finishing and detailing, and…
Is Sensitivity After Teeth Veneers Normal? What Settles on Its Own and What to Report
Some sensitivity to cold, air or biting is common in the first days after veneers are placed, because a thin layer of enamel has…

Can Gum Disease Be Cured or Reversed? What Treatment Achieves at Each Stage
Gum disease can be cured only in its earliest stage. Gingivitis, where gums are red, swollen and bleed but no bone is lost, is…