

How Foot Deformities Progress Over Time and How Orthopedic Treatment Is Planned

Key Takeaways
- Clinicians stage most foot deformities as flexible, semi-rigid or rigid, and the stage, not the size of the bump, determines which treatments remain possible.
- Bunions are the most common foot deformity and usually reflect inherited foot shape, with tight footwear acting as an accelerator rather than the sole cause.
- Adult acquired flatfoot follows a four-stage course from an inflamed posterior tibial tendon to a rigid collapsed arch and eventually a tilted ankle.
- Charcot foot in people with neuropathy can fracture and collapse without pain, so a hot, red, swollen foot in someone with diabetes is urgent even when it does not hurt.
- Weight-bearing X-rays are essential for planning because deformity angles measured on a non-standing image underestimate the true alignment.
- Orthoses, footwear changes and physiotherapy relieve pain and slow progression but do not reverse bony deformity, and surgery is generally reserved for pain or function that persists despite them.
Most foot deformities progress slowly, over years, as soft tissues stretch, joints drift and bone remodels under repeated load; bunions widen, flatfoot moves from a flexible to a rigid arch, and hammertoes stiffen. Orthopedic teams plan treatment by staging the deformity with a weight-bearing exam and X-rays, trying footwear, orthoses and physiotherapy first, and reserving surgery for pain or function that no longer responds.
She noticed it in a shoe-shop mirror: the right big toe leaning toward its neighbor, the joint at its base a little wider than it had been in the photograph from her daughter’s graduation. Nothing hurt yet. Her mother’s feet had looked like this, and then, twenty years later, quite different. The question she carried into the orthopedic clinic was not really “what is this?” but “where is this going, and when do we act?”
That is the honest heart of understanding how foot deformities progress. A foot is 26 bones, more than 30 joints and a web of ligaments and tendons carrying your whole weight thousands of times a day. When alignment slips, load shifts, and load is what drives change.
This explainer walks through the common deformities, the stages clinicians use, and how a treatment plan is built, without promising outcomes nobody can guarantee.
What actually happens when a foot deformity progresses
Think of the foot as a suspension bridge. The arch is the span, the ligaments are the cables, and the muscles and tendons are the maintenance crew that adjusts tension with every step. A deformity begins when one element gives a little: a tendon weakens, a ligament stretches, a joint capsule loosens. The bridge does not collapse. It sags a fraction, and the load that used to spread evenly now concentrates on a few points.
Bone answers load. Where pressure rises, bone thickens and spurs form; where a joint is pushed off-center, cartilage wears unevenly. Soft tissue answers too. A tendon working at a poor angle loses mechanical advantage, so it strains harder and weakens further. This is why progression tends to be self-reinforcing: the more the alignment drifts, the more force pushes it in the same direction.
Clinicians describe three broad phases. First comes the flexible phase, when the joint can still be moved back to normal position by hand and the change is mostly soft tissue. Next is the semi-rigid phase, in which the joint moves partway. Last is the rigid phase, when bone and joint surfaces have remodeled and the shape is fixed. Mayo Clinic notes that bunions and hammertoes both follow this arc from flexible to fixed if the driving forces continue.
The pace varies enormously. Genetics set the starting geometry, and footwear, body weight, activity, arthritis and nerve function set the speed. Nobody can tell a patient the exact year a flexible toe will become rigid. What a good clinician can do is identify which phase you are in, because that phase, more than the appearance, decides which treatments are still on the table.
What is the most common foot deformity?
Ask a room of orthopedic and podiatric clinicians which deformity fills their clinic lists and most will say the bunion, known medically as hallux valgus, a term meaning the big toe angling outward toward the smaller toes. Mayo Clinic describes it as a bony bump at the base of the big toe that forms when the first metatarsal, the long bone behind the toe, drifts inward while the toe itself leans the opposite way. The result is a widening of the forefoot and a joint that no longer sits under its intended load.

Bunions are common enough that many people assume they are simply a consequence of pointed shoes. The evidence is more nuanced. NHS guidance notes that bunions often run in families, and that the inherited factor is foot shape and joint laxity rather than the bump itself. Tight, narrow footwear can accelerate the drift and make an existing bunion painful, but plenty of people who never wear heels develop one, and some lifelong heel-wearers never do.
Close behind bunions in frequency come hammertoe and its cousins, mallet toe and claw toe, all of which involve a lesser toe bending at one or more joints. Adult acquired flatfoot, the gradual collapse of the arch in adulthood, is less common but more disabling when it advances. Charcot foot, a neuropathic collapse of the midfoot, is rare in the general population but a serious concern for people with long-standing diabetes.
Why does frequency matter to you? Because the most common deformities are also the best studied, which means their staging systems are mature and the natural history is reasonably well described. When a clinician tells you a bunion is “mild” or a flatfoot is “stage two,” that label carries decades of accumulated observation behind it.
How do bunions progress over time?
A bunion rarely announces itself. The earliest change is often invisible: the ligament that anchors the first metatarsal to its neighbor loosens, and the bone begins to splay. Only later does the big toe start to lean, and only later still does the joint capsule on the inner side stretch enough to form the visible bump. Mayo Clinic lists the drift of the toe toward the others, thickened skin over the joint and reduced movement as features that develop over time rather than all at once.
Once the toe leans, the tendons that should pull it straight begin to pull it sideways instead, because their line of action has shifted. Imagine trying to close a door by pulling a rope attached near the hinge rather than the handle. Every step nudges the toe a little further. In moderate bunions the big toe may start to underlap or overlap the second toe, and the second toe, crowded and unsupported, frequently develops a hammertoe of its own.
Later still, the joint surfaces wear unevenly. The cartilage on the outer side of the big toe joint takes load it was never designed for, and arthritis can follow. At this point the deformity is usually rigid: pushing the toe straight by hand no longer works, and shoe changes relieve pressure on the bump but cannot change the angle.
Two honest caveats. First, the size of the bump does not reliably predict pain; small bunions can hurt and large ones can be quiet for years. Second, NHS guidance is clear that non-surgical measures do not reverse the bony change; they aim to slow the process, ease symptoms and protect the neighboring toes. That distinction between managing and reversing runs through every deformity in this article.
What are the stages of flatfoot deformity in adults?
Adult acquired flatfoot is the clearest example of how a single failing structure can reshape an entire foot. The structure in question is the posterior tibial tendon, which runs behind the inner ankle bone and acts as the main dynamic support for the arch. When it becomes inflamed, stretched or torn, the arch loses its principal cable. Johns Hopkins Medicine describes this condition as posterior tibial tendon dysfunction and outlines a four-stage progression that most orthopedic teams use in some form.
In stage one, the tendon is inflamed but still functioning. There may be pain and swelling along the inner ankle, yet the arch holds its shape and the person can still rise onto the toes of one foot. In stage two, the tendon has lengthened or partially torn, and the arch begins to flatten; the deformity is flexible, meaning the arch reappears when the foot is off the ground, but the heel tilts outward under weight and rising onto one set of toes becomes difficult. Stage three marks the shift to rigidity: the joints of the hindfoot have adapted to the collapsed position and the arch no longer returns even without load. Stage four adds the ankle joint itself, which tilts because the foot beneath it has been sitting crooked for so long.
The staging matters because treatment options narrow at each step. Stages one and two respond to supportive measures and, if surgery is needed, to procedures that preserve the joints. Stage three and four typically require procedures that fuse, or permanently join, some hindfoot joints to restore alignment. Johns Hopkins notes that early recognition is the single biggest lever, because a flexible deformity leaves far more choices open than a rigid one.
Hammertoe and lesser-toe deformities: from flexible to fixed
The lesser toes are small, but their deformities follow the same logic as the big ones. A hammertoe bends downward at the middle joint of a toe; a mallet toe bends at the joint nearest the nail; a claw toe bends at both while the base joint hyperextends. Mayo Clinic explains that these shapes arise from an imbalance between the muscles and tendons that flex and extend the toe, and that the imbalance can come from footwear that crowds the toes, from a bunion pushing the second toe out of line, from arthritis, or from nerve conditions that weaken the small foot muscles.
Early on, a hammertoe is flexible. You can straighten it with a finger, and it may only bother you in closed shoes. Corns form over the knuckle where it rubs the shoe, and a callus may build under the ball of the foot because the bent toe no longer shares the load. Over months to years the joint capsule contracts, the tendons shorten to match the bent position, and the toe becomes rigid. Mayo Clinic notes this transition from flexible to fixed as the key turning point for treatment.
Nerve-related deformities deserve a separate mention. In inherited neuropathies, and in diabetic nerve damage, the small muscles that stabilize the toes weaken before the larger leg muscles do. The long tendons from the calf then act unopposed, curling the toes into claws and often raising the arch into a high, cavus shape. Progression here tracks the underlying nerve condition, which is why the orthopedic plan for these patients is built alongside a neurologist or diabetes team rather than in isolation.
Flexible lesser-toe deformities respond to padding, toe spacers, footwear with a deep toe box and stretching. Rigid ones generally do not, and that is where surgical discussion begins.
Charcot foot: when a deformity forms without warning pain
Every other deformity in this article progresses with pain as a signal. Charcot foot is different, and that difference is what makes it dangerous. Cleveland Clinic describes it as a condition in which the bones and joints of the foot weaken and can fracture or dislocate, most often in people with peripheral neuropathy from diabetes, the nerve damage that blunts or removes protective sensation. Because the person cannot feel the injury, they keep walking on a foot that is quietly breaking.
Clinicians stage Charcot foot in three phases. The active or fragmentation phase shows a hot, red, swollen foot, often mistaken for infection or a sprain, while bone is breaking down inside. The coalescence phase follows as the acute inflammation settles and the fragments begin to knit. The consolidation phase leaves the bones healed, but in whatever position they collapsed into. The classic result is the rocker-bottom foot, in which the midfoot drops below the level of the heel and toes, creating a pressure point that ulcerates easily.
The treatment principle is protection during the active phase, which usually means keeping weight off the foot in a cast or specialized boot for weeks to months while the bone stabilizes, followed by lifelong protective footwear. Cleveland Clinic emphasizes that early diagnosis, before collapse, is what preserves a walkable foot. Reconstruction surgery exists for unstable or ulcer-prone deformities, but it is complex, and the team weighs it against the person’s circulation, glucose control and overall health.
If you have diabetes and neuropathy, MedlinePlus advises checking your feet daily and treating a warm, swollen foot as urgent even when it does not hurt. Waiting for pain is exactly the mistake this condition exploits.
How orthopedic treatment is planned: what happens at the first appointment
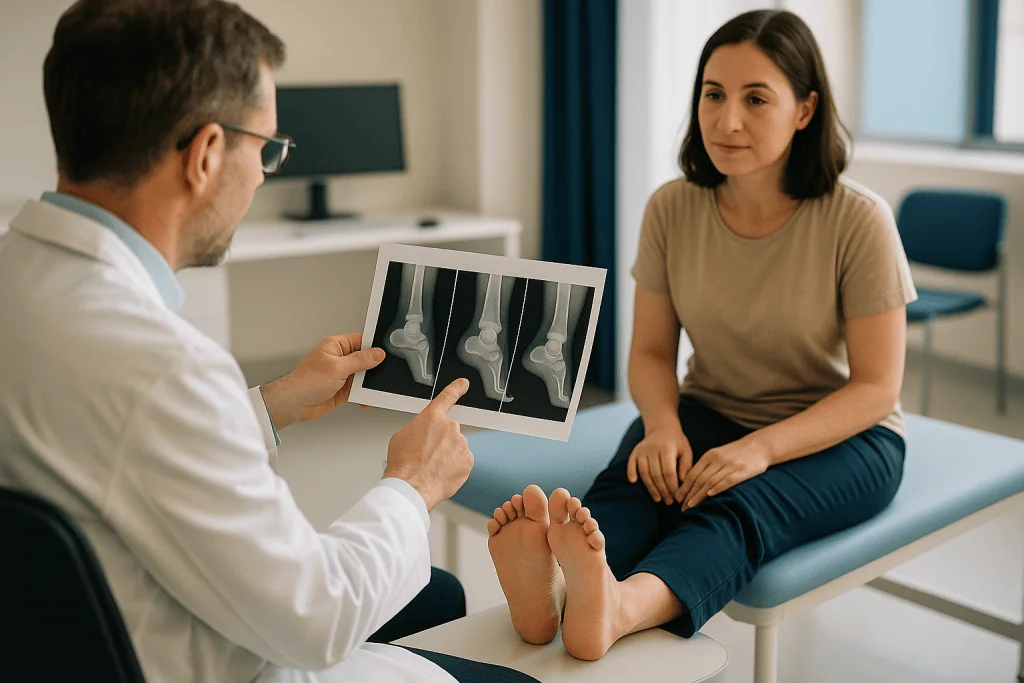
Planning begins with watching you stand and walk, because a deformity photographed sitting down can look entirely different under load. The clinician will observe the foot from behind to see whether the heel tilts and how many toes are visible on the outer side, a rough marker of arch collapse. They will ask you to rise onto your toes, first on both feet and then on one, which tests the posterior tibial tendon directly. They will handle each toe and joint to sort flexible from rigid, and press along tendons and joint lines to locate the true source of pain, which is not always the most obvious bump.
Imaging follows, and the detail that matters is that X-rays for deformity planning are taken standing. A non-weight-bearing image underestimates almost every angle clinicians care about. From standing films the team measures the angle between the first and second metatarsals and the angle of the big toe for bunions, the alignment of the talus and first metatarsal for flatfoot, and the joint spaces for arthritis. MRI or ultrasound may be added when the state of a tendon, rather than a bone angle, will decide the plan. CT scans are sometimes used to map complex hindfoot or Charcot deformities before surgery.
The team then places you on a stage and asks three questions. Is the deformity flexible or rigid? Is the pain coming from the deformity itself, from a secondary problem such as a callus or crowded toe, or from arthritis? And what is the trajectory, given your age, activity, weight, nerve function and any inflammatory disease?
Only after those answers does the conversation turn to options, and the first option discussed is almost always the least invasive one that fits your stage.
How foot deformities progress: a stage-by-stage summary
The table below draws together the staging language used across the common deformities. It is a map, not a diagnosis; where you sit on it is for your treating team to decide after examination and standing X-rays.
| Deformity | Early stage | Advanced stage | Typical planning emphasis |
|---|---|---|---|
| Bunion (hallux valgus) | Metatarsal splays; toe leans but can be straightened by hand; bump small, often painless | Toe overlaps or underlaps second toe; joint rigid; arthritis may develop | Wide footwear, padding, spacers first; surgical realignment considered for persistent pain or crowding of neighboring toes |
| Adult acquired flatfoot | Inner ankle pain and swelling; arch intact or flexibly flattened; single-leg toe rise difficult | Rigid collapsed arch; heel fixed in outward tilt; ankle may tilt (stage four) | Orthoses, bracing, physiotherapy early; joint-preserving surgery for flexible stages, fusion for rigid stages |
| Hammertoe and claw toe | Toe bends but straightens with a finger; corn over knuckle | Joint fixed; callus under forefoot; toe may dislocate at base | Deep toe box, padding, stretching; tendon release or joint procedures once rigid and painful |
| Charcot foot | Hot, red, swollen foot with little or no pain; bone fragmenting on imaging | Rocker-bottom midfoot; pressure ulcer risk | Strict offloading in cast or boot during active phase; lifelong protective footwear; reconstruction for unstable or ulcerating feet |
Two patterns jump out. Early stages across every row are managed with the same family of measures: reduce load, correct alignment externally, keep tissues moving. Advanced stages across every row shift the conversation toward bone. That is not because surgeons prefer operating; it is because rigid bone no longer responds to a shoe insert. The practical lesson is that the window for the simplest treatments is earliest, which is exactly when the deformity hurts least and is easiest to ignore.
Who is usually offered surgery, and who is asked to wait
People are often surprised to learn that appearance alone rarely qualifies someone for deformity surgery. NHS guidance on bunions states plainly that surgery is usually considered only when pain or difficulty walking persists despite non-surgical measures, not to improve how the foot looks. The same principle applies across flatfoot, hammertoe and most other deformities: the surgeon is treating function and pain, and the shape change is a means to that end.
Candidates who are typically offered surgery share a few features. Their pain limits daily activity or work. They have genuinely tried footwear changes, padding, orthoses or bracing for a reasonable period. Their deformity is causing secondary damage, such as a second toe being pushed out of joint, a recurrent ulcer over a pressure point, or an ankle beginning to tilt. And their overall health, circulation and bone quality make healing likely.
Those usually asked to wait, or steered away from surgery, include people whose deformity is painless, since operating on a quiet foot trades certain recovery for uncertain benefit. Adolescents with bunions are often asked to wait until growth is complete, because bones still growing can shift again. People with uncontrolled diabetes, poor circulation, active smoking or unhealed skin over the surgical site are usually asked to address those factors first, because they raise the risk of infection and slow bone healing. Someone in the active phase of Charcot foot is protected in a cast rather than operated on, since bone that is still fragmenting will not hold fixation.
Age by itself is not a barrier. A fit person in their seventies with a painful rigid bunion may be a better candidate than a younger person with a mild, flexible one. The decision sits with the treating team, built from your specific stage, your goals and your health.
What nonsurgical treatment can and cannot do
The most useful thing to understand about conservative care is its honest scope. Mayo Clinic and NHS guidance agree that footwear, padding, orthoses and physiotherapy do not straighten a bunion or rebuild a collapsed arch. What they can do is reduce pain, slow progression by lowering the forces that drive it, protect neighboring structures and, for many people, make surgery unnecessary for years or for life.
Footwear is the first lever. Shoes with a wide, deep toe box remove pressure from the bunion bump and the hammertoe knuckle, and a firm heel counter with a modest heel height steadies the hindfoot. Orthoses, the shaped inserts placed inside shoes, support the arch in flexible flatfoot and shift load away from painful areas. For advanced flatfoot, a more rigid ankle brace may be used to hold the heel upright. Toe spacers and silicone sleeves address crowding and friction, and padding over corns reduces skin breakdown.
Physiotherapy targets the muscles that can still help. In early flatfoot, strengthening the posterior tibial tendon and calf while stretching a tight Achilles can meaningfully reduce symptoms. For flexible hammertoes, stretching the contracted tendons and strengthening the small intrinsic muscles helps maintain flexibility.
Medicines have a supporting role. Anti-inflammatory drugs, used as directed by a prescriber, can settle pain and swelling in a flared joint or tendon, though they do not alter the deformity. Corticosteroid injections are sometimes used for inflamed joints, but many surgeons avoid injecting a strained tendon because of concern about weakening it further. Any decision to start, continue or stop a medicine belongs with the prescribing clinician.
Where conservative care most clearly wins is Charcot foot, in which strict offloading during the active phase is the treatment, not a placeholder before surgery.
What the days and weeks after corrective foot surgery usually look like
Recovery from deformity surgery is measured in bone-healing time, which is why it is slower than most people expect. The exact course depends on the procedure, but a broad pattern holds.
The first two weeks focus on elevation, wound care and pain control. Swelling is the enemy of healing skin, so surgeons ask patients to keep the foot raised above heart level for much of the day. Most bunion and hammertoe procedures allow walking in a stiff-soled surgical shoe from early on, bearing weight through the heel. Flatfoot reconstructions and any procedure involving fusion typically require no weight on the foot at all, in a cast or boot, because the bones are held by screws or plates that must not be stressed until healing begins.
From roughly week two to week six, stitches come out, and X-rays check that the corrected position is holding. NHS guidance on bunion surgery describes several weeks in a special shoe before ordinary footwear is possible, and notes that swelling often persists for months. Physiotherapy usually starts in this window to restore joint movement and retrain walking.
Between six weeks and three months, bone is uniting and load is gradually increased. Fusions take longer; hindfoot fusions may need three months or more before full weight-bearing without protection. Driving, returning to standing work and resuming sport are cleared by the team based on healing on imaging, not on a fixed calendar.
Full settling takes longer than function returns. NHS guidance suggests it can take many months for a foot to feel fully normal after bunion surgery, and some residual stiffness or swelling can be permanent. Your team will give ranges for your specific operation; treat them as typical, not promised.
Can foot deformity be corrected?
The direct answer is yes for many deformities, with important qualifications about what “corrected” means and who benefits. Surgical procedures exist that realign the bones of a bunion, reposition a collapsed hindfoot and straighten a rigid hammertoe. What no procedure can do is restore a foot to the one you had at twenty, and the goal your surgeon writes in your notes will be a functional, pain-reduced, shoe-fitting foot rather than an aesthetic ideal.
For bunions, surgery typically involves cutting and shifting the first metatarsal, a procedure called an osteotomy, then fixing it with small screws, often combined with tightening the stretched joint capsule. In severe or arthritic cases, fusing the big toe joint or the joint at the base of the metatarsal may be preferred for durability. Mayo Clinic notes that many surgical techniques exist and that the choice depends on the severity and the surgeon’s assessment. Recurrence is possible, particularly if the underlying foot shape and footwear habits persist.
For flatfoot, flexible stages are addressed by transferring a healthy tendon to take over for the failed one and reshaping the heel bone with an osteotomy to restore alignment. Rigid stages usually require fusing hindfoot joints; the foot becomes stable and better aligned, but it loses some side-to-side motion permanently.
For hammertoes, a flexible deformity may be corrected by releasing or transferring a tendon, while a rigid one usually requires removing a small piece of bone at the bent joint and holding the toe straight with a pin or implant while it heals.
Every one of these procedures carries risks: infection, nerve irritation and numbness, stiffness, delayed bone healing, hardware irritation and recurrence. The honest framing is that correction is available, imperfect and worth it for the right person at the right stage, as judged by their treating team.
What people often get wrong about how foot deformities progress
“If it does not hurt, nothing is happening.” Pain is a late signal for most deformities and an absent one in Charcot foot. A bunion or flatfoot can drift for years in silence, and the flexible window closes without any change in how the foot feels. Clinicians stage deformities by alignment and joint mobility, not by discomfort.
Which leads to a related myth: “Surgery should wait until it is really bad.” There is truth in not operating on a painless foot, but rigidity, not size, is what removes options. A moderate bunion causing daily pain in someone who has exhausted footwear changes may be a more sensible surgical candidate than a large one that only aches occasionally.
“Insoles will pull the arch back up.” Orthoses support and offload; they do not reshape bone or repair a torn tendon. Their value lies in comfort and in slowing the forces that drive collapse, which is worthwhile, but expecting reversal leads to disappointment and sometimes to abandoning a treatment that was quietly working.
“Bunions are caused by high heels, full stop.” NHS guidance points to inherited foot shape as the main driver, with footwear as an accelerator. This matters because people who never wore heels sometimes assume their bump must be something else and delay assessment.
“Once corrected, it stays corrected.” Recurrence after bunion and hammertoe surgery is well described, especially when the original mechanical causes persist. Protective footwear and, where relevant, orthoses remain part of life after surgery.
“Flat feet in children are the same problem as flatfoot in adults.” Most children have flexible flat feet that develop an arch as they grow; adult acquired flatfoot is a tendon failure in a foot that once had an arch. Different mechanism, different plan.
Questions to ask your care team
A good consultation leaves you knowing not just what you have, but where it is heading and what would change the plan. These questions tend to draw out the answers that matter.
- Which stage is my deformity in, and is it still flexible or has it become rigid?
- What is driving the progression in my case: foot shape, a tendon problem, arthritis, nerve function, footwear, or a combination?
- Which of my symptoms come from the deformity itself, and which from secondary problems such as calluses, crowded toes or an irritated tendon?
- What non-surgical measures are worth trying first, for how long, and how will we judge whether they are working?
- What signs would tell us that the deformity is advancing to the next stage, and how often should we recheck with standing X-rays?
- If surgery is eventually discussed, which type of procedure fits my stage, and what would that mean for joint movement afterward?
- What are the specific risks for someone with my health history, including healing, infection, numbness and recurrence?
- What would the recovery look like in weeks and months, including time off my feet, time away from work and driving, and when I could expect swelling to settle?
- How should I manage my footwear, weight and activity now to slow progression, regardless of whether I have surgery?
- Who do I contact between appointments if something changes, and what changes should prompt a call?
Bring a pair of your usual shoes to the appointment, and, if you have them, any older photographs of your feet. Wear patterns and past images give the team a sense of trajectory that no single X-ray can. Write the answers down; recovery timelines and staging language are easy to misremember once you leave the room.
When to call your doctor
Most foot deformities progress slowly and can be reviewed at routine appointments. Some changes, however, need prompt attention, because they signal either a rapid shift in the deformity or a complication that will worsen with delay.
Seek same-day advice if a foot becomes hot, red and swollen without an obvious injury, particularly if you have diabetes or known nerve damage; Cleveland Clinic and MedlinePlus both flag this as a possible active Charcot process or infection, and the absence of pain does not make it less urgent. Call promptly if any area of skin over a bunion, hammertoe or the sole breaks down, blisters, weeps or shows an open sore that is not healing, since pressure ulcers on a deformed foot can deepen quickly.
Contact your team if a toe or the whole foot suddenly changes shape, if you can no longer rise onto your toes on one side when you previously could, or if pain escalates over days rather than months. These can indicate a tendon tear or a joint dislocation rather than gradual drift.
After surgery, red flags include increasing rather than decreasing pain after the first few days, fever, spreading redness or warmth around the wound, discharge or a bad smell from the dressing, numbness or color change in the toes, calf pain or swelling in either leg, chest pain or breathlessness. The last three can signal a blood clot and require emergency assessment.
Finally, if you have diabetes, MedlinePlus advises reporting any new foot problem, however minor it seems, rather than watching it. Your treating team knows your stage and your history; they would rather hear from you early than manage a complication late.
Frequently asked questions
Can a foot deformity be corrected without surgery?
Not in the sense of restoring bone alignment. Footwear changes, orthoses, padding and physiotherapy reduce pain, protect skin and slow progression, and for many people that is enough for years. They do not straighten a bunion or rebuild a collapsed arch. Flexible deformities respond best to these measures; rigid ones generally need surgical realignment if they become painful.
What are the different stages of flatfoot deformity in adults?
Johns Hopkins describes four stages of posterior tibial tendon dysfunction. Stage one is tendon inflammation with a preserved arch; stage two is a flexible flattened arch with a tilted heel; stage three is a rigid collapsed arch; stage four adds tilting of the ankle joint. Treatment options narrow as the stages advance, which is why early assessment matters.
What is the most common foot deformity?
The bunion, or hallux valgus, is the most common foot deformity seen in orthopedic and podiatric practice. It develops when the first metatarsal drifts inward and the big toe angles toward the smaller toes. Hammertoe and related lesser-toe deformities are the next most frequent, and the two often occur together because a leaning big toe crowds its neighbor.
What does a deformed foot look like to a clinician?
Clinicians look at alignment under load rather than appearance at rest. They note whether the heel tilts outward when you stand, how the arch behaves when you rise onto your toes, whether toes overlap or bend at fixed angles, and where calluses have formed, since callus marks abnormal pressure. Standing X-rays then confirm the angles seen on examination.
How fast does adult acquired flatfoot progression happen?
There is no fixed timetable. Some people remain in the flexible stage for many years with supportive footwear and bracing, while others progress to a rigid deformity within a few years, particularly if the tendon has torn or if body weight, arthritis or inflammatory disease add load. Regular review with standing X-rays is how your team tracks the pace.
Do bunions always get worse over time?
Most bunions progress slowly if the driving forces continue, but the rate varies widely and some remain stable and painless for decades. Wider footwear, padding and toe spacers reduce the pressure that accelerates drift. Mayo Clinic notes that bunions are permanent unless surgically corrected, so the realistic goal of conservative care is slowing change and controlling symptoms.
Is Charcot foot the same as a diabetic foot ulcer?
No, though they are linked. Charcot foot is a collapse of bones and joints in a foot with nerve damage; an ulcer is a break in the skin. The rocker-bottom shape left by Charcot foot creates pressure points that ulcerate easily, so the two often occur in the same person. Both require prompt assessment, and Cleveland Clinic stresses early offloading for Charcot.
How long is recovery after bunion surgery?
NHS guidance describes several weeks in a special surgical shoe before returning to ordinary footwear, with swelling that can persist for months and full recovery that may take many months. Bone healing on X-ray, not the calendar, determines when your team clears driving, standing work and sport. Fusion procedures generally take longer than realignment osteotomies.
Will a hammertoe straighten on its own?
A flexible hammertoe will not straighten spontaneously, but it can be kept flexible and comfortable with a deep toe box, padding, toe stretching and treatment of any bunion that is crowding it. Once the joint becomes rigid, the toe stays bent unless a surgical procedure releases the tendon or removes a small piece of bone at the fixed joint.
Should children with flat feet be treated to prevent adult deformity?
Usually not. Most children have flexible flat feet that form an arch as they grow, and NHS guidance notes treatment is rarely needed unless there is pain, stiffness or a rigid arch. Adult acquired flatfoot is a different condition caused by tendon failure in a foot that previously had an arch. A pediatric clinician should assess any painful or rigid flat foot in a child.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

When Does Trigger Finger Need Surgery? Splints, Injections and the Point of Release
Trigger finger usually needs surgery only when a finger locks and cannot be straightened, when night splinting and one or two corticosteroid injections have…

Nerve Pain: How It Differs From Other Pain and the Treatments That Target It
Nerve pain, also called neuropathic pain, comes from damage or malfunction in the nerves themselves rather than from injured tissue, which is why it…

NHS Hip Replacement Waiting Times: What They Mean and What You Can Do
In England, the NHS aims to start hip replacement treatment within 18 weeks of GP referral, but many patients currently wait longer, often several…

How Arthritis Wears a Joint Down: When Damage Reaches the Point Where Replacement Is Discussed
Arthritis wears a joint down by thinning the cartilage that cushions the bone ends, roughening the bone beneath, and inflaming the joint lining, until…

How X-Rays and CT Scans Guide Trauma Surgery Decisions After a Serious Injury
After a serious injury, X-rays and CT scans give trauma surgeons a map of what is broken, bleeding or displaced before anyone decides to…

Preparing for Hand Surgery: Nerve Tests, Imaging and the Medicines Your Team Reviews
To prepare for hand surgery, most people complete nerve tests such as a nerve conduction study or EMG, imaging such as X-ray, ultrasound or…