

How Hemolytic Uremic Syndrome Is Treated in Hospital: Fluids, Transfusion and Dialysis Support

Key Takeaways
- According to the CDC, about 5 to 10 percent of people diagnosed with Shiga toxin-producing E. coli infection develop HUS, usually around seven days after symptoms begin and often as diarrhea is improving.
- Typical HUS has no drug that shortens it; treatment is supportive, built on measured intravenous fluids, blood count and kidney monitoring, red cell transfusion when needed, blood pressure control and temporary dialysis.
- Platelet transfusions are generally reserved for active bleeding or procedures, because the clots forming in small vessels consume platelets and more may feed the process.
- Antibiotics and antidiarrheal medicines are generally avoided in E. coli-related HUS because killing the bacteria or slowing the gut can increase Shiga toxin exposure.
- Atypical HUS is caused by uncontrolled complement activity, often from inherited gene changes plus a trigger, is diagnosed largely by excluding STEC infection and TTP, and may be treated with complement-blocking antibodies.
- Kidney follow-up continues for years after HUS because high blood pressure and protein in the urine can emerge long after apparent recovery.
Hemolytic uremic syndrome is treated in hospital with supportive care rather than a single drug: carefully balanced intravenous fluids, close monitoring of kidney function and blood counts, red blood cell transfusion when anemia becomes severe, blood pressure control, and temporary dialysis if the kidneys cannot clear waste or fluid. Antibiotics and antidiarrheal medicines are generally avoided in E. coli-related HUS. Atypical HUS may also be treated with complement-blocking therapy.
On a pediatric ward, a father sits beside a bed watching two things at once: his four-year-old’s face, pale in a way he has never seen before, and the small bag hanging from the bed rail that should be filling with urine but barely is. A week ago this was a stomach bug with bloody diarrhea. Now a nurse is writing down every milliliter that goes in and every milliliter that comes out, and someone has said the word dialysis.
That scene is where most families first hear about hemolytic uremic syndrome treatment, and it is a strange kind of medicine to watch. There is no antidote, no single infusion that fixes the problem. Instead, the team keeps the body stable while damaged blood vessels heal on their own timetable: fluids in measured amounts, blood when it is truly needed, a machine to stand in for the kidneys if they stop.
This explainer walks through what each of those decisions means, what the evidence supports, and where honest uncertainty remains.
What does hemolytic uremic syndrome treatment actually involve?
Hemolytic uremic syndrome, usually shortened to HUS, is a condition in which red blood cells are destroyed, platelets fall, and the kidneys are injured, most often after an intestinal infection with a toxin-producing strain of E. coli. The kidney damage is why nearly everyone with HUS is admitted to hospital, according to Mayo Clinic, and why the treatment plan is built around supporting organs rather than attacking a germ.
The core of hemolytic uremic syndrome treatment is supportive care. That phrase can sound passive, but on the ward it means a dense schedule of measurement and adjustment. Blood is drawn once or more each day to track hemoglobin (the oxygen-carrying protein in red cells), platelet count, creatinine (a waste product the kidneys should clear) and electrolytes such as potassium. Weight is checked, sometimes twice daily, because in a child with failing kidneys a gain of a few hundred grams can signal fluid building up in the body. Blood pressure is measured frequently.
From those numbers come the four main interventions this article covers: intravenous fluids given in carefully judged amounts, transfusion of red blood cells when anemia becomes severe, medicines to control high blood pressure, and dialysis, a treatment that filters waste and excess fluid from the blood when the kidneys cannot. MedlinePlus lists exactly these pillars, along with nutrition support when a child cannot eat normally.
What the plan does not usually include for the typical E. coli form are antibiotics, antidiarrheal drugs, or platelet transfusions, for reasons explained below. Atypical HUS, a rarer form driven by the body’s own immune chemistry, adds a different class of medicine. Every one of these choices is made by the treating team in response to the numbers in front of them, and they change day to day.
What is happening inside the body during HUS?
To understand why fluids, blood and kidneys all need attention at once, it helps to follow the toxin. Certain strains of E. coli, most notoriously O157:H7, produce Shiga toxin, a protein that is absorbed from the inflamed gut into the bloodstream. According to the CDC, symptoms of the infection itself usually begin three to four days after exposure, and HUS, when it develops, tends to appear about seven days after the first symptoms, often just as the diarrhea is improving. That timing catches families off guard: the child seems to be getting better, then turns pale and stops urinating.

Shiga toxin binds to the lining cells of small blood vessels, called the endothelium, and the kidney’s filtering units are unusually rich in the receptor it uses. The injured lining triggers tiny clots. Platelets, the cell fragments that plug leaks, are consumed forming those clots, so the platelet count drops. Red blood cells squeezing through the narrowed, clot-lined vessels are torn apart, which is the hemolysis in the name. Fragments of broken cells appear on a blood smear, and hemoglobin released from the ruptured cells is part of what makes the urine dark.
The kidney is hit hardest because its filters are clogged and starved of blood flow. Creatinine climbs, potassium may rise to dangerous levels, and fluid the kidneys would normally remove stays in the body. The same process can occur, less often, in the brain, pancreas, heart and bowel, which is why Mayo Clinic lists seizures, stroke and heart problems among possible complications.
None of this can be reversed by a drug. What treatment does is prevent the secondary harms, dehydration, dangerous chemistry, fluid overload and severe anemia, while the vessel lining repairs itself over days to weeks.
Why IV fluids are the first move, and why the amount is watched so closely
Fluid is the first and most constant part of hemolytic uremic syndrome treatment, and also the one that requires the finest judgment. A child who has had days of vomiting and diarrhea arrives depleted. Dehydration lowers blood flow to already struggling kidneys, and Mayo Clinic notes that fluid and electrolyte replacement is a foundation of HUS care.
The complication is that HUS kidneys may be losing the ability to get rid of water. Give too little, and the kidneys are deprived of the perfusion they need. Give too much once urine output has fallen, and fluid backs up into the lungs and tissues, raising blood pressure and making breathing harder. This is why the team is so fixated on the numbers on the whiteboard: every drink, every intravenous bag, every wet diaper or bedpan is tallied. Daily weights act as a check on the ledger.
In practice, fluids are usually given intravenously through a small cannula in the hand or arm, using a balanced salt solution rather than plain water, because sodium helps keep the fluid inside blood vessels where it supports circulation. Potassium is often left out of the bags at first, since failing kidneys cannot excrete it and high levels can disturb heart rhythm.
Clinicians also watch for signs that fluid is the wrong lever. If a child has stopped urinating and is gaining weight, the response is typically to restrict intake rather than push more, and to prepare for dialysis. Blood pressure medicines from standard classes, such as calcium channel blockers, may be added when the pressure climbs; the choice, timing and adjustments belong to the prescribing clinician.
Families sometimes ask whether they should encourage more drinking. On the ward, the honest answer is: only as much as the team has written down that day.
When does someone with HUS need a blood transfusion, and why are platelets handled differently?
Hemolysis can drop hemoglobin fast. Red blood cell transfusion, meaning donated red cells given through a vein, is used when anemia becomes severe enough to compromise oxygen delivery or when a child shows signs of strain such as a racing heart, breathlessness or lethargy. Both MedlinePlus and Mayo Clinic list red cell transfusion among standard treatments for HUS.
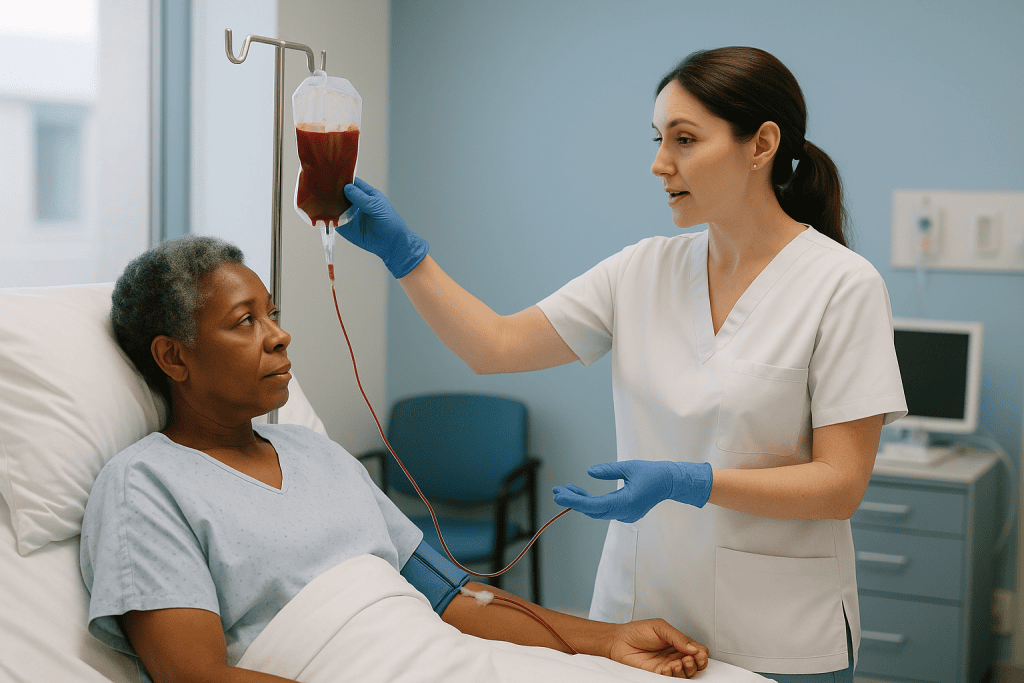
The transfusion itself is routine hospital medicine. Blood is matched to the patient’s type, the bag runs over a few hours through the existing cannula, and the child is monitored for fever or allergic reaction during the infusion. Because the underlying destruction continues for a while, a single transfusion may not be the last; the team checks hemoglobin afterward and again over the following days.
Platelets are a different story, and this surprises many parents. A very low platelet count sounds like something to correct, yet platelet transfusions are generally reserved for active bleeding or for an invasive procedure such as placing a dialysis catheter. The reasoning follows from the disease mechanism: the clots forming in small vessels are consuming platelets, and supplying more may simply feed that process. Mayo Clinic describes platelet transfusion as an option when bleeding is a problem, not as a routine measure.
What does a transfusion feel like from the bedside? Usually anticlimactic. The color returns to a child’s cheeks over a day, and energy picks up. Parents often describe it as the first moment they saw their child look like themselves again. It does not, however, treat the kidney injury, and a rising hemoglobin should not be read as a sign that the kidneys have recovered. Those two problems run on separate clocks.
HUS dialysis in children and adults: who needs it and what actually happens
Dialysis is a treatment in which a machine, or the lining of the abdomen, takes over the kidney’s job of removing waste products and excess water from the blood. According to NIDDK, HUS is among the most common causes of acute kidney injury in children, and dialysis is used when the kidneys can no longer keep the body’s chemistry safe.
The decision is not made on a single lab value. Teams typically look for a combination: very low or absent urine output, rising potassium that does not respond to medicines, fluid overload causing high blood pressure or breathing difficulty, or waste levels high enough to cause confusion or nausea. Any one of these can tip the balance.
Two forms are used. Peritoneal dialysis places a soft catheter into the abdomen; a special fluid is cycled in and out, drawing waste across the abdominal lining. It is gentle and often favored in young children. Hemodialysis pumps blood through an external filter via a larger catheter, usually placed in a neck or groin vein under sedation or anesthesia, and returns it cleaned. Sessions may run several hours and are repeated as needed, sometimes daily at first.
Dialysis in HUS is meant to be temporary. It is a bridge, holding the body steady until the kidneys resume filtering. Teams watch for the first signs of recovery, often a rise in urine output before creatinine begins to fall, and space out or stop sessions as the kidneys take back the work.
Adults with HUS, who more often have the atypical form or a secondary trigger, follow the same principles. Hemodialysis is more common in adults simply because vascular access is easier. In every case the choice of method, timing and duration sits with the nephrology team.
Why antibiotics and antidiarrheal medicines are usually avoided in E. coli HUS
One of the counterintuitive parts of hemolytic uremic syndrome treatment is what clinicians withhold. A bloody diarrheal illness looks like exactly the situation antibiotics were made for. Yet the CDC advises that antibiotics are not generally recommended for infections with Shiga toxin-producing E. coli, and that antidiarrheal medicines should also be avoided.
The concern with antibiotics is mechanistic. When certain antibiotics kill these bacteria, the dying cells can release a surge of Shiga toxin into the gut, and some antibiotic classes may also switch on the genes that produce it. Observational evidence suggests that children treated with antibiotics during the diarrheal phase may be more likely to progress to HUS. The data are not uniform across all antibiotic classes, and this remains an area where researchers argue about details; what mainstream guidance agrees on is that routine antibiotic use is not supported. If a child has a separate bacterial infection, the treating team weighs that individually.
Antidiarrheal drugs that slow gut movement are avoided for a related reason: keeping toxin-laden stool in the bowel longer may increase absorption of the toxin. They can also mask worsening illness.
Nonsteroidal anti-inflammatory painkillers are usually set aside as well, because they reduce blood flow to the kidney at the very moment it is most vulnerable. Fever and discomfort are managed with alternatives chosen by the team.
For families this often means the hardest kind of instruction: do less. No pharmacy remedies from home, no leftover antibiotics from a previous illness. Bringing a list of anything already given before admission helps the team enormously.
What causes aHUS, and how is atypical hemolytic uremic syndrome diagnosed?
Atypical hemolytic uremic syndrome, or aHUS, produces the same triad of hemolysis, low platelets and kidney injury, but without Shiga toxin. Its cause lies in the complement system, a set of blood proteins that normally help destroy invading microbes. In aHUS, the brakes on that system fail. Mayo Clinic and NIDDK describe inherited changes in genes that regulate complement, such as those coding for factor H, factor I, membrane cofactor protein, C3 and factor B, as well as antibodies the body makes against its own factor H. With the regulators disabled, complement attacks the body’s own vessel lining, and the same clotting cascade follows.
Genetic susceptibility alone is often not enough. A trigger frequently precedes the first episode: a viral or bacterial infection, pregnancy or the weeks after delivery, certain medicines, an organ transplant, or another autoimmune condition. This is why aHUS can appear at any age, in adults as readily as in children, and can recur.
Diagnosis is largely a process of exclusion, because no single test proves aHUS quickly. Clinicians confirm the triad with blood counts, a smear showing fragmented red cells, kidney function tests and markers of hemolysis. They then test stool for Shiga toxin or the bacteria that make it; a negative result, especially without preceding bloody diarrhea, points away from typical HUS. Next they measure ADAMTS13 activity, an enzyme whose severe deficiency defines thrombotic thrombocytopenic purpura (TTP), a look-alike disorder treated differently. Normal ADAMTS13 with negative STEC testing and no other secondary cause supports aHUS. Complement levels, anti-factor H antibodies and genetic panels are sent, though genetic results can take weeks and treatment decisions rarely wait for them.
What is the first-line treatment for hemolytic uremic syndrome? Typical versus atypical
Ask what the first-line treatment for HUS is and the honest answer depends on which HUS. For the typical E. coli-related form, first-line care is the supportive package already described: fluids, monitoring, transfusion when needed, blood pressure control and dialysis if required. No medicine has been shown to shorten the disease itself, and Mayo Clinic frames the goal as easing symptoms and preventing further problems while the body recovers.
For aHUS the picture changed with the arrival of complement inhibitors, monoclonal antibodies that block the complement protein C5 and interrupt the attack on vessel lining. Eculizumab is the generic name most often described. Before these medicines were available, plasma exchange, a procedure that removes a patient’s plasma and replaces it with donor plasma, was the main approach, on the logic that it might supply missing regulators or remove harmful antibodies. Mayo Clinic notes plasma exchange may still be used in some situations. Because blocking complement raises the risk of meningococcal infection, patients are vaccinated and monitored; the decision to start, continue or stop this therapy rests with a specialist nephrologist or hematologist and depends on genetics, response and recurrence risk.
| Feature | Typical (STEC) HUS | Atypical HUS | TTP (look-alike) |
|---|---|---|---|
| Usual trigger | Shiga toxin-producing E. coli | Complement dysregulation, often with a trigger | Severe ADAMTS13 deficiency |
| Key confirming test | Stool Shiga toxin or STEC culture | Exclusion plus complement studies | ADAMTS13 activity very low |
| Mainstay of treatment | Supportive care, dialysis if needed | Supportive care plus complement inhibition | Plasma exchange and immune therapy |
| Role of antibiotics | Generally avoided | Only for a separate infection | Not part of treatment |
The table is a simplification. Some people have secondary HUS from pneumococcal infection, medicines or transplant, and the team tailors care accordingly.
Who is admitted right away, and who is asked to wait and be watched?
HUS itself is a hospital diagnosis. Once blood tests show hemolysis, low platelets and kidney injury together, admission is the norm, and children are often transferred to a center with pediatric nephrology and dialysis. The more nuanced question is what happens in the days before, when a child simply has diarrhea from a Shiga toxin-producing E. coli infection.
According to the CDC, about five to ten percent of people diagnosed with STEC infection go on to develop HUS, with young children and older adults at highest risk. That means most children with this infection will not need hospital treatment for HUS, but all of them need watching during the window when it typically appears, roughly a week after symptoms begin. Many clinics arrange repeat blood counts and kidney tests every day or two during that period, and ask families to track urine output at home.
Who tends to be admitted early? Children who are dehydrated and cannot keep fluids down, those with very high white cell counts or early drops in platelets, infants, and anyone whose urine output is falling. Some centers admit children with confirmed STEC for intravenous fluids before HUS develops; observational studies suggest early volume expansion may be associated with a lower need for dialysis, though this is not proven in randomized trials and practice varies.
Who is usually asked to wait? An otherwise well child who is drinking, urinating normally, and whose blood counts are stable may be monitored as an outpatient with clear return instructions. Waiting here is not neglect; it is active surveillance with a low threshold to come back.
Adults with suspected aHUS or TTP are generally admitted immediately, because the look-alike TTP can worsen within hours and the distinction shapes urgent treatment.
What the following days and weeks usually look like
The first days on the ward are the most intensive. Blood tests come daily or more often; fluids are adjusted, blood pressure medicines added or changed, and if dialysis is needed it usually begins within this window. Children are often tired, irritable and puffy from fluid, and may need a feeding tube or intravenous nutrition if they cannot eat.
Hemolysis typically settles before the kidneys recover. Families frequently notice the change in color and energy first, sometimes after a transfusion, while creatinine stays stubbornly high. Platelets usually climb back as the clotting process burns out, and a rising platelet count is often read as a sign that the acute phase is passing.
Kidney recovery is the slower arc. Urine output frequently returns before the lab values improve, and once it does, dialysis sessions can be spaced out and stopped. For most children the hospital stay runs from a week or two to several weeks, depending largely on whether dialysis was needed and how long the kidneys took to restart; there is no fixed schedule, and clinicians avoid promising dates.
Discharge does not end treatment. Mayo Clinic notes that some people develop lasting kidney problems or high blood pressure, so follow-up with a kidney specialist continues for years, with periodic checks of blood pressure, urine protein and kidney function. Children who appeared to recover completely may still be seen annually because late-onset high blood pressure or protein in the urine can emerge long after the illness.
People with aHUS have a different long-term path. Because the underlying complement problem persists, they may remain on complement-blocking therapy for an extended period, and the question of whether and when to stop is decided individually by the specialist team.
What is the survival rate of HUS? What the evidence actually shows
This is the question every parent asks and the one that deserves the most careful answer. Mayo Clinic states that most people with HUS, especially young children, recover fully with appropriate treatment. That is a genuinely reassuring statement from a mainstream source, and it reflects the fact that the disease process is self-limiting: once the toxin clears, the vessel lining heals.
It is not a promise for any individual. HUS remains a serious illness. Deaths do occur, most often from complications outside the kidney, such as brain involvement with seizures or stroke, heart involvement, or severe bowel injury. Mayo Clinic lists kidney failure, high blood pressure, stroke, heart problems, coma and death among possible complications. The risk is higher in the very young, in older adults, and in people with severe involvement of several organs at the start.
The long-term picture is also mixed rather than binary. A proportion of children who survive typical HUS are left with reduced kidney function, protein in the urine or high blood pressure, and a smaller number eventually need long-term dialysis or a kidney transplant. Because the size of that proportion varies between studies, populations and eras, this article does not quote a single figure; any percentage offered to you should come with the study it is drawn from.
Atypical HUS historically carried a worse kidney outlook, with frequent progression to kidney failure and recurrence, and complement inhibitors changed that trajectory for many patients. How much, and for whom, depends on the underlying genetic change.
What matters most, based on the evidence, is early recognition, meticulous supportive care, and long follow-up. Those are the levers the team controls, and they are the ones worth asking about.
What people often get wrong about HUS treatment
Antibiotics will clear the infection faster. For Shiga toxin-producing E. coli, the CDC advises against routine antibiotics because killing the bacteria may release more toxin. The infection is self-limiting; the danger is the toxin, not the bacterial load.
Low platelets should be topped up. Platelets in HUS are being consumed in small-vessel clots. Transfusing them is generally reserved for bleeding or procedures, because more platelets may feed the clotting rather than fix it.
Dialysis means the kidneys have failed for good. In HUS, dialysis is usually a temporary bridge. Many children come off it as their kidneys recover, and the team watches urine output for exactly that turn.
Once the diarrhea stops, the danger has passed. The CDC notes that HUS often develops about a week after symptoms begin, frequently as diarrhea is improving. Paleness, reduced urine and unusual tiredness after a bloody diarrheal illness warrant urgent assessment.
HUS is caught from another person with HUS. HUS itself is not contagious. The E. coli that triggers it can spread through contaminated food, unpasteurized products, animal contact and person-to-person via poor hand hygiene, which is why siblings are sometimes tested.
Drinking lots of fluids at home prevents it. Hydration matters, but in a child whose kidneys are shutting down, unmeasured fluid can cause overload. Fluid strategy is set by clinicians based on urine output and weight.
aHUS is just a milder version. It is a different disease with a different cause, often recurring, and it is the form for which targeted medicines exist. The name shared between them causes real confusion, and asking which type has been diagnosed is a reasonable first question.
Questions to ask your care team
Wards are busy and rounds are short, so having a written list helps. These questions are the ones families most often wish they had asked earlier, and none of them has a standard answer; each depends on the patient in front of the team.
- Which type of HUS do you think this is: typical, atypical or secondary? What tests are still pending, and when do you expect results?
- What numbers are you watching most closely today, and what change would prompt a new decision?
- How are you deciding how much fluid to give, and how will I know if my child is becoming fluid-overloaded?
- Is a blood transfusion likely, and what signs would lead you to give one?
- If dialysis becomes necessary, which type would you use, where would the catheter go, and how would you decide when to stop?
- Which medicines are being avoided right now, and is there anything we gave at home that you need to know about?
- What complications outside the kidney are you monitoring for, and what would they look like?
- What does recovery typically look like from here, and what would make you more or less optimistic?
- After discharge, who follows the kidneys, how often, and for how long?
- Should other household members be tested, and what hygiene steps reduce spread of the bacteria?
- For aHUS: is genetic testing planned, what would the results change, and how long might complement-blocking treatment continue?
Asking a clinician to explain the day’s lab trend in plain terms is not a burden. Most teams welcome an informed family, because parents notice changes in color, energy and urine that a monitor cannot.
When to call your doctor: red-flag signs during and after HUS
Before a diagnosis. A child or adult with diarrhea, especially bloody diarrhea, needs urgent medical assessment if they become unusually pale, pass much less urine than normal or none for many hours, develop dark or cola-colored urine, appear puffy around the eyes or legs, become confused or very drowsy, bruise easily or bleed from the nose or gums, or have a seizure. The CDC lists decreased urination, extreme fatigue and loss of pink color in the cheeks and lower eyelids as signs of HUS that warrant immediate care.
During the diarrheal illness. Call the doctor the same day if fluids cannot be kept down, if diarrhea is bloody, or if fever persists. Do not give antidiarrheal medicines or leftover antibiotics while waiting to be seen.
After discharge. Contact the kidney team promptly if urine output falls again, swelling returns, headaches or vision changes develop (possible high blood pressure), there is new blood in the urine, or the person becomes pale and exhausted after seeming to recover. For someone with aHUS, any new infection, fever, or return of dark urine should be reported without delay, and anyone receiving complement-blocking therapy should seek emergency care for fever with headache, stiff neck or a rash, because of meningococcal risk.
Emergency services. Seizure, difficulty breathing, chest pain, sudden weakness on one side, or unresponsiveness are emergencies at any stage.
None of this replaces the individual instructions given at discharge. Keep the team’s contact details visible at home, and when in doubt, call; a phone call that turns out to be unnecessary costs nothing but a few minutes.
Frequently asked questions
What is the first-line treatment for hemolytic uremic syndrome?
For typical E. coli-related HUS, first-line treatment is supportive care: carefully balanced intravenous fluids, daily monitoring of blood counts and kidney function, red blood cell transfusion for severe anemia, blood pressure control and dialysis if the kidneys cannot clear waste or fluid. No medicine has been shown to shorten the illness itself. For atypical HUS, complement-blocking therapy may be added, a decision made by specialist teams.
What causes aHUS?
Atypical HUS is caused by uncontrolled activity of the complement system, a group of immune proteins that normally attack microbes. Inherited changes in genes that regulate complement, or antibodies against the regulator factor H, remove the brakes so complement damages the body’s own vessel lining. A trigger such as infection, pregnancy, certain medicines or transplant often sets off the first episode.
How is atypical hemolytic uremic syndrome diagnosed?
Largely by exclusion. Clinicians confirm hemolysis, low platelets and kidney injury, test stool for Shiga toxin-producing E. coli, and measure ADAMTS13 enzyme activity to rule out TTP, a look-alike disorder treated differently. Negative STEC testing with normal ADAMTS13 and no other secondary cause supports aHUS. Complement levels, anti-factor H antibodies and genetic testing follow, though genetic results can take weeks.
What is the survival rate of HUS?
Mayo Clinic states that most people with HUS, particularly young children, recover fully with appropriate treatment, but HUS remains serious and deaths do occur, usually from brain, heart or bowel complications. Because reported figures vary widely between studies and populations, any percentage quoted should come with its source. Individual outlook depends on age, organ involvement and HUS type, and is best discussed with the treating team.
How long does HUS dialysis in children usually last?
There is no fixed duration. Dialysis in HUS is a temporary bridge used until the kidneys recover, and teams typically look for returning urine output as the first sign. Depending on severity, this can take days to several weeks. Sessions are spaced out and stopped as kidney function returns. A small minority do not recover kidney function and need longer-term dialysis or transplant.
Why are antibiotics not given for HUS?
The CDC advises against routine antibiotics for Shiga toxin-producing E. coli infections because killing the bacteria can release more toxin and some antibiotics may increase toxin production, potentially raising the chance of HUS. The infection clears on its own; the harm comes from the toxin. If a separate bacterial infection is present, the treating team weighs antibiotic use individually.
Can HUS be treated at home?
No. HUS involves kidney injury that requires hospital monitoring of blood counts, potassium, fluid balance and blood pressure, with dialysis available if needed. What can happen at home is surveillance during an E. coli diarrheal illness, tracking urine output and returning for repeat blood tests, when a clinician judges the person well enough for outpatient monitoring.
Is hemolytic uremic syndrome contagious?
HUS itself is not contagious. The Shiga toxin-producing E. coli that triggers typical HUS can spread through contaminated food or water, unpasteurized products, contact with farm animals, and from person to person through poor hand hygiene. Household members are sometimes tested, and careful handwashing after toilet use and diaper changes reduces spread.
Is plasma exchange still used for HUS?
Plasma exchange, which removes a patient’s plasma and replaces it with donor plasma, is not part of routine treatment for typical E. coli HUS. It remains central for TTP and was historically the main approach for atypical HUS before complement-blocking antibodies became available. Mayo Clinic notes it may still be used in selected aHUS situations, at the specialist team’s discretion.
Will the kidneys recover fully after HUS?
Many children regain normal kidney function, but a proportion are left with reduced function, protein in the urine or high blood pressure, sometimes appearing years later. This is why kidney follow-up continues long after discharge with periodic checks of blood pressure, urine protein and creatinine. No clinician can guarantee full recovery for an individual; the trend in lab values over weeks offers the best guide.
References
- CDC: About Escherichia coli Infection
- MedlinePlus: Hemolytic-uremic syndrome
- NIDDK (NIH): Hemolytic Uremic Syndrome in Children
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Passing Stone Fragments After ESWL: What the First Days Feel Like and How Fluids Help
After ESWL, the crushed stone leaves the body as sand-like grit and small fragments in the urine, usually over the following days to weeks.…

What Do Tests for Urethra Diseases Involve? Cystoscopy, Uroflowmetry and Ultrasound Explained
Tests for urethra diseases usually combine a urine sample, uroflowmetry (urinating into a machine that measures flow rate), an ultrasound of the bladder and…

Which Scans Show a Ureter Problem? Ultrasound, CT and Kidney Function Tests Explained
A non-contrast CT scan is the most accurate way to find a stone or blockage in a ureter, while ultrasound is often the first…

What Makes a UTI Complicated? Obstruction, Catheters, Pregnancy and Kidney Involvement
A UTI is called complicated when something about the person or their urinary tract raises the risk that standard treatment will fail or the…

Renal Replacement Therapy Options: Hemodialysis, Peritoneal Dialysis and Transplant Compared
Hemodialysis filters blood through a machine, usually three times a week; peritoneal dialysis uses the lining of the abdomen as a filter at home,…
How Do Urinary Biomarkers Fit Into Bladder Cancer Surveillance Between Cystoscopy Visits?
Urinary biomarkers are laboratory tests on a urine sample that look for cancer-related cells, proteins or DNA changes. In bladder cancer surveillance they are…