

How Is Adrenal Insufficiency Confirmed? Cortisol, ACTH and Stimulation Testing Explained

Key Takeaways
- Cortisol peaks in the early morning and falls toward midnight, so a diagnostic cortisol test is drawn around 8 a.m., and an afternoon value within range excludes very little.
- Measuring ACTH alongside cortisol locates the fault: a high ACTH with low cortisol points to the adrenal glands, while a low or normal ACTH with low cortisol points to the pituitary or hypothalamus.
- The ACTH stimulation test gives a synthetic dose of the pituitary's messenger and measures cortisol at baseline and about 30 and 60 minutes later; healthy glands respond with a brisk rise.
- A normal stimulation test can miss pituitary failure that began only weeks earlier, because the adrenal glands have not yet shrunk, so clinicians may repeat it or use a different test.
- Skin darkening, salt craving and high potassium occur mainly in primary adrenal insufficiency, because excess ACTH stimulates pigment and the aldosterone-producing layer has also failed.
- Long-term glucocorticoid medicine is the most common reason for a suppressed cortisol axis, and testing is timed by the prescribing clinician because a result taken while the drug is active is uninterpretable.
Adrenal insufficiency is confirmed with blood tests rather than symptoms alone. Clinicians usually start with an early-morning cortisol level, add an ACTH measurement to show whether the problem sits in the adrenal glands or the pituitary, and then run an ACTH stimulation test to see how much cortisol the glands can produce on demand. Further tests, including antibodies, electrolytes or imaging, help identify the cause.
The appointment had been booked for tiredness. Six months of it, the kind that a weekend of sleep never touched, plus a salt craving that had turned into a nightly bag of pretzels and a tan that lingered long after the beach trip ended. The physician listened, checked blood pressure lying and then standing, watched the numbers drop, and asked a question that changed the direction of the visit: “Has anyone ever checked your cortisol?”
That question opens a door into one of the more careful corners of endocrinology. Adrenal insufficiency, the medical name for glands that cannot make enough cortisol, is uncommon, easy to miss and dangerous when it is missed. Its symptoms borrow from a dozen other conditions. A single blood value can look reassuring at one hour of the day and alarming at another.
So the adrenal insufficiency diagnosis is built rather than declared. It rests on a sequence of measurements, each answering a slightly different question, and on a clinician who knows which result can be trusted and which one needs a second look. Here is how that sequence actually works.
Why adrenal insufficiency diagnosis is rarely a single blood test
Cortisol is a hormone that refuses to sit still. Levels climb steeply in the hours before waking, peak in the early morning and drift toward their lowest point around midnight. Stress, pain, illness and even the anxiety of a needle push the number upward. That daily rhythm is exactly why one random cortisol result tells a clinician so little on its own, and why the adrenal insufficiency diagnosis is assembled from several pieces of evidence rather than read off one report.
The pieces answer different questions. A morning cortisol asks, “How much is the body making at the time it should be making the most?” An ACTH level asks, “Where along the chain of command is the failure?” A stimulation test asks, “If the glands are given a direct order, can they respond?” Only when those answers line up does the picture become firm enough to act on, and even then the cause still has to be found.
The stakes explain the caution. Missing adrenal insufficiency leaves a person exposed to adrenal crisis, a sudden collapse of blood pressure and blood sugar that can be life-threatening during an infection, surgery or injury. Over-diagnosing it commits someone to lifelong hormone replacement they may not need, along with the monitoring and the emergency planning that come with it. Endocrinologists are trained to be equally wary of both mistakes.
What follows is the standard pathway described by the National Institute of Diabetes and Digestive and Kidney Diseases and by the major health services: start with the simplest measurement, interpret it in the light of timing and medicines, escalate to dynamic testing when the answer is unclear, and then search for the cause. The order matters less than the logic, and the logic is what makes the result trustworthy.
What the adrenal glands and cortisol actually do
Each adrenal gland sits on top of a kidney like a small, folded cap. The outer layer, the cortex, makes three families of steroid hormones. Cortisol handles the body’s response to stress, keeps blood pressure and blood sugar steady, and dampens inflammation. Aldosterone tells the kidneys how much sodium to keep and how much potassium to release, which is why it quietly governs blood volume and blood pressure. A third group, the adrenal androgens, contributes to body hair and, in women, to sex-hormone balance.

None of this runs on autopilot. The hypothalamus, a region at the base of the brain, releases a signal called CRH. The pituitary gland, a pea-sized structure just below it, answers by releasing ACTH, short for adrenocorticotropic hormone, the messenger that instructs the adrenal cortex to make cortisol. Rising cortisol then feeds back to the brain and pituitary and turns the signal down. Endocrinologists call this loop the HPA axis, and every diagnostic test for adrenal insufficiency is essentially a way of probing one link in that loop.
Picture a thermostat. The hypothalamus sets the target, the pituitary relays the instruction, the adrenal glands are the furnace, and cortisol is the heat. When the room stays cold, the question is not simply “is the furnace broken?” but “is the furnace broken, or is the thermostat failing to call for heat?” That distinction is the reason an ACTH level is drawn alongside cortisol, and the reason the tests described later fall into two broad patterns.
Aldosterone follows a slightly different chain of command, controlled mainly by the kidneys through a hormone called renin rather than by ACTH. That detail becomes useful later, because it explains why salt craving and low blood pressure tend to appear when the adrenal gland itself has failed, and why they are often absent when the problem is upstream in the pituitary.
Primary, secondary and tertiary: why the label changes the tests
Clinicians divide adrenal insufficiency by where the fault lies, and the label steers everything that follows. Primary adrenal insufficiency, often called Addison’s disease, means the adrenal glands themselves are damaged and cannot respond to ACTH no matter how loudly the pituitary calls. In the United States and Europe the most common cause is an autoimmune attack on the adrenal cortex, according to the NIDDK. Infections such as tuberculosis, bleeding into the glands, certain genetic conditions and some cancer treatments can also be responsible.
Secondary adrenal insufficiency means the pituitary is not producing enough ACTH. The adrenal glands are structurally healthy but under-stimulated, and over time they shrink from disuse. Pituitary tumors, pituitary surgery, radiation to the head and inflammation of the gland are recognized causes.
Tertiary adrenal insufficiency sits one step higher, at the hypothalamus. Its most frequent cause is not disease at all but medicine: long-term treatment with glucocorticoids, a class of steroid drugs used for asthma, autoimmune conditions and many other illnesses. External steroid tells the brain that cortisol is plentiful, so CRH and ACTH production switch off. Because the tests and the practical consequences overlap so heavily, many clinicians group secondary and tertiary forms together as “central” adrenal insufficiency.
Why does the label matter to a person waiting for results? Three reasons. First, aldosterone is usually lost only in the primary form, so salt and potassium abnormalities point toward the adrenal gland rather than the pituitary. Second, the ACTH level runs in opposite directions in the two patterns, which is the single most useful clue to location. Third, the cause-hunting tests diverge completely: antibody tests and adrenal imaging for the primary form, pituitary imaging and a check of the other pituitary hormones for the central form. Getting the label right early prevents a great deal of unnecessary testing later.
Step one: the morning cortisol test
Most diagnostic journeys begin with a cortisol blood test drawn early in the morning, typically around 8 a.m., because that is when levels should be near their daily peak, as MedlinePlus explains in its description of the test. A person who cannot mount a respectable cortisol level at the hour their body is trying hardest to produce it has revealed something important. Conversely, a robust early-morning value makes adrenal insufficiency unlikely and can spare a person the more involved tests that follow.
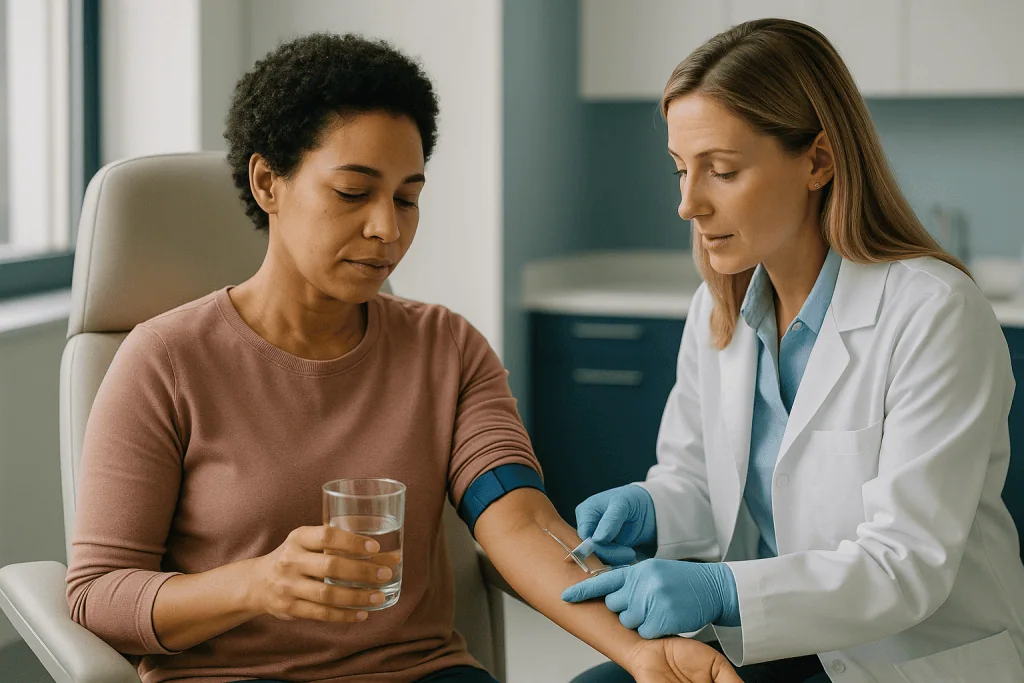
The test itself is unremarkable: a single venous blood sample, no fasting required in most laboratories, results within a few days. Its interpretation is where the skill lies. Laboratories set their own reference ranges, and a clinician reads the result against three zones rather than a single cut-off. A clearly low morning cortisol, especially with matching symptoms, strongly supports the diagnosis. A clearly high value largely rules it out. A wide middle zone is indeterminate, and it is this middle zone that sends most people on to stimulation testing.
Several everyday factors can nudge the number. Oral estrogen, including many contraceptive pills, raises the protein that carries cortisol in the blood, so total cortisol reads higher than the active, unbound fraction; clinicians factor this in or arrange to test at a different time. Shift work and jet lag shift the daily peak. Acute illness and severe pain drive cortisol up, which can mask a borderline deficiency. None of these make the test useless, but each is a reason to tell the ordering clinician exactly what medicines are being taken and what the past week has looked like.
One caution deserves its own sentence: a normal random cortisol drawn at 3 p.m. does not exclude adrenal insufficiency, because afternoon values are expected to be lower and the reference ranges were built around morning samples.
What the ACTH blood test adds to the picture
Drawing an ACTH level at the same time as the morning cortisol turns a one-dimensional result into a map. ACTH is the pituitary’s instruction to the adrenal glands, and its behaviour tells a clinician which end of the chain has failed.
When the adrenal glands themselves are damaged, cortisol falls and the pituitary responds the only way it can: by shouting. ACTH climbs, often far above the normal range, in an unanswered attempt to coax the glands into action. A low cortisol paired with a high ACTH is the classic signature of primary adrenal insufficiency. That excess ACTH also explains one of the most distinctive signs of Addison’s disease. ACTH is made from a larger parent molecule that also yields a pigment-stimulating hormone, so people with the primary form frequently notice darkening of the skin, particularly in creases, scars, gums and areas of friction.
When the pituitary or hypothalamus is at fault, the pattern flips. Cortisol is low, but ACTH is low or inappropriately normal, because the messenger itself is missing. Skin darkening is absent. Aldosterone is generally preserved, since it is controlled mainly through the kidneys, so sodium and potassium tend to stay closer to normal.
The ACTH sample has practical quirks. The hormone breaks down quickly at room temperature, so the tube is usually chilled and delivered to the laboratory promptly, and results may take longer than routine chemistry. Like cortisol, ACTH follows a daily rhythm and is best drawn in the morning alongside it. A single ACTH value is interpreted strictly in the context of the paired cortisol; on its own it can mislead, as MedlinePlus notes in its description of the test.
For a person awaiting results, the useful takeaway is that these two numbers are read together. The combination, rather than either one in isolation, is what allows a clinician to say not just “cortisol is low” but “cortisol is low because of the adrenal glands” or “because of the pituitary.”
How the ACTH stimulation test works, step by step
The ACTH stimulation test, known in the United Kingdom as the short synacthen test, is the workhorse of confirmation. Its logic is simple: instead of waiting to see what the adrenal glands produce on their own, clinicians deliver a direct order and measure the response.
Here is what actually happens. A baseline blood sample is drawn for cortisol. A synthetic form of ACTH, chemically similar to the body’s own messenger, is then given by injection into a vein or muscle. Further blood samples are taken at set intervals, typically 30 and 60 minutes afterward, as MedlinePlus describes. Healthy adrenal glands respond to the surge of instruction with a brisk rise in cortisol. Glands that are damaged, or that have withered from months of missing ACTH, cannot.
The whole visit usually lasts about an hour. The injection itself is quick; some people describe brief warmth or flushing, and a few feel mildly nauseated, but serious reactions are rare. Most centers prefer to run the test in the morning so that the baseline value is interpretable too, though the stimulated result is less dependent on timing than a lone cortisol.
Reading the result comes down to the peak cortisol reached. A stimulated value above the laboratory’s threshold indicates the glands can respond and makes primary adrenal insufficiency very unlikely. A flat or inadequate response supports the diagnosis. Thresholds vary between laboratories and between the newer, more specific cortisol assays and older methods, which is why clinicians quote the result against their own laboratory’s range rather than a universal number.
The test has one well-recognized blind spot. If the pituitary stopped producing ACTH only recently, for example within a few weeks of pituitary surgery, the adrenal glands may not yet have shrunk and can still respond normally to a synthetic burst. In that setting a clinician may repeat the test later or turn to a different method, described in the section on secondary adrenal insufficiency.
Who is usually tested, and who is asked to wait
Testing is offered when the story and the examination point the same way. The NIDDK and the NHS describe the typical prompts: fatigue that does not lift with rest, unexplained weight loss, dizziness or fainting on standing, persistent nausea or abdominal pain, salt craving, low blood pressure, low sodium or high potassium on routine blood work, and, in the primary form, darkening of the skin. People with other autoimmune conditions such as type 1 diabetes, autoimmune thyroid disease or vitiligo carry a higher background risk and may be tested with a lower threshold of suspicion. So may anyone who has had pituitary surgery or radiation, or who is being weaned from long-term steroid treatment.
Some people are asked to wait, and the reasons are worth understanding rather than resenting. Someone taking a glucocorticoid medicine for another condition cannot have a meaningful cortisol measured while the drug is active, because many of these medicines are detected by the cortisol assay or suppress the axis the test is trying to assess. The clinician who prescribed that medicine, not the person taking it, decides whether and how the timing can be adjusted; abrupt changes carry their own risks and are never made independently.
Oral estrogen is a second common reason for rescheduling or reinterpretation, because it inflates total cortisol readings. A person in the middle of an acute infection or recovering from surgery may also be asked to defer non-urgent testing, since illness drives cortisol upward and can hide a borderline deficiency.
Pregnancy changes the reference ranges considerably, and specialists interpret results against pregnancy-specific expectations. Infants and children follow their own pathway, in which a genetic cause such as congenital adrenal hyperplasia, a group of inherited enzyme deficiencies, is considered early and tested for directly.
Waiting, in other words, is usually about protecting the accuracy of the answer. A test that produces a confidently wrong result is worse than one that is delayed by a few weeks.
Reading the results: what each test pattern usually means
Once the numbers arrive, the combination tells the story. Individual values are always read against the laboratory’s own reference range, but the direction of each result, high, low or flat, follows recognizable patterns that clinicians rely on.
| Test | Healthy response | Primary adrenal insufficiency | Secondary or tertiary (central) |
|---|---|---|---|
| Early-morning cortisol | Within or above reference range | Low | Low or borderline |
| Paired ACTH | Normal | High | Low or inappropriately normal |
| ACTH stimulation test | Brisk rise in cortisol | Flat or inadequate rise | Often flat if long-standing; may be normal if recent |
| Sodium and potassium | Normal | Sodium often low, potassium often high | Sodium may be low; potassium usually normal |
| Renin and aldosterone | Normal | Renin high, aldosterone low | Usually normal |
| Skin darkening | Absent | Common | Absent |
A few nuances soften the neatness of the table. Borderline morning cortisol with a normal stimulation test is a frequent outcome, and it usually reassures rather than alarms, though a clinician may arrange a repeat if symptoms persist. A normal stimulation test does not exclude very recent pituitary failure, as noted earlier. Electrolyte changes are helpful when present but their absence does not rule anything out, particularly in the early stages or in the central forms.
Laboratories increasingly use newer cortisol assays that measure the hormone more specifically, and the thresholds for a “normal” stimulated response have shifted downward with them, according to the Endocrine Society guidance many specialists follow. This is one more reason a result should be discussed with the team that ordered it rather than compared against numbers found online.
The pattern points the way; it does not end the investigation. Confirming that cortisol is deficient and locating the fault are two of the three tasks. The third, finding out why, is the subject of the next section.
Tests beyond cortisol: electrolytes, antibodies and imaging
Confirming low cortisol is the middle of the story, not the end. The cause shapes everything from long-term monitoring to whether family members should be aware, so once the pattern is established the search shifts to explanation.
For primary adrenal insufficiency, the first stop is usually an antibody test. Autoimmune destruction of the adrenal cortex leaves a fingerprint in the form of antibodies against an adrenal enzyme called 21-hydroxylase. A positive result points firmly to an autoimmune cause and often prompts screening for companion conditions, since autoimmune adrenal disease frequently travels with autoimmune thyroid disease, type 1 diabetes, pernicious anemia and premature ovarian insufficiency, as the NIDDK describes. When antibodies are negative, imaging of the adrenal glands with a CT scan looks for other explanations: enlarged glands suggesting infection or bleeding, calcification hinting at old tuberculosis, or masses. In boys and young men, a blood test for very-long-chain fatty acids screens for adrenoleukodystrophy, an inherited condition that can present with adrenal failure before neurological symptoms appear.
Renin and aldosterone are measured together to assess the mineralocorticoid side of the gland. In the primary form, renin rises as the kidneys sense low salt and blood volume, while aldosterone stays low because the gland cannot answer. That combination confirms that both hormone systems have failed and informs the treating team’s approach.
For central adrenal insufficiency, attention turns upward. An MRI of the pituitary looks for tumors, inflammation or the after-effects of surgery and radiation. Because the pituitary controls several glands, the other pituitary hormones, including those governing thyroid, growth, sex hormones and fluid balance, are checked, since one deficiency rarely arrives alone.
A detailed medicine history is itself a diagnostic test. Steroid tablets, injections, inhalers, creams, eye drops and even some herbal or imported products can suppress the axis, and identifying them can explain a result that no scan will.
Diagnosing adrenal insufficiency when someone is acutely unwell
The careful, morning-timed sequence described so far assumes there is time to be careful. Sometimes there is not. Adrenal crisis, the abrupt failure of cortisol supply during physical stress, presents with severe vomiting, profound weakness, confusion, dangerously low blood pressure and sometimes low blood sugar. In that situation, waiting an hour for a stimulation test would be unsafe, and every major guideline, including guidance summarized by the NIDDK and Mayo Clinic, is explicit that treatment for suspected crisis begins before the diagnosis is confirmed.
What clinicians do instead is draw blood for cortisol and ACTH at the moment of suspicion, before any hormone treatment is given, and then start emergency management without waiting for the results. A single cortisol value drawn during severe illness is far more interpretable than one drawn on a quiet morning, because the body should be producing near-maximal amounts under that degree of stress. A low or even modest value in a critically ill person is therefore strongly suggestive. Formal stimulation testing, if still needed, is arranged once the person has recovered and the emergency treatment has been adjusted in a way that allows accurate measurement.
Emergency departments see this scenario in two main groups. The first is people with undiagnosed primary adrenal insufficiency whose first presentation is a crisis triggered by an infection, an injury or surgery. The second, and more common, is people already on long-term glucocorticoid treatment for another condition who become unwell and whose bodies cannot raise cortisol in response, or who have missed or stopped their medicine. In both groups the diagnostic clues are the same: low blood pressure that responds poorly to fluids, low sodium, sometimes high potassium and low glucose, and a history that fits.
The lesson for anyone in the middle of a work-up is reassuring rather than frightening. If symptoms escalate sharply before testing is complete, clinicians do not need a finished diagnosis to protect you. They need to be told about the suspicion, which is why carrying a note or telling any treating team that adrenal insufficiency is being investigated matters.
Secondary adrenal insufficiency, steroid medicines and the tests that catch it
The single most common reason an adult develops a suppressed HPA axis is not a disease of the adrenal or pituitary glands but a medicine taken for something else. Glucocorticoids, the steroid class used for asthma, inflammatory bowel disease, rheumatoid arthritis, transplant care and many other conditions, mimic cortisol so closely that the brain reads them as the real thing and stops sending ACTH. Over weeks to months the under-used adrenal glands shrink. If the medicine is then reduced or stopped, the glands may not be ready to take over, and a period of secondary or tertiary adrenal insufficiency follows.
Diagnosing this form has its own rhythm. Testing while the steroid is active is uninformative, so the prescribing clinician decides when a measurement can be taken, often at a point in the tapering process when the dose has fallen to a level where the body’s own production should be detectable. A morning cortisol is usually the first step; if it is adequate, recovery is under way. If it is low or borderline, a stimulation test follows. Recovery of the axis is gradual and highly variable between individuals, and the NIDDK notes it can take months after long-term treatment. The decision about how quickly to taper, and whether to retest, belongs entirely to the prescribing team; stopping or changing steroid treatment without that guidance is one of the recognized triggers of adrenal crisis.
The stimulation test’s blind spot is most relevant here and after recent pituitary surgery. When ACTH loss is recent, adrenal glands can still respond to a synthetic burst and the test reads falsely normal. Specialists may then repeat the test later or use an alternative that tests the whole axis rather than just the gland. The insulin tolerance test, which deliberately lowers blood sugar under close supervision to provoke a cortisol response, is one such option; it is reserved for selected people and performed only in specialist settings because of the risks involved, as Mayo Clinic describes.
Inhaled, topical, injected and even intra-articular steroids can suppress the axis in some people, which is why the medicine history matters as much as any laboratory value.
What the days and weeks after testing usually look like
For most people the testing phase is undramatic. A morning cortisol and ACTH involve one early appointment and a wait of a few days for results. If a stimulation test is needed, a second visit of roughly an hour follows, again usually in the morning. Antibody and renin results can take longer, sometimes one to two weeks depending on the laboratory, and imaging is scheduled separately. From the first suspicious result to a settled answer, a few weeks is a realistic span when the person is well; the NHS describes exactly this stepwise progression from routine blood tests to synacthen testing to cause-finding.
If the tests confirm adrenal insufficiency, the next conversation is with an endocrinologist about hormone replacement. The principle is straightforward, replacing what the body can no longer make, and the treating team will explain how the medicine mimics the daily rhythm of cortisol and, in the primary form, how the mineralocorticoid side is addressed. Alongside that comes education that many people find more consequential than the prescription itself: how to recognize the early signs of crisis, why physical stress changes needs, how to communicate the diagnosis to any clinician treating them, and what to carry. Medical alert identification and a written emergency plan are standard recommendations from the NIDDK and the NHS.
Follow-up in the first months typically involves reviewing symptoms, blood pressure, weight and electrolytes rather than repeatedly measuring cortisol, since blood levels on replacement therapy do not map neatly onto how a person feels. Timelines for feeling better vary widely between individuals, and the treating team is the right source for expectations.
If the tests are reassuring, that too has a shape. The clinician will usually revisit the original symptoms with fresh eyes, since fatigue, weight change and dizziness have many causes, and may suggest repeat testing if the picture evolves. A normal result closes one door; it does not mean the concern was unreasonable.
What people often get wrong about adrenal insufficiency diagnosis
Myth one: “adrenal fatigue” is the same thing, or an early stage of it. It is not. Adrenal fatigue is a term used outside mainstream medicine to describe tiredness attributed to overworked glands, and it has no accepted diagnostic criteria. Adrenal insufficiency is a measurable hormone deficiency confirmed by the tests in this article. Endocrinology bodies have reviewed the evidence and found no support for adrenal fatigue as a distinct condition, and no test that reliably identifies it.
Myth two: a saliva, hair or mail-order cortisol kit can rule adrenal insufficiency in or out. These tests measure something real, but they were not developed or validated for this purpose. Guideline-based diagnosis rests on early-morning blood cortisol, paired ACTH and stimulation testing interpreted by a clinician.
Myth three: one normal cortisol settles it. A random or afternoon cortisol within range excludes very little, because the hormone is expected to fall as the day goes on. Even a normal stimulation test can miss recent pituitary failure. Conversely, one low value on a stressful afternoon does not confirm the diagnosis either.
Myth four: Addison’s disease always shows up as dark skin and collapse. Skin darkening appears only in the primary form and can be subtle, particularly in people with darker complexions, where it may be easier to see in the gums, palm creases or nail beds. Many people are diagnosed after months of vague symptoms without ever having a dramatic event.
Myth five: the stimulation test is dangerous or painful. It involves one injection and a few blood draws over about an hour. Mild flushing or nausea occurs in some people; serious reactions are rare, as MedlinePlus notes.
Myth six: steroid inhalers and creams cannot affect the axis. They can, in some people and at some intensities of use, which is why a complete medicine list, including over-the-counter and topical products, is part of the diagnostic work-up rather than an afterthought.
Questions to ask your care team
A diagnostic work-up goes more smoothly when both sides know what the other is thinking. These questions are ones endocrinologists say they welcome, because each one clarifies the plan rather than second-guessing it.
- Which form of adrenal insufficiency are you considering, primary or central, and what in my history points that way?
- What time should my blood be drawn, and is there anything about my medicines, including contraceptives, inhalers or creams, that could change how the result is read?
- If my morning cortisol comes back in the indeterminate range, what is the next step, and how soon would it be arranged?
- Will an ACTH level be drawn with the cortisol, and how will the two be interpreted together?
- If I need a stimulation test, what should I expect during the hour, and do I need to prepare in any way?
- How will you decide whether my result is normal, given that laboratories use different thresholds and assays?
- If the tests confirm the diagnosis, what further tests will you use to find the cause, and will any of them have implications for my family?
- What symptoms should prompt me to seek urgent care while the work-up is under way, and should I carry anything that tells other clinicians I am being investigated?
- If the tests are reassuring, what do you think is most likely to explain my symptoms, and would you repeat testing if they persist?
- Who do I contact with questions between appointments, and how will results be communicated?
Writing the answers down during the appointment, or bringing someone who can, is a small habit that pays off in a process spread over several visits. Many people also find it useful to keep a short diary of symptoms, blood pressure readings if a home monitor is available, and any illness that occurs during the weeks of testing, because that context can change how a borderline result is weighed.
None of these questions replaces the clinician’s judgment. They exist to make that judgment easier to follow, and to leave every decision, from test timing to treatment, where it belongs: with the treating team who knows the full picture.
When to call your doctor
Most of the adrenal insufficiency diagnosis unfolds in outpatient appointments, but the condition has one emergency that overrides every schedule. Adrenal crisis develops when cortisol supply cannot meet the body’s demand, most often during an infection, an injury, surgery or after steroid medicine has been missed or stopped. It is life-threatening and treatable, and the outcome depends heavily on how quickly it is recognized.
Call emergency services or go to the nearest emergency department immediately if you, or someone being investigated or treated for adrenal insufficiency, develops:
- Severe vomiting or diarrhea that prevents keeping fluids down
- Sudden, severe weakness or an inability to stand
- Fainting, or dizziness so profound that standing is impossible
- Confusion, unusual drowsiness or difficulty staying awake
- Severe pain in the abdomen, lower back or legs that comes on quickly
- Very low blood pressure or a racing heartbeat, especially with cold, clammy skin
- Signs of very low blood sugar such as shaking, sweating and confusion
Tell the emergency team that adrenal insufficiency is suspected or confirmed. They do not need a finished diagnosis to act; they need the information.
Contact your doctor promptly, within a day, if during the work-up you notice worsening fatigue, new fainting or near-fainting, progressive weight loss, new or spreading skin darkening, persistent nausea, or a fever or infection that is making you feel unusually unwell. These do not always signal crisis, but they can change the urgency of testing.
Anyone already taking glucocorticoid medicine for another condition should speak to the prescribing clinician before any change is made, and should contact them urgently if the medicine has been missed for more than a day or cannot be kept down because of vomiting. The NHS and the NIDDK both stress that people on long-term steroid treatment need a plan for illness, and that plan comes from the prescriber, not from a magazine article.
If in doubt, call. Clinicians who manage adrenal disease would far rather hear about a false alarm than learn about a crisis afterward.
Frequently asked questions
What is the first test for adrenal insufficiency diagnosis?
An early-morning blood cortisol, usually drawn around 8 a.m. when levels should be highest, is almost always the first step. A clearly low value supports the diagnosis and a clearly high one makes it unlikely. Most clinicians draw an ACTH level at the same time so the two can be read together, and a borderline cortisol leads on to an ACTH stimulation test for confirmation.
How does the ACTH stimulation test work?
A baseline blood sample is taken, a synthetic form of ACTH is injected into a vein or muscle, and cortisol is measured again at set intervals, typically 30 and 60 minutes later. Healthy adrenal glands respond with a sharp rise in cortisol. Glands that are damaged or have shrunk from lack of stimulation cannot, and a flat response supports the diagnosis. The visit takes about an hour.
Can a morning cortisol test alone rule out adrenal insufficiency?
Sometimes, but only when the value is clearly high. A robust early-morning cortisol makes adrenal insufficiency unlikely and may spare further testing. A low value supports the diagnosis, while the wide middle range is indeterminate and needs a stimulation test. Timing, oral estrogen, acute illness and steroid medicines can all shift the result, so the clinician interprets it in context rather than as a standalone answer.
How is Addison's disease diagnosis different from secondary adrenal insufficiency?
Addison’s disease, the primary form, shows low cortisol with a high ACTH, because the pituitary is signalling glands that cannot respond. Secondary adrenal insufficiency shows low cortisol with a low or inappropriately normal ACTH. Addison’s often adds low sodium, high potassium, high renin and skin darkening, which are usually absent in the secondary form. The cause-finding tests then diverge: adrenal antibodies and CT for Addison’s, pituitary MRI and other pituitary hormones for secondary.
Why does the clinician want to know about my steroid inhaler or contraceptive pill?
Both can change how the tests are read. Glucocorticoid medicines, including some inhaled, topical and injected steroids, can suppress the body’s own cortisol production and may be detected by the assay itself, making results uninterpretable while the drug is active. Oral estrogen raises the protein that binds cortisol, so total cortisol reads higher than the active fraction. Clinicians adjust timing or interpretation, and any change to prescribed medicine is decided only by the prescriber.
What happens if I become seriously unwell before the tests are finished?
Treatment for suspected adrenal crisis begins before the diagnosis is confirmed. Clinicians draw blood for cortisol and ACTH at the moment of suspicion and then start emergency management without waiting for results. A low cortisol during severe illness is highly informative because the body should be producing near-maximal amounts. Formal stimulation testing, if still needed, is arranged after recovery. Telling any treating team that adrenal insufficiency is being investigated is essential.
Can secondary adrenal insufficiency be missed by the stimulation test?
Yes, in one specific situation. If the pituitary stopped producing ACTH only recently, for example within weeks of pituitary surgery, the adrenal glands may not yet have shrunk and can still respond normally to a synthetic burst. Specialists are aware of this blind spot and may repeat the test after several weeks or use an alternative such as the insulin tolerance test, performed only under close supervision in specialist settings.
Do I need imaging to confirm adrenal insufficiency?
Imaging does not confirm the hormone deficiency; blood tests do that. Scans are used afterward to find the cause. In primary adrenal insufficiency with negative adrenal antibodies, a CT of the adrenal glands looks for infection, bleeding or masses. In secondary adrenal insufficiency, an MRI of the pituitary looks for tumors, inflammation or the effects of surgery or radiation. Many people with autoimmune Addison’s disease never need adrenal imaging.
Are saliva or home cortisol kits useful for diagnosing adrenal insufficiency?
Not for this purpose. Saliva and hair cortisol measure something real, but they have not been validated to diagnose or exclude adrenal insufficiency, and guideline-based diagnosis rests on early-morning blood cortisol, paired ACTH and ACTH stimulation testing interpreted by a clinician. A reassuring home result should not delay proper evaluation if symptoms suggest the condition, and an abnormal one needs formal testing before any conclusion is drawn.
How long does the adrenal insufficiency diagnosis process usually take?
When a person is well, the sequence typically unfolds over a few weeks. A morning cortisol and ACTH take one early appointment with results in days. A stimulation test, if needed, adds a second visit of about an hour. Antibody, renin and imaging results may take one to two weeks depending on the laboratory. In an emergency the timeline collapses, because treatment starts as soon as a sample has been drawn.
References
- Adrenal Insufficiency & Addison's Disease: NIDDK, National Institutes of Health
- ACTH stimulation test: MedlinePlus Medical Encyclopedia
- Cortisol blood test: MedlinePlus Medical Encyclopedia
- Addison's disease: Diagnosis: NHS
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Hormone Replacement vs Thyroid Surgery: How Thyroid Disease Treatment Paths Are Chosen
Thyroid medication and surgery usually treat different problems rather than competing for the same one. An underactive thyroid is managed with lifelong hormone replacement,…

Life After Pituitary Tumor Treatment: Follow-Up MRI, Hormone Checks and Recurrence Watch
Pituitary tumor follow up usually combines three strands: a baseline MRI a few months after surgery or radiotherapy, then scans at intervals set by…

After Surgery for Hyperparathyroidism: Calcium Monitoring and the Return to Daily Activity
After surgery for hyperparathyroidism, most people go home within a day and return to light daily activity within one to two weeks, while blood…

After a Longevity Program Visit: Sleep, Stress and Exercise Plans and When Reassessment Is Due
A longevity program follow up usually turns the first visit's measurements into three written plans: a sleep target of at least seven hours a…

Before Thyroidectomy: Ultrasound, Biopsy, Voice Checks and Medicines to Pause
Thyroidectomy preparation usually includes a neck ultrasound, a needle biopsy if a nodule looks suspicious, blood tests for thyroid hormone and calcium, and often…
Robotic Thyroidectomy Through the Armpit: What Does the Robot Change vs a Neck Incision?
A robotic transaxillary thyroidectomy removes the thyroid through an incision hidden in the armpit, using a surgeon-controlled robot to reach the neck beneath the…