

How Long Does Liquid Rhinoplasty Last? Filler Longevity in the Nose and Repeat Timing

Key Takeaways
- Hyaluronic acid filler generally lasts about 6 to 18 months according to NHS guidance, and case series suggest the nose sits toward the longer end because it barely moves.
- Bridge corrections placed against bone typically outlast tip corrections, which sit on cartilage that flexes with expression.
- Repeat treatment is usually judged by visible fading rather than a calendar; adding filler before the previous gel has cleared risks over-correction and slow buildup.
- Filler adds volume and cannot make a nose physically smaller, narrow nostrils or fix breathing, all of which Mayo Clinic describes as surgical goals.
- The nose is a high-risk filler site because its arteries connect to the eye's blood supply; skin color change or any vision change after treatment is an emergency.
- Hyaluronic acid can be dissolved with the enzyme hyaluronidase, which makes an unwanted result correctable and is one reason it is favored over non-reversible fillers for the nose.
Liquid rhinoplasty, which uses hyaluronic acid filler to reshape the nose without surgery, is temporary. Most people see results for roughly 6 to 18 months, and the nose often holds filler longer than mobile areas such as the lips, sometimes approaching two years. Longevity depends on the product, the amount placed, individual metabolism and placement depth. Repeat treatment is usually discussed only once earlier filler has largely faded.
She had a wedding in the spring and a small bump on the bridge of her nose that had bothered her since high school. Surgery felt like too much: the weeks of swelling, the splint, the time off work. A friend mentioned nose filler. The first question she typed into her phone that night was the one almost everyone asks before booking: how long does liquid rhinoplasty last, and will she be back in the chair every few months?
It is a fair question, because the answer shapes everything else. A treatment that fades in a season is a different decision from one that holds for a year or more. And the honest answer sits somewhere in between, with more nuance than a single number on a consent form.
This explainer walks through what the evidence actually shows about filler longevity in the nose, why this particular part of the face behaves differently from the lips or cheeks, how repeat timing is usually judged, and what warning signs should never be waited out.
How long does liquid rhinoplasty last? The honest range
Liquid rhinoplasty is a nonsurgical procedure in which a gel filler, almost always made of hyaluronic acid, is injected under the skin of the nose to smooth a bump, lift a drooping tip or straighten a mild asymmetry. Hyaluronic acid is a sugar molecule your body already makes; in the skin it binds water and gives tissue volume. Because the body slowly breaks the injected gel down, the change is temporary by design.
General guidance from the NHS puts the lifespan of hyaluronic acid dermal fillers at roughly 6 to 18 months, depending on the product and where it is placed. Cleveland Clinic gives a similar window and notes that thicker, more cross-linked gels tend to persist longer than softer ones. Those figures describe fillers across the face; the nose is a special case, which the next section explains.
What the nose-specific evidence looks like matters here. Most published data on liquid rhinoplasty comes from case series and observational studies rather than large randomized trials. Those reports consistently describe results outlasting the same product in the lips, with many patients still showing visible correction at a year and some beyond that. The reports also vary widely in how they measured “lasting,” so a precise nose-only average does not exist in the literature.
A practical way to hold this in mind: the first treatment usually gives a result that softens gradually rather than vanishing on a date. Around the one-year mark many people notice the bump beginning to reappear or the tip settling slightly. Some notice it earlier, at six to nine months; some are still satisfied with their profile well past a year. The range is real, and any clinician who quotes a single guaranteed number is speaking beyond what the evidence supports.
What actually happens during a liquid rhinoplasty
The appointment itself is short. After a consultation about what bothers you and what filler can and cannot do, the skin is cleaned and usually numbed with a topical anesthetic cream; many fillers also contain a local anesthetic mixed into the gel. Cleveland Clinic describes the injection phase of a filler treatment as taking around 15 to 30 minutes, though the nose often takes less because the volumes involved are small.
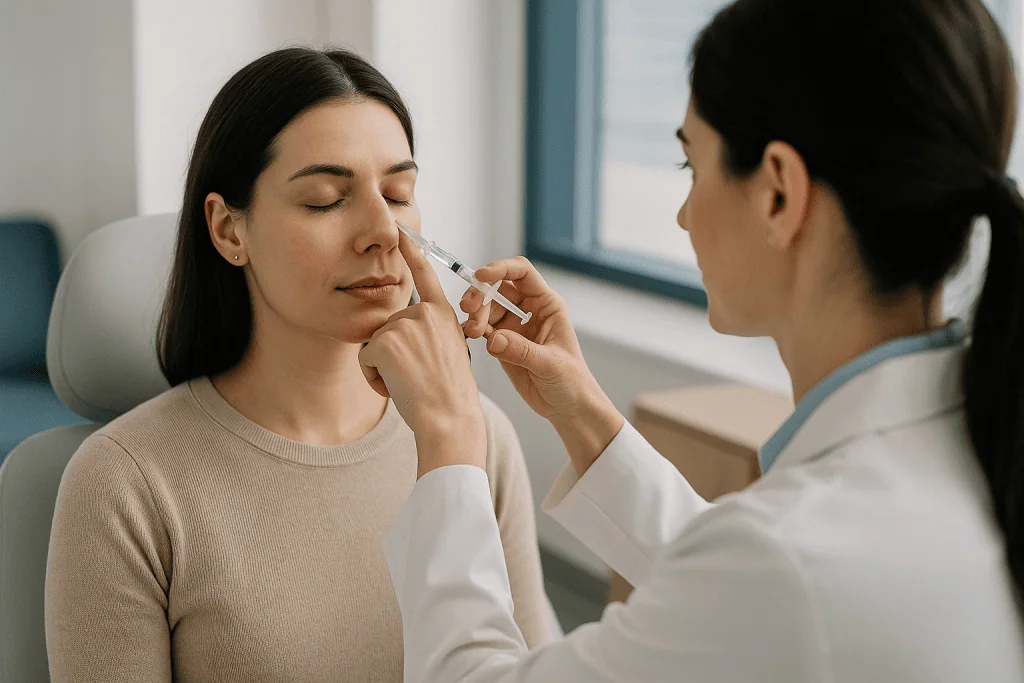
The clinician then places tiny amounts of gel in precise spots. To hide a dorsal hump, which is the bump along the bridge of the nose, filler is placed above and below the bump so the line from forehead to tip reads as straight. To lift a drooping tip, a small amount goes at the base of the columella, the strip of tissue between the nostrils, or at the tip itself. To correct a mild curve, gel fills the concave side. The nose is not made smaller; it is made to look straighter by adding, not removing.
Injectors typically work in the deep plane, meaning directly on top of the bone or cartilage rather than in the skin. That depth matters for two reasons. Deep placement gives a crisper, more natural contour because the gel is pressed firmly against a hard surface. It also keeps the needle or cannula (a thin, blunt-tipped tube some clinicians prefer to a sharp needle) away from the blood vessels that run closer to the skin surface.
You can see the result immediately, though what you see on day one includes a little swelling. In the United States, dermal fillers carry approvals for specific facial areas, and nasal use is generally considered off-label, meaning the clinician is applying an approved product in a way not listed on its label. That is legal and common in medicine, but it is worth understanding before you sign.
Why filler in the nose tends to outlast filler in the lips
The same syringe of gel can fade in eight months in the lips and hold its shape for more than a year on the bridge of the nose. The difference comes down to three things: movement, blood supply and pressure.
Movement is the big one. Hyaluronic acid filler is broken down by a naturally occurring enzyme called hyaluronidase, and the process is accelerated wherever tissue is constantly flexing. Lips speak, eat, kiss and purse thousands of times a day; the gel there is effectively kneaded. The bony bridge of the nose barely moves at all. The tip moves a little when you smile or wrinkle your nose, which is one reason tip corrections sometimes soften sooner than bridge corrections.
Blood supply matters too. Filler placed in richly vascular, soft tissue is exposed to more enzyme and more fluid exchange. Gel sitting directly against bone or cartilage, in a relatively tight compartment, is comparatively sheltered.
Pressure completes the picture. When gel is confined between firm tissue and the skin of the nose, which is thicker and less elastic than lip skin in most people, it stays compact rather than spreading out. A compact deposit keeps its visible effect longer than the same volume dispersed thinly.
There is an honest caveat. The general filler longevity figures from the NHS and Cleveland Clinic were not generated from nose-only studies, and the nose-specific case series that report longer persistence used different products, techniques and follow-up methods. The direction of the finding is consistent across those reports; the exact size of the advantage is not. What you can reasonably expect is that the nose will hold filler at least as long as the general 6-to-18-month range, and often toward the upper end of it.
What decides how long nose filler lasts for you
Two people can have the same product placed by the same clinician on the same afternoon and find that one profile has softened by month eight while the other looks unchanged at month fourteen. Several variables are doing the work.

The product. Hyaluronic acid gels differ in how tightly their molecules are cross-linked, a chemistry term for the bonds that turn a liquid into a cohesive gel. Cleveland Clinic notes that more cross-linked, firmer gels resist breakdown longer. Nose work usually calls for a firm gel that can hold a sharp line, which is one reason results there are relatively durable.
The amount and depth. Small, deeply placed deposits against bone persist better than superficial ones. Very small corrections can also appear to fade sooner, simply because a little loss of volume is a larger share of the total.
Your metabolism. People break hyaluronic acid down at different rates. Younger people, very lean people and regular high-intensity exercisers often report faster fading. This is widely observed in practice but not well quantified in trials, so treat it as a plausible pattern rather than a rule.
Whether it is a first or repeat treatment. Many clinicians observe that second and later sessions seem to last longer, possibly because residual gel and mild tissue response provide a scaffold. Again, that is clinical experience more than measured evidence.
Lifestyle. Smoking, heavy sun exposure and poor sleep affect skin quality generally, though direct evidence linking them to filler lifespan in the nose is thin.
Because so many of these factors are individual, the most reliable predictor of how long your second treatment lasts is how long your first one did. Keeping a dated photo at each stage is more useful than any average.
Non surgical nose job results timeline: the first days and weeks
The immediate result is visible before you leave the room, but the true result takes a couple of weeks to settle. Knowing the typical sequence helps you avoid judging the outcome too early or too harshly.
The first hours. Expect mild redness at the injection points and a sensation of firmness or pressure on the bridge. Some people see a small amount of swelling that makes the nose look slightly wider than it will. The NHS lists redness, swelling, bruising and tenderness as common, short-lived effects after any filler treatment.
Days one to three. Swelling usually peaks and then begins to recede. Bruising, if any, tends to appear now and can take a week or so to fade, as with a bruise anywhere else. Most people go straight back to work. Clinicians commonly advise avoiding heavy exercise, alcohol, saunas and firm pressure on the nose, including glasses that sit on the bridge, for a day or two; your own care team’s instructions take priority.
Weeks one to two. Residual swelling clears and the gel finishes integrating with the surrounding tissue. Cleveland Clinic advises that the final look of a filler treatment is best judged once swelling has fully resolved, typically within about two weeks. This is the point at which a review appointment makes sense, and when a clinician might place a tiny top-up if one side has settled differently.
Weeks two onward. The result should now look stable and feel like your own nose. Any lump you can see, rather than one you can only feel with a fingertip, is worth mentioning at review.
What you should not see in this timeline is worsening pain, skin that turns white or dusky, or any change in vision. Those are not part of normal settling and are covered in the section on when to call your doctor.
How often to redo nose filler: judging repeat timing
The instinct after a treatment you like is to book the next one before the last one fades. With nose filler, patience is usually the better strategy, and there are specific reasons why.
The first is that you cannot see what remains. Hyaluronic acid gel does not disappear evenly; it thins from the edges, and a fair amount can persist under the skin after the visible correction has softened. Adding a full second treatment on top of a half-present first one risks over-correction, a bridge that looks too high or a tip that appears heavy. Most clinicians therefore prefer to wait until the change is clearly returning, then add only what is needed to restore the line.
The second reason is safety. Each injection in the nose carries a small risk of entering a blood vessel, and scar tissue or residual gel from earlier sessions can make the anatomy slightly less predictable. Fewer, well-spaced sessions mean fewer opportunities for that rare event.
So what does typical repeat timing look like? Following the NHS and Cleveland Clinic ranges for hyaluronic acid filler, and the pattern in nose-specific case reports that results persist toward the longer end, many people find that a review at around 9 to 12 months is a sensible first checkpoint, with a top-up anywhere from that point to 18 months or beyond depending on how the profile looks. Some people are content with a smaller maintenance amount once a year; others go considerably longer, particularly after a second treatment.
The honest way to frame it: there is no calendar rule. The trigger for a repeat is a visible change you and your clinician both agree is worth treating, not an anniversary. If you are being encouraged to return on a fixed schedule regardless of appearance, that is a reasonable moment to ask why.
Does nose filler migrate or build up over time?
Two worries surface repeatedly in searches about repeat nose filler: that the gel will drift out of place, and that years of treatments will leave a nose permanently bulkier. Both deserve a straight answer.
Migration means filler moving from where it was placed to somewhere it was not. It is a recognized phenomenon with dermal fillers generally and is most often reported in the lips and around the eyes, where tissue is mobile and loose. In the nose, deep placement against bone and cartilage in a tight compartment makes true migration less common, but it is not impossible. Placing too much gel, injecting too superficially, or firm massage in the first days can push product sideways toward the cheeks or upward toward the space between the brows. A visible widening of the bridge that appears weeks after treatment should be reviewed rather than ignored.
The buildup concern is more nuanced. Hyaluronic acid is genuinely biodegradable, and Cleveland Clinic describes it as gradually absorbed by the body. Yet imaging studies of long-term filler users elsewhere in the face have found traces of gel persisting well beyond the expected window. The body sometimes walls off small deposits, and repeated treatments before full clearance can leave a cumulative reservoir. In the nose, that can show up as a bridge that slowly looks heavier or a tip that loses definition after several years of frequent top-ups.
Two practical habits reduce both risks. Wait until earlier filler has visibly faded before adding more, and ask your clinician to use the smallest amount that achieves the correction rather than a set volume. Because hyaluronic acid can be dissolved with an enzyme, neither migration nor mild buildup is usually permanent; that reversibility is covered in its own section below.
Liquid rhinoplasty vs surgical rhinoplasty: what each can and cannot do
Filler and surgery are not competing versions of the same treatment. They solve different problems, carry different risks and behave very differently over time. The table below draws on Mayo Clinic’s and Johns Hopkins’ descriptions of surgical rhinoplasty and on NHS and Cleveland Clinic guidance on dermal fillers.
| Feature | Liquid rhinoplasty (filler) | Surgical rhinoplasty |
|---|---|---|
| What it does | Adds volume to camouflage a bump, lift a tip or balance a mild curve | Reshapes bone and cartilage; can reduce size, narrow the nose, fix breathing |
| Can it make the nose smaller? | No | Yes |
| How long it lasts | Temporary; roughly 6–18 months, often longer in the nose | Permanent, though the nose continues to change with age |
| Anesthesia | Topical or local | Local with sedation or general |
| Downtime | Usually none to a few days of mild swelling or bruising | Splint about 1 week; most swelling settles over weeks, final shape up to a year |
| Reversible? | Yes, with hyaluronidase | Revision requires further surgery |
| Serious risks | Vascular occlusion, skin damage, rare vision loss | Bleeding, infection, breathing problems, need for revision |
A few points from the table deserve emphasis. Filler cannot shrink a large nose, narrow wide nostrils or repair a deviated septum that affects breathing; Mayo Clinic describes those as surgical goals. Conversely, surgery cannot be trialed and undone. For someone unsure whether they would like a straighter profile, a temporary, reversible option offers a preview that surgery cannot.
Longevity cuts both ways. A permanent surgical result is an advantage if you are certain; a temporary filler result is an advantage if you are not, or if you expect your preferences to change. Neither is the “better” choice in the abstract. The right one depends on what you want changed and how you weigh reversibility against durability, a conversation that belongs with a qualified treating team.
Who liquid rhinoplasty is usually for, and who is usually asked to wait
The people who tend to be well suited to nose filler share a specific kind of concern: a profile issue that can be improved by adding rather than removing. A modest dorsal hump, a slightly drooping or under-projected tip, a mild dip after previous surgery, or a small asymmetry all fall into that category. Filler also suits people who want to test a straighter profile before committing to surgery, or who cannot take time off for a surgical recovery.
Certain situations usually lead a clinician to suggest waiting, declining or choosing a different route.
- A nose that is already large or wide, where adding volume would make things worse.
- Breathing difficulty or a deviated septum, which filler cannot address and which Mayo Clinic identifies as surgical territory.
- Pregnancy or breastfeeding. Fillers have not been studied in these groups, and the NHS notes there is no safety data, so most clinicians defer treatment.
- Active skin infection, cold sores, acne flare or inflammation on or near the nose.
- A history of severe allergic reaction to filler ingredients, or certain autoimmune conditions where the treating team wants specialist input first.
- Recent surgical rhinoplasty. Scar tissue can alter blood flow and make injection riskier; many surgeons ask patients to wait a year or more, and that judgment belongs to the surgeon who knows the anatomy.
- Blood-thinning medicines. These raise bruising risk; never stop a prescribed medicine for a cosmetic treatment without the prescribing clinician’s advice.
- Under 18. The NHS advises against cosmetic fillers for minors, and in England it is unlawful to provide them to under-18s for cosmetic purposes.
Expectations matter as much as anatomy. Someone hoping for a dramatically smaller nose, or expecting the result to be permanent, is likely to be disappointed. A good consultation is partly about fit and partly about making sure the goal is one filler can actually reach.
The risks of nose filler and what "high-risk area" really means
Dermal fillers have a generally good safety record, but the nose is not the cheek. Clinicians describe it as a high-risk area, and it helps to understand precisely why rather than to be vaguely frightened or falsely reassured.
The reason is blood supply. The arteries that feed the skin of the nose connect, through a network of small vessels, to the arteries that supply the eye. If filler is injected into one of these vessels, or compresses one from outside, it can block blood flow. This is called vascular occlusion. When the blocked vessel feeds skin, the tissue can blanch, turn dusky purple and, if untreated, break down over days. When gel travels backward into the vessels of the eye, the result can be sudden loss of vision, which Harvard Health lists among the rare but serious complications of facial fillers. Occlusion events are uncommon, but published reviews of filler-related blindness consistently place the nose and the glabella (the area between the eyebrows) among the most frequently involved sites.
Other risks are less dramatic. The NHS lists infection, lumps under the skin, filler moving from its intended site, and allergic reaction. Bruising and swelling are common and short-lived. Late-onset nodules, small firm swellings appearing weeks or months later, occur occasionally and sometimes follow a viral illness or dental work; they are usually managed with the enzyme that dissolves hyaluronic acid.
Skin quality is a longer-term consideration. Repeated occlusion scares or over-filling can thin the skin over the bridge, and thin skin shows irregularities more readily.
What reduces risk is well established in clinical guidance: injection by a qualified, medically trained practitioner who knows the vascular anatomy, deep placement against bone, small volumes delivered slowly, and immediate access to hyaluronidase in the treatment room. Ask about all four before agreeing to proceed.
Can nose filler be dissolved? Hyaluronidase and reversibility
One of the strongest arguments for hyaluronic acid over other filler materials is that it can be undone. The tool for that is hyaluronidase, an enzyme that breaks the bonds in hyaluronic acid gel so the body can absorb it quickly. It is injected into the area where the filler sits, and it works fast: softening is often visible within hours, with the bulk of the effect over a day or two. Cleveland Clinic describes this reversibility as a distinctive feature of hyaluronic acid fillers.
Dissolving is used in three situations. The first is an emergency: suspected vascular occlusion, where the enzyme is given urgently to relieve the blockage. The second is correction of an unwanted result, whether over-filling, asymmetry, a visible lump or migration. The third is preparation for surgery, when a surgeon wants residual filler cleared before a rhinoplasty so the anatomy can be assessed accurately.
There are honest limitations. Hyaluronidase is not perfectly selective; it also breaks down some of the body’s own hyaluronic acid, which can leave the area looking temporarily deflated until natural levels recover over a few weeks. More than one session is sometimes needed for firmer gels. Allergic reactions to the enzyme are rare but possible, and clinicians often ask about bee-sting allergy because of a cross-reactivity concern. Dissolving cannot fix skin damage that has already occurred.
The enzyme is also why waiting to re-treat is safe rather than wasteful. If filler lingers longer than expected and you decide you preferred your original profile, or want to pursue surgery, the situation is recoverable. Non-hyaluronic acid fillers such as calcium-based or polymer-based products do not share this property, which is a central reason mainstream guidance favors hyaluronic acid for the nose.
What people often get wrong about how long liquid rhinoplasty lasts
Some beliefs about nose filler are repeated so often online that they have hardened into folklore. Here is how they stand up against the evidence.
“It’s permanent after a few sessions.” Hyaluronic acid is biodegradable. Residual gel can persist longer than the visible correction, and repeat treatments sometimes seem to last longer, but there is no evidence that filler becomes permanent. The correction still fades, and the NHS advises expecting to repeat treatment to maintain it.
“It only lasts six months, like lips.” The nose is one of the least mobile parts of the face, and case series consistently describe results outlasting lip filler. Six months is the low end of the general filler range, not the nose average.
“Filler makes the nose smaller.” It adds volume. It can make the nose look straighter, more refined and, through an optical effect, sometimes smaller in profile, but the physical nose is marginally larger. Reduction is surgical.
“Once it’s gone, the nose will look worse than before.” There is no good evidence that a single well-placed treatment stretches nasal skin or leaves lasting deformity. Repeated over-filling over years is a different matter and can affect skin quality.
“Any injector can do it; it’s just filler.” The nose’s link to the eye’s blood supply makes it one of the highest-risk filler sites. Training and anatomical knowledge are not optional extras.
“More filler lasts longer.” Larger volumes raise the risk of vascular compression, migration and an over-projected look without proportionately extending duration. Precision, not quantity, drives both safety and longevity.
“Massaging it helps it settle.” Firm pressure in the first days can displace gel. Follow your clinician’s instructions, which usually mean leaving the area alone.
Does the result change as the filler fades? Long-term considerations
Fading is rarely a cliff. Understanding how it unfolds, and what happens across years of intermittent treatment, helps set realistic expectations.
In the early months, the correction usually holds steady. Then, as the gel gradually thins, the first sign is often subtle: the bump you had camouflaged reappears faintly in certain lighting, or the tip settles a millimeter or two. Because the change is slow, many people do not notice until they compare photographs. That gradual quality is a feature; there is no sudden day when the nose reverts.
Bridge and tip do not always fade together. Gel placed against the stable bone of the bridge tends to last longest, while tip corrections, which sit on cartilage that moves with expression, can soften sooner. It is common for a review to find the bridge still well corrected but the tip due for a small refresh.
Over several years, the picture depends heavily on how treatment was paced. Someone who tops up only when a change becomes visible, with the smallest necessary amount, generally maintains a natural result with little cumulative effect. Someone treated frequently, before earlier gel has cleared, risks the slow buildup and skin thinning described earlier.
Aging adds its own layer. Mayo Clinic notes that the nose continues to change over a lifetime even after surgical rhinoplasty: the tip tends to droop slightly and the skin thins. Filler does not stop that process, and the correction that suited you in your twenties may need rethinking later.
Finally, a treatment that has faded is an opportunity as much as a loss. It is the moment to decide, with fresh eyes, whether you want to repeat, adjust, leave things be or consider a permanent option. The reversibility that makes nose filler appealing also means that decision never has to be rushed.
Questions to ask your care team before liquid rhinoplasty
A thorough consultation should leave you with answers, not a booking. These questions cover the points that most affect safety, longevity and your satisfaction, and a confident practitioner will welcome them.
- What are your medical qualifications, and how much of your practice involves the nose specifically?
- Is my concern one that adding volume can improve, or would I be better served by surgery or by leaving it alone?
- Which type of filler do you plan to use, and why is it suited to the nose? Is it hyaluronic acid?
- Do you keep hyaluronidase in the room, and have you managed a vascular occlusion before?
- How will you minimize the risk to blood vessels: needle or cannula, depth, volume, speed?
- What does a realistic result look like for my nose, and what can filler not achieve here?
- How long have your patients with similar noses typically kept their result, and how did you measure that?
- How will we decide when a repeat is appropriate rather than following a fixed schedule?
- What should I avoid in the first week, and when will you review me?
- What exactly should I do, and whom do I call, if the skin changes color or my vision changes after I leave?
- Are there medicines or supplements I take that you want to know about? (Never stop a prescribed medicine on your own initiative.)
- If I later want surgical rhinoplasty, how would this filler affect that, and how long would a surgeon want it cleared beforehand?
Take notes, or bring someone with you. Then leave without booking if you feel any pressure. The NHS encourages people to take time before any cosmetic procedure and to be wary of same-day offers or time-limited deals; a treatment you can safely have next month is not an emergency this week.
When to call your doctor after nose filler: red-flag signs
Most people experience nothing beyond a little tenderness and perhaps a bruise. A small number develop complications where minutes matter. Knowing the difference is the single most important piece of aftercare, and it should be printed on whatever you take home.
Seek emergency care immediately, or contact your injector’s emergency line if that is the faster route, if you notice:
- Sudden change in vision in either eye, including blurring, dark patches, double vision or loss of sight, even if it is brief.
- Skin on the nose or nearby that turns white, then blotchy, dusky purple or gray, or develops a lace-like pattern.
- Severe or escalating pain that seems out of proportion to the procedure, or pain that started after you left.
- Sudden severe headache, weakness on one side, difficulty speaking or drooping of the face, which could indicate a stroke.
- Signs of a serious allergic reaction: swelling of the lips, tongue or throat, difficulty breathing, hives spreading across the body.
These can indicate a blocked blood vessel or a systemic reaction, both of which need urgent treatment. Harvard Health and the NHS both identify vascular blockage and vision loss as the serious complications of facial filler for which prompt care is essential.
Call your treating clinician within a day or two, not urgently, for:
- Increasing redness, warmth, swelling or pus, or fever, which may signal infection.
- A visible lump, ridge or asymmetry that persists beyond two weeks of settling.
- Gradual widening of the bridge or a change in shape weeks after treatment, which could suggest migration.
- Cold-sore outbreak on or near the nose.
Trust your instincts. If something feels wrong and you cannot reach your injector, urgent care or an emergency department is the right choice. Skin and vision outcomes after occlusion depend heavily on how quickly treatment starts, and no one will criticize you for arriving with a false alarm.
Frequently asked questions
How long does liquid rhinoplasty last on average?
Most people keep a visible result for roughly 6 to 18 months, the general range the NHS and Cleveland Clinic give for hyaluronic acid fillers, and nose-specific case series often describe persistence toward or beyond the upper end. Longevity depends on the product, placement depth, amount used and individual metabolism. A first treatment is the best predictor of how long later ones will hold for you.
What is the typical non surgical nose job results timeline?
The change is visible immediately, but mild swelling and possible bruising affect the look for the first few days. Cleveland Clinic advises judging the final result once swelling has resolved, usually within about two weeks, which is when a review and any small adjustment make sense. After that the result should look stable for many months before gradually softening.
How often to redo nose filler?
There is no fixed schedule. Clinicians generally recommend waiting until the correction has visibly faded, which for many people means a review around 9 to 12 months and a top-up somewhere between that point and 18 months or later. Treating before earlier gel has cleared risks over-filling and cumulative buildup, so the trigger should be appearance, not an anniversary.
Does nose filler migrate?
It can, though it is less common in the nose than in the lips because gel is placed deep against bone in a tight compartment. Over-filling, superficial injection or firm pressure in the first days can push product toward the cheeks or between the brows. A bridge that looks wider weeks after treatment should be reviewed; hyaluronidase can dissolve displaced hyaluronic acid.
Can nose filler be dissolved if I don't like it?
Yes, if it is hyaluronic acid. An enzyme called hyaluronidase is injected into the area and breaks the gel down, with softening usually visible within hours to a couple of days. More than one session is sometimes needed for firm gels, and the enzyme also temporarily affects the body’s own hyaluronic acid. Non-hyaluronic fillers cannot be dissolved this way.
Does liquid rhinoplasty last longer the second time?
Many clinicians observe that second and later treatments seem to hold longer, possibly because residual gel and mild tissue response provide a scaffold for new filler. This is a pattern from clinical experience rather than a finding from controlled trials, so it is reasonable to hope for but not to count on. Waiting until the first result has faded before re-treating remains the safer approach.
Can filler make my nose smaller?
No. Filler works by adding volume to camouflage a bump, lift a tip or even out a curve, which can make the profile look straighter and sometimes visually more refined. The physical nose is marginally larger afterward. Reducing size, narrowing the bridge or nostrils, or correcting breathing problems requires surgical rhinoplasty, as Mayo Clinic describes.
Is liquid rhinoplasty safe?
Dermal fillers have a generally good safety record, but the nose is considered a higher-risk site because its blood vessels connect to those of the eye. Rare complications include blocked vessels causing skin damage and, very rarely, vision loss. Risk is reduced by treatment from a medically qualified injector who knows the anatomy, uses small volumes placed deep, and has hyaluronidase available immediately.
Can I have nose filler if I've had a surgical rhinoplasty?
Sometimes, and filler is occasionally used to smooth small irregularities after surgery. Scar tissue can change blood flow and make injection riskier, so many surgeons ask patients to wait a year or more after surgery and prefer to assess the nose themselves first. That decision sits with the surgeon who knows your anatomy and operative history.
What should I avoid after nose filler?
Clinicians commonly advise avoiding strenuous exercise, alcohol, saunas and firm pressure on the nose, including heavy glasses, for a day or two, and not massaging the area. Follow your own care team’s instructions over any general list. Any skin color change, severe pain or vision change is not normal aftercare and needs urgent assessment.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Facial Aesthetic Surgery Recovery: Head Elevation, Bruising Stages and Return to Work
Facial surgery recovery time runs on three overlapping clocks. Dressings, drains and sutures are usually dealt with within the first week; visible bruising and…

Natural-Looking Face Aesthetics Results: What Surgeons Mean by Balance Rather Than Change
Natural looking facial surgery results come from restoring a face's own proportions rather than reshaping them. Surgeons study how skin, fat, muscle and bone…

How Long Botox Lasts (Including Masseter Botox)
Cosmetic botulinum toxin injections, commonly called Botox, typically start working within a few days, reach full effect in about two weeks, and last roughly…

How Facial Implants Are Placed: Chin, Cheek and Jaw Incision Sites, Pockets and Fixation
Facial implants are placed through short incisions hidden inside the mouth or under the chin, then slid into a precisely sized space, called a…

How Ethnic Rhinoplasty Differs Surgically: Grafts for Support, Tip Refinement and Nostrils
Ethnic rhinoplasty differs from classic reduction rhinoplasty mainly in what it adds rather than removes. Surgeons often build a stronger internal framework with cartilage…

What Does Forehead Lift Recovery Involve? Stitches or Clips, Swelling and Return to Work
Forehead lift recovery time usually runs one to two weeks for the visible phase. Patient education from Mayo Clinic and MedlinePlus describes swelling and…