

How Long Does Mommy Makeover Surgery Take? Anesthesia, Sequence and Time in the Operating Room

Key Takeaways
- NHS guidance gives 2 to 5 hours for a tummy tuck, 2 to 3 hours for a breast lift and 1 to 3 hours for liposuction; a combined session shares setup time, so the total is less than the raw sum but longer than any single procedure.
- The operating estimate on your consent form excludes preparation, anesthesia induction and monitored recovery, so the full day away is considerably longer than the surgical figure.
- Combining procedures saves one anesthetic and one recovery period but does not shorten operating time, and longer operations carry incrementally higher risks of clots and wound-healing problems.
- Mayo Clinic lists a body mass index above 30, current smoking, planned future pregnancy, planned major weight loss and poorly controlled chronic disease as reasons a surgeon may advise waiting.
- The commonly cited recovery period for a tummy tuck is about six weeks, during which a compression garment is usually worn and heavy lifting, including a toddler, is restricted.
- Pain after a mommy makeover comes mainly from the abdominal muscle repair, peaks in the first two to three days, and is managed with layered plans that combine local anesthetic, nerve blocks and scheduled medicines decided by the prescribing clinician.
A mommy makeover usually takes several hours under general anesthesia because it combines two or more operations in one session. NHS guidance gives 2 to 5 hours for a tummy tuck alone, 2 to 3 hours for a breast lift and 1 to 3 hours for liposuction; combined procedures share setup and anesthesia time, so the total depends on which elements are included and is set by the surgical team.
The consent form is three pages long, and she has read it twice. The part she keeps returning to is not the list of risks. It is the blank where the operation’s expected duration is written, because that number tells her how long her partner will sit in a waiting room, how long her mother will have the kids, and how long her own body will be somewhere she cannot follow it.
So the question people type at midnight, how long does a mommy makeover take, is really several questions stacked together. How long is the surgery itself? How long is the anesthesia? How long before she is awake, home, walking, driving, lifting a toddler?
The honest answer starts with arithmetic, because a mommy makeover is not one procedure. It is a package, and each item in it carries its own clock.
How long does a mommy makeover take in the operating room?
There is no single figure, because “mommy makeover” is a marketing phrase, not a surgical code. It typically bundles an abdominoplasty (a tummy tuck, which removes loose abdominal skin and tightens the muscle wall), a breast lift or augmentation, and often liposuction (suction removal of fat through small tubes). The time in the operating room is roughly the sum of those parts, minus the setup they share.
Published ranges for the individual pieces are the most reliable place to anchor expectations:
| Component | Typical operating time (NHS) | What drives the variation |
|---|---|---|
| Tummy tuck (full abdominoplasty) | 2 to 5 hours | Amount of skin removed, whether muscles are repaired, navel repositioning |
| Breast lift (mastopexy) | 2 to 3 hours | Incision pattern, whether an implant is added at the same time |
| Liposuction | 1 to 3 hours | Number of areas treated and volume removed |
Add the low ends and you get about 5 hours; add the high ends and you get 11. Neither extreme is a realistic combined figure. Combined operations share one anesthesia induction, one set of drapes and one positioning, and liposuction is often done as part of the tummy tuck rather than as a separate stage. Surgical teams generally plan combined sessions in the middle of that arithmetic, and the number written on your consent form will reflect your specific plan.
Two things matter more than the headline number. First, the figure your surgeon quotes is the time between the first incision and the last stitch, not the time you are away from your family; anesthesia, preparation and recovery add hours on either side. Second, a longer operation is not a better one. The time should be whatever the work requires, and nothing more.
What actually happens during the operation, step by step
Picture the day as a series of rooms rather than a single event.
The first is a preoperative bay. A nurse checks identity, allergies and fasting, an intravenous line goes in, and the surgeon arrives with a marker. The skin markings drawn while you stand are a map of where tissue will be removed and how the breasts will be reshaped; they cannot be drawn accurately once you are lying flat, so this step happens before any medication. Marking can take a surprising amount of time, and it is time well spent.
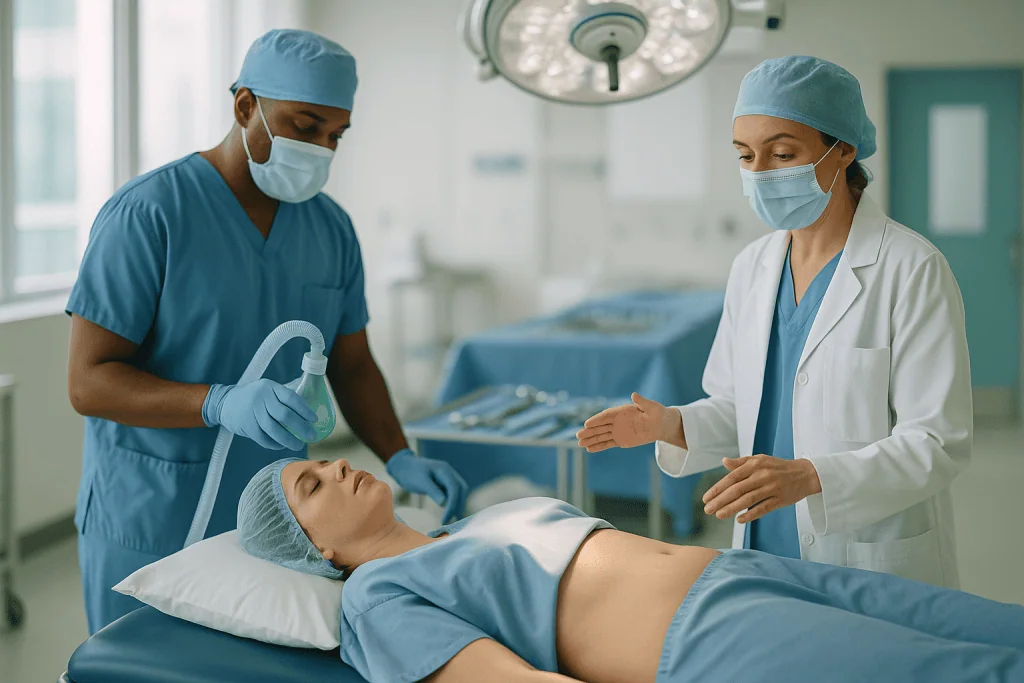
The second room is the operating theater. The anesthesia team puts you to sleep, secures your airway, and places monitors for heart rhythm, blood pressure and oxygen. Compression devices are wrapped around your calves to keep blood moving. Only then is the skin cleaned and draped.
The surgical work follows in a sequence decided in advance. For the abdomen, the surgeon makes a low horizontal incision, frees the skin from the underlying muscle, stitches the separated rectus muscles back toward the midline if needed, removes the excess skin, and rebuilds the navel in its new position. Mayo Clinic describes this as the core of a tummy tuck, and it is usually the longest single element. For the breasts, the surgeon removes excess skin, repositions the nipple and areola, and reshapes the tissue; an implant, if planned, is placed during the same steps. Liposuction, when included, uses small incisions and a hollow tube to remove fat from the flanks or hips.
Drains may be placed, incisions are closed in layers, and a compression garment goes on. The third room is recovery, where you wake up. The fourth, for many people, is an overnight bed.
Mommy makeover anesthesia: what "asleep" really means
Almost all combined body-contouring operations are done under general anesthesia, a medically controlled state of unconsciousness in which you feel nothing, remember nothing and breathe with support. According to Mayo Clinic, the anesthesiologist delivers medication through the intravenous line or a mask, places a breathing tube or airway device once you are asleep, and adjusts the drugs continuously throughout the operation while monitoring your vital signs.
People often ask whether hours of anesthesia are harmful in themselves. The honest answer is that duration matters mainly through what it does to the body around it: longer immobility, more fluid shifts, a cooler core temperature, and more time for blood to pool in the legs. Anesthesia teams counter each of these actively with warming blankets, careful fluid management, calf compression and positioning. For a healthy adult, the planned length of a combined operation is a routine part of the pre-anesthesia assessment rather than a reason for alarm.
That assessment is where duration becomes personal. The anesthesiologist will want to know about sleep apnea, reflux, previous reactions to anesthesia, current medicines and supplements, and how far you live from the hospital. Some of these answers change the plan; a few of them lead to a recommendation to stage the procedures over two dates instead of one.
Waking up is gradual. Mayo Clinic notes that grogginess, a sore throat from the airway device, nausea and shivering are common in the first hours and usually settle. Pain control typically begins before you wake, often through a combination approach: local anesthetic infiltrated into the surgical site, a regional nerve block around the abdominal wall, and non-opioid medicines, with stronger medicines reserved for breakthrough pain. Which of those are used, and for how long, is a prescribing decision that belongs to your team.
Why surgeons order the steps the way they do
The sequence of a combined operation is not arbitrary, and understanding it explains a good deal of the timing.

Many surgeons begin with the breasts. The patient is positioned on her back with the arms out, the chest is worked on first, and the incisions are closed and dressed before the abdomen is opened. The logic is practical: breast surgery benefits from a symmetric, undisturbed torso, and finishing it first avoids repositioning later. Others start with the abdomen because it is the longest and most physically demanding part, and they prefer to do it while the team is freshest. Both approaches are standard; neither is right for everyone.
Liposuction usually threads through the tummy tuck rather than standing alone. Suctioning the flanks before the abdominal skin is lifted improves the contour of the final result and rarely adds much to the clock.
A few principles shape the order almost everywhere:
- Positioning changes cost time and carry small risks, so surgeons group steps by body position.
- Areas where bleeding is a concern are addressed while blood pressure is most stable, typically early.
- Steps that require sitting the patient upright on the table, such as checking breast symmetry, are timed so they do not disturb fresh abdominal closure.
You are entitled to ask your surgeon what order they plan and why. The answer will tell you something about how they think, and it will make the hours your family spends waiting feel less like a black box. It also explains why an update from the theater that says “they have finished the breasts” can arrive at very different points in two apparently identical operations.
Tummy tuck and breast lift together: does combining save time?
Yes and no, and the distinction is worth being precise about.
Combining a tummy tuck and breast lift into one session saves time in the sense that most people mean it. There is one anesthesia induction instead of two, one recovery-room stay, one set of preoperative tests and one block of time off work. Both operations heal in parallel, so the roughly six weeks of restricted activity that NHS guidance describes for a tummy tuck also covers the breast recovery.
It does not save operating time. The combined operation is longer than either alone, and the total time under anesthesia is close to the sum of the parts. Longer procedures are, as a general principle in surgery, associated with more blood loss, more cooling, and a higher chance of complications such as clots and wound-healing problems. That is why surgeons and anesthesiologists set limits on how much they will do in one sitting, and why the limits are stricter for people with additional health conditions.
Staging, meaning doing the operations on separate dates, is the alternative. It is more commonly recommended when:
- the planned work would push the operation well beyond the usual range;
- a medical condition makes a long anesthetic less desirable;
- large-volume liposuction is planned alongside a full abdominoplasty;
- the person prefers two shorter recoveries to one long one.
Neither approach is inherently safer for every patient. A shorter combined operation in a healthy person may carry less overall risk than two staged ones; a very long combined operation in someone with risk factors may not. The decision sits with the surgical and anesthesia team, and it is one of the most important conversations of the consultation.
Who a mommy makeover is usually for, and who is asked to wait
Body-contouring surgery treats changes that diet and exercise cannot reverse: skin that has lost its elasticity, abdominal muscles that separated during pregnancy and did not close, and breast tissue that has descended after breastfeeding. It does not treat weight itself, and it is not a substitute for weight loss.
Mayo Clinic’s guidance on tummy tuck describes the profile of a person who is usually considered a reasonable candidate: at a stable weight, not planning significant further weight loss, not planning future pregnancy, a non-smoker, and without chronic conditions that impair healing. The same guidance lists reasons a surgeon might advise waiting or declining altogether, and they apply across the whole package:
- a plan to lose a large amount of weight, because the skin envelope will change again;
- a possible future pregnancy, which can stretch repaired muscles and skin;
- a body mass index above 30, which raises wound and clot risk;
- current smoking, which restricts blood flow to healing tissue;
- previous abdominal surgery with significant scarring;
- a chronic condition such as diabetes or heart disease that is not well controlled.
Timing after childbirth deserves a plain word. Surgeons generally prefer that breastfeeding has finished and that the breasts and abdomen have settled, and that the person is back to a weight they can maintain. There is no universal number of months for this; the right interval depends on how the body has recovered and on the person’s own plans.
None of these criteria are moral judgments. They are predictions about healing, and a surgeon who asks you to wait is usually protecting the result as much as your safety.
Recovery room to discharge: the hours after the last stitch
The operating time is only the middle of the day. Add the hour or more of preparation before it and the hours of monitored recovery after it, and the total time from arrival to leaving the recovery area is considerably longer than the surgical figure your consent form quotes. Families are often told a start time and an operating estimate, then surprised when the first news takes longer to arrive. Build slack into the plan.
In the recovery room, nurses check your breathing, blood pressure, temperature, pain level, dressings and drains at short intervals. You will be encouraged to take deep breaths and to move your feet and ankles almost immediately; both are clot-prevention basics rather than optional extras. Nausea is treated as it arises. Most people are propped in a slightly bent position at the hips to keep tension off the abdominal closure, which is why the first attempts at standing feel like folding a lawn chair.
Whether you go home the same day or stay overnight depends on the length of the operation, how much was done, how you recover from the anesthetic and how far you live from care. NHS guidance describes a hospital stay of at least one night as usual after a tummy tuck, and combined procedures often follow the same pattern. Same-day discharge after smaller combined operations is possible in some settings but is a clinical judgment made on the day.
You will not be permitted to drive yourself, and most teams ask that an adult stays with you for the first night at home. Before discharge, someone should show you and your companion how to empty and record any drains and what the dressings should look like.
Mommy makeover recovery timeline: the first days and weeks
Timelines are ranges, not promises, and your team’s instructions override anything written here. Even so, the shape of recovery is consistent enough to describe.
The first three days are about basics: short walks around the house every couple of hours, staying hunched at the hips, keeping the compression garment on, and managing drains if you have them. Mayo Clinic notes that drains are commonly left in place for several days after a tummy tuck. Swelling and bruising peak in this window, and the abdomen and breasts feel tight rather than sharply painful once the initial soreness eases.
By the end of the first week most people are standing straighter, sleeping in slightly longer stretches, and taking fewer prescription medicines. The second week usually brings a follow-up visit, drain removal if it has not already happened, and clearance for light activity such as longer walks.
The six-week mark is the milestone that appears in most guidance. NHS advises that it takes about six weeks to recover from a tummy tuck, and Mayo Clinic describes wearing the support garment for around the same period and avoiding strenuous activity until then. Returning to desk work typically happens earlier than that, and physically demanding work later; your surgeon will give you a date based on what was done.
Lifting deserves its own line, because the person asking this question often has a small child. Lifting anything heavier than a few kilograms, including a toddler, is usually restricted for weeks, and arranging help for that period is not a luxury. Driving is allowed once you can sit comfortably in a seat belt and perform an emergency stop without pain, which NHS guidance places at a few weeks, and your insurer may have its own requirements.
How painful is a mommy makeover? An honest answer to the 1-to-10 question
People want a number, and surgeons are reluctant to give one, because pain after this operation is genuinely individual. What can be said with confidence is where the pain comes from, how it changes, and what makes it better or worse.
The muscle repair in a tummy tuck is the main source. Stitching the separated abdominal muscles back to the midline creates a deep, tight ache that is felt most when moving from lying to sitting, coughing, laughing or straightening up. The skin incisions themselves are usually less troublesome, partly because the nerves in the lifted skin are temporarily numb, a change in sensation that Mayo Clinic lists among expected effects and that often takes months to resolve. Breast surgery tends to produce soreness and pressure rather than sharp pain, and liposuction leaves an ache that many people compare to a deep bruise.
The pattern is more useful than a score. The worst period is typically the first two to three days, with a steady easing over the first week and a shift from pain to tightness and stiffness by the second. People who had a muscle repair generally report more discomfort than those who did not; people who had liposuction alongside report more widespread bruising.
Modern pain plans are built in layers so that no single medicine has to do all the work: local anesthetic placed during surgery, sometimes a nerve block that numbs the abdominal wall for many hours, scheduled non-opioid medicines, and stronger medicines held in reserve. Which layers you receive, in what amounts and for how long, is decided by the prescribing clinician, and any change to that plan should go through them.
Two non-drug measures matter as much as any prescription: walking early and often, and keeping the garment on. Both reduce swelling, and swelling is a large part of what hurts.
Does a longer operation raise the risk? Clots, healing and time
Duration is a risk factor in its own right, and pretending otherwise would not serve anyone. The relationship is not a cliff but a slope: each additional hour of anesthesia and immobility adds a little to several risks at once.
Blood clots are the concern surgeons take most seriously. Lying still for hours slows blood flow in the leg veins, surgery activates clotting, and the bent-hip position after a tummy tuck compresses the veins behind the knee. The countermeasures are standard: calf compression devices during the operation, early walking afterwards, and in some cases an injectable or oral anticoagulant (a medicine that reduces the blood’s ability to clot) for a period after surgery. Whether you receive one, and for how long, depends on your individual risk assessment and is a decision for your team.
Wound healing is the second. Mayo Clinic lists fluid collection under the skin (seroma), poor wound healing, unexpected scarring, tissue damage and changes in skin sensation among the risks of tummy tuck. Longer operations mean more tissue disturbance and more cooling, both of which can slow healing at the incision edges. Smoking multiplies this risk considerably, which is why surgeons insist on stopping well beforehand.
Bleeding, infection and anesthesia-related events complete the list. None of these is unique to combined surgery, but the odds shift upward with duration, with body mass index and with underlying illness.
This is the evidence behind a surgeon’s decision to limit what is done in one sitting. The right question is not “how much can be done at once?” but “how much can be done at once safely for me?” A shorter plan is sometimes the better plan, and a team that says so is doing its job.
What's the best age for a tummy tuck, and how many sizes will you drop?
These two questions arrive together so often that they deserve one answer, because both are asking for a number the evidence cannot supply.
There is no best age for a tummy tuck. The criteria that matter are stage-of-life and health rather than years: finished with pregnancies, at a stable weight, not smoking, and without conditions that impair healing. A person in her late twenties who meets those criteria may be a more suitable candidate than one in her forties who does not, and the reverse is equally true. Skin elasticity does decline with age, which can affect how the result settles, but that is one variable among many and not a cutoff. Surgeons do become more cautious about long combined operations as cardiovascular and other risks rise with age, which again points toward staging rather than exclusion.
Clothing sizes are an even less reliable target. A tummy tuck removes skin and, to a modest degree, fat; it is not a weight-loss operation, and the amount of tissue removed varies enormously from person to person. Clothing sizes are not standardized between manufacturers, and how a waistband fits depends on fat under the muscle wall that surgery does not touch. Some people find their clothes fit differently at the waist; others change little in size but a great deal in shape. Any specific promise about sizes dropped is a marketing claim, not a clinical one.
What surgery can reasonably be expected to change is contour: a flatter abdominal wall where the muscles have been repaired, removal of the overhanging skin fold, and a breast shape that sits higher on the chest. Whether that translates into a different number on a label is beside the point, and a good consultation will steer the conversation back to shape, function and realistic expectations.
What people often get wrong about how long a mommy makeover takes
Several durable myths circulate about this operation, and correcting them changes how people plan.
“Longer surgery means a more thorough result.” It does not. Operating time reflects how much work is required and how the surgeon works, not quality. A faster surgeon is not cutting corners and a slower one is not being more careful; both are working at the pace the tissue and their technique demand.
“The surgery time is the time I’ll be away.” The operating estimate excludes preparation, anesthesia induction, wake-up and monitored recovery. Families should expect the full day.
“Everything can be done at once if I’m healthy.” Health lowers risk but does not remove the effect of duration. Surgical and anesthesia teams set limits on total operating time for good reasons, and a request to stage is not a sign that something is wrong with you.
“Recovery is a week or two.” The commonly cited figure for tummy tuck recovery in NHS guidance is about six weeks, and that is for the physical restrictions alone. Swelling continues to settle for months, and Mayo Clinic notes that scars fade over a long period but do not disappear.
“Pain is the same for everyone.” Pain after muscle repair differs sharply from pain after skin-only procedures, and people with liposuction report more diffuse bruising. Comparing your experience to a stranger’s online account is rarely helpful.
“Once the drains are out, I’m done.” Drain removal is a milestone, not a finish line. The activity restrictions that protect the muscle repair and the breast incisions continue well beyond it.
A plan built on the realistic version of each of these tends to go more smoothly than one built on the myth.
Questions to ask your care team before you sign
The consultation is the moment to trade vague reassurance for specifics. These questions are designed to produce answers you can act on.
- What exactly is included in my plan, and what is your estimated operating time for that combination?
- In what order will you do the procedures, and why that order for me?
- Will an anesthesiologist assess me beforehand, and what would make you recommend staging instead of one session?
- What will you do during and after surgery to reduce my clot risk, and does my history change that plan?
- Will I stay overnight, and what would prompt a longer stay?
- Will I have drains, and how will I be taught to manage them?
- How will my pain be managed, which layers of the plan are prescribed, and who do I contact if it is not controlled?
- When can I lift my child, drive, return to my particular job and exercise?
- What are the most common complications you see with this combination, and how are they managed?
- How do I reach the team out of hours in the first two weeks?
- What should the incisions and drains look like on day three, day seven and day fourteen?
- What would make you advise waiting or not proceeding?
Write the answers down or bring someone who will. The estimated operating time, the discharge plan and the out-of-hours contact are the three pieces of information your household most needs, and they are easiest to lose in a conversation that also covers risks and expectations.
Note the tone of the answers as well as their content. A team that discusses duration, staging and limits without prompting is telling you it takes those questions seriously, which is exactly what you want from the people who will be responsible for you while you are asleep.
When to call your doctor
Most recoveries are uneventful, and most surprises turn out to be ordinary swelling or bruising. A small number of signs, though, should prompt a call to your surgical team the same day or a visit to emergency care, because they can indicate a clot, a bleed or an infection that needs treatment quickly.
Contact emergency services or go to the nearest emergency department if you have:
- sudden shortness of breath, chest pain, or coughing up blood, which can signal a clot that has traveled to the lungs;
- fainting, a racing heartbeat, or feeling as though you might pass out;
- a rapidly enlarging, tense, painful swelling at the abdomen or a breast, which can indicate bleeding under the skin.
Call your surgical team promptly, including out of hours, if you notice:
- pain, swelling, warmth or tenderness in one calf, especially if one leg is larger than the other;
- fever, chills, or feeling generally unwell;
- spreading redness, increasing warmth, or a foul-smelling or cloudy discharge from an incision;
- an incision edge that separates or a wound that looks dark or dusky;
- drain output that changes suddenly in volume or becomes bright red;
- pain that is escalating rather than easing after the first few days, or that is not controlled by the plan you were given;
- persistent nausea, inability to keep fluids down, or not passing urine.
Do not adjust, stop or restart any prescribed medicine, including anticoagulants or pain medicines, without speaking to the prescribing clinician. Keep the out-of-hours number somewhere visible, and err on the side of calling; teams would far rather hear about a false alarm than miss an early sign. Every decision about your care, from the length of the operation to the timing of your return to normal life, belongs with the team that knows your history.
Frequently asked questions
How long does a mommy makeover take under anesthesia in total?
Longer than the operating time alone. Anesthesia begins before the first incision and continues until closure, and the monitored wake-up period follows. Using NHS ranges for the components, a combined tummy tuck and breast lift session commonly runs several hours; your anesthesiologist will give a figure specific to your plan and will factor that duration into the pre-anesthesia assessment.
On a scale of 1 to 10, how painful is a tummy tuck?
There is no reliable universal number, because pain depends heavily on whether the abdominal muscles were repaired and on the individual. The deep, tight ache from muscle repair is usually the dominant sensation, worst in the first two to three days and easing over the first week. Layered pain plans, early walking and the compression garment all reduce it; the specific medicines are decided by your prescribing clinician.
How painful is a mommy makeover compared with a tummy tuck alone?
Breast surgery generally adds soreness and pressure rather than sharp pain, and liposuction adds a diffuse bruised feeling, so a combined operation produces discomfort in more places rather than dramatically more intense pain. The abdominal muscle repair remains the main source. Because both areas heal at once, most people find the overall recovery follows the same six-week pattern described for a tummy tuck.
What is the best age for a tummy tuck?
There is no best age. Surgeons look at life stage and health rather than years: finished with pregnancies, at a stable weight, not smoking, and without conditions that impair healing. Skin elasticity declines with age and cardiovascular risk rises, which can influence how much is done in one session, but neither sets a cutoff. Candidacy is an individual judgment by the treating team.
How many sizes do you go down after a mommy makeover?
No honest number exists. The operation removes loose skin and some fat and repairs the muscle wall; it does not remove fat beneath the muscles or change weight meaningfully, and clothing sizes are not standardized. Some people find their waistbands fit differently, others see a change in shape more than size. Any specific promise about sizes dropped should be treated as marketing rather than clinical information.
Is it safe to have a tummy tuck and breast lift together?
For a healthy person at a stable weight, combining the two is a standard approach, but it does lengthen the operation, and longer surgery carries incrementally higher risks of clots and healing problems. Surgeons and anesthesiologists set limits on total operating time and may recommend staging when the plan is large or when health conditions add risk. The decision is made individually by the surgical team.
Will I stay in the hospital overnight after a mommy makeover?
Often, yes. NHS guidance describes a hospital stay of at least one night as usual after a tummy tuck alone, and combined procedures frequently follow the same pattern. Same-day discharge is possible after smaller combinations in some settings but is a clinical judgment made on the day, based on how the operation went, how you recover from the anesthetic and how far you live from care.
What does the mommy makeover recovery timeline look like week by week?
The first few days are about short walks, the compression garment and drain care, with swelling peaking. By the end of week one most people stand straighter and need fewer medicines; week two typically brings drain removal and light activity. NHS guidance places overall recovery from a tummy tuck at about six weeks, when strenuous activity and heavy lifting are usually cleared. Swelling keeps settling for months.
How long before I can drive after a mommy makeover?
NHS guidance suggests a few weeks after a tummy tuck, and the practical test is whether you can sit comfortably in a seat belt, turn to check mirrors and perform an emergency stop without pain. You should also no longer be taking medicines that impair alertness. Your surgeon will confirm the timing, and some insurers have their own requirements worth checking beforehand.
Does a longer mommy makeover operation mean more scarring?
Not directly. Scar length is determined by how much skin is removed and which incision patterns are used, not by how long the surgeon takes. What duration can affect is wound healing at the incision edges, because longer operations involve more tissue disturbance and cooling. Mayo Clinic notes that scars fade over a long period but remain permanent, and smoking is a far stronger influence on scar quality than operating time.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Does CoolSculpting (Cryolipolysis) Work? What Controlled Cooling Does to Fat Cells
CoolSculpting is the trade name for cryolipolysis, a non-surgical procedure that cools a pinch of fat through the skin. Fat cells are more sensitive…

BBL Pillow: How Sitting Works After a Brazilian Butt Lift (and for How Long)
A BBL pillow is a firm cushion placed under the thighs so a person recovering from a Brazilian butt lift can sit without putting…

Seroma After Tummy Tuck: Signs, Drainage and When to Call Your Surgeon
A seroma after a tummy tuck is a pocket of clear, straw-colored fluid that collects under the abdominal skin, usually within the first few…

Trim vs Wedge Labiaplasty: How Each Technique Handles Edge, Color and Scar Position
Trim labiaplasty removes the outer free edge of the labia minora along a line, so the scar runs along the new border and the…

Fibrosis After Liposuction: Why Hard Lumps Form and How They Are Managed
Hard lumps after liposuction are usually fibrosis: firm bands or nodules of scar tissue that form under the skin as the treated area heals.…

Drainless Tummy Tuck: How the No-Drain Technique Works and Who It Suits
A drainless tummy tuck is an abdominoplasty performed with progressive tension, or quilting, sutures that anchor the abdominal skin flap to the muscle layer,…