

How to Read a Longevity Report: Cardiovascular, Metabolic and Cancer Risk Markers Explained
Key Takeaways
- Lipoprotein(a) is largely set by genes, changes little with diet and usually needs measuring only once, which makes it one of the few truly new pieces of information on a longevity panel.
- Hemoglobin A1C reflects average blood sugar over the previous two to three months, with 5.7–6.4% indicating prediabetes and 6.5% or higher on two tests indicating diabetes.
- Across a fifty-marker panel, a healthy person can expect two or three results outside the reference range by chance alone, which is why repeat testing matters more than a single flag.
- Tumor markers such as CA-125 and CEA are designed to monitor people already diagnosed with cancer and perform poorly as screening tests in healthy adults.
- A coronary artery calcium score of zero in someone without symptoms is reassuring, while a high score can reveal plaque even when cholesterol looks normal.
- The population gains in US life expectancy over the past half century came mostly from controlling blood pressure, cholesterol and smoking, not from any marker in the research-grade section of a report.
A longevity report explained simply is a bundle of standard laboratory tests, blood pressure readings and sometimes imaging, grouped into cardiovascular, metabolic and cancer risk categories and compared against population reference ranges. It can show where your risk is drifting, but it cannot predict your lifespan, diagnose disease or replace guideline-based screening, so results should always be interpreted with your treating clinician.
The envelope arrives thicker than a normal lab slip. Twelve pages, three traffic-light dashboards, a number that claims to be your “biological age”, and a line at the bottom that says your inflammation marker is amber. You sit at the kitchen table with a cup of coffee going cold and realize you have no idea whether to be relieved or worried.
That scene is now common. Longevity panels have moved from boutique physician offices into employer wellness programs and direct-to-consumer kits, and the reports they generate can run to fifty separate values. Most are ordinary tests your family physician has ordered for decades; a few are newer and still being studied. The design of the report, with its colored bands and percentile bars, can make all of them look equally important. They are not.
This guide walks through a typical longevity report explained marker by marker: what each number measures, how strong the evidence behind it is, and which results genuinely deserve a conversation with your care team.
What is a longevity report, and what does it actually measure?
Strip away the branding and a longevity report is a results summary. It gathers values from a blood draw, a urine sample, a blood pressure cuff and sometimes a body-composition scan or an imaging study, then sorts them into themes: heart and vessels, sugar and fat metabolism, inflammation, organ function, hormones, and cancer-related markers. A software layer compares each value with a reference range and often adds a composite score.
Two things are worth understanding before reading any individual value. First, the word “longevity” in the title is a framing choice, not a measurement. No blood test measures lifespan. What the panel measures is current physiology: how much low-density lipoprotein (LDL, the cholesterol-carrying particle most strongly linked to artery plaque) is circulating, how your average blood sugar has behaved over the past two to three months, whether your kidneys are filtering at the expected rate. These are risk markers, meaning they correlate with future disease across large populations. They do not tell one person what will happen to them.
Second, reference ranges come from the middle 95% of a healthy population, which is a statistical convention rather than a judgment about you. A value just outside the range is often noise; a value far outside it, or one that is moving steadily in the wrong direction across repeated tests, is a signal. Many reports also add a narrower “optimal” band. Some of those bands reflect published guideline targets; others reflect a company’s opinion. The report rarely tells you which is which, so part of reading one well is learning where the mainstream evidence ends.
The sections that follow take each category in turn, starting with the markers that carry the most weight in guideline-based prevention and ending with the ones still in the research phase.
How a longevity report is built: what actually happens from blood draw to dashboard
The process begins the night before, which surprises people. Several metabolic markers are meant to be measured after an overnight fast of roughly 8–12 hours, because a recent meal raises triglycerides (the main form of fat carried in blood) and glucose. A report that mixes fasting and non-fasting values without saying so will look alarming for the wrong reasons. Hydration, a hard workout the day before, a cold, poor sleep and even the time of day shift certain results; cortisol and testosterone, for instance, peak in the morning.
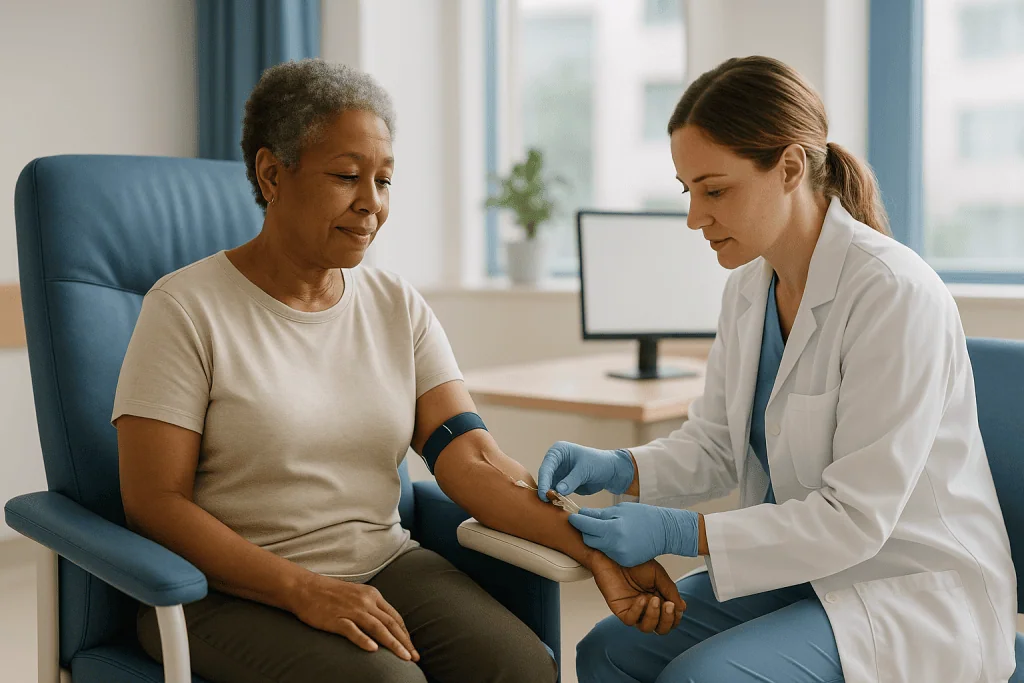
At the draw itself, a phlebotomist fills several tubes. Different colored caps contain different preservatives, because a test for glucose needs the sugar frozen in time while a test for clotting needs the blood kept liquid. The tubes travel to a laboratory where automated analyzers run chemistry panels in minutes, while specialized tests such as lipoprotein(a) or an epigenetic clock may be sent to a separate facility and take days or weeks.
The results return as raw numbers with units. A longevity platform then applies three layers of interpretation. The first is the laboratory reference range. The second is a guideline threshold, such as the hemoglobin A1C cut-points used by the Mayo Clinic and CDC to define prediabetes and diabetes. The third is a proprietary scoring system that may blend dozens of markers into a single “biological age” or risk score. Only the first two layers have broad clinical validation.
Finally, someone writes the summary. In physician-led programs that person is a clinician who has your history; in consumer kits it may be an algorithm with a template. Knowing which you received changes how much weight the narrative deserves. The numbers are the same either way; the commentary is not.
Who a longevity report is usually for, and who is usually asked to wait
Most of the core markers belong to routine preventive care, which is why guideline bodies already recommend them on a schedule. Adults from early middle age onward typically have cholesterol, blood pressure and blood sugar checked periodically; people with a family history of early heart disease, diabetes or certain cancers may be offered more. A longevity panel essentially pulls those checks forward into one visit and adds extras. For a healthy adult who has not had a check-up in years, the core of the panel can be genuinely useful as a baseline.
Some people are usually asked to wait or to test differently. Anyone who is acutely unwell, recovering from surgery or infection, or within a few weeks of a significant illness will show raised inflammatory markers and skewed liver or kidney values that reflect the illness rather than long-term risk; clinicians generally prefer to retest after recovery. Pregnancy changes thyroid hormone, lipid and kidney reference ranges, so standard longevity scoring does not apply. People already under specialist care for a chronic condition often get more from disease-specific monitoring than from a broad panel, and duplicate testing can muddy that monitoring.
There is also a group for whom extra testing can cause harm rather than help: people prone to health anxiety, or those who would act on borderline cancer markers by pursuing scans and biopsies that guidelines do not support. The decision to test, and which tests, sits with the treating clinician who can weigh benefit against the real downsides of false alarms.
One more practical point. Children and adolescents are not candidates for adult longevity panels. Their reference ranges differ, growth alters hormone and bone markers, and no pediatric guideline endorses this kind of screening.
Longevity report explained: the cardiovascular markers that carry the most evidence
If one page of the report deserves the longest look, it is the lipid page, because the link between blood lipids and heart disease rests on decades of trials and genetic studies. The standard panel lists total cholesterol, LDL cholesterol, HDL cholesterol (the particle that carries cholesterol away from tissues), and triglycerides. The NHS and the American Heart Association both treat LDL as the primary target of prevention, since LDL particles are the ones that lodge in artery walls and build plaque.

Many longevity reports add two markers that are less familiar. Apolipoprotein B (ApoB) is a protein found once on every LDL and similar particle, so it effectively counts how many plaque-forming particles are circulating rather than how much cholesterol they carry. Lipoprotein(a), written Lp(a), is an LDL-like particle whose level is set mostly by genes and changes little with diet. MedlinePlus notes that a high Lp(a) is an independent risk factor for heart attack and stroke, and that because it is largely inherited, a single lifetime measurement is often enough. Many people have never had it checked, which makes it one of the more valuable additions on a longevity panel.
How should you read these numbers? Look first at LDL and ApoB in the context of your overall risk, not in isolation. Guidelines set different LDL targets depending on whether someone has diabetes, high blood pressure, a smoking history or existing artery disease, so the same value can be acceptable for one person and a treatment trigger for another. Your clinician will usually run a validated risk calculator that combines these inputs before deciding anything.
Treatment, where it is needed, ranges from dietary change and exercise to cholesterol-lowering medicine classes such as statins. Those medicines work by reducing the liver’s cholesterol output and increasing LDL clearance; whether to start one, and when, is a decision for the prescribing clinician after discussing your personal risk.
Blood pressure, calcium score and the markers that show the pipes, not just the plasma
A blood test shows what is in the blood. Two other items on a longevity report show what the blood has already done to the vessels, and they often shift the conversation more than any lipid value.
Blood pressure comes first. The American Heart Association defines stage 1 hypertension as a reading of 130–139 systolic or 80–89 diastolic, and stage 2 as 140/90 or higher, with normal below 120/80. A single clinic reading is unreliable; nerves, caffeine and a full bladder all push it up. Reports built on one cuff reading should be treated as a prompt for home monitoring over several days, which guidelines regard as a better reflection of true pressure.
Second is the coronary artery calcium (CAC) score, a low-dose CT scan that counts calcified plaque in the heart’s arteries. The Mayo Clinic describes it as a tool to refine risk in people at intermediate risk, where the decision about preventive medicine is uncertain. A score of zero in someone without symptoms is reassuring; a high score indicates established plaque even if cholesterol looks fine. The scan involves radiation and is not recommended for everyone, particularly those already at clearly high or clearly low risk, so its presence on a report should have been a deliberate clinical choice.
Some panels include carotid ultrasound, which measures artery wall thickness in the neck, or a resting ECG. These add information in specific situations but are not part of routine screening in current guidelines for people without symptoms.
Reading this page well means asking one question: do the structural findings and the blood findings agree? Normal lipids with a high calcium score, or the reverse, is exactly the pattern a clinician needs to see, because it changes which risk estimate to trust.
Metabolic markers: A1C, fasting glucose, insulin and the liver
The metabolic section is where many people get their first real surprise, because the body can run elevated blood sugar for years without any symptoms.
Hemoglobin A1C measures the percentage of hemoglobin in red blood cells that has sugar attached, which reflects average blood glucose over the previous two to three months. The Mayo Clinic lists the standard cut-points: below 5.7% is in the normal range, 5.7–6.4% indicates prediabetes, and 6.5% or above on two separate tests indicates diabetes. A1C is less reliable in people with anemia, certain hemoglobin variants or recent blood loss, which is why fasting glucose is usually reported alongside it.
Fasting insulin and derived indices such as HOMA-IR attempt to estimate insulin resistance, the state in which cells respond sluggishly to insulin so the pancreas has to produce more. The concept is well established; the specific thresholds used by consumer reports are not standardized, and routine screening with fasting insulin is not part of major diabetes guidelines. A high value is a reasonable prompt for discussion, not a diagnosis.
Liver enzymes (ALT, AST, GGT) appear here because the most common cause of a mildly raised ALT in adults is fat accumulation in the liver, which travels with insulin resistance and excess waist circumference. A modest rise often responds to the same changes that improve glucose; a marked rise, or one with other abnormal liver values, warrants proper evaluation.
CDC data indicate that most adults with prediabetes do not know they have it, which is the strongest argument for this part of the panel. Progression to diabetes is not inevitable; structured lifestyle programs have reduced progression in trials, and the clinician reading your result will know whether such a program is appropriate before any medicine is considered.
Inflammation and kidney function: hs-CRP, eGFR and uric acid
Inflammation markers generate more amber flags than almost anything else on a longevity report, partly because they are so easily disturbed.
High-sensitivity C-reactive protein (hs-CRP) is a protein the liver releases in response to inflammation anywhere in the body. MedlinePlus describes it as a marker that can help estimate heart disease risk when combined with other factors, with higher values associated with higher risk. The key word is anywhere: a head cold, a dental abscess, a hard training session, a recent vaccination or a flare of arthritis will raise it. A single elevated reading means little; a persistently elevated reading on repeat testing, in someone who felt well at both draws, is what clinicians find meaningful.
Kidney function appears as creatinine and the estimated glomerular filtration rate (eGFR), a calculated value for how many milliliters of blood the kidneys filter per minute. Values above about 90 are considered normal; a sustained value below 60 for three months or longer meets the definition of chronic kidney disease used by major guidelines. eGFR declines slowly with age and is affected by muscle mass, hydration and some supplements, so a borderline result in a muscular or dehydrated person is often rechecked before any label is applied. A urine albumin-to-creatinine ratio, which detects protein leaking into urine, is a more sensitive early signal and is worth looking for on the report.
Uric acid, the compound behind gout, has been linked to cardiovascular and metabolic risk in observational studies, but the evidence that lowering it in people without gout improves outcomes is weak. Treat it as context rather than a target.
Across this page, the principle is the same: trends beat snapshots. Ask whether the report shows previous values, and if it does not, ask for them.
Cancer risk markers: what a blood test can and cannot tell you
This is the section where honesty matters most, because the gap between what the report implies and what the evidence supports is widest here.
Tumor markers are substances, usually proteins, that some cancers release into blood in larger amounts than healthy tissue does. Common examples on longevity panels include PSA (prostate-specific antigen), CA-125, CEA, CA 19-9 and alpha-fetoprotein. MedlinePlus is clear about their proper role: they are mainly used to monitor people already diagnosed with cancer, to check whether treatment is working or disease has returned. For screening healthy people they perform poorly, because many benign conditions raise them and many early cancers do not.
PSA is the exception with a real screening role, and even there major guidelines call for an individual decision after discussing harms and benefits, because elevated PSA leads to biopsies that often find nothing or find slow-growing tumors that would never have caused harm. CA-125 rises with endometriosis, fibroids and menstruation; CEA rises in smokers; CA 19-9 rises with gallstones and pancreatitis. A raised value on a panel in a well person usually triggers worry, imaging and sometimes invasive tests, with a low probability of finding cancer.
Newer blood tests that look for fragments of tumor DNA across many cancer types are being studied in large trials. Until those trials report outcomes, no major guideline recommends them for routine screening.
What does reduce cancer deaths is the evidence-based screening you may already be offered: mammography, cervical screening, colorectal screening by colonoscopy or stool testing, and low-dose CT for people with a heavy smoking history. If a longevity report lists tumor markers but does not confirm you are up to date on those programs, it has its priorities inverted. Ask your clinician which guideline-based screenings apply to your age, sex and history, and treat the tumor marker page as the least actionable part of the document.
Biomarkers of longevity explained: biological age, epigenetic clocks and telomeres
The headline number on many reports is a “biological age”, often presented as proof that you are five years younger or older than your birth certificate. Understanding how it is produced takes the drama out of it.
Several methods exist. The simplest combine ordinary clinical values (glucose, CRP, creatinine, blood counts) with chronological age in a formula trained on population survival data. Epigenetic clocks go further, measuring chemical tags called methyl groups attached to DNA at hundreds of sites; the pattern of these tags shifts predictably with age, and a clock estimates age from the pattern. Telomere tests measure the protective caps at the ends of chromosomes, which shorten as cells divide.
What the evidence shows is more modest than the marketing. Epigenetic clocks are a genuine research advance and track with mortality at the population level in cohort studies. For an individual, the test-retest variability can be comparable to the “age gap” being reported, different clocks give different answers on the same sample, and no trial has yet shown that changing your clock result changes your health outcome. Telomere length varies widely between healthy people, is only loosely associated with disease, and is not recommended as a clinical test by any major body.
None of this makes these markers worthless. They are interesting, and they may become useful. The honest reading today is that a biological age score is a composite summary of mostly conventional markers plus a layer of research-grade measurement, and that the conventional markers underneath it, blood pressure, LDL, A1C, waist circumference, smoking status, are the parts with proven levers.
If the report quotes a biological age, look for the method. If it does not say how the number was calculated, it is a conversation starter, not a result.
Longevity blood test results at a glance: a reading guide
A table cannot replace the clinician’s judgment, but it can show where each marker sits on the evidence ladder and what tends to move it. The thresholds listed are the ones used by the cited sources; your laboratory’s units and ranges may differ.
| Marker | What it reflects | Guideline-backed thresholds | Common reasons for a misleading result |
|---|---|---|---|
| LDL cholesterol / ApoB | Number and load of plaque-forming particles | Target depends on overall risk; set by clinician (NHS, AHA) | Rarely misleading; acute illness lowers it |
| Lipoprotein(a) | Inherited LDL-like particle | Flagged above lab cut-off; once-in-a-lifetime test (MedlinePlus) | Few; largely stable over time |
| Blood pressure | Vessel load | Normal below 120/80; stage 1 from 130/80 (AHA) | Single reading, caffeine, anxiety, cuff size |
| Hemoglobin A1C | Average glucose over 2–3 months | 5.7–6.4% prediabetes; 6.5%+ diabetes (Mayo Clinic) | Anemia, hemoglobin variants, recent blood loss |
| hs-CRP | Body-wide inflammation | Adds to risk estimate only (MedlinePlus) | Infection, injury, exercise, vaccination |
| eGFR | Kidney filtration rate | Below 60 for 3+ months defines CKD | Dehydration, high muscle mass, supplements |
| Tumor markers | Proteins some cancers release | Not recommended for screening healthy adults (MedlinePlus) | Benign conditions, smoking, menstruation |
| Biological age / clocks | Composite or DNA methylation pattern | No clinical threshold; research use | Test variability, method differences |
Two patterns in the table are worth noticing. The markers with the firmest thresholds are the oldest and least glamorous. And the markers most likely to produce a dramatic color on the dashboard, inflammation and tumor markers, are the ones most easily thrown off by everyday life. Read the report from the top of this table downward, and let the bottom rows raise questions rather than fears.
The hormone and thyroid page: where "optimal" ranges deserve scrutiny
Longevity panels nearly always include a hormone section, and it is the part of the report most likely to be read as a verdict on how well someone is aging. It deserves a calmer eye.
Thyroid testing usually starts with TSH, the pituitary hormone that tells the thyroid gland how hard to work. A high TSH suggests the gland is underactive and the pituitary is pushing; a low TSH suggests the opposite. Free T4 and sometimes free T3, the thyroid hormones themselves, are added for context. Guideline practice is to interpret TSH against the laboratory’s reference range and the person’s symptoms, and to repeat a mildly abnormal value after several weeks before acting, because TSH fluctuates with illness, sleep loss and the time of day. The idea that a narrower “optimal” TSH band improves longevity in people without symptoms is not supported by current guidance; treating mild abnormalities without symptoms has not been shown to improve outcomes in trials.
Testosterone in men falls gradually with age, and a single morning value within the reference range is reassuring. A low result needs repeating, ideally on two mornings, and should be read alongside symptoms, because testosterone replacement carries cardiovascular and fertility considerations that only the prescribing clinician can weigh. In women, estrogen and FSH values on a random day say little outside a defined clinical question.
Cortisol, DHEA-S, IGF-1 and vitamin D also appear often. Random cortisol is almost uninterpretable because of its daily rhythm. IGF-1, a growth-hormone marker, has been linked to both lower and higher mortality at the extremes in observational studies, which is a reason not to chase a target. Vitamin D testing is reasonable in people at risk of deficiency; the NIH Office of Dietary Supplements notes that routine testing of healthy adults is not recommended.
The rule for this page: a hormone out of range is a prompt for a repeat test and a conversation, never a prompt to start a supplement or medicine on your own.
What the following weeks usually look like after a longevity report
The report lands, and the question is what happens next. In a well-run program the sequence is predictable, and knowing it stops the waiting from feeling like limbo.
The first step is a review, ideally with a clinician who has your full history. Expect that conversation to sort findings into three piles: values that are normal or explainable, values that need repeating, and values that need action now. The second pile is usually the largest. Mildly abnormal thyroid, inflammatory, liver and kidney results are commonly rechecked after a few weeks, once any illness has cleared and the fasting instructions have been followed properly. Blood pressure flagged on one reading is typically confirmed with a week of home measurements, twice daily, before anyone uses the word hypertension.
For the third pile, timelines depend on the marker. An A1C in the prediabetes range usually leads to a structured discussion of eating pattern, activity and weight, with the next A1C planned roughly three months later, since that is how long the test takes to reflect change. A clearly elevated LDL in someone at raised overall risk may lead to a trial of lifestyle measures or, where the clinician judges it appropriate, a cholesterol-lowering medicine; lipid levels on such medicines are generally rechecked after several weeks to see the response. A raised tumor marker leads to a careful history and examination first, with imaging only if the picture justifies it.
What the weeks should not look like is a cascade of self-directed supplements, elimination diets and additional tests ordered online. Each extra test adds another chance of a false alarm.
A reasonable rhythm for most adults after the initial review is a repeat of the core markers at an interval set by the clinician, often yearly, with Lp(a) and calcium score needing no repeat for years unless something changes.
Do people live longer now than 50 years ago? What the statistics mean by longevity
Readers often ask what “longevity” means when researchers use it, and whether the numbers in the headlines reflect real change. Both questions have clear answers.
In statistics, longevity is usually expressed as life expectancy at birth: the average number of years a newborn would live if the death rates of a given year stayed constant for its whole life. It is a summary of a whole population’s mortality, not a forecast for any individual. A related measure, life expectancy at age 65, strips out childhood and early-adult deaths and is often more relevant to adults reading a longevity report. Healthy life expectancy, used by the WHO, estimates years lived without significant disability and is the figure that prevention aims to stretch.
On the second question, CDC data show that life expectancy at birth in the United States now stands at a little over 77 years, several years higher than it was half a century earlier, when it was in the low seventies. The gain came mainly from fewer deaths from heart disease and stroke, improved treatment of infections, and reductions in smoking. Progress has not been a straight line; the figure fell during recent pandemic years before recovering, and it still varies substantially by sex, region and income.
Why does this matter for a personal report? Because the biggest population-level gains came from exactly the markers at the top of the table: blood pressure, cholesterol, smoking and blood sugar. That is the evidence base behind the dull advice. The exotic markers at the bottom have not yet contributed a measurable year to anyone’s life expectancy.
Questions about which birth month lives longest, or whether one season produces hardier babies, come up constantly online. Small seasonal differences have appeared in historical datasets, but they are tiny compared with the effects of smoking, blood pressure and physical activity, and they are not something anyone can act on.
What people often get wrong about a longevity test and what it measures
Some misreadings recur so often that correcting them is half the job of interpreting the report.
The first is treating every amber flag as equally urgent. A report may color an LDL result and a uric acid result the same shade, yet one has decades of trial evidence behind it and the other has none for people without gout. Weight the colors by the evidence, not by the design.
The second is believing a normal panel means low risk. Family history, smoking, physical inactivity and sleep apnea do not show up in a blood tube. A person can have an impeccable lipid page and a calcium score that tells a different story. Blood tests are one input to a risk estimate, never the estimate itself.
The third is the opposite error: assuming an abnormal value is a diagnosis. Laboratory ranges are drawn so that about one in twenty healthy results falls outside them by definition. Across a fifty-marker panel, a perfectly healthy person can expect two or three flags by chance alone. Repeat testing exists precisely to separate chance from signal.
The fourth is reading biological age as a prediction. The clocks behind that number are population tools with meaningful individual variability, and no trial has shown that lowering a clock result changes what happens to a person.
The fifth is the supplement reflex. Low-normal vitamin B12, borderline ferritin or an “unoptimized” testosterone level are commonly followed by online purchases rather than a conversation. Several of those decisions carry real risks, and all of them belong with a clinician.
The last is believing that more testing is always safer. Every additional marker carries a chance of a false positive, and false positives lead to scans, biopsies and anxiety with their own harms. The most protective reports are the focused ones.
Questions to ask your care team about your longevity report
A good review of a longevity report is a conversation, and conversations go better with prepared questions. These are the ones that tend to change decisions.
- Which of these results would you have ordered anyway, and which were added by the panel?
- Of the flagged values, which ones need repeating before we interpret them, and when?
- What is my overall cardiovascular risk estimate once these numbers are combined with my age, blood pressure, smoking status and family history?
- Does my Lp(a) result change how aggressively we should manage my LDL?
- Is a coronary calcium score appropriate for me, and if I already had one, how does it fit with the blood results?
- Am I up to date on the guideline-based cancer screenings for my age and history, regardless of what the tumor markers show?
- Is there a benign explanation for any raised tumor marker before we consider imaging?
- Which lifestyle changes have the strongest evidence for my specific flagged markers, and how long before a repeat test could show a difference?
- If medicine is being considered, what is the mechanism, what would we be monitoring, and what would make you stop it?
- How was the biological age figure calculated, and does it change any decision we would make from the standard markers?
- Which values should I track at home, such as blood pressure, and how should I record them?
- When should the core panel be repeated, and which tests never need repeating?
Bring the full report, not the summary page, and bring any earlier results you have. Trend lines matter more than any single number, and the clinician cannot draw one from a snapshot.
One further question is worth asking yourself before the appointment: what would I actually do differently with a given answer? If the honest reply is nothing, that test may not need to be repeated, and the time is better spent on the handful of markers where action is proven to help.
When to call your doctor
A longevity report is a planning document, and almost everything in it can wait for a scheduled review. A small number of findings and symptoms should not.
Contact your doctor promptly, rather than waiting for a routine appointment, if the report shows a blood pressure reading of 180/120 or higher, which the American Heart Association classifies as a hypertensive crisis; a hemoglobin A1C or fasting glucose far above the diabetes threshold, particularly with thirst, frequent urination or unexplained weight loss; an eGFR markedly below the normal range or protein in the urine; liver enzymes several times the upper limit; a very low or very high potassium, sodium or calcium; a hemoglobin low enough that the laboratory has flagged it as critical; or a thyroid result accompanied by a racing heart, tremor or marked fatigue.
Seek emergency care immediately, regardless of what the report says, for chest pain or pressure, pain spreading to the arm, jaw or back, sudden shortness of breath, sudden weakness or numbness on one side of the body, difficulty speaking, a severe sudden headache, fainting, or a blood pressure of 180/120 or above together with any of those symptoms.
Call about a raised tumor marker without delay if it is accompanied by unexplained weight loss, persistent pain, a new lump, blood in urine or stool, a change in bowel habit lasting weeks, or night sweats. Without such symptoms, a raised marker is still worth discussing soon, but it is not an emergency.
Laboratories usually phone the ordering clinician directly about critical values, so if you receive a call before you have seen the report, that is the system working as intended. Every decision about what to repeat, what to investigate and what to treat rests with your treating team, who can read the numbers alongside the person in front of them.
Frequently asked questions
What is a longevity report, and how is it different from a normal blood test?
A longevity report is a standard set of blood, urine and blood pressure results, sometimes with imaging, grouped into cardiovascular, metabolic, inflammatory, hormonal and cancer-related categories and often topped with a composite score. The underlying tests are mostly the same ones a physician orders in routine prevention. The difference lies in the packaging, the number of extra markers and the scoring layer, which is where the evidence becomes thinner.
What does longevity mean in the context of statistics?
In statistics, longevity is usually expressed as life expectancy at birth, the average years a newborn would live if current death rates never changed. It describes a whole population, not an individual. Related measures include life expectancy at age 65 and the WHO’s healthy life expectancy, which counts years lived without significant disability. None of these figures can be applied to one person’s blood test results.
Do people live longer now than 50 years ago?
Yes. CDC data show US life expectancy at birth is now a little over 77 years, several years higher than half a century earlier, when it was in the low seventies. Most of the gain came from fewer deaths from heart disease and stroke, better treatment of infections and less smoking. Progress has not been steady, and large gaps remain by sex, region and income.
What birthday lives the longest, and does birth month affect lifespan?
Historical population datasets have shown small seasonal differences in lifespan by birth month, likely linked to past patterns of nutrition and infection in early life. The effect is tiny compared with the influence of smoking, blood pressure, physical activity and blood sugar, and it is not something anyone can act on. A longevity report is a far better guide to modifiable risk than a birth date.
What is a longevity health company, and should I trust its scoring?
The term usually refers to businesses that bundle laboratory tests with software that produces risk scores or a biological age. The laboratory values themselves are reliable when drawn and processed properly. The scoring layer varies widely and is often proprietary, so the safest approach is to ask how each score is calculated and to have a clinician interpret the raw values against established guideline thresholds rather than relying on the dashboard alone.
How accurate is the biological age on my longevity report?
Less precise than it looks. Biological age estimates come from formulas combining standard markers or from epigenetic clocks that read chemical tags on DNA. These track mortality across populations in research studies, but for an individual the test-to-test variability can be similar to the reported age gap, different clocks disagree, and no trial has shown that improving the score changes health outcomes. Treat it as a discussion point.
What do longevity blood test results mean when one value is just outside the range?
Usually very little on its own. Reference ranges capture the middle 95% of healthy people, so about one in twenty normal results falls outside them by design. A value slightly beyond the range, especially after a cold, a hard workout or a missed fast, is commonly repeated after a few weeks before anyone interprets it. A value far outside the range, or one trending steadily in one direction, is the pattern that matters.
Can a longevity test detect cancer early?
Not reliably. The tumor markers on most panels, such as CA-125, CEA and CA 19-9, are designed to monitor people already diagnosed with cancer and are raised by many benign conditions, so they produce frequent false alarms in healthy adults. PSA has a defined but individualized screening role. The proven way to catch cancer early remains guideline-based screening such as mammography, cervical screening, colorectal screening and lung CT for eligible smokers.
What does a longevity test measure in terms of hormones, and should I chase optimal levels?
Hormone sections typically include TSH and free T4 for thyroid function, testosterone or estrogen and FSH, cortisol, DHEA-S, IGF-1 and vitamin D. These values swing with time of day, illness and sleep, so a single out-of-range result is normally repeated. Current guidelines do not support treating mild abnormalities in people without symptoms to reach a narrower optimal band, and any decision about hormone treatment belongs with the prescribing clinician.
How often should the markers on a longevity report be rechecked?
It depends on the marker and on what was found. Lipoprotein(a) is usually measured once in a lifetime, and a coronary calcium score is rarely repeated for years. Hemoglobin A1C takes about three months to reflect change, so earlier repeats add little. Blood pressure, lipids and kidney function are commonly reviewed at intervals set by the clinician, often yearly for healthy adults and sooner when a value was flagged.
References
- CDC FastStats: Life Expectancy
- MedlinePlus: Lipoprotein (a) Blood Test
- MedlinePlus: Tumor Marker Tests
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Graves Disease Work-Up: Thyroid Hormone Tests, Antibodies, Ultrasound and Scintigraphy
Graves disease is usually diagnosed with blood tests first: a low or undetectable TSH with raised free T4 or T3 confirms an overactive thyroid,…
Why Is Thyroid Disease Monitored More Closely in Pregnancy, and How Is Care Coordinated?
Thyroid disease in pregnancy is monitored more closely because pregnancy changes how the thyroid works and because the baby depends on the mother's thyroid…
Questions to Ask Your Endocrine Surgeon Before a Parathyroidectomy
Before a parathyroidectomy, ask your endocrine surgeon which gland or glands are thought to be overactive, whether a focused or four-gland operation is planned,…
Endoscopic Pituitary Tumor Surgery Explained: The Transsphenoidal Route and What It Avoids
Transsphenoidal surgery is an operation that reaches the pituitary gland through the nose and the sphenoid sinus, an air pocket behind the nasal cavity…

Surgery, Medication or Radiotherapy for Acromegaly: How Do Specialists Combine the Three?
Specialists usually start with transsphenoidal surgery to remove the pituitary tumor when it can be reached safely, then add medicines such as somatostatin analogs,…
Total or Partial Thyroidectomy: How Do Surgeons Decide Whether the Whole Gland Comes Out?
Surgeons choose between total and partial thyroidectomy mainly on what the gland is doing and why it needs surgery. Removing one lobe (hemithyroidectomy) is…