

Is Your Keratoconus Progressing? How Specialists Read the Topography Map

Key Takeaways
- The global consensus definition of keratoconus progression requires consistent change in at least two of three features: front-surface steepening, back-surface steepening, or corneal thinning.
- Kmax, the curvature at the single steepest point of the cornea, is the most quoted number on the map but also the noisiest, so specialists read it alongside posterior elevation and thinnest-point thickness.
- The colors on a topography map depend on an adjustable scale, which is why the difference map comparing two scans is more informative than how red a single image looks.
- Contact lens wear, dry eye and small fixation errors can all alter a scan, so clinics often repeat a suspicious measurement before labeling it progression.
- Keratoconus most often appears in the late teens or early twenties and tends to change for ten years or longer before slowing, according to Mayo Clinic, with eye rubbing listed as a risk factor.
- Corneal cross-linking uses riboflavin and ultraviolet A light to create new bonds between collagen fibers, with the aim of stiffening the cornea and slowing progression, not improving vision.
Keratoconus is considered progressing when repeated corneal scans show a consistent trend rather than a single change: steepening of the front surface (often tracked as Kmax, the steepest point), steepening of the back surface, or thinning of the cornea, confirmed across at least two visits. Specialists weigh these together with age, scan quality and symptoms before deciding whether continued monitoring or a treatment such as cross-linking should be discussed.
The room is dark, the chin rest is cold, and a voice says, once more, keep looking at the little light. A few seconds later a printout slides across the desk: four rainbow-colored ovals, a column of numbers, and one word circled in pen. Progression? Or stable? For a nineteen-year-old who was told two years ago that the cornea was slightly cone-shaped, that circled word now carries more weight than the eye chart ever did.
Judging keratoconus topography progression is one of the most consequential readings in corneal medicine, and also one of the most misunderstood. A single map cannot answer the question. A single number cannot either. What specialists are really doing is comparing shapes over time and asking whether a change is real, consistent and heading in one direction.
This explainer walks through what those maps measure, which numbers matter and why, how much a scan can be trusted on a given day, and what the next steps usually look like when the trend is unmistakable. The decisions remain with your eye care team; the aim here is to help you read the room, and the printout, with them.
What does keratoconus topography progression actually mean?
Keratoconus is a condition in which the cornea, the clear dome at the front of the eye, gradually thins and bulges outward into a cone-like shape. That shape scatters light instead of focusing it, which is why vision becomes blurred and distorted. According to Mayo Clinic, it usually begins in the late teens or early twenties and tends to change slowly for a decade or more before settling.
Progression simply means the shape is still changing. The difficulty is deciding when a change is genuine. Corneal shape is measured to fractions of a diopter, and a diopter is the unit used to describe how strongly a curved surface bends light; a steeper curve has a higher value. Small shifts can come from the measurement itself rather than from the eye.
A global consensus of corneal specialists, published in the journal Cornea and indexed on PubMed, offered the working definition most clinics now use. Progression is a consistent change in at least two of three features: steepening of the front surface of the cornea, steepening of the back surface, or thinning of the cornea (or an acceleration in how fast it thins). The same panel was candid that no universally accepted numerical cut-off exists, and that any threshold must be judged against how repeatable the particular scanner is.
Two ideas follow from that definition. The first is that progression is a trend, not a snapshot: the map from today only means something next to the map from last time. The second is that specialists look for agreement between measurements. When the front surface steepens, the back surface steepens and the thinnest point gets thinner, all in the same eye and all in the same direction, the signal is far more convincing than any one number drifting on its own.
How corneal topography for keratoconus is measured: what actually happens in the chair
Nothing touches the eye. You rest your chin and forehead against the instrument, fix your gaze on a target light, and hold still while the device captures an image. The whole measurement takes a few seconds, though a technician may repeat it two or three times to pick the best-quality capture.
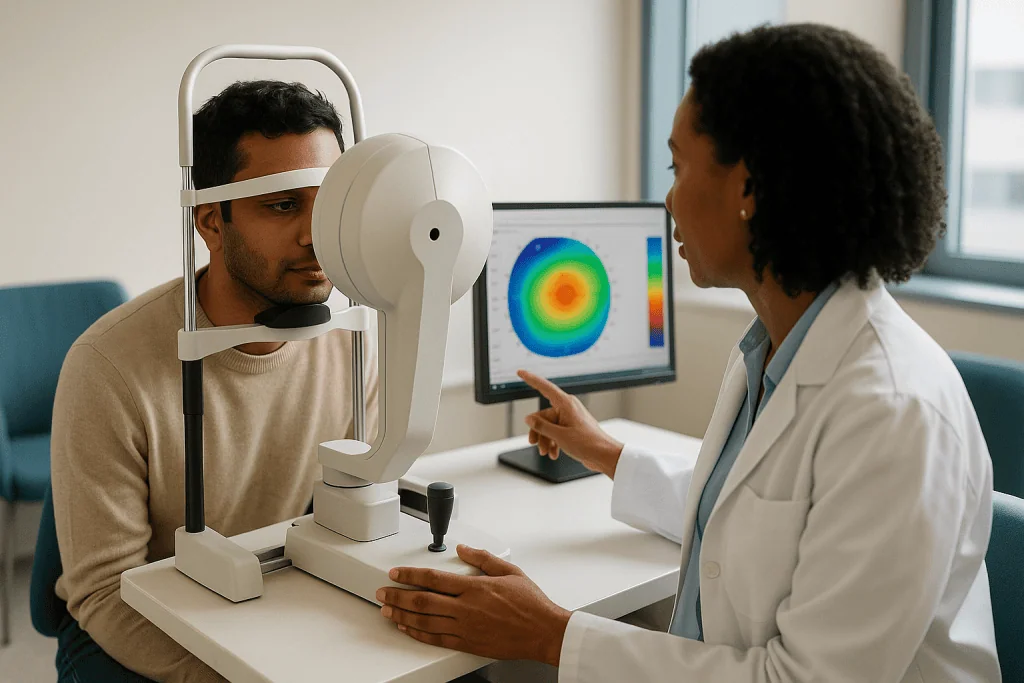
Two technologies are common. The older method, Placido-based topography, projects a series of concentric illuminated rings onto the cornea and photographs their reflection from the tear film. Where the cornea is steep, the rings crowd together; where it is flat, they spread apart. Software converts that distortion into a curvature map of the front surface.
The newer method, often called tomography, uses a rotating camera (frequently a Scheimpflug camera, named for the optical principle it exploits) to take dozens of cross-sectional slit images as it sweeps around the eye. From those slices the software reconstructs a three-dimensional model that includes the front surface, the back surface and the thickness between them. Because keratoconus often shows its earliest changes on the back surface and in thickness, tomography has become central to monitoring; the global consensus specifically lists back-surface and thickness changes among its progression criteria.
A few practical points shape scan quality. Clinics commonly ask patients to leave contact lenses out for a period beforehand, because a lens can temporarily mold the cornea; follow the instruction your own clinic gives rather than a generic rule. Blinking fully just before the capture spreads the tear film evenly. Try to have each follow-up done on the same type of device, since maps from different machines are not directly interchangeable. Cleveland Clinic notes that these imaging tests are what allow keratoconus to be detected and tracked long before a routine eye exam would show much.
Reading the colors: why red on the map is not automatically bad
The colored oval that patients photograph on their phones is the curvature map, and its palette follows a convention borrowed from weather charts. Warm colors (red, orange, yellow) mark steeper curvature; cool colors (blue, green) mark flatter areas. In keratoconus the cone typically sits below the center of the cornea, so a classic map shows a warm island in the lower half, often with an asymmetric pattern that specialists describe as a skewed or broken bow tie.
Here is the catch: the color scale itself is adjustable. Some displays use an absolute scale, where a given color always means a fixed curvature. Others use a normalized scale that stretches whatever range is present across the full palette, so even a mild cone can look fiery. The same eye can appear alarming on one setting and modest on another. If a map looks redder than last year, the first question a clinician asks is whether the scale is identical.
What specialists prefer to study is the difference map, sometimes labeled a subtraction or comparison display. The software takes two scans from different dates and plots only the change between them, point by point. A difference map that is uniformly green, meaning essentially no change, is reassuring regardless of how dramatic the raw maps appear. A difference map with a focused warm patch exactly over the cone, present in the front-surface map and echoed on the back-surface map, is the kind of picture that prompts a conversation.
Pattern matters as well as color. Steepening that lines up with the existing cone is more meaningful than scattered noise across the whole surface, and the consensus panel on PubMed stresses that progression should be judged on the corneal shape over time rather than on how a single image looks.
Kmax keratoconus meaning: the number everyone asks about
Kmax, short for maximum keratometry, is the curvature value at the single steepest point on the front of the cornea, expressed in diopters. In plain terms it is the height of the cone’s peak. Because it is one number on a page of hundreds, it has become the shorthand that patients and clinicians both reach for, and it is often the first figure read aloud in the consultation.

Its appeal is clear. Kmax rises as a cone sharpens, so a climbing Kmax across visits fits the intuition of a worsening bulge. Many of the clinical trials summarized in the Cochrane review of corneal cross-linking, indexed on PubMed, used an increase of roughly one diopter in Kmax over about twelve months as their definition of progression, which is why that figure circulates so widely.
Yet the global consensus deliberately declined to anoint Kmax as the sole criterion, and for sound reasons. A single point is the noisiest thing a scanner measures. Tear film irregularity, a slightly off-center fixation or a contact lens worn the day before can move the steepest point by a fraction of a diopter without the cornea changing at all. Repeatability tends to worsen as cones become more advanced, exactly when precision matters most. Kmax also says nothing about the back surface or the thickness, where early change often appears first.
So how do specialists use it? As one witness among several. A Kmax that rises steadily across three visits, in step with a thinning cornea and a rising back surface, carries real weight. A Kmax that jumps once and settles back is treated as noise until proven otherwise. If your clinician seems unexcited by a half-diopter shift, that is usually measured judgment, not indifference.
Beyond Kmax: the back surface, thickness and the ABCD way of thinking
Modern tomography gives specialists three families of measurement, and the most useful progression decisions rest on reading them together.
The posterior elevation map shows how far the back surface of the cornea rises above a smooth reference shape (usually a best-fit sphere or ellipse). In keratoconus the back surface tends to bulge earlier and more than the front, partly because the front is smoothed over by the tear film and the surface cell layer. A rising elevation value directly beneath the cone is one of the most sensitive signs on the whole display.
Pachymetry is the measurement of corneal thickness, and the thinnest-point value is the figure that matters here. Thinning that progresses, or a thinnest point that migrates, supports a diagnosis of active change. Thickness also shapes treatment conversations, because some cross-linking protocols have minimum thickness requirements that the treating team will assess.
The ABCD framework, developed to grade keratoconus on tomography, packages these ideas: A for anterior curvature, B for back (posterior) curvature, C for corneal thickness and D for distance vision with correction. Each letter gets its own stage, so a report might show the back surface worsening even while the front and the vision hold steady.
| Parameter | What it measures | Why specialists watch it |
|---|---|---|
| Kmax | Steepest front-surface curvature, in diopters | Rises as the cone sharpens; noisiest single value |
| Posterior elevation | Back-surface bulge above a reference shape | Often changes before the front surface |
| Thinnest-point pachymetry | Corneal thickness at its thinnest spot | Thinning signals active disease; relevant to treatment eligibility |
| Difference map | Point-by-point change between two scans | Separates real shape change from scale and display effects |
| Corrected distance vision | Best vision achieved with lenses | Links the map to daily function |
No row in that table is decisive alone. Agreement across rows is what turns suspicion into a finding.
Keratoconus progression signs you can measure versus what you notice at home
Two kinds of evidence arrive at the consultation. One comes from instruments; the other comes from you. Both matter, but they are weighed differently.
Measurable signs include the scan changes already described, along with shifts in the glasses prescription. Keratoconus typically increases astigmatism (uneven focusing caused by an irregularly curved cornea) and often nearsightedness. A refraction that changes substantially between visits, especially with astigmatism rotating to a new axis, supports what the map is showing. Specialists who fit rigid lenses add another clue: a lens that fit well last year and now rocks, decenters or leaves a changed fluorescein pattern may be sitting on a cornea that has changed shape.
What people notice at home is subtler and less specific. Mayo Clinic describes the experience of keratoconus as blurred or distorted vision, increased sensitivity to light and glare, and a need for frequent changes in eyeglass prescriptions. Ghosting, where a single light becomes a smear or multiple images, is a common description. Night driving often becomes harder before daytime vision changes much.
Treat these as observations to report, not as a test to run on yourself. Many everyday factors can mimic them. Dry eye roughens the tear film and distorts vision in a way that comes and goes. Allergy season, screen fatigue and an aging contact lens can all produce ghosting that has nothing to do with the cone. The map, and only the map, can separate a changing cornea from a tired one.
A useful habit is to jot down specific changes with rough dates: when night halos became bothersome, when the lens started feeling unstable, when the prescription last changed. Specific notes help the team decide whether to bring the next scan forward, and they make the difference map easier to interpret in context.
Why one scan can mislead: tear film, contact lenses and device noise
Every corneal scanner measures the eye through its tear film, the thin layer of fluid that coats the surface and smooths it into a usable optical window. When that film is patchy, the reflected rings or slit images break up and the software fills gaps with estimates. The result can be a map that looks steeper or more irregular than the cornea truly is. People with dry eye, which Cleveland Clinic notes is common and worsens with screen use, are particularly prone to this effect.
Contact lenses are the second great confounder. A rigid gas-permeable lens rests on the cornea for hours and can mold its shape temporarily, flattening the cone and masking progression, or leaving a warped pattern that mimics it. Soft lenses have a smaller effect but are not neutral. Clinics therefore specify how long to leave lenses out before a scan; the right period for you is whatever your own team sets.
Then there is the machine itself. Scanners quote a repeatability figure, meaning how much two back-to-back scans of the same unchanged eye tend to differ. Any change smaller than that figure cannot be distinguished from noise, and the global consensus explicitly says progression thresholds must be read against the specific device’s repeatability. Advanced cones, with their steep and irregular surfaces, are measured less consistently than mild ones.
Alignment and fixation add further variability: a scan taken while the eye drifts slightly off the target light shifts the apparent location of the steepest point. Good technicians discard poor-quality captures and repeat the measurement.
All of this explains a frustrating but sensible clinical reflex. When one scan suggests change, the specialist often repeats it on the day, or asks you to return in a few weeks, before calling it progression. That pause is quality control, not delay.
Who is watched most closely, and who is usually asked to wait
Age is the strongest predictor of change. Because keratoconus most often appears in the teens and early twenties and tends to evolve for a decade or more, as Mayo Clinic describes, younger patients are scanned more frequently and their maps are read with a lower threshold for concern. Many specialists schedule repeat tomography at intervals of roughly six to twelve months in adolescents and young adults; the consensus statement leaves the exact interval to clinical judgment rather than fixing a rule.
Other factors raise the level of vigilance. A history of vigorous eye rubbing, which Mayo Clinic and Cleveland Clinic both list as linked to keratoconus, is one. Allergic eye disease and atopic conditions such as eczema and asthma, which drive rubbing, are another. A family history of keratoconus, Down syndrome, and a fellow eye that has already advanced all prompt closer follow-up. So does a sudden change in refraction or a rigid lens that no longer fits.
Being asked to wait is not the same as being dismissed. Specialists usually recommend continued monitoring rather than treatment when scans are stable across visits, when a suspected change is still within the scanner’s noise range, or when an adult patient is at an age where the cornea has typically stiffened on its own. Waiting may also be advised for reasons unrelated to the cone: an active surface infection, significant corneal scarring that would limit the benefit of stabilizing treatment, or pregnancy, during which hormonal changes can temporarily alter corneal measurements.
Thickness can place someone in a different category entirely. Standard cross-linking protocols have minimum thickness requirements, and a cornea that has already thinned beyond them may be directed toward lens-based management or, in advanced disease, toward surgical options. Each of these paths is a decision for the treating team, made with your scans and your circumstances in front of them.
When does keratoconus stop progressing? Age, hormones and eye rubbing
The honest answer is that it usually slows, and in many people it eventually stabilizes, but no map can promise the exact year. Mayo Clinic describes a condition that typically appears in the late teens or early twenties and progresses slowly for ten years or longer before changes tend to level off. MedlinePlus similarly notes onset in the teens and gradual worsening into the thirties or forties.
The biology behind that slowing is reassuring. The cornea is built largely from collagen fibers, and over a lifetime these fibers acquire natural chemical bonds between them through a process linked to ordinary aging. The effect is a cornea that stiffens with age. Corneal cross-linking, discussed in the next section, is essentially an attempt to accelerate that natural stiffening in a cornea that is still changing.
Stabilization is a tendency, not a rule. Some adults continue to show measurable change on tomography, and specialists do not stop monitoring simply because a patient has passed a birthday. Hormonal shifts are a recognized wild card: pregnancy and other periods of significant hormonal change have been associated in case reports with temporary steepening, which is one reason clinicians interpret scans taken during those times with extra caution.
The modifiable factor that comes up in every consultation is rubbing. Mayo Clinic lists vigorous eye rubbing as a risk factor, and Cleveland Clinic advises people with keratoconus to avoid it. The proposed mechanism is mechanical: repeated pressure on a thinned cornea may encourage the cone to bulge. Managing the itch that drives rubbing, often by treating allergic eye disease with your care team, is part of protecting the map. None of this makes rubbing the cause of keratoconus, whose origins remain only partly understood, but it is the lever most within reach.
If the map shows keratoconus topography progression: what corneal cross-linking actually does
When repeated scans confirm progression, the treatment most often discussed is corneal collagen cross-linking. It is worth being precise about its purpose. Cross-linking is designed to stiffen the cornea and slow or stop further bulging. It is not designed to reshape the cornea back to normal or to sharpen vision, although small changes in curvature sometimes occur as a side effect. Mayo Clinic describes it as a procedure that may help slow or stop keratoconus from getting worse.
The mechanism is chemical rather than mechanical. The cornea is saturated with riboflavin, which is vitamin B2, delivered as eye drops. The eye is then exposed to ultraviolet A light. Together, riboflavin and light generate reactive oxygen species that create new bonds, or cross-links, between neighboring collagen fibers in the corneal stroma, the thick middle layer. More bonds mean a stiffer structure that resists bulging.
Two broad approaches exist. In the epithelium-off method, the surface cell layer (the epithelium) is removed first so the riboflavin can penetrate; this is the technique used in most of the long-running studies. Epithelium-on methods leave the surface intact and use modified formulations or delivery techniques to help the riboflavin pass through. The treating team selects the approach based on corneal thickness, age and other factors.
The evidence deserves honest framing. A Cochrane systematic review on PubMed concluded that the available trials were small and at risk of bias, and rated the evidence that cross-linking halts progression as low quality at the time of review. Clinical experience and later studies have been encouraging, but a guideline-level summary would say the treatment is widely adopted with evidence that is still maturing rather than definitive.
Risks described in the literature include temporary pain, light sensitivity, corneal haze, delayed surface healing and, rarely, infection or scarring. Alternatives range from continued monitoring and specialty lenses to corneal transplantation in advanced disease. The choice sits with you and your corneal specialist.
What the following days and weeks usually look like, and how the map is read afterward
If the epithelium-off method is used, the first few days are about surface healing. The removed cell layer regrows from the edges inward, and until it closes the eye is typically sore, watery and sensitive to light. A soft bandage contact lens is often placed to protect the healing surface, and the surgeon prescribes drops to reduce the risk of infection and inflammation; how those drops are used, and for how long, is set entirely by the prescribing clinician. Cleveland Clinic and Mayo Clinic both describe a recovery period during which vision is blurred and fluctuates.
Vision in the following weeks is often worse than before treatment, which unsettles people who expected improvement. This is normal and expected. Light corneal haze, a faint cloudiness in the stroma, is common in the early months and usually fades. Contact lens wear is typically paused until the surface has fully recovered and the team gives the go-ahead.
The post-treatment map has its own quirks. Trials summarized in the Cochrane review describe measurements that fluctuate during the early months, and a slight initial steepening of Kmax before any flattening is a recognized pattern rather than a sign of failure. For this reason specialists usually treat the first scans after cross-linking as establishing a new baseline rather than as a verdict.
Follow-up tomography is then scheduled at intervals the team chooses, often at several points across the first year and then annually or as clinically indicated. The question at each visit is the same one asked before treatment: are the front surface, back surface and thickness holding steady relative to the new baseline? Stability on that difference map, sustained over time, is how the result is judged. A cornea that continues to steepen despite treatment is uncommon but possible, and the team will discuss what that means if it arises.
What people often get wrong about keratoconus topography maps
A red map means an emergency. Red marks steepness, and the color scale is adjustable. A dramatic-looking map on a normalized scale may represent a mild, stable cone. The difference map between visits tells you about change; the raw colors tell you about shape.
One scan can prove progression. It cannot, because every scanner has measurement noise and every cornea is affected by tears, lenses and alignment on the day. The consensus definition requires change across time and across more than one parameter.
Needing stronger glasses always means the cone is growing. Prescription changes support the map but do not replace it. Dry eye, allergy and ordinary shifts in nearsightedness during the growing years can all move a refraction without any change in corneal shape.
Cross-linking improves vision. Its purpose is to stiffen the cornea and slow progression. Some people notice modest changes, others none, and early on vision is often temporarily worse. Expecting sharper sight sets up disappointment.
Rigid contact lenses hold the cornea in place and stop progression. Lenses correct vision by replacing the irregular front surface with a smooth optical one. Mainstream sources describe them as a way to improve vision, not as a treatment that alters the course of the disease, and no guideline recommends them for that purpose.
Stable at thirty means finished for life. Stabilization is a strong tendency, not a guarantee, and periodic scans remain sensible, particularly around hormonal changes or if symptoms shift.
Kmax is the only number worth knowing. It is the noisiest value on the page. The back surface and the thinnest point often tell the earlier and more reliable story.
Each of these misreadings has a common root: treating a complex measurement as a single verdict. Specialists read trends, agreement and context, and that is the habit worth borrowing.
Questions to ask your care team about your topography results
Consultations move quickly and the printout is dense. Arriving with questions turns a passive review into a shared reading of the map. The following are the ones corneal specialists tend to welcome, because each one points at how the decision is actually made.
- Compared with my previous scans, which measurements have changed, and are they changing in the same direction?
- Is the change larger than what this scanner would show on an unchanged eye, in other words larger than its repeatability?
- Were these scans taken on the same device, with the same color scale, and with my contact lenses out for the same period?
- What do the back-surface elevation and the thinnest-point thickness show, not just the Kmax?
- Given my age and history, how often do you want to repeat the scan, and what would bring that visit forward?
- If you are considering treatment, what is its goal in my case, and what results would count as success on the map?
- What are the alternatives, including continued monitoring, and what are the trade-offs of each for me?
- Are there reasons in my situation, such as corneal thickness, scarring or allergy, that affect which options are suitable?
- What should I do about eye rubbing and allergy symptoms, and whom do I contact if they flare?
- Can I have a copy of today’s maps and numbers for my own records?
Write down the answers, or ask whether a summary can be added to your record. Having your own copy of the maps is more than reassurance; if you ever move or see a different specialist, a clear baseline from the same type of scanner is the single most useful thing you can bring with you. Keratoconus is a long relationship with your cornea, and the questions above are how that relationship stays informed.
When to call your doctor
Most keratoconus care unfolds at scheduled visits, but a few situations should prompt a same-day call to your eye care team or, if you cannot reach them, urgent medical attention.
A sudden, marked drop in vision in one eye, often with pain, light sensitivity and a visibly cloudy or white cornea, can signal corneal hydrops. This happens when the innermost layer of a very steep cornea splits and fluid rushes into the stroma, causing abrupt swelling. Cleveland Clinic describes it as a complication of advanced keratoconus. It needs prompt assessment.
After cross-linking, or at any time while wearing contact lenses, a red, painful eye with discharge, worsening rather than easing discomfort, or a new white spot on the cornea raises concern for infection. Cross-linking leaves the surface temporarily vulnerable, and contact lenses carry their own infection risk. Do not wait for the next appointment.
Pain that intensifies instead of settling in the days after treatment, or vision that was recovering and then abruptly worsens, should also be reported promptly rather than attributed to normal healing.
Less urgent, but still worth a call rather than silence: a rigid lens that suddenly no longer fits or cannot be worn, a noticeable change in vision in one eye over weeks, or a glasses prescription that seems to shift between appointments. Any of these may be a reason to bring your next tomography forward.
None of this is a checklist for diagnosing yourself. It is a guide to when the conversation with your team should happen sooner. Whether a symptom reflects progression, a surface problem or something unrelated is a judgment for the clinician who can examine the eye and read the map alongside you. When in doubt, call; corneal teams would far rather review an eye that turns out to be fine than hear about a problem late.
Frequently asked questions
What are the early keratoconus progression signs on a scan?
The earliest measurable signs usually appear on the back surface of the cornea and in its thickness rather than on the front curvature. Rising posterior elevation directly beneath the cone, a thinnest point that is getting thinner, and front-surface steepening that lines up with the existing cone all count. Specialists look for these to move together across at least two visits, since any one of them can shift on its own because of measurement noise.
What does Kmax mean in a keratoconus report?
Kmax is the maximum keratometry value, the curvature in diopters at the single steepest point on the front of the cornea. A higher Kmax means a sharper cone. Many clinical trials used an increase of about one diopter over roughly twelve months as a definition of progression, but the global consensus does not treat Kmax as the sole criterion because it is the least repeatable measurement on the map.
When does keratoconus stop progressing?
It typically slows with age, but there is no fixed year. Mayo Clinic describes a condition that usually begins in the late teens or early twenties and progresses slowly for ten years or longer before leveling off, as the cornea naturally stiffens. Some adults still show change on tomography, and hormonal shifts such as pregnancy have been linked to temporary steepening, so monitoring continues at intervals your specialist sets.
How is corneal topography for keratoconus different from a regular eye test?
A regular eye test measures how well you see and what lens corrects it. Corneal topography and tomography measure the shape of the cornea itself, mapping curvature across the surface and, with tomography, the back surface and thickness as well. Nothing touches the eye; a camera captures the image in seconds. These maps can show keratoconus changing before the eye chart does, which is why they are the basis for progression decisions.
Can one topography scan tell me whether my keratoconus is progressing?
No. A single scan describes shape on one day, and progression is a change over time. Tear film quality, recent contact lens wear, fixation and the scanner’s own repeatability can all move the numbers without the cornea changing. The consensus definition requires consistent change across more than one parameter, and specialists usually compare scans from the same device, often repeating a suspicious measurement before reaching a conclusion.
Does needing stronger glasses mean my keratoconus is getting worse?
Not necessarily. Keratoconus can increase astigmatism and nearsightedness, so a changing prescription supports what the map shows, but it is not proof on its own. Ordinary changes in nearsightedness during the growing years, dry eye and allergic eye disease can all shift a refraction. Your specialist will set the prescription change next to the tomography before deciding whether the cornea has actually changed shape.
Why does my map look redder than last year if the doctor says it is stable?
The color scale is adjustable. Some displays use a normalized scale that stretches whatever curvature range is present across the full palette, so even a mild cone can appear fiery, and the setting may differ between printouts. The more informative view is the difference map, which plots only the change between two dates. If that map is essentially flat, the cornea has not meaningfully changed despite the colors.
Why do I have to leave my contact lenses out before a topography scan?
Contact lenses, especially rigid ones, rest on the cornea for hours and can temporarily mold its shape. That can flatten the cone and hide progression, or leave a warped pattern that mimics it. Removing lenses for a period before the scan lets the cornea return to its natural shape so the map reflects the eye rather than the lens. The right lens-free period is whatever your own clinic specifies.
What does corneal cross-linking aim to do if progression is confirmed?
Its goal is to stiffen the cornea and slow or stop further bulging, not to reshape the cornea or sharpen vision. Riboflavin (vitamin B2) drops saturate the cornea, then ultraviolet A light triggers new bonds between collagen fibers. A Cochrane review rated the trial evidence as low quality at the time, while mainstream sources describe it as a treatment that may help slow progression. Whether it suits you is a decision for your corneal specialist.
How often should keratoconus be monitored with tomography?
There is no single guideline interval; the global consensus leaves it to clinical judgment. In practice, younger patients and anyone with recent change are often scanned at intervals of roughly six to twelve months, while stable adults may be seen less frequently. Factors such as eye rubbing, allergy, family history or a changing lens fit can prompt an earlier visit. Your specialist will set the schedule based on your own scans.
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Living With Macular Degeneration: Lighting, Magnifiers and the Grid Check Between Visits
Living with macular degeneration usually means protecting the sight you still have and using it well: bright, glare-free task lighting, high-contrast surroundings, a magnifier…

Living With an Ocular Prosthesis: Cleaning Routines, Sleep, Sport and When to Refit
Living with a prosthetic eye usually means wearing it day and night, cleaning it only occasionally with mild soap and water, and having an…

Contact Lenses, Glasses or Laser Surgery: When Contacts Are the Sensible Next Step
Contact lenses are usually the sensible next step when glasses feel limiting but your prescription is still changing, you are under 18, or you…

How a Chalazion Forms From a Blocked Oil Gland and Why Some Linger for Months
A chalazion is a firm, usually painless eyelid lump caused by a blocked meibomian oil gland, not an infection. Most shrink on their own…

Why LASEK Vision Sharpens More Slowly Than LASIK and What the Final Result Looks Like
LASEK lifts and repositions the cornea's thin surface layer rather than cutting a flap, so the eye has to regrow that layer before light…

Returning to Work and Screens After PRK: Planning Time Off Around Surface Healing
Most people who have PRK need roughly a week away from desk work, because the eye's surface layer takes about three to five days…