

Kidney Transplant Evaluation Explained: Blood Tests, Tissue Typing, Imaging and Interviews

Key Takeaways
- The six markers in tissue typing are two antigens each at HLA-A, HLA-B and HLA-DR, and most transplants proceed with some mismatch rather than a perfect six-of-six.
- In the United States, waiting time for a deceased donor kidney begins accruing once estimated GFR is 20 or lower or dialysis starts, not from the day you are listed.
- Only three of the roughly thirteen evaluation components are about matching; the rest assess your heart, infection status, cancer risk and support network.
- Age alone, diabetes, controlled HIV and treated hepatitis are not exclusions; active cancer, untreated infection and unimprovable severe heart disease are the findings that most often stop a listing.
- A deferral is not a refusal: dental treatment, a cardiology procedure or a supervised nutrition plan typically comes with a defined route back to the committee.
- Antibody screens are repeated while you wait because pregnancy, transfusion and infection can change your PRA, and a final crossmatch is run in the hours before any offer is accepted.
A kidney transplant evaluation is a series of blood tests, tissue typing, imaging studies and interviews that a transplant team uses to judge whether surgery is likely to be safe and whether a donor kidney could be matched to you. It usually unfolds over several appointments, checks your heart, blood vessels, infection history and cancer risk, and ends with the team deciding whether to list you, ask you to wait, or recommend another path.
The referral letter arrives with a phone number and a sentence that sounds simple: please call to schedule your transplant evaluation. What follows is anything but a single visit. Most people are handed a folder, a list of fasting instructions and a calendar that fills with vials, scanners and conversations with strangers who ask about their childhood illnesses and their support at home.
It can feel like an audition. It is closer to an engineering inspection. Kidney transplant evaluation tests exist because a new kidney only helps if the body receiving it can tolerate the surgery, the medicines that follow and years of follow-up. Each test answers one narrow question, and the team assembles the answers into a decision.
This explainer walks through what actually happens, why the six tissue markers matter, what the imaging is really looking for, and which findings tend to pause a listing rather than end it.
What are kidney transplant evaluation tests, and why are there so many?
A kidney transplant evaluation is a structured medical review that decides two things: whether a transplant is likely to be safe for you, and how a donor organ might be matched to your immune system. Programs bundle the work into blood tests, tissue typing, imaging, a physical exam and a set of interviews, then meet as a committee to weigh the results (Mayo Clinic).
The reason for the volume is that transplant surgery asks a lot of a body already weakened by kidney failure. The operation is several hours long under general anesthesia. Afterward, you take immunosuppressants, medicines that damp down the immune system so it does not attack the new organ. Those medicines raise the risk of infection and of some cancers, so the team needs to know in advance what infections you have already met and whether any tumor is hiding.
Think of it in three layers:
- Is your heart and circulation strong enough to survive the operation and recover from it?
- Is there any active infection, cancer or untreated illness that immunosuppression would make worse?
- What does your immune system look like, so a donor kidney can be selected that it is least likely to reject?
Each layer maps to a set of kidney transplant evaluation tests. The first layer is mostly imaging and heart testing. The second is blood work, cancer screening and dental review. The third is tissue typing and antibody testing. The interviews sit across all three, because a transplant also has to fit into a real life with transport, medicine routines and someone to help in the first weeks.
None of these tests produces a score that decides your fate on its own. The committee reads them together, and a finding that looks alarming in isolation is often simply something to treat first and recheck later.
Who is usually referred for evaluation, and who is asked to wait?
Evaluation is generally offered to adults and children with advanced chronic kidney disease or kidney failure who are expected to live long enough to benefit and who are well enough for major surgery (NHS). You do not have to be on dialysis to be referred. A transplant performed before dialysis starts is called pre-emptive, and nephrologists often raise the subject once kidney function falls into the range where failure is approaching.

Age by itself is not a barrier. Programs assess biological fitness rather than birth year, and many people in their seventies are listed after a satisfactory heart work-up (NHS). What matters is whether the whole picture suggests the transplant would help more than it harms.
People are usually asked to wait, rather than declined outright, when something fixable is found. Common examples include:
- An active infection, from a dental abscess to hepatitis, that needs treatment before immunosuppression can begin.
- A recent cancer, where the team waits for a disease-free interval that depends on the tumor type.
- Untreated coronary artery disease or severe heart valve problems that would make the operation dangerous.
- Ongoing substance use disorder or a pattern of missed dialysis and medicines that suggests the post-transplant routine would be hard to keep, where support is offered first.
- Body weight or nutritional status outside a program’s surgical safety range, where a supervised plan and re-evaluation are offered.
A smaller group is advised that transplant is unlikely to be the right path at all: for example, someone with a severe, progressive illness elsewhere in the body that limits life expectancy to a short window, or a person who cannot tolerate anesthesia. Even then, most programs allow reassessment if circumstances change (Mayo Clinic).
The distinction between wait and no is worth asking about directly. Many people leave the first appointment believing they were rejected when the team actually wrote a to-do list.
At what GFR should you get a kidney transplant?
GFR, the glomerular filtration rate, is an estimate of how many milliliters of blood your kidneys filter each minute; a healthy young adult sits above 90. The number is estimated from a blood creatinine level, your age and sex, and it is the single figure that drives referral timing.
In the United States, the allocation system lets a person begin accumulating waiting time once their estimated GFR is 20 or lower, or once they start dialysis, whichever comes first (NIDDK). Because the evaluation itself takes time, nephrologists commonly refer patients well before that threshold, often once GFR trends into the twenties and is still falling. The NHS similarly describes assessment beginning as kidney function approaches the point where dialysis will be needed rather than after it.
Why not transplant earlier, at a GFR of 30 or 40? Because a person with that much residual function may live for years without dialysis, and immunosuppressants carry their own risks. The kidney is offered when the expected benefit clearly exceeds the burden of the medicines.
Why not wait until dialysis is well established? Because time on dialysis is associated with worse outcomes after transplant, and a pre-emptive transplant avoids the vascular access surgery and the cardiovascular strain that dialysis brings (NIDDK). This is a general association reported in guideline summaries, not a promise about any individual.
Two practical points follow. First, if your GFR is in the twenties and no one has mentioned transplant, it is reasonable to ask your nephrologist whether a referral makes sense. Second, GFR below 20 is a listing threshold, not a deadline: many people are listed at 15 or 18 and wait months or years for an offer while remaining under review. The decision about when to list sits with your kidney team.
Blood tests in a kidney transplant evaluation: what the lab is looking for
Expect the first visit to draw more tubes than you have ever seen at once. The panel is broad because each result closes off a different risk (MedlinePlus).
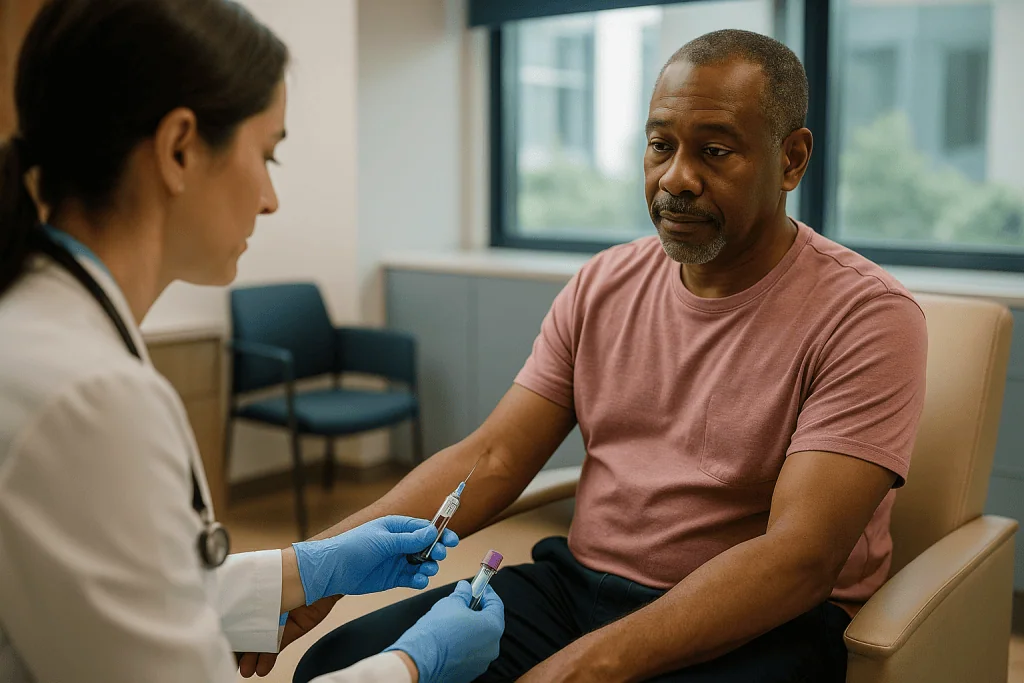
The core groups are:
- Kidney and metabolic chemistry. Creatinine, urea, potassium, phosphate, calcium and parathyroid hormone show how advanced the failure is and whether bone and mineral balance needs correcting before surgery.
- Blood count and clotting. Anemia is common in kidney failure and affects how the anesthesia team plans the operation; clotting tests flag bleeding risk during surgery.
- Liver tests and glucose. Liver disease changes how immunosuppressants are processed, and undiagnosed diabetes matters because some anti-rejection drugs can raise blood sugar.
- Infection serology. Blood is checked for HIV, hepatitis B and C, cytomegalovirus (CMV), Epstein-Barr virus, syphilis and often tuberculosis exposure. A positive result rarely excludes you; it changes the plan. CMV status, for instance, guides which protective medicines are used after transplant, and hepatitis B or C can usually be treated first.
- Blood group. Your ABO type is the first compatibility gate for any donor kidney.
- Tissue typing and antibody screening. These immune tests are described in the next two sections.
Vaccination titers are often checked too, because live vaccines cannot be given once immunosuppression starts. Catching up on hepatitis B, pneumococcal and other vaccines during evaluation is one of the quieter but more valuable outcomes of the process (CDC guidance on immunocompromised adults).
Urine is analyzed as well, when you still produce it, to look for infection and protein. If you are on dialysis, some of these labs are drawn around a session so results reflect your usual state. Results are typically reviewed at a follow-up visit, and abnormal values often lead to a referral to another specialist rather than a change in your transplant status.
What are the 6 markers for kidney transplant? HLA typing explained
The six markers people ask about are human leukocyte antigens, or HLA: proteins on the surface of almost every cell that your immune system uses to tell self from foreign. Each person inherits one set from each parent, so at the three locations most relevant to kidney transplant, HLA-A, HLA-B and HLA-DR, you carry two antigens apiece. That makes six.
Tissue typing, also called HLA typing, is a blood test that identifies which six you carry. When a donor kidney becomes available, the donor’s six are compared with yours. A six-out-of-six match means every antigen is identical; a zero mismatch is the same thing stated the other way around. Most transplants happen with some degree of mismatch, and modern immunosuppression is designed to manage that (NHS).
Why does HLA matter more than blood group? Blood group is a gate: incompatible and the kidney is not offered. HLA is a gradient: a closer match is associated with a lower risk of rejection and longer graft function in population studies, but a well-matched kidney is not a guarantee and a poorly matched one is not doomed (MedlinePlus). Siblings have a one-in-four chance of a full match, which is why family members are often tested first when a living donor is being considered.
HLA typing also has a second purpose. Once your antigens are known, the lab can predict which donors your existing antibodies would react against, a topic covered next.
Two points people find reassuring. First, the test is done once; your HLA type does not change. Second, the modern allocation system in the United States gives priority for certain very well-matched kidneys and for people who are hard to match, so the typing works in your favor rather than simply narrowing options (NIDDK).
Blood group, antibodies and the crossmatch
Three immune tests decide whether a specific kidney can be offered to you. They build on each other.
ABO blood group. Kidney donation follows the same rules as blood transfusion: group O donors can give to anyone, group AB recipients can receive from anyone, and the others match within type. Some programs perform ABO-incompatible living donor transplants after removing antibodies, but that is a specialized pathway discussed case by case (NHS).
Antibody screening, or PRA. Panel reactive antibody testing checks your blood against a panel of common HLA types to see how many you already react to. The result is expressed as a percentage: a calculated PRA of 80 percent means your antibodies would attack roughly 80 percent of the donor population. Antibodies form after pregnancy, blood transfusion or a previous transplant, which is why women who have carried children and people with a failed first graft often test higher. A high PRA does not exclude you; it makes matching harder, and US allocation policy awards additional priority to highly sensitized candidates for that reason (NIDDK). The test is usually repeated at intervals while you are listed because antibody levels change.
Crossmatch. This is the final check, done when a specific donor is identified. A sample of your blood is mixed with donor cells to see whether your antibodies bind to them. A positive crossmatch predicts immediate, severe rejection and stops the transplant. A negative crossmatch clears the way. For deceased donor offers this happens quickly, often in the hours before surgery, which is one reason you are asked to keep a phone charged and reachable.
Programs increasingly run a virtual crossmatch first, comparing your known antibodies against the donor’s typed antigens on a computer, then confirming with the laboratory test.
Imaging in the kidney transplant work-up: heart, blood vessels and bladder
Imaging answers a mechanical question: can the surgeon safely plumb a new kidney into your pelvis, and will your heart cope with the operation?
The common studies are:
- Chest X-ray. A baseline look at the lungs and heart size, and a check for old tuberculosis scarring or fluid.
- Electrocardiogram and echocardiogram. The ECG records electrical rhythm; the echocardiogram is an ultrasound that shows how well the heart pumps and whether the valves leak. Heart disease is the leading cause of death in people with kidney failure, so this step is never skipped (American Heart Association).
- Stress testing. If you have diabetes, are older, or have symptoms, a treadmill or medicine-induced stress test looks for reduced blood flow to the heart muscle. An abnormal result can lead to a coronary angiogram, an X-ray of the heart arteries using contrast dye, and sometimes to a stent or bypass before listing.
- Pelvic and abdominal ultrasound or CT. The donor kidney is placed low in the abdomen and connected to the iliac blood vessels. Imaging checks those vessels for calcification or narrowing that would complicate the join, and looks at your own kidneys and bladder.
- Bladder studies. If you have a history of urinary problems, a test of bladder emptying or a cystoscopy, a camera examination of the bladder, may be arranged, because the new ureter has to drain into a bladder that works.
Contrast dye is used cautiously in people with residual kidney function, and the team will time studies around dialysis when necessary (Mayo Clinic).
Findings from imaging are among the most frequent reasons an evaluation is paused. A blocked coronary artery or heavily calcified pelvic vessels are treatable or plannable problems, and the surgeon would far rather know now than discover them under anesthesia.
Cancer screening, dental checks and infection review
Immunosuppression lowers the body’s surveillance against abnormal cells and microbes. Anything that is quietly smoldering before transplant tends to flare afterward. The evaluation therefore borrows the full menu of age-appropriate cancer screening and adds a few extras (Mayo Clinic).
Depending on your age, sex and history, expect:
- Colonoscopy or a stool-based test for colorectal cancer.
- Mammography and cervical screening.
- Prostate assessment.
- Skin examination, since skin cancers are the most common malignancy after transplant.
- Imaging of your own kidneys, because long-standing kidney disease and cystic kidneys carry a higher rate of kidney tumors.
Screening that is already up to date is simply documented; the team is not trying to repeat what your primary care physician has done.
The dental review surprises people. An infected tooth root is a reservoir of bacteria that can seed the bloodstream once immune defenses drop, so most programs ask for a dentist’s letter confirming there is no active disease. Treatment of gum disease or extraction of unsalvageable teeth happens before listing, not after.
Infection review is broader than the blood serology. The team asks about travel and residence, because exposure to tuberculosis or certain fungal infections changes the preventive medicines used later. Vaccination records are gathered, and anything missing that can safely be given is scheduled during evaluation (CDC).
People who have had a cancer in the past are not automatically excluded. Guidelines describe waiting periods that vary with the tumor type and stage, ranging from no wait for some very low-risk lesions to several years for others, and the transplant team usually consults your oncologist rather than applying a blanket rule (NHS). The purpose throughout is to start immunosuppression into a body with as few hidden problems as possible.
The interviews: social work, psychology, nutrition and coordination
The conversations feel less clinical than the scans, and some people brace for judgment. In practice they are a fit check, not a character test, and they often unlock help that would otherwise never be offered.
Transplant coordinator. A nurse who becomes your main contact. The interview covers your medical history in detail, current medicines, previous surgeries and how you have managed dialysis.
Social worker. Asks about who lives with you, who could drive you to the hospital at short notice, and who could stay with you in the first weeks after surgery when you cannot drive or lift. Transport to frequent early follow-up visits is a genuine safety issue, not an administrative one. The social worker also discusses insurance coverage for long-term medicines in general terms and connects you with support programs; no one is expected to solve this alone (Mayo Clinic).
Psychologist or psychiatrist. Screens for depression, anxiety and cognitive difficulty, all common in kidney failure and all treatable. Untreated depression is associated with missed medicines after transplant, so identifying it is protective. Questions about alcohol, tobacco and other substances are asked of everyone.
Dietitian. Reviews weight, muscle mass and eating patterns. Nutrition before surgery affects wound healing, and the dietary rules after transplant differ sharply from dialysis rules, so education starts here.
Pharmacist. In many programs, a pharmacist walks through the future medicine routine so you know what a typical day would involve before you commit.
Surgeon and nephrologist. The physical exam, discussion of surgical risk and alternatives, and the chance to ask what the team is worried about.
Bring a family member or friend. Most programs encourage it, and a second set of ears catches half of what you will forget.
Kidney transplant evaluation tests at a glance
The table below groups the common components by the question each one answers. Not every person has every test; the list is tailored to age, history and what earlier results show (Mayo Clinic; NHS).
| Component | What it involves | Question it answers |
|---|---|---|
| Blood chemistry and blood count | Venous blood draw | How advanced is kidney failure; is anemia or mineral imbalance present? |
| Infection serology | Blood tests for HIV, hepatitis B and C, CMV, EBV, syphilis, TB exposure | Which infections need treatment or prevention before immunosuppression? |
| ABO blood group | Blood test | Which donors are compatible at the first gate? |
| HLA typing | Blood test, done once | What are your six tissue markers for matching? |
| Antibody screen (PRA) | Blood test, repeated periodically | How many donors would your antibodies react against? |
| Crossmatch | Your blood mixed with donor cells, at time of offer | Is this specific kidney safe to transplant? |
| ECG and echocardiogram | Electrodes; chest ultrasound | Can the heart tolerate surgery? |
| Stress test, sometimes angiogram | Treadmill or medicine test; catheter X-ray if needed | Is coronary disease present and treatable? |
| Chest X-ray | Standard film | Lung and heart baseline |
| Abdominal and pelvic imaging | Ultrasound or CT | Are the pelvic vessels and bladder suitable? |
| Cancer screening | Age-appropriate tests | Is any tumor present? |
| Dental clearance | Dentist’s examination and letter | Is there hidden oral infection? |
| Interviews | Coordinator, social work, psychology, dietitian, pharmacist, surgeon | Does transplant fit safely into your life and support network? |
Reading it as a whole, notice that only three rows, blood group, HLA and crossmatch, are about matching. Everything else is about you, and most of it is about making the surgery and the years afterward as safe as they can be.
What happens in the weeks after the evaluation?
The evaluation itself is usually spread over several appointments, and programs commonly describe the process taking weeks to a few months from first visit to committee decision, longer if specialist referrals are needed (Mayo Clinic; NHS). Some centers compress much of it into one or two long days; others run it alongside your dialysis schedule. Increasingly, the interview portions are offered by video, with in-person visits reserved for examination and tests.
Once results are in, the multidisciplinary committee meets and reaches one of a few outcomes:
- Listed. You are placed on the national waiting list for a deceased donor kidney, and your waiting time is credited from the date your GFR fell to 20 or lower or dialysis began, not from the date of listing (NIDDK).
- Listed with a living donor pathway. If someone has offered to donate, their evaluation begins in parallel, and surgery is scheduled rather than awaited.
- Deferred. Specific items must be completed first: a cardiology procedure, dental work, a period of cancer surveillance, a supervised nutrition plan. You are told exactly what and roughly when to return.
- Not a candidate at this time. Explained in person, with reasons, and usually with the option to be reassessed if circumstances change.
Being listed is not the end of testing. Antibody screens are repeated at intervals, and blood samples are stored at the tissue typing laboratory so a crossmatch can be run the moment an offer arrives. Annual or more frequent reviews check that the heart work-up is still current, because waiting times for a deceased donor kidney in the United States are often measured in years (NIDDK).
During the wait, you are expected to report new symptoms, hospital admissions, transfusions and pregnancies, since each can alter your antibody profile or your surgical fitness. A number you can call at any hour is standard.
What disqualifies you from a kidney transplant? What people often get wrong
Much of the anxiety around evaluation comes from half-truths passed between dialysis chairs. Several deserve correction.
Myth: there is an age cutoff. There is not. Programs assess fitness, and healthy older adults are listed regularly. Frailty and heart disease matter; the number on a birth certificate does not (NHS).
Myth: diabetes disqualifies you. Diabetes is the most common cause of kidney failure among people who receive transplants. It prompts more careful heart screening, not exclusion.
Myth: a positive hepatitis or HIV test ends the process. Controlled HIV and treated hepatitis C are compatible with transplant at most programs. These findings change the plan rather than close it (Mayo Clinic).
Myth: you must be on dialysis first. Pre-emptive transplant is encouraged where possible; dialysis is not a prerequisite (NIDDK).
Myth: a perfect six-antigen match is required. Most transplants proceed with mismatches. Match quality influences risk, but immunosuppression is designed for imperfect pairs.
Myth: being told to lose weight or fix your teeth is a polite rejection. It is a deferral with a route back. Programs set weight and dental criteria for surgical safety, and re-evaluation is the expected next step.
Myth: a living donor must be a blood relative. Spouses, friends and even strangers can donate if compatible, and paired exchange programs can pair an incompatible donor with another recipient.
What does tend to stop a listing: active, untreated cancer; an active systemic infection; severe heart or lung disease that cannot be improved; ongoing substance use disorder without treatment; and a condition elsewhere in the body that limits life expectancy to a short period (NHS). Even these are judgments made by a committee about a particular person, and asking the team to explain its reasoning is always appropriate.
Questions to ask your care team during evaluation
The evaluation is the one stretch of the transplant journey when time is on your side and every relevant specialist is in the room. Use it. The questions below are the ones that experienced coordinators say people wish they had asked earlier.
- Which of my results are you most concerned about, and what would change your view?
- Am I being listed, deferred or declined, and if deferred, what exactly needs to happen before I return?
- From what date will my waiting time be counted?
- What is my blood group and calculated PRA, and how do they affect how long I am likely to wait?
- Would you accept a living donor for me, and who should a potential donor contact?
- Would I be considered for kidneys from donors with higher risk profiles, such as older donors or those with treated hepatitis C, and what would that mean for me?
- What will a typical day of medicines look like after transplant, and how will I know if I am reacting badly to them?
- How often will I need to come back in the first three months, and how will I get there?
- What symptoms after surgery should make me call immediately?
- If the transplant fails, what happens next?
- Who do I call between appointments, and at what hours?
- Are there vaccines I should receive now, before immunosuppression?
Write the answers down or ask permission to record the conversation. Bring your current medicine list, including supplements and over-the-counter products, because some interact with immunosuppressants and the pharmacist will want to review them (Mayo Clinic).
One more question people rarely ask: what are the alternatives if I choose not to proceed? Continued dialysis, a different dialysis modality and conservative kidney management are all legitimate paths, and a good team will discuss them without pressure. The decision to list, and the decision to accept an offer when it comes, both remain yours in partnership with the treating team.
When to call your doctor: red flags during evaluation, on the list and after transplant
Three periods carry their own warning signs.
During evaluation. Some tests carry small risks. Seek urgent care for chest pain or breathlessness after a stress test, for heavy bleeding, swelling or a cold, pale limb after an angiogram, or for fever, severe pain or blood in the urine after a cystoscopy or biopsy. Tell your kidney team promptly about any new infection, hospital stay or blood transfusion, because each can change your antibody profile and your listing status (Mayo Clinic).
While waiting. Report new chest pain, fainting, unexplained weight loss, a new lump, or a skin lesion that changes. The heart and cancer work-up needs to stay current, and these symptoms may trigger a repeat test. Missing dialysis or being unreachable by phone can also cost you an offer, so update the coordinator whenever your number or address changes.
After transplant. People often ask what the first signs of a transplant failing look like. Rejection is frequently silent in its early stages and is caught on routine blood tests, which is why early follow-up is so frequent. When symptoms do appear, the ones that should prompt a same-day call to the transplant team include (MedlinePlus; Mayo Clinic):
- Fever or chills.
- A sharp fall in urine output, or rapid weight gain and swelling of the legs or face.
- Pain or tenderness over the new kidney, which sits low in the abdomen.
- Rising blood pressure that is unusual for you.
- Flu-like aching or a general sense of being unwell.
- Any missed doses of anti-rejection medicine, whether through vomiting, illness or supply problems.
Call emergency services for chest pain, severe shortness of breath, confusion, or a wound that is bleeding heavily or gaping. Never stop, skip or adjust an anti-rejection medicine on your own, even if you feel well or suspect a side effect; call the team and let them decide. Most early problems, including many episodes of rejection, can be treated when they are reported quickly.
Frequently asked questions
What disqualifies you from a kidney transplant?
Absolute barriers are few: active untreated cancer, an active systemic infection, severe heart or lung disease that cannot be improved enough for surgery, ongoing substance use disorder without treatment, and a separate illness that sharply limits life expectancy. Most other findings, including obesity, dental infection or a past cancer, lead to a deferral with conditions rather than a refusal, and the committee’s reasoning can be reviewed if circumstances change.
What are the 6 markers for kidney transplant?
They are human leukocyte antigens at three sites: HLA-A, HLA-B and HLA-DR. You inherit one antigen at each site from each parent, giving six in total. Tissue typing identifies yours once; the donor’s six are compared at the time of an offer. Closer matches are associated with lower rejection risk in population data, but a full match is not required and mismatched transplants are routine.
At what GFR should you get a kidney transplant?
US allocation policy lets waiting time start once estimated GFR is 20 or lower or dialysis begins. Because evaluation takes weeks to months, nephrologists usually refer people when GFR is in the twenties and falling. Transplant before dialysis, called pre-emptive, is encouraged where possible. The exact timing of referral and listing is a decision for your kidney team based on your trajectory and overall health.
What are the first signs of a kidney transplant failing?
Early rejection is often silent and detected on routine blood tests, which is why follow-up is frequent. Symptoms that warrant a same-day call to the transplant team include fever, a sudden drop in urine output, rapid weight gain or swelling, pain over the new kidney, unusually high blood pressure and flu-like aching. Reported quickly, many episodes can be treated. Never adjust anti-rejection medicines without the team’s instruction.
How long does a kidney transplant evaluation take?
Programs commonly describe the process taking several weeks to a few months from the first appointment to a committee decision, spread over multiple visits. It runs longer if specialist referrals, such as a cardiology procedure or dental treatment, are needed first. Some centers condense the tests into one or two long days, and interview components are increasingly offered by video, with in-person visits kept for examination and imaging.
What are the kidney transplant waiting list criteria?
In general terms, you need advanced kidney disease with an estimated GFR of 20 or below or to be on dialysis, no active cancer or untreated serious infection, a heart and circulation judged able to tolerate surgery, and a realistic plan for medicines, transport and support after transplant. The transplant committee applies these criteria to your full evaluation and explains its decision, including any conditions for re-review.
Is HLA typing for kidney transplant done every time a kidney is offered?
No. Your HLA type is inherited and does not change, so typing is done once during evaluation. What is repeated is antibody screening, because antibodies against foreign HLA can rise after transfusion, pregnancy or infection. When a specific kidney is offered, a crossmatch mixes your stored blood with donor cells to confirm your antibodies do not react, and a positive result cancels that particular offer.
Can you be too old for a kidney transplant?
There is no fixed upper age limit. Programs assess physical fitness, heart health and frailty rather than chronological age, and adults in their seventies are listed when the work-up is satisfactory. Older candidates may be offered kidneys from older donors through matching schemes. Whether transplant is likely to help more than continued dialysis in an individual case is a judgment made jointly with the treating team.
Why do I need a dental check before a kidney transplant?
Anti-rejection medicines lower the immune system’s ability to contain infection. An infected tooth root or advanced gum disease can release bacteria into the bloodstream, which is far more dangerous once immunosuppression begins. Most programs therefore require a dentist’s letter confirming no active oral disease, and any needed treatment or extractions are completed before listing rather than after surgery.
Do I have to be on dialysis before I can be evaluated?
No. Evaluation can begin while you still have some kidney function, and a pre-emptive transplant performed before dialysis starts avoids access surgery and the cardiovascular burden of dialysis. Time already spent on dialysis is associated with worse outcomes in guideline summaries, which is one reason early referral is encouraged. Ask your nephrologist about referral once your GFR falls into the twenties.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Life After a Kidney Transplant: Diet, Exercise, Travel and the Habits That Protect the Graft
Life after a kidney transplant usually means taking anti-rejection medicines every day for as long as the kidney works, keeping regular clinic and blood-test…

How a Kidney Transplant Is Performed: Where the New Kidney Goes and What Happens to the Old
A kidney transplant is performed under general anesthesia through an incision in the lower abdomen. The surgeon places the donated kidney in the pelvis,…

Liver Transplant Evaluation: Heart, Lung, Kidney and Infection Checks Before Listing
A liver transplant evaluation is a structured series of heart, lung, kidney, infection, cancer-screening and psychosocial tests that a transplant team uses to decide…

What Liver Transplant Recovery Looks Like: Intensive Care, the Transplant Unit and Months After
Liver transplant recovery usually begins with a few days in intensive care, followed by roughly one to two weeks on a transplant ward, then…