

Lifting, Bending and Sitting After Herniated Disc Surgery: Habits That Protect the Repair

Key Takeaways
- The operation frees the nerve but leaves the tear in the disc wall to heal on its own, which is why lifting limits run for weeks even though the skin closes in about two.
- Mainstream patient guidance keeps early lifting to roughly 5–10 pounds, about a gallon of milk, and raises the ceiling only after the surgeon's review, typically near six weeks.
- Slumped sitting loads the lumbar disc more than standing, so breaking up sitting every 20–30 minutes in the first weeks protects the disc as much as avoiding heavy lifts.
- Bending and twisting together is the combination the healing annulus tolerates least; the hip hinge and turning with your feet remove most of that stress.
- Recurrent herniation is reported in roughly 5 to 15 of every 100 people and clusters in the first months, with smoking, early heavy lifting and excess weight among the modifiable risks.
- Graded programs commonly place unrestricted heavy training at 3 to 6 months, and the disc level operated on (L3-L4 versus L5-S1) does not change the disc's healing timeline.
After herniated disc surgery, most surgical teams ask patients to avoid lifting anything heavier than a light grocery bag, roughly 5 to 10 pounds, for the first two to six weeks, to bend from the hips and knees rather than the waist, and to break up sitting every 20 to 30 minutes. Timelines depend on the operation and your job, so final clearance always comes from your treating team.
Ask someone three weeks out from a discectomy what frightens them, and it is rarely the incision. It is the laundry basket. It is the toddler with arms up, the suitcase on the carousel, the bag of potting soil that has been waiting by the garage door. Lifting after herniated disc surgery turns into a private negotiation: how much, how soon, and what happens if I get it wrong.
The worry is understandable, but it is usually aimed at the wrong target. The operation frees a nerve. It does not rebuild the disc, and it does not leave the spine fragile. What it leaves is a small healing opening that needs a few weeks of sensible loading.
This explainer walks through what the surgery actually does, why bending and sitting matter as much as lifting, what the first weeks tend to look like, how people get back to the gym, and which signs mean you should pick up the phone.
Why lifting after herniated disc surgery worries people more than the operation itself
Once the anesthetic wears off and the leg pain eases, a new preoccupation takes over: every object in the house acquires a weight. People weigh kettles in their minds. They eye the recycling bin with suspicion. The fear is not irrational, but it deserves a clearer target.
A discectomy removes the fragment of disc pressing on a nerve. What remains is a small window in the tough outer wall of the disc, called the annulus, through which the original fragment escaped. That window is the weak point for the first several weeks, and every sensible instruction about lifting, bending and sitting comes back to one goal: keep pressure inside the disc from spiking while the tissue scars over.
Posture changes that pressure dramatically. Classic measurements of pressure inside the lumbar discs, summarized in mainstream spine reviews, show that slumped sitting and lifting with a rounded back load the disc far more than standing or lying down. Mayo Clinic’s patient information on diskectomy frames early recovery around exactly these habits: limiting lifting, bending and twisting while the surgical site heals.
So the honest framing is this. You are not guarding a mended vase. You are protecting a healing edge, for a defined period, by changing how you move rather than by not moving at all. The habits involved are small, and most people keep them long after the restrictions end, because they turn out to be how a back prefers to be used anyway.
What actually happens in a discectomy, and what the 'repair' really is
A lumbar disc sits between two vertebrae like a jelly-filled cushion: a soft center, the nucleus, wrapped in rings of tough fiber, the annulus. A herniation means part of the soft center has pushed through a tear in those rings and is pressing on a spinal nerve, producing the leg pain, numbness or weakness known as sciatica. MedlinePlus describes the surgery, a diskectomy or discectomy, as removal of the protruding piece so the nerve is no longer compressed.
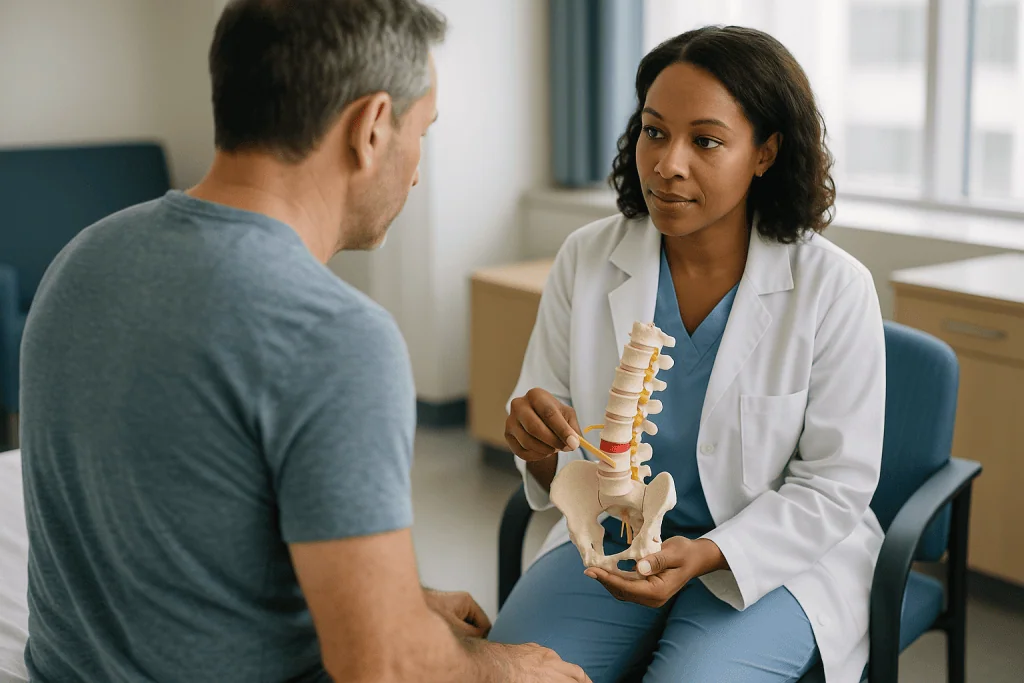
In the most common version, a microdiscectomy, the surgeon works through a small incision with a microscope or magnifying lenses, moves the back muscles aside, sometimes removes a sliver of bone (a laminotomy) to reach the nerve, lifts the nerve root gently and takes out the loose fragment. Cleveland Clinic notes that the procedure often takes about an hour and many people go home the same day or the next. Tubular and endoscopic instruments exist, but the goal is identical: decompress the nerve.
Here is the part patients often miss. The surgeon does not stitch the disc shut. The tear in the annulus is left to heal by scarring, and the disc ends up a little thinner than before. There is no repair in the sense of a patched tire.
That explains the two things people notice first. Leg pain often eases quickly because the compression is gone, while the back feels sore because muscle and bone were disturbed. It also explains why the rules focus on the disc rather than the skin. The incision closes in about two weeks; the annulus takes considerably longer, which is why lifting guidance runs to weeks rather than days.
Who is usually cleared for early activity, and who is asked to wait
Restrictions are not one-size-fits-all, which frustrates anyone comparing notes online. Someone with a single-level microdiscectomy for a fresh herniation, a desk job and an otherwise healthy spine is usually told to walk from day one and may return to light work within a couple of weeks. MedlinePlus reports that many people go back to work in 2 to 6 weeks, while those in physically demanding jobs are often asked to wait longer, commonly 6 to 8 weeks or more.
Others are steered toward patience. A larger opening in the annulus, a herniation that recurred and was operated on again, surgery at two levels, or a fusion done alongside the decompression all change the calculation. Fusion, in which two vertebrae are joined with bone graft and hardware, needs months for bone to knit, and its lifting rules follow that slower biology. Mayo Clinic also flags smoking, diabetes and conditions that slow healing as reasons for more conservative advice.
Body weight matters too, stated plainly and without judgment: carrying more weight increases the mechanical load on every lumbar disc during bending, so the same movement asks more of the healing tissue.
Then there is the question of who should not be lifting yet regardless of the calendar. Persistent leg pain that has not settled, new weakness, or a wound that is not closing all pause the timeline. Surgeons typically check at around two weeks and again near six, and it is at those visits that restrictions are loosened. If you have not been told you are cleared, you are not cleared. The default is always the more careful path.
Bending after microdiscectomy: the hip hinge that spares your spine
Bending is where good intentions collapse. You promise yourself you will not lift, then drop a sock and fold in half to retrieve it. That fold, rounding the lower back to reach the floor, is the movement the annulus tolerates least, because flexion pushes the nucleus backward toward the healing tear.

The alternative is the hip hinge, and it is worth practicing before you need it. Stand with feet about hip width apart. Soften the knees. Push the hips back as if closing a car door with your backside, keeping the chest tall and the spine in its natural curve. The torso tilts from the hips, not the waist. To reach lower, bend the knees more rather than rounding. To return, drive the hips forward. Done well, the back stays quiet and the thighs and buttocks do the work.
For floor-level tasks in the first weeks, use a lunge or a golfer’s lift: one hand on a stable surface, one leg extending behind you for balance as you tip forward. A long-handled grabber, a shoehorn and slip-on shoes remove the most frequent daily bends. Keep everyday items between waist and shoulder height so cupboards do not demand a fold.
Twisting while bent is the other habit to retire for now. Reaching across the body to pull a bag from the passenger seat, or turning to load a dishwasher, combines flexion and rotation, the pairing that biomechanics studies identify as most stressful for the disc. Turn your whole body with your feet instead.
None of this means never bending forward again. Rehabilitation reintroduces gentle, controlled flexion over the weeks, because a spine that never bends becomes stiff and fearful. The aim is to avoid loaded, repeated, end-range rounding while the tear is fresh.
Sitting after discectomy: why the chair is the sneaky one
Nobody counts sitting as an activity, yet pressure measurements inside the lumbar disc show that unsupported sitting, especially slumped, loads the disc more than standing, and sitting while leaning forward loads it more still. After a discectomy, many people find that 20 minutes on a soft sofa produces a deep ache in the back or leg that a short walk eases within minutes.
Patient guidance from Cleveland Clinic and MedlinePlus discharge instructions converges on a simple early rule: sit for short spells, generally 20 to 30 minutes at a time, then stand and walk briefly before sitting again. This is not about a stopwatch; it is about not letting stiffness and pressure accumulate.
When you do sit, choose a firm chair with a backrest over a low sofa. Keep hips level with or slightly above the knees, feet flat, and try a small rolled towel in the curve of the lower back. Recliners are fine if they preserve a gentle lumbar curve rather than folding you at the waist. Getting up matters as much as sitting: slide to the edge, place feet under you, hinge at the hips and push through the legs rather than jerking the torso.
Car seats deserve special mention. They are low, soft and angled in ways that round the back, and the road adds bumps you cannot control. Most teams ask people not to drive until they are off sedating pain medicines, can twist to check mirrors comfortably and can brake hard without hesitation; Mayo Clinic suggests this is often within one to two weeks, but clearance is individual. As a passenger, break early trips into roughly 30-minute segments where practical.
A raised toilet seat and a shower instead of a bath remove two deep daily bends at a stroke.
Lifting after herniated disc surgery: a week-by-week picture
Every surgical team writes its own protocol, and yours overrides anything printed here. Still, people want the shape of the road, so this is how patient education from MedlinePlus, Mayo Clinic and Cleveland Clinic typically frames lifting after herniated disc surgery for a single-level lumbar discectomy without fusion. Weights are everyday approximations, not measured thresholds.
| Phase | Typical lifting guidance | Everyday equivalent | Bending and sitting |
|---|---|---|---|
| Days 1–14 | Nothing heavier than about 5–10 lb (2–4.5 kg) | A gallon of milk; a small bag of groceries | Hip hinge only; sit 20–30 minutes, then move |
| Weeks 2–6 | Gradual increase if cleared, often toward 15–25 lb | A full laundry basket; a toddler, with care | Light bending reintroduced in therapy; longer sitting as tolerated |
| Weeks 6–12 | Progressive loading under physical therapy guidance | Carry-on suitcase; gardening tasks | Most daily bending returns; ergonomic sitting continues |
| After 12 weeks | Return toward normal, gym included, with technique | Whatever your job or sport requires | Unrestricted for most; lifelong hip-hinge habit |
Two things the table cannot show. First, how you lift matters as much as what you lift: a 10-pound box held at arm’s length with a rounded back loads the disc more than a 20-pound box held against the body after a hip hinge, because leverage multiplies force at the spine. Second, the pace through weeks 6 to 12 is set by your surgeon’s examination and your symptoms, not the calendar. If a lift reproduces leg pain, tingling or weakness, that is the healing disc registering a vote, and the answer that day is no.
What the first six weeks usually look like
The first six weeks have a rhythm that surprises people. Days one to three are about walking: to the bathroom, along the corridor, then around the block. Mayo Clinic and MedlinePlus both stress early walking as the single most useful activity, because it moves the spine gently, keeps fluid moving through the disc and lowers the risk of blood clots. Leg pain often improves quickly; back soreness and a tugging feeling near the incision are expected.
Week one at home is a study in small logistics. Someone else carries the groceries. You shower rather than bathe, keep the incision dry and discover that every chore involves a bend you never noticed. Pain relief, when prescribed, is typically a short course tapering over days; how it is used is entirely your prescriber’s call, but many people need less than they feared once they are moving.
Around two weeks comes the first follow-up. The wound is checked and the conversation turns to activity. Many desk workers return around now, sometimes part time, with a plan to stand and move every half hour. Driving is frequently discussed at this visit.
Weeks three to six are when the opening in the disc is scarring and when the window for re-herniation is widest, which is why the lifting ceiling stays low even though you feel better. Physical therapy often begins here, focused on walking distance, hip and hamstring mobility, and waking up the deep abdominal and gluteal muscles that stabilize the pelvis. Frustration is common: the leg feels normal, the mind wants the gym, and the calendar says not yet.
The six-week review is typically where restrictions are lifted or loosened, based on examination rather than symptoms alone. Some people are back to almost everything; others, especially in manual jobs, receive a graded plan running to 12 weeks. Both are normal.
Can you re-herniate a disc after surgery?
Yes. Because the tear in the annulus is not sealed at surgery, another piece of the nucleus can push through the same opening. Cleveland Clinic’s patient information puts the chance of a recurrent herniation at the same level at roughly 5 to 15 in every 100 people, and most recurrences that do occur happen in the first months, when the scar over the defect is immature.
Certain factors raise the odds, and it helps to separate what you can influence from what you cannot. A large defect in the annulus, a disc that was already badly worn, and surgery at a lower level such as L5-S1 are anatomical facts. Smoking, which impairs blood supply to disc and bone, carrying excess weight, and an early return to heavy or repetitive lifting are the modifiable ones. Mayo Clinic lists recurrent herniation among the recognized risks of diskectomy alongside bleeding, infection, nerve injury and leakage of spinal fluid.
What does a recurrence feel like? Typically the original leg pain returns, often suddenly after a specific movement, sometimes with the same numbness or weakness. A temporary flare of leg pain in the first weeks is common and does not always mean re-herniation; a nerve irritated for months stays touchy while it recovers. What distinguishes a true recurrence is persistence and pattern, and only your team’s examination and imaging can confirm it.
Prevention is the point of this whole article. Low lifting ceilings, the hip hinge, breaking up sitting, daily walking and stopping smoking all target the healing window. None guarantees anything, and a recurrence is never a personal failure. But these habits stack the odds in your favor during the weeks when the odds are most movable.
Exercises after lumbar discectomy: what the evidence supports
People search for exercises for L4-L5 and L5-S1 disc bulges as if a list existed for each level. It does not. The levels differ in which nerve roots they irritate, not in how the surrounding muscles are trained. What NHS and Mayo Clinic guidance supports after discectomy is a progression: walk first, stabilize second, load third.
Walking is the foundation. Start with several short walks a day and extend the distance rather than the pace. It is low load, upright and rhythmic, which discs appear to tolerate well.
From around the second to fourth week, and only once your team agrees, gentle activation work is commonly introduced. Physical therapists often use the abdominal draw-in (gently pulling the navel toward the spine while breathing normally), glute bridges (lying on your back, feet flat, lifting the hips) and the bird dog (on hands and knees, extending opposite arm and leg while keeping the trunk still). Nerve glides for the sciatic nerve, taught by a therapist, can ease residual leg tension. Hamstring stretches are usually done lying down with a strap rather than by folding forward.
What is usually held back early: sit-ups and crunches, which load the disc in flexion; toe-touch stretches; loaded twisting; and anything performed with the spine rounded under weight. Swimming is generally fine once the wound has fully healed, though some therapists limit breaststroke kick early because of the arching it demands.
A therapist does two things a video cannot. They check that you are actually hinging at the hips rather than the back, and they match the amount of exercise to your tissue rather than a generic schedule. NHS guidance emphasizes staying active over rest, and that holds after surgery: the aim is a spine that moves well inside a body strong enough that the disc is not the first structure to feel a load.
Getting back to weight training, deadlifts and the gym
For many people the real question is not the laundry basket but the barbell. Can I deadlift again? Is the gym over? The honest answer is that most people who trained before surgery train after it, and the path back is measured in months rather than weeks. Johns Hopkins patient information on lumbar discectomy notes that return to strenuous activity is directed by the surgeon and usually follows a graded rehabilitation program; many such programs place unrestricted heavy lifting and contact sports somewhere in the 3 to 6 month range.
Between clearance for daily lifting and clearance for training, physical therapy builds a bridge: loaded carries, goblet squats to a box, hip hinges with a light kettlebell, then progressively heavier versions. Technique becomes non-negotiable. The neutral spine you learned for picking up socks is the same one the deadlift demands; the rounded-back pull many people got away with before is the movement that ended in an operating room.
Exercises to reintroduce cautiously, if at all early: seated rows and leg presses that fold the hips deeply, good mornings, loaded sit-ups and anything where fatigue makes the lower back round. Overhead work compresses the spine less than people assume when the trunk is braced, but it is often delayed until the core is reliable.
Two practical rules travel well. First, change one variable at a time: weight, range or volume, never all three in a session. Second, treat leg symptoms as a hard stop. Muscle soreness after training is expected; sciatic pain, tingling or weakness during or after a lift is a reason to stop and report it.
Powerlifters and manual athletes should expect a slower, more supervised return, and some choose to keep top-end loads below their old maximum permanently. That is a decision made with the surgeon and therapist, not a rule.
Work, driving and daily chores: the middle ground nobody warns you about
The discharge sheet says ‘no heavy lifting’. Real life says the recycling needs to go out, the dog pulls on the leash and printer paper arrives in a 25-pound box. Most of recovery happens in this middle ground, where nothing is obviously forbidden and everything is a judgment call.
Work first. MedlinePlus gives a return-to-work window of around 2 to 6 weeks for most people, longer for heavy jobs. Desk roles are mainly a sitting problem, so ask for an adjustable chair, a standing option if available and permission to move every 30 minutes without explanation. Jobs involving lifting, long periods of driving or repeated bending often need a written graded-return plan from the surgeon, and many employers can offer lighter duties temporarily. Whole-body vibration, such as driving over rough ground or operating machinery, is a recognized load on discs and is often restricted for longer.
Chores can be triaged. Vacuuming and mopping are deceptive because the push-pull motion invites twisting and a forward lean; keep the handle long and step with the movement rather than reaching. Laundry is a floor-to-drum bend repeated dozens of times; raise the basket onto a chair. Dishwashers demand exactly the bent-and-twisted posture to avoid, so load from a squat or kneeling position, or hand the job over for a few weeks. Gardening is best delayed until you are cleared to kneel and lift soil.
Children and pets are the emotional hard cases. A toddler weighs more than most early limits allow, and toddlers do not stay still. Sit down and let them climb into your lap rather than lifting them; use a stroller with a high seat; for a dog that lunges, use a harness and recruit a second walker. Carrying nothing can feel like failing your family. For a few weeks, it is exactly the opposite.
What people often get wrong about protecting a disc repair
Myth one: rest protects the disc. NHS guidance on slipped disc is explicit that staying active speeds recovery and prolonged bed rest slows it, and the same applies after surgery. Lying down does lower disc pressure, but muscles weaken, stiffness sets in and clot risk rises. Walk.
Myth two: the surgery fixed the disc. It decompressed the nerve. The disc is thinner and carries an unsealed tear that heals by scarring over weeks to months. That is why the restrictions exist, and why they have an end date.
Myth three: a brace holds everything together. Lumbar braces can remind you not to bend and may feel comforting, but evidence that they improve outcomes after discectomy is limited, and prolonged use can let trunk muscles switch off. If your team recommends one, ask for how long and why.
Myth four: any pain means damage. The nerve was compressed and inflamed before surgery, and irritated nerves stay sensitive for weeks. Aches, twinges and brief zings of leg pain are common during healing. Persistent, worsening or new symptoms are different, and the red-flag section below covers them.
Myth five: I must never bend forward again. Permanent avoidance of flexion produces a stiff, fearful back. Rehabilitation deliberately reintroduces controlled bending once the tear has scarred. The lasting rule concerns loaded, repetitive, end-range rounding, not tying shoelaces for life.
Myth six: recovery from L3-L4 surgery differs from L5-S1. The level changes which nerve was affected, so numbness may sit in the thigh rather than the calf, but the surgical steps and the disc’s healing timeline are essentially the same. Mayo Clinic’s recovery guidance does not distinguish by level.
Myth seven: if surgery worked, leg pain vanishes instantly. Often it improves fast, but a nerve compressed for months can take months to recover, and some residual numbness may be permanent. Improvement is measured over a season, not a week.
Questions to ask your care team
Bring these to your pre-operative visit or first follow-up, and write the answers down; two weeks after surgery, memory is not at its best.
About my operation: How large was the opening in the disc wall, and does that change my restrictions? Was bone removed, and was anything fused? Did anything unexpected happen that affects my recovery?
About lifting and bending: What is my lifting limit now, and at which visit will you review it? Is there a difference between a single lift and repeated lifting for my job? When can I bend to the floor with a hip hinge, and when can I bend with a rounded back at all?
About sitting and driving: How long should I sit at one time in the first weeks? When can I drive, and does that depend on my pain medicines? Are long car or plane journeys a concern, and for how long?
About exercise and work: When does physical therapy start, and will you refer me or should I arrange it? Which exercises should I avoid until you say otherwise? What should my employer be told about a graded return, and can you put it in writing?
About warning signs: Which symptoms should make me call the office the same day, and which mean an emergency department? What does a re-herniation typically feel like, and how would you assess it?
About the long term: Is there anything about my disc or spine that means I should adjust how I train or work permanently? When can I consider myself fully unrestricted?
You are not being difficult by asking. Surgeons and therapists generally prefer a patient who knows the plan to one who guesses, and every question above has an answer specific to you that no article can supply.
When to call your doctor
Most of recovery is ordinary: soreness, fatigue, a wound that itches. A short list of signs is not ordinary, and MedlinePlus and Mayo Clinic agree on the ones that need attention.
Go to an emergency department or call emergency services if you develop new difficulty controlling your bladder or bowels, numbness in the area you sit on (the saddle region), or rapidly progressing weakness in one or both legs. These can indicate pressure on the bundle of nerves at the base of the spine, called cauda equina syndrome, which is rare but time-critical.
Call your surgical team the same day for any of the following:
- Fever with chills, or redness, warmth, swelling or discharge from the incision, or a wound that opens.
- Clear fluid leaking from the wound, which can signal a spinal fluid leak, sometimes with a headache that worsens when upright.
- A sudden return of the original leg pain after a specific movement, especially if it persists beyond a day or brings new numbness.
- New weakness in the foot or leg, such as a foot that slaps or catches when you walk.
- Pain that is steadily worsening rather than easing after the first week.
- Calf pain, swelling or warmth in one leg, or chest pain and breathlessness, which can indicate a blood clot and need urgent assessment.
For milder but worrying symptoms, the office nurse line is the right first call. A flare after doing a little too much is common and often settles within a couple of days with walking and the plan you were given. What the team wants to hear about is anything new, anything progressing, or anything that does not match what they told you to expect. When in doubt, call; that is what the follow-up number is for.
Frequently asked questions
How long does it take to recover from L3-L4 herniated disc surgery?
For a single-level discectomy, most people return to light work in about 2 to 6 weeks and to heavier work in 6 to 8 weeks or more, according to MedlinePlus, and the level does not change that. An L3-L4 herniation affects thigh and knee sensation rather than the calf, but the surgical steps and disc healing are the same. Full nerve recovery can take months.
Is herniated disc surgery worth it?
It depends on your symptoms and what has already been tried. NHS guidance reserves surgery for people whose leg pain, numbness or weakness persists despite several weeks of non-surgical care, or who have progressive weakness or bladder and bowel symptoms. Mainstream evidence suggests surgery tends to relieve leg pain faster than continued conservative care, while long-term results often converge. The decision sits with you and your treating team.
Can you re-herniate a disc after surgery?
Yes. The tear in the disc wall is not stitched shut, so another fragment can push through, most often in the first months. Cleveland Clinic reports recurrence in roughly 5 to 15 of every 100 people. Larger tears, smoking, excess weight and early heavy lifting raise the risk. A sudden return of the original leg pain after a movement should be reported to your team.
What are good exercises for L4-L5 and L5-S1 disc bulges after surgery?
The same ones, regardless of level: walking first, then therapist-guided activation such as abdominal draw-ins, glute bridges and bird dogs, then gradual loading. Nerve glides and lying hamstring stretches often help residual leg tightness. Sit-ups, toe touches and loaded twisting are usually held back early. Start any program only after your surgeon clears it, ideally with a physical therapist checking your technique.
How long should I avoid bending after microdiscectomy?
Rounded-back bending to the floor is typically avoided for the first 4 to 6 weeks, with a hip hinge or golfer’s lift used instead, according to patient guidance from Mayo Clinic and MedlinePlus. Controlled forward bending is then reintroduced gradually in rehabilitation. The permanent habit to keep is avoiding loaded, repetitive, end-range rounding, especially combined with twisting.
How long can I sit after discectomy?
In the first few weeks, most teams suggest sitting for about 20 to 30 minutes at a time, then standing and walking briefly before sitting again. Choose a firm chair with back support over a low sofa, and keep hips level with or slightly above the knees. Sitting tolerance usually lengthens steadily through weeks 2 to 6 as the surgical site settles.
When can I lift my child after herniated disc surgery?
Usually not until the surgeon raises your lifting limit above the child’s weight, often at the six-week review for a toddler. Early limits of roughly 5 to 10 pounds are below most children’s weight. In the meantime, sit down and let the child climb onto your lap, use a high-seated stroller, and avoid lifting from the floor or into a car seat.
When can I deadlift or go back to the gym?
Light gym work often resumes around 6 to 12 weeks under physical therapy guidance, while unrestricted heavy lifting is commonly placed at 3 to 6 months in graded programs, as Johns Hopkins patient information describes. Progress one variable at a time and treat any leg pain, tingling or weakness as a signal to stop. Your surgeon and therapist set the pace.
Should I wear a back brace after discectomy?
Only if your surgical team recommends one. Braces can act as a reminder not to bend and may feel comforting, but evidence that they improve outcomes after lumbar discectomy is limited, and long-term use can let trunk muscles weaken. If one is suggested, ask how long to wear it and when to wean off so your own muscles take over.
Which exercises after lumbar discectomy should I avoid?
In the early weeks, avoid sit-ups and crunches, toe-touch stretches, loaded twisting, deep seated rows or leg presses that fold the hips, and any lift where fatigue rounds the lower back. High-impact running and contact sports are usually delayed for months. Walking, gentle core activation and therapist-taught mobility work are the typical substitutes until your team clears more.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Nucleoplasty Recovery: Why Back Pain Can Rise Briefly and When Bending and Lifting Resume
Nucleoplasty recovery usually involves going home the same day, a brief rise in back pain over the first days as the needle path and…

When Spinal Fusion Does Not Fuse: Pseudarthrosis Explained and What Revision Involves
A failed spinal fusion, called pseudarthrosis or nonunion, means the bone graft placed between vertebrae did not grow into one solid piece within the…

Who Is a Candidate for Artificial Disc Replacement? Single-Level Disease and Healthy Facets
The typical artificial disc replacement candidate has neck or low back pain traced to a single worn disc, with facet joints and surrounding bone…

Schroth Method for Adults With Scoliosis: How Goals Differ From Treating a Growing Teen
The Schroth method for adults uses the same three-dimensional posture, breathing and strengthening principles taught to teenagers, but the goal shifts. In a growing…

Preparing for ACDF Surgery: Medicines to List, Tests to Complete and Soft Foods to Stock
Preparing for ACDF surgery usually means three tasks: giving your surgical team a complete list of every prescription, over-the-counter medicine and supplement you take;…

What an Artificial Disc Actually Does: How the Mobile Implant Moves With Your Spine
An artificial disc is a small mobile implant placed between two vertebrae after a worn or herniated disc is removed. Two metal endplates anchor…