

Living With Bronchiectasis: Exercise, Travel and Fitting Airway Clearance Into Your Day

Key Takeaways
- Bronchiectasis is permanent widening of the airways that stalls the natural mucus escalator, so daily airway clearance is the core treatment rather than an add-on.
- The NHS describes clearance sessions of around 20 to 30 minutes, ideally twice daily, done before inhaled medicines so the medicine reaches the airway wall.
- A flare-up is defined by a worsening of at least three of six features lasting 48 hours or more, not by a single change in sputum color.
- Exercise itself moves mucus, and there is no evidence that appropriate activity damages airways in bronchiectasis; deconditioning from inactivity is the better-documented harm.
- Aircraft cabins are pressurized to the equivalent of 6,000 to 8,000 feet, which is why some people need a fitness-to-fly assessment before booking.
- Journeys longer than four hours raise the risk of leg clots, so moving, ankle exercises and hydration matter on every long flight.
Living with bronchiectasis usually centers on a daily airway clearance routine, regular physical activity, and prompt attention to flare-ups. Most people can exercise and travel, including by air, with planning: keeping clearance sessions consistent, carrying medicines and equipment in hand luggage, discussing oxygen needs before flying, and agreeing a flare-up plan with their respiratory team. Any change to treatment should be decided with that team.
The alarm goes at 5:40. Not for the flight, which is at nine, but for the twenty minutes of breathing exercises that have to happen first, in a hotel bathroom, with a towel folded under the nebulizer so the buzz does not wake the person in the next room. Then a huff, a tissue, a check of the color, and only then coffee. That is a fairly ordinary morning for someone living with bronchiectasis who has decided that a chronic lung condition is not going to decide where they go.
People newly diagnosed tend to ask the same three things in the same order: Can I still exercise? Can I still travel? And how on earth do I fit this clearance routine into a life that already has a job, a family and a commute in it?
The honest answer is that most people can do all three, but the details matter, and the details are exactly what a rushed clinic appointment rarely has time for. This is the longer conversation.
What is actually happening in your airways when you are living with bronchiectasis?
Bronchiectasis means that some of the breathing tubes in the lungs have become permanently widened and scarred, so their walls have lost the springiness that normally helps move mucus upward. Healthy airways are lined with tiny hairs called cilia that sweep mucus toward the throat in a slow, steady escalator. In a widened, floppy airway that escalator stalls. Mucus, which is called sputum once you cough it up, pools in the sagging sections like water in a low stretch of gutter.
Pooled mucus is warm, wet and nutritious, so bacteria settle in it. Some of them stay for months or years without causing a full infection, a state doctors call colonization. The immune system responds with inflammation, and inflammation damages the airway wall a little more, which pools a little more mucus, which invites a little more infection. Respiratory specialists describe this loop as a vicious cycle, and almost everything in day-to-day management is aimed at interrupting one part of it.
The condition can follow a severe childhood pneumonia or whooping cough, sit alongside an immune deficiency or a condition such as cystic fibrosis, or arrive with no identifiable cause at all, which is the case for a large share of adults, according to the NIH StatPearls review. It is diagnosed on a CT scan, where the widened airways are visible in cross-section.
Here is the point that matters most for the rest of this article. Because the airways cannot clear themselves properly, you do the clearing for them. Airway clearance, exercise and prompt treatment of flare-ups are not extras added on top of the real treatment. In bronchiectasis, they are the real treatment, and the pattern of most people’s symptoms tracks how consistently they are done.
How do bronchiectasis airway clearance techniques work?
Every clearance technique relies on the same piece of physics. If you can get a column of air behind a plug of mucus and then push that air out at the right speed, the moving air drags the mucus along with it, the way a fast river carries silt that a slow one leaves on the bottom. The skill lies in loosening mucus in the small airways first, moving it up to the larger ones, and only then coughing, so the cough has something worth catching.

The Active Cycle of Breathing Techniques, usually shortened to ACBT, is the method most often taught first in the UK, according to the NHS. It alternates relaxed breathing, a few deep breaths that hold for a moment at the top, and a forced exhalation through an open mouth called a huff, which sounds like fogging a mirror. The huff moves mucus without the airway squeeze of a hard cough.
Autogenic drainage is a quieter cousin that uses breathing at different lung volumes to shift mucus in stages; it takes longer to learn but suits people who find coughing exhausting. Positive expiratory pressure devices, small handheld tubes you breathe out against, keep the airways splinted open so air can slip behind the mucus, and the oscillating versions add a flutter that vibrates it loose. Postural drainage uses gravity, lying with a particular part of the chest uppermost so mucus runs downhill toward the throat.
A nebulizer, which turns liquid into a fine mist, is often used beforehand to deliver a salt solution that draws water into the mucus and thins it. The NHS is clear that techniques should be taught by a respiratory physiotherapist rather than copied from a video, because the timing of the huff and the position of the body are what separate a productive session from twenty minutes of tiring, unproductive coughing.
Building a bronchiectasis daily routine that sticks
The routine that works is the one you actually do on a Tuesday when you feel fine. That sounds glib, but it is the single most consistent observation from respiratory physiotherapists, and it is why they spend so long on scheduling rather than on technique alone.
Morning is usually the highest-yield session, because mucus has pooled overnight. The NHS describes sessions of roughly 20 to 30 minutes, ideally twice a day, with the frequency adjusted upward during a flare-up and agreed with your physiotherapist when you are stable. Doing it before breakfast avoids the nausea that can come from huffing on a full stomach, and it means the airways are clearer before any inhaled medicines, which is the order most teams recommend: clear the mucus first so the medicine reaches the airway wall rather than sitting on a layer of sputum.
Habit research is unglamorous but useful here. Sessions survive when they are attached to something that already happens every day: the kettle boiling, a particular podcast, the ten minutes before a child’s school run. People who treat clearance as a floating task to be fitted in later tend to find that later never arrives.
Two practical refinements help most. First, keep a simple record of what you cough up on a normal day, its rough volume and color, because that baseline is what makes an early flare-up recognizable. Second, have a shortened travel-day version of the routine agreed in advance, so a delayed train does not become an excuse to skip the whole thing. A ten-minute session done is worth more than a thirty-minute one postponed.
Weekends and holidays are where routines fray. Planning the first session of a day off exactly as you would on a workday, before the day’s pleasant distractions begin, is the least exciting and most effective advice in this article.
Which airway clearance technique suits which situation?
No single technique has been shown to be clearly superior for everyone with bronchiectasis; the evidence, summarized in the NIH StatPearls review, supports doing clearance regularly far more strongly than it supports any one method over another. What differs is practicality: what you can do on a train, what you can do when exhausted, what needs a piece of kit that must be cleaned. This table sets the main options side by side.
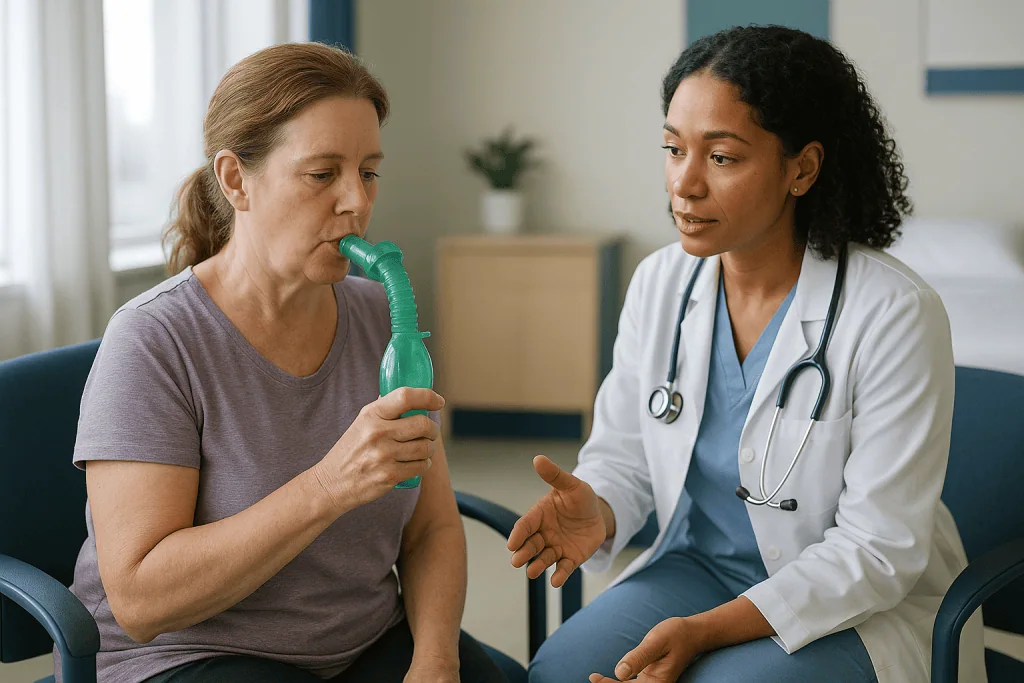
| Technique | What it involves | Equipment | Often suits |
|---|---|---|---|
| Active Cycle of Breathing (ACBT) | Cycles of relaxed breathing, deep breaths and huffs | None | Most people as a first method; easy to do anywhere, including travel |
| Autogenic drainage | Controlled breathing at low, mid and high lung volumes | None | People who tire from coughing; needs more teaching time |
| Positive expiratory pressure device | Breathing out against resistance through a handheld tube | Small device, needs cleaning | Those who want structure and feedback; portable |
| Oscillating PEP | Resistance plus a vibration that shakes mucus loose | Small device, needs cleaning | Thick, sticky sputum; often combined with huffing |
| Postural drainage | Lying in positions that let gravity drain specific lung areas | Pillows or wedge | Known pooling in one region; less practical when travelling |
| Exercise as clearance aid | Brisk activity followed by huffs | Depends on activity | Stable days; complements rather than replaces a session |
Two cautions belong alongside the table. Positions that tip the head below the chest are usually avoided by people with acid reflux or certain heart conditions, which is one reason a physiotherapist rather than a leaflet should choose the method. And any device that goes in your mouth every day becomes a breeding ground unless it is washed and dried after each use, a point the following sections return to.
Is exercising with bronchiectasis safe, and does it help clear mucus?
For most people with stable bronchiectasis, exercise is not only safe but is itself a form of airway clearance. Faster, deeper breathing moves more air past pooled mucus, and the jostling of a brisk walk or a swim shakes it loose. Physiotherapists often suggest a few huffs after a workout for exactly this reason. The cough that arrives ten minutes into a run is not a sign of harm; it is the lungs doing what the session is meant to make them do.
The general adult activity target from the American Heart Association, around 150 minutes of moderate activity a week plus muscle-strengthening work on two days, is a reasonable long-term aim for many people with bronchiectasis too, reached gradually rather than in the first fortnight. Moderate means you can talk but not sing. If you cannot finish a sentence, ease off.
Breathlessness is the barrier people fear most, and it deserves a plain explanation. Feeling short of breath during effort is expected with any lung condition and is not the same as being short of oxygen. What matters is recovery: breathing that settles within a few minutes of stopping is the normal pattern. Breathing that does not settle, or a new tightness in the chest, is a reason to stop and speak to your team rather than push through.
Pulmonary rehabilitation, a supervised program of exercise and education run by respiratory physiotherapists, is offered by many services to people whose breathlessness limits daily activity. The NHS describes programs running over several weeks with two or more sessions each week. People often report that the most valuable part is not the treadmill but learning how hard they can safely push, from someone watching their oxygen readings while they do it.
Timing helps. Exercising after a clearance session, rather than before it, means you are moving air through airways that are already partly clear.
Who is usually encouraged to be active and travel, and who is usually asked to wait?
Most people with bronchiectasis who are between flare-ups, have a clearance routine they can do anywhere, and know their own baseline are usually encouraged to exercise and travel much as anyone else would. The condition does not, by itself, rule out long-haul flights, hill walking or a gym membership.
Waiting is usually advised in a handful of situations, and they are worth knowing in advance so that a trip is postponed rather than cut short.
- In the middle of a flare-up, or in the first days of treatment for one, vigorous exercise and travel are generally paused. Rest and extra clearance sessions take priority, and being far from your own team when you are unwell is rarely wise.
- Coughing up blood, called hemoptysis, beyond the faint streaking some people see routinely, is a reason to stop exercise and seek advice before any travel. Air travel is normally deferred until the cause has been assessed.
- A recent pneumothorax, a collapsed lung caused by air leaking into the space around it, is a standard reason to avoid flying until a doctor confirms it has fully resolved, because cabin pressure changes can enlarge trapped air.
- Low oxygen levels at rest, or a recent hospital admission, usually prompt a fitness-to-fly assessment and sometimes a plan for in-flight oxygen before a ticket is booked.
- Coexisting heart disease or another condition that is not yet well controlled may need its own clearance from the relevant specialist.
None of these is a permanent no. They are questions to settle with the treating team, who will weigh how you are right now rather than the label on the scan. Booking flexible tickets is a sensible hedge for anyone whose condition fluctuates.
Flying with bronchiectasis: cabin air, oxygen and clots
Aircraft cabins are pressurized, but not to sea level. The CDC’s travel health guidance notes that cabin pressure is typically equivalent to an altitude of 6,000 to 8,000 feet, roughly the height of a substantial mountain. Everyone’s blood oxygen falls a little at that pressure. Healthy lungs compensate without anyone noticing; lungs with damaged airways may not compensate as fully.
This is why respiratory teams sometimes arrange a fitness-to-fly assessment, which may include a pulse oximeter reading, a small clip on the finger that estimates blood oxygen, and occasionally a test that simulates cabin conditions. The outcome is not a verdict on whether you can fly but a decision about whether you need supplemental oxygen while airborne. Airlines have their own procedures for portable oxygen concentrators and battery requirements, and these need arranging well before departure rather than at the gate.
Cabin air is also dry, which thickens mucus. Drinking water steadily, doing a full clearance session before leaving for the airport and another after landing, and carrying tissues and a small sealable bag for used ones make a long flight far more comfortable. Most airlines allow medical devices such as nebulizers in addition to normal hand luggage, but policies vary and a letter from your team describing the equipment saves arguments at security.
The other in-flight risk has nothing to do with lungs. The CDC identifies travel lasting more than four hours as a risk factor for blood clots in the deep veins of the leg, known as deep vein thrombosis. Sitting still is the problem, so the standard advice applies: walk the aisle when you can, flex and circle the ankles while seated, avoid crossing the legs for long stretches, and keep hydrated. Anyone who has had a previous clot, or who takes hormone therapy, should raise this with their doctor before a long journey.
Travel planning when living with bronchiectasis: a practical checklist
Good trips are made a month before departure. The people who travel most confidently with bronchiectasis tend to have worked through a short, boring list with their team, and then forgotten about it and enjoyed themselves.
- Carry all medicines and clearance devices in hand luggage, never in the hold, with a copy of your prescription list and a brief letter from your team describing your condition and equipment.
- Ask your prescriber how a flare-up should be handled while away. Some teams arrange a standby plan for people who travel; the decision about whether that suits you, and what it contains, is theirs.
- Check the destination’s air quality, altitude and humidity. High altitude compounds the oxygen drop of flying; heavy urban pollution and wildfire smoke irritate damaged airways.
- Confirm that your travel insurance covers a pre-existing lung condition and that you have disclosed it fully; a claim can fail on an undisclosed diagnosis.
- Keep vaccinations current. The NHS recommends annual flu vaccination and pneumococcal vaccination for people with long-term lung conditions, and travel-specific vaccines should be discussed early because some need weeks to take effect.
- Plan how you will clean your nebulizer or device on the road. Boiled or bottled water and a clean towel to air-dry on are the minimum; tap water of uncertain quality is a poor choice for rinsing something you inhale through.
- Build rest into the itinerary. Two active days followed by a slow one is more sustainable than trying to see everything in the first forty-eight hours.
- If crossing time zones and taking medicines at set times, ask your team how to shift the schedule rather than guessing.
Knowing where the nearest emergency department is at your destination is not pessimism. It is the same preparation a person with diabetes or a heart condition would make, and it makes the rest of the trip lighter.
Medicines, nebulizer hygiene and vaccines: what each one does
Medicines in bronchiectasis are chosen to break a specific link in the infection and inflammation cycle described earlier. Which ones you use, if any, is a decision for the prescribing clinician; what follows explains mechanisms so the conversation makes sense.
Inhaled salt solutions, delivered by nebulizer, draw water into thick mucus by osmosis and make clearance sessions more productive. Some people feel the difference within a session; others find a saltier solution irritating at first and need it introduced under supervision, which is why the first use is often done in clinic.
For people who have frequent flare-ups despite good clearance, some teams consider a long-term antibiotic of the macrolide class taken at a low level for months. It appears to work partly as an anti-inflammatory rather than simply by killing bacteria. Because this class can affect hearing and heart rhythm in some people, monitoring is part of the arrangement, and it is not offered to everyone.
When a particular bacterium called Pseudomonas has colonized the airways, inhaled antibiotics delivered straight into the lungs are sometimes used to reduce the bacterial load. Inhalers that open the airways, familiar from asthma, are not routine in bronchiectasis and are usually reserved for people who also have asthma or COPD, according to the NIH StatPearls review.
Whatever is prescribed, the device that delivers it needs attention. A nebulizer chamber or PEP device that is not washed and fully dried after every use grows the very bacteria you are trying to keep out. Manufacturers give cleaning instructions; the common failure is drying, not washing, because damp parts left in a bag stay damp.
Vaccination is the least dramatic and most cost-free protection available. The NHS lists flu and pneumococcal vaccines for people with long-term lung conditions, and staying current with COVID-19 vaccination is generally advised for the same reason: each infection you avoid is a flare-up you avoid.
What a flare-up is, and what the following days and weeks usually look like
A flare-up, which doctors call an exacerbation, is not simply a bad day. The consensus definition used in clinical research and summarized in the NIH StatPearls review requires a worsening lasting 48 hours or more in at least three of six features: cough, sputum volume or thickness, sputum color turning more yellow or green, breathlessness, tiredness, and blood in the sputum. That definition is useful to patients too, because it separates a rough morning after a poor night’s sleep from a genuine change that needs action.
The first practical step is usually a sputum sample, sent before any antibiotic is started, so the laboratory can identify the bacteria and check which antibiotics they respond to. Then treatment begins, typically with an antibiotic chosen on the basis of previous samples. The NHS notes that antibiotic courses for bronchiectasis flare-ups are generally longer than those for a simple chest infection, and finishing the course matters even when symptoms improve early. The specifics belong to the prescriber.
In the first few days, most people are asked to increase clearance sessions rather than reduce them, even though it is the last thing a tired person wants to do. More mucus is being produced, and getting it out is what shortens the episode. Rest, fluids and cancelled plans are the appropriate response, not a failure of willpower.
Energy often recovers more slowly than the cough. People commonly describe feeling back to baseline some time after the sputum has returned to its usual color, and that lag is normal rather than a sign the treatment has failed. A review with your team after the episode is worthwhile, because the number of flare-ups you have in a year is one of the main things that shapes decisions about long-term preventive treatment.
Keeping a note of each episode, its trigger if you can identify one, and how long it lasted turns a frustrating illness into data your team can use.
Fatigue, mood and the parts of living with bronchiectasis that never show on a scan
The CT scan shows widened airways. It does not show the exhaustion of a body that has spent the night coughing, the embarrassment of clearing your chest in an open-plan office, or the low mood that follows a third flare-up in a winter. These are not side issues. Long-term lung conditions carry a well-recognized burden of anxiety and depression, and the NHS lists fatigue and low mood among the common experiences of people with bronchiectasis.
Fatigue responds best to pacing rather than pushing. Spreading demanding tasks across the week, protecting sleep with an evening clearance session so that less coughing happens at 3 a.m., and accepting that a flare-up week is a low-output week all help. So does exercise, counterintuitively; the deconditioning that comes from resting too much makes everyday effort feel harder, which is part of why pulmonary rehabilitation improves energy as well as breathlessness.
The cough itself has social costs that deserve to be named. A wet, productive cough in a meeting draws looks, particularly in the years since a pandemic. Many people find that a short, matter-of-fact explanation to colleagues, along the lines of a chronic lung condition that produces mucus and is not infectious, removes most of the awkwardness. Some carry a card saying the same for strangers.
A less discussed problem is urine leakage during hard coughing, which affects a meaningful number of people with chronic cough, women especially. Pelvic floor exercises taught by a physiotherapist help, and it is worth raising rather than enduring in silence.
Talking to others with the condition, through a patient organization or a group run by a respiratory service, is consistently described as one of the most useful things people do. Hearing that someone else also does their huffs in a supermarket car park before a long shift is oddly steadying.
What people often get wrong
Some misunderstandings about bronchiectasis are so common that correcting them changes how people manage the condition from that day on.
Coughing up mucus is the problem. Mucus sitting in the airways is the problem. Coughing it up is the solution. Cough suppressants are generally avoided in bronchiectasis for exactly this reason, and a productive morning session is a good sign, not a bad one.
Any change in sputum color means antibiotics. Color alone is not the trigger. The consensus definition of a flare-up looks for a sustained change across several features. Treating every off-color morning with antibiotics encourages resistant bacteria, which is why teams ask for a sample and a pattern rather than a single observation.
Exercise wears out damaged lungs. There is no evidence that appropriate exercise damages the airways in bronchiectasis. The reverse pattern, where inactivity leads to deconditioning and worse breathlessness, is well documented across chronic lung disease.
Bronchiectasis is just another word for COPD, and it comes from smoking. They are different conditions that can coexist. Bronchiectasis is defined by permanently widened airways, and most cases are not caused by smoking; the NIH StatPearls review lists past infections, immune problems and inherited conditions among the causes, with a large proportion having no identified cause.
You can skip clearance when you feel well. The stable weeks are when routine clearance does its preventive work. Skipping it when well is how the next flare-up is set up.
It is contagious. It is not. The bacteria in your sputum are ordinary environmental organisms that do not cause bronchiectasis in people with healthy airways.
An inhaler fixes it. Airway-opening inhalers are not routine treatment for bronchiectasis unless asthma or COPD is also present. Clearance, infection control and exercise carry more of the weight than most people expect.
Questions to ask your care team
Clinic appointments are short and the questions that matter most are often the ones that feel too small to raise. Taking a written list changes the balance. These are the ones respiratory physiotherapists and nurses say they wish more people asked.
- Which airway clearance technique do you recommend for me, how often should I do it when I am well, and how should I change it during a flare-up?
- Can you watch me do a full session so you can correct my technique?
- What is my usual sputum like, and what change would you want to know about?
- Have any bacteria been found in my sputum samples, and does that affect how a flare-up should be treated?
- How should a flare-up be handled if I am away from home, and is a standby plan appropriate for me?
- Is pulmonary rehabilitation available to me, and would I benefit from it?
- How hard is it safe for me to push during exercise, and are there any activities you would ask me to avoid?
- Do I need a fitness-to-fly assessment before air travel, and would in-flight oxygen be advised?
- Am I a candidate for any long-term preventive treatment, and what monitoring would that involve?
- How should I clean and replace my nebulizer or clearance device?
- Which vaccinations should I keep current?
- Is there anything about my other health conditions or medicines that changes any of this advice?
- Who do I contact, and how quickly, if my symptoms change?
One further question is worth asking even though it feels awkward: how well controlled do you think my bronchiectasis is right now, and what would better control look like? The answer gives you a target rather than a vague sense of managing.
When to call your doctor
Most changes in bronchiectasis are gradual and can be handled with a call to your respiratory team during working hours. A few are not, and knowing the difference in advance is part of living well with the condition.
Contact your team promptly, usually the same day or next working day, if you notice a sustained worsening of your cough, sputum volume, sputum color, breathlessness or tiredness lasting more than a couple of days, particularly if three or more of these change together, since that pattern is how a flare-up is defined. Call if you have started treatment for a flare-up and are not improving after several days, or are getting worse. Call if you see more than the faint streaking of blood you may already be used to, if you develop fever, chills or night sweats, or if your oxygen readings, where you monitor them, fall below the level your team has told you is acceptable for you.
Seek emergency care, by calling emergency services or going to an emergency department, if you cough up a significant amount of blood rather than streaks, become severely breathless at rest or cannot speak in full sentences, develop chest pain, notice blue or gray lips or fingertips, feel confused or unusually drowsy, or have a sudden sharp chest pain with breathlessness, which can signal a collapsed lung. After a long flight or journey, a swollen, painful calf, or sudden breathlessness with chest pain, needs urgent assessment for a blood clot.
None of this list is meant to be memorized under stress. Agreeing it with your own team, writing down who to call and when, and keeping that note with your medicines is the practical version. The decisions about what to do next always sit with the clinicians who know your history; your job is to make the call early enough that they have room to make them.
Frequently asked questions
How often should I do airway clearance if I feel well?
Most people are advised to keep clearing daily even when well, because the stable weeks are when routine clearance prevents the next flare-up. The NHS describes sessions of roughly 20 to 30 minutes, ideally twice a day, with your physiotherapist adjusting the frequency to your own sputum load. Skipping sessions on good days is one of the most common reasons symptoms creep back.
Which bronchiectasis airway clearance techniques work best?
No single technique has been shown to be clearly better than the others for everyone; the evidence supports doing clearance consistently more than it supports any one method. The Active Cycle of Breathing Techniques is often taught first because it needs no equipment. Autogenic drainage, positive expiratory pressure devices and postural drainage each suit particular people, and a respiratory physiotherapist should choose and teach the method.
Is exercising with bronchiectasis safe if I get breathless?
For most people with stable bronchiectasis, yes. Feeling breathless during effort is expected with any lung condition and is not the same as lacking oxygen; what matters is that breathing settles within a few minutes of stopping. Build up gradually toward general activity guidance, exercise after a clearance session, and ask your team about pulmonary rehabilitation if breathlessness limits daily life.
Can I fly with bronchiectasis?
Most people with stable bronchiectasis can fly. Because cabin pressure is equivalent to 6,000 to 8,000 feet, blood oxygen falls slightly, so some people are offered a fitness-to-fly assessment to decide whether in-flight oxygen is needed. Flying is usually deferred during a flare-up, after coughing up blood, or after a recent collapsed lung until a doctor confirms it is safe.
What should a bronchiectasis daily routine include?
A typical routine has a morning clearance session before breakfast and inhaled medicines, an evening session to reduce overnight coughing, some physical activity, and cleaning and drying of any nebulizer or clearance device after each use. Keeping a brief note of your usual sputum makes early changes easier to spot. The exact structure should be agreed with your physiotherapist and adjusted during flare-ups.
Can I swim or use a hot tub with bronchiectasis?
Swimming is often well tolerated and the breathing rhythm can help move mucus, so many people find it useful. Hot tubs and poorly maintained spa pools are a different matter, because warm standing water can harbor bacteria that irritate damaged airways. Ask your team about your own situation, and choose well-chlorinated, well-maintained pools where possible.
Is bronchiectasis contagious?
No. Bronchiectasis is structural damage to the airways, not an infection you can pass on. The bacteria found in sputum are usually ordinary environmental organisms that do not cause bronchiectasis in people with healthy airways. Ordinary cough etiquette and hand hygiene are sensible for everyone, but you do not need to isolate from family or colleagues because of the condition itself.
Does climate or altitude make bronchiectasis worse?
Very dry air, heavy pollution and wildfire smoke can thicken mucus and irritate the airways, so destination air quality is worth checking. High altitude compounds the oxygen drop already experienced when flying, so trips to mountainous regions should be discussed with your team beforehand. Humidity itself is not harmful, but damp, moldy accommodation can trigger symptoms in some people.
What does a change in sputum color mean?
Sputum turning more yellow or green can signal increased infection, but on its own it is not the definition of a flare-up. Clinicians look for a sustained change over 48 hours or more in at least three features, including cough, sputum volume, color, breathlessness, tiredness and blood. A single off-color morning is usually a reason to watch closely rather than a reason to start antibiotics.
Will bronchiectasis get worse over time?
Not necessarily. Bronchiectasis does not follow one path; some people remain stable for many years while others have frequent flare-ups that gradually add damage. Consistent airway clearance, prompt treatment of flare-ups, exercise and vaccination are the factors most within your control, and the number of flare-ups you have is one of the main things your team uses to guide long-term preventive treatment.
References
- NHS: Bronchiectasis: Treatment
- MedlinePlus Medical Encyclopedia: Bronchiectasis
- Cleveland Clinic: Bronchiectasis
- NIH StatPearls: Bronchiectasis
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Pulmonary Edema Is Treated in the Emergency Room: Oxygen, Diuretics and Monitoring
Pulmonary edema emergency treatment focuses on getting oxygen into the blood and fluid out of the lungs quickly. Emergency teams typically sit the person…

Questions to Ask at Your Asthma Review: Triggers, Inhaler Technique and Follow-Up
At an asthma review, the most useful questions to ask cover three areas: which triggers are driving your symptoms and how to reduce exposure,…

Can You Fly With Emphysema? Altitude, In-Flight Oxygen and Planning Long Trips
Many people with emphysema can fly, but it depends on how much oxygen your blood carries at rest and how stable your lungs have…

Which Tests Diagnose Asbestosis? Chest CT, Spirometry and the Role of Your Exposure History
Asbestosis is diagnosed by combining three things: a documented history of significant asbestos exposure, usually decades earlier; imaging that shows lung scarring, with high-resolution…

Flying After a Pneumothorax: Why Doctors Ask You to Wait and How Clearance Works
Flying after a pneumothorax is usually delayed until a follow-up chest X-ray confirms the lung has fully re-expanded, then for a further waiting period…

When Does a Chronic Cough Need a Pulmonologist? How Lung Disease Evaluation Is Organized
A cough that has lasted eight weeks or more in an adult, or that comes with breathlessness, coughing up blood, unexplained weight loss, or…