

Lyme Disease Symptoms: The Rash, the Stages and Why Early Treatment Matters

Key Takeaways
- The Lyme rash appears in about 70 to 80 percent of infections, usually within a week of the bite, and is defined by growth over days rather than by a bull's-eye pattern.
- Blacklegged ticks generally need 36 to 48 hours of attachment to transmit the bacterium, so a same-day tick check and removal prevents most infections.
- CDC surveillance recorded more than 62,000 cases in 2022, but insurance-claims data suggest roughly 476,000 Americans are diagnosed and treated each year.
- Antibody tests miss most infections in the first two to three weeks, which is why a typical rash in a tick-prone area is treated without waiting for blood results.
- Facial palsy occurs in about 9 percent of reported cases and heart block in about 1 percent, both usually within weeks to a few months of the bite.
- Four randomized placebo-controlled trials found that prolonged antibiotics do not improve symptoms that persist after treated Lyme disease.
Lyme disease symptoms usually begin 3 to 30 days after a blacklegged tick bite with an expanding red rash called erythema migrans, often alongside fever, fatigue, headache, and muscle or joint aches. Weeks to months later, untreated infection can cause facial drooping, nerve pain, heart-rhythm problems, or swollen joints, especially the knees. Most people treated early with antibiotics recover fully, so anyone with a suspected tick-related rash or these symptoms should see a clinician promptly.
A father in Connecticut posts a photo of his daughter’s thigh: a pale pink oval, faintly warm, roughly the size of his palm. No itch, no pain, no memory of a tick. The comments split instantly between ‘that’s nothing’ and ‘that’s Lyme, get to a doctor tonight.’ Thousands of versions of that photo are circulating this season, which is one reason searches for lyme disease symptoms have surged.
There are others. As of June 2025, the most recent national count from the CDC shows more than 62,000 reported cases in a single year, the highest figure ever recorded, and a Lyme vaccine candidate has completed enrollment in its final-stage trial. At the same time, viral posts are recasting almost any lingering fatigue as ‘hidden Lyme.’
The evidence supports neither panic nor shrugging. It supports knowing what the rash looks like, what the stages feel like, and why the calendar matters more than most people realize.
What changed recently: why lyme disease symptoms are trending
Three developments explain the spike in attention, and only one of them is about the bacterium itself.
The first is arithmetic. In February 2024 the CDC published its national surveillance figures for 2022: 62,551 reported cases, roughly 1.7 times the annual average for 2017 through 2019. The agency was explicit that most of the jump came from a paperwork change, not a sudden explosion of infections. In January 2022, high-incidence states were allowed to count a case on a positive laboratory result alone, without a clinician’s report of symptoms. Fewer cases fell through the cracks, so the number rose. The underlying trend still points upward, though. The CDC’s separate estimate, built from insurance claims between 2010 and 2018, puts the true burden at about 476,000 people diagnosed and treated each year in the United States, nearly eight times the reported figure.
The second is geography. Blacklegged ticks have spread steadily into counties where residents and clinicians have little practice recognizing the illness. A pale oval on a hiker’s calf in Ohio or Tennessee now warrants the same second look it would get in Massachusetts.
The third is the vaccine pipeline. No Lyme vaccine is currently approved for people in the United States or Europe. One candidate, developed by Pfizer and Valneva, has finished enrolling a phase 3 trial, the final large-scale stage before regulators review a product, and results are awaited. A human vaccine was briefly available between 1998 and 2002 before its manufacturer withdrew it from the market. Until any new product is approved, tick avoidance and prompt recognition of symptoms remain the only tools available, which is exactly why the details below matter.
How does Lyme disease affect you? The bite, the bacterium, the timeline
Lyme disease is caused by Borrelia burgdorferi, and less commonly Borrelia mayonii, a spirochete: a corkscrew-shaped bacterium that moves through tissue by rotating like a drill bit. It reaches people through the bite of an infected blacklegged tick (Ixodes scapularis in the East and Midwest, Ixodes pacificus on the Pacific Coast). Ticks do not jump or fly. They wait on grass and leaf litter, then climb aboard whoever brushes past.
Timing is the single most useful fact about transmission. In laboratory and animal studies, the bacterium usually needs the tick to stay attached for roughly 36 to 48 hours before it moves from the tick’s gut into the person. A tick found and removed the same evening is very unlikely to have passed anything on. The catch is size: the nymph stage, which causes most human infections and peaks from May through July, is about as large as a poppy seed and easily missed for days.
Once inside the skin, the bacterium multiplies locally, and the body’s inflammatory response produces the expanding rash. Over the following days to weeks, spirochetes can travel through the bloodstream to other patches of skin, the nervous system, the heart’s electrical wiring, and the lining of joints. Much of the damage at each stop comes from the immune reaction rather than from the bacteria directly, which is why symptoms can lag well behind the infection itself.
Lyme disease does not spread from person to person, through kissing, or by sharing food. Transmission during pregnancy appears to be rare, and prompt treatment protects both parent and baby, so pregnant people who suspect exposure should tell their clinician early rather than wait.
The Lyme disease rash: what erythema migrans actually looks like
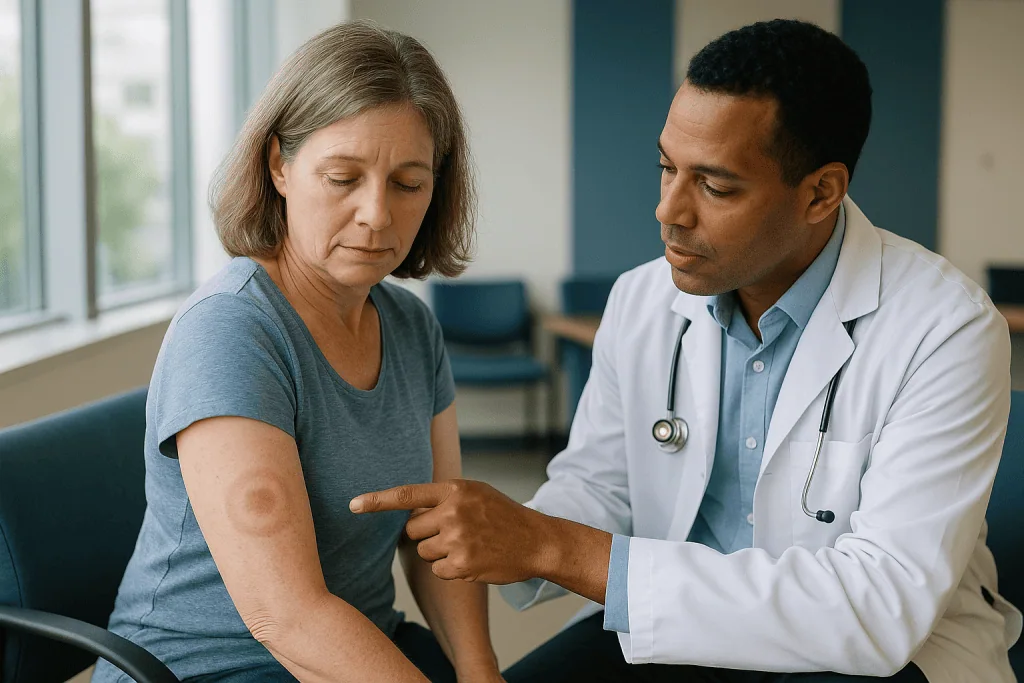
Erythema migrans, the medical name for the Lyme rash, simply means ‘migrating redness,’ and migration is its defining habit. It appears in about 70 to 80 percent of infected people, typically 3 to 30 days after the bite, with a week being most common. It starts as a small red area at the bite site and grows, day by day, to 2 inches across or considerably more; lesions of 12 inches are not unusual. That slow expansion separates it from an ordinary bite reaction, which flares within a day and stays put.
Forget the poster image for a moment. Only a minority of rashes show the classic bull’s-eye with a clear ring. Many are uniformly pink or red, some have a darker center, and a few blister slightly. The surface is usually smooth and may feel warm to the touch. It is rarely itchy and almost never painful, which is precisely why people ignore it.
Skin tone changes the picture. On brown or Black skin, erythema migrans can look like a bruise, a purplish or dusky patch, or an area only subtly darker than the surrounding skin. Clinicians and patients alike miss it more often, and later-stage diagnoses are more common as a result. If a patch is enlarging over days, color matters less than growth.
Ticks favor warm, hidden spots: the groin, armpit, back of the knee, waistline, scalp, and behind the ears. A practical habit is to photograph any suspicious patch next to a coin for scale and trace its edge with a pen, then check the next morning. Multiple rashes appearing at once mean the infection has already spread and deserve same-week medical attention. Untreated, a single rash fades on its own within weeks; the bacterium does not.
Early signs of Lyme disease: at least five to know
The rash is the headline, but Lyme disease in its first weeks is often a whole-body illness that feels like a summer flu with the wrong details. People searching for at least five early signs usually get a list; here is the list with the texture that makes each sign recognizable.

- The expanding rash, described above, present in most but not all cases.
- Fever and chills, usually low to moderate rather than dramatic.
- Fatigue that feels heavier than a poor night’s sleep and arrives without a cold to explain it.
- Headache, often steady and dull; a severe headache with a stiff neck is a different, more urgent sign covered later.
- Muscle and joint aches that drift from place to place over days rather than staying in one joint.
- Swollen lymph nodes, especially near the bite site.
- Neck stiffness without frank pain.
Two clues sharpen the picture. Genuine influenza and most colds bring a cough, a runny nose, or a sore throat; early Lyme disease almost never does. And the season is wrong: the aches-and-fever cluster arriving in June or July after time spent outdoors in a tick-prone region should prompt the question, even without a rash and even without any memory of a tick. Most people with Lyme disease never saw the tick that bit them.
In children, irritability, headache, and refusal to play may stand in for the adult complaints. Because these early symptoms overlap with dozens of ordinary illnesses, the rash, the exposure history, and the calendar together carry more diagnostic weight than any one symptom alone. That is why a clinician will ask where you have been as carefully as how you feel.
Lyme disease stages, side by side
Clinicians describe three overlapping stages. They are not a strict ladder; some people skip the first, and untreated infection does not advance in every case. The percentages below come from CDC surveillance of reported cases and reflect how often each feature is documented, not the risk for any single person.
| Stage | Typical timing after bite | Hallmark features | How often reported |
|---|---|---|---|
| Early localized | 3 to 30 days | Single expanding rash; fever, fatigue, headache, aches, swollen nodes | Rash in about 70 percent of cases |
| Early disseminated | Weeks to a few months | Multiple rashes; facial palsy; meningitis; shooting nerve pain; heart block | Facial palsy about 9 percent; carditis about 1 percent |
| Late | Months to years | Arthritis with marked swelling, usually the knee; less often numbness or memory problems | Arthritis in roughly a third of reported cases |
The early disseminated stage is where symptoms turn specific enough to alarm. Facial palsy, a weakness or drooping of one or both sides of the face, is the most common neurologic sign and can appear before any rash is noticed. Lyme meningitis, inflammation of the membranes around the brain and spinal cord, brings a severe headache, neck stiffness, and sensitivity to light. Radiculopathy, irritation of a nerve root where it leaves the spine, causes shooting or burning pain, often at night, sometimes with numbness.
Lyme carditis is the least common and most urgent. The bacterium inflames the heart’s conduction system and can produce heart block, a delay or interruption of the electrical signal between the upper and lower chambers. Symptoms include palpitations, lightheadedness, fainting, chest discomfort, and shortness of breath. It is treatable, and a temporary pacemaker is occasionally needed while antibiotics work, but it must be recognized quickly.
Untreated Lyme disease symptoms: what months and years can bring
Before antibiotics were understood to treat it, Lyme disease was first described in the 1970s as a mysterious cluster of childhood arthritis in one Connecticut town. That history still explains the late stage best. In classic observational studies of people who went untreated, roughly 60 percent developed Lyme arthritis within months to two years.
Lyme arthritis has a particular signature. It usually strikes one or two large joints, most often a knee, which becomes visibly swollen and warm but is typically less painful than the swelling would suggest. Attacks come and go over weeks, sometimes settling in one joint and then appearing in another. Fluid drawn from the joint shows heavy inflammation. Because a swollen knee in an active adult is so often blamed on injury, Lyme arthritis in an area where the disease was rare a decade ago can go unrecognized for a long time.
Late neurologic disease is less common. It can include numbness and tingling in the hands or feet from peripheral neuropathy, damage to the nerves outside the brain and spinal cord, and a pattern of poor concentration, memory lapses, and mood change sometimes called Lyme encephalopathy. In Europe, where different Borrelia species dominate, a thin, bluish skin change on the hands or feet called acrodermatitis chronica atrophicans can appear years later; it is rare in North America.
The encouraging part is that late disease still responds to antibiotics. Arthritis usually resolves, though it can take longer than early illness and may need more than one course under a specialist’s care. A small share of people develop antibiotic-refractory arthritis, in which joint inflammation persists after the bacteria are gone and is treated as an immune-driven condition rather than an ongoing infection. That distinction shapes every treatment decision at this stage, and it belongs with the treating clinician.
How long can you have Lyme disease without knowing it?
Honest answer: usually weeks, occasionally months, and only rarely longer without something objective showing up. The uncertainty comes from three places.
First, the bite itself. Most people with confirmed Lyme disease do not remember being bitten, because nymphal ticks are tiny and painless and favor hidden skin. Second, the rash. About a quarter of infected people never develop one, or develop it where they cannot see it. Third, the early illness can be mild enough to be written off as a summer bug that passed.
What follows for those people is not silence. Facial palsy or meningitis typically appears within weeks. Lyme arthritis, the most common late presentation, arrives on average about six months after the bite, though it can take longer. Someone who first learns they have Lyme disease from a swollen knee has usually carried the infection for months, not years.
The idea of a decade-long, symptom-free infection that suddenly explains everything is not supported by the evidence. Studies following untreated people show that when the bacterium persists, it produces measurable findings: joint swelling, nerve changes, abnormal heart rhythm, a positive antibody test. Long stretches of vague fatigue with none of these findings are far more often something else.
Antibody tests add their own wrinkle. Antibodies to Borrelia can remain detectable for years after an infection has been treated or has resolved on its own, so a positive result in a person who feels well does not by itself mean an active infection. Clinicians interpret the test alongside the story, and the story includes when and where you might have been exposed.
Lyme disease test accuracy: why a negative early result is not the end
Lyme disease testing looks for the body’s antibodies against the bacterium, not the bacterium itself. That single fact explains most of the confusion about accuracy.
The standard approach is two-tiered. A first blood test, an enzyme immunoassay that screens for antibodies, is followed by a confirmatory test, either a Western blot or a second immunoassay in the newer modified two-tier method. Both must be positive for the result to count.
Antibodies take time to build. In the first two or three weeks after a bite, studies find that roughly a third or fewer of truly infected people test positive. That is why guidelines say a typical erythema migrans rash in a person from a tick-prone area is diagnostic on its own and should be treated without waiting for blood work. Testing a fresh rash is more likely to mislead than to help. By the time of early disseminated disease, sensitivity rises sharply, and in late Lyme arthritis almost everyone infected has a positive result.
The mirror problem is persistence. Antibodies can remain for years after successful treatment, so the test cannot be used to check whether treatment worked or to prove an infection is ongoing. False positives also occur with certain other infections and autoimmune conditions, which is exactly what the second tier is designed to filter out.
Direct tests for the bacterium, such as PCR (a method that detects bacterial genetic material) on joint fluid, have a role in specific situations, mainly suspected Lyme arthritis. The CDC cautions against tests that have not been validated in published studies, including some urine tests and certain culture methods offered outside standard laboratories. A clinician weighing symptoms, exposure, timing, and the right test at the right time will get further than any single result can.
Why early treatment matters, and can you fully recover?
The most important thing to know about Lyme disease is that it is a bacterial infection with an effective treatment, and that treatment works best before the bacterium has traveled. Oral antibiotics such as doxycycline, amoxicillin, or cefuroxime are the standard for early disease. Some neurologic and cardiac presentations are treated with an intravenous antibiotic such as ceftriaxone. Which drug, for how long, and in what form are decisions for the prescribing clinician, shaped by age, pregnancy, allergies, and stage.
Can you fully recover? For the large majority, yes. People treated during the rash stage typically feel well within weeks. Facial palsy usually resolves. Heart block reverses. Arthritis treated appropriately generally settles, though sometimes slowly.
A minority, estimated at around one in ten in some studies and fewer in others, report fatigue, aches, or difficulty concentrating that last six months or more after treatment. Clinicians call this post-treatment Lyme disease syndrome, defined by symptoms that persist after a documented, treated infection. Its cause is not settled; leading hypotheses involve lingering immune activation or residual tissue effects rather than surviving bacteria. Symptoms tend to improve gradually over months, and management focuses on sleep, graded activity, pain, and mood, the same approach used for similar syndromes after other infections.
What the randomized trials show clearly is that months of additional antibiotics do not help these patients and carry real risks, including serious infections from intravenous lines. Anyone with persistent symptoms deserves a thorough evaluation, because thyroid disease, sleep disorders, depression, and other tick-borne infections can all wear the same disguise. The earlier the original infection is caught, the smaller every one of these later problems becomes, and that is the plainest argument for taking a spreading pink patch seriously in the first week.
What the evidence actually says, graded by strength
Not every statement about Lyme disease rests on the same footing. Here is how the main claims in this article rank.
Strong evidence from randomized controlled trials. Standard antibiotic courses treat early Lyme disease effectively; comparative trials of doxycycline, amoxicillin, and cefuroxime show similar high response rates. A large randomized trial published in 2001 found that a short preventive antibiotic course given soon after a high-risk blacklegged tick bite reduced the chance of developing erythema migrans. Four placebo-controlled trials in the United States and the Netherlands, enrolling several hundred people with persistent symptoms after treated Lyme disease, found that prolonged or repeated antibiotics produced no lasting improvement over placebo.
Moderate evidence from surveillance and observational cohorts. The proportions of patients with rash, facial palsy, carditis, and arthritis come from CDC case reports and clinical series, which are consistent across decades but can be skewed by which cases get reported. The 60 percent arthritis figure for untreated infection comes from cohorts followed in the 1970s and 1980s, before routine treatment; it is robust for its era but has not been, and ethically cannot be, repeated.
Laboratory and animal data. The 36-to-48-hour attachment window rests on experiments in animals and on studies of ticks removed from people. It is a well-supported average, not a guarantee in either direction.
Expert consensus. Treatment details for late neurologic disease, the handling of antibiotic-refractory arthritis, and the management of post-treatment symptoms draw heavily on specialist guidelines where trial data are thin. These recommendations are reasonable and widely followed, but they can change as better studies arrive.
The vaccine candidate sits in its own category: a phase 3 trial is under way, and until results are published and reviewed, no claim about its performance is supported by evidence.
Common myths about Lyme disease symptoms
Viral posts recycle the same misunderstandings each summer. The corrections are less dramatic and more useful.
‘If it is not a bull’s-eye, it is not Lyme.’ Most erythema migrans rashes are uniformly red or pink. The ring with a clear center is the exception that got famous. Growth over days is the real signal.
‘No rash means you are safe.’ Roughly one in four infected people never notice a rash. Fever, fatigue, and roving aches after outdoor exposure in tick season warrant a conversation with a clinician regardless.
‘A negative test settles it.’ In the first weeks, antibody tests miss most infections. A positive test, meanwhile, can reflect an old, resolved infection. Neither result should be read without the clinical story.
‘Long-term fatigue is probably chronic Lyme.’ Persistent symptoms after treated Lyme disease are real and deserve care, but randomized trials show extended antibiotics do not help them. Fatigue without a documented infection has many likelier causes, and each is worth checking properly.
‘You will feel the tick bite.’ Nymph bites are painless, and most people with Lyme disease never saw their tick.
‘Burn it or smother it to make the tick let go.’ Heat, petroleum jelly, and nail polish do not work and may cause the tick to release more saliva. Fine-tipped tweezers, a steady pull, and soap and water are the whole procedure.
‘Lyme is a Northeast problem.’ The tick’s range has expanded across the upper Midwest, the mid-Atlantic, the Pacific Coast, and into parts of the South and Canada. Travel history matters as much as home address.
Every one of these myths pushes people toward the same two errors: dismissing a real early infection, or chasing a late one that is not there.
Conditions that look like Lyme disease, and the ticks that carry more than one
Several things can imitate the rash, the early illness, or the late joint and nerve problems. Sorting them is part of why clinicians ask so many questions.
The closest rash lookalike is southern tick-associated rash illness, or STARI, which follows a lone star tick bite and produces an expanding red lesion nearly indistinguishable from erythema migrans. It is not caused by Borrelia, and antibody tests for Lyme disease will be negative. Cellulitis, a bacterial skin infection, is red and warm too, but it is usually painful and tender. Ringworm is scaly with a raised, defined border. An allergic reaction to the bite itself flares within hours and is often itchy. A spider bite reaction is typically painful.
The early flu-like illness overlaps with other tick-borne infections that the same blacklegged tick can carry, sometimes in the same bite. Anaplasmosis brings high fever and low blood counts. Babesiosis, caused by a parasite that infects red blood cells, can cause fever, anemia, and dark urine and is more dangerous in older adults or people without a spleen. Powassan virus is rare but can cause encephalitis. When someone treated for Lyme disease stays feverish, a clinician will often look for these co-infections.
Facial palsy has many causes, most commonly Bell’s palsy of unknown origin; in tick season and tick country, Lyme disease rises on the list, and two-sided palsy raises it further. A swollen knee may be injury, gout, or reactive arthritis. Late fatigue and brain fog share ground with thyroid disorders, sleep apnea, depression, and long COVID.
None of this makes diagnosis hopeless. It makes the combination of exposure, timing, rash, and specific signs more valuable than any single feature, which is the case for describing your summer to your doctor in detail.
Preventing tick bites, and where a Lyme vaccine stands
Because there is no approved vaccine for people, prevention still comes down to keeping ticks off, finding them fast, and removing them right.
Repellents registered with the Environmental Protection Agency and containing DEET, picaridin, IR3535, or oil of lemon eucalyptus reduce bites when applied to exposed skin. Clothing and gear treated with permethrin, an insecticide that kills ticks on contact, adds a second layer; it is for fabric, not skin. Long pants tucked into socks look unfashionable and work.
The 36-to-48-hour window turns a daily habit into protection. Showering within two hours of coming indoors washes off unattached ticks and prompts a full-body check: scalp, behind the ears, armpits, navel, waistband, groin, and behind the knees. A tumble dryer on high heat for ten minutes kills ticks on dry clothing. Pets bring ticks indoors and deserve their own checks and veterinary prevention.
To remove an attached tick, grasp it with fine-tipped tweezers as close to the skin as possible and pull upward with steady, even pressure, without twisting. Clean the area with soap and water or rubbing alcohol. Photographing the tick, or saving it in a sealed bag, can help a clinician judge species and how long it fed. Guidelines allow a clinician to offer a short preventive antibiotic course after certain high-risk bites in high-incidence areas, generally within 72 hours of removal; whether a given bite qualifies is a judgment for that clinician, not a rule of thumb.
On vaccines: a human Lyme vaccine was licensed in 1998 and discontinued by its manufacturer in 2002. The current candidate is in a phase 3 trial with results awaited; it is not available outside that study and is not for sale. Vaccines exist for dogs but are not relevant to human protection.
When to see a doctor about Lyme disease symptoms
Seeing a clinician early is the entire strategy, so the threshold should be low. Make an appointment within a day or two if any of the following applies.
- A red, pink, or bruise-like patch that is growing over several days, with or without a remembered tick bite.
- Fever, chills, fatigue, headache, or roving muscle and joint aches in the weeks after outdoor exposure in a tick-prone area, especially without cough or congestion.
- A tick that was attached for more than 36 hours, appears engorged, or was removed from a young child or a pregnant person.
- A swollen, warm joint, most often a knee, without an injury to explain it.
- Numbness, tingling, or shooting pains that began after possible tick exposure.
Seek same-day or emergency care for the red-flag signs of disseminated disease:
- Drooping or weakness on one or both sides of the face.
- A severe headache with a stiff neck, fever, or sensitivity to light.
- Palpitations, lightheadedness, fainting, chest pain, or shortness of breath, which can signal Lyme carditis and heart block. Call emergency services for fainting or chest pain.
- Confusion, seizures, or difficulty speaking.
Bring the details that sharpen diagnosis: where you have spent time outdoors, the date you first noticed a rash or symptom, any photos of the rash or the tick, and any medicines you take. If you are already on antibiotics for Lyme disease and feel no better after a week or two, or feel worse, contact the prescriber rather than adjusting anything yourself. Choices about which antibiotic, how long, whether preventive treatment after a bite is warranted, and how to manage lingering symptoms all rest with the clinician who examines you.
Frequently asked questions
What are at least 5 early signs of Lyme disease?
The five most common early signs are an expanding red or pink rash, fever with chills, unusual fatigue, headache, and muscle or joint aches that move around. Swollen lymph nodes and a stiff neck often join them. Unlike a cold or flu, early Lyme disease rarely causes a cough, runny nose, or sore throat, and it typically follows outdoor exposure during tick season.
How does Lyme disease affect you over time?
Lyme disease starts as a skin infection at the tick bite and, if untreated, can spread through the bloodstream to the nervous system, heart, and joints over weeks to months. Early illness feels flu-like; later stages can bring facial drooping, nerve pain, heart-rhythm disturbances, and swollen knees. Antibiotics given at any stage treat the infection, though later disease may take longer to settle.
Can you fully recover from Lyme disease?
Most people do recover fully, particularly when treated during the rash stage. A minority, estimated at around one in ten in some studies, report fatigue, aches, or concentration problems lasting six months or more after treatment, known as post-treatment Lyme disease syndrome. Those symptoms usually improve gradually, and randomized trials show extended antibiotics do not speed that improvement.
How long can you have Lyme disease without knowing it?
Typically weeks, sometimes months. Most people never see the tick, and about a quarter never notice a rash, so the first clue may be facial weakness within weeks or a swollen knee around six months later. Years of vague symptoms with no objective findings and no positive test are not supported by the evidence as hidden Lyme disease.
What does the Lyme disease rash look like on darker skin?
On brown or Black skin, erythema migrans often looks like a bruise, a purplish or dusky patch, or an area only slightly darker than the surrounding skin rather than bright red. Because it is easily missed, later-stage diagnoses are more common. The reliable clue at any skin tone is a patch that keeps enlarging over several days without itching or pain.
What are the lyme disease stages?
There are three: early localized (3 to 30 days after the bite) with a single rash and flu-like symptoms; early disseminated (weeks to months) with multiple rashes, facial palsy, meningitis, nerve pain, or heart block; and late (months to years) marked mainly by arthritis, usually in a knee. The stages overlap, and not everyone passes through each one.
How good is lyme disease test accuracy in the first weeks?
Poor early, strong later. Standard two-tier antibody tests detect roughly a third or fewer of infections in the first two to three weeks because antibodies take time to develop. By late disease, nearly all infected people test positive. Antibodies can persist for years after treatment, so a positive test alone cannot confirm an active infection.
Should I get tested right after a tick bite?
Generally no. Testing immediately after a bite cannot detect infection because antibodies have not formed, and testing a typical rash is unnecessary since the rash itself is diagnostic in tick-prone areas. A clinician may instead assess how long the tick was attached and whether a short preventive antibiotic course is appropriate, then watch for symptoms over the following weeks.
Is the Lyme disease rash always a bull's-eye?
No. The ring with a clear center is the famous version but a minority of cases. Most erythema migrans rashes are uniformly red or pink, some have a darker center, and a few blister. What matters is that the patch grows steadily over days, is usually warm but not itchy or painful, and often appears in hidden spots like the groin, armpit, or behind the knee.
Is there a Lyme disease vaccine?
Not currently for people. A human vaccine was licensed in the United States in 1998 and discontinued by its manufacturer in 2002. A new candidate is being tested in a phase 3 trial, the final large-scale stage before regulatory review, with results awaited; it is not available outside that study. Prevention today relies on repellents, clothing, daily tick checks, and prompt removal.
References
- CDC: Signs and Symptoms of Lyme Disease
- CDC: Lyme Disease Surveillance and Data
- NHS: Lyme Disease
- MedlinePlus: Lyme Disease
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Pink Eye: Viral, Bacterial or Allergic: How to Tell and When It Is Contagious
Pink eye (conjunctivitis) is inflammation of the thin membrane covering the white of the eye. Viral cases cause watery discharge and often spread from…

COVID-19 Treatment for Older Adults and People With Chronic Illness: Why Early Review Matters
For older adults and people with chronic conditions, COVID-19 treatment works best when it starts early. Antiviral medicines act on the virus during its…

Sinus Infection: Viral or Bacterial? How Doctors Decide and When Antibiotics Help
Most sinus infections start as viral colds and clear on their own within about ten days without antibiotics. Doctors suspect a bacterial sinus infection…

Lyme Disease Follow-Up: Why Doctors Check Joints, Heart Rhythm and Nerves After Treatment
After treatment for Lyme disease, doctors follow up on joints, heart rhythm and nerves because these are the systems the infection can affect weeks…

RSV Symptoms in Adults: How to Tell It From Flu and COVID, and Who Is at Risk
RSV symptoms in adults usually look like a heavy cold: runny nose, cough, sneezing, sore throat, mild fever and sometimes wheezing, building over several…

Ringworm: The Fungal Infection That Is Not a Worm: Symptoms and Treatment
Ringworm is a common skin infection caused by fungi called dermatophytes, not by any worm. It usually appears as a red or pink, scaly,…