

Microsurgical vs Laparoscopic Varicocelectomy: How the Two Varicocele Repairs Compare

Key Takeaways
- Microsurgical varicocelectomy works low in the groin under roughly 8–15x magnification, while laparoscopic repair clips the veins high in the abdomen through two or three ports.
- The 2009 Cayan meta-analysis reported recurrence of about 1 percent after microsurgical repair versus about 4 percent after laparoscopy, and hydrocele under 1 percent versus about 3 percent.
- Laparoscopy requires general anesthesia and entry into the abdominal cavity; microsurgical repair can be done under regional or local anesthesia with sedation.
- Because sperm take roughly 72 days to develop, the first meaningful post-operative semen analysis is usually scheduled around three to four months after surgery.
- Ejaculation frequency has no effect on a varicocele, which is a structural problem of vein valves and back-pressure, not of fluid volume.
- Most adults return to non-strenuous work within about a week after either technique, with heavy lifting and sport deferred for roughly two weeks or as the surgeon directs.
Microsurgical varicocelectomy ties off the enlarged testicular veins through a small groin incision under an operating microscope, sparing the artery and lymph channels; laparoscopic varicocelectomy clips the veins higher in the abdomen through keyhole ports. Published meta-analyses report fewer recurrences and fewer post-operative hydroceles with the microsurgical approach, while laparoscopy is sometimes chosen for two-sided repair. Surgeon experience and individual anatomy matter most, and the choice belongs to the treating team.
The ultrasound report is two pages long, but one line is the reason a 31-year-old is sitting in a urology waiting room: left-sided varicocele, grade 3. He and his partner have been trying for a baby for fourteen months. The urologist has said the word “repair” and offered two ways of doing it, one through a small cut low in the groin with a microscope, the other through three keyhole ports in the abdomen. He has a week to think about it.
The microsurgical vs laparoscopic varicocelectomy decision is one that many people meet without any earlier warning. They often arrive with a search history full of forum posts, a few percentages that contradict each other, and a strong wish to simply be told which one is “best.”
This explainer walks through what each operation actually involves, what the pooled evidence shows about recurrence and complications, what the weeks afterward usually look like, and which questions are worth asking before anyone signs a consent form.
What is a varicocele, and why does anyone operate on it?
A varicocele is a cluster of enlarged veins inside the scrotum, the same sort of change that produces varicose veins in a leg. The veins in question drain the testicle and form a network called the pampiniform plexus, which runs upward inside the spermatic cord, the bundle of vessels, nerves and the sperm-carrying tube that connects the testicle to the abdomen.
The condition is common. Mayo Clinic estimates that roughly 10 to 15 of every 100 men have one, and most never notice it. Around nine in ten sit on the left side, a quirk of anatomy: the left testicular vein takes a longer, steeper route and joins the left kidney vein at a right angle, which makes back-pressure and valve failure more likely.
So why operate on something so ordinary? Two reasons come up again and again in clinic. The first is fertility. Cleveland Clinic notes that varicoceles are found in about 40 percent of men evaluated for infertility, far above the background rate. Pooled venous blood is thought to warm the testicle by a degree or two and to expose it to metabolic waste, and both changes can affect sperm count, movement and shape. The second reason is a dull, dragging ache that worsens through the day, with standing, or after exercise, and eases when lying down.
A third, less common trigger is a shrinking testicle. When the affected side is measurably smaller than the other, especially in an adolescent, the surgeon may worry that the tissue is being damaged over time.
Repair itself has a single goal, whatever the technique: block the faulty veins so blood finds other, healthier routes back to the heart, while leaving the artery and the lymph channels that drain the testicle untouched. The two operations in this article are simply two different ways of reaching those veins.
How microsurgical and laparoscopic varicocelectomy actually work
Picture the spermatic cord as a rope of cables running from the scrotum up through the groin and into the lower abdomen. The two operations approach that rope at different heights.
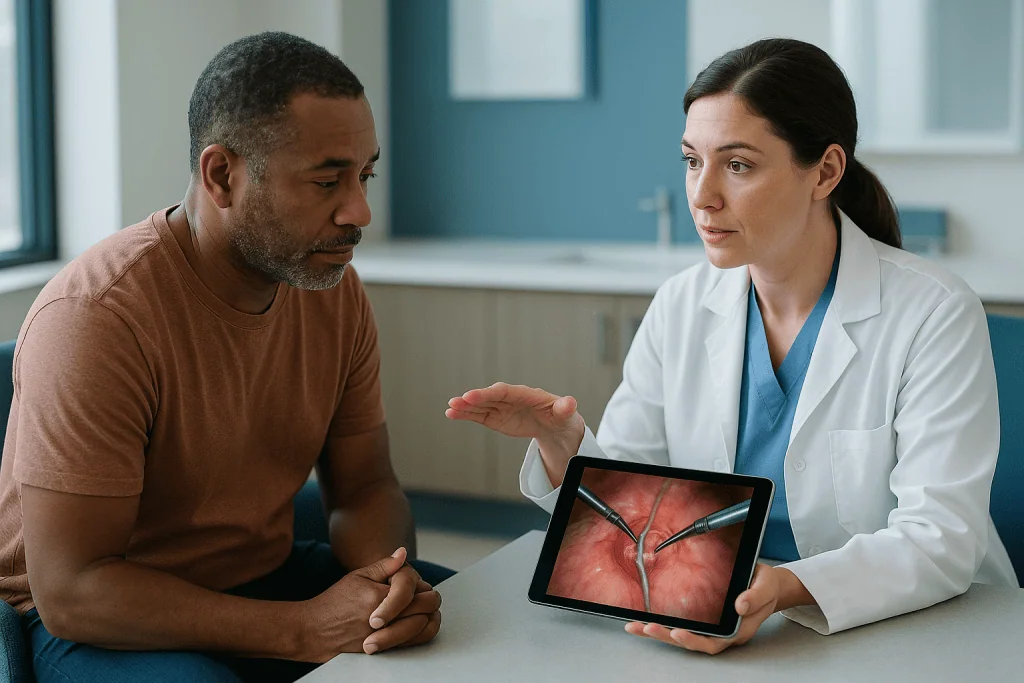
Microsurgical varicocelectomy works low, near where the cord leaves the groin canal. The surgeon makes an incision of a few centimeters just below the crease of the groin (the subinguinal approach) or slightly higher within the canal (the inguinal approach). The cord is lifted onto the surface and examined under an operating microscope at magnification of roughly eight to fifteen times. At that scale, the testicular artery, which can be less than a millimeter wide, shows up as a pulsing thread, and the lymph vessels appear as clear, fluid-filled tubes. The surgeon ties off every enlarged vein, often a dozen or more, and deliberately preserves the artery, the lymphatics and the vas deferens with its own small vessels. Because the cord is exposed rather than tunneled toward, the surgeon can also check veins running alongside the cord outside its sheath, a known source of missed drainage.
Laparoscopic varicocelectomy works high. Under general anesthesia, the abdomen is inflated with carbon dioxide and two or three ports, each around half a centimeter to a centimeter, are placed through the abdominal wall. A camera goes through one, instruments through the others. The surgeon finds the testicular vessels where they run along the back of the abdominal cavity, well above the groin, and clips or seals the veins there. At this height the veins have usually merged into one or two larger trunks, so there is less to divide, and both sides can be reached through the same ports. The trade-off is that the artery and lymphatics are bundled closely with the veins and are harder to separate without magnification; some surgeons preserve them, others deliberately take the whole bundle.
Both methods achieve the same physiological end: blood re-routes through the many smaller veins that drain the scrotum and groin.
What happens on the day of surgery
Both operations are typically day-case procedures, meaning most people go home the same day, according to Cleveland Clinic and Mayo Clinic patient information. The details differ in ways that matter for planning.
Anesthesia is the first fork. Laparoscopy needs a general anesthetic, because inflating the abdomen and placing ports is not tolerable awake and the muscles must be fully relaxed. Microsurgical repair is also usually done under general anesthesia, but it can be performed under regional or local anesthesia with sedation, which some people with lung or heart conditions prefer to discuss.
Operating time runs in the same rough band for both, often an hour to two, and lengthens when both sides are treated. Under the microscope the surgeon works slowly by design, isolating each vein individually; laparoscopy involves fewer structures to divide but more setup at the start and the end.
Incisions look different afterward. A microsurgical patient leaves with a single dressing low in the groin, close to the pubic hairline. A laparoscopic patient has two or three small dressings across the abdomen, one usually at the navel. People sometimes assume the keyhole option means less soreness, but abdominal insufflation can cause shoulder-tip discomfort for a day or two as trapped gas irritates the diaphragm, a sensation the groin approach does not produce.
Before leaving, the care team usually explains wound care, when to shower, how to support the scrotum, and which sensations are expected. Firm, tender swelling along the cord and some bruising into the scrotum are common after either method. A written plan for follow-up, including when a semen analysis will be repeated if fertility was the reason for surgery, should go home with the patient.
Anyone with a bleeding disorder, previous groin or abdominal surgery, or a hernia repair with mesh should raise it early, because scar tissue can push a surgeon toward one approach over the other.
Who is usually offered varicocele repair, and who is asked to wait?
Not every varicocele earns an operation. Guideline-level advice from major urology bodies, summarized in Mayo Clinic and Cleveland Clinic patient material, converges on a short list of situations where repair is reasonable to consider.

Repair is most often discussed when three things line up: the varicocele can be felt on examination (a palpable or clinical varicocele, rather than one seen only on ultrasound), the semen analysis is abnormal, and a couple has been trying to conceive without success while the partner’s own evaluation is normal or correctable. Pain that is clearly attributable to the varicocele, has not settled with conservative measures such as supportive underwear and anti-inflammatory approaches directed by a clinician, and interferes with daily life is a second accepted reason. A third is a testicle on the affected side that is measurably smaller than its pair, particularly in adolescents, where the concern is ongoing damage to growing tissue.
The people usually asked to wait, or not offered surgery at all, are those whose varicocele is small and found only on imaging, those with a normal semen analysis and no symptoms, and men whose partners are pursuing assisted reproduction on a timeline that would not allow the three to six months it typically takes for any sperm changes to appear. In that last group, the fertility specialist and urologist often weigh repair against moving directly to treatment such as intrauterine insemination or in vitro fertilization, and the answer depends heavily on the partner’s age and ovarian reserve.
Men with a varicocele and no sperm at all in the ejaculate, known as azoospermia, occupy a gray area. Some studies report that a minority regain some sperm after repair, but the evidence is mixed and the discussion is highly individual.
A right-sided varicocele that appears suddenly in an adult, or one that does not deflate when lying down, prompts imaging of the abdomen before any repair is considered, because a mass pressing on the veins must be excluded first.
Microsurgical vs laparoscopic varicocelectomy at a glance
The table below compresses the practical differences people most often ask about. The complication figures come from a 2009 meta-analysis by Cayan and colleagues that pooled studies of palpable varicocele repair in infertile men; those studies were mostly observational rather than randomized, so the numbers describe reported experience rather than a guarantee for any individual.
| Feature | Microsurgical (subinguinal or inguinal) | Laparoscopic |
|---|---|---|
| Where the veins are blocked | Low, at the groin, on the exposed cord | High, inside the abdomen near the kidney level |
| Magnification | Operating microscope, roughly 8–15x | Video camera, modest optical zoom |
| Anesthesia | General, regional or local with sedation | General only |
| Incisions | One, a few centimeters in the groin | Two or three ports across the abdomen |
| Artery and lymphatic preservation | Routinely identified and spared | Harder to separate; practice varies |
| Reported recurrence (Cayan 2009) | About 1 in 100 | About 4 in 100 |
| Reported hydrocele (Cayan 2009) | Under 1 in 200 | About 3 in 100 |
| Two-sided repair | Second groin incision needed | Same ports reach both sides |
| Specific risks | Groin wound issues, rare arterial injury | Bowel or vessel injury from port entry, gas-related shoulder pain |
| Typical return to desk work | Within about a week | Within about a week |
Two caveats belong next to any table like this. First, results in the pooled literature came from surgeons already experienced in their chosen technique; a microscope does not compensate for an operator who rarely uses one. Second, the categories are not airtight. Some laparoscopic series describe careful artery- and lymphatic-sparing dissection, and some open groin repairs use magnifying loupes rather than a full microscope. When a surgeon describes a technique, it is fair to ask exactly which structures will be preserved and how.
Which method of varicocele surgery is best? What the evidence actually shows
The honest answer is that no single technique is best for every patient, but the pooled evidence does lean in one direction for the commonest scenario: a single palpable varicocele in a man seeking to improve fertility.
The 2009 meta-analysis by Cayan, Shavakhabov and Kadioglu compared open non-microsurgical repair, laparoscopic repair, microsurgical repair and radiologic embolization across dozens of published series. Microsurgical repair produced the lowest recurrence and the lowest hydrocele rates of any technique, and it was associated with the highest spontaneous pregnancy rate among partners, reported at roughly 42 percent compared with roughly 30 percent after laparoscopy. Those pregnancy figures should be read as a signal rather than a promise: the underlying studies varied in follow-up length, partner age was not consistently controlled, and most were not randomized.
Why might magnification matter so much? Recurrence after any varicocelectomy usually comes from a vein that was missed, either a small one inside the cord or one running outside its sheath. Working at the groin under a microscope, the surgeon sees and ties those small and external veins individually. Working high in the abdomen, the surgeon divides the main trunk but cannot reach veins that branch off lower down. Hydrocele, a collection of fluid around the testicle, arises when lymph channels are tied along with the veins; the microscope makes those clear channels visible, whereas at laparoscopy they are easier to include in a clip.
Laparoscopy keeps genuine advantages. When both sides need repair, one set of ports does the job that two groin incisions would otherwise require. Surgeons already fluent in laparoscopy may achieve results in their own hands that outperform a microsurgical series from a center where the microscope is rarely used. Randomized trials directly comparing the two remain small in number and size, so the evidence grade is moderate at best.
What matters most, in this writer’s reading of the data, is a surgeon who does one of these operations often, can quote their own recurrence and hydrocele figures, and can explain why they favor their approach for this particular anatomy.
What is the success rate of microsurgical varicocelectomy?
“Success” hides three different questions, and the answer changes depending on which one is being asked.
If success means the varicocele does not come back, the pooled figure from the Cayan 2009 meta-analysis is a recurrence rate of about 1 percent for microsurgical repair, the lowest of the techniques reviewed. Recurrence is usually judged by re-examination and ultrasound several months later.
If success means semen parameters improve, the picture is more nuanced. Mayo Clinic’s patient information notes that improvement, when it happens, tends to appear over several months, because a sperm cell takes roughly two and a half to three months to develop from stem cell to mature sperm, and the testicle needs time to recover from the heat and pressure it was under. Many men see gains in sperm concentration and movement; some see little change; a few see numbers move in unexpected directions on a single test, which is one reason clinicians repeat semen analysis rather than acting on one result. Semen analysis is notoriously variable from week to week even in men who have had no surgery at all.
If success means a baby, the honest statement is that repair shifts odds rather than settling them. The same meta-analysis reported a spontaneous pregnancy rate near 42 percent after microsurgical repair in the pooled infertile population, but partner age, the woman’s own fertility evaluation and the length of follow-up all shape that number, and none of the pooled studies can tell an individual couple what will happen to them.
For pain, most published series describe relief in the majority of men whose pain was carefully attributed to the varicocele beforehand, with a minority reporting persistent discomfort. Pain that does not fit the classic pattern (dull ache, worse standing, better lying down) is less likely to respond, which is why surgeons screen so carefully before operating for pain alone.
Anyone quoted a single “success rate” is entitled to ask which of these outcomes it refers to, in which population, over what period.
Laparoscopic varicocelectomy side effects, and how the microsurgical list differs
Every operation has a risk profile, and these two overlap in some places and diverge in others. Cleveland Clinic and Mayo Clinic list the common concerns after any varicocele repair as hydrocele formation, recurrence, injury to the testicular artery, infection, bleeding and, rarely, testicular shrinkage.
Laparoscopic repair carries a set of risks that come from entering the abdomen rather than from the varicocele itself. Placing ports involves passing instruments through the abdominal wall, and although injury to bowel, bladder or major blood vessels is rare, it is a recognized hazard that does not exist with a groin incision. Carbon dioxide used to inflate the abdomen can leave people with bloating and referred pain at the tip of the shoulder for a day or two. General anesthesia is mandatory, with its own small risks. Because the lymphatic vessels are bundled tightly with the veins at that level, hydrocele is more frequent, reported at roughly 3 percent in the Cayan 2009 pooled analysis compared with well under 1 percent after microsurgical repair. Recurrence is also higher, at around 4 percent versus about 1 percent, because veins branching lower than the clip site are left behind.
Microsurgical repair trades those abdominal hazards for groin-specific ones. The wound sits in a skin fold that can become moist and irritated. Numbness or altered sensation over the upper inner thigh and scrotum can follow handling of a small sensory nerve that runs with the cord; it is usually temporary. The testicular artery is deliberately preserved, but it is thin and can spasm or, very rarely, be injured despite magnification, which is the mechanism behind the uncommon complication of testicular atrophy.
Both approaches share bruising along the cord and into the scrotum, firm swelling that softens over weeks, and a small risk of wound infection. Neither is known to reduce testosterone production in the long term; some studies suggest a modest rise after repair, but the evidence is not strong enough to make that a reason to operate.
Does varicocelectomy improve sperm and pregnancy chances, and on what timeline?
The biology sets the calendar. Sperm production, called spermatogenesis, runs on a roughly 72-day cycle, and the sperm then need another couple of weeks to travel and mature. Any change a repair produces cannot show up in a semen sample tomorrow; it becomes measurable only once a new cohort of sperm has developed in cooler, less congested tissue. That is why Mayo Clinic advises that results may take several months to become apparent, and why most urologists schedule the first post-operative semen analysis around three to four months after surgery, with a second at about six months if the first is equivocal.
What the analysis is looking for is movement in three parameters: concentration (how many sperm per milliliter), motility (what proportion swim, and how well) and morphology (what proportion have a normal shape). Repair is most consistently linked to gains in concentration and motility. Some research groups also report reductions in sperm DNA fragmentation, a measure of genetic damage within sperm that may matter for embryo quality, although testing for it is not yet routine everywhere.
Whether those laboratory gains become a pregnancy depends on the couple as a unit. A repair that lifts a man’s count from very low to moderate may be transformative for a couple whose only barrier was male factor infertility, and irrelevant for a couple whose main obstacle sits elsewhere. Fertility specialists often frame the decision as buying time versus using time: repair and a six-month wait can be reasonable when the partner is younger and has a normal evaluation, while moving directly to assisted reproduction may make more sense when time is tighter.
The technique question threads through this. Because microsurgical repair has the lowest reported recurrence, a man who has waited six months is less likely to discover that a missed vein has undone the effort. That is a practical argument, not a promise of a particular result.
Varicocele surgery recovery time: what the first days and weeks look like
Recovery from either operation is measured in days for the basics and weeks for the details, and the two approaches run on similar clocks with slightly different textures.
The first 48 hours are about soreness and swelling. After microsurgical repair, the groin incision aches with movement, especially getting in and out of a car or climbing stairs, and the scrotum on that side may bruise and swell. After laparoscopy, the port sites are tender and the belly feels bloated; shoulder-tip discomfort from residual gas is common on day one and fades as the body absorbs it. Supportive underwear or an athletic supporter helps with either approach by taking weight off the cord. Cleveland Clinic advises that most people can return to non-strenuous work and normal daily activity within about a week.
The second week is when many people feel almost normal but are asked to hold back. Lifting anything heavy, running, cycling and contact sports are typically deferred for a couple of weeks or as the surgeon directs, because straining raises pressure in the newly re-routed veins and stresses healing tissue. Sexual activity is usually cleared once the incision is comfortable, often within one to two weeks, though individual advice varies.
Around weeks three to six, firm swelling along the cord softens. It can take longer for the last of the fullness in the scrotum to settle, and a small, firm knot at the incision is scar tissue rather than a returning varicocele.
Follow-up usually happens at a few weeks to check the wound and again around three to four months with a repeat semen analysis if fertility was the goal, according to Cleveland Clinic. Pain relief, when repair was done for pain, tends to be judged at the three-month mark, once surgical soreness has fully cleared and the underlying ache can be assessed on its own.
None of these timelines is a promise; they are typical ranges, and the surgeon’s own instructions take precedence.
Varicocele embolization vs surgery: where the third option fits
Any honest comparison of the two operations has to acknowledge a non-surgical alternative, because many people first hear about it from a friend or an online forum and wonder why it was not offered.
Percutaneous embolization is a procedure performed by an interventional radiologist rather than a surgeon. A thin tube called a catheter is threaded into a vein, usually at the groin or the neck, and guided under X-ray to the testicular vein. Coils, plugs or a sclerosing liquid are released to block the vein from the inside. There is no incision beyond a needle puncture, sedation rather than general anesthesia is common, and people typically walk out within hours. Mayo Clinic lists it as an established alternative to surgical repair.
The pooled evidence gives it a mixed report card. In the Cayan 2009 meta-analysis, embolization had a recurrence rate higher than microsurgical repair, and technical failure, meaning the radiologist cannot reach or fully block the vein because of its anatomy, occurs in a minority of attempts. It carries its own specific risks: coil migration, contrast reactions and radiation exposure, all uncommon. It is often considered after a failed surgical repair, because the anatomy of recurrent veins can be easier to map from inside than to re-explore through scar tissue.
Beyond embolization, the alternatives are simpler. Watchful waiting with repeat semen analysis is a legitimate choice when parameters are borderline. Supportive underwear and clinician-directed anti-inflammatory strategies address pain without addressing the veins. For couples, assisted reproduction can bypass a varicocele’s effect on sperm entirely, though at the price of treating the woman for a problem that sits with the man.
Which route suits a given person depends on why the varicocele is being treated, how urgent the fertility timeline is, and what expertise is available locally. Those are conversations to have with the urologist, and often with a fertility specialist in the same room.
What people often get wrong about varicocele repair
The myths around this topic are stubborn, partly because the subject is private and people research it alone. A few deserve direct correction.
“Ejaculating more often shrinks a varicocele.” It does not. A varicocele is a structural problem with vein valves and back-pressure; sexual activity does not change vein anatomy in either direction. Frequency of ejaculation affects how long sperm sit in storage before a semen analysis, which is why labs ask for a set abstinence window, but it has no bearing on the varicocele itself.
“Every varicocele needs surgery.” Most do not. Mayo Clinic and Cleveland Clinic both emphasize that a varicocele causing no symptoms, with a normal semen analysis and no testicular size difference, is usually left alone.
“Keyhole means less invasive, so laparoscopic is automatically gentler.” The ports are small, but the operation enters the abdominal cavity under general anesthesia and involves inflating it with gas. A microsurgical repair, though done through an open incision, stays outside the abdomen. “Less invasive” is not a straightforward label here.
“A bigger varicocele hurts more and does more damage.” Size and symptoms correlate loosely at best. Large varicoceles are often painless, and small palpable ones can be associated with abnormal semen parameters.
“If the semen analysis has not improved by three months, the operation failed.” Three months is the earliest point at which change could appear, not the deadline. Repeat testing at six months is routine.
“Cost tells you which technique is better.” This article does not publish prices, and no figure would be meaningful across different health systems, insurers and facilities. What costs vary with, in any system, is the type of anesthesia, facility time, imaging and the number of follow-up semen analyses. Those are questions for the care team’s administrative staff and the insurer, and they say nothing about which technique fits a particular anatomy.
Varicocele repair in teenagers: a different calculation
Adolescents are the group in whom varicoceles are most often first noticed, typically during a sports physical or when a teenager mentions a heaviness on one side. Cleveland Clinic notes that varicoceles usually develop during puberty, as blood flow to the growing testicles increases and any weakness in the vein valves becomes apparent.
The decision to repair looks different at this age because the outcomes being protected are years away. A teenager cannot reasonably provide a fertility history, and semen analysis is not routinely requested from minors. Instead, clinicians watch two things: the size of the affected testicle compared with the other, measured on ultrasound, and any progression over time. A persistent size difference, generally judged as the affected testicle being markedly smaller than its pair on repeated measurement, is the most common reason a pediatric urologist raises the possibility of surgery. Pain that limits activity is the other.
Where surgery is chosen, the technical arguments mirror those in adults, with one extra consideration. Hydrocele after repair is a nuisance in an adult; in a teenager it can mean a second operation during formative years. Because the microsurgical approach has the lowest reported hydrocele rate, many pediatric urologists favor it, though laparoscopic and lymphatic-sparing laparoscopic techniques are also widely used, and outcomes in experienced hands are good with either.
Preparation and comfort matter as much as technique for this age group. Teenagers do better when they understand what the incisions will look like, when they can return to sport, and that bruising into the scrotum is expected rather than alarming. Parents are often surprised that day-case discharge is standard and that the first week of recovery resembles a bad muscle strain more than a hospital stay.
Many adolescent varicoceles are simply observed with an examination and ultrasound every year or so, and a teenager who is not offered surgery has not been dismissed; watchful waiting is the guideline-level default when the testicles are growing evenly.
Questions to ask your care team before choosing a technique
A good surgical consultation leaves time for questions, and the quality of the answers is itself a piece of information. These are the ones that most reliably move a decision forward.
- Which technique do you perform most often for varicocele, and roughly how many do you do each year? Experience with a specific approach predicts results more than the approach itself.
- Will you use an operating microscope, magnifying loupes, or laparoscopic optics? The word “microsurgical” is sometimes used loosely, so it is fair to ask what magnification is actually planned.
- Will the testicular artery and the lymphatic channels be identified and preserved? If not, how do you manage the hydrocele risk?
- What are your own recurrence and hydrocele rates, and how do you follow patients to know them?
- Is my varicocele on one side or both, and does that change your recommendation?
- What anesthesia will be used, and are there options given my medical history?
- If fertility is the goal, when will my semen analysis be repeated, and what result would prompt a different plan?
- Should a fertility specialist be involved before surgery, given my partner’s age and evaluation?
- What would make you recommend embolization or watchful waiting instead of surgery for someone like me?
- What should I stop or continue before the operation, and who do I contact if something feels wrong afterward?
Writing the answers down during the visit helps, because the details blur quickly once the conversation turns to dates and paperwork. Bringing a partner or friend also helps, not only for recall but because fertility decisions belong to both people in a couple.
One question people rarely ask but should: what happens if the first repair does not hold? Knowing in advance whether the surgeon would re-operate, refer for embolization or reassess the fertility plan removes a great deal of anxiety later, and the answer often reveals how the surgeon thinks about the whole pathway rather than the single operation.
When to call your doctor after varicocele surgery
Most recovery from either technique is uneventful, and the expected course is soreness that peaks in the first two or three days and then fades steadily. A few signs fall outside that pattern and warrant a call to the surgical team or, in some cases, emergency care.
Contact the care team the same day for a fever, spreading redness, warmth or pus at an incision, or a wound that opens. Rapidly increasing swelling of the scrotum, especially if it is tense, discolored and accompanied by worsening pain, can indicate bleeding into the tissues and needs prompt assessment. Pain that escalates after the second or third day rather than easing, or pain that is not controlled by the plan the team provided, should also be reported.
Seek urgent or emergency care for sudden severe testicular pain, a testicle that feels hard and exquisitely tender, nausea or vomiting with the pain, or a testicle that appears to be sitting higher or at an unusual angle. These can signal a compromised blood supply and are treated as time-critical. After laparoscopic repair, worsening abdominal pain, a rigid or very distended abdomen, persistent vomiting, or inability to pass urine or stool are red flags for an internal injury or obstruction and need emergency evaluation.
Symptoms of a blood clot in the leg or lung are uncommon after these day-case operations but should never be ignored: calf pain or swelling on one side, sudden breathlessness, chest pain or coughing up blood require emergency care.
Later concerns are gentler but still worth a call: a soft, painless swelling around the testicle appearing weeks after surgery may be a hydrocele; a return of the bag-of-worms feel or the original dull ache months later may indicate recurrence; and numbness in the inner thigh that has not improved after several weeks should be reviewed.
When in doubt, call. Surgical teams would far rather hear about a false alarm than see a real problem arrive late. Every decision about further tests or treatment sits with them.
Frequently asked questions
Which method of varicocele surgery is best?
For a single palpable varicocele in a man seeking to improve fertility, pooled evidence favors the microsurgical approach, which had the lowest recurrence and hydrocele rates in the 2009 Cayan meta-analysis. Laparoscopy remains a reasonable choice for two-sided repair and in centers with strong laparoscopic experience. Surgeon volume with a specific technique matters more than the label, and the final recommendation rests with the treating team.
What is the microsurgical varicocelectomy success rate?
It depends on what is being measured. The 2009 Cayan meta-analysis reported recurrence of roughly 1 percent and a spontaneous partner pregnancy rate near 42 percent in pooled infertile populations. Those figures come mostly from observational studies with varied follow-up, so they describe reported experience rather than an individual forecast. Semen improvements, when they occur, usually appear over three to six months.
Does ejaculating reduce varicocele?
No. A varicocele is a structural problem: the valves in the testicular veins fail and blood pools under back-pressure. Ejaculation does not alter vein anatomy or valve function in either direction. The only reason clinicians ask about ejaculation frequency is that labs require a set abstinence window before a semen analysis so results can be compared fairly between tests.
How much does a microsurgical varicocelectomy cost?
This article does not publish prices, because no figure is meaningful across different health systems, insurers and facilities. What drives variation in any system is the type of anesthesia, operating room and recovery time, pre-operative imaging and the number of follow-up semen analyses. The care team’s administrative staff and the insurer can give a person an accurate picture for their own situation.
What is the typical varicocele surgery recovery time?
Most people go home the same day and return to non-strenuous work and daily activity within about a week after either technique, according to Cleveland Clinic. Heavy lifting and sport are typically deferred for a couple of weeks or as the surgeon directs. Bruising and firm swelling along the cord soften over several weeks. Individual instructions from the surgical team override any general timeline.
What are the main laparoscopic varicocelectomy side effects?
Laparoscopy carries the general risks of entering the abdomen under general anesthesia: rare injury to bowel or blood vessels during port placement, and temporary shoulder-tip pain from the carbon dioxide used to inflate the abdomen. Pooled data also show higher hydrocele and recurrence rates than microsurgical repair, because lymphatic channels are harder to separate from veins at that level and lower branching veins may be missed.
How does varicocele embolization vs surgery compare?
Embolization blocks the vein from the inside using a catheter, with no incision and usually sedation rather than general anesthesia. It is a recognized alternative listed by Mayo Clinic, and it is often used after a failed surgical repair. In pooled analyses its recurrence rate was higher than microsurgical repair, and the vein cannot be reached in a minority of attempts. Suitability depends on anatomy and the reason for treatment.
Can a varicocele come back after microsurgical repair?
Yes, though it is uncommon. The 2009 Cayan meta-analysis reported recurrence of about 1 percent after microsurgical repair, the lowest of the techniques compared. Recurrence usually comes from a small vein missed at the original operation, which the microscope is designed to minimize. A returning dull ache or bag-of-worms feel months after surgery should be reviewed with the surgeon, often with a repeat ultrasound.
How long after varicocelectomy will sperm improve?
Sperm production runs on a roughly 72-day cycle, so any effect of repair cannot appear until a new generation of sperm has matured in the cooler, less congested testicle. Most urologists repeat the semen analysis around three to four months after surgery and again at about six months. Mayo Clinic notes that improvements, when they occur, may take several months to become apparent.
Does every varicocele need surgery?
No. Mayo Clinic and Cleveland Clinic both note that a varicocele causing no pain, with a normal semen analysis and no testicular size difference, is usually monitored rather than repaired. Surgery is generally considered when the varicocele is palpable and associated with abnormal semen parameters in a couple trying to conceive, when it causes persistent pain, or when the affected testicle is measurably smaller.
References
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Are You Stone-Free After Laser Lithotripsy? What Follow-Up Imaging Checks and Why It Matters
Being stone free after laser lithotripsy means no fragments remain in the kidney or ureter on follow-up imaging, not just that the surgeon saw…
Medication, Injections, Traction or Surgery: How a Peyronie’s Disease Plan Is Chosen
A Peyronie's disease plan is chosen mainly by timing and severity. During the active phase, when pain and curvature are still changing, clinicians usually…

Is a Fever After a Cystoscopy Normal? Which Symptoms Need a Same-Day Call to Your Urologist
A true fever after cystoscopy is not part of a normal recovery. Mild burning, pink-tinged urine and needing to pee more often usually settle…

Renal Tubular Acidosis in Children: How Growth and Treatment Are Monitored Over Time
Renal tubular acidosis in children is monitored with a repeating cycle of growth measurements, blood tests for bicarbonate and potassium, urine tests, and periodic…

Ureteral Stricture Repair Recovery: Living With the Stent and the Follow-Up Scans Ahead
Ureteral stricture surgery recovery usually unfolds in two stages: healing from the repair itself, then living with a temporary internal stent that splints the…

Recent Antibiotics, Kidney Disease or Allergies: How They Shape Acute UTI Treatment
Recent antibiotic use, reduced kidney function and drug allergies each narrow which antibiotics are likely to work safely for an acute urinary tract infection.…