

Peritoneal Dialysis or Hemodialysis: Which Fits Your Life, Health and Home Setup?

Key Takeaways
- The NHS and NIDDK both frame peritoneal dialysis and hemodialysis as equally effective for most people, so lifestyle and medical suitability, not potency, usually decide the choice.
- In-center hemodialysis typically means about three four-hour sessions a week, while peritoneal dialysis runs daily, either as roughly four manual exchanges or eight to ten hours overnight on a cycler.
- Peritonitis, infection of the abdominal lining signaled by cloudy drained fluid, is the main disadvantage of peritoneal dialysis and the leading reason people eventually switch to hemodialysis.
- A hemodialysis fistula usually needs two to three months to mature, which is why access surgery is planned well before dialysis is expected to start.
- Peritoneal dialysis tends to preserve residual kidney function longer, so many people keep passing urine for years and often have looser fluid and potassium limits.
- Registry evidence shows no clear long-term survival winner overall; peritoneal dialysis often looks favorable early in younger non-diabetic patients, with the comparison evening out later.
For most people with kidney failure, peritoneal dialysis and hemodialysis are considered equally effective, so the choice usually rests on lifestyle, home setup and other health conditions rather than on one being medically superior. Hemodialysis typically means several hours of treatment about three times a week, often at a center. Peritoneal dialysis is done daily at home through an abdominal catheter and requires training and storage space. The kidney team weighs anatomy, other illnesses and personal preferences before deciding together with the patient.
The folder on the kitchen table has two pamphlets in it, and neither one has been opened since the appointment. One shows a person in a recliner with a machine humming beside them. The other shows someone hanging a soft bag of fluid from a hook in a bedroom. Somewhere between those two pictures is the next decade of a life, and the person whose kidneys are failing has been asked to choose.
The peritoneal dialysis vs hemodialysis question is one of the few genuinely shared decisions in medicine, because the evidence does not hand anyone an easy winner. Both methods take over the filtering work that kidneys can no longer do. Both keep people alive and functioning for years. They differ in where the treatment happens, how often, what it asks of your body and your home, and what kind of day it leaves you with afterward.
This explainer walks through what each method actually involves, who tends to do well on which, what people commonly misunderstand, and which questions are worth bringing to the next visit.
How does dialysis work? The job your kidneys were doing
Healthy kidneys filter roughly the body’s entire blood volume dozens of times a day, pulling out urea, excess potassium, acid and surplus water while holding on to proteins and cells. They also help regulate blood pressure and make hormones that keep bone and blood healthy. When kidney function falls to a small fraction of normal, waste and fluid build up, and dialysis steps in to do the filtering part of that job.
Every form of dialysis relies on the same physical principle: a semipermeable membrane, which is a thin barrier with pores small enough to let water and small waste molecules pass but too small for blood cells and large proteins. On one side sits the blood, on the other a specially prepared fluid called dialysate. Waste products drift from where they are concentrated (the blood) to where they are scarce (the dialysate), and extra water is pulled across as well.
Hemodialysis uses an artificial membrane inside a machine. Blood leaves the body through a needle or catheter, passes across the filter, and returns cleaned. Peritoneal dialysis uses a membrane you already own: the peritoneum, the smooth lining of the abdominal cavity, which is rich in tiny blood vessels. Dialysate is placed inside the abdomen, waste crosses from the blood vessels in the lining into the fluid, and the fluid is drained away.
Neither method replaces the hormone-making or fine-tuning work of a real kidney, which is why people on dialysis still need medicines for anemia, bone health and blood pressure, and why a kidney transplant remains a separate option the team will usually discuss alongside both types of dialysis.
What actually happens during hemodialysis
A hemodialysis session begins with access. For most long-term patients that means a fistula, which is a surgically created connection between an artery and a vein in the arm that enlarges the vein so it can take repeated needles and carry a high blood flow. Some people have a graft, a soft synthetic tube joining artery and vein, and some start with a catheter placed in a large vein in the neck or chest while a fistula matures.
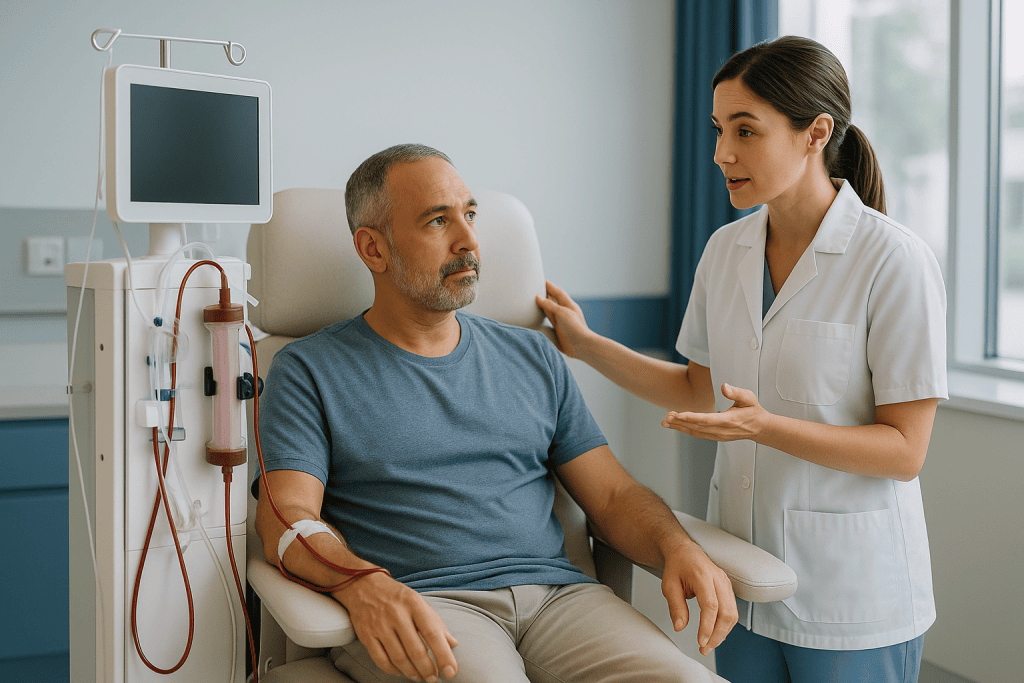
Two needles go into the access. One draws blood out to the machine at a steady rate; the other returns it. Inside the machine the blood runs through a dialyzer, a canister packed with thousands of hollow fibers made of semipermeable membrane, while dialysate flows around the outside of the fibers in the opposite direction. A pump controls the speed, sensors watch for air and pressure changes, and a small amount of blood thinner is often used in the circuit so it does not clot in the tubing.
A typical in-center schedule described by the NHS is three sessions a week, each lasting about four hours. People read, sleep, watch a screen or talk. Some feel washed out afterward, particularly if a large amount of fluid has been removed, and a drop in blood pressure or muscle cramps during the session are the most common reasons a nurse adjusts settings midway.
Between sessions, waste and fluid accumulate again, which is why hemodialysis patients usually have tighter fluid and dietary limits than peritoneal patients. The treatment is intense and intermittent: a few hours of very efficient cleaning, then two or three days of the body carrying the load until the next visit. Home and nocturnal variants spread that work across more frequent or longer sessions, which we return to later.
What actually happens during peritoneal dialysis
Peritoneal dialysis starts with a soft, flexible catheter, a thin tube placed by a surgeon through the abdominal wall so that its inner end rests in the lower part of the peritoneal cavity. A few inches of tubing stay outside the body, usually near the navel, capped when not in use. Mayo Clinic notes the catheter is generally placed about two weeks before treatment begins so the site can heal.
Each treatment cycle is called an exchange. First, a bag of warmed dialysate is connected and allowed to run into the abdomen by gravity. Then the fluid dwells there for several hours, during which waste and extra water cross from the blood vessels in the peritoneal lining into the fluid. Finally the used fluid is drained into an empty bag and discarded, and fresh fluid goes in. The dialysate contains sugar or a related compound that draws water out of the bloodstream by osmosis; stronger solutions pull more fluid.
There are two rhythms. Continuous ambulatory peritoneal dialysis, or CAPD, is done by hand during the day. The NHS describes roughly four exchanges daily, each taking around 30 to 40 minutes to drain and refill, with fluid dwelling in between while the person goes about their day. Automated peritoneal dialysis, or APD, uses a bedside machine called a cycler that performs the exchanges overnight, typically over eight to ten hours while the person sleeps, sometimes leaving a daytime dwell in place.
Because treatment happens every day, waste never builds up as far between sessions as it does with hemodialysis. Many people describe fewer peaks and troughs in how they feel. The trade is that the work is constant, the supplies are bulky, and every connection is a moment where germs could enter.
Peritoneal dialysis vs hemodialysis: the side-by-side comparison
The table below summarizes the practical differences most patients weigh. Figures are typical ranges from the sources listed at the end of this article; individual prescriptions vary widely and are set by the kidney team.

| Feature | In-center hemodialysis | Peritoneal dialysis |
|---|---|---|
| Where | Dialysis unit (home option exists) | Home, work or while traveling |
| Typical schedule | About 3 sessions a week, roughly 4 hours each | Daily: ~4 manual exchanges, or 8–10 hours overnight on a cycler |
| Access | Arm fistula or graft, or a chest/neck catheter | Soft abdominal catheter |
| Needles | Two per session | None after catheter placement |
| Who performs it | Nurses and technicians (or trained patient at home) | Patient or trained partner |
| Diet and fluid | Usually stricter limits | Often more flexible; sugar in fluid matters |
| Main infection risk | Access-site and bloodstream infection | Peritonitis (infection of the abdominal lining) |
| Home requirements | Minimal for in-center; plumbing and space for home HD | Clean area, storage for boxes of fluid |
| Post-treatment feeling | Fatigue common after sessions | Steadier day-to-day; abdominal fullness |
Notice what the table does not contain: a row saying which one works better. That omission is deliberate. The NHS advises that both types are considered equally effective for most people, and the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) frames the choice around lifestyle and medical suitability rather than potency. The rows that usually tip the decision are schedule, needles, independence and what a person’s body and home can accommodate.
Who is peritoneal dialysis best for — and who is usually asked to wait
Peritoneal dialysis tends to suit people who value control over their own schedule and are comfortable learning a careful routine. Someone who works full time, cares for young children, lives far from a dialysis unit or travels regularly often finds that daily exchanges at home fit better than three fixed appointments a week. Because it is gentler on the circulation, with no rapid fluid shifts, clinicians often consider it for people whose blood pressure drops easily or whose heart tolerates hemodialysis poorly.
There is also a physiological argument. Observational studies summarized by NIDDK and others suggest that peritoneal dialysis tends to preserve residual kidney function, meaning whatever filtering the person’s own kidneys still manage, for longer than hemodialysis does. That residual function helps with fluid balance and often lets people keep passing urine, which in turn loosens dietary limits.
Not everyone is a candidate. The peritoneum has to be intact and roomy enough to hold fluid. People with extensive abdominal scarring from previous surgery, large untreated hernias, active inflammatory bowel disease or a stoma are often steered away, because the membrane may not work well or the infection risk is judged too high. Severe obesity can make catheter placement and adequate clearance difficult. Someone who cannot see well, has limited hand dexterity or memory problems will need a trained partner at home; without one, the team may recommend hemodialysis instead.
Timing matters too. A person who arrives in the hospital with sudden, severe kidney failure and dangerously high potassium will usually be started on hemodialysis through a temporary catheter because it works within hours. Peritoneal dialysis can be discussed afterward, once the immediate crisis has passed and there is time for catheter placement and training.
Who tends to do well on hemodialysis
Hemodialysis is the more common choice worldwide, and for many people it is the right one rather than a fallback. Someone who prefers that professionals run the treatment, who lives alone without a partner able to help, or who simply does not want medical equipment and boxes of supplies in their living space often chooses the in-center route deliberately. The structure of three fixed appointments can be a strength: nurses check weight, blood pressure and bloodwork every visit, and problems are caught early.
Medically, hemodialysis clears waste far faster per hour than peritoneal dialysis, which matters when someone is very unwell, when potassium is dangerously high, or when large amounts of fluid must be removed quickly. It is also the method that keeps working when the peritoneum fails, whether from scarring after repeated peritonitis or because the membrane’s transport characteristics change over years of exposure to dialysate.
People with the abdominal conditions described in the previous section, those who have already had a failed peritoneal catheter, and those who need dialysis urgently are the groups most often started on hemodialysis. A functioning fistula is the goal for long-term treatment; NIDDK notes it usually takes two to three months to mature, so planning surgery well before dialysis is needed is one of the most useful things a person with advancing kidney disease can do.
Who is asked to wait? Anyone whose veins are too small or too damaged for a fistula may need vein mapping and a graft instead, and a person with a serious heart condition may have the session length and fluid removal adjusted cautiously at first. Hemodialysis is rarely refused outright, but its details are individualized, and the team may recommend the home or nocturnal versions for people who find standard sessions exhausting.
What is the main disadvantage of peritoneal dialysis?
If the question is asked bluntly, the honest single answer is peritonitis: infection of the peritoneal lining. Every connection and disconnection is a chance for bacteria from the skin or the environment to enter the abdomen, and the catheter itself provides a pathway. The classic signs are cloudy drained fluid, abdominal pain and sometimes fever. Most episodes respond to antibiotics, but repeated or severe peritonitis can scar the membrane, and a scarred membrane eventually stops filtering well enough. Loss of the peritoneum as a usable membrane is the most common reason people move from peritoneal dialysis to hemodialysis over time.
Other peritoneal dialysis disadvantages are less dramatic but affect daily life. The dialysate contains glucose, and some of that sugar is absorbed into the bloodstream during each dwell. Over months this can contribute to weight gain and higher triglycerides, and people with diabetes often need closer blood sugar monitoring. Fluid sitting in the abdomen raises pressure on the abdominal wall, which can worsen hernias, cause back discomfort, and occasionally leak around the catheter or into the chest.
There is also the simple burden of relentlessness. A treatment that happens every single day, with supplies delivered in bulk and a routine that cannot be skipped, asks something of a household that three appointments a week do not. Some people thrive on that ownership; others find, after a year or two, that the constancy wears them down. The team may call this treatment fatigue, and switching to hemodialysis for that reason alone is a legitimate choice rather than a failure.
Finally, effectiveness depends on the membrane. People whose peritoneum transports solutes very quickly may struggle to remove enough fluid on long dwells, and those with a large body size may not achieve adequate clearance. Regular tests of dialysis adequacy guide adjustments.
The real trade-offs of hemodialysis
Hemodialysis asks less of the household and more of the body and calendar. Three sessions a week of about four hours, plus travel and recovery, can consume a large share of the week for people who feel drained afterward, a symptom commonly called post-dialysis washout. Employment, school and caregiving often have to be rearranged around the unit’s schedule rather than the other way round.
Physiologically, the intermittent pattern is the main issue. Fluid and potassium climb between sessions and then fall quickly during treatment, and those swings stress the heart and blood vessels. Low blood pressure during dialysis, cramping and nausea are the most frequent in-session problems, and Mayo Clinic lists them among the common complications. The longer gap over the weekend, when many schedules skip two days rather than one, is a period of particular concern for fluid overload, which is why fluid limits are usually stricter than on peritoneal dialysis.
Access carries its own risks. Needles twice per session can be painful, though most people adapt and numbing techniques exist. Fistulas can narrow or clot; grafts are more prone to infection than fistulas; and catheters in the chest or neck carry the highest bloodstream infection risk of any access, which is why teams push hard to move people onto a fistula. Repeated hospital exposure also brings the general infection risks of any healthcare setting.
Dietary rules tend to be tighter, with potassium, phosphorus, sodium and fluid all limited more closely than for peritoneal patients. And residual kidney function often declines faster on hemodialysis, so urine output frequently dwindles over the first year or two, which then tightens the fluid allowance further. None of these trade-offs makes hemodialysis inferior; they simply describe a different shape of burden.
Home hemodialysis vs peritoneal dialysis: comparing the home dialysis options
Home is not the exclusive territory of peritoneal dialysis. Home hemodialysis, in which a trained patient and usually a partner run a compact dialysis machine at home, has grown as machines have become simpler. Comparing the two home routes is a distinct decision from the center-versus-home question, and people who want independence sometimes find the second option suits them better.
Home hemodialysis allows more frequent or longer sessions than a unit can offer, commonly five or six shorter treatments a week or long overnight sessions several nights a week. Spreading the same clearance across more time means gentler fluid removal, fewer blood pressure dips, and often more relaxed diet and fluid limits. NIDDK notes that people on frequent home hemodialysis often report feeling better and sleeping better than on the standard schedule, though this comes from observational and small trial evidence rather than large randomized studies.
The price is complexity. The person or partner must learn to insert needles, prime the machine, monitor pressures and respond to alarms. Homes usually need water treatment equipment and sometimes electrical or plumbing modifications. Training takes several weeks and a committed care partner is often required by programs.
Peritoneal dialysis, by contrast, needs no needles, no plumbing and a shorter training period, and the cycler is small enough to travel with. Its space demand is different: boxes of dialysate for a month can fill a closet. It is also the option more easily done alone.
So who leans which way? Someone with a healthy peritoneum who wants simplicity and solo independence often prefers peritoneal dialysis. Someone whose peritoneum is unsuitable, who has already used it for years, or who wants the most intensive clearance at home may be better served by home hemodialysis. Both keep treatment where life happens.
Peritoneal dialysis vs hemodialysis: does one help you live longer?
This is the question most people carry into the appointment and hesitate to ask. The evidence deserves a careful answer rather than a reassuring one.
No large randomized trial has compared survival between the two methods; the few attempts failed because too few people were willing to be assigned at random to a treatment that reshapes daily life. What exists is registry data covering hundreds of thousands of patients across many countries. Those comparisons, summarized by the NIDDK and in reviews indexed on PubMed, have generally found that long-term survival is broadly similar between the two modalities once age, diabetes and other illnesses are accounted for.
Within that overall picture, patterns recur. Peritoneal dialysis often appears to carry an advantage in the first one to two years, particularly for younger people and those without diabetes, possibly because it preserves residual kidney function and avoids the strain of rapid fluid shifts. Later, as the membrane ages, the comparison tends to even out or tilt toward hemodialysis, especially among older patients and those with diabetes. These are population averages from observational data, susceptible to the bias that healthier people are more often offered peritoneal dialysis in the first place.
What the data do support is this: the method itself is rarely the biggest determinant of how long someone lives. Age, heart disease, diabetes, nutrition, how well blood pressure and fluid are controlled, and whether a transplant becomes possible all matter more. Attending sessions consistently, following the fluid plan and keeping access sites healthy influence outcomes regardless of modality.
A person choosing between the two should feel free to weigh quality of life heavily, because survival evidence does not clearly penalize either choice. And nothing about the decision is permanent; switching in either direction is common, and many people use both methods across a lifetime of kidney care.
What the first weeks look like: access, training and settling in
The timeline differs sharply depending on the route, and knowing it in advance removes a lot of dread.
For peritoneal dialysis, the catheter is placed under local or general anesthesia, often as a day procedure. Mayo Clinic describes a healing window of about two weeks before regular exchanges begin, during which the exit site is kept dry and dressed. Training then takes place at the unit, typically over one to two weeks, covering hand hygiene, connecting and disconnecting, recognizing cloudy fluid, and troubleshooting slow drains. Most people do their first exchanges under supervision, then at home with phone support. The first few weeks often bring a sense of abdominal fullness and some sleep disruption as the body adjusts to fluid volume; the prescription is fine-tuned over the first one to three months as adequacy tests come back.
For hemodialysis, the ideal path starts months earlier. Fistula surgery is a short operation, but NIDDK notes the vein needs two to three months to enlarge and toughen enough for needles. During that time the team checks for a palpable buzz, called a thrill, that signals good flow. If dialysis is needed before the fistula is ready, a temporary catheter bridges the gap.
The first hemodialysis sessions are usually shorter and gentler while the body adapts, then extended toward the full prescription. Fatigue after sessions is common early and often eases as the schedule settles. Bloodwork is checked frequently during this period to adjust fluid removal targets, anemia treatment and mineral balance.
Either way, the team schedules a follow-up within the first month to review how the plan is working. People frequently report that the third month, not the first week, is when treatment finally feels like a routine rather than an event.
Daily life on each method: diet, urine, work, travel and sleep
Do you still urinate on peritoneal dialysis? Frequently, yes, at least for a while. Dialysis begins when kidneys are failing, not when they have stopped entirely, and most people still produce some urine at the start. Because peritoneal dialysis tends to preserve that residual function longer, many people continue to pass urine for years, though the amount usually declines over time. On hemodialysis, urine output typically falls faster, and some people eventually produce very little. The team measures residual output because it directly affects how much fluid a person can drink safely.
Diet follows from this. Peritoneal patients usually have more freedom with fluids and potassium, but they absorb sugar from the dialysate and lose protein into the drained fluid, so dietitians often emphasize higher protein intake and attention to calories and blood glucose. Hemodialysis patients tend to have firmer caps on fluid, potassium, phosphorus and salt, with the tightest attention paid to the longer gap between weekend sessions.
Work and travel favor the home methods. A cycler fits in a suitcase, and suppliers can often deliver dialysate to a destination with advance notice. Hemodialysis patients can travel too, by booking sessions at a unit near their destination well ahead, though this requires more coordination. Sleep is disturbed by different things: cycler alarms and drain sensations for peritoneal patients, post-session exhaustion or restless legs for hemodialysis patients.
Body image and intimacy come up often and deserve frank discussion with the team. A peritoneal catheter is visible and must be secured during sex and bathing; swimming is possible in clean pools or the sea with a waterproof dressing, but lakes and hot tubs are generally discouraged because of infection risk. A fistula leaves a raised vein on the arm that some people cover and others do not think about. Neither method prevents exercise, and both teams actively encourage it.
What people often get wrong about choosing dialysis
“Peritoneal dialysis is the weaker treatment.” It clears waste more slowly per hour, but it runs every day, so total weekly clearance is comparable for most people. The NHS advises both are considered equally effective for the majority of patients. Slower is not weaker when it is continuous.
“Once you pick one, you are stuck with it.” Switching is routine. People move to hemodialysis when the peritoneal membrane wears out or after repeated infections, and they move to peritoneal dialysis when hemodialysis access fails or when they want more independence. Many use both over a lifetime.
“Home dialysis is only for young, tech-savvy people.” Training programs are designed for people of all ages, and assisted peritoneal dialysis, where a nurse or family member helps with connections, exists in many regions. Age alone is not a barrier; what matters is dexterity, vision, cognition and support.
“Dialysis means you stop passing urine.” Most people still pass some urine when they start, and peritoneal patients in particular often keep doing so for years. The amount is monitored, not assumed.
“If I choose hemodialysis I do not have to think about my access.” The fistula needs daily checks for the thrill, protection from tight sleeves and blood pressure cuffs, and prompt reporting of any change. Access care is a shared responsibility on every method.
“The choice is really about survival.” The observational evidence does not show a clear long-term survival winner for most groups, which is exactly why guidelines encourage weighing lifestyle so heavily. Choosing the method that fits your days is a medically sound way to decide.
“A transplant is off the table once you start dialysis.” Dialysis and transplant listing run in parallel. Starting dialysis does not remove transplant as an option, and the team should raise it regardless of which method you choose.
Questions to ask your care team before you decide
A good decision meeting tends to feel like a conversation about your life rather than a briefing about machines. The questions below are the ones patients later say they wished they had asked, grouped so you can pick what matters most.
- Given my anatomy, previous surgeries and other conditions, are both methods genuinely open to me, or is one being recommended because the other carries specific risks for me?
- How much urine am I still producing, and how would each method be expected to affect that over the next year?
- What would my fluid and dietary limits look like on each option?
- If I chose peritoneal dialysis, would I be a candidate for the overnight cycler, and how much storage space would supplies need in my home?
- If I chose hemodialysis, when should fistula surgery happen, and is home or nocturnal hemodialysis available through this program?
- What training would I or my partner need, how long does it take, and what happens if I live alone?
- How would we know the treatment is working well enough, and how often would that be checked?
- What are the warning signs I should never wait on, and who do I call at night or on weekends?
- Am I a candidate for transplant evaluation, and does my dialysis choice change that in any way?
- If I try one method and it does not suit me, how does switching work?
- How do work, travel and my caregiving responsibilities fit each schedule realistically?
- Is conservative kidney management, meaning symptom-focused care without dialysis, something we should discuss as well?
Bring someone with you, ask for the answers in writing if that helps, and expect to return for a second conversation. Kidney teams generally welcome the person who asks twice; the decision is theirs to guide and yours to own.
When to call your doctor: red flags on either type of dialysis
Some problems need same-day contact with the dialysis unit or emergency care rather than waiting for the next scheduled visit. Every unit gives patients a number to call around the clock; keep it where you can find it quickly.
On peritoneal dialysis, call promptly if drained fluid turns cloudy, which is the earliest sign of peritonitis, or if there is new abdominal pain, fever, or redness, swelling, warmth or pus at the catheter exit site. Fluid that will not drain, sudden difficulty breathing, or a noticeable leak of fluid around the catheter also warrant a call the same day.
On hemodialysis, seek help if bleeding from the access site does not stop with firm pressure after ten to fifteen minutes, if the thrill in the fistula or graft disappears or the arm becomes cold, pale or painful, or if there is redness, swelling or discharge at the access or catheter site. A fever after a session, especially with a chest or neck catheter, should be treated as a possible bloodstream infection until proven otherwise.
On either method, call emergency services for chest pain, severe shortness of breath, sudden weakness or confusion, fainting, or a very irregular or slow heartbeat, which can signal dangerously high potassium or fluid on the lungs. Rapid weight gain of several pounds over a day or two with swelling and breathlessness should be reported the same day, as should vomiting or diarrhea that prevents keeping fluids and medicines down.
These lists are not for self-diagnosis; they are prompts to pick up the phone. The team decides what each sign means for you and whether treatment needs adjusting. Calling early about something that turns out to be minor is far better than waiting on something that is not.
Frequently asked questions
Do you live longer on hemodialysis or peritoneal dialysis?
Large observational comparisons have generally found broadly similar long-term survival between the two methods once age, diabetes and other conditions are accounted for. Peritoneal dialysis often appears to have an early advantage, especially in younger people without diabetes, while the comparison tends to even out over time. No large randomized trial exists, and factors such as heart health, diabetes and transplant access matter more than the modality itself.
What is the main disadvantage of peritoneal dialysis?
Peritonitis, an infection of the abdominal lining, is the most serious drawback because every connection is a potential entry point for bacteria. Repeated episodes can scar the peritoneum and end its usefulness as a filter. Other peritoneal dialysis disadvantages include sugar absorption from the fluid, which can affect weight and blood glucose, abdominal fullness or hernias, and the daily, unrelenting nature of the routine.
Who is peritoneal dialysis best for?
It tends to suit people who want to manage treatment at home on their own schedule, who work, study, care for others or travel, and who have a healthy, unscarred abdomen. Clinicians also consider it for people whose blood pressure drops easily on hemodialysis and those who still have meaningful residual kidney function. Good vision, hand dexterity and a clean storage space, or a trained partner, are practical requirements.
Do you still urinate with peritoneal dialysis?
Often, yes. Most people still produce some urine when dialysis starts, and peritoneal dialysis tends to preserve that residual kidney function longer than hemodialysis does, so many patients keep passing urine for years. Output usually declines gradually over time. The team measures it regularly because the amount of urine you make directly affects how much fluid you can safely drink.
What are the different types of dialysis?
There are two main types: hemodialysis, which filters blood through a machine and can be done in a center or at home, and peritoneal dialysis, which uses the lining of the abdomen as the filter and is done at home. Peritoneal dialysis comes in a manual daytime form (CAPD) and an automated overnight form (APD). Home and nocturnal hemodialysis are variants of the first type with longer or more frequent sessions.
How does dialysis work in simple terms?
Dialysis uses a thin membrane with tiny pores to let waste and extra water move from the blood into a special fluid called dialysate, while blood cells and proteins stay behind. Hemodialysis uses an artificial membrane inside a machine; peritoneal dialysis uses the natural lining of the abdomen. Neither replaces the hormone functions of real kidneys, so medicines for anemia, bone and blood pressure are usually still needed.
Can I switch from peritoneal dialysis to hemodialysis later, or the other way round?
Yes, switching in either direction is common and planned for. People often move to hemodialysis if the peritoneal membrane stops working well or after repeated infections, and move to peritoneal dialysis if hemodialysis access fails or they want more independence. Because access takes time to establish, the team usually starts preparing the alternative before the current method reaches its limit.
Is home hemodialysis better than peritoneal dialysis?
Neither is better across the board. Home hemodialysis allows more frequent or longer sessions, which can mean gentler fluid removal and looser diet limits, but requires needle skills, water treatment equipment and usually a care partner. Peritoneal dialysis needs no needles or plumbing and can be done alone, but depends on a healthy peritoneum and daily commitment. The choice depends on anatomy, household support and preference.
How long does it take to start each type of dialysis?
A peritoneal catheter generally needs about two weeks to heal before regular exchanges begin, followed by one to two weeks of training. A hemodialysis fistula typically takes two to three months to mature enough for needles, so surgery is ideally done months ahead. If dialysis is needed urgently, hemodialysis can start within hours through a temporary catheter while permanent access is arranged.
Can you travel or keep working on dialysis?
Many people do both. Peritoneal dialysis is the most portable, since the cycler fits in luggage and suppliers can often deliver fluid to a destination with advance notice. Hemodialysis patients can arrange sessions at a unit near where they are going, which takes more planning. Flexible work hours or overnight treatment help many people stay employed. Discuss plans with the team early so prescriptions and supplies can be arranged.
References
- NHS – Dialysis: Pros and cons
- NHS – Dialysis: What happens
- NIH NIDDK – Peritoneal Dialysis
- NIH NIDDK – Hemodialysis
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog
Why Do Bladder Stones Form? Retained Urine, Enlarged Prostate and What Treatment Fixes
Bladder stones usually form when the bladder does not empty fully, so leftover urine sits, concentrates and lets minerals crystallize. In adults the most…

What Happens in Testicular Torsion Surgery: Detorsion, Orchiopexy and Fixing Both Sides
Testicular torsion surgery is an emergency operation to untwist a spermatic cord that has cut off blood flow to a testicle. Under general anesthesia,…
How CT, Ultrasound and Urine Tests Shape a Kidney Stone Treatment Plan
A non-contrast CT scan is the most accurate single test for finding kidney stones and measuring their size and position, but it is not…

Vascular, Hormonal or Nerve-Related: How the Cause of Erectile Dysfunction Guides Treatment
The causes of erectile dysfunction fall into three broad groups: vascular (narrowed or leaky penile blood vessels), hormonal (low testosterone, thyroid or prolactin problems)…

Vasectomy Recovery Timeline: Rest, Cold Packs and When Everyday Activity Usually Resumes
Most people rest for the first 24 hours after a vasectomy, use wrapped cold packs and snug supportive underwear for about two days, and…