

Petechial Rash and Purpura: What the Tiny Red or Purple Spots Mean and When Care Is Urgent
Key Takeaways
- Petechiae are pinpoint bleeds under the skin that do not fade under a pressed glass, which is what separates them from most ordinary rashes.
- A non-fading rash with fever, drowsiness, stiff neck or cold extremities is an emergency, and in meningococcal disease the rash is often the last sign, not the first.
- Coughing, vomiting, straining and tight straps are the commonest causes and leave a single crop above the pressure point in a person who feels well.
- The typical platelet reference interval is 150,000 to 450,000 per microliter, and a complete blood count with a blood film resolves most uncertainty within a day.
- Raised purpura on the legs and buttocks with joint or stomach pain in a child points to IgA vasculitis, which usually resolves within weeks but needs urine checks for the kidneys.
- New petechiae within one to two weeks of starting a medicine are a known pattern of drug-induced low platelets, and the prescriber, not the patient, should decide what happens next.
A petechial rash is a scatter of pinpoint red or purple dots caused by bleeding from tiny vessels under the skin; the spots do not fade when pressed. Most cases follow pressure, straining, a viral illness or a minor platelet dip and settle on their own. A petechial rash with fever, drowsiness, severe headache, a stiff neck or rapidly spreading spots is an emergency that needs same-day care.
It usually starts with a second look. A parent lifting a pajama top sees a sprinkle of dots across a toddler’s chest that look like someone flicked a red pen. A runner notices a dusting on her shins after a long race. A man in his sixties, three weeks into a new tablet, finds a spray of purple freckles above his socks. The instinct is the same: press one, hope it fades, and search the phrase.
A petechial rash is a fairly blunt signal. Something has let a small amount of blood leak from the smallest vessels, the capillaries, into the skin. The question is what. The answer ranges from a hard coughing fit to a serious infection, and the gap between those two cannot be closed by looking at a photo online.
What can be done is this: learn which patterns are reassuring, which deserve a blood test within days, and which mean you stop reading and get care now.
What a petechial rash usually means, and the signs that make it an emergency
Petechiae are tiny flat spots, usually under a few millimeters across, created when capillaries leak blood into the skin. Because the blood sits in the tissue rather than inside a vessel, pressing the spot does not push the color away. That non-fading quality is the defining feature, and it is why clinicians take a petechial rash more seriously than ordinary redness, as MedlinePlus explains in its page on bleeding into the skin.
Most petechial rashes are not dangerous. The commonest stories are mechanical: a bout of vomiting, a violent cough, heavy lifting, a tight blood-pressure cuff. Next come viral infections, which can irritate vessel walls or briefly lower platelet counts. Less often, the rash points to a platelet problem, a clotting disorder, a vessel inflammation or, rarely, a bone marrow disease.
The emergency version is different and recognizable. Treat a petechial rash as urgent, and seek same-day care, if it comes with any of the following:
- fever, especially in a child or anyone who seems unusually drowsy or hard to wake
- severe headache, stiff neck, dislike of bright light, or confusion
- spots that are spreading or enlarging over hours
- bleeding from the gums or nose that will not stop, or blood in urine or stool
- cold hands and feet, pale or mottled skin, fast breathing
The NHS meningitis guidance is explicit that a non-fading rash plus fever should not be watched at home overnight. In that situation the rash is the last sign to appear, not the first, so the other symptoms matter just as much.
Purpura vs petechiae rash: how size changes the picture
Petechiae and purpura are the same event at different scales. MedlinePlus describes petechiae as pinpoint dots and purpura as larger flat patches where more blood has collected under the skin. Dermatology texts generally draw the line at a few millimeters: dots below that are petechiae, patches above it are purpura, and anything bigger than a thumbnail is an ecchymosis, the formal word for a bruise.

Size is not just vocabulary. It shifts the list of likely causes. Scattered pinpoint petechiae often reflect a platelet problem or a pressure surge, because platelets are the first plug in a tiny leak. Larger purpura, particularly when the patches are raised or feel slightly firm, suggests the vessel wall itself is inflamed, a process called vasculitis. Purpura that is flat, irregular and widespread in a sick, feverish person raises the possibility of disseminated intravascular coagulation, a condition in which the clotting system is activated throughout the body during a severe infection.
Texture helps too. Flat, smooth spots are typical of low platelets. Palpable purpura, meaning spots you can feel as tiny bumps, points toward small-vessel vasculitis such as IgA vasculitis, the condition the NHS still lists under its older name, Henoch-Schönlein purpura.
Color tells time. Fresh petechiae are bright red; over a few days they darken to purple, then brown, then fade as the leaked blood is broken down and cleared. A single crop that evolves together usually had a single cause on a single day.
The glass test: how to check whether spots blanch
The glass test is one of the few home checks that doctors actively recommend. Press the side of a clear drinking glass firmly against the rash and look through it. Ordinary rashes, including most viral rashes, heat rash and hives, turn pale under pressure because the redness is blood inside dilated vessels, and pressure squeezes it out. Petechiae and purpura stay visible because the blood has already left the vessel and sits in the tissue.
The NHS recommends this test in its meningitis guidance, with two caveats that matter. First, a rash that does blanch early can stop blanching later, so repeat the test if someone is unwell. Second, on darker skin tones, spots can be harder to see; check paler areas such as the palms, soles, inside the eyelids and the roof of the mouth, where petechiae show more readily.
Good light helps, and a photo with a timestamp helps more, because a clinician’s first question is whether the rash has changed. A scatter that is identical twelve hours later behaves differently from one that has doubled.
The glass test tells you only that bleeding into the skin has occurred. It cannot tell you why. A non-fading rash in a child who is otherwise cheerful, eating and alert after a bout of coughing is a different situation from the same rash in a child with fever and limpness. The test narrows the question; the overall condition of the person answers it.
Common, usually harmless causes of petechiae
Capillaries are delicate, and a sudden spike in pressure inside them is enough to cause leakage. Cleveland Clinic lists the everyday triggers: prolonged coughing, repeated vomiting, straining during childbirth or a hard bowel movement, intense crying in infants, and heavy weightlifting. The pattern is distinctive. The dots cluster above the point of pressure, typically on the face, neck, upper chest and around the eyes, and they appear in a single crop that does not spread once the trigger stops.

Local pressure does the same thing on a smaller scale. A tourniquet left on for a blood draw, a tight waistband, the strap of a heavy bag or a blood-pressure cuff can leave a neat band of petechiae. These fade over several days and need no treatment.
Sunburn and aging skin thin the supporting tissue around capillaries, so minor knocks on the forearms and shins produce small purple patches, sometimes called actinic or senile purpura. MedlinePlus notes this is common in older adults and usually harmless, though it should still be mentioned at a routine visit if it is new or frequent.
Vitamin C deficiency, which is uncommon but still seen in people with very restricted diets, weakens the collagen that supports vessel walls and classically causes petechiae around hair follicles. It is one of the few dietary causes that a clinician will specifically ask about.
What these causes share is a plausible explanation, a stable crop and a person who otherwise feels well. When any of those three is missing, the list of possibilities gets longer.
Causes of petechiae on legs: why the shins are a special case
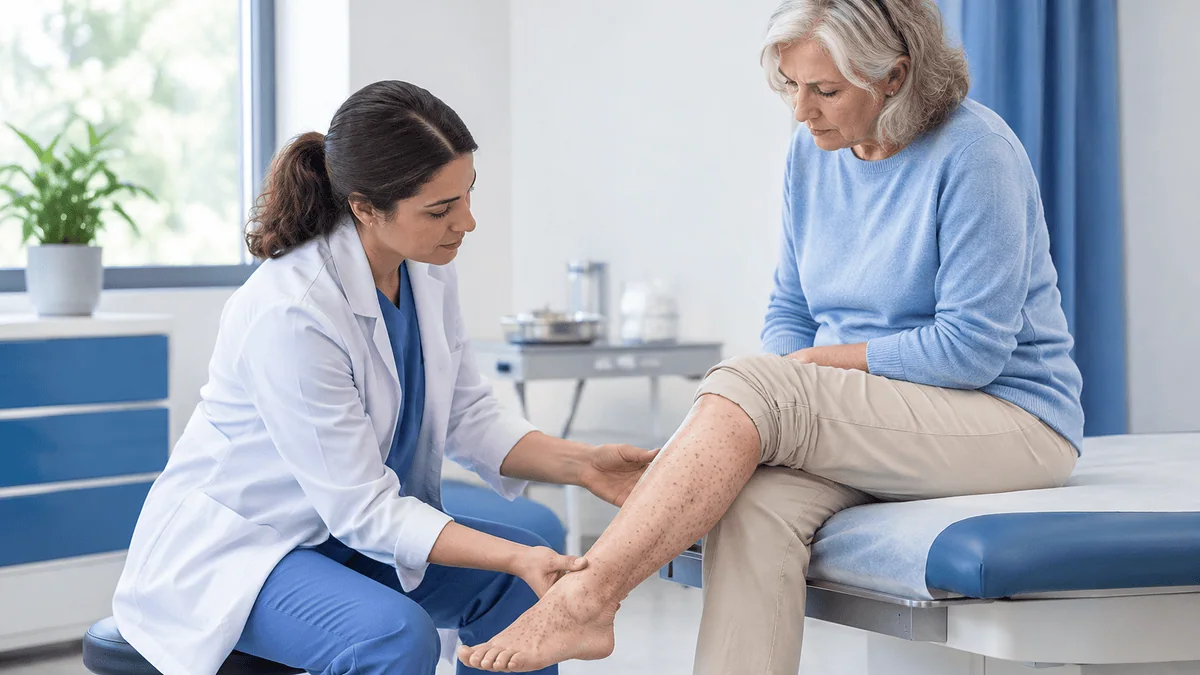
Searches for causes of petechiae on legs are common for a simple reason: gravity. Blood pressure in the capillaries of the lower legs is higher than anywhere else when a person is standing, so the legs are where marginal weaknesses in vessels or platelets show first. A crop of petechiae confined to the lower legs after a long day on your feet, a long flight or a long run is a familiar, benign finding, sometimes called exercise-induced purpura.
Chronic venous insufficiency, where the leg veins return blood sluggishly, causes a slow leak of red cells into the skin over months. The result is a rust-brown stippling above the ankles rather than fresh red dots, and it is usually paired with swelling and varicose veins.
Leg-dominant petechiae and purpura that are raised, symmetrical and accompanied by joint pain or abdominal pain shift attention to small-vessel vasculitis. The NHS describes IgA vasculitis as a rash of purple spots mainly on the legs and buttocks, often with painful joints, stomach pain and sometimes blood in the urine. It mostly affects children under ten and typically follows a cold or throat infection.
Medicines are another leg-first cause. A hypersensitivity vasculitis triggered by a new antibiotic, anti-inflammatory or diuretic tends to appear on the lower legs within days to a few weeks of starting the drug. Clinicians look at the timeline rather than the drug name, and any decision to stop a medicine belongs to the prescriber.
Infections that cause a petechial rash, from viral illness to meningococcal disease
Many common viruses can produce a few petechiae, particularly in children. Enteroviruses, the virus that causes glandular fever, and some respiratory viruses either irritate the lining of capillaries directly or temporarily reduce platelet numbers while the immune system is busy. The child is usually mildly unwell, the spots are few, and they resolve as the illness does.
Some bacterial infections are a different matter. Meningococcal disease, caused by the bacterium Neisseria meningitidis, can seed the bloodstream and damage vessel walls so fast that a rash of petechiae progresses to large purple patches within hours. The CDC notes that it can be fatal within a day of symptoms beginning, which is why fever plus a non-fading rash is treated as an emergency regardless of how well the person looked that morning. A dark purple, bruise-like rash in a very ill person is sometimes called purpura fulminans and is a sign the clotting system has been overwhelmed.
Rocky Mountain spotted fever, spread by ticks, classically produces a rash that begins on the wrists and ankles, spreads toward the trunk and can become petechial after a few days of fever; the CDC advises that treatment should start on suspicion rather than waiting for the rash. Infective endocarditis, an infection of the heart valves, can throw tiny clots into capillaries and produce petechiae on the conjunctivae, the palate and under the nails, usually in someone with weeks of fever and fatigue.
Infections are not a judgment on the person who has them. They are events that need recognizing early, and a non-fading rash in a feverish person is one of the clearest prompts medicine has.
Low platelets, medicines and the bone marrow
Platelets are the cell fragments that plug small leaks. The National Heart, Lung, and Blood Institute gives the typical reference interval as 150,000 to 450,000 platelets per microliter of blood; ranges differ slightly between laboratories, and the clinician who ordered the count interprets it alongside the person. Petechiae from low platelets tend to appear when the count drops well below the lower limit, and spontaneous bleeding becomes a real concern at much lower levels.
Immune thrombocytopenia, or ITP, is the classic cause. The immune system makes antibodies that tag platelets for destruction in the spleen. MedlinePlus describes a childhood form that typically follows a viral infection and usually resolves on its own within six months, and an adult form that is more often long-term. Bleeding gums, nosebleeds, heavy periods and easy bruising often accompany the rash. The 2019 American Society of Hematology guideline on ITP, which clinicians use for decisions, emphasizes that treatment depends on bleeding and count together, not the count alone.
Medicines can lower platelets by triggering antibodies or suppressing the marrow. Heparin, some antibiotics, anti-seizure drugs, quinine and many chemotherapy agents are on the list. The effect usually appears within one to two weeks of starting the drug, which is why the question “anything new in the last month?” comes early in the consultation.
Leukemia and other bone marrow disorders are an uncommon cause, but they are the reason a clinician will not simply reassure without a blood count. The marrow crowded with abnormal cells stops making platelets, and petechiae may appear alongside fatigue, pallor, frequent infections, night sweats and bone pain. A complete blood count with a film examined under the microscope usually separates this possibility from the far more common ones within a day.
What autoimmune disease can cause petechiae?
Autoimmune conditions cause petechiae by two routes: attacking platelets or inflaming vessels. ITP, discussed above, is the purest example of the first. Systemic lupus erythematosus, an autoimmune disease that can affect skin, joints, kidneys and blood, does both. Lupus can lower platelets through antibodies and can inflame small vessels, producing petechiae and purpura alongside joint pain, a facial rash, mouth ulcers and fatigue.
IgA vasculitis is the most frequent vasculitis in children and the one most likely to present with purpura on the legs. The NHS notes that most children recover fully within a few weeks, with kidney involvement the main reason for follow-up urine checks over subsequent months. In adults the same condition is rarer and more often affects the kidneys.
Antiphospholipid syndrome, in which antibodies make blood clot too readily, paradoxically produces a lace-like purple skin pattern and sometimes low platelets, usually in someone with a history of clots or pregnancy complications. Rheumatoid arthritis and Sjögren’s syndrome can cause a small-vessel vasculitis that shows up as palpable purpura on the shins.
Thrombotic thrombocytopenic purpura is rare but serious. An enzyme that trims a clotting protein is blocked by antibodies, tiny clots form throughout the body, platelets are consumed, and petechiae appear with fever, confusion and kidney strain. It is treated as an emergency, and its rarity is exactly why clinicians order a blood film rather than guess.
None of these diagnoses is made from the rash alone. Each comes with a cluster of other features, and the blood count, urine test and specific antibody tests do the sorting.
What could be mistaken for petechiae?
Several harmless skin findings are regularly photographed and mislabeled as a petechial rash. The glass test settles most of them, and a few have giveaways of their own.
Cherry angiomas are small, bright red, slightly raised bumps made of clustered capillaries. They are extremely common in adults over 30, persist for years rather than fading, and often blanch partially under firm pressure. Petechiae are flat, arrive in crops and disappear within days.
Flea or bedbug bites are tiny red bumps, often in lines or clusters of three, intensely itchy, and they blanch. Petechiae do not itch. Heat rash and the fine red stippling of keratosis pilaris on the upper arms are follicular, feel rough, and fade under glass.
Spider angiomas have a central red dot with fine radiating lines and empty when pressed, then refill from the center. Pinpoint red freckles from sun damage are flat but have been present for years and never change color.
Viral rashes such as those of measles, rubella or roseola blanch early in their course, though a few true petechiae can appear in severe measles. Hives are raised, migrate within hours and blanch completely.
Finally, some medicines and foods stain skin without bleeding; a brownish tint after certain antibiotics or in chronic venous insufficiency is pigment, not fresh blood, and lacks the red-to-purple-to-brown evolution of a true petechial rash.
How a clinician sorts out a petechial rash: a summary table and the tests involved
The consultation follows a predictable path: how the person looks, how the rash is distributed, what else is happening in the body, and a small set of blood tests. The table condenses what usually points where.
| Cause | Typical features | Usual next step |
|---|---|---|
| Pressure or straining | Single crop on face, neck or chest after coughing, vomiting, lifting; person well | Reassurance; routine check if recurrent |
| Viral infection | Few scattered spots, mild illness, resolves with the virus | Blood count if persistent or spreading |
| Low platelets (ITP, medicines) | Widespread flat petechiae, bruising, gum or nose bleeding, recent new drug | Same-week blood count and film; urgent if active bleeding |
| Small-vessel vasculitis | Raised purpura on legs and buttocks, joint or abdominal pain | Blood count, kidney function, urine test; referral |
| Meningococcal or severe sepsis | Fever, drowsiness, spreading or bruise-like rash, cold extremities | Emergency department now |
| Bone marrow disorder | Petechiae with pallor, fatigue, infections, night sweats | Urgent blood count; hematology referral |
The first test is a complete blood count, which gives the platelet number along with red and white cells. A peripheral blood film, in which a technician or hematologist examines cells under the microscope, confirms the count is real rather than a clumping artefact and looks for abnormal cells. Clotting studies check the proteins that work alongside platelets. A urine dipstick looks for blood or protein that would suggest kidney involvement in vasculitis. Kidney and liver function tests follow if the picture is unclear. In a feverish patient, blood cultures are drawn before antibiotics. A skin biopsy of a purpuric spot is reserved for suspected vasculitis, where it can show inflamed vessel walls and the antibody type involved.
Petechiae in children and during pregnancy
Children get petechiae more often than adults, and the overwhelming majority are benign. A crop above the neck after crying, coughing or vomiting in an otherwise bright child is a familiar sight. A few spots during a viral cold are also common. The rule most pediatric guidance uses is simple: petechiae below the neck, petechiae in a child who is feverish, or petechiae in a child who is unusually sleepy, floppy, pale or irritable need assessment the same day. The NHS stresses that a child with meningitis or sepsis may have no rash at all until late, so fever with lethargy or a high-pitched cry matters on its own.
Childhood ITP typically appears a week or two after a viral illness, with sudden widespread petechiae and bruising in a child who feels well. MedlinePlus notes that most children recover within six months, many without medicine; decisions about treatment rest on bleeding, not just the count, and belong to the pediatric team.
In pregnancy, platelet counts drift downward in a mild, harmless way for many people, a pattern called gestational thrombocytopenia that rarely causes petechiae. New petechiae in pregnancy, particularly with high blood pressure, headache, visual disturbance or pain under the right ribs, require urgent review because they can signal pre-eclampsia or HELLP syndrome, in which platelets are consumed. Petechiae with heavy bleeding after delivery also need immediate attention. Any medicine questions in pregnancy go to the obstetric team.
What people often get wrong about a petechial rash
The most dangerous mistake is waiting for the rash. Meningococcal disease is defined in the public mind by the non-fading spots, yet the NHS guidance makes the point that the rash is a late sign and does not appear in everyone. A feverish, drowsy, cold-limbed child with no rash is more urgent than a cheerful one with a sprinkle of dots.
The second mistake runs the other way: assuming every petechial rash means leukemia. Bone marrow disorders are on the list and are the reason for a blood count, but they are rare compared with coughing, viruses and ITP. A count that comes back normal removes that worry in a single result.
People also tend to blame the wrong thing on the legs. Rust-brown stippling above the ankles in someone with varicose veins is years of slow leakage from venous pressure, not a new bleeding disorder.
A fourth misunderstanding concerns aspirin and anti-inflammatory painkillers. These reduce platelet stickiness and can make bruising and petechiae more likely, which is useful information for the clinician, but stopping a prescribed antiplatelet drug on your own is not a safe response. The person who prescribed it balances bleeding against clotting risk and needs to be part of that call.
Finally, photos are not diagnostic. Image search returns the most dramatic cases; the blanching test, the distribution and a blood count are what separate the harmless from the serious.
When to see a doctor about a petechial rash, and what is reasonable at home
Go to an emergency department, or call emergency services, if a petechial or purpuric rash appears with fever, drowsiness, confusion, severe headache, a stiff neck, difficulty breathing, cold or mottled hands and feet, or if the spots are spreading within hours. Do the same for petechiae with bleeding that will not stop, blood in urine or stool, or a sudden severe headache, which can indicate bleeding inside the body when platelets are very low.
See a doctor within a day or two for a petechial rash with no obvious trigger, a rash that is widespread or below the neck in a child, new bruising without injury, gum or nose bleeding, unusually heavy periods, a rash that began within weeks of starting a new medicine, or raised purpura on the legs with joint or abdominal pain. Book a routine appointment for recurrent small crops after straining, or for new easy bruising in an older adult.
At home, sensible measures are limited and simple. Note the time the spots appeared and take a dated photograph. Repeat the glass test if the person feels unwell. Avoid aspirin and anti-inflammatory painkillers for new aches unless a clinician has advised them, since they can increase bleeding; acetaminophen is the usual alternative mentioned in mainstream guidance, in standard labeled use. Keep the legs elevated if the crop is exercise-related, and protect thin, aging skin on the forearms from knocks. Nothing applied to the skin speeds the clearing of petechiae; the body reabsorbs the blood over one to two weeks on its own.
The spots themselves rarely need treatment. What needs treatment, when anything does, is the reason they appeared, and that is a conversation for the clinician who can see the person and the blood count together.
Frequently asked questions
What is the cause of a petechial rash?
A petechial rash is caused by blood leaking from capillaries into the skin. The common triggers are a sudden rise in pressure from coughing, vomiting or straining, viral infections, and a temporary drop in platelets. Less common causes include immune thrombocytopenia, medicines that lower platelets, small-vessel vasculitis, serious bacterial infections such as meningococcal disease, and, rarely, bone marrow disorders. The distribution, the person’s general condition and a blood count tell these apart.
When should you worry about petechiae?
Worry, and seek same-day care, when petechiae come with fever, drowsiness, severe headache, a stiff neck, confusion, cold or mottled limbs, or when the spots spread within hours. Bleeding from gums or nose that will not stop, blood in urine or stool, and widespread spots below the neck in a child also need prompt assessment. Petechiae in a well person with an obvious trigger are usually not a concern.
What is the difference between a purpura and a petechiae rash?
They are the same process at different sizes. Petechiae are pinpoint dots under a few millimeters; purpura are larger flat or slightly raised patches, and a bruise is larger still. Size changes the likely cause: scattered pinpoint spots often reflect low platelets or a pressure surge, while raised, larger purpura on the legs suggests inflamed vessel walls. Both fail to fade when pressed under a glass.
What autoimmune disease can cause petechiae?
Immune thrombocytopenia, in which antibodies destroy platelets, is the most direct autoimmune cause. Lupus can lower platelets and inflame small vessels at the same time. IgA vasculitis, the leading cause of purpura in children, inflames the small vessels of the legs, gut and kidneys. Antiphospholipid syndrome, rheumatoid arthritis and Sjögren’s syndrome can also produce purpura. Each comes with other features and specific blood tests that confirm it.
What could be mistaken for petechiae?
Cherry angiomas, flea or bedbug bites, heat rash, keratosis pilaris and spider angiomas are the usual look-alikes. The glass test separates them: these fade or empty under pressure, whereas true petechiae stay visible. Cherry angiomas persist for years and are slightly raised, bites itch and cluster, and viral rashes such as measles blanch early. Petechiae are flat, painless, arrive in crops and darken then fade over about a week.
Can stress or anxiety cause petechiae?
Not directly. There is no good evidence that emotional stress alone causes capillaries to leak. What stress can do is prompt behaviors that produce petechiae, such as repeated forceful vomiting, bouts of hard crying, or disrupted sleep that makes a person more aware of marks that were already there. Petechiae that appear without a physical trigger still deserve a blood count rather than being attributed to stress.
How long do petechiae take to go away?
A single crop from pressure or a mild viral illness usually fades over one to two weeks, shifting from red to purple to brown as the leaked blood is broken down and reabsorbed. Petechiae that keep appearing, spread or last beyond two weeks suggest an ongoing cause, such as low platelets or vasculitis, and need assessment. Nothing applied to the skin speeds the clearing.
Are petechiae on the legs serious?
Often not. The lower legs carry the highest capillary pressure when standing, so petechiae appear there first after long walks, runs or flights and in people with varicose veins. They become more concerning when raised, symmetrical and paired with joint or abdominal pain, which suggests vasculitis, or when they follow a new medicine or come with bruising and bleeding elsewhere, which suggests low platelets. A blood count and urine test settle most cases.
Do petechiae always mean leukemia?
No. Leukemia is one of the rarer causes and is usually accompanied by fatigue, pallor, repeated infections, night sweats or bone pain. Far more petechial rashes come from coughing, straining, viral infections or immune thrombocytopenia. Because a bone marrow disorder cannot be excluded by looking, a clinician orders a complete blood count, which in most people comes back normal and removes the concern with a single result.
Which blood tests are done for a petechial rash?
The first is a complete blood count, which measures platelets along with red and white cells. A blood film examined under the microscope confirms the count and looks for abnormal cells. Clotting studies check the proteins that work with platelets. A urine dipstick looks for blood or protein pointing to kidney involvement. In a feverish patient, blood cultures are drawn, and a skin biopsy is reserved for suspected vasculitis.
References
- MedlinePlus Medical Encyclopedia: Bleeding into the skin
- MedlinePlus Medical Encyclopedia: Immune thrombocytopenic purpura (ITP)
- NHS: Meningitis, symptoms and the glass test
- NHS: Henoch-Schönlein purpura (IgA vasculitis)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Is a Specialist Second Opinion Useful in Aplastic Anemia? What a Transplant Center Adds
A specialist second opinion is widely considered useful in aplastic anemia because the condition is rare, easily confused with other bone marrow disorders, and…

Fever, Bruising or Unusual Fatigue With Myelodysplastic Syndrome: What to Report Promptly
With myelodysplastic syndrome, a temperature of 100.4°F (38°C) or higher, new or spreading bruises, bleeding that does not stop, or fatigue that suddenly worsens…

Iron Chelation in Thalassemia: Why It Accompanies Transfusions and How It Is Monitored
Iron chelation accompanies regular transfusions in thalassemia because every unit of donated red cells adds iron the body cannot excrete on its own, and…

Living With Low Counts in Aplastic Anemia: Infection and Bleeding Precautions That Matter
In aplastic anemia, low neutrophils raise infection risk and low platelets raise bleeding risk, so daily precautions focus on both. Core habits include careful…

Supporting Someone With Sickle Cell Anemia: Hydration, Warmth and Recognizing a Crisis
Supporting someone with sickle cell means helping prevent the triggers that make red blood cells sickle, chiefly dehydration, cold and infection, and knowing when…

What Ferritin and Transferrin Saturation Show, and When Genetic Testing Is Added
Ferritin estimates how much iron the body has stored, while transferrin saturation shows how much iron is circulating on its transport protein. In hereditary…