

Questions to Ask Your Physical Therapist at the Start of a Rehabilitation Program

Key Takeaways
- A first physical therapy visit is mainly an assessment of history, movement, strength, and goals, and most people leave with two or three starter exercises rather than a full program.
- The single most useful question is how progress will be measured and what would make the therapist change the plan, because feelings drift while timed tests and questionnaire scores do not.
- Ask for a specific pain rule: mild discomfort that settles soon after exercise is generally acceptable, while sharp, spreading, or worsening pain is a signal to stop and report.
- For most acute low back pain, guidance from Mayo Clinic favors staying active over bed rest, and routine early imaging is not recommended because scans often show changes unrelated to symptoms.
- Harvard Health advises holding a stretch about 30 seconds without bouncing after a 5 to 10 minute warm-up, a detail worth confirming for your own home program.
- Red flags such as new bladder or bowel changes, limb weakness or numbness, fever with spinal pain, a hot swollen calf, or chest symptoms during exercise mean calling a doctor before the next session.
The most useful questions to ask a physical therapist at the start of rehabilitation cover five areas: what the therapist thinks is causing the problem, what a realistic goal looks like and how progress will be measured, how long and how often treatment is expected to run, what to do at home between visits, and which symptoms mean you should stop and call. Clear answers early make the whole program easier to follow.
The waiting room chair is slightly too low, the paperwork asks you to rate your pain on a scale that never quite fits, and a therapist you have known for four minutes is about to ask you to bend, lift, and step onto a box while they watch. Most people leave that first visit with a printout of exercises and a follow-up date, then realize in the car that they never asked the things they actually wanted to know.
That gap matters. Rehabilitation is one of the few treatments where the patient does most of the work, unsupervised, on ordinary weekday evenings. Knowing which questions to ask a physical therapist early turns a vague list of stretches into a plan you understand and can stick with.
This explainer walks through what happens at a first evaluation, the questions worth asking in each phase, the answers you should expect, and the signs that mean a call to your doctor should come before the next session.
What actually happens at a first physical therapy appointment?
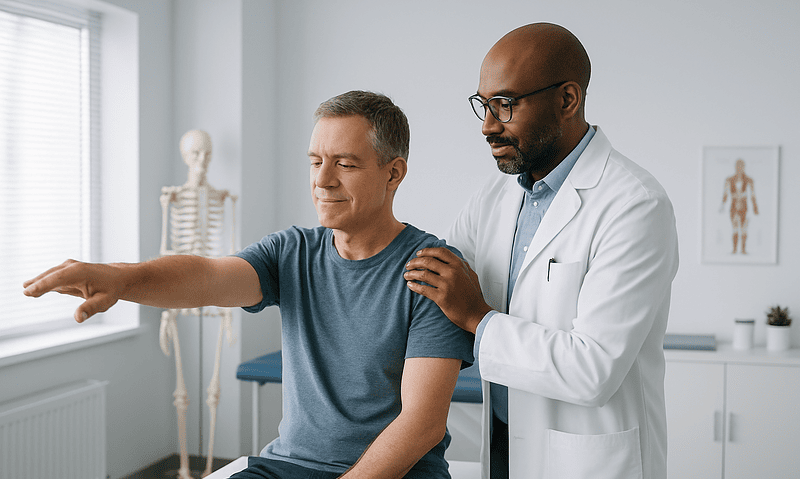
A first physical therapy appointment is an evaluation, not a treatment session, and it helps to arrive expecting to talk as much as move. The therapist will usually start with your history: when the problem began, what makes it better or worse, what you have already tried, your work and hobbies, and any conditions or surgeries that shape what is safe. The NHS describes this first visit as an assessment of your movement and a discussion of goals before any plan is set.
Then comes the physical part. Expect to be asked to walk, reach, squat, or balance while the therapist watches how your joints move and where you compensate. They may measure range of motion with a small protractor called a goniometer, test muscle strength by hand, and press on specific spots to find what reproduces your pain. None of this should be a surprise; a good therapist narrates what they are checking and why.
By the end you should hear a working explanation of the problem in plain words, a first set of goals, and an outline of how often you will be seen. You will almost always leave with two or three exercises to start immediately, because early movement is a core part of most rehabilitation programs, according to MedlinePlus.
Bring a short written list of questions, your medication list, and any imaging reports. Wear clothing that lets the therapist see the area being treated. If English is not your first language, or if hearing or memory is a concern, ask ahead whether a family member can sit in. Most clinics welcome it.
Questions to ask your physical therapist about the diagnosis and the goal
Start with the question that shapes everything else: what do you think is going on, and how confident are you? Physical therapists work from a movement diagnosis, meaning a description of which tissues and patterns are contributing, rather than a single label. A useful answer sounds like “your hip is not rotating well, so your knee is taking load it should not” instead of a Latin term you cannot picture.

Follow with what would need to be true for you to change that opinion? This tells you whether the plan has built-in checkpoints. If the therapist expects improvement within a stated window and it does not arrive, the honest next step is to reassess, not to repeat the same exercises for another month.
Then move to goals. Ask what does success look like for me specifically, and how will we measure it? Good goals are functional and numeric: walking a set distance without stopping, climbing stairs reciprocally, lifting a grandchild, returning to a particular sport. Therapists often track these with validated questionnaires and simple timed tests, so ask which ones will be used and what your baseline score is today.
- What is the most likely cause, and what else is on the list?
- Which findings from today support that view?
- What is the first milestone, and roughly when should I expect it?
- How will you know if the plan is not working?
- What is the long-term aim: full return, modified activity, or managing a chronic condition?
Write the answers down. A goal you can read back at week four is far more motivating than a feeling that things are “a bit better.”
How long will rehab take, and how often should I come?
Nobody can promise a date, and a therapist who gives one without hedging is guessing. What you can reasonably ask for is a typical range for people with a similar problem, and the factors that push you toward the shorter or longer end.
Ranges vary widely by condition. For acute low back pain, Mayo Clinic notes that most episodes improve within a few weeks with home care and staying active, which is why early programs often emphasize movement and reassurance over intensive treatment. Injuries involving surgery, tendon repair, or ligament healing follow slower biological timelines, and the therapist should be able to describe which healing phase you are in and what that phase allows.
Frequency is a separate question. Some programs work best with several supervised sessions early and taper as you become independent; others are mostly home-based with periodic check-ins. Ask why this frequency, and what would make you change it? Ask too about the plan for discharge, because a clear endpoint prevents the drift where visits continue out of habit rather than need.
Useful questions on timeline and dose:
- What is the typical range for someone like me, and what shortens or lengthens it?
- How many supervised visits do you expect, and when will I be doing most of the work at home?
- What signs will tell us to move to the next phase?
- If I miss a week because of work or illness, how do we catch up?
- When will we formally review whether to continue, adjust, or refer me elsewhere?
Treat the answer as a forecast rather than a contract. Bodies heal on their own schedule, and honest uncertainty is a better sign than false precision.
Who is rehabilitation usually for, and who is usually asked to wait?
Physical therapy suits a broad range of situations: recovery after orthopedic surgery, sprains and strains, persistent back or neck pain, balance problems in older adults, neurological conditions such as stroke or Parkinson’s disease, cardiac and pulmonary recovery, and pelvic floor dysfunction. MedlinePlus lists rehabilitation as appropriate for injuries, surgery, and long-term conditions that affect everyday function.

Timing still matters. Some people are asked to wait or to limit the program because tissue needs protection first. After certain surgeries the surgeon sets weight-bearing and range-of-motion limits that override any exercise plan, and the therapist works inside those limits. An acute fracture, a fresh tendon repair, or an unstable joint may mean weeks of protected movement before strengthening begins.
Other situations call for a pause and a medical check before or alongside therapy. If your pain began with significant trauma, if there is fever, unexplained weight loss, or new bowel or bladder changes, Mayo Clinic advises seeing a doctor promptly, because these features point away from a simple musculoskeletal cause. Uncontrolled heart or blood pressure problems, recent clots, or dizziness with exertion also need clearance so that exercise intensity can be set safely.
Questions that clarify whether now is the right time:
- Are there restrictions from my surgeon or physician that shape this plan?
- Is there anything in my history you want checked before we load this area?
- Which parts of the program can start today, and which are on hold?
- If I have a flare of another condition, should I still come?
Being asked to wait is not a setback. It usually means the team is protecting a structure that cannot yet tolerate the work.
What to ask a physiotherapist about the home exercise program
The supervised hour is the smallest part of rehabilitation. The larger part is what happens on your kitchen floor at nine at night, so the home program deserves the most careful questions of all.
Ask first for the why behind each exercise. An exercise you understand is one you will do. If a movement is meant to restore hip rotation, you will notice when it starts to feel easier and know what to report. Then pin down the specifics: how many repetitions, how many sets, how often each day, and how long you should hold a stretch. Harvard Health suggests holding a stretch for about 30 seconds without bouncing, and warming up for 5 to 10 minutes before stretching cold muscles, which are practical details many people never hear.
Next, ask how the program will progress. Rehabilitation works through gradual overload, meaning the demand on the tissue increases slightly as it adapts. If nothing changes for weeks, adaptation stalls. Find out what the next version of each exercise looks like and what signals readiness to move on.
Finally, cover the practical friction that derails most programs:
- What equipment do I need, and what household items can substitute?
- Can you record a short video of me doing this correctly, or give me a written sheet with pictures?
- What are the two exercises that matter most if I only have ten minutes?
- How should I track what I did so we can review it together?
- What common mistakes do people make with this movement?
Be honest about what you will realistically do. A three-exercise program done daily beats a twelve-exercise program done twice.
How much pain during physical therapy is normal, and how much is too much?
This is the question people most want answered and most often skip. The honest reply is that some discomfort is expected during rehabilitation, particularly when restoring movement to a stiff joint or loading a weak tendon, but pain is information rather than a target.
Ask your therapist to give you a specific rule for your condition. Many use a traffic-light approach: mild discomfort that settles within a short time after exercise is acceptable, moderate pain that lingers into the next day suggests the dose was too high, and sharp, sudden, or worsening pain means stop. The exact thresholds depend on what is healing, so a rule for a post-surgical knee will differ from one for chronic low back pain.
Ask also about the difference between soreness and warning pain. Muscle soreness a day or two after new exercise is a normal adaptive response. Pain that is sharp, that produces swelling, that changes how a joint feels when it bears weight, or that spreads down a limb with numbness needs a different response. The NIH’s National Institute of Arthritis and Musculoskeletal and Skin Diseases advises stopping activity and seeking evaluation for injuries with severe pain, swelling, or inability to bear weight.
Questions that make the pain rule usable:
- On a scale of zero to ten, what is my ceiling during and after exercise?
- How long after a session should discomfort settle before I should worry?
- Which specific sensations mean I should stop immediately?
- If I have a flare, should I rest fully, reduce the dose, or continue?
- What should I do about ice or heat, and does the evidence actually support either for me?
A therapist who answers these clearly is giving you permission to work hard and permission to stop, which are both essential.
Questions to ask at each phase of rehabilitation: a summary table
Rehabilitation questions change as you move from the first visit through the middle weeks to discharge. The table below groups the most useful ones by phase so you can bring the right list at the right time.
| Phase | What is happening | Questions worth asking |
|---|---|---|
| Evaluation (first visit) | History, movement testing, working diagnosis, baseline measures | What do you think is causing this? What is my baseline score? What is the first milestone? What should I avoid right now? |
| Early phase | Pain control, protected movement, restoring basic range and activation | What is my pain ceiling? How do I progress the home exercises? What signs mean I am doing too much or too little? |
| Middle phase | Strength, endurance, balance, task-specific practice | Are we on track compared with the range you expected? What needs to change if progress has stalled? When do I return to work or sport tasks? |
| Late phase and discharge | Independence, return to full activity, relapse prevention | What do I keep doing long term? What are early signs of relapse? When and how should I come back if things slip? |
Two threads run through every phase. The first is measurement: at each stage, ask what number or test will show progress, because feelings drift and numbers do not. The second is the exit plan: from the first visit onward, ask what independence looks like and when you are expected to reach it.
Keep the table in your phone. Before each appointment, glance at the row you are in and pick two questions. That habit alone changes the visit from something done to you into something done with you.
What the following days and weeks usually look like
The days after a first evaluation are often the most confusing part of rehabilitation, because you are doing new movements with a body that has been guarding itself. Some soreness in muscles you have not used properly for months is common and typically eases within a day or two. Pain in the injured area itself should not be dramatically worse; if it is, the dose needs adjusting, and that is worth a message to the clinic rather than silent perseverance.
In the first two to three weeks, progress is often measured in small functional gains rather than pain scores: getting out of a chair more smoothly, sleeping through the night, walking further before stiffness sets in. Therapists expect this pattern. Pain often lags behind function, so ask which one to watch.
The middle weeks are where most programs succeed or stall. Exercises get harder, novelty wears off, and life intrudes. This is when the measurement plan you set at the start earns its keep. If your timed tests or questionnaire scores are improving in line with the range the therapist quoted, keep going even if it feels slow. If they are flat, ask directly whether the diagnosis or the plan should change.
Toward the end, sessions shift from treatment to coaching. Expect conversations about long-term activity: the CDC’s guideline of at least 150 minutes of moderate activity each week plus two days of muscle strengthening is a reasonable framework for many adults finishing rehabilitation, adapted to your condition by your team.
Discharge is not the end of the relationship. Ask what would prompt a return visit and how quickly you could be seen. Knowing the door stays open makes it easier to walk through it early if symptoms creep back.
Questions about hands-on treatment, machines, and what the evidence supports
Clinics use a wide range of tools: manual therapy, massage, dry needling, ultrasound, electrical stimulation, taping, heat, cold, and various devices. Some have reasonable evidence for short-term relief in specific conditions; others persist more from tradition than from trials. You are entitled to ask which category each one falls into.
A fair framing is this: what is this treatment meant to do, how strong is the evidence for it in my condition, and what happens if we skip it? For many musculoskeletal problems, guideline-level advice from bodies such as the NHS places active exercise and education at the center, with passive treatments as optional additions that may help comfort in the short term but do not replace loading and movement.
Hands-on techniques can reduce pain and improve movement temporarily, which may make exercise easier. That is a legitimate role. The concern arises when passive treatment becomes the whole session and the home program fades. If most of your visit is spent lying on a table, ask how that time is moving you toward your functional goals.
Useful questions:
- Which parts of my plan are active and which are passive?
- What does the research say about this technique for my problem, in plain terms?
- Is this expected to change the underlying issue or mainly to ease symptoms for a few hours?
- Are there risks or reasons I should not have this?
- If I decline a passive treatment, does the rest of the plan still work?
A good therapist will not be offended. Evidence-informed practice means being able to explain the reasoning, including where the evidence is thin, and adjusting when a patient prefers a different mix.
Questions to ask about medicines, imaging, and the rest of your care team
Physical therapists do not prescribe medicines, but pain relief, anti-inflammatory drugs, muscle relaxants, and nerve-pain medicines all affect how you feel during exercise, and the therapist should know what you take. Ask whether any medicine changes how they interpret your pain feedback, and whether timing a dose relative to a session matters. Decisions about starting, stopping, or adjusting any medicine sit with the prescribing clinician, and the therapist’s role is to communicate with them, not to advise you around them.
Imaging is another common source of confusion. Many people expect a scan before therapy begins. For most uncomplicated back, neck, and joint pain, guidelines including those summarized by Mayo Clinic do not recommend routine imaging early, because scans frequently show age-related changes that are not the source of pain and can lead to unnecessary worry or treatment. Ask your therapist what, if anything, a scan would change about the plan, and which findings would prompt them to request one through your doctor.
Rehabilitation often involves several clinicians: a surgeon, a family physician, sometimes an occupational therapist, a pain specialist, or a dietitian. Ask how information flows between them and who holds the overall plan.
- Does anything I take change how you read my pain during exercise?
- Would a scan change my plan, and who orders one if needed?
- How do you communicate with my surgeon or physician, and how often?
- Who do I contact first if something changes between visits?
- Are there other services, such as occupational therapy or a falls program, that would help?
Clear lines of communication protect you from the two failure modes of multi-clinician care: conflicting advice and nobody noticing a problem.
What is a red flag in physical therapy?
In clinical language, a red flag is a symptom or history feature that raises the possibility of a serious underlying condition and calls for medical evaluation rather than continued exercise. Physical therapists are trained to screen for these at the first visit and to keep watching for them throughout treatment. Knowing the main ones lets you speak up early.
For spinal pain, Mayo Clinic lists features that warrant prompt medical attention: pain following a fall or blow to the back, pain with fever, new bowel or bladder problems, pain accompanied by unexplained weight loss, and pain spreading down a leg with weakness or numbness. Pain that wakes you at night and does not ease with position change is another feature clinicians take seriously.
For limbs, the concerning signs include a calf that becomes swollen, warm, and painful, particularly after surgery or immobility, which can indicate a blood clot; a joint that suddenly becomes hot, red, and swollen; and inability to bear weight after an injury. For anyone exercising, chest pain, unusual breathlessness, dizziness, or fainting during activity should stop the session and prompt urgent assessment.
Red flags also include the quieter kind: symptoms that steadily worsen despite appropriate treatment, or a pattern that does not fit the working diagnosis. A good therapist treats a failure to progress as a reason to re-examine, not a reason to push harder.
Ask at the first visit: what specific signs should make me stop and call you or my doctor before the next session? The answer should be short, concrete, and tailored to your condition. If you are unsure whether something counts, report it. Over-reporting costs a phone call; under-reporting can cost a great deal more.
What people often get wrong about starting physical therapy
Myth: the therapist fixes you. Rehabilitation is closer to coaching than to repair. The sessions guide the work; the work happens between them. People who understand this from day one tend to ask better questions and adhere more consistently.
Myth: no pain means no gain, so push through everything. Some discomfort is expected, but escalating or sharp pain is a signal to adjust, not a badge of effort. Overloading healing tissue can set recovery back by weeks. Ask for a specific pain rule and follow it.
Myth: rest is the safest option. For many musculoskeletal problems, prolonged rest weakens muscle, stiffens joints, and prolongs pain. Mayo Clinic advises that for most back pain, staying active within tolerable limits helps recovery more than bed rest.
Myth: a scan is needed before exercise is safe. Imaging often reveals changes that are common in pain-free people and rarely alters early management. Your therapist and doctor can tell you if your situation is an exception.
Myth: more sessions always means faster progress. Frequency should match what you cannot yet do alone. As independence grows, fewer visits is a sign of success, not neglect.
Myth: if it hurts in the same place, the injury is the same as before. Recurring pain can have different drivers, which is why a fresh evaluation matters rather than repeating an old program from memory.
Myth: asking questions is rude or slows things down. Therapists consistently describe engaged patients as easier to help. Questions surface misunderstandings early, when they are cheap to fix. Bring your list.
Questions to ask your care team: a one-page checklist
Below is a compact list to print or photograph. You do not need every question at every visit; choose the ones that fit the phase you are in and leave space for what comes up.
About the problem
- What do you think is causing my symptoms, and how sure are you?
- What findings support that, and what would change your mind?
- Is there anything you want my doctor to check first?
About the plan
- What are my specific, measurable goals, and what is my baseline today?
- What is the typical time range for someone like me, and what shifts it?
- How many supervised visits do you expect, and when do we review?
- Which treatments are active, which are passive, and why each is included?
About home work
- Why does each exercise matter, and how do I know I am doing it correctly?
- How many, how often, how long, and how do I progress?
- What are the two exercises that matter most if I am short on time?
About safety
- What is my pain ceiling during and after exercise?
- Which symptoms mean stop and call?
- Does anything I take affect how I should exercise or report pain?
About the finish
- What does discharge look like, and what do I keep doing afterward?
- What early signs of relapse should I watch for?
- How do I get back in touch if things slip?
End each visit with one more question: is there anything I should have asked that I did not? Experienced clinicians often use that prompt to raise the thing they were waiting for a chance to say.
When to call your doctor
Most rehabilitation runs smoothly, and most setbacks are ordinary: a sore week, a missed session, a plateau that a small change fixes. Some situations, though, need a doctor rather than a therapist, and sometimes need one urgently. Contact your physician or seek emergency care if you notice any of the following during your program.
- New weakness, numbness, or tingling spreading into an arm or leg, especially if it is worsening.
- New difficulty controlling your bladder or bowels, or numbness around the groin or inner thighs.
- Back or neck pain with fever, chills, or unexplained weight loss.
- Pain that began after a significant fall or impact, or that does not ease at night regardless of position.
- A calf or leg that becomes swollen, warm, tender, or discolored, particularly after surgery or a period of immobility.
- A joint that becomes suddenly hot, red, swollen, and too painful to move or bear weight on.
- Chest pain, pressure, unusual shortness of breath, palpitations, dizziness, or fainting during or after exercise.
- A wound near the treatment area that becomes red, warm, leaks fluid, or opens.
- Pain or function that steadily worsens over one to two weeks despite following the program.
Mayo Clinic’s guidance on back pain and the NIH’s guidance on sports injuries both single out severe pain, inability to bear weight, and neurological changes as reasons to be seen promptly rather than to keep exercising. Chest symptoms or signs of a clot need emergency assessment.
Tell your therapist as well, so the plan can pause safely. Your treating team, meaning your physician together with your therapist and any specialists involved, makes the call on when and how to resume. No article, and no exercise sheet, should override that judgment.
Frequently asked questions
What are some good questions to ask a physiotherapist at the first appointment?
Ask what the therapist thinks is causing your problem and how confident they are, what your measurable goals are and what your baseline score is today, the typical time range for someone like you, how many supervised visits to expect, what to do at home and how to progress it, your pain ceiling during exercise, and which symptoms mean you should stop and call. Write the answers down before you leave.
What is a red flag in physical therapy?
A red flag is a symptom or history feature suggesting a serious underlying condition that needs medical evaluation rather than continued exercise. Common examples include new weakness or numbness in a limb, bladder or bowel changes, spinal pain with fever or unexplained weight loss, pain after significant trauma, a hot swollen calf, and chest pain or breathlessness during activity. Therapists screen for these and refer you back to a doctor when they appear.
What should I expect at my first physical therapy appointment?
Expect a conversation about your history, activities, and goals, followed by movement, strength, and balance testing to see how your body compensates. The therapist will explain a working diagnosis in plain terms, set initial goals, outline visit frequency, and usually give you a few exercises to start immediately. Wear clothing that allows access to the area being treated and bring your medication list and any imaging reports.
How long does a physical therapy program usually last?
It depends on the condition, the healing timeline of the tissue involved, your general health, and how consistently the home program is done. Acute low back pain often improves within a few weeks with activity and self-care, according to Mayo Clinic, while post-surgical or tendon-related programs follow slower biological schedules. Ask your therapist for a typical range for your situation and for the checkpoints that will show whether you are on track.
What physical therapy evaluation questions will the therapist ask me?
Typical evaluation questions cover when symptoms started, what triggered them, what makes them better or worse, how they affect sleep, work, and daily tasks, previous injuries and treatments, current medicines, and your personal goals. The therapist may also ask screening questions about fever, weight loss, night pain, bladder or bowel changes, and numbness, because those help rule out conditions that need a doctor first.
Is it normal to feel worse after starting physical therapy?
Mild muscle soreness for a day or two after new exercise is common and usually reflects normal adaptation. Pain in the injured area that is sharply worse, lasts well into the next day, or comes with swelling, weakness, or numbness suggests the dose was too high or something else is going on. Report it to your therapist so the program can be adjusted rather than pushing through.
Should I have a scan before starting physical therapy?
Usually not for uncomplicated back, neck, or joint pain. Guidelines summarized by Mayo Clinic do not recommend routine early imaging because scans often show age-related changes present in pain-free people and rarely alter initial management. Imaging is considered when red flags are present, when pain fails to improve as expected, or when a specific structural problem needs confirming. Your doctor and therapist decide together.
How do I know if my physical therapist is a good fit?
Look for someone who explains their reasoning in plain language, sets measurable functional goals, gives you a clear home program with reasons for each exercise, welcomes questions, and treats a lack of progress as a reason to reassess. Sessions dominated by passive treatments with little active work, vague goals, or no discussion of discharge are reasonable prompts to ask for a clearer plan or a second opinion.
What are good questions to ask a therapist about home exercises?
Ask why each exercise is included, exactly how many repetitions and sets to do and how often, how long to hold stretches, what correct form looks like and what mistakes are common, how the exercise will progress, which two exercises matter most when time is short, and how to record what you did. Request a video or illustrated sheet so you can check yourself at home.
What are good questions to ask in a physical therapy interview when choosing a clinic?
Ask how much of each session is active exercise versus passive treatment, how goals are measured, whether you will see the same therapist consistently, how the clinic communicates with your physician or surgeon, what a typical discharge plan looks like, and how quickly you can be seen if symptoms return. Answers that emphasize measurement, independence, and communication tend to reflect evidence-based practice.
References
- MedlinePlus: Rehabilitation
- NHS: Physiotherapy
- CDC: Adult activity, an overview
- NIH NIAMS: Sports injuries
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

How Family Members Can Support Neurological Rehabilitation Between Therapy Sessions
Family members can support neurological rehabilitation between sessions by helping the person practice the specific exercises and everyday tasks their therapists have prescribed, keeping…
What Happens in a Manual Therapy Session: Mobilization, Manipulation and Soft Tissue Work
A manual therapy session usually begins with a short conversation about your symptoms and a physical assessment, followed by hands-on techniques chosen for your…

How Long Does Vestibular Rehabilitation Take? Typical Milestones From Dizziness to Steady
Vestibular rehabilitation commonly takes about six to eight weeks of supervised sessions plus daily home exercises, though the range is wide. Positional vertigo (BPPV)…

Which Medicines Matter During Stroke Rehabilitation and Why the Team Keeps Reviewing Them
During stroke rehabilitation the medicines that matter most prevent a second stroke, such as antiplatelets or anticoagulants, statins and blood pressure medicines, and treat…

Sports Rehabilitation Phases: From Protected Movement to Return-to-Play Testing
Sports rehabilitation usually moves through five overlapping phases: protected movement while swelling and pain settle, restoring range of motion and muscle activation, rebuilding strength…

Preparing for Brain Injury Rehabilitation: Records, Routines and the Goals That Matter to You
Preparing for brain injury rehabilitation means gathering the medical records the rehab team will need, settling predictable daily routines for sleep, meals and rest,…