

Tension-Type Headache vs Migraine: How Headache Medicine Treats Each Differently

Key Takeaways
- Untreated migraine attacks typically last 4 to 72 hours, while tension-type headaches can last from 30 minutes to several days, a difference clinicians use in diagnosis.
- Aura, the visual or sensory warning phase, occurs in roughly one in four to one in three people with migraine and never occurs with tension-type headache.
- Acute migraine medicine is most effective taken at the first sign of an attack, before nausea slows absorption and pain pathways become sensitized.
- Using simple pain relievers on more than about 14 days a month, or triptans on more than about 9, can create medication-overuse headache that perpetuates the problem.
- Chronic tension-type headache is defined as 15 or more headache days a month for more than three months, the threshold at which preventive strategies are usually considered.
- Preventive medicines for either condition are judged over a trial of roughly two to three months, and success usually means fewer and milder attacks rather than none.
Tension-type headache and migraine are treated differently because they arise differently. Tension-type headache is usually managed with simple pain relievers used sparingly, stress and posture strategies and, when attacks are frequent, preventive medicine or physical therapy. Migraine is treated as a neurological event: acute medicine taken early in the attack, trigger management and preventive treatment when attacks are frequent or disabling. A clinician confirms which type is present before choosing a plan.
It is 3:40 in the afternoon and she has been pressing two fingers into her temples for the last hour. The screen is too bright. Her neck feels like a clenched fist. Yesterday she called this a stress headache and pushed through. Today, halfway through a meeting, the room tilted slightly and her stomach turned, and she is no longer sure what to call it.
That uncertainty sits at the heart of almost every conversation in a headache clinic. People arrive convinced they have “just tension” when the pattern is classic migraine, or frightened they have migraine when the picture is a common tension-type headache. The label matters more than most people expect, because the two conditions respond to different strategies, and the wrong approach can quietly make things worse.
This explainer walks through how clinicians tell the two apart, what is happening in the nervous system during each, and how tension headache vs migraine treatment differs in practice, from the first hour of an attack to the months of prevention that sometimes follow.
How do clinicians know if it is a migraine or tension headache?
The honest answer is that they listen more than they look. There is no blood test or scan that confirms either diagnosis; both are what neurologists call primary headache disorders, meaning the headache is the condition itself rather than a sign of something else. Imaging is reserved for cases with warning features, not for sorting migraine from tension-type headache.
Instead, a clinician builds a picture from the story of a typical attack. According to the Mayo Clinic, tension-type headache usually produces a dull, pressing, non-throbbing ache on both sides of the head, often described as a tight band, and it does not typically worsen with ordinary walking or climbing stairs. Migraine more often produces a throbbing or pulsing pain, frequently on one side, that physical activity makes worse, along with nausea or a strong wish to avoid light and sound.
Duration is a second clue. The Mayo Clinic notes that untreated migraine attacks last from 4 to 72 hours, while tension-type episodes can be as short as 30 minutes or stretch across several days. A third clue is what happens before the pain. Roughly a quarter to a third of people with migraine experience aura, a set of temporary neurological symptoms such as shimmering zigzag lines or tingling that usually build over minutes and fade within an hour, per Mayo Clinic figures. Aura does not occur with tension-type headache.
None of these features is decisive alone, and many people carry both diagnoses. That is exactly why a headache diary kept for a few weeks is often the most useful thing a patient can bring to a first appointment.
What is actually happening inside the head during each type?
Two headaches can feel similar at the surface and still have quite different machinery underneath, and that machinery explains why the treatments diverge.
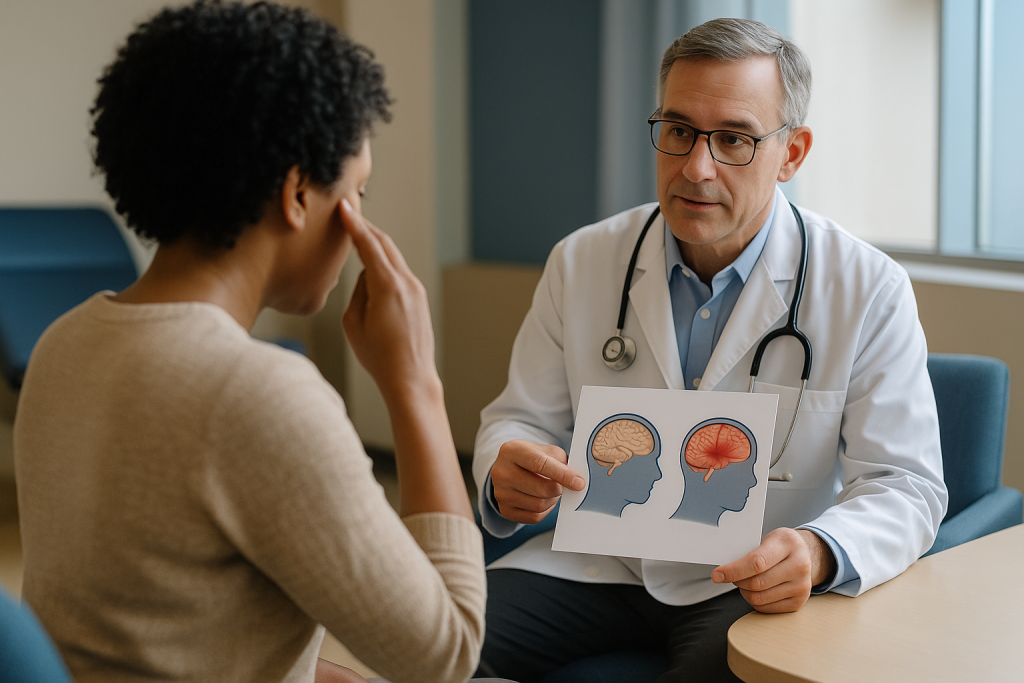
Migraine is now understood as a disorder of brain excitability rather than a problem of blood vessels alone. During an attack, a network called the trigeminovascular system, the nerve fibers that carry pain signals from the coverings of the brain and its blood vessels, becomes activated. Those fibers release chemical messengers, including a peptide known as CGRP (calcitonin gene-related peptide), which promotes inflammation around blood vessels and amplifies pain signaling. The brainstem, which normally dampens incoming pain, appears to lose some of that control. This is why migraine brings company: nausea, light sensitivity, sound sensitivity and, for some, a hypersensitivity of the scalp called allodynia, where even brushing hair hurts.
Tension-type headache is less well mapped, and the Cleveland Clinic is candid that its exact cause remains unclear. The older idea that it comes purely from clenched scalp and neck muscles has softened. Current thinking, described by the Cleveland Clinic and the NHS, is that peripheral factors such as tender pericranial muscles interact with heightened pain processing in the central nervous system, especially when episodes become frequent. In chronic forms, the pain system itself seems to become more sensitive, a process called central sensitization.
The practical consequence is straightforward. Migraine treatment aims to interrupt a specific neurological cascade, ideally early. Tension-type headache treatment leans on calming muscle tension, stress physiology and, over time, resetting a pain system that has grown too easily triggered.
Where do tension headaches start, and where do migraines?
People often try to diagnose themselves by location, and location does carry information, though less than most hope.
Tension-type headache, per the Mayo Clinic, typically settles across the forehead, around the sides of the head, or at the back of the head and upper neck, and it is usually felt on both sides. Many describe it starting as tightness in the shoulders or base of the skull that creeps upward and forward. Tenderness when pressing on the scalp, neck or shoulder muscles is common, which is part of why massage and heat feel helpful for some.
Migraine more often begins on one side, frequently around the temple or behind one eye, although the Mayo Clinic notes it can affect both sides or shift sides between attacks. What makes migraine distinctive is less the map than the sequence. Many people notice a prodrome, a warning phase hours before pain, that can include yawning, mood shifts, neck stiffness or unusual food cravings. Then, in some, aura arrives. Then the headache itself, which pulses and intensifies with movement.
That neck stiffness deserves a note, because it fools people. Neck pain is a common feature of migraine, and a person can attribute a migraine to “stress in the neck” for years. The NHS points out that stress is a recognized trigger for both conditions, so a stress-related headache is not automatically a tension-type headache.
Clinicians therefore weigh location alongside quality, duration, movement sensitivity and accompanying symptoms. A one-sided throbbing pain with nausea that started with flashing lights is migraine wherever it sits; a two-sided pressure without nausea points the other way.
Tension headache vs migraine treatment: the core principle that separates them
Strip away the specific medicines and one difference remains: how urgently and how broadly each condition is treated.

Tension-type headache is usually managed with a light touch. The NHS describes it as generally not serious, typically responding to simple pain relievers, rest, hydration and attention to stress, sleep and posture. The emphasis is on not over-treating, because frequent use of pain relievers can itself create a headache problem, a point explored later. Prevention comes into the picture only when episodes are frequent or persistent.
Migraine is treated as an event with a window. The Mayo Clinic notes that acute migraine medicines work best when taken at the first sign of an attack, while pain is still mild. Wait too long, particularly once nausea sets in, and absorption slows and the attack may become harder to interrupt. Because migraine typically comes with nausea, sensory sensitivity and days of reduced function, treatment plans often address those pieces too, and the threshold for offering preventive medicine is lower, because the disability per attack is higher.
Another distinction is the toolbox. Several medicine classes are designed specifically for migraine and have no role in tension-type headache: triptans, which act on serotonin receptors to quiet the trigeminovascular system, and newer agents that block CGRP or its receptor. Using a migraine-specific drug for a tension-type headache is not just ineffective; it is unnecessary exposure.
None of this means one headache is “real” and the other trivial. Chronic tension-type headache can be every bit as life-limiting as migraine. It means the plan should match the mechanism, and the prescribing clinician is the one to make that match.
Tension-type headache vs migraine at a glance
The table below summarizes how the two conditions differ in presentation and in the general shape of treatment, drawn from Mayo Clinic, NHS and Cleveland Clinic descriptions. It is a reference for conversations with a clinician, not a self-diagnosis tool.
| Feature | Tension-type headache | Migraine |
|---|---|---|
| Pain quality | Dull, pressing, band-like | Throbbing, pulsing |
| Usual location | Both sides; forehead, temples, back of head | Often one side; may shift or involve both |
| Typical duration (untreated) | 30 minutes to several days (Mayo Clinic) | 4 to 72 hours (Mayo Clinic) |
| Effect of routine activity | Usually not worsened | Usually worsened; people seek stillness |
| Nausea or vomiting | Uncommon | Common |
| Light and sound sensitivity | Mild, if present | Often marked |
| Aura | Absent | Present in about one in four to one in three (Mayo Clinic) |
| Acute treatment approach | Simple pain relievers used sparingly; rest, heat, relaxation | Early acute medicine; may include migraine-specific classes and anti-nausea support |
| Preventive treatment considered | When frequent or chronic (15 or more days a month for over 3 months) | When attacks are frequent, prolonged or disabling despite acute treatment |
| Non-drug approaches with evidence | Physical therapy, relaxation training, biofeedback, CBT | Trigger and routine management, relaxation, biofeedback, CBT, some neuromodulation devices |
Two caveats keep this table honest. First, real attacks blur the lines; a migraine can be two-sided and a tension-type headache can carry mild queasiness. Second, the same person can have both disorders, and about half of people with one primary headache type report another. Treatment then has to be tailored to whichever pattern is dominant, which is a judgment the treating team makes over time.
How is a tension-type headache attack treated?
For most people, a tension-type episode is a nuisance rather than a crisis, and treatment is proportionate to that.
The first-line approach, as described by the NHS and the Mayo Clinic, is a simple over-the-counter pain reliever from the class of non-steroidal anti-inflammatory drugs or acetaminophen, taken as directed on the label or by a pharmacist or clinician. These medicines work by reducing the production of prostaglandins, chemicals that sensitize pain nerves, and they are generally more effective when taken early rather than after hours of white-knuckling. Which product suits a given person depends on their other health conditions, and that is a conversation for a pharmacist or prescriber, not a magazine.
Around the medicine sit measures that cost nothing. A warm shower or heat pack on the neck and shoulders relaxes tender muscles; some people prefer cold on the forehead. A glass of water addresses dehydration, a trigger the NHS lists specifically. Stepping away from a screen for ten minutes, adjusting a chair so the head is not craned forward, or lying down briefly can be enough to let an episode fade.
What clinicians actively discourage is the reflex of reaching for pain relievers on most days. The Mayo Clinic warns that frequent use of acute medicines, generally more than two or three days a week over months, can lead to medication-overuse headache, a rebound pattern in which the medicine itself perpetuates the pain. For someone whose tension-type headaches are creeping toward that frequency, the correct treatment for the attack is often a reassessment of the whole pattern with a clinician rather than another dose.
How is a migraine attack treated, and why does timing matter so much?
Migraine treatment is built around a single clinical observation: the earlier an attack is interrupted, the more likely it is to be interrupted at all.
The Mayo Clinic advises that acute migraine medicine works best taken at the first sign of an attack. Two things explain this. Once the trigeminovascular cascade is fully under way and central sensitization develops, pain becomes harder to switch off. And once nausea and gastric slowing arrive, oral medicine is absorbed more slowly and unpredictably. This is why some people are offered non-oral forms, such as nasal sprays or injections, and why anti-nausea medicine is sometimes part of a plan even when vomiting is not the main complaint.
The medicine classes used fall into two groups. For milder attacks, the same simple pain relievers used for tension-type headache are often the starting point. For moderate to severe attacks, or those that do not respond, clinicians may consider migraine-specific classes: triptans, which narrow dilated blood vessels and dampen pain signaling through serotonin receptors; gepants, which block the CGRP receptor; and ditans, which act on a different serotonin receptor. Each has its own cautions, notably around cardiovascular history for triptans, and the choice belongs to the prescriber.
Environment is the other half of acute care. Because movement, light and sound worsen migraine, the Mayo Clinic recommends resting in a dark, quiet room, and many people find a cool cloth on the forehead or gentle pressure on the temples eases the wait. Sleep, when it comes, often ends an attack.
A ceiling applies here too: triptan use on more than about 9 days a month, or simple analgesics on more than about 14, raises medication-overuse risk, per the Mayo Clinic.
Who is usually offered preventive treatment, and who is asked to wait?
Prevention, sometimes called prophylaxis, means taking a medicine or following a program daily to reduce how often attacks happen, rather than treating attacks once they start. Not everyone needs it, and clinicians apply a rough threshold that differs between the two conditions.
For migraine, the Mayo Clinic describes prevention as an option when attacks are frequent, long-lasting or severe, when acute medicines do not help enough or cannot be used, or when a person is drifting toward medication overuse. Guideline bodies commonly frame this as roughly four or more migraine days a month, or fewer if attacks are disabling, although the exact trigger point is individual. The disability of migraine, not simply its frequency, drives the decision.
For tension-type headache, the bar is set by chronicity. The Mayo Clinic defines chronic tension-type headache as occurring 15 or more days a month for more than three months; people in or approaching that range, or whose episodes no longer respond to simple measures, are those most often offered preventive strategies. Someone with a tension-type headache once or twice a month is usually asked to wait, manage triggers and track the pattern.
Who else is asked to wait? People whose pattern has not yet been observed long enough. Most clinicians want a diary of at least four to eight weeks before committing to daily medicine, partly to confirm the diagnosis and partly to establish a baseline against which to judge any preventive. People with medication-overuse headache are often asked to address the overuse first, because preventives work poorly while rebound headache continues.
Pregnancy, planned pregnancy and certain heart, liver or kidney conditions also shape the decision and can rule some options out entirely. These are conversations for the prescribing team.
Preventive tension headache vs migraine treatment: what the options look like
Preventive plans for the two conditions overlap in philosophy but diverge in the details, and the migraine side has grown considerably in recent years.
For chronic tension-type headache, the Mayo Clinic and Cleveland Clinic describe a small set of daily medicines with evidence, most prominently tricyclic antidepressants, which are used at doses lower than for depression and appear to work by modulating pain pathways in the spinal cord and brainstem rather than by lifting mood. Alongside them sit non-drug programs: physical therapy for neck and shoulder mechanics, relaxation training, biofeedback (learning to control muscle tension and stress responses with real-time feedback from sensors) and cognitive behavioral therapy for the stress and sleep patterns that feed frequent headache.
For migraine, the preventive menu is broader. Older classes, each originally developed for another condition and found to reduce migraine frequency, include certain beta-blockers, some anti-seizure medicines and the same tricyclics used for tension-type headache. Newer options were designed specifically for migraine: monoclonal antibodies that block CGRP or its receptor, given by injection at intervals, and some gepants taken daily. For chronic migraine, injections of botulinum toxin into scalp and neck muscles are an established option. Several nerve-stimulation devices are also cleared for migraine.
Two features apply to all of these. Preventives are judged over a trial period of weeks to months, not days, and the NHS notes people often need to take them for a while before benefit is clear. And “working” usually means fewer, shorter or milder attacks rather than none. The choice among classes turns on side-effect profiles, other health conditions and personal priorities, and it rests with the prescribing clinician.
What does it mean to have daily tension headaches?
A headache that arrives most days is not a more intense version of an occasional one. It is a different clinical situation, and it usually prompts a different set of questions.
The first question a clinician will ask is about medicine use. Medication-overuse headache, sometimes called rebound headache, is a pattern in which regular use of acute pain relievers on many days a month gradually lowers the brain’s pain threshold, so headaches return sooner and more often. The Mayo Clinic notes this can happen with simple analgesics taken more than about 14 days a month or with triptans on more than about 9, and that it commonly develops in people whose original problem was migraine or tension-type headache. The frustrating loop is obvious: more headache leads to more medicine, which leads to more headache. Untangling it, usually by stepping back from the overused medicine under supervision while starting a preventive, is a core skill of headache medicine, and it is not something to attempt alone.
The second question is whether this is truly tension-type headache. Chronic daily headache that is two-sided and pressing may be chronic tension-type headache, but chronic migraine also presents on 15 or more days a month and can lose its throbbing character over time, becoming a flatter, more constant pain. The distinction matters because chronic migraine has migraine-specific preventive options that chronic tension-type headache does not.
The third question is what else is going on. Sleep disorders, untreated anxiety or depression, jaw clenching, caffeine patterns and, less commonly, medical conditions such as thyroid problems or high blood pressure can all sit behind a daily headache. A daily pattern is a reason to book an appointment, not to double the pain relievers.
Which non-drug approaches have real evidence, and for which headache?
People ask about non-drug approaches with a mix of hope and suspicion, and both are reasonable. Some have decent evidence; many are marketed on none.
For tension-type headache, the strongest support sits with behavioral therapies. The Cleveland Clinic and Mayo Clinic list biofeedback, relaxation training and cognitive behavioral therapy as options that can reduce frequency, particularly when stress and muscle tension are prominent. Physical therapy addressing posture, neck mobility and workstation setup helps some people, and regular aerobic exercise is associated with fewer headaches across both conditions. Heat, massage and gentle stretching ease individual episodes for many, even if trial evidence is thin.
For migraine, the same behavioral approaches carry evidence, and to them clinicians add routine management: regular meals, consistent sleep and wake times, steady hydration and moderating caffeine, because the migraine brain appears to dislike irregularity. The Mayo Clinic notes that identifying and managing personal triggers through a diary can reduce attacks. Certain neuromodulation devices, which deliver mild electrical or magnetic pulses to nerves involved in migraine, have regulatory clearance and modest supporting trials.
Acupuncture has been studied for both conditions with mixed but not dismissive results; the NHS lists it as an option some people find helpful for migraine. Supplements such as riboflavin, magnesium and coenzyme Q10 have small trials in migraine prevention with modest effects; the NIH Office of Dietary Supplements summarizes the evidence as limited, and these should be discussed with a clinician because they can interact with medicines.
What lacks evidence: chiropractic manipulation as a treatment for migraine, most “detox” regimens, and any product promising to stop headaches permanently. The honest position is that non-drug approaches are usually most effective as part of a plan, not as a replacement for one.
What do the following weeks usually look like after starting treatment?
The first weeks after a headache diagnosis are less about dramatic change and more about information gathering, and knowing that in advance saves a lot of discouragement.
For someone starting acute-only treatment, whether for tension-type headache or migraine, the immediate task is learning the plan: what to take at the first sign, what to pair it with, and how many days a month is too many. Most clinicians ask for a diary noting each headache’s start time, features, what was taken and how well it worked. Patterns often emerge within four to eight weeks that were invisible day to day: a cluster around the menstrual cycle, a link to skipped lunches, a weekend rebound from weekday caffeine.
For someone starting a preventive, expectations need calibrating. Older oral preventives are typically started low and increased gradually over weeks to limit side effects, and the NHS notes it may take a while before any benefit is felt. Clinicians commonly judge an oral preventive after a trial of two to three months at a tolerated dose; the newer injectable CGRP antibodies are often assessed over a similar period. “Benefit” is usually defined as a meaningful drop in monthly headache days, not zero headaches. Side effects, if they appear, tend to show early and often settle, but any that are troubling belong in a conversation with the prescriber rather than in a decision to stop abruptly.
For someone withdrawing from overused pain relievers, the early weeks can be harder before they are better, and clinicians usually warn of a temporary worsening. Structured follow-up in this period matters. Across all three paths, the marker of progress at the first review is a clearer picture and a plan that fits it, not a headache-free month.
What people often get wrong about tension headaches and migraines
Some misunderstandings are harmless. Others send people down the wrong treatment path for years. These come up repeatedly.
“Migraine is just a bad headache.” It is not. Migraine is a neurological disorder with a characteristic sequence, and headache is only one phase. Some attacks involve aura or vertigo with little pain at all. Treating migraine as a scaled-up tension headache leads to under-treatment and, often, medication overuse.
“Stress headaches are always tension headaches.” Stress is a recognized trigger for both conditions, per the NHS. Many people with migraine describe their attacks as stress headaches because they follow a hard week, and never receive migraine-appropriate care.
“A one-sided headache means migraine; both sides means tension.” Location is a clue, not a verdict. The Mayo Clinic notes migraine can be two-sided, and pain quality, movement sensitivity and nausea carry more weight.
“Sinus headaches are common.” Most self-diagnosed sinus headaches, with facial pressure and weather sensitivity, turn out on evaluation to be migraine. True sinus headache accompanies an active sinus infection with fever and thick discharge.
“Taking a pain reliever every day keeps headaches away.” The opposite is more often true. Frequent acute medicine is a leading cause of daily headache, as the Mayo Clinic’s medication-overuse guidance describes.
“Preventives are for life.” Many people take a preventive for a period, stabilize, and are then supported to taper. That decision, like starting, sits with the prescriber.
“If a scan is normal, nothing is wrong.” Both conditions have normal scans. Imaging rules out other causes; it does not diagnose or dismiss primary headache. A normal scan is reassurance, not a reason to stop seeking treatment.
Questions to ask your care team about your headache plan
A good headache appointment is a two-way exchange, and people who arrive with specific questions tend to leave with clearer plans. These are worth writing down beforehand.
- Based on my diary, which headache type do you think I have, and could I have more than one?
- What features of my attacks pointed you toward that diagnosis, and what would make you reconsider?
- For an acute attack, what should I take, when exactly should I take it, and what should I do if it does not work?
- How many days a month of acute medicine is too many for me, given what I am taking?
- Do I meet the usual threshold for preventive treatment, or would you rather observe the pattern first? What would change that?
- If we start a preventive, how long before we judge whether it is helping, and what counts as success?
- What side effects should I expect early, which ones settle, and which should prompt a call?
- Are there non-drug approaches you would put alongside the medicine, and can you refer me?
- Do any of my other conditions or medicines rule certain headache treatments out?
- Which warning signs mean I should seek urgent care rather than wait for the next appointment?
- How should I track progress between now and the next review?
Two of these deserve emphasis. The question about acute-medicine limits protects against the single most common way headache treatment goes wrong. And the question about what counts as success sets realistic expectations: a preventive that halves monthly headache days is a good result by guideline standards, even if it does not feel like victory in week two. Bring the diary, bring the list of everything taken including supplements, and bring a partner or friend if attacks make it hard to recall details. The plan that emerges belongs to the treating team, but the questions that shape it belong to the patient.
When to call your doctor: red-flag signs that need urgent care
Most tension-type headaches and migraines are not dangerous. A small number of headaches signal something that is, and the features below are the ones headache specialists want people to act on rather than wait out. This paragraph is not a self-diagnosis list; it is a threshold for picking up the phone or going to an emergency department.
Seek emergency care, per Mayo Clinic and NHS guidance, for a headache that reaches maximum intensity within seconds to a minute, often described as the worst headache of your life; a headache with fever and a stiff neck, confusion, seizure, fainting or a rash; a headache accompanied by weakness or numbness on one side, slurred speech, vision loss, drooping face or trouble walking, especially if these do not fade the way a familiar aura does; a headache after a head injury or fall; a headache with a red, painful eye or halos around lights; or a severe headache in someone with a weakened immune system or a history of cancer.
Call your doctor promptly, without waiting for a routine slot, for a headache pattern that is new and different from your usual attacks; headaches that are steadily worsening over days or weeks; a first severe headache after age 50; headaches that wake you from sleep or are worst on waking and improve when upright; headaches brought on by coughing, straining or exertion; a headache with new vision changes, persistent vomiting or unexplained weight loss; or a headache during pregnancy or shortly after delivery, particularly with swelling or high blood pressure.
Also make an appointment, even if nothing feels dramatic, when headaches are occurring on more than a few days a week, when acute medicine is being used most days, when a familiar treatment has stopped working, or when headaches are interfering with work, sleep or relationships. Those are not emergencies, but they are exactly the situations where earlier assessment changes the course. Any change to prescribed medicine should be made with the prescribing clinician, never alone.
Frequently asked questions
How can I tell if it is a migraine or tension headache?
Only a clinician can confirm the diagnosis, but the features that weigh most are pain quality and company. Migraine tends to throb, worsen with movement and bring nausea or light and sound sensitivity, and may follow visual aura. Tension-type headache tends to press like a band on both sides without nausea and does not worsen with walking. Keeping a diary for several weeks gives your doctor the clearest picture.
What are five evidence-based tips for fast relief from a migraine?
There is no genuinely instant fix, but five steps have support: take your prescribed acute medicine at the very first sign, as the Mayo Clinic advises; lie down in a dark, quiet room; apply a cool cloth to the forehead or gentle pressure to the temples; sip water, since dehydration is a common trigger; and sleep if you can, which often ends an attack. Discuss any medicine plan with your clinician.
What does it mean if I have tension headaches every day?
Daily headache warrants a medical appointment rather than more pain relievers. It may be chronic tension-type headache, chronic migraine that has lost its throbbing character, or medication-overuse headache from frequent use of acute medicines. Sleep problems, anxiety, jaw clenching and caffeine patterns can also contribute. A clinician will review your medicine use, confirm the headache type and consider preventive treatment.
Where do stress migraines typically start?
Migraine triggered by stress usually starts the same way as any migraine: often on one side, around the temple or behind an eye, sometimes preceded hours earlier by neck stiffness, yawning or mood change, and in some people by visual aura. Because neck stiffness is common in migraine, many people mistake a stress migraine for a tension-type headache. The pulsing quality, movement sensitivity and nausea are the giveaways.
Can someone have both tension-type headaches and migraines?
Yes, and it is common. Many people with migraine also have tension-type headaches between attacks, and the two can blur when headaches become frequent. This is one reason a headache diary matters: it helps the clinician see which pattern dominates and whether both need addressing. Treatment is then tailored, because migraine-specific medicines have no role in a pure tension-type episode.
Why do doctors treat migraine more aggressively than tension headache?
Because the mechanism and the disability differ. Migraine involves a specific neurological cascade that is easier to interrupt early than late, and attacks typically cost more function, with nausea and sensory sensitivity lasting hours to days. Tension-type headache usually responds to simple measures and carries a higher risk of harm from over-treatment. Matching intensity of treatment to the condition is the whole point.
How long does it take for preventive headache medicine to work?
Clinicians generally judge a preventive after a trial of roughly two to three months at a tolerated level, and the NHS notes people may need to take preventive medicine for a while before benefit shows. Improvement usually means fewer or milder headache days rather than none. If a preventive is not helping after a fair trial, the prescriber may adjust or switch, but that decision should never be made alone.
Do I need a brain scan to diagnose migraine or tension headache?
Usually not. Both are primary headache disorders diagnosed from the pattern of symptoms, and scans are normal in both. Imaging is ordered when red-flag features are present, such as a sudden thunderclap headache, neurological deficits, fever with stiff neck, or a new headache pattern after age 50. A normal scan reassures about other causes but does not diagnose or rule out either condition.
Is a sinus headache actually a migraine?
Often, yes. Many headaches people attribute to sinuses, with facial pressure and sensitivity to weather, turn out on evaluation to be migraine, because the trigeminal nerve involved in migraine also serves the face and sinuses. True sinus headache accompanies an active sinus infection with fever, thick nasal discharge and facial tenderness. A clinician can distinguish them and adjust treatment accordingly.
Can I stop my headache preventive once the headaches improve?
Possibly, but only with your prescriber. Many people take a preventive for a period, stabilize, and are then supported to taper gradually while watching for return of headaches. Stopping abruptly can cause side effects with some classes and a rebound in headache frequency with others. The right time and method depend on the medicine and your pattern, which is a decision for the treating team.
References
- NHS – Tension headaches
- NHS – Migraine
- Cleveland Clinic – Tension-Type Headaches
- WHO – Migraine and other headache disorders fact sheet
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Cataplexy, Naps and Night Sleep: Questions to Ask at Your Narcolepsy Follow-Up Appointment
At a narcolepsy follow-up, the most useful questions cover three areas: how often cataplexy, sleep paralysis or hallucinations are happening and what triggers them;…

Caring for Someone With ALS: How Families Can Support Breathing, Eating and Communication
Caring for someone with ALS means helping with the three functions the disease affects most: breathing, swallowing and speech. Families can learn safe positioning,…

After Stroke Medicine: How Family Can Support Swallowing Checks and Daily Medicines
Families support a stroke patient after discharge by keeping meals to the textures and fluid thickness the speech-language pathologist recommended, sitting the person upright…

Traumatic Brain Injury in Older Adults: Why Blood Thinners and Balance Change the Care Plan
Traumatic brain injury in older adults is managed more cautiously than in younger people because age-related brain shrinkage, blood-thinning medicines and unsteady balance raise…

Neurodegenerative Disease Diagnosis: Which Exam, Imaging and Lab Tests Come First?
Neurodegenerative disease diagnosis usually begins with a detailed history from the patient and someone who knows them well, a physical and neurological examination, and…

Peripheral Neuropathy Treatment Results: What Usually Improves and What Takes Longer
Peripheral neuropathy treatment results depend on the cause. Pain, sleep and balance often improve within weeks to a few months once the cause is…