

What Does the Screening Injection Before Baclofen Pump Implantation Show?
Key Takeaways
- The screening trial tests a small dose of baclofen placed in the spinal fluid by lumbar puncture; nothing is implanted that day and the effect fades within hours.
- Clinicians compare tone scores such as the Modified Ashworth Scale, rated 0 to 4, before the test dose and at its peak, alongside spasm counts and functional tasks.
- Intrathecal delivery bypasses the blood-brain barrier, which is why people who gained little from baclofen tablets can still respond clearly to the test.
- A trial that reveals excessive weakness is a useful result, because some people depend on stiffness to stand or transfer.
- A positive trial shows response and tolerance for one day; it does not predict long-term function, and pump rates are fine-tuned over months by the treating team.
- Sudden loss of baclofen delivery from a missed refill or catheter failure can cause a withdrawal syndrome with high fever, itching and rebound spasticity that MedlinePlus classes as an emergency.
A baclofen pump screening trial shows whether a person's spasticity loosens when a small test dose of baclofen is placed directly into the spinal fluid, usually by lumbar puncture, and observed over a day. It measures the change in muscle tone, spasm frequency and function, and how the person tolerates the medicine. It does not predict the final long-term result of a pump, and the decision rests with the treating team.
The letter arrives with a single line highlighted: screening trial, arrive by eight, bring a driver. For a father whose legs lock like a rusted hinge every time he tries to transfer from wheelchair to bed, that line raises more questions than it answers. Will something be implanted that day? What if nothing happens? What if too much happens?
The baclofen pump screening trial is the quiet middle step between years of pills that made him sleepy and the possibility of a small programmable device under the skin. It is deliberately modest. Nothing is implanted. A physical therapist scores his muscle tone in the morning, a clinician places a test dose into the fluid around his spinal cord, and then people watch, measure and ask him to try the things that matter to him.
Understanding what that day can reveal, and what it honestly cannot, helps families walk in with realistic expectations rather than either dread or blind hope.
What is a baclofen pump screening trial, in plain language?
Spasticity is muscle stiffness caused by damage to the brain or spinal cord, which leaves the reflexes that control muscle tone over-active. It shows up after stroke, spinal cord injury, multiple sclerosis, cerebral palsy and brain injury, and it ranges from a mild catch in the ankle to legs that scissor so tightly that dressing takes two people. The NIH describes it as a condition with treatments that range from stretching and oral medicines to injections and implanted devices.
A baclofen pump is one of those implanted devices. It stores baclofen, a muscle relaxant, and feeds it slowly through a thin catheter into the cerebrospinal fluid, the clear liquid that bathes the spinal cord. Delivering the medicine there, rather than by mouth, is called intrathecal therapy.
Before anyone agrees to surgery, teams want a rehearsal. The baclofen pump screening trial is that rehearsal. A clinician places a small test dose of baclofen into the spinal fluid, most often through a lumbar puncture in the lower back, and the person is observed for several hours while trained staff repeat the same tone and spasm measurements they took beforehand.
The point is a simple comparison: how stiff were you at breakfast, how stiff are you by mid-afternoon, and did anything unwelcome happen along the way. It is a test of response and tolerance, not a treatment in itself. The effect fades by the end of the day, which is exactly what clinicians want, because it leaves behind a clean piece of information rather than a commitment.
Nothing about the trial obliges anyone to proceed. Plenty of people finish the day, learn something useful, and choose a different path with their team.
How does baclofen work when it is placed in the spinal fluid?
Baclofen mimics a natural calming chemical in the nervous system called GABA. In the spinal cord, GABA normally puts a brake on the reflex circuits that make muscles contract. After brain or spinal cord injury, signals from above that used to fine-tune those circuits are lost, the brake weakens, and reflexes fire too easily. Baclofen presses the brake back down by acting on a receptor called GABA-B on spinal nerve cells, according to the drug information published by MedlinePlus.
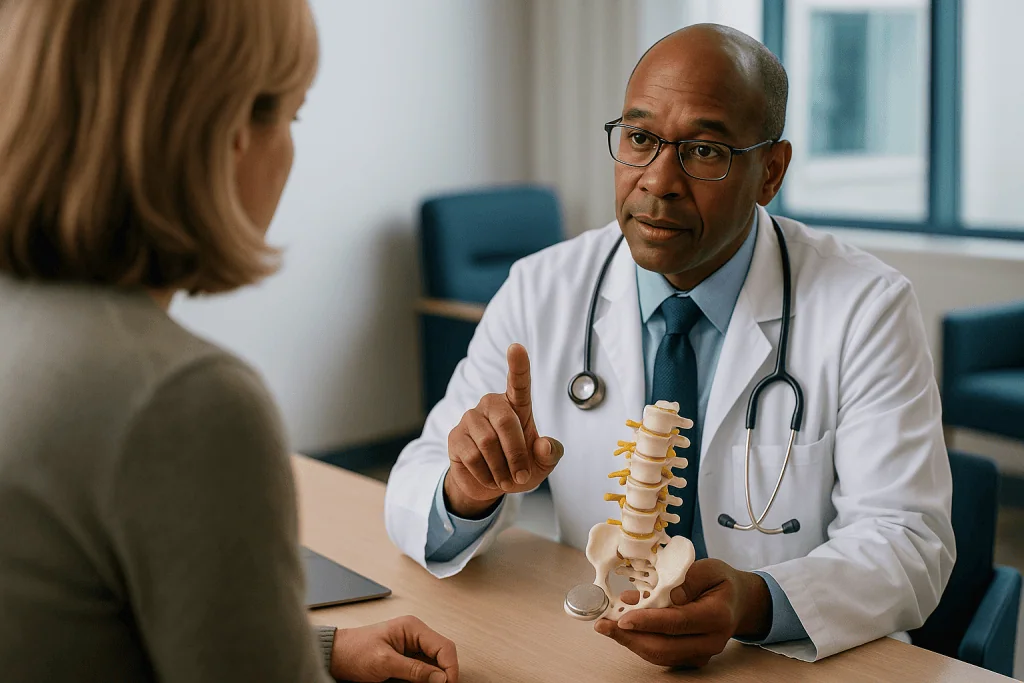
The catch with baclofen tablets is geography. The medicine has to travel through the bloodstream and cross the blood-brain barrier, a protective lining that keeps most substances out of the nervous system. Only a small fraction of an oral dose reaches the spinal cord, so the rest of the body is exposed to a much larger amount, which is why drowsiness, weakness and confusion limit how far tablets can be pushed.
Placing the medicine directly in the cerebrospinal fluid changes that arithmetic. The spinal cord is bathed in it, so a far smaller quantity reaches the target, with less circulating elsewhere. That is the whole rationale for a pump, and it is also why the screening test dose is tiny compared with what a person might swallow.
Two practical consequences follow. First, the effect during a trial builds over hours rather than minutes, because the medicine spreads through the fluid and binds to receptors gradually. Second, because the nervous system adapts to baclofen, stopping it suddenly, whether tablets or pump flow, can trigger a withdrawal reaction. MedlinePlus lists this as a serious risk of intrathecal therapy. Anyone on oral baclofen should never adjust it themselves around a trial; the prescribing team plans any change.
How is the baclofen pump trial performed, step by step?
Most trials happen in a day unit or on a hospital ward with rehabilitation staff nearby. The rhythm of the day is fairly standard, though the exact protocol belongs to your team.
The morning starts with baseline measurements. A physical or occupational therapist moves your limbs through their range and scores the resistance, counts how many spasms you have had recently, and often records a video or a timed task such as a transfer or a short walk if you are able. Any tone-related pain, bladder pattern and sleep quality may be noted too. These numbers are the yardstick everything else is measured against.
Next comes the test dose itself. You lie on your side or sit leaning forward. The lower back is cleaned, numbed with local anesthetic, and a thin needle is guided between the vertebrae into the fluid-filled space below the end of the spinal cord, the same technique used for a diagnostic lumbar puncture. A small amount of baclofen is delivered, the needle is removed, and a dressing goes on. Some teams use imaging guidance if scoliosis or previous spinal surgery makes the anatomy tricky.
Then the watching begins. Nurses check blood pressure, breathing, alertness and comfort at regular intervals. The therapist repeats the tone scoring at set points through the day. According to MedlinePlus, the effect of intrathecal baclofen typically builds over the first few hours and wears off within the same day, so the peak assessment usually falls in the early afternoon.
Family are often asked to stay. They notice things staff might miss: that a hand opened for the first time in months, or that legs went too floppy to stand. Both observations matter.
What does the screening injection actually show, and what does it not?
The trial answers three narrow questions well and several broad ones poorly. Knowing the difference is the heart of this article.

It shows whether your nervous system responds to intrathecal baclofen at all. Some spasticity, especially when contractures have set in, is driven more by shortened tendons and stiffened joints than by over-active reflexes. Baclofen cannot lengthen a tendon. If a limb barely changes after a test dose, that is valuable information that steers the conversation toward orthopedic options instead.
It shows how you tolerate the medicine at a modest level. Drowsiness, nausea, dizziness, headache or low blood pressure during the observation period tell the team something about your sensitivity. So does the absence of those problems.
It shows what reduced tone would mean for you functionally. This is the part people underestimate. Many people rely on stiffness. Extensor tone in the legs lets someone stand for a transfer even when their muscles are weak. Remove it and the person may slide to the floor. A trial that reveals this is a success in the sense that it prevented a poor decision, even though it points away from a pump.
What it cannot show is the long-term picture. A single day says nothing reliable about how the body will adjust over months, how the team would tune a continuous infusion, or how the pump, catheter and surgery will go. It does not predict walking, independence or pain relief in any guaranteed way. The NIH is clear that spasticity management is individualized and that no single treatment suits everyone.
Think of the trial as a proof of concept, not a preview of the finished result.
How do clinicians measure whether the intrathecal baclofen trial worked?
Observers use structured scales so that a good day is not confused with a good result. The most common is the Modified Ashworth Scale, a rating from 0 to 4 in which 0 means no increase in tone and 4 means the limb is rigid. A therapist moves each joint at a steady speed and grades the resistance. Because the scale is subjective, the same trained person usually scores before and after.
The Modified Tardieu Scale adds speed. Spastic muscles resist fast movement more than slow movement, so the examiner moves the limb quickly and notes the angle at which it catches. A change in that catch angle is a more specific signal of reflex activity than a change in stiffness alone.
Spasm frequency scores, usually a simple count or a daily rating, capture the sudden involuntary jerks that disturb sleep or sitting. Pain ratings, ease of catheterization or hygiene, and timed functional tasks round out the picture.
| Measure | What it captures | Why it matters in a trial |
|---|---|---|
| Modified Ashworth Scale | Resistance to passive movement, 0 to 4 | Core tone comparison, morning versus peak effect |
| Modified Tardieu Scale | Angle of catch at fast versus slow speed | Separates reflex spasticity from fixed tightness |
| Spasm frequency score | How often involuntary jerks occur | Tracks the symptom that often bothers people most |
| Functional task or video | Transfers, sitting, hand opening, gait | Shows whether looser muscles help or hinder daily life |
| Vital signs and alertness | Blood pressure, breathing, drowsiness | Safety and tolerance of the medicine |
Best-practice consensus documents indexed on PubMed generally define a positive response as a clinically meaningful drop in tone score together with acceptable side effects and, ideally, a functional gain that matches the person’s own goals. Which goal counts most is decided with you, not for you.
Who qualifies for a baclofen pump, and who is usually asked to wait?
Teams generally consider intrathecal baclofen when spasticity is severe, affects more than one limb or the trunk, interferes with care, comfort or function, and has not responded well enough to stretching, positioning, oral medicines or targeted injections such as botulinum toxin, or when those options cause side effects that cannot be tolerated. The NHS lists the pump among the treatments used for severe spasticity in cerebral palsy and multiple sclerosis, alongside these earlier steps.
The underlying diagnosis is less important than the pattern. Spinal cord injury, multiple sclerosis, cerebral palsy, stroke and traumatic brain injury all appear in intrathecal baclofen programs. Adults and children are both considered, though children need enough body size to house the pump comfortably, and growth changes the anatomy over time.
Some people are usually asked to wait or are steered elsewhere:
- Those whose stiffness is mostly fixed contracture rather than active spasticity, since baclofen cannot address shortened tissue.
- Anyone with an active infection, particularly skin infection near the implant site, until it clears.
- People whose tone is their main support for standing or transfers, unless the trial shows function survives looser muscles.
- Situations where follow-up is impractical, because a pump needs regular refills and programming for as long as it stays in place.
- Those in the early, still-changing months after a stroke or injury, when tone may settle on its own.
A history of poor response to oral baclofen does not automatically rule someone out, because tablets deliver so little to the spinal cord. Equally, a good oral response does not guarantee a good trial. The screening test exists precisely because these things cannot be predicted from history alone. Eligibility is a clinical judgment made by the team who would manage the pump long term.
What side effects can a baclofen test dose cause?
Because the test dose is small and the observation period is close, serious problems are uncommon, but the whole design of the day assumes they could happen. That is why nurses check on you repeatedly rather than sending you to the cafeteria.
The most frequent complaints are those MedlinePlus lists for intrathecal baclofen generally: drowsiness, dizziness, headache, nausea, and a feeling of weakness or heaviness in the legs. Muscle weakness beyond what was intended is, in a sense, the medicine working too well for that person’s needs, and it is one of the most informative findings of the day.
A headache that worsens on sitting up and eases when lying flat can follow any lumbar puncture. It is caused by a small leak of spinal fluid through the needle track, not by the baclofen itself, and it usually settles with rest and fluids over a few days. Persistent cases are treated by the team.
Less common but more important effects include low blood pressure, slowed or shallow breathing, confusion or unusual sleepiness. These are the reason the medicine is given in a monitored setting with the means to support breathing if needed. Staff are trained to spot them early.
Bladder changes, temporary retention or urgency, are occasionally reported, particularly in people who already have neurogenic bladder.
Two practical notes. Bring a list of everything you take, including sedatives, opioids and alcohol use, because these can add to drowsiness. And arrange transport home. Even people who feel fine by late afternoon should not drive after a spinal procedure and a centrally acting medicine. Your team will tell you when it is safe to resume normal activity, and whether any oral spasticity medicine should be held or continued around the trial. Never change that on your own.
Bolus injection or temporary catheter: which trial method is used?
Not every screening trial looks the same. Two broad approaches exist, and your team will have a reason for choosing one.
The bolus trial, described above, is a single-day test: a lumbar puncture, a test dose, hours of observation, home by evening. If the response is unclear, some centers repeat the test on a later day at a different level, chosen by the clinician, rather than proceeding on a maybe.
The continuous catheter trial places a thin temporary catheter into the spinal fluid and connects it to an external pump for several days, often during an inpatient rehabilitation stay. It lets the team adjust the flow, watch how tone behaves during real therapy sessions, sleep and bowel routines, and see whether walking or transfers hold up. It carries a higher risk of infection and headache because a line stays in the back, and it costs the person more time. It is used more often when the trade-off between tone and function is delicate, such as in someone who walks.
| Feature | Bolus trial | Continuous catheter trial |
|---|---|---|
| Typical duration | One day, effect fades the same day | Several days, often inpatient |
| What is placed | Needle only, removed immediately | Temporary catheter with external pump |
| Can the level be adjusted? | Not during the same session | Yes, over the trial period |
| Best suited to | Clear-cut severe spasticity, non-ambulatory people | Walkers, complex goals, unclear earlier results |
| Main drawbacks | Snapshot only; may need repeating | Infection and leak risk, time commitment |
Neither method is universally better. The bolus test is the more common screening route because it is simpler and safer for most candidates, while the catheter trial answers subtler questions at a higher price in inconvenience. Ask which one your team prefers and why.
What happens after a positive baclofen pump screening trial?
A positive result opens a door; it does not push anyone through it. The next conversation is usually longer than the trial itself.
The team will review the numbers with you: how much tone dropped, when it peaked, what happened to transfers or hand use, and what side effects appeared. They will connect that to your own goals. Someone hoping for easier caregiving and better sleep is weighing a different equation from someone hoping to walk further.
If everyone agrees to proceed, the surgical work-up begins. A neurosurgeon or another implanting specialist examines the abdomen and back to choose a pump site, usually a pocket under the skin of the lower abdomen, and a spine level for the catheter tip. Blood tests, imaging of the spine and a review of clotting, skin condition and infection risk follow. People taking oral baclofen continue it as prescribed; the team plans any taper around the surgery so that withdrawal is avoided.
The implant procedure is done under anesthesia. The catheter is threaded into the spinal fluid through the lower back and tunneled under the skin around the flank to the pump pocket. The pump is filled, programmed to a starting rate chosen by the clinician, and the incisions are closed. Hospital stays of a few days are typical while the team checks wound healing, breathing and early response, according to descriptions of the procedure from academic medical centers and MedlinePlus.
Expect the early weeks to involve fine-tuning rather than a finished result. The starting rate is conservative by design, and the effect is adjusted gradually at clinic visits using a handheld programmer that communicates with the pump through the skin. The screening trial told the team you respond; the months afterward are where they learn how much you need.
What if the intrathecal baclofen trial is negative or unclear?
A negative trial is a disappointment, but it is not a dead end, and it is rarely a verdict on the person.
First, the team will ask why. Occasionally the test dose simply did not reach the target, for instance if the needle was partly outside the fluid space, or if scarring from earlier surgery blocked spread. In that situation a repeat test is reasonable. Sometimes the person responded, but the assessment window missed the peak. Sometimes the tone dropped but the person felt no better, which usually means the stiffness that troubles them is not the stiffness the medicine reaches.
Second, the result redirects. If fixed contracture dominates, orthopedic options such as tendon lengthening, serial casting or bracing move up the list. If only one or two muscle groups drive the problem, targeted injections of botulinum toxin, sometimes combined with therapy, may be more sensible than a whole-body approach. Selective dorsal rhizotomy, a spinal nerve procedure, is considered for certain children with cerebral palsy, as the NHS notes. Oral options beyond baclofen exist, and each carries its own profile that the prescriber weighs.
Third, an unclear result may prompt the more detailed continuous catheter trial described earlier, particularly when function and tone pull in opposite directions.
What a negative trial should not do is send someone to a different provider hoping for a different answer. The same physiology will show up on the same test. A better use of energy is to ask the team what the day taught them and what they now recommend.
People sometimes describe the trial as a wasted day when it comes back negative. It is the opposite: it spared them an operation that would not have helped.
How long does baclofen pump surgery recovery take, and what do the first weeks look like?
Recovery after implantation has two overlapping timelines: the surgical wound and the medicine settling in.
The wound side is fairly predictable. Two incisions, one in the back and one over the pump pocket, are sore for the first week or two. Teams typically ask people to avoid bending, twisting, lifting and swimming for several weeks so that the catheter does not shift before scar tissue anchors it, and to keep the dressing dry until the wound check. Lying flat for a period after surgery is often advised to reduce spinal-fluid headache, the same kind that can follow the trial. The exact restrictions come from your surgeon.
The medicine side takes longer. The pump starts at a conservative rate, and adjustments are made every few weeks at first, based on tone scores and your own reports. It is common for the first months to feel like a work in progress: too stiff one visit, a little too loose the next, until the rate settles. Physical therapy is usually restarted early, because looser muscles are an opportunity to build strength and range, not a finished result.
Refills are the long-term rhythm. The pump reservoir is topped up through the skin with a needle at intervals that depend on the rate and reservoir size; MedlinePlus notes that the pump must be refilled regularly and that appointments must not be missed, because an empty reservoir can cause withdrawal. Pump batteries last several years, after which the pump is replaced in a smaller operation while the catheter often stays.
A sensible expectation is this: the sutures heal in weeks, the settling of the dose is measured in months, and the commitment to refills and programming lasts as long as the pump does.
How to interrogate a baclofen pump, and what a refill visit involves
Interrogation is the clinic term for reading the pump. A handheld programmer is held over the skin and communicates wirelessly with the device, no needles involved. Within a minute the clinician can see the current flow rate, the calculated volume remaining in the reservoir, the date the pump expects to run low, any alarms that have triggered, and the battery status. Comparing the calculated remaining volume with what is actually withdrawn at refill is one of the main ways teams spot a problem before the person feels it.
A refill visit usually runs like this. The pump is located by touch, sometimes with a template or ultrasound. The skin is cleaned, a fine needle is passed through the skin into the central port of the reservoir, the old medicine is withdrawn and measured, and fresh medicine is injected. The programmer is then updated so that the pump knows its new volume. The whole appointment often takes less than an hour.
Interrogation also guides troubleshooting. If a person’s spasticity creeps back, the clinician checks whether the rate has been changed, whether the reservoir is lower than predicted (suggesting a leak), or whether a catheter problem is likely. Imaging with a plain X-ray or a dye study through the pump’s side port can then look at the catheter itself.
Two practical points for people living with a pump. Carry the identification card you are given, because the pump is metal and contains medicine, and tell any clinician arranging an MRI, since the pump may pause during the scan and needs to be checked afterward. And keep a note of your refill dates in more than one place; MedlinePlus is explicit that missing refills is dangerous. The team manages the device, but the calendar is shared.
What people often get wrong about the baclofen pump screening trial
Myths gather around any procedure that involves a needle in the spine. These are the ones that cause the most avoidable anxiety.
The pump goes in on trial day. It does not. The trial is a test dose through a needle that is removed straight away. Surgery, if it happens, is a separate decision and a separate date.
A great trial means a great outcome. The trial shows response and tolerance over a few hours. It cannot forecast how tone will behave under continuous infusion, how surgery will go, or how much function will change. The NIH describes spasticity treatment as individualized precisely because outcomes vary.
If oral baclofen never worked, the trial is pointless. Tablets deliver only a fraction of the medicine to the spinal cord. Many people who gained little from pills respond clearly to the intrathecal test, and the reverse happens too. That gap is the reason the trial exists.
Looser is always better. For someone who stands by leaning on stiff legs, looser can mean falling. A trial that shows this has done its job.
The test dose is dangerous. Serious reactions are uncommon at screening levels, and the monitored setting exists to manage them. The lumbar puncture headache people fear is usually mild and self-limiting.
A pump replaces therapy. It reduces tone; it does not build strength, range or skill. Rehabilitation continues, and often becomes more productive.
Once implanted, you are set. A pump is a long-term relationship with a clinic: refills, programming, battery replacement and vigilance about withdrawal. People who understand that before the trial make better decisions after it.
None of these corrections should discourage anyone. They simply move the conversation from hope to evidence, which is where good decisions live.
Questions to ask your care team before and after the trial
A trial day is busy, and questions evaporate under fluorescent lights. Writing them down beforehand gives you and your family a better footing. These are the ones experienced clinicians say they wish more people asked.
- Which kind of trial are you planning for me, a single-day test or a temporary catheter, and why that one?
- What exactly will you measure before and after, and which change would you consider a positive result?
- Should I take my usual spasticity medicines on the morning of the trial? Please tell me rather than leaving me to guess.
- What will you be watching for during the observation period, and what would make you stop or extend it?
- If my legs get too weak to transfer during the trial, what does that tell you about a pump?
- What are the alternatives to a pump for someone with my pattern of spasticity, including injections, orthopedic options and other oral medicines?
- If the trial is unclear, will you repeat it, change the method or recommend something else?
- If we go ahead with surgery, where would the pump sit, how long would I stay in hospital, and what restrictions would I have afterward?
- How often would refills be needed, who does them, and what happens if I cannot get to an appointment?
- What are the signs of withdrawal or overdose that my family should know, and whom do we call at night or on weekends?
- How would pregnancy, MRI scans, air travel or future spinal surgery affect the pump?
- What is the plan if I decide, at any stage, that I do not want to continue?
Ask for the answers in writing where possible. The best teams welcome the list, because a person who understands the trade-offs is a person who does well with whatever they choose.
When to call your doctor: red-flag signs after a trial or with a pump
Most people go home from a screening trial with nothing more than a small dressing and some tiredness. A few signs, though, need a same-day call to the team or emergency care, whether they appear after the trial, after implant surgery or years into living with a pump.
After the test dose or implantation, seek urgent help for breathing that is slow or shallow, extreme sleepiness that is hard to rouse, new confusion, fainting, or a seizure. These can indicate that too much baclofen is acting on the nervous system, and MedlinePlus lists them as reasons for immediate medical attention.
Call promptly for a headache that is severe, keeps worsening or does not ease when lying flat; fever with a stiff neck; redness, swelling, warmth or fluid leaking from a puncture or incision site; or new numbness, weakness or loss of bladder or bowel control that was not present before. These can point to infection, spinal-fluid leak or a problem around the catheter.
For anyone with an implanted pump, the most dangerous emergency is withdrawal. MedlinePlus describes the warning pattern: a sudden return or sharp increase of spasticity, itching all over without a rash, high fever, rapid heartbeat, agitation or confusion, and in severe cases muscle breakdown and organ failure. It can follow a missed refill, a catheter break or a pump problem. Treat it as an emergency, tell responders you have a baclofen pump, and show the identification card.
A pump alarm, a beeping sound from the abdomen, also needs a call the same day; it usually means the reservoir is low or the battery is near its end.
When in doubt, call. The team would far rather hear about a false alarm than miss a real one.
Frequently asked questions
How is the baclofen pump trial performed?
A therapist scores your muscle tone and spasms in the morning, then a clinician places a small test dose of baclofen into the spinal fluid through a lumbar puncture in the lower back under local anesthetic. Nurses monitor breathing, blood pressure and alertness while the therapist repeats the tone measurements over several hours. You go home the same day once the effect has faded, and the team reviews the results with you at a later visit.
Who qualifies for a baclofen pump?
People with severe spasticity affecting several limbs or the trunk, from conditions such as spinal cord injury, multiple sclerosis, cerebral palsy, stroke or brain injury, whose stiffness interferes with care or function and has not responded well to stretching, oral medicines or targeted injections. A positive screening trial, realistic goals and the ability to attend regular refills are usually required. Those with mostly fixed contractures or active infection are generally asked to wait or offered other options.
What does an intrathecal baclofen trial show that tablets cannot?
It shows how your spinal cord reflexes respond when baclofen reaches them directly, bypassing the blood-brain barrier that blocks most of an oral dose. Because tablets deliver only a small fraction to the spinal cord, a poor response to pills does not predict a poor trial. The test also reveals whether looser muscles help or hinder your daily activities, something a tablet response cannot easily separate.
What are common baclofen test dose side effects?
The most frequent are drowsiness, dizziness, nausea, headache and temporary weakness or heaviness in the legs. A positional headache can follow any lumbar puncture and usually settles with rest and fluids. Less common but important effects include low blood pressure, slowed breathing and confusion, which is why the test is done in a monitored setting. Report anything unusual to the nursing staff during the day and to your team afterward.
How to interrogate a baclofen pump?
A clinician holds a handheld programmer over the skin above the pump, and it communicates wirelessly to display the current flow rate, the calculated reservoir volume, the expected low-reservoir date, any alarms and the battery status. No needle is needed for interrogation itself. Comparing the calculated volume with the amount actually withdrawn at a refill helps detect leaks or catheter problems early. Interrogation is done only by trained staff.
How long does it take to recover from baclofen pump surgery?
Wound soreness at the back and abdominal incisions typically eases over the first one to two weeks, with restrictions on bending, lifting and twisting for several weeks so the catheter stays in place. Hospital stays of a few days are usual. Settling the pump rate takes longer, often several months of gradual adjustments at clinic visits. Your surgeon sets the exact restrictions and follow-up schedule.
Does a positive screening trial guarantee the pump will work long term?
No. A positive trial shows that your spasticity responds to intrathecal baclofen and that you tolerated a small test dose over a few hours. It does not predict how tone behaves under continuous infusion, how surgery will go, or how much function will change. The NIH describes spasticity management as individualized because results vary between people. The trial informs the decision; the treating team makes the plan with you.
Can I keep taking my oral baclofen before the trial?
Follow your prescriber’s instructions exactly rather than deciding on your own. Some teams ask people to continue their usual medicines so the trial reflects real conditions; others plan a temporary change. Stopping baclofen abruptly can trigger withdrawal, so no one should alter it without guidance. Bring a complete list of everything you take, including sedatives and alcohol use, because these can add to drowsiness on the day.
What happens if the baclofen trial does not work?
The team first checks whether the test dose reached the target and whether the peak was missed, in which case a repeat test may be offered. If the response is truly poor, the discussion moves to other options: targeted botulinum toxin injections, orthopedic procedures for contractures, other oral medicines, or in selected children selective dorsal rhizotomy. A negative trial spares you an operation that was unlikely to help.
What are the warning signs of baclofen pump withdrawal?
A sudden return or sharp increase in spasticity, itching all over without a rash, high fever, fast heartbeat, agitation or confusion are the classic warning signs, according to MedlinePlus. Withdrawal can follow a missed refill, a catheter break or a pump malfunction and can become life-threatening. Treat it as an emergency, tell responders you have a baclofen pump and show your identification card.
References
- Spasticity, National Institute of Neurological Disorders and Stroke (NIH)
- Baclofen Injection, MedlinePlus Drug Information
- Spasticity, MedlinePlus Medical Encyclopedia
- Cerebral palsy: Treatment, NHS
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Mealtime Support for Someone With Dysphagia: Positioning, Pacing and Swallowing Safety
Mealtime support for dysphagia means helping someone eat and drink in the way their swallowing assessment recommends: sitting fully upright with the head slightly…

What Families Can Do Between Therapy Sessions to Support a Child With Cerebral Palsy
Between therapy sessions, families support a child with cerebral palsy mainly by folding the therapist's goals into daily routines: planned positioning, regular stretching, supported…

Can Cognitive Stimulation and Nutrition Help in Alzheimer’s Disease? What Care Plans Include
Cognitive stimulation, usually delivered as structured group sessions, produces small but measurable gains in thinking and quality of life for people with mild to…

Who Is a Candidate for Deep Brain Stimulation in Parkinson’s Disease? How Teams Decide
A person is usually considered a candidate for deep brain stimulation in Parkinson's disease when the diagnosis is confirmed, symptoms still respond well to…

How Can Family Help During and After a Seizure? A Caregiver’s Guide to Epilepsy Care
Helping someone during a seizure means keeping them safe, not stopping the seizure. Ease them to the floor, cushion the head, move hard objects…

When Symptoms Do Not Match the Scans: How an FND Diagnosis Is Confirmed and Treatment Begins
FND is diagnosed by a neurologist on the basis of positive clinical signs, not by normal scans alone. The examiner looks for features that…