

What Happens at a Physical Therapy Evaluation and How It Shapes Your Program

Key Takeaways
- A physical therapy evaluation has four parts, interview, examination, measurement and planning, and the interview usually narrows the diagnosis more than any single physical test.
- The gap between how far you can move a joint yourself and how far the therapist can move it passively helps distinguish stiffness from weakness or pain inhibition.
- In the CDC's Timed Up and Go test, taking 12 seconds or longer to rise, walk, turn and sit is associated with increased fall risk.
- Red flags such as new bladder or bowel changes, spreading limb weakness, fever with back pain or pain after a significant fall mean the therapist should refer you to a physician before continuing.
- Measured baselines matter because rehabilitation progress is often too gradual for memory to judge reliably, in either direction.
- The WHO estimates about 2.4 billion people worldwide live with a condition that could benefit from rehabilitation, so being referred is common rather than a sign of a serious problem.
A physical therapy evaluation is the first, longer appointment where a physical therapist interviews you about your problem, health history and goals, then examines movement, strength, joint range, balance and function with standardized tests. The findings are combined into a working movement diagnosis, a set of measurable goals and a plan of care that sets the exercises, hands-on treatment and visit frequency for the weeks ahead.
The referral slip has been sitting on the kitchen counter for two weeks. It says “PT eval and treat” in a doctor’s shorthand, and beneath it, in your own handwriting, a phone number you have not yet called. Part of the hesitation is practical: what do you wear, what will they do, will it hurt? Part of it is quieter. You have been compensating for this shoulder for months, and letting a stranger watch you reach for a shelf feels oddly exposing.
That first visit deserves a better explanation than “they’ll check you out.” A physical therapy evaluation is closer to a structured investigation than a treatment session. The therapist is gathering evidence, ruling things in and out, and measuring a baseline that every later visit will be compared against.
Knowing what is being looked for, and why, turns you from a patient being assessed into a partner in the assessment. This guide walks through the appointment step by step, including what the tests mean, how long it usually takes, and how those first findings shape everything that follows.
What actually happens at a physical therapy evaluation
Strip away the clipboard and the treatment table, and the appointment has four moving parts: a conversation, a physical examination, a set of measurements, and a plan built from the first three. The order is fairly consistent across clinics, whether you arrive with a stiff neck, a healing ankle or a hip replaced three weeks ago.
The conversation comes first because it steers everything else. A therapist who hears that your knee pain started after a twisting fall will examine different structures than one who hears it crept in over a year of stair climbing. The examination that follows is hands-on but purposeful. Each movement you are asked to perform, each joint the therapist moves for you, answers a specific question about what is limited, what is painful and what is protective.
Measurement is what separates an evaluation from an informal look. A goniometer, which is a hinged protractor for measuring joint angles, records how far a knee bends in degrees. Strength is graded on a standard scale. Balance and walking are timed. These numbers are your baseline, and they matter more than they sound: progress in rehabilitation is often slow enough that memory alone cannot tell you whether you are improving.
The plan closes the visit. The therapist explains what the findings suggest, sets goals with you, and outlines how often you should come and what you will do between visits. Most evaluations also include the first taste of treatment, usually one or two exercises or some hands-on work, so you leave with something to do rather than only something to think about. MedlinePlus describes rehabilitation as care that helps people regain, keep or improve the abilities daily life requires, and that framing, function first, is what the whole visit is organized around.
Before your first physical therapy appointment: what to bring and wear
Preparation is mostly about removing friction so the appointment time goes toward you rather than toward paperwork and wardrobe problems.

Clothing matters more than people expect. The therapist needs to see and touch the area being examined, so a shoulder evaluation goes better in a tank top or loose T-shirt, and a knee or hip evaluation in shorts. Supportive shoes you actually walk in daily are useful because how you move in them is part of the assessment. Skin lotion on the treatment area makes tape and hands-on techniques harder, so skip it that morning.
Paperwork is the second category. Bring the referral if you have one, any imaging reports (the written report is more useful than the disc of pictures), a current list of medicines including over-the-counter ones and supplements, and the names of other clinicians involved in your care. The medicine list is not idle curiosity: some drugs affect balance, bleeding, bone density or pain perception, and the therapist adjusts the examination accordingly.
The third category is your own account. Before the visit, think about three things: when the problem started and what you were doing, what specifically you cannot do or do with difficulty now, and what you want back. “I want to lift my grandson without bracing” is a better goal than “less pain,” because it can be measured and because it tells the therapist which movements to prioritize.
Expect to fill in one or more questionnaires about how the problem limits daily tasks. These are outcome measures, meaning standardized scoring tools that translate your experience into a number, and they will be repeated later to track change. The NHS notes that physiotherapists take a whole-person approach rather than treating a body part in isolation, so questions about sleep, work and mood belong on those forms.
The interview: why the therapist asks so many questions
Fifteen minutes into your appointment you may wonder when the actual examining starts. The questions are the examining. In musculoskeletal care, the history narrows the possibilities more than any single physical test does, which is why a good therapist listens before touching.
The interview typically covers the mechanism, meaning how the problem began. A sudden onset with a clear injury points one way; a gradual onset with no trigger points another. Next comes the behavior of the symptoms over a day: pain that is worst on waking and eases with movement behaves differently from pain that builds through the afternoon or wakes you at night. Location and quality matter too. Pain that travels down a limb, tingles or feels like numbness raises the question of nerve involvement, which shapes both the examination and the plan.
Then the therapist widens the lens. Past injuries and surgeries, other diagnoses such as diabetes or heart disease, medicines, work demands, sport, sleep and stress all feed into the picture. Some of these questions are screening for problems that do not belong in a physical therapy clinic at all, which the next sections cover.
Your goals close the interview, and this is where honesty pays. If you have no intention of doing thirty minutes of exercise daily, say so; the plan can be built around five. If you are worried the pain means something serious, say that too. Fear of movement is itself a recognized barrier to recovery, and a therapist cannot address a worry they have not heard.
The interview also sets the tone of the relationship. You should leave it feeling heard and understood, not processed. If you do not, that is legitimate information about whether this therapist is the right fit.
The physical examination: what the hands-on tests are measuring
Once the story is told, the therapist tests it against your body. The examination is systematic rather than random, and each cluster of tests answers one question.
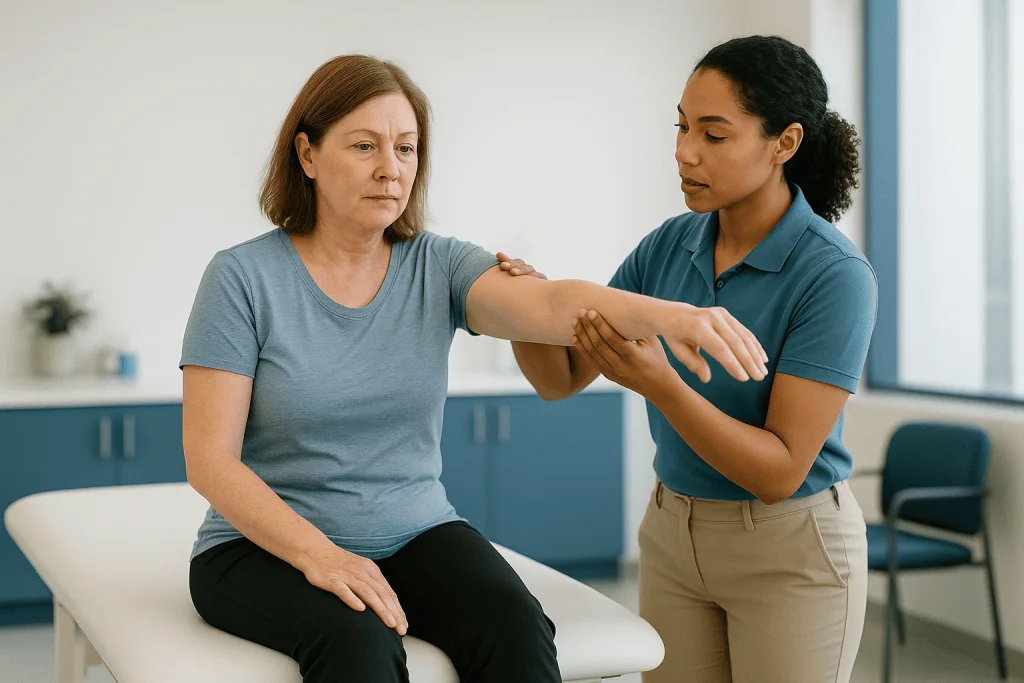
Observation comes first and starts before you notice. How you walked in, how you sat, whether one shoulder sits higher, whether you avoid putting weight through a leg: these are data. The therapist may ask you to stand, bend, turn and squat while watching for asymmetry, guarding or a movement pattern that loads the wrong structures.
Range of motion is next. That phrase means how far a joint moves, and it is measured two ways. Active range is what you can do yourself; passive range is how far the therapist can move the joint with your muscles relaxed. The gap between them is diagnostic. A shoulder you can lift only halfway but the therapist can lift fully suggests weakness or pain inhibition rather than a stiff joint capsule.
Strength testing usually uses manual muscle testing, in which you push against the therapist’s resistance while the effort is graded on a standard scale. Where the joint or the question allows, a handheld device may add a more precise number.
Palpation, which simply means examining by touch, locates tenderness, swelling, temperature change and muscle tone. Special tests follow: named maneuvers that stress a specific ligament, tendon or nerve to see whether it reproduces your symptoms. None of these tests is perfect on its own; their value comes from combining them with the history.
Finally, a neurological screen checks reflexes, sensation and the strength of specific muscle groups when the history hints at nerve involvement. Some tests will provoke your pain briefly. That is by design, and you can ask the therapist to stop at any point.
Functional tests, balance measures and the numbers that become your baseline
Range and strength describe body parts. Function describes you. This part of the evaluation asks how the problem plays out in tasks that resemble real life, and it produces the numbers that later visits will be measured against.
For a lower-body or balance problem, the therapist may time you rising from a chair, walking a short distance, turning and sitting back down. This is the Timed Up and Go test, one of the tools in the CDC’s STEADI falls-prevention toolkit, and the CDC notes that adults who take 12 seconds or longer to complete it are at increased risk of falling. Sit-to-stand repetitions in 30 seconds, single-leg standing time and walking speed are other common measures.
For the upper body, function might mean reaching overhead, lifting a weighted object to a shelf or turning a doorknob. For an athlete, it might mean hopping, landing and changing direction, with the two sides compared.
The questionnaires you filled in earlier belong here too. A patient-reported outcome measure asks you to rate difficulty with everyday activities and produces a score. Repeating the same questionnaire in a few weeks shows change in a way that is hard to argue with, in either direction.
Why so much measuring? Rehabilitation is a slow-moving field, and both patients and therapists are prone to optimism bias, seeing improvement because they hope for it. A knee that bends 10 degrees further than it did a month ago is progress you can verify. A walk-turn-sit that has dropped from 14 seconds to 10 is a fall-risk conversation that has changed. These numbers also justify continuing, changing or ending the program, and they form the objective language the therapist uses when reporting back to your referring clinician.
What are red flags in physical therapy, and why the screen matters
Not every backache belongs in a physical therapy clinic, and one of the least visible but most consequential parts of the evaluation is checking whether yours does.
In clinical language, a red flag is a symptom or finding that raises the possibility of a serious condition needing medical rather than rehabilitative care. For back pain, the Mayo Clinic and the NHS both list features that warrant prompt medical assessment: pain following a significant fall or blow, new problems with bladder or bowel control, numbness around the groin or buttocks, weakness or numbness spreading in the legs, unexplained weight loss, fever alongside the pain, or pain that is constant and worse at night rather than easing with rest.
The therapist screens for these through the interview and the neurological examination. Questions about weight, appetite, night sweats, previous cancer, steroid use and general health that seem unrelated to your knee are part of this filter. So is the reflex hammer.
Finding a red flag does not mean something is wrong; it means the therapist wants a physician to look before continuing. The direction of that referral, and what happens next, sits with the medical team, not the therapist, and not with you alone. A well-run evaluation that ends with “I would like your doctor to see you first” has done its job.
Red flags also apply during a program, not only at the start. A sudden change in symptoms, new numbness, swelling and heat in a calf, or chest pain during exercise are reasons to stop and report, whatever session you are on. The final section of this article lists the signs that should prompt a call.
Therapists also watch for what are sometimes called yellow flags: fear of movement, low mood, work stress or a belief that the body is fragile. These are not dangers, but they strongly influence recovery and are addressed in the plan rather than referred out.
From findings to a working diagnosis and plan of care
Somewhere near the end of the appointment, the therapist stops testing and starts explaining. This is where the evaluation earns its name: evaluation means interpretation, not just data collection.
The therapist forms a movement diagnosis, which describes the pattern of impairment they have found, for example restricted hip rotation with weak side-hip muscles contributing to knee pain when descending stairs. This is different from, and sits alongside, any medical diagnosis your doctor made. It says what the therapist can treat.
Then comes prognosis, meaning the therapist’s reasoned estimate of how much improvement is likely and how long it may take. Honest therapists frame this as a range and revisit it as the program unfolds. A prognosis is a working hypothesis, not a promise.
Goals are written next, and the best ones are yours, translated into measurable terms. “Walk the dog for 20 minutes without stopping” becomes a goal that can be checked. Short-term goals usually cover the first few weeks; long-term goals cover the whole episode of care.
The plan of care ties it together: the interventions to be used, how often you will attend, roughly how many weeks the program is expected to run, and what you will do at home. Interventions might include specific exercises, hands-on joint or soft-tissue techniques, walking or balance training, education about activity pacing, and advice on work or sport modification. If a physician referred you, this plan is documented and sent back so that everyone involved is reading from the same page.
You should leave able to say, in plain words, what the therapist thinks is going on, what the plan is and what you need to do before the next visit. If you cannot, ask before you leave. Understanding your own plan is not a courtesy; it predicts whether you will follow it.
Who a physical therapy evaluation is usually for, and who is asked to wait
The World Health Organization estimates that about 2.4 billion people worldwide live with a health condition that could benefit from rehabilitation, so the honest answer to “who is it for” is: a very wide group. The more useful question is who benefits from being seen now versus later.
Evaluations are commonly arranged for people recovering from orthopedic surgery such as joint replacement or ligament repair; people with persistent joint, back or neck pain that limits daily tasks; people recovering from a stroke or other neurological event who need to relearn movement; older adults who have fallen or fear falling; people with breathing or heart conditions in structured rehabilitation programs; and athletes returning from injury. Children with developmental movement differences are evaluated by therapists with pediatric training, following a pathway built around play and family involvement.
Some people are asked to wait, and the reasons are protective rather than dismissive. After surgery, the surgeon’s protocol sets the earliest safe start, because healing tissue has limits that no amount of motivation changes. A person with an acute fracture waits until the bone is stable enough to load. Someone with an undiagnosed cause of severe pain, or with any of the red flags discussed above, is usually sent for medical assessment before therapy begins. A person acutely unwell with infection, uncontrolled blood pressure or a suspected clot is also deferred until the medical picture is settled.
Waiting does not always mean doing nothing. The therapist or referring clinician may give simple positioning, breathing or gentle movement guidance in the interim. Whether to proceed, wait or investigate further is a decision that rests with the treating team, informed by the evaluation findings. If you are told to wait and do not understand why, ask what the team is waiting for and what would change the decision.
An example of a physical therapy evaluation, start to finish
Abstract descriptions only go so far. Here is how an evaluation for a common problem, a painful shoulder, might unfold. The details are illustrative, not a template for your own case.
A woman in her fifties arrives describing three months of right shoulder pain that began without injury. It aches at rest, sharpens when she reaches behind her to fasten a seatbelt and wakes her when she rolls onto that side. She works at a desk, swims twice a week and has stopped because of the pain. Her goal is to swim again and to sleep through the night.
The therapist notes the gradual onset, the night pain and the loss of reaching behind, and mentally lists several possibilities involving the rotator cuff, the joint capsule and the neck. Screening questions about neck symptoms, arm numbness, general health and weight are unremarkable.
On examination, the right shoulder lifts to about two-thirds of the left side’s height actively, and only slightly further when the therapist moves it passively, suggesting stiffness in the joint itself rather than only weakness. Rotation is the most limited movement. Strength is reduced in the muscles that rotate the arm outward, partly from pain. Neck movement is full and does not reproduce the shoulder pain. A standardized shoulder questionnaire gives a baseline score.
The therapist explains that the pattern points toward a stiff, irritable shoulder joint with secondary weakness, that the neck does not appear involved, and that recovery of this kind tends to be gradual and measured in weeks to months rather than days. Goals are set around pain-free sleep positions, reaching to the seatbelt and a return to swimming in stages. The plan pairs gentle range-of-motion work and progressive strengthening with sleep positioning advice. She leaves with two exercises, a follow-up booked and a written summary. A report goes to her physician.
How long should a physical therapy evaluation take?
People often arrive braced for a quick check and are surprised when the first visit runs long. That is by design. An evaluation has to accomplish everything described so far, and rushing it produces a plan built on guesswork.
Clinics vary in how they schedule, and the honest answer is that the length depends on the complexity of your problem, whether the visit includes treatment, and the setting. A straightforward single-joint problem in a person who is otherwise healthy takes less time than a multi-system assessment after a stroke, where balance, coordination, sensation, walking and daily self-care each need their own tests. Hospital-based evaluations after surgery may be shorter and repeated daily; outpatient evaluations are usually a single longer block. Rather than relying on a general figure, ask the clinic when you book how long your initial appointment is scheduled for and whether treatment is included.
Follow-up visits are generally shorter because the groundwork is done. The therapist rechecks a few key measures, adjusts the program and moves into treatment.
A more useful question than “how long” is “how thorough.” A complete evaluation, whatever its clock time, should include an interview that covers onset, symptom behavior and goals; screening for red flags; observation of how you move; measured range of motion and strength for the relevant region; at least one functional or patient-reported measure; and a clear explanation of the findings and plan. If the appointment ends without a plan you can describe in your own words, or without any measurement at all, that is a reasonable thing to raise.
Length also depends on you. Arriving with your history organized, your medicine list in hand and your questions written down frees time for the parts only the therapist can do.
PT evaluation vs. follow-up visit: what changes and why
The first appointment and the tenth look different because they are doing different jobs. The evaluation gathers and interprets; follow-ups apply, adjust and re-measure. Understanding the split helps you set expectations for both.
| Element | Initial evaluation | Typical follow-up visit |
|---|---|---|
| Main purpose | Establish a movement diagnosis, baseline measures and plan of care | Deliver treatment and progress the program |
| Interview | Full history, health screen, goals | Brief update on symptoms and home program |
| Red-flag screening | Systematic | Ongoing, triggered by any change |
| Measurement | Range, strength, function, questionnaires | Selected key measures rechecked at intervals |
| Hands-on treatment | Often brief, if included | Central part of the visit where indicated |
| Exercise | One or two starter exercises | Progressed and expanded each visit |
| Documentation | Detailed report, often shared with referring clinician | Shorter progress note |
| Reassessment | Baseline set | Formal re-evaluation at planned points |
Two features of this table deserve a comment. First, screening does not stop after the evaluation. A therapist who notices a new symptom on your fifth visit runs through the same mental checklist as on day one. Second, formal re-evaluation, in which the baseline measures are repeated and the plan is revised, is scheduled deliberately, often every few weeks or at a change in status, rather than left to chance. The NHS describes physiotherapy as a process of assessment, treatment and reassessment; the table is simply that cycle laid out in rows.
Knowing this rhythm also protects you against two disappointments: expecting a full treatment on day one, and expecting every later visit to be a fresh investigation. Neither is how the model works.
The days and weeks after your physical therapy evaluation
The appointment ends, and the real program begins in your living room. What the following weeks look like depends on your diagnosis and goals, but the shape is fairly consistent.
The first day or two may bring some soreness. You were asked to move joints that have been guarded and to test muscles that have been underused. Mild, muscle-type aching that settles within a day or so is common and expected; sharp, worsening or new pain, swelling, numbness or symptoms that spread are not, and should be reported before your next session rather than pushed through.
The home program is the engine of recovery. One or two exercises at first, chosen for relevance rather than difficulty, with a clear instruction on how often. Therapists increasingly hand out written or video instructions; keep them somewhere visible. Doing a small program consistently beats doing a large one sporadically.
Visits during the early weeks tend to be more frequent while the therapist refines the diagnosis, checks your technique and progresses the load. As you become more independent, visits typically space out. Each visit should feel like a step: something is rechecked, something is made harder or changed, and the reason is explained.
Expect a formal re-evaluation at planned intervals, where the baseline questionnaires and key measurements are repeated. This is the moment the numbers speak. Improvement confirms the plan; a plateau triggers a rethink, which may mean changing the approach, consulting the referring clinician or, sometimes, accepting that the goal needs revising.
Discharge is not a graduation ceremony but a handover. A good program ends with a maintenance plan you can run yourself and clear guidance on what would justify returning. Rehabilitation, as MedlinePlus frames it, aims at keeping abilities as well as regaining them, and the keeping part is mostly done without a therapist in the room.
What people often get wrong about physical therapy evaluations
Myths about the first visit keep people from booking it or leave them disappointed when they do. Several deserve correcting.
“They will just give me a sheet of exercises.” A printout may be part of the visit, but the evaluation’s value is the reasoning behind it. Two people with the same diagnosis on paper can need different exercises because their movement findings differ. If all you received was a generic sheet with no examination, you did not receive an evaluation.
“If it does not hurt during the exam, they missed something.” Reproducing your symptoms is useful, but many tests are meant to rule structures out, and a pain-free test is often the informative one.
“The therapist will tell me exactly what is torn.” Physical tests cannot see inside a joint the way imaging can, and the therapist will usually describe a pattern rather than name a specific tissue with certainty. That is honesty, not vagueness. Imaging decisions sit with your physician, and the Mayo Clinic notes that back pain, for example, often does not require imaging unless red flags or persistent symptoms are present.
“I should rest until the evaluation.” Unless a clinician has told you to immobilize, gentle movement within comfort is generally encouraged for most musculoskeletal problems, and the NHS advises staying as active as you can with back pain rather than resting in bed.
“One visit will fix it.” Some people do need only an evaluation and a self-managed program. Most need a series of visits, because tissue adaptation and motor learning take weeks, not days. An evaluation is the beginning of a plan, not the plan itself.
“More pain during exercise means more progress.” Mild discomfort can be acceptable; escalating pain is a signal to modify. Your therapist should give you a clear rule for the difference.
Questions to ask your care team at the evaluation
The evaluation is one of the few appointments where the clinician’s job is partly to listen, so use it. Written questions are not a sign of anxiety; they are a sign of preparation, and therapists generally welcome them. These are the ones that tend to change the course of care.
- What do you think is going on, in plain language, and how confident are you at this stage?
- Which of your findings are most important, and which will you track to know whether I am improving?
- What is a realistic range of time for the changes we are aiming at, and what would make you revise that estimate?
- How often should I attend, and what happens between visits?
- Which activities should I continue, which should I modify, and is there anything I should stop entirely for now?
- What kind of discomfort during exercise is acceptable, and what should make me stop and call?
- Will you communicate with my referring clinician, and how?
- What would you expect to see at the re-evaluation, and what happens if we do not see it?
- Is there anything in my history or examination that you want a physician to look at before we continue?
- When the program ends, what will I need to keep doing on my own?
Two further questions are about fit rather than findings. Ask how much of each visit will be one-to-one with the therapist, and ask who you should contact if something changes between appointments. Neither is rude. Both tell you how the clinic operates and whether its rhythm matches what you need.
Bring a pen or ask whether you can record the explanation on your phone. The plan you can recall accurately at home is the one you will follow. And if something the therapist says conflicts with what your physician told you, raise it in the room; reconciling advice is the team’s job, not yours to carry alone.
When to call your doctor
Physical therapy is generally safe, and most soreness after an evaluation is the ordinary kind that eases in a day or so. A small number of signs mean the problem may need medical attention rather than more rehabilitation, and they apply whether they appear before your first visit, after the evaluation or partway through a program.
Contact your doctor promptly, or seek urgent care, if you notice new or worsening numbness, tingling or weakness in an arm or leg; loss of bladder or bowel control or numbness around the groin or buttocks; pain following a significant fall or accident, particularly if you have osteoporosis or are older; back or neck pain accompanied by fever, unexplained weight loss or that is constant and worse at night; a calf that becomes swollen, warm, red or painful, especially after surgery or a period of reduced mobility; or a joint that becomes suddenly hot, swollen and too painful to move.
Call emergency services for chest pain or pressure, sudden shortness of breath, fainting, or a sudden severe headache, facial drooping, slurred speech or weakness on one side of the body during or after exercise.
Tell your therapist about anything that changes between visits, including new symptoms elsewhere in the body. Therapists are trained to recognize these red flags and will stop treatment and refer you if they are concerned, but they can only act on what they know. Both the NHS and the Mayo Clinic list the back-pain warning signs above as reasons to seek medical advice rather than wait.
Whether to pause therapy, continue it or investigate further is a decision for your treating team, informed by your report. When in doubt, a phone call that turns out to be unnecessary costs far less than a symptom that was ignored.
Frequently asked questions
What is done in a physical therapy evaluation?
The therapist takes a detailed history of your problem and health, screens for signs that need medical attention, observes how you move, measures joint range, strength, balance and function, and asks you to complete a questionnaire about daily limitations. The findings are interpreted into a movement diagnosis, measurable goals and a plan of care, and you usually leave with one or two starter exercises.
What are red flags in physical therapy?
Red flags are findings that suggest a serious condition needing medical assessment rather than rehabilitation. For back pain, the Mayo Clinic and NHS list new bladder or bowel problems, numbness around the groin, spreading leg weakness, pain after a significant fall, fever, unexplained weight loss and constant night pain. A therapist who finds one will typically pause and refer you to a physician.
How long should a physical therapy evaluation take?
Longer than a follow-up visit, because it includes the full history, screening, examination and planning. The exact time depends on the complexity of your problem, the setting and whether treatment is included, so ask the clinic when booking. A complete evaluation should include measured findings and a plan you can explain in your own words, whatever the clock says.
Can you give an example of a physical therapy evaluation?
For a stiff, painful shoulder, the therapist would ask about onset, night pain and difficult movements, screen the neck and general health, measure active and passive shoulder range, grade rotator strength, record a shoulder questionnaire score, and explain the likely pattern. Goals might target sleep, reaching behind and return to activity, with a plan of gradual range and strengthening work.
What should I expect at my first physical therapy appointment?
Expect more talking and measuring than treating. Wear clothing that exposes the area, bring imaging reports and a medicine list, and be ready to describe when the problem started, what it stops you doing and what you want back. Some tests may briefly provoke your pain. You should leave with a clear explanation, a plan and a small home program.
Is a physical therapy assessment the same as a diagnosis from my doctor?
No. Your physician’s diagnosis names a medical condition, while the therapist’s assessment produces a movement diagnosis describing the pattern of stiffness, weakness or altered control they can treat. The two sit alongside each other. Therapists cannot see inside a joint the way imaging can, and decisions about imaging or further investigation remain with your physician.
Will the evaluation hurt?
Some tests are designed to reproduce your symptoms briefly so the therapist can identify the structures involved, and mild soreness for a day or so afterward is common. You can ask the therapist to stop any test at any time. Sharp, escalating or new pain, swelling or numbness afterward is not expected and should be reported before your next visit.
Do I need a referral for a physical therapy evaluation?
Requirements vary by region, health system and insurer, and some settings allow direct access while others require a physician’s referral. Check with the clinic and your coverage before booking. Regardless of how you arrive, the therapist will still screen for problems that need medical assessment and will communicate with your other clinicians when appropriate.
Why does the therapist measure so much instead of just treating?
Because rehabilitation progress is gradual and both patients and clinicians are prone to seeing improvement they hope for. Recorded joint angles, strength grades, timed functional tests and questionnaire scores create a baseline that can be rechecked objectively, showing whether the plan is working, justifying changes, and giving your referring clinician concrete information rather than impressions.
What happens after the physical therapy evaluation?
You begin a home program of one or two exercises and attend follow-up visits, typically more frequent early on and spaced out as you improve. Baseline measures are repeated at planned re-evaluations to confirm progress or prompt a change of approach. Discharge comes with a self-managed maintenance plan and guidance on what would justify returning.
References
- MedlinePlus: Rehabilitation
- NHS: Physiotherapy
- WHO: Rehabilitation fact sheet
- CDC STEADI: Timed Up and Go (TUG) assessment
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

What Physiotherapy Involves, and What to Wear to Your First Session
Physiotherapy (called physical therapy in the United States) is a licensed health profession that restores movement and function after injury, surgery, illness, or long-term…

CPM Machines: What Continuous Passive Motion Does After Knee Surgery
A CPM (continuous passive motion) machine slowly bends and straightens the knee on a motorized cradle, with no effort from the patient. Large reviews…

What Does Stroke Rehabilitation Involve? Physical, Occupational, Speech and Cognitive Therapy
Stroke rehabilitation is a coordinated program that helps the brain and body relearn lost skills after a stroke. It usually combines physical therapy for…
Dry Needling Benefits: What Patients Report vs What Studies Measure
Dry needling is a technique in which a trained clinician inserts thin filament needles into tight muscle bands to reduce pain and improve movement.…
Dry Needling vs Acupuncture: Same Needles, Different Logic
Dry needling and acupuncture use the same thin, solid filiform needles, but the reasoning behind them differs. Dry needling targets myofascial trigger points, the…

How to Strengthen Your Knees: Exercises Physiotherapists Use
To strengthen knee joints, build the muscles that control the knee rather than the joint itself: the quadriceps, hamstrings, gluteals, and calves. Physiotherapists typically…