

What Happens at Each Hemodialysis Session: Checks Before, Monitoring During and After
Key Takeaways
- In-center hemodialysis typically runs three times a week for about 3 to 5 hours per session, and the length exists so fluid and waste can be removed at a pace the heart and blood vessels tolerate.
- Your pre-session weight minus your dry weight sets the day's fluid removal goal, which is why arriving with a large fluid gain makes cramps and low blood pressure more likely.
- Only a small amount of blood is outside the body at any moment; it cycles continuously through a dialyzer containing thousands of hollow fibers with pores that let waste and water through but hold back blood cells.
- Low blood pressure during treatment is the most common complication, and the standard response is to lower the chair, slow fluid removal and reassess your target weight.
- Dialysis adequacy is measured, not felt: NIDDK cites targets of a urea reduction ratio of at least 65 percent and a Kt/V of at least 1.2 per session.
- A fistula usually needs 2–3 months to mature before it can be used, while a catheter can be used at once but carries the highest infection risk of any access type.
A hemodialysis session usually begins with a weight, blood pressure and temperature check and an inspection of your access site. Two needles or a catheter connect you to a machine that filters waste and extra fluid from your blood for roughly three to five hours while staff monitor pressure, flow and how you feel. Afterward, the needles are removed, bleeding is controlled, and you are weighed again.
The chair is bigger than you expected, and it reclines. Someone hands you a blanket before you have asked for one. Across the room a machine hums at a pitch you will come to recognize the way you recognize your own refrigerator. On a first visit, most people are not thinking about kidney chemistry. They are thinking: what exactly is going to happen to me in the next four hours, and will it hurt?
Understanding what happens during a hemodialysis session takes much of the fear out of it. The treatment follows a predictable sequence, and the people running it check the same things in the same order every time, because the order is what keeps it safe. This article walks through that sequence from the moment you step on the scale to the moment you walk back to the parking lot.
Nothing here replaces the conversation with your own kidney team, who tailor every setting to you. It should, though, make that conversation easier to have.
What happens during a hemodialysis session, in plain language
Hemodialysis is a treatment that uses a machine and a filter to do part of the job your kidneys can no longer do: removing waste products, salts and excess water from your blood. Healthy kidneys manage this quietly around the clock. When they fail, the same work has to be compressed into a few hours, several times a week.
The filter is called a dialyzer, sometimes described as an artificial kidney. Inside a clear plastic cylinder about the size of a large water bottle sit thousands of hollow fibers, each thinner than a hair. Your blood flows through the inside of these fibers. A special fluid called dialysate, a carefully balanced mix of water, salts and minerals, flows around the outside in the opposite direction. The fiber walls are dotted with pores small enough to let waste molecules and water pass through but too small for blood cells and most proteins.
Two processes do the cleaning. Diffusion moves waste such as urea and potassium from your blood, where concentrations are high, into the dialysate, where they are low. Ultrafiltration uses gentle pressure to pull excess water across the membrane, which is how the fluid you have gained between sessions is removed. According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), only a small amount of your blood is outside your body at any one moment; it travels out through one needle or catheter line, passes through the dialyzer, and returns through the other in a continuous loop.
The machine itself is mostly a set of pumps, sensors and alarms. It moves blood at a steady rate, warms and mixes the dialysate, tracks pressures on both sides of the filter, and stops instantly if it detects air, a leak or a pressure outside the limits your team has set. Your nurse programs those limits before the first drop of blood leaves your arm.
Who hemodialysis is usually for, and who is usually asked to wait
Hemodialysis is prescribed when the kidneys can no longer keep the body in balance on their own. That most often means kidney failure, the stage of chronic kidney disease in which roughly 15 percent or less of normal filtering function remains (NIDDK). Some people also need it for a short period during acute kidney injury, a sudden drop in kidney function from illness, surgery or a medication reaction, and stop once their kidneys recover.

The decision to start is not made from one blood test. Nephrologists, doctors who specialize in kidney disease, look at a combination of laboratory values, symptoms such as fluid buildup or persistent nausea, and how the person is coping day to day. Two people with the same filtration number may start at different times because their bodies are behaving differently.
Who is usually asked to wait? People whose kidney function is declining but still adequate are typically monitored rather than started early; Mayo Clinic notes that beginning dialysis before it is needed carries the burdens of treatment without proven benefit. Someone with a newly created fistula, the surgically joined artery and vein that serves as a long-term access point, may wait 2–3 months for it to mature before it can be used, per NIDDK, and may use a temporary catheter in the meantime if treatment cannot be delayed.
Hemodialysis is one of several paths, not the only one. Peritoneal dialysis, which filters blood inside the abdomen using its own lining, home hemodialysis, kidney transplantation and conservative kidney management without dialysis are all options that a care team discusses with the person and their family. Which path fits depends on medical suitability, home circumstances and personal priorities, and the choice belongs to the patient and their treating team together.
Before you sit down: the pre-dialysis checks
The session starts before you reach the chair. Nearly every unit follows the same short ritual, and each step exists to answer a specific question.
The scale. You step on it in the same kind of clothing each time, shoes off. Your weight tells the team how much fluid you have gained since the last session, because between treatments your body cannot get rid of the water you drink. The difference between today’s weight and your target weight, sometimes called dry weight, becomes the fluid removal goal for the day. NIDDK describes dry weight as your weight when your body holds no excess fluid.
Blood pressure and pulse. These are measured sitting and often standing. A reading that is unusually high may point to fluid overload; one that is unusually low warns the team to remove fluid more cautiously, since blood pressure typically drops during treatment.
Temperature. A fever before you are connected is a signal to pause and look for infection, particularly if you have a catheter.
Access assessment. The nurse looks at, touches and listens to your fistula or graft. They feel for the thrill, a soft buzzing vibration that means blood is flowing well, and listen with a stethoscope for the bruit, the whooshing sound of that same flow. Redness, swelling, warmth or a missing thrill changes the plan.
A quick conversation. How have you felt since last time? Any cramps, dizziness, bleeding from the needle sites, shortness of breath at night, missed medicines? Your answers adjust the prescription in small but real ways: a little less fluid removed, a slightly different starting rate, an extra check partway through.
These checks take a few minutes and can feel routine after a few weeks. They are the reason the session that follows is safe.
How your access is prepared: fistula, graft or catheter
Vascular access is the point where blood leaves and re-enters your body, and it is the part of the process most people worry about first. There are three main types, and preparation differs for each.
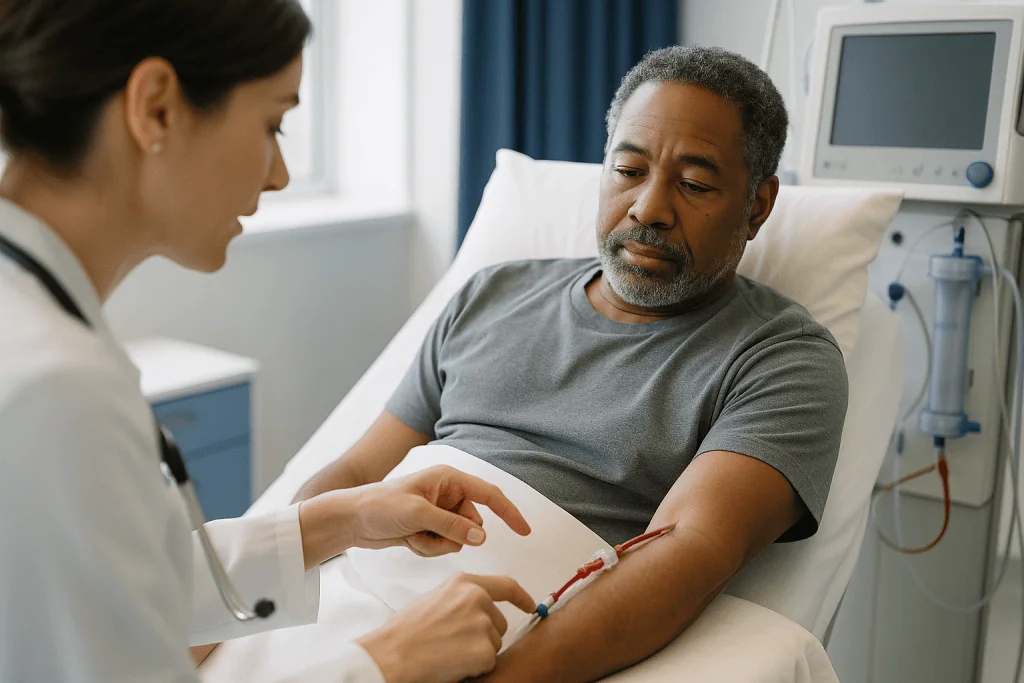
A fistula is created by a surgeon who connects an artery directly to a vein, usually in the forearm or upper arm. Over weeks the vein thickens and enlarges under the higher flow, becoming sturdy enough for repeated needle placement. NIDDK considers the fistula the preferred access because it tends to last longer and has fewer infections and clots than the alternatives. A graft uses a soft synthetic tube to join the artery and vein when a person’s own veins are too small; it can often be used sooner, typically within 2–3 weeks according to NIDDK, but is more prone to clotting.
For either, the routine is the same. You wash the arm with soap and water. The nurse cleans the skin with antiseptic and lets it dry. Two needles are placed: one draws blood toward the machine, the other returns it. Many people describe a sharp pinch that fades within seconds. Some units use a numbing cream or spray beforehand, a decision made with your team. The needles are taped securely, and the tubing is looped so a tug on the line does not pull on the needle.
A catheter is a soft tube inserted into a large vein in the neck or chest, with two ends that sit outside the skin under a dressing. No needles are needed; instead, the nurse removes the caps, cleans the hubs, checks that each line draws and flushes freely, and connects the tubing. Because the catheter opens a direct route into the bloodstream, this step is done with masks and strict hand hygiene, and the CDC lists catheters as the access type with the highest infection risk.
Whatever your access, tell the nurse if placement hurts more than usual. Pain that is different from your normal pattern is information they need.
The hemodialysis session steps once the machine starts
With the access connected, the nurse presses start and the blood pump begins to turn. Watching your own blood travel through clear tubing for the first time is strange for almost everyone. Within a minute or two the lines fill, the dialyzer turns from pale to red, and the machine settles into its rhythm.
The first thing most units do is give an anticoagulant, a medicine that slows clotting, through the circuit. Blood naturally tries to clot when it touches plastic, and a clotted dialyzer stops working. The drug most commonly used for this belongs to the heparin class; how much, or whether it is used at all, is a decision your nephrologist makes based on your bleeding risk, and some people are dialyzed without it.
Next the nurse sets the blood flow rate, which is how fast the pump moves blood, and the dialysate flow rate, then enters the fluid removal goal calculated from your weight. The machine spreads that removal evenly across the session unless the team programs a different profile. Your prescription also specifies the dialysate composition, particularly potassium and bicarbonate levels, tailored to your recent blood results.
From there, the session is mostly waiting. Blood cycles continuously through the filter, waste diffuses into the dialysate, and the used dialysate drains away while fresh fluid is mixed on the spot. Every 30 to 60 minutes a nurse or technician records your blood pressure, pulse and the machine’s readings, more often if anything looks off.
What you do with the time is up to you. People read, sleep, watch a tablet, do crossword puzzles or talk to the person in the next chair. Eating during treatment is handled differently across units and depends on your situation, so ask before bringing a snack. Keeping the access arm still matters more than keeping the rest of you still; a bent elbow or a rolled wrist can slow flow and trigger an alarm.
How long does hemodialysis take, and why the time matters
The honest answer is: longer than most people hope. In-center hemodialysis is typically done three times a week, with each session lasting about 3 to 5 hours, according to Mayo Clinic; the NHS and NIDDK describe a similar pattern of three weekly sessions of roughly 4 hours. Add the checks before, the disconnection after and travel, and a treatment day can absorb five or six hours.
Why so long? Because gentleness takes time. The two jobs of dialysis, clearing waste and removing fluid, both go better when done slowly. Pulling several liters of water out of the bloodstream in two hours drops blood pressure and causes cramps; spreading the same removal over four hours lets fluid shift from tissues back into the blood at a pace the heart can tolerate. Waste clearance also plateaus: the last hour removes toxins that have taken time to move from inside cells into the blood.
Your team measures whether the time is doing its job. Two numbers matter most. The urea reduction ratio, or URR, compares urea in your blood before and after a session; NIDDK cites a target of at least 65 percent. Kt/V is a more precise calculation that folds in the filter’s performance, treatment time and your body size, with a target of at least 1.2 per session in the NIDDK guidance. If your numbers fall short, the fix is usually more time, a larger filter or better access flow, not a faster pump.
Shortening a session, even by 15 minutes, means leaving waste and fluid behind, and the effect compounds across a week. That is why nurses will gently push back if you ask to come off early for an appointment. Home hemodialysis and nocturnal programs change this arithmetic by treating more often or longer, which is one reason some people choose them; suitability for those options is something to raise with your team.
Monitoring during treatment: what the numbers on the screen mean
The machine display looks like a cockpit, and it can help to know what the crew is watching.
Arterial pressure is the pressure in the line drawing blood from your access. A very negative number means the pump is straining to pull blood, often because the needle is poorly positioned or the access is narrowing. Venous pressure is the pressure in the return line; a high reading suggests resistance downstream, such as a clot forming or a kink in the tubing.
Blood flow rate shows how fast blood is moving through the circuit. Ultrafiltration rate shows how much fluid is being removed per hour, and the running total tells you how far along the day’s fluid goal you are. Transmembrane pressure reflects the pressure difference across the filter, which the machine adjusts to hit the fluid target.
Beyond the machine, the team watches you. Blood pressure is the single most important reading, because intradialytic hypotension, a drop in blood pressure during treatment, is the most common complication, according to NIDDK. Nurses also note your pulse, breathing and, in many units, your temperature partway through. Some machines track how concentrated your blood is becoming in real time, which gives early warning that fluid is coming off faster than your tissues can refill.
Alarms are frequent and mostly minor. The machine is designed to stop the pump and clamp the lines the moment something is out of range: a pressure spike from a bent arm, a tiny air bubble detected in the return line, a dialysate temperature drifting off target. A staff member checks, corrects the cause and restarts. An alarm is not an emergency; a silent machine with a worried nurse is the thing to notice.
Blood samples are usually drawn from the circuit at the start of one session each month to check hemoglobin, potassium, phosphorus, calcium, albumin and dialysis adequacy, per NIDDK. Those results drive the small changes to your prescription over time.
Common problems during dialysis and how the team responds
Most sessions pass without incident. When something does happen, it is usually one of a short list of predictable events, each with a practiced response.
Low blood pressure is the most frequent, as noted by both NIDDK and Mayo Clinic. It shows up as lightheadedness, sweating, nausea, yawning or a sudden feeling that something is wrong. The nurse lowers the chair so your head is flat, slows or pauses fluid removal, and may return a small amount of fluid through the line. Recovery is usually quick. Repeated episodes prompt a review of your target weight and how fast fluid is being removed.
Muscle cramps, most often in the calves and feet, tend to appear late in the session when fluid removal is well underway. Stretching, adjusting the fluid removal rate and reviewing your dry weight are the typical remedies. Cramps that recur session after session often mean the target is set slightly too low.
Nausea, headache and itching are common enough that Cleveland Clinic lists them among expected side effects. They often ease as your body adjusts over the first weeks, and persistent itching may reflect phosphorus levels that your team can address.
Access problems include a needle that slips, infiltration where blood leaks into surrounding tissue causing a bruise or swelling, or poor flow. The nurse will stop the pump, reposition or replace the needle, and apply pressure or ice as needed.
Chest pain, sudden breathlessness or a fever during treatment are taken seriously every time. The team may stop the session, check your heart rhythm and blood, and call a physician. Rare events such as an allergic reaction to the dialyzer or air entering the circuit are exactly what the machine’s alarms and the staff’s training are built to catch.
Your job in all of this is simple: say something early. A quiet mention of feeling odd gives the team ten minutes they would not otherwise have.
Coming off the machine: the last 20 minutes
When the timer reaches zero, the pump does not simply stop. The nurse performs a rinse-back: saline is pushed through the circuit so the blood still in the tubing and filter is returned to you rather than discarded. This takes a few minutes and is why you may notice the lines turn from red to pink to clear.
The clamps close and the tubing is disconnected. With a fistula or graft, the needles are withdrawn one at a time and firm pressure is applied over each site with gauze. Bleeding must stop completely before you leave, which usually takes several minutes per site and can take longer if you are on anticoagulants or the access is new. Many people learn to hold their own sites, which gives a sense of control and frees the nurse; pressing hard enough to stop bleeding without pressing so hard that you stop flow through the fistula is a skill the staff will teach you. A small dressing goes on, and you are asked to leave it in place for several hours.
With a catheter, the lines are disconnected, each lumen is flushed, and a locking solution designed to prevent clotting and infection between sessions is placed inside. New sterile caps go on and the dressing is changed if it is due. You should not get the dressing wet or take it off yourself.
Then comes the second set of vital signs: blood pressure sitting, then standing, because pressure can dip when you rise after hours in a chair. Finally you go back to the scale. The post-dialysis weight tells the team whether the fluid goal was reached and becomes the reference point for next time.
Do not rush the standing-up part. Sit on the edge of the chair for a minute, then stand with something to hold. Most units want you to remain a short while if your pressure was low, and they may ask you not to drive if you felt faint.
What to expect during dialysis: a session at a glance
The table below gathers the sequence into one view. Times are typical ranges drawn from NIDDK, NHS and Mayo Clinic descriptions and vary from unit to unit and person to person; your own schedule is set by your prescription.
| Stage | Typical time | What the team checks or does | What you might notice |
|---|---|---|---|
| Arrival checks | 5–15 minutes | Weight, blood pressure, pulse, temperature, access exam, symptom review | Same routine each visit; questions about the days between |
| Access preparation | 5–10 minutes | Skin cleaning, needle placement or catheter connection, taping | Brief pinch with needles; no pinch with a catheter |
| Start of treatment | First 15 minutes | Pump started, anticoagulant given if prescribed, flow rates and fluid goal set, first pressure readings | Cool sensation in the arm as blood returns; machine sounds |
| Main treatment | 3–5 hours (Mayo Clinic) | Vital signs every 30–60 minutes, pressure and flow monitoring, response to alarms | Rest, sleep or entertainment; possible cramps or lightheadedness late in the session |
| Rinse-back and disconnection | 10–20 minutes | Saline return of circuit blood, needle removal with pressure, or catheter flush and locking | Holding gauze on sites until bleeding stops |
| Final checks | 5–10 minutes | Blood pressure sitting and standing, post-treatment weight, dressing check | Possible dizziness on standing; tiredness beginning |
Two patterns stand out. First, roughly a fifth of the time you spend in the unit is checks and preparation rather than filtering, and none of it is wasted. Second, the parts that feel most eventful, the needles and the disconnection, are the shortest. The long middle stretch is where the treatment actually happens, quietly, at the rate your body can accept.
Dialysis side effects after treatment and the days between sessions
What happens after you leave the chair is as much a part of the treatment as what happens in it. The pattern across a week is recognizable to almost everyone on hemodialysis.
The first few hours. Tiredness after dialysis, sometimes called washout, is the most commonly reported after-effect, and the NHS lists fatigue among the main side effects of dialysis. Some people feel it for an hour; others lose most of the afternoon to it. Headache, mild nausea and feeling cold are also common in the hours after. Eating a light meal, resting and avoiding strenuous activity that evening help many people. The needle sites should stay dry and covered for several hours, and any bleeding that restarts should be handled with firm pressure and a call to the unit.
The next day. This is often the best day of the cycle. Waste and fluid are at their lowest, and energy tends to be highest. Many people schedule the things that matter to them here.
The day before the next session. Fluid and waste have been building for one or two days, and this is when breathlessness lying flat, swollen ankles or a metallic taste can appear. The two-day gap over the weekend in a Monday-Wednesday-Friday schedule is the longest stretch, and NIDDK notes that people often feel worst before the first session of the week.
Over the first weeks. Side effects usually settle as your dry weight is fine-tuned and your body adjusts, according to Cleveland Clinic. Many people find the second month easier than the first. Blood results drawn monthly guide adjustments to your dialysis prescription and to medicines that manage anemia, bone and mineral balance, and blood pressure; those decisions rest with your nephrologist.
Between sessions, the daily work is fluid and diet management guided by a renal dietitian, protecting your access from pressure and injury, and keeping the schedule. Missing or shortening sessions is strongly associated with worse outcomes in dialysis populations, which is why units treat attendance as a clinical issue rather than an administrative one.
What people often get wrong about hemodialysis
Myth: the machine cleans all of your blood at once. Only a small amount is outside your body at any moment; blood cycles through the filter repeatedly over the session (NIDDK). You are never emptied and refilled.
Myth: dialysis does what kidneys do. It replaces the filtering function partially, typically restoring a fraction of what two healthy kidneys manage continuously. It does not replace the kidneys’ hormone work, which is why anemia, bone health and blood pressure still need separate attention from your team.
Myth: you can drink freely because the machine takes the fluid off. The machine can only remove fluid as fast as your circulation tolerates. Large gains between sessions force either faster removal, which causes cramps and low blood pressure, or leaving fluid behind. The fluid allowance your team sets is a safety limit, not a suggestion.
Myth: the needles are the dangerous part. Needle placement is uncomfortable but low risk. The serious risks of hemodialysis relate to blood pressure swings, access infection, particularly with catheters, and clotting of the access, all of which the monitoring described above is designed to catch.
Myth: feeling fine means you can leave early. Waste clearance in the final hour is real even when you do not feel it. Adequacy is measured by URR and Kt/V, not by how you feel at hour three.
Myth: starting dialysis means the end of normal life. Many people work, travel with arranged treatment elsewhere, exercise and raise families on hemodialysis. The schedule is demanding, and the fatigue is real, but the treatment is built to sustain a life, not to replace one.
Myth: once on dialysis, always on dialysis. People with acute kidney injury may recover and stop. Others move to peritoneal dialysis, home hemodialysis or transplantation. Which path is realistic for you is a question for your nephrologist, and it is worth asking more than once as circumstances change.
Questions to ask your care team
The people at the chair beside you have heard every question before, and asking is how a prescription becomes yours rather than a default. Consider bringing a few of these to your next session or clinic visit.
- What is my current dry weight, and how did you arrive at it? How often will it be reviewed?
- What is my fluid allowance between sessions, and what counts toward it?
- How long is each of my sessions, and what are my most recent URR or Kt/V results?
- Which type of access do I have, and what is the long-term plan for it? If I have a catheter, is a fistula or graft being considered?
- How should I check my access at home, and what changes should prompt a call?
- Am I receiving an anticoagulant during treatment, and how does that affect bleeding from my sites or elsewhere?
- What side effects am I experiencing that could be reduced by adjusting the prescription rather than tolerated?
- Which of my medicines are timed around dialysis, and which are removed by treatment?
- Would home hemodialysis, nocturnal dialysis or peritoneal dialysis be options for me, and what would I need to learn?
- Am I a candidate for transplant evaluation, and how is that process started?
- Who do I call after hours if something goes wrong at home, and what should I do while waiting?
- Can I speak with the renal dietitian and the social worker, and how often?
Write the answers down, or ask whether they can be added to a printed summary. Dialysis units track a great deal of data about you, and most are glad to share it. A patient who knows their own numbers tends to notice changes sooner, and noticing sooner is the whole game.
When to call your doctor
Most after-effects of hemodialysis are mild and fade within hours. A few signs mean you should not wait for your next scheduled session.
Call emergency services immediately for chest pain or pressure, severe shortness of breath, bleeding from your access that does not stop after 10 to 15 minutes of firm direct pressure, sudden weakness or numbness on one side, confusion, slurred speech, fainting, or a seizure. If a catheter line is pulled out or comes apart, clamp or pinch it, cover the site, lie down and call for emergency help.
Call your dialysis unit or nephrologist the same day if you notice any of the following. The thrill in your fistula or graft has stopped, weakened or changed, which may mean a clot is forming and the access can sometimes be rescued if treated quickly. There is redness, warmth, swelling, pus or increasing pain at your access or catheter site. You have a fever or shaking chills, especially with a catheter, since bloodstream infection can develop fast. Your breathing is worse when lying flat, your ankles or face are more swollen than usual, or you have gained noticeably more weight than expected between sessions. You feel a new irregular or racing heartbeat, or an unusual weakness in your arms or legs that could signal high potassium. Cramps, dizziness or nausea after treatment are much worse than your usual pattern or last into the next day.
Also let the team know about anything that changes your risk before the next session: a fall, a new medicine from another prescriber, vomiting or diarrhea that has left you dehydrated, or an appointment you think means you need to come off early. Each of these alters what a safe session looks like, and your treating team can only adjust for what they know.
When in doubt, call. Dialysis units expect these calls and would far rather hear about a small change that turns out to be nothing than learn about a large one after the fact.
Frequently asked questions
What are the main hemodialysis session steps from start to finish?
A session moves through weight and vital-sign checks, an access examination, skin cleaning and needle placement or catheter connection, starting the blood pump and setting the fluid goal, three to five hours of filtering with regular monitoring, a saline rinse-back to return blood in the circuit, needle removal with pressure or catheter locking, and final blood pressure and weight checks. The order is the same each visit because consistency is what makes the process safe.
How long does hemodialysis take each time?
Each in-center session usually lasts about 3 to 5 hours, most often three times a week, according to Mayo Clinic, NHS and NIDDK descriptions. Preparation, disconnection and waiting for bleeding to stop add roughly 30 to 45 minutes, and travel adds more. Sessions are long because gentle fluid removal and thorough waste clearance both take time; shortening them leaves waste and fluid behind.
Does hemodialysis hurt?
The needle placement causes a brief sharp pinch that most people describe as fading within seconds, and a numbing cream or spray can be discussed with your team. The filtering itself is not painful. Discomfort during a session is more often cramps, lightheadedness or feeling cold, all of which staff can address by adjusting the treatment. Pain that is different from your usual pattern should always be reported.
What should I expect during dialysis if it is my first session?
Expect the first session to be shorter and slower than later ones, because teams often start gently while they learn how your body responds. You may feel unusually tired afterward. Staff will explain each step, and it is normal to ask them to talk through the alarms. Bring a blanket, something to read or watch, and your medicine list, and plan a quiet evening rather than a busy one.
Why do I feel so tired after dialysis?
Post-dialysis fatigue, sometimes called washout, is one of the most commonly reported side effects and is listed by the NHS among the main effects of treatment. The exact cause is not fully understood; rapid fluid shifts, blood pressure changes, and the body’s inflammatory response to the circuit all appear to contribute. It often eases over the first weeks and improves when dry weight and fluid removal rates are well tuned.
What dialysis side effects after treatment are considered normal?
Tiredness, mild headache, feeling cold, slight nausea and small bruises at the needle sites are common in the hours after a session and usually fade the same day. Cramps that linger, dizziness on standing, or itching are also frequent and worth mentioning so the prescription can be adjusted. Fever, chest pain, breathlessness, bleeding that will not stop, or a change in your access thrill are not normal and need a same-day call.
Why do I have to be weighed before and after every session?
Between sessions your body cannot remove the water you take in, so it shows up as weight. Comparing your arrival weight with your dry weight tells the team exactly how much fluid to remove that day. Weighing you afterward confirms the goal was reached and becomes the starting point for next time. Wearing similar clothing each visit keeps the comparison accurate.
Can I eat and drink during hemodialysis?
Policies vary between units and depend on your individual situation. Eating during treatment can lower blood pressure in some people because blood is diverted to digestion, so some units limit food to small snacks or ask people to eat beforehand. Fluid taken during the session counts toward your allowance and adds to what must be removed. Ask your own team before bringing anything to the chair.
What happens if I miss or cut short a hemodialysis session?
Missing a session leaves waste, potassium and fluid in the body for several more days, which raises the risk of dangerous heart rhythms, breathlessness from fluid in the lungs and hospital admission. Cutting a session short has a smaller but cumulative effect and lowers your measured adequacy. If you must miss or shorten a treatment, tell the unit in advance so they can advise on fluid, diet and rescheduling.
How do I look after my access between sessions?
Check the thrill in your fistula or graft daily by placing fingers over it; a steady buzz means good flow, and a change means a call to the unit. Keep the arm free of tight sleeves, watches, blood pressure cuffs and heavy lifting, and do not let anyone draw blood from it. For a catheter, keep the dressing clean, dry and intact, never remove the caps, and report redness, drainage or fever promptly.
References
- Hemodialysis (NIDDK, National Institutes of Health)
- Dialysis: What happens (NHS)
- Dialysis (Cleveland Clinic)
- Dialysis (MedlinePlus)
This article is for general information only and is not a substitute for professional medical advice. Please consult a qualified doctor about your individual situation.

More from the Blog

Why Does the Shoulder Ache After Laparoscopic Urology Surgery? Gas Pain Explained
Shoulder pain after laparoscopic surgery is usually referred pain: the carbon dioxide gas used to inflate the abdomen stretches and irritates the diaphragm, whose…
How a Kidney Biopsy Is Done: Ultrasound Guidance, the Needle and What You Feel
A kidney biopsy is usually done with you lying on your stomach while a doctor uses ultrasound to locate the lower part of one…

Before a Renal Toxicology Visit: The Medication, Contrast and Exposure History to Gather
For a renal toxicology appointment, bring a complete list of every prescription, over-the-counter medicine and supplement you have used in the past year, dates…

Preparing Your Child for Orchiopexy: Fasting, Anesthesia Assessment and Calming Worries
Preparing a child for orchiopexy, the operation that moves an undescended testicle into the scrotum and secures it there, involves three things: a pre-operative…

Urethritis vs a Bladder Infection: How Inflammation of the Urethra Is Treated Differently
Urethritis is inflammation of the urethra, the tube that carries urine out of the body, and in adults it is most often caused by…

Recovery After VUR Surgery in Children: Urination, Comfort and the Follow-Up Ultrasound
Recovery after VUR surgery in a child depends on the type of procedure. After endoscopic injection, most children go home the same day and…